Healthcare analytics, AI solutions for biological big data, providing an AI platform for the biotech, life sciences, medical and pharmaceutical industries, as well as for related technological approaches, i.e., curation and text analysis with machine learning and other activities related to AI applications to these industries.
Urgent Request for Action on Proposed Rule Affecting Federal Funding Grant Review
Reporter: Stephen J. Williams, Ph.D.
Yesterday I received an email from the Mesothelioma Applied Research Foundation (MARFA), as well as Life Sciences PA and the American Association for Cancer Research (AACR). This was on a little publicized proposed change to the NIH scientific review process allowing the Office of Management and Budget (OMB) to have direct authority over the funding of grants which had passed the rigorous scientific review process. This proposed change by the current administration could negate decision made by NIH grant review panels as well as NIH program project directors and NIH administration as well as other funding agencies.
OMB has put a deadling of July 13, 2026 for comments by the public on this proposed change so it is of urgent matter that US scientists be informed of these potential changes.
I have included the three letters below: from MARFA, Life Sciences PA, and AACR.
From the Mesothelioma Applied Research Foundation
For decades, scientific breakthroughs in mesothelioma have depended on one essential principle: research should be guided by science.
A proposed rule from the Office of Management and Budget (OMB) could weaken that principle by allowing political appointees to override scientific peer review when making federal research funding decisions. It could also allow active federally funded research projects to be terminated if deemed inconsistent with changing agency priorities.
For the mesothelioma community, the stakes are especially high.
As a rare cancer, mesothelioma research already faces significant funding challenges. Every federal grant helps advance promising discoveries, supports clinical trials, and gives patients access to new treatment options. The proposal could also restrict international scientific collaboration—partnerships that are often essential for rare disease research, where researchers must work across borders to enroll enough patients and share critical scientific knowledge.
Please take just a few minutes to submit a public comment asking OMB to protect independent scientific peer review, preserve ongoing federally funded research, and support international collaboration for rare diseases.
The OMB proposal, which is currently accepting public comments, would make significant changes to how research funding decisions are administered across federal agencies, including the NIH and NSF. The public comment period closes in just one week, Monday, July 13, 2026, and public comments can be submitted HERE. However, it is equally important for U.S. Senators and Representatives to hear directly from their constituents on matters like this. We encourage your outreach beyond the public comment period.
For decades, independent, merit-based scientific peer review has been the foundation of federal research funding. Currently, the NIH is investing over $2.5 billion in more than 4,300 research projects across the Commonwealth. These investments have helped establish Pennsylvania as a global leader in research and development for innovative therapies and technologies. The revisions proposed by OMB put in jeopardy the transparency, predictability, and scientific integrity of that process.
Federal research investments are critical to the success of Pennsylvania’s leading life sciences ecosystem. They support scientific discovery at our academic research institutions, foster crucial partnerships with industry, and help advance the therapies and technologies that improve the lives of patients in the Commonwealth, across the country, and around the world. Maintaining certainty, consistency, and confidence in this established research funding process is essential to sustaining scientific progress and continued economic growth.
Life Sciences Pennsylvania is sharing our concerns with members of the Pennsylvania Congressional delegation, as well as submitting public comment reaffirming the importance of preserving an independent, science-driven research funding system. We urge you to share your perspectives by submitting concerns to your U.S. Senators and Representatives HERE.
PHILADELPHIA – The American Association for Cancer Research (AACR) is deeply concerned that the recent action of the White House Office of Management and Budget (OMB) to propose a new set of regulations on how federal grants are awarded and managed is a major threat to the National Institutes of Health (NIH) and its lifesaving mission to accelerate progress for patients with cancer and the hundreds of other diseases that afflict millions of Americans.
AACR strongly opposes many of the changes that OMB has proposed in its recently issued rule, titled “Regulation for Federal Financial Assistance.” A considerable number of the regulations included in the rule, if finalized, will be extremely disruptive to the lifesaving research that the federal government funds and oversees, mainly through NIH.
Therefore, AACR calls on the Administration to abandon this harmful proposal, as proceeding along these lines will irreparably damage NIH, an agency that is widely revered as the world’s leading medical research enterprise for its support of the innovative discoveries and groundbreaking treatments that are increasing survival rates and enhancing the quality of life for patients.
According to OMB, the intention of these proposed revisions is to improve transparency, accountability, and oversight of federal awards while reducing administrative burden and ensuring responsible stewardship of taxpayer resources. While AACR shares these goals and supports efforts to strengthen the effectiveness, integrity, and accountability of federal grant programs, a significant number of the provisions in this proposal would in fact increase administrative complexity, create uncertainty for grant recipients, reduce transparency in funding decisions, and undermine the merit-based processes that have effectively guided federal research investments. In short, this OMB proposal is reckless and does not meet the high U.S. standards required for a meritorious, impactful research grant program.
AACR has identified several especially concerning provisions in this OMB proposal that will severely set back our nation’s medical science enterprise and delay the groundbreaking treatments that are pivotal to improving patient outcomes and saving lives:
OMB proposes to markedly expand the power of political appointees to override expert assessment of scientific merit by subjecting every federal research funding decision to political review. These politically appointed officials are unlikely to have subject-matter expertise and would also be instructed to determine whether grant proposals are aligned with the Administration’s political priorities, regardless of their scientific merit. If political appointees are required to provide oversight of federal grant decisions and are allowed or encouraged to ignore the advice of highly qualified scientists, it will threaten the significant progress in patient outcomes that has been achieved over many decades.The merit review process, in which scientific experts in a particular field are brought together to review scientific proposals and assign scores that are based on the quality of the application and its potential to advance new knowledge, has underpinned many discoveries that have led to major improvements in public health. This objective approach to scientific review establishes a foundation of trust within the broader scientific community and throughout the U.S. population. Revising the rules to establish an environment that sidesteps traditional and transparent scientific metrics will weaken overall confidence in the U.S. research enterprise. [This area corresponds to provision 200.205 in the OMB proposal.]
OMB proposes to expand agency authority to suspend or terminate awards based on changing political priorities at the agency or program goals that no longer align with the Administration’s concept of “Gold Standard Science,” which is a term the Administration uses to terminate research not because it is unsound, but because it does not fit a preferred political or methodological agenda. These suspensions and terminations could take place regardless of whether the recipient is performing the project based on the previously approved scope of work. Therefore, an active grant, including a multi-year award that is already underway, could be terminated because of a political or ideological agenda.This OMB-proposed provision would create uncertainty for researchers, institutions, and patients. As one example, this proposed change may have an adverse effect on patient accrual to cancer clinical trials, as patients with cancer may be less likely to enroll if ongoing support for these clinical trials is uncertain. Cancer research often requires years of sustained investment, and permitting political appointees to discontinue support for a grant or clinical trial after the grant or clinical trial has already been awarded or begun threatens scientific progress, wastes taxpayer resources, and destabilizes research programs and studies on which patients are relying for their survival. [This area corresponds to provisions 200.340; 200.341; and 200.342 in the OMB proposal.]
OMB proposes to create additional barriers to scientific collaboration by imposing undue restrictions on international partnerships that are often essential for making advances against cancer and other human diseases. Modern cancer science relies on global networks of researchers, clinical trial participants, data resources, and specialized expertise. Limiting these collaborations will slow the pace of discovery and innovation. As one example among many, international collaborations are vitally important for pediatric cancer research. Because childhood cancers are rare, pooling global patient data, resources, and expertise accelerates clinical trials, drives breakthroughs in drug-resistant subtypes, and bridges survival disparities across high- and low-income countries. [This area corresponds to provisions 200.202 and 200.220 in the OMB proposal.]
OMB proposes to prohibit all federal funding related to diversity, equity, and inclusion.OMB’s justification includes vague language that could be interpreted in ways that restrict research on cancer disparities, access to care, and differences in outcomes among all patient populations. Cancer touches every community, yet, sadly, its burden is not shared equally. A person’s race, ethnicity, income, ZIP code, insurance status, access to screening, ability to enroll in a clinical trial, and proximity to overall high-quality cancer care shape whether cancer is found early, treated effectively, and ultimately cured. [This area corresponds to provisions 200.218 and 200.300 in the OMB proposal.]
OMB proposes to restrict activities that are fundamental components of innovative scientific research and that are essential to how research findings are shared and translated into patient benefit. Provisions in the OMB proposal to limit funding support for scientific publications, journal subscriptions, and attendance at scientific conferences would hinder the ability of researchers to disseminate discoveries, learn about emerging advances, and establish highly productive collaborations. [This area corresponds to provisions 200.432; 200.454; and 200.461 in the OMB proposal.]
For decades, the framework that supports America’s scientific research enterprise through agencies such as NIH and the National Cancer Institute has fueled transformative discoveries in cancer prevention, detection, treatment, and survivorship. This established system has reduced the U.S. cancer death rate by 35% since 1991, resulting in more than 4.8 million U.S. lives saved. This progress has been made possible because of research funding decisions guided by the rigorous review of grant applications by scientific experts and their assessment of these grants to improve public health—NOT guided by political and ideological considerations.
If this OMB-proposed regulation is ultimately finalized, it will severely weaken the U.S. federal research grant program that has supported American innovation and medical breakthroughs for decades. It will also upend the collaborative and evidence-based model that has resulted in U.S. leadership in cancer research and medical science.
It is imperative that all US scientists respond to this potential disasterous change. NIH grant review panels take their time out of their schedule to volunteer to review grants and committ great effort and time to this labor of love. In addition, those who write the grants have spent countless hours, days and months meticulous preparing exellent grants for review. These scientists show an utmost committment to the conduct of great science and a dedication to their field of expertise. Many volunteer countless hours and resources for their research, the scientific community and for patients. And most importantly, scientists include verbage and material in grants BASED ON SOUND SCIENCE, not their opinions.
Please take some time to respond to your lawmakers before July 13, 2026
OpenAI and ChatGPT face unique legal challenges over CopyRight Laws
Reporter: Stephen J. Williams, PhD
In previous weeks on this page and on the sister page ChatGPT applied to Cancer & Oncology, a comparison between ChatGPT, OpenAI, and Google large language model based search reveals a major difference between the algorithms with repect to citation and author credit. In essence while Google returns a hyperlink to the information used to form an answer, ChatGPT and OpenAI are agnostic in crediting or citing the sources of information used to generate answers to queries. With ChatGPT the source data, or more specifically the training set used for the AI algorithm is never properly cited in the query results.
This, as outlined below, is making a big problem when it comes to copyright law and intelectual property. Last week a major lawsuit has been filed because of incorrect and citing, referencing, and attribution of ownership of intellectual property.
As Miles Klee reports in The Rolling Stone
“OpenAI faces allegations of privacy invasion and violating authors’ copyright — but this may be just the tip of the iceberg”
The burgeoning AI industry has just crossed another major milestone, with two new class-action lawsuits calling into question whether this technology violates privacy rights, scrapes intellectual property without consent and negatively affects the public at large. Experts believe they’re likely to be the first in a wave of legal challenges to companies working on such products. Both suits were filed on Wednesday and target OpenAI, a research lab consisting of both a nonprofit arm and a corporation, over ChatGPT software, a “large language model” capable of generating human-like responses to text input. One, filed by Clarkson, a public interest law firm, is wide-ranging and invokes the potentially “existential” threat of AI itself. The other, filed by the Joseph Saveri Law Firm and attorney Matthew Butterick, is focused on two established authors, Paul Tremblay and Mona Awad, who claim that their books were among those ChatGPT was trained on — a violation of copyright, according to the complaint. (Saveri and Butterick are separately pursuing legal action against OpenAI, GitHub and Microsoft over GitHub Copilot, an AI-based coding product that they argue “appears to profit from the work of open-source programmers by violating the conditions of their open-source licenses.”)
Saveri and Butterick’s latest suit goes after OpenAI for direct copyright infringement as well as violations of the Digital Millennium Copyright Act (DMCA). Tremblay (who wrote the novel The Cabin at the End of the World) and Awad (author of 13 Ways of Looking at a Fat Girl and Bunny) are the representatives of a proposed class of plaintiffs who would seek damages as well as injunctive relief in the form of changes to ChatGPT. The filing includes ChatGPT’s detailed responses to user questions about the plots of Tremblay’s and Awad’s books — evidence, the attorneys argue, that OpenAI is unduly profiting off of infringed materials, which were scraped by the chat bot. While the suits venture into uncharted legal territory, they were more or less inevitable, according to those who research AI tech and privacy or practice law around those issues.
“[AI companies] should have and likely did expect these types of challenges,” says Ben Winters, senior counsel at the Electronic Privacy Information Center and head of the organization’s AI and Human Rights Project. He points out that OpenAI CEO Sam Altman mentioned a few prior “frivolous” suits against the company during his congressional testimony on artificial intelligence in May. “Whenever you create a tool that implicates so much personal data and can be used so widely for such harmful and otherwise personal purposes, I would be shocked there is not anticipated legal fire,” Winters says. “Particularly since they allow this sort of unfettered access for third parties to integrate their systems, they end up getting more personal information and more live information that is less publicly available, like keystrokes and browser activity, in ways the consumer could not at all anticipate.”
They say that OpenAI defendants “profit richly” from the use of their copyrighted materials and yet the authors never consented to the use of their copyrighted materials without credit or compensation.
ChatGPT lawsuit says OpenAI has previously utilized illegal ‘shadow libraries’ for AI training datasets
Although many types of material are used to train large language models, “books offer the best examples of high-quality longform writing,” according to the ChatGPT lawsuit.
OpenAI has previously utilized books for its AI training datasets, including unpublished novels (the majority of which were under copyright) available on a website that provides the materials for free. The plaintiffs suggest that OpenAI may have utilized copyrighted materials from “flagrantly illegal shadow libraries.”
Tremblay and Awad note that OpenAI’s March 2023 paper introducing GPT-4 failed to include any information about the training dataset. However, they say that ChatGPT was able to generate highly accurate summaries of their books when prompted, suggesting that their copyrighted material was used in the training dataset without their consent.
They filed the ChatGPT class action lawsuit on behalf of themselves and a proposed class of U.S. residents and entities that own a U.S. copyright for any work used as training data for the OpenAI language models during the class period.
Earlier this year, a tech policy group urged federal regulators to block OpenAI’s GPT-4 AI product because it does not meet federal standards.
What is the general consensus among legal experts on generative AI and copyright?
Given the hype around ChatGPT and the speculation that it could be widely used, it is important to understand the legal implications of the technology. First, do copyright owners of the text used to train ChatGPT have a copyright infringement claim against OpenAI? Second, can the output of ChatGPT be protected by copyright and, if so, who owns that copyright?
To answer these questions, we need to understand the application of US copyright law.
Copyright Law Basics
Based on rights in Article I, Section 8 of the Constitution, Congress passed the first copyright law in 1790. It has been amended several times. Today, US copyright law is governed by the Copyright Act of 1976. This law grants authors of original works exclusive rights to reproduce, distribute, and display their work. Copyright protection applies from the moment of creation, and, for most works, the copyright term is the life of the author plus 70 years after the author’s death. Under copyright law, the copyright holder has the exclusive right to make copies of the work, distribute it, display it publicly, and create derivative works based on it. Others who want to use the work must obtain permission from the copyright holder or use one of the exceptions to copyright law, such as fair use.
The purpose of copyright law is to incentivize authors to create novel and creative works. It does this by granting authors exclusive rights to control the use of their work, thus allowing them to financially benefit from their works. Copyright law also encourages the dissemination of knowledge by allowing others to use copyrighted works under certain conditions, such as through the fair use doctrine, which allows for limited use of copyrighted material for the purposes of criticism, commentary, news reporting, teaching, scholarship, or research. By protecting the rights of authors and creators while also allowing for the use of copyrighted works for the public benefit, copyright law aims to strike a balance between the interests of authors and the public.
Inputs – Training ChatGPT with Copyrighted Material
ChatGPT was trained on a large training dataset sourced from the internet, including a vast amount of text from websites, articles, books, social media posts, and academic papers. Importantly, ChatGPT was not aware of the source of the data, it only saw the text and learned the patterns and relationships between the words, phrases and sentences. The vast majority of the text used to train ChatGPT was certainly subject to copyright protection—except for text that is in the public domain like facts or discoveries or works whose term of copyright protection has ended.
Did the ChatGPT training process violate the copyright of the original authors? To answer that question we must determine: if during the training process OpenAI copied the underlying works—because copyright infringement requires an act of copying works that are protected by copyright; is the output of ChatGPT a “derivative work” under copyright law; and would such copying or production of a derivate work fall under the “fair use” exception of copyright law.
Copying During Training
We are not aware of publicly available information regarding whether, during the training process, the training text for ChatGPT was copied or simply referenced. Therefore, we asked ChatGPT and received this answer:
Prompt: During the ChatGPT training process, was the underlying training text copied into a OpenAI database?
Answer: During the training process, text from various sources is used to train the ChatGPT model. It is likely that the text was copied into an internal database at OpenAI for the purpose of training the model. However, the training text is typically preprocessed to remove any sensitive information such as personal identifiers, copyrighted text, etc. In addition, the text is also used to train the model and not stored in a database. The model uses the text to learn patterns and structure of the language and once the training is done, it doesn’t require the text anymore.
So, it seems that during the training process, text was copied. It is also interesting that ChatGPT stated that the training text was “preprocessed” to remove any copyrighted text. That seems highly unlikely since otherwise nearly all text would have been removed.
Is ChatGPT Output a Derivative Work?
Under US copyright law, the owner of a copyright has the exclusive right “to prepare derivative works based upon the copyrighted work.” A “derivative work” is “a work based upon one or more preexisting works.” ChatGPT is trained on preexisting works and generates output based on that training.
As Daniel Gervais, a professor at Vanderbilt Law School who specializes in intellectual property law, says, the definition of a derivative work under copyright law “could loosely be used as a definition of machine learning when applied to the creation of literary and artistic productions because AI machines can produce literary and artistic content (output) that is almost necessarily ‘based upon’ a dataset consisting of preexisting works.” Under this view, it seems that all ChatGPT output is a derivative work under copyright law.
On a related point, it is worth noting that in producing its output, ChatGPT is not “copying” anything. ChatGPT generates text based on the context of the input and the words and phrase patterns it was trained on. ChatGPT is not “copying” and then changing text.
What About Fair Use?
Let’s assume that the underlying text was copied in some way during the ChatGPT training process. Let’s further assume that outputs from Chatto are, at least sometimes, derivative works under copyright law. If that is the case, do copyright owners of the original works have a copyright infringement claim against OpenAI? Not if the copying and the output generation are covered by the doctrine of “fair use.” If a use qualifies as fair use, then actions that would otherwise be prohibited would not be deemed an infringement of copyright.
In determining whether the use made of a work in any particular case is a fair use, the factors include:
The purpose and character of the use, including whether such use is of a commercial nature or is for nonprofit educational purposes.
The nature of the copyrighted work.
The amount and substantiality of the portion used in relation to the copyrighted work as a whole.
The effect of the use upon the potential market for or value of the copyrighted work.
In this case, assuming OpenAI copied copyrighted text as part of the ChatGPT training process, such copying was not for a commercial purpose and had no economic impact on the copyright owner. Daniel Gervais says “it is much more likely than not” that training systems on copyrighted data will be covered by fair use.
In determining if a commercial use will be considered “fair use,” the courts will primarily look at the scope and purpose of the use and the economic impact of such use. Does the use in question change the nature of the underlying copyright material in some material way (described as a “transformative” use) and does it economically impact the original copyright holder?
Without a specific example, it is difficult to determine exactly if a resulting output from ChatGPT would be fair use. The fact that ChatGPT does not copy and has been trained on millions of underlying works, it seems likely most output would be fair use—without using significant portions of any one protected work. In addition, because of the vast corpus of text used to train ChatGPT, it seems unlikely that ChatGPT output will have a negative economic impact on any one copyright holder. But, given the capabilities of ChatGPT, that might not always be the case.
Imagine if you asked ChatGPT to “Write a long-form, coming of age, story in the style of J.K. Rowling, using the characters from Harry Potter and the Chamber of Secrets.” In that case, it would seem that the argument for fair use would be weak. This story could be sold to the public and could conceivably have a negative economic impact on J.K. Rowling. A person that wants to read a story about Harry Potter might buy this story instead of buying a book by J. K. Rowling.
Finally, it is worth noting that OpenAI is a non-profit entity that is a “AI research and deployment company.” It seems that OpenAI is the type of research company, and ChatGPT is the type of research project, that would have a strong argument for fair use. This practice has been criticized as “AI Data Laundering,” shielding commercial entities from liability by using a non-profit research institution to create the data set and train AI engines that might later be used in commercial applications.
Outputs – Can the Output of ChatGPT be Protected by Copyright
Is the output of ChatGPT protected by copyright law and, if so, who is the owner? As an initial matter, does the ChatGPT textual output fit within the definition of what is covered under copyright law: “original works of authorship fixed in any tangible medium of expression.”
The text generated by ChatGPT is the type of subject matter that, if created by a human, would be covered by copyright. However, most scholars have opined, and the US Copyright Office has ruled that the output of generative AI systems, like ChatGPT, are not protectable under US copyright law because the work must be an original, creative work of a human author.
In 2022, the US Copyright Office, ruling on whether a picture generated completely autonomously by AI could be registered as a valid copyright, stated “[b]because copyright law as codified in the 1976 Act requires human authorship, the [AI Generated] Work cannot be registered.” The U.S. Copyright Office has issued several similar statements, informing creators that it will not register copyright for works produced by a machine or computer program. The human authorship requirement of the US Copyright Office is set forth as follows:
The Human Authorship Requirement – The U.S. Copyright Office will register an original work of authorship, provided that the work was created by a human being. The copyright law only protects “the fruits of intellectual labor” that “are founded in the creative powers of the mind.” Trade-Mark Cases, 100 U.S. 82, 94 (1879).
While such policies are not binding on the courts, the stance by the US Copyright Office seems to be in line with the purpose of copyright law flowing from the Constitution: to incentivize humans to produce creative works by giving them a monopoly over their creations for a limited period of time. Machines, of course, need and have no such motivation. In fact, copyright law expressly allows a corporation or other legal entity to be the owner of a copyright under the “work made for hire” doctrine. However, to qualify as a work made for hire, the work must be either work prepared by an employee within the scope of his or her employment, or be prepared by a party who “expressly agrees in a written instrument signed by them that the work shall be considered a work made for hire.” Only humans can be employees and only humans or corporations can enter a legally binding contract—machines cannot.
Other articles of note in this Open Access Scientific Journal on ChatGPT and Open AI Include:
Can the Public Benefit Company Structure Save US Healthcare?
Curator: Stephen J. Williams, Ph.D.
UPDATED 11/05/2023
Public Benefit Corporation structure in healthcare has actually been around since the 1970s in New Yourk State, when New York City’s new Health and Hospitals Corporation took over the city Department of Hospitals and today runs 11 hospitals and four long-term care facitlites in the city. The following link to an article describes however the problems occuring with Nassau and Westchester hosptial systems, which were converted to New York PBC status in the 1990s. As the article states the financial problems in 2004 which these hospitals encountered
do not stem from their unusual status as public benefit corporations, and might have been even worse off had they not converted
The New York Times article of 2004 “At 2 Hospitals, Fiscal Troubles in the Glare of Public View” highlight in fact the growing problem that all hospitals are encountering, especially on the fiscal side. But it does highlight how to better structure these entities and why full commitment to the PBC structure is necessary.
In 2003 New York State had a record closure of hospitals, and in 2004 Nassau and WestChester were having such fiscal problems it threatened the bond status of those counties. Despite the regular problems hospitals had, critics had said there were two major contributing factors to their woes
the two agencies had not completed their transition from government operations to fully competitve hospitals
as a PBC they bear a costly mission of serving the uninsured
As a PBC the structure allows one to shed cumbersome government rules, giving them the flexibility to conduct business like other hospitals.
In addition they are no longer dependent, in fact now forced, to forgo dependence on public funding and look for independent means of investment. With their semi-independence from government the agencies also are more insulted from political pressure.
However this seemed to be the problem. These agencies were still to dependent on their local government and there was still local political influence on their boards.
UPDATED 3/15/2023
According to Centers for Medicare and Medicare Services (CMS.gov) healthcare spending per capita has reached 17.7percent of GDP with, according to CMS data:
From 1960 through 2013, health spending rose from $147 per person to $9,255 per person, an average annual increase of 8.1 percent.
the National Health Expenditure Accounts (NHEA) are the official estimates of total health care spending in the United States. Dating back to 1960, the NHEA measures annual U.S. expenditures for health care goods and services, public health activities, government administration, the net cost of health insurance, and investment related to health care. The data are presented by type of service, sources of funding, and type of sponsor.
Graph: US National Healthcare Expenditures as a percent of Gross Domestic Product from 1960 to current. Recession periods are shown in bars. Note that the general trend has been increasing healthcare expenditures with only small times of decrease for example 2020 in year of COVID19 pandemic. In addition most of the years have been inflationary with almost no deflationary periods, either according to CPI or healthcare costs, specifically.
U.S. health care spending grew 4.6 percent in 2019, reaching $3.8 trillion or $11,582 per person. As a share of the nation’s Gross Domestic Product, health spending accounted for 17.7 percent.
And as this spending grew (demand for health care services) associated costs also rose but as the statistical analyses shows there was little improvement in many health outcome metrics during the same time.
Graph of the Growth of National Health Expenditures (NHE) versus the growth of GDP. Note most years from 1960 growth rate of NHE has always been higher than GDP, resulting in a seemingly hyperinflationary effect of healthcare. Also note how there are years when this disconnect is even greater, as there were years when NHE grew while there were recessionary periods in the general economy.
It appears that US healthcare may be on the precipice of a transformational shift, but what will this shift look like? The following post examines if the corporate structure of US healthcare needs to be changed and what role does a Public Benefit Company have in this much needed transformation.
Hippocratic Oath
I swear by Apollo the physician, and Asclepius, and Hygieia and Panacea and all the gods and goddesses as my witnesses, that, according to my ability and judgement, I will keep this Oath and this contract:
To hold him who taught me this art equally dear to me as my parents, to be a partner in life with him, and to fulfill his needs when required; to look upon his offspring as equals to my own siblings, and to teach them this art, if they shall wish to learn it, without fee or contract; and that by the set rules, lectures, and every other mode of instruction, I will impart a knowledge of the art to my own sons, and those of my teachers, and to students bound by this contract and having sworn this Oath to the law of medicine, but to no others.
I will use those dietary regimens which will benefit my patients according to my greatest ability and judgement, and I will do no harm or injustice to them.
I will not give a lethal drug to anyone if I am asked, nor will I advise such a plan; and similarly I will not give a woman a pessary to cause an abortion.
In purity and according to divine law will I carry out my life and my art.
I will not use the knife, even upon those suffering from stones, but I will leave this to those who are trained in this craft.
Into whatever homes I go, I will enter them for the benefit of the sick, avoiding any voluntary act of impropriety or corruption, including the seduction of women or men, whether they are free men or slaves.
Whatever I see or hear in the lives of my patients, whether in connection with my professional practice or not, which ought not to be spoken of outside, I will keep secret, as considering all such things to be private.
So long as I maintain this Oath faithfully and without corruption, may it be granted to me to partake of life fully and the practice of my art, gaining the respect of all men for all time. However, should I transgress this Oath and violate it, may the opposite be my fate.
Translated by Michael North, National Library of Medicine, 2002.
Much of the following information can be found on the Health AffairsBlog in a post entitled
Limitations of For Profit and Non-Profit Hospitals
For profit represent ~ 25% of US hospitals and are owned and governed by shareholders, and can raise equity through stock and bond markets.
According to most annual reports, the CEOs incorrectly assume they are legally bound as fiduciaries to maximize shareholder value. This was a paradigm shift in priorities of companies which started around the mid 1980s,aphenomenon discussed below.
A by-product of this business goal, to maximize shareholder value, is that CEO pay and compensation is naturally tied to equity markets. A means for this is promoting cost efficiencies, even in the midst of financial hardships.
A clear example of the failure of this system can be seen during the 2020- current COVID19 pandemic in the US. According to the Medicare Payment Advisory Commission, four large US hospitals were able to decrease their operating expenses by $2.3 billion just in Q2 2020. This amounted to 65% of their revenue; in comparison three large NONPROFIT hospitals reduced their operating expense by an aggregate $13 million (only 1% of their revenue), evident that in lean times for-profit will resort to drastic cost cutting at expense of service, even in times of critical demands for healthcare.
Because of their tax structure and perceived fiduciary responsibilities, for-profit organizations (unlike non-profit and public benefit corporations) are not legally required to conduct community health need assessments, establish financial assistance policies, nor limit hospital charges for those eligible for financial assistance. In addition to the difference in tax liability, for-profit, unlike their non-profit counterparts, at least with hospitals, are not funded in part by state or local government. As we will see, a large part of operating revenue for non-profit university based hospitals is state and city funding.
Therefore risk for financial responsibility is usually assumed by the patient, and in worst case, by the marginalized patient populations on to the public sector.
Tax Structure Considerations of for-profit healthcare
Financials of major for-profit healthcare entities (2020 annual)
Non-profit Healthcare systems
Nonprofits represent about half of all hospitals in the US. Most of these exist as a university structure, so retain the benefits of being private health systems and retaining the funding and tax benefits attributed to most systems of higher education. And these nonprofits can be very profitable. After taking in consideration the state, local, and federal tax exemptions these nonprofits enjoy, as well as tax-free donations from contributors (including large personal trust funds), a nonprofit can accumulate a large amount of revenue after expenses. In fact 82 nonprofit hospitals had $33 billion of net asset increase year-over-year (20% increase) from 2016 to 2017. The caveat is that this revenue over expenses is usually spent on research or increased patient services (this may mean expanding the physical infrastructure of the hospital or disseminating internal grant money to clinical investigators, expanding the hospital/university research assets which could result in securing even larger amount of external funding from government sources.
And although this model may work well for intercity university/healthcare systems, it is usually a struggle for the rural nonprofit hospitals. In 2020, ten out of 17 rural hospitals that went under were nonprofits. And this is not just true in the tough pandemic year. Over the past two decades multitude of nonprofit rural hospitals had to sell and be taken over by larger for-profit entities.
Hospital consolidation has led to a worse patient experience and no real significant changes in readmission or mortality data. (The article below is how over 130 rural hospitals have closed since 2010, creating a medical emergency in rural US healthcare)
And according to the article below it is only to get worse
The authors of the Health Affairs blog feel a major disadvantage of both the for-profit and non-profit healthcare systems is “that both face limited accountability with respect to anticompettive mergers and acquisitions.”
More hospital consolidation is expected post-pandemic
Hospital deal volume is likely to accelerate due to the financial damage inflicted by the coronavirus pandemic.
The anticipated increase in volume did not show up in the latest quarter, when deals were sharply down.
The pandemic may have given hospitals leverage in coming policy fights over billing and the creation of “public option” health plans.
Hospital consolidation is likely to increase after the COVID-19 pandemic, say both critics and supporters of the merger-and-acquisition (M&A) trend.
The financial effects of the coronavirus pandemic are expected to drive more consolidation between and among hospitals and physician practices, a group of policy professionals told a recent Washington, D.C.-based web briefing sponsored by the Alliance for Health Policy.
“There is a real danger that this could lead to more consolidation, which if we’re not careful could lead to higher prices,” said Karyn Schwartz, a senior fellow at the Kaiser Family Foundation (KFF).
Schwartz cited a recent KFF analysis of available research that concluded “provider consolidation leads to higher health care prices for private insurance; this is true for both horizontal and vertical consolidation.”
Kenneth Kaufman, managing director and chair of Kaufman Hall, noted that crises tend to push financially struggling organizations “further behind.”
“I wouldn’t be surprised at all if that happens,” Kaufman said. “That will lead to further consolidation in the provider market.”
The initial rounds of federal assistance from the CARES Act, which were based first on Medicare revenue and then on net patient revenue, may fuel consolidation, said Mark Miller, PhD, executive vice president of healthcare for Arnold Ventures. That’s because the funding formulas favored organizations that already had higher revenues, he said, and provided less assistance to low-revenue organizations.
HHS has distributed $116.2 billion from the $175 billion in provider funding available through the CARES Act and the Paycheck Protection Program and Health Care Enhancement Act. The largest distributions used the two revenue formulas cited by Miller.
No surge in M&A yet
The expected burst in hospital M&A activity has yet to occur. Kaufman Hall identified 14 transactions in the second quarter of 2020, far fewer than in the same quarter in any of the four preceding years, when second-quarter transactions totaled between 19 and 31. The latest deals were not focused on small hospitals, with average seller revenue of more than $800 million — far larger than the previous second-quarter high of $409 million in 2018.
Six of the 14 announced transactions were divestitures by major for-profit health systems, including Community Health Systems, Quorum and HCA.
Kaufman Hall’s analysis of the recent deals identified another pandemic-related factor that may fuel hospital M&A: closer ties between hospitals. The analysis cited the example of Lifespan and Care New England, which had suspended merger talks in 2019. More recently, in a joint announcement, the CEOs of the two systems noted that because of the COVID-19 crisis, the two systems “have been working together in unprecedented ways” and “have agreed to enter into an exploration process to understand the pros and cons of what a formal continuation of this collaboration could look like in the future.”
The M&A outlook for rural hospitals
The pandemic has had less of a negative effect on the finances of rural hospitals that previously joined larger health systems, said Suzie Desai, senior director of not-for-profit healthcare for S&P Global.
A CEO of a health system with a large rural network told Kaufman the federal grants that the system received for its rural hospitals were much larger than the grants paid through the general provider fund.
“If that was true across the board, then the federal government recognized that many rural hospitals could be at risk of not being able to make payroll; actually running out of money,” Kaufman said. “And they seem to have bent over backwards to make sure that didn’t happen.”
Other CARES Act funding distributed to providers included:
$12.8 billion for 959 safety net hospitals
$11 billion to almost 4,000 rural healthcare providers and hospitals in urban areas that have certain special rural designations in Medicare
Telehealth has helped rural hospitals but has not been sufficient to address the financial losses inflicted by the pandemic, Desai said.
Other coming trends include a sharper cost focus
Desai expects an increasing focus “over the next couple years” on hospital costs because of the rising share of revenue received from Medicare and Medicaid. She expects increased efforts to use technology and data to lower costs.
Billy Wynne, JD, chairman of Wynne Health Group, expects telehealth restrictions to remain relaxed after the pandemic.
Also, the perceptions of the public and politicians about the financial health of hospitals are likely to give those organizations leverage in coming policy fights over changes such as banning surprise billing and creating so-called public-option health plans, Wynne said. As an example, he cited the Colorado legislature’s suspension of the launch of a public option “in part because of sensitivities around hospital finances in the COVID pandemic.”
“Once the dust settles, it’ll be interesting to see if their leverage has increased or decreased due to what we’ve been through,” Wynne said.
About the Author
Rich Daly, HFMA Senior Writer and Editor,
is based in the Washington, D.C., office. Follow Rich on Twitter: @rdalyhealthcare
The quality of care at hospitals acquired during a recent wave of consolidations has gotten worse or stayed the same, according to a study led by Harvard Medical School scientists published Jan. 2 in NEJM.
The findings deal a blow to the often-cited arguments that hospital consolidation would improve care. A flurry of earlier studies showed that mergers increase prices. Now after analyzing patient outcomes after hundreds of hospital mergers, the new research also dashes the hopes that this more expensive care might be of higher quality.
Get more HMS news here
“Our findings call into question claims that hospital mergers are good for patients—and beg the question of what we are getting from higher hospital prices,” said study senior author J. Michael McWilliams, the Warren Alpert Foundation Professor of Health Care Policy in the Blavatnik Institute at HMS and an HMS professor of medicine and a practicing general internist at Brigham and Women’s Hospital.
McWilliams noted that rising hospital prices have been one of the leading drivers of unsustainable growth in U.S. health spending.
To examine the impact of hospital mergers on quality of care, researchers from HMS and Harvard Business School examined patient outcomes from nearly 250 hospital mergers that took place between 2009 and 2013. Using data collected by the Centers for Medicare and Medicaid Services, they analyzed variables such as 30-day readmission and mortality rates among patients discharged from a hospital, as well as clinical measures such as timely antibiotic treatment of patients with bacterial pneumonia. The researchers also factored in patient experiences, such as whether those who received care at a given hospital would recommend it to others. For their analysis, the team compared trends in these indicators between 246 hospitals acquired in merger transactions and unaffected hospitals.
The verdict? Consolidation did not improve hospital performance, and patient-experience scores deteriorated somewhat after the mergers.
The study was not designed to examine the reasons behind the worsening in patient experience. Weakening of competition due to hospital mergers could have contributed, the researchers said, but deeper exploration suggested other potential mechanisms. Notably, the analysis found the decline in patient-experience scores occurred mainly in hospitals acquired by hospitals that already had a poor patient-experience score—a finding that suggests acquisitions facilitate the spread of low quality care but not of high quality care.
The researchers caution that isolated, individual mergers may have still yielded positive results—something that an aggregate analysis is not powered to capture. And the researchers could only examine measurable aspects of quality. The trend in hospital performance on these standard measures, however, appears to point to a net effect of overall decline, the team said.
“Since our study estimated the average effects of mergers, we can’t rule out the possibility that some mergers are good for patient care,” said first author Nancy Beaulieu, research associate in health care policy at HMS. “But this evidence should give us pause when considering arguments for hospitals mergers.”
The work was supported by the Agency for Healthcare Research and Quality (grant no. U19HS024072).
Co-investigators included Bruce Landon and Jesse Dalton from HMS, Ifedayo Kuye, from the University of California, San Francisco, and Leemore Dafny from Harvard Business School and the National Bureau of Economic Research.
Public benefit corporations (versus Benefit Corporate status, which is more of a pledge) are separate legal entities which exist as a hybrid, for-profit/nonprofit company but is mandated to
Pursue a general or specific public benefit
Consider the non-financial interests of its shareholders and other STAKEHOLDERS when making decision
report how well it is achieving its overall public benefit objectives
Have limited fiduciary responsibility to investors that remains IN SCOPE of public benefit goal
In essence, the public benefit corporations executives are mandated to run the company for the benefit of STAKEHOLDERS first, if those STAKEHOLDERS are the public beneficiary of the company’s goals. This in essence moves the needle away from the traditional C-Corp overvaluing the needs of shareholders and brings back the mission of the company and in the case of healthcare, the needs of its stakeholders, the consumers of healthcare.
PBCs are legal entities recognized by states rather than by the federal government. So far, in 2020 about 37 states allow companies to incorporate as a PBC. Stipulations of the charter include semiannual reporting of the public benefits bestowed by the company and how well it is achieving its public benefit mandate. There are about 3,000 US PBCs. Some companies have felt it was in their company mission and financial interest to change incorporation as a PBC.
Some well known PBCs include
Ben and Jerry’s Ice Cream
American Red Cross
Susan B. Komen Foundation
Allbirds (a shoe startup valued at $1.7 billion when made switch)
Bombas (the sock company that donates extra socks when you buy a pair)
Lemonade (a publicly traded insurance PBC that has beneficiaries select a nonprofit that the company will donate to)
Although the number of PBCs in the healthcare arena is increasing
Not many PBCs are in the area of healthcare delivery
Noone is quite sure what the economic model would look like for a healthcare delivery PBC
Some example of hospital PBC include NYC Health + Hospitals and Community First Medical Center in Chicago.
Benefits of moving a hospital to PBC Status
PBCs are held legally accountable to a predefined public benefit. For hospitals this could be delivering cost-effective quality of care and affordable to a local citizenry or an economically disadvantaged population. PBCs must produce at least an annual report on the public benefits it has achieved contrasted against a third party standard. For example a hospital could include data of Medicaid related mortality risks, data neither the C-corp nor the nonprofit 501c would have to report on. Most nonprofits and charities report their taxes on a schedule H or Form 990, which only has to report the officer’s compensation as well as monies given to charitable organizations, or other 501 organizations. The nonprofit would show a balance of zero as the donated money for that year would be allocated out for various purposes. Hospitals, even as nonprofits, are not required to submit all this data. Right now in US the ACA just requires any hospital that receives government or ACA insurance payments to report certain outcome statistics. Although varying state by state, a PBC should have a “benefit officer” to make sure the mandate is being met. In some cases a PBC benefit officer could sue the board for putting shareholder interest over the public benefit mandate.
A PBC can include community stakeholders in the articles of incorporation thus giving a voice to local community members. This would be especially beneficial for a hospital serving, say, a rural community.
PBCs do have advantages of the for-profit companies as they are not limited to non-equity forms of investment. A PBC can raise money in the equity markets or take on debt and finance it. These financial instruments are unavailable to the non-profit. Yet one interesting aspect is that PBCs require a HIGHER voting threshold by shareholders than a traditional for profit company in the ability to change their public benefit or convert their PBC back to a for-profit.
Limitations of the PBC
Little incentive financially for current and future hospitals to incorporate as a PBC. Herein lies a huge roadblock given the state of our reimbursement structure in this country. Although there may be an incentive with regard to hiring and retention of staff drawn to the organization’s social purpose. There have been, in the past, suggestions to allow hospitals that incorporate at PBC to receive some tax benefit, but this legislation has not gone through either at state or federal level. (put link to tax article).
In order for there to be value to constituents (patients) there must be strong accountability measures. This will require the utmost in ethical behavior by a board and executives. We have witnessed, through M&A by large health groups, anticompetitive and near monopoly behavior.
There are no federal guidelines but varying guidelines from state to state. There must be some federal recognition of the PBC status when it comes to healthcare, such as that the government is one of the biggest payers of US healthcare.
This is a great interview with ArcHealth, a PBC healthcare system.
Arc Health PBC is a public benefit corporation, a mission-driven for-profit company that utilizes a market-driven approach to achieving our short and long-term social goals. As a public benefit corporation, Arc Health is also a social enterprise working to further our mission of providing healthcare to rural, underserved, and indigenous communities through business practices that improve the recruitment and retention of quality healthcare providers.
What is a Social Enterprise?
While there is no one exact definition, according to the Social Enterprise Alliance, a social enterprise is an “organization that addresses a basic unmet need or solves a social or environmental problem through a market-driven approach.” A social enterprise is not a distinct legal entity, but instead, an “ideological spectrum marrying commercial approaches with social good.” Social enterprises foster a dual-bottom-line – simultaneously seeking profits and social impact. Arc Health, like many social enterprises, seeks to be self–sustainable.
Two primary structures fall under the social enterprise umbrella: nonprofits and for-profit organizations. There are also related entities within both structures that could be considered social enterprises. Any of these listed structures can be regarded as a social enterprise depending on if and how involved they are with socially beneficial programs.
What is a Public Benefit Corporation?
Public Benefit Corporations (PBCs), also known as benefit corporations, are “for-profit companies that balance maximizing value to stakeholders with a legally binding commitment to a social or environmental mission.” PBCs operate as for-profit entities with no tax advantages or exemptions. Still, they must have a “purpose of creating general public benefit,” such as promoting the arts or science, preserving the environment, or providing benefits to underserved communities. PBCs must attain a higher degree of corporate purpose, expanded accountability, and expected transparency.
There are now over 3,000 registered PBCs, comprising approximately 0.1% of American businesses.
As a PBC, Arc Health expects to access capital through individual investors who seek financial returns, rather than through donations. Arc Health’s investors make investments with a clear understanding of the balance the company must strike between financial returns (I.e., profitability) and social purpose. Therefore, investors expect the company to be operationally profitable to ensure a financial return on their investments, while also making clear to all stakeholders and the public that generating social impact is the priority.
What is the difference between a Social Enterprise and PBC?
Social enterprises and PBCs emulate similar ideals that value the importance and need to invoke social change vis-a-vis working in a market-driven industry. Public benefit corporations fall under the social enterprise umbrella. An organization may choose to use a social enterprise model and incorporate itself as either a not-for-profit, C-Corp, PBC, or other corporate structure.
How did Arc Health Become a Public Benefit Corporation?
Arc Health was initially formed as a C-Corp. In 2019, Arc Health’s CEO and Co-Founder, Dave Shaffer, guided the conversion from a C-Corp to a PBC, incorporated in Delaware. Today, Arc Health follows guidelines and expectations for PBCs, including adhering to the State of Delaware’s requirements for PBCs.
Why is Arc Health a Social Enterprise and Public Benefit Corporation?
Arc Health believes it is essential to commit ourselves to our mission and demonstrate our dedication through our actions. We work to adhere to the core values of accountability, transparency, and purpose. As a registered public benefit company and a social enterprise, we execute our drive to achieve health equity in tangible and effective ways that the communities we work with, our stakeholders, and our providers expect of us.
90% of Americans say that companies must not only say a product or service is beneficial, but they also need to prove its benefit.
When we partner with health clinics and hospitals, we aim to provide services that enact lasting change. For example, we work with healthcare providers who desire to contribute both clinical and non-clinical skills. In 2020, Arc Health clinicians developed COVID-19 response protocols and educational materials about the vaccines. They participated in pain management working groups. They identified and followed up with kids in the community who were overdue for a well-child check. Arc Health providers should be driven by a desire to develop a long-term relationship with a healthcare service provider and participate in its successes and challenges.
Paradigm Shift in the 1980’s: Companies Start to Emphasize Shareholders Over Stakeholders
So earlier in this post we had mentioned about a shift in philosophy at the corporate boardroom that affected how comparate thought, value, and responsibility: Companies in the 1980s started to shift their focus and value only the needs of corporate ShAREHOLDERS at the expense of their traditional STAKEHOLDERS (customers, clients). Many movies and books have been written on this and debatable if deliberate or a by-product of M&A, hostile takeovers, and the stock market in general but the effect was that the consumer was relegated as having less value, even though marketing budgets are very high. The fiduciary responsibility of the executive was now defined in terms of satisfying shareholders, who were now big huge and powerful brokerage houses, private equity, and hedge funds. A good explanation by Medium.com Tyler Lasicki is given below.
In a famous 1970 New York Times Article, Milton Friedman postulated that the CEO, as an employee of the shareholder, must strive to provide the highest possible return for all shareholders. Since that article, the United States has embraced this idea as the fundamental philosophy supporting the ultimate purpose of businesses — The Shareholders Come First.
In August of 2019, the Business Roundtable, a group made up of the most influential U.S CEOs, published a letter shifting their stance on the purpose of a corporation. Regardless of whether this piece of paper will actually result in any systematic changes has yet to be seen, however this newly stated purpose of business is a dramatic shift from the position Milton Friedman took in 1970. According to the statement, these corporations will no longer prioritize maximizing profits for shareholders, but instead turn their focus to benefiting all stakeholders — including citizens, customers, suppliers, employees, on par with shareholders.
Now the social responsibility of a company and the CEO was to maxiimize the profits even at the expense of any previous social responsibility they once had.
Small sample of the 181 Signatures attached to the Business Roundtable’s letter
What has happened over the past 50 years that has led to such a fundamental change in ideology? What has happened to make the CEO’s of America’s largest corporations suddenly change their stance on such a foundational principle of what it means to be an American business?
Since diving into this subject, I have come to find that the “American fundamental principle” of putting shareholders first is one that is actually not all that fundamental. In fact, for a large portion of our nation’s history this ideology was actually seen as the unpopular position.
Key ideological shifts in U.S. history
This post dives into a brief history of these two contrasting ideological viewpoints in an attempt to contextualize the forces behind both sides — specifically, the most recent shift (1970–2019). This basic idea of what is most important; the stakeholder or the shareholder, is the underlying reason as to why many things are the way they are today. A corporation’s priority of shareholder or stakeholder ultimately impacts employee salaries, benefits, quality of life within communities, environmental conditions, even the access to education children can receive. It affects our lives in a breadth and depth of ways and now that corporations may be changing positions (yet again) to focus on a model that prioritizes the stakeholder, it is important to understand why.
Looking forward, if stakeholder priority ends up being the popular position among American businesses, how long will it last for? What could lead to its downfall? And what will managers do to ensure a long term stakeholder-friendly business model?
It is clear to me the reasons that have led to these shifts in ideology are rather nuanced, however I want to highlight a few trends that have had a major impact on businesses changing their priorities while also providing context as to why things have shifted.
The Ascendancy of Shareholder Value
Following the 1929 stock market crash and the Great Depression, stakeholder primacy became the popular perspective within corporate America. Stakeholder primacy is the idea that corporations are to consider a wider group of interested parties (not just shareholders) whose positions need to be taken into consideration by corporate governance. According to this point of view, rather than solely being an agent for shareholders, management’s responsibilities were to be dispersed among all of its constituencies, even if it meant a reduction in shareholder value. This ideology lasted as the dominant position for roughly 40 years, in part due to public opinion and strong views on corporate responsibility, but also through state adoption of stakeholder laws.
By the mid-1970s, falling corporate profitability and stagnant share prices had been the norm for a decade. This poor economic performance influenced a growing concern in the U.S. regarding the perceived divergence between manager and shareholder interest. Many held the position that profits and share prices were suffering as a result of corporation’s increased attention on stakeholder groups.
This noticeable divergence in interests sparked many academics to focus their research on corporate management’s motivations in decision making regarding their allocation of resources. This branch of research would later be known as agency theory, which focused on the relationship between principals (shareholders) and their agents (management). Research at the time outlined how over the previous decades corporate management had pursued strategies that were not likely to optimize resources from a shareholder’s perspective. These findings were part of a seismic shift of corporate philosophy, changing priority from the stakeholders of a business to the shareholders.
By 1982, the U.S. economy started to recover from a prolonged period of high inflation and low economic growth. This recovery acted as a catalyst for change in many industries, leaving many corporate management teams to struggle in response to these changes. Their business performance suffered as a result. These distressed businesses became targets for a group of new investors…private equity firms.
Now the paradigm shift had its biggest backer…. private equity! And private equity care about ONE thing….. THEIR OWN SHARE VALUE and subsequently meaning corporate profit, which became the most important directive for the CEO.
So it is all hopeless now? Can there be a shift back to the good ‘ol days?
Well some changes are taking place at top corporate levels which may help the stakeholders to have a voice at the table, as the following IRMagazine article states.
And once again this is being led by the Business Roundtable, the same Business Roundtable that proposed the shift back in the 1970s.
n a major corporate shift, shareholder value is no longer the main objective of the US’ top company CEOs, according to the Business Roundtable, which instead emphasizes the ‘purpose of a corporation’ and a stakeholder-focused model.
The influential body – a group of chief executive officers from major US corporations – has stressed the idea of a corporation dropping the age-old notion that corporations function first and foremost to serve their shareholders and maximize profits.
Rather, the focus should be on investing in employees, delivering value to customers, dealing ethically with suppliers and supporting outside communities as the vanguard of American business, according to a Business Roundtable statement.
‘While each of our individual companies serves its own corporate purpose, we share a fundamental commitment to all of our stakeholders,’ reads the statement, signed by 181 CEOs. ‘We commit to deliver value to all of them, for the future success of our companies, our communities and our country.’
Gary LaBranche, president and CEO of NIRI, tells IR Magazine that this is part of a wider trend: ‘The redefinition of purpose from shareholder-focused to stakeholder-focused is not new to NIRI members. For example, a 2014 IR Update article by the late Professor Lynn Stout urges a more inclusive way of thinking about corporate purpose.’
NIRI has also addressed this concept at many venues, including the senior roundtable annual meeting and the NIRI Annual Conference, adds LaBranche. This trend was further seen in the NIRI policy statement on ESG disclosure, released in January this year.
Analyzing the meaning of this change in more detail, LaBranche adds: ‘The statement is a revolutionary break with the Business Roundtable’s previous position that the purpose of the corporation is to create value for shareholders, which was a long-held position championed by Milton Friedman.
‘The challenge is that Friedman’s thought leadership helped to inspire the legal and regulatory regime that places wealth creation for shareholders as the ‘prime directive’ for corporate executives.
‘Thus, commentators like Mike Allen of Axios are quick to point out that some shareholders may actually use the new statement to accuse CEOs of worrying about things beyond increasing the value of their shares, which, Allen reminds us, is the CEOs’ fiduciary responsibility.
‘So while the new Business Roundtable statement reflects a much-needed rebalancing and modernization that speaks to the comprehensive responsibilities of corporate citizens, we can expect that some shareholders will push back on this more inclusive view of who should benefit from corporate efforts and the capital that makes it happen. The new statement may not mark the dawn of a new day, but it perhaps signals the twilight of the Friedman era.’
In a similarly reflective way, Jamie Dimon, chairman and CEO of JPMorgan Chase & Co and chairman of the Business Roundtable, says: ‘The American dream is alive, but fraying. Major employers are investing in their workers and communities because they know it is the only way to be successful over the long term. These modernized principles reflect the business community’s unwavering commitment to continue to push for an economy that serves all Americans.’
Note: Mr Dimon has been very vocal for many years on corporate social responsibility, especially since the financial troubles of 2009.
Impact of New Regulatory Trends in M&A Deals
The following podcast from Pricewaterhouse Cooper Health Research Institute (called Next in Health) discusses some of the trends in healthcare M&A and is a great listen. However from 6:30 on the podcast discusses a new trend which is occuring in the healthcare company boardroom, which is this new focus on integrating companies that have proven ESG (or environmental, social, governance) functions within their organzations. As stated, doing an M&A deal with a company with strong ESG is looked favorably among regulators now.
Please click on the following link to hear a Google Podcast Next in Health episode
Heather shows the feasability of this model with multiple biotech and healthtech startups, including one founded by Mark Cuban.
Health tech unicorn Aledade recently announced that it made the strategic decision to become a public benefit corporation (PBC).
The company joins just a handful of others in healthcare that are structured this way.
So what exactly is a PBC, and why does it matter?
PBCs are a type of for-profit corporate entity that has also adopted a public benefit purpose and is currently authorized by 35 states and the District of Columbia. A PBC must consider the nonfinancial interests of its shareholders and other stakeholders when making decisions. As a public benefit corporation, companies have to weigh their social/environmental objectives alongside maximizing value for shareholders.
While PBC and B Corp. are often used interchangeably, they are not the same. A B Corp. is a certification provided to eligible companies by the nonprofit, B Lab. A PBC is an actual legal entity that bakes into its certificate of incorporation a “public benefit,” according to Rubicon Law Group.
“I don’t think that there is a trade-off between either you do things that are good for society or you make profits in your business.” —Farzad Mostashari, M.D.
PBCs also are required to provide a report to shareholders every two years that detail how well the company is achieving its overall public benefit objectives. In some states, the report must be assessed against a third-party standard and be made publicly available. Delaware PBCs are not required to report publicly or against a third-party standard.
Aledade launched in 2014 and uses data analytics to help independent doctors’ offices transition to value-based care models. The company currently partners with more than 1,000 independent primary care practices comprising over 11,000 physicians and has nearly 150 contracts covering more than 1.7 million patients and $17 billion in total healthcare spending. Last June, the company raised $123 million in a series E round, boosting its valuation to $3.1 billion.
In a blog post, Aledade CEO and co-founder Farzad Mostashari, M.D., explained the company’s reasoning behind the move and said the corporate structure of a PBC is “well suited to mission-oriented companies where alignment with stakeholders is a key driver of the business model.”
“Aledade’s public benefit purpose means that we must weigh the interests of our primary care practice partners, their patients, our employees, and those who bear the burden of rising health care costs, alongside those of our shareholders, when we make decisions,” Mostashari said in an interview. This duty extends to all significant board decisions, including decisions on whether to go public, to make acquisitions or to sell the company, he noted.
The PBC structure helps create alignment among stakeholders and build trust, he said. “I don’t think that there is a trade-off between either you do things that are good for society or you make profits in your business. That might be true for fee-for-service businesses. It’s not true for Aledade,” he said.
He added, “For businesses that are built on trust and alignment, not considering stakeholder benefits gets you neither social good nor profits. If you’re in a business like our business where it’s actually really important that everybody have faith and belief that you are doing what’s best for patients, that you are actually in it for the long-term for practices, that’s what makes us successful as a business.”
Mark Cuban Cost Plus Drugs, which launched in January 2022 to offer low-cost rivals to overpriced generic drugs, also is structured as a public benefit corporation. The company’s founder and CEO Alexander Oshmyansky started the company in 2015 as a nonprofit, according to a feature story in D Magazine. Through Y Combinator, investors told Oshmyansky that the nonprofit model wouldn’t be able to raise the needed funds. He then reworked the business model to a PBC and launched Osh’s Affordable Pharmaceuticals in 2018.
Some other companies that are biotech drug development companies that operate under the PBC model include
Even a traditional for-profit C corporation can work toward a public mission without becoming a PBC. But, in an industry like healthcare, too often the duty to maximize financial returns for shareholders or investors can be in conflict with what is best for patients, executives say.
“With a startup, it might limit the ability to sell their business to a larger company in the future because there might be some limitations on what the larger company could do with the organization.”—Jodi Daniel, a partner in Crowell & Moring’s Health Care Group
According to some healthcare experts, PBCs offer a promising alternative as a business model for healthcare companies by providing a “North Star” by which a company can navigate critical business decisions.
“I think it really helps to drive accountability,” Huang, Osmind’s chief executive, said. “I think that’s important, especially in healthcare where it’s easy sometimes to get misaligned with all the different stakeholders that are involved in the industry. We wanted to make sure we had something to be accountable to. Second, it’s ingrained in the culture. The third element of why it was so helpful for us from the beginning is just on focus and alignment. I think we can be much more clear and transparent about what we’re focused on, our values, how we try to use that transparently to influence our decisions and how we can build a business that really ties all of that together.”
In a Health Affairs article, medical researchers at Stanford, including Jimmy Qian, a co-founder of Osmind, laid out the case for why PBCs may simultaneously improve individual patient outcomes and collective benefit without sacrificing institutions’ financial stability.
PBCs are held legally accountable to a predefined public benefit, which, for hospitals, could involve delivering high-quality, affordable care to local populations. PBCs are required to produce annual benefits reports that are assessed against a third-party standard. “These reports could be used by regulatory agencies such as the Centers for Medicare and Medicaid Services (CMS) or local health authorities to evaluate whether the PBC is making progress toward its stated mission and respond accordingly,” the researchers wrote.
But are there any trade-offs?
Having a public benefit obligation could potentially “tie the hands” of board members who can’t just focus on profits and must focus on those dual responsibilities, noted Jodi Daniel, a partner in Crowell & Moring’s Health Care Group.
“Companies that transition to being a public benefit corporation are intentionally trying to ensure that that the company’s mission doesn’t get diminished over time because it’s in their charter. So it helps [the mission] to endure. But there are pros and cons to that. It is somewhat binding the future board members and executives to follow that mission,” she said.
Daniel said she has spoken with several healthcare companies recently that are weighing the possibility of transitioning to a PBC. “Companies often don’t want to necessarily limit their options in their decision-making in the future. With a startup, it might limit the ability to sell their business to a larger company in the future because there might be some limitations on what the larger company could do with the organization,” she said in an interview.
By making decisions based on interests outside of financial ones, organizations may put themselves at a margin disadvantage as compared to pure for-profit players in the space, wrote Hospitalogy founder Blake Madden.
Faddis with Veeva said the company hasn’t seen any financial or performance trade-off as a result of operating as a PBC. He noted that the move has been good for recruiting, spurred more long-term conversations with customers and has been a source of new ideas.
“Prior to the conversion, you had employees who were thinking of new products or new functionality with the mindset of getting to be commercially successful,” Faddis said. “Now, you also have people thinking about it from the angle of, ‘Does it further one of our PBC purposes and then maybe it’s also going to be commercially successful?'”
Converting to a PBC also can be a tactic to build trust, Daniel noted, especially in healthcare, and that holds the potential to drive business.
One factor that isn’t clear is whether there is sufficient oversight to hold these companies accountable to their stated public mission. Who checks to make sure companies are making progress toward their objectives to improve healthcare?
Osmind publishes its benefit corporation report on its website to make it available to the public even though it is not required to do so. “I think that really highlights the accountability piece of you need to tell the world or at least tell your shareholders how you’re really trying to uphold your public benefit,” Huang said.
Other related articles published on this Open Access Online Scientific Journal on Healthcare Issues include the following:
The coronavirus pandemic has affected almost every country in every continent however, after months of the novel advent of novel COVID-19 cases, it has become apparent that the varied clinical responses in this epidemic (and outcomes) have laid bare some of the strong and weak aspects in, both our worldwide capabilities to respond to infectious outbreaks in a global coordinated response and in individual countries’ response to their localized epidemics.
Some nations, like Israel, have initiated a coordinated government-private-health system wide action plan and have shown success in limiting both new cases and COVID-19 related deaths. After the initial Wuhan China outbreak, China closed borders and the government initiated health related procedures including the building of new hospitals. As of writing today, Wuhan has experienced no new cases of COVID-19 for two straight days.
However, the response in the US has been perplexing and has highlighted some glaring problems that have been augmented in this crisis, in the view of this writer. In my view, which has been formulated after social discussion with members in the field ,these issues can be centered on three major areas of deficiencies in the United States that have hindered a rapid and successful response to this current crisis and potential future crises of this nature.
The mistrust or misunderstanding of science in the United States
Lack of communication and connection between patients and those involved in the healthcare industry
Socio-geographical inequalities within the US healthcare system
1. The mistrust or misunderstanding of science in the United States
For the past decade, anyone involved in science, whether directly as active bench scientists, regulatory scientists, scientists involved in science and health policy, or environmental scientists can attest to the constant pressure to not only defend their profession but also to defend the entire scientific process and community from an onslaught of misinformation, mistrust and anxiety toward the field of science. This can be seen in many of the editorials in scientific publications including the journal Science and Scientific American (as shown below)
Boston rally coincides with annual American Association for the Advancement of Science (AAAS) conference and is a precursor to the March for Science in Washington, D.C.
Responding to the troubling suppression of science under the Trump administration, thousands of scientists, allies, and frontline communities are holding a rally in Boston’s Copley Square on Sunday.
“Science serves the common good,” reads the call to action. “It protects the health of our communities, the safety of our families, the education of our children, the foundation of our economy and jobs, and the future we all want to live in and preserve for coming generations.”
It continues:
But it’s under attack—both science itself, and the unalienable rights that scientists help uphold and protect.
From the muzzling of scientists and government agencies, to the immigration ban, the deletion of scientific data, and the de-funding of public science, the erosion of our institutions of science is a dangerous direction for our country. Real people and communities bear the brunt of these actions.
The rally was planned to coincide with the annual American Association for the Advancement of Science (AAAS) conference, which draws thousands of science professionals, and is a precursor to the March for Science in Washington, D.C. and in cities around the world on April 22.
However, some feel that scientists are being too sensitive and that science policy and science-based decision making may not be under that much of a threat in this country. Yet even as some people think that there is no actual war on science and on scientists they realize that the public is not engaged in science and may not be sympathetic to the scientific process or trust scientists’ opinions.
Certainly, opponents of genetically modified crops, vaccinations that are required for children and climate science have become louder and more organized in recent times. But opponents typically live in separate camps and protest single issues, not science as a whole, said science historian and philosopher Roberta Millstein of the University of California, Davis. She spoke at a standing-room only panel session at the American Association for the Advancement of Science’s annual meeting, held in Washington, D.C. All the speakers advocated for a scientifically informed citizenry and public policy, and most discouraged broadly applied battle-themed rhetoric.
In general, it appears to be a major misunderstanding by the public of the scientific process, and principles of scientific discovery, which may be the fault of miscommunication by scientists or agendas which have the goals of subverting or misdirecting public policy decisions from scientific discourse and investigation.
This can lead to an information vacuum, which, in this age of rapid social media communication,
can quickly perpetuate misinformation.
This perpetuation of misinformation was very evident in a Twitter feed discussion with Dr. Eric Topol, M.D. (cardiologist and Founder and Director of the Scripps Research Translational Institute) on the US President’s tweet on the use of the antimalarial drug hydroxychloroquine based on President Trump referencing a single study in the International Journal of Antimicrobial Agents. The Twitter thread became a sort of “scientific journal club” with input from international scientists discussing and critiquing the results in the paper.
Please note that when we scientists CRITIQUE a paper it does not mean CRITICIZE it. A critique is merely an in depth analysis of the results and conclusions with an open discussion on the paper. This is part of the normal peer review process.
Below is the original Tweet by Dr. Eric Topol as well as the ensuing tweet thread
I reviewed the cited paperhttps://t.co/E4Iw7GpVh6 an open-label, non=randomized study The endpoint was viral PCR (mostly + or -, many ND) by nasopharyngeal swab. 6 of the 36 people were asymptomatic. 6 with pneumonia (LRTI) 6 people received "H + A" pic.twitter.com/KBjR1QcZRV
Eric – a huge issue here is they only report data on 20 of the 26 patients, and of the 6 – all deteriorated! Six hydroxychloroquine-treated patients were lost in follow-up: they worsened and weee sent to the ICU! They need to do last observation carried forward for those.
— Christopher Cannon, M.D. 🇺🇦 (@cpcannon) March 21, 2020
OMG, do you realize none of the patients in the treatment arm were definitive positives to start with? They were all in the "gray zone". JFC, this study was worse than I thought when I skimmed it the first time!
Within the tweet thread it was discussed some of the limitations or study design flaws of the referenced paper leading the scientists in this impromptu discussion that the study could not reasonably conclude that hydroxychloroquine was not a reliable therapeutic for this coronavirus strain.
The lesson:The public has to realizeCRITIQUE does not mean CRITICISM.
Scientific discourse has to occur to allow for the proper critique of results. When this is allowed science becomes better, more robust, and we protect ourselves from maybe heading down an incorrect path, which may have major impacts on a clinical outcome, in this case.
2. Lack of communication and connection between patients and those involved in the healthcare industry
In normal times, it is imperative for the patient-physician relationship to be intact in order for the physician to be able to communicate proper information to their patient during and after therapy/care. In these critical times, this relationship and good communication skills becomes even more important.
Recently, I have had multiple communications, either through Twitter, Facebook, and other social media outlets with cancer patients, cancer advocacy groups, and cancer survivorship forums concerning their risks of getting infected with the coronavirus and how they should handle various aspects of their therapy, whether they were currently undergoing therapy or just about to start chemotherapy. This made me realize that there were a huge subset of patients who were not receiving all the information and support they needed; namely patients who are immunocompromised.
These are patients represent
cancer patient undergoing/or about to start chemotherapy
Patients taking immunosuppressive drugs: organ transplant recipients, patients with autoimmune diseases, multiple sclerosis patients
Patients with immunodeficiency disorders
These concerns prompted me to write a posting curating the guidance from National Cancer Institute (NCI) designated cancer centers to cancer patients concerning their risk to COVID19 (which can be found here).
Surprisingly, there were only 14 of the 51 US NCI Cancer Centers which had posted guidance (either there own or from organizations like NCI or the National Cancer Coalition Network (NCCN). Most of the guidance to patients had stemmed from a paper written by Dr. Markham of the Fred Hutchinson Cancer Center in Seattle Washington, the first major US city which was impacted by COVID19.
Also I was surprised at the reactions to this posting, with patients and oncologists enthusiastic to discuss concerns around the coronavirus problem. This led to having additional contact with patients and oncologists who, as I was surprised, are not having these conversations with each other or are totally confused on courses of action during this pandemic. There was a true need for each party, both patients/caregivers and physicians/oncologists to be able to communicate with each other and disseminate good information.
Last night there was a Tweet conversation on Twitter #OTChat sponsored by @OncologyTimes. A few tweets are included below
The Lesson: Rapid Communication of Vital Information in times of stress is crucial in maintaining a good patient/physician relationship and preventing Misinformation.
3. Socio-geographical Inequalities in the US Healthcare System
It has become very clear that the US healthcare system is fractioned and multiple inequalities (based on race, sex, geography, socio-economic status, age) exist across the whole healthcare system. These inequalities are exacerbated in times of stress, especially when access to care is limited.
Some of the passengers had to be extricated from the wrecked cars. Many of the passengers and local residents helped first responders during the rescue operation. Five local hospitals treated the injured. The derailment disrupted train service for several days.
What was not reported was the difficulties that first responders, namely paramedics had in finding an emergency room capable of taking on the massive load of patients. In the years prior to this accident, several hospitals, due to monetary reasons, had to close their emergency rooms or reduce them in size. In addition only two in Philadelphia were capable of accepting gun shot victims (Temple University Hospital was the closest to the derailment but one of the emergency rooms which would accept gun shot victims. This was important as Temple University ER, being in North Philadelphia, is usually very busy on any given night. The stress to the local health system revealed how one disaster could easily overburden many hospitals.
Over the past decade many hospitals, especially rural hospitals, have been shuttered or consolidated into bigger health systems. The graphic below shows this
Note the huge swath of hospital closures in the midwest, especially in rural areas. This has become an ongoing problem as the health care system deals with rising costs.
Lesson:Epidemic Stresses an already stressed out US healthcare system
When tennis player Maria Sharapova recently revealed that she had tested positive for the banned drug meldonium, the reaction of most healthcare providers was, “What is it?”
Meldonium is manufactured and sold as Mildronate by the pharmaceutical company Grindeks in the Baltic nation of Latvia. Meldonium is not available in the United States or elsewhere in the European Union (it was grandfathered in Latvia) other than via purchase on the Internet.
The World Anti-Doping Agency classifies meldonium as a “metabolic modulator” and moved the drug from its watch list to its list of banned substances in January 2016.
Other “metabolic modulators” are insulin and trimetazidine, an anti-ischemic metabolic agent that increases myocardial glucose utilization through inhibition of fatty acid metabolism.[1,2] Trimetazidine is approved in the European Union for the treatment of angina, but it is not approved in the United States.
The chemical name for meldonium is trimethylhydrazinium propionate. Meldonium works by decreasing the availability of levocarnitine (L-carnitine). L-carnitine is found naturally in milk and meats, and also can be synthesized by the body from lysine and methionine with the help of gamma-butyrobetaine hydroxylase. L-carnitine helps move long-chain fatty acids into the mitochondria for oxidation and energy production in the muscles.
Ironically, L-carnitine, which meldonium inhibits, is taken as a dietary supplement alone and as an ingredient in energy drinks to increase athletic performance. (L-carnitine is available in the United States as the prescription drug Carnitor®, which is indicated for carnitine deficiency owing to inborn errors of metabolism and for end-stage renal disease requiring dialysis.) After two decades of research, no consistent evidence has emerged indicating that carnitine supplements can improve exercise or physical performance. Carnitine supplements do not appear to increase the body’s use of oxygen or improve metabolic status when exercising, and may not increase the amount of carnitine in muscle.[3,4]Carnitine is not on the list of banned substances.[1]
As a modulator of L-carnitine metabolism, meldonium inhibits gamma-butyrobetaine hydroxylase and L-carnitine transmembrane transport of long-chain fatty acids, thus decreasing L-carnitine levels in tissue and plasma. Reducing the amount of bioavailable L-carnitine shifts the source of metabolic energy production from fatty acid oxidation to glucose metabolism. Aerobic glucose oxidation consumes less oxygen than fatty acid oxidation and increases the effectiveness of adenosine triphosphate (ATP) generation. Additionally, meldonium appears to increase glucose uptake. In ischemic conditions (hypoxia), meldonium appears to restore the balance between cellular oxygen supply and demand, and prevents ATP transport impairment.[3,5]
All published clinical efficacy studies on meldonium, except one,[6] are in Russian. Abstracts of randomized controlled trials have reported the efficacy of meldonium in reducing angina, arrhythmias, and anxiety and other early sequelae of myocardial infarction[7-10]; as an “adaptogen” in patients with cardiovascular disease[11,12]; and in treating angina and reducing myocardial ischemia after percutaneous coronary intervention,[6,13,14] heart failure,[15] and diabetic peripheral neuropathy.[16] Doses, when included in the abstracts, ranged from 750 to 1000 mg per day. Only one abstract mentioned adverse effects, stating that none occurred.[7]
A pharmacokinetic study of meldonium showed that the drug has a dose-dependent half-life and volume of distribution with accumulation on multiple-dose administration. In eight healthy volunteers who received meldonium for 13 days, almost all reported insomnia, half reported burping, and one quarter reported “dreaminess.” No serious adverse effects were reported.[17]
A study in healthy, nonvegetarian volunteers receiving 1000 mg meldonium per day for 4 weeks showed that plasma concentrations of L-carnitine decreased by 18%. Urine samples showed an increase in L-carnitine excretion. Adverse effects were not mentioned.[18] Meldonium is excreted in the urine largely unchanged, making urine testing a valid monitor presence of meldonium.[19]
No long-term studies on the safety and efficacy of meldonium have been published. No studies on the effect of meldonium on athletic performance in humans have been published. One study on the reliability of urine testing in professional sports[19]mentions an article and an abstract, but neither of those appears in PubMed. The abstract purports to be a review of “recent studies on mildronate especially in fields associated with physical work capabilities and sport” but cites only the study mentioned in the urine testing review.[20] Most articles about meldonium cited on PubMed are by Latvian authors.
Animal research suggests the potential usefulness of meldonium in Alzheimer disease,[21-23] Parkinson disease,[24,25] and diabetes.[26-29] Meldonium increased sexual activity in boars[30] but not in male rats.[31] Research in rodents found that meldonium can cause carnitine deficiency in offspring, so the drug should not be taken in pregnancy.[32]
Because meldonium is excreted renally, serum levels may be higher in patients with reduced kidney function, and the drug may accumulate with repeated dosing.[19] L-carnitine appears to antagonize the effects of meldonium[33]; otherwise, drug interactions are not known.
To recap, meldonium is an interesting drug developed by Latvian researchers. Published research suggests that it may be an effective treatment for cardiovascular diseases, such as angina. Little information about its adverse effects has been published, however, and the long-term safety of meldonium is not known. And although reliable research on meldonium’s use for athletic performance is not available, the World Anti-Doping Agency has declared it a banned substance.
The late Cambridge Mayor Alfred Vellucci welcomed Life Sciences Labs to Cambridge, MA – June 1976
Reporter: Aviva Lev-Ari, PhD, RN
How Cambridge became the Life Sciences Capital
Worth watching is the video below, which captures the initial Cambridge City Council hearing on recombinant DNA research from June 1976. The first speaker is the late Cambridge mayor Alfred Vellucci.
Vellucci hoped to pass a two-year moratorium on gene splicing in Cambridge. Instead, the council passed a three-month moratorium, and created a board of nine Cambridge citizens — including a nun and a nurse — to explore whether the work should be allowed, and if so, what safeguards would be necessary. A few days after the board was created, the pro and con tables showed up at the Kendall Square marketplace.
At the time, says Phillip Sharp, an MIT professor, Cambridge felt like a manufacturing town that had seen better days. He recalls being surrounded by candy, textile, and leather factories. Sharp hosted the citizens review committee at MIT, explaining what the research scientists there planned to do. “I think we built a relationship,” he says.
By early 1977, the citizens committee had proposed a framework to ensure that any DNA-related experiments were done under fairly stringent safety controls, and Cambridge became the first city in the world to regulate research using genetic material.
Supreme Court reverses Zimmer win in $20m knee implant lawsuit
Reported by: Irina Robu, PhD
The Pennsylvania Supreme Court yesterday reversed a state appeals court’s decision to overturn a $20 million verdict against in a knee implant lawsuit. Margo Pollet had a double knee replacement procedure in 2006 using Zimmer’s Gender Solutions devices but after making a Zimmer promotional video which included riding a bicycle and running on treadmill, she claimed that it damaged her knees. She sued for negligence saying the injuries occured during filming the video. A jury awarded Polett millions in damages after finding that Zimmer was 34% culpable. The jury also put 30% of the blame on Polett herself and 36% on the marketing firm Public Communications for its involvement with the ad.
The Pennsylvania Superior Court last October ruled that the lower court incorrectly shifted the burden of proof onto Zimmer by asking the company to provide alternative explanations for Polett’s revisions surgeries, thus leading the jury to a potentially false conclusion, and ordered a new trial.
“In sum, the trial court’s ruling that Dr. Booth’s expert testimony as to causation was not barred by [Pennsylvania law] was amply supported by the evidence of record, and thus was reasonable. Consequently, we conclude that the trial court did not abuse its discretion in allowing Dr. Booth to render an expert opinion at trial, and that the Superior Court erred by reassessing the evidence relied upon by the trial court in making its ruling, and by supplanting the trial court’s findings with its own evaluation of that evidence. We, therefore, reverse the order of the Superior Court as to this issue,” McCloskey Todd wrote.
The Supreme Court ordered the Superior Court to review whether the trial court was wrong to deny the defendants’ bid to overturn the verdict.
pathway and network analysis of complex ‘omics data
Larry H. Bernstein, MD, FCAP, Curator
LPBI
While blood tests can be used to detect some cancers, the FDA said a San Diego company has no proof its blood test works in patients who have not already been diagnosed with some form of the disease.
WASHINGTON, Sept. 25 (UPI) — A San Diego company selling an early cancer detection test was notified by the U.S. Food and Drug Administration it can find no evidence the test actually works, and is concerned it could prove to be harmful for some people.
Pathway Genomics debuted its CancerIntercept test in early September with claims it can detect cancer cell DNA in the blood, picking up mutations linked to as many as 10 different cancers. The goal is to catch cancer early in people who are “otherwise healthy” and not showing symptoms of the disease.
“Based on our review of your promotional materials and the research publication cited above, we believe you are offering a high risk test that has not received adequate clinical validation and may harm the public health,” said FDA Deputy Director James L. Woods in a letter to the company.
CancerIntercept is billed by the company as a blood test looking for DNA fragments in the bloodstream and testing them for 96 genomic markers it says are found in several specific tumor types.
The direct-to-consumer test can be purchased through the Pathway Genomics website, with programs ranging from a one-time test to a quarterly “subscription” for people who want regular testing.
The company states, in several sections of its website, “the presence of one or more of these genomic markers in a patient’s bloodstream may indicate that the patient has a previously undetected cancer. However, the test is not diagnostic, and thus, follow-up screening and clinical testing would be required to confirm the presence or absence of a specific cancer in the patient.”
The FDA is concerned that people may seek treatment for tumors that do not require medical attention, or spend money and possibly seek out treatment they do not need at all — in either case, unnecessary treatment for cancer is potentially harmful to people, the agency said.
CancerIntercept has not been approved by the FDA for use as a medical device, nor has it been subjected to peer review as most tests of its type would be. The company published a white paper on its website which outlines how the test works, supporting its efficacy with references to several clinical trials on detection of mutated DNA in the bloodstream.
Glenn Braunstein, Chief Medical Officer at Pathway Genomics, told The VergePathway had validated its tests with “hundreds” of patients, though those patients had well-defined, often advanced cancers.
In the letter from the FDA, Woods requests the company provide a timeline for meeting with the agency to review plans for future longitudinal studies on the product and specific details on studies that have been conducted before it was made available to consumers.
The clinical laboratory is an essential player in the treatment of cancer providing a diagnostic, potentially a prognostic, and follow-up treatment armamentarium. The laboratory diagnostics industry has grown over the last half century into a highly accurate, well regulated industry with highly automated and point of care technologies. Prior to introduction, the tests that are put on the market have to be validated prior to introduction.
How are they validated?
The most common approach is for the test to be used concomitantly with treatment in a clinical trial. Measurements may be made prior to surgical biopsy and treatment, and at a month or 6 months to a year later. The pharmaceutical and diagnostics industries are independent, even though a large company may have both pharmaceutical and diagnostic divisions. Consequently, the integration of diagnostics and therapeutics occurs on the front lines of patient care.
How this discrepancy between the FDA and the manufacturer could occur is not clear because prior to introduction, the test would have to be rigorously reviewed by the American Association for Clinical Chemistry, the largest and most competent organization to cover the scientific work, having industry-based committees. The only problem is that the companies may have products that are patented and have competing claims or interests. This is perhaps most likely to be problematic in the competitive environment of genomics testing.
The company here reported on is Pathway Genomics, that offers Ingenuity for pathway and variant analysis. There is no concern about the analysis methods, that are well studied. The concern is the validation of such method for screening of patients without prior diagnosis.
Model, analyze, and understand the complex biological and chemical systems at the core of life science research with IPA
QIAGEN’S Ingenuity Pathway Analysis (IPA) has been broadly adopted by the life science research community and is cited in thousands of peer-reviewed journal articles.
For the analysis and interpretation of ’omics data
Market Leading Pathway Analysis
Unlock the insights buried in experimental data by quickly identifying relationships, mechanisms, functions, and pathways of relevance.
Predictive Causal Analytics
Powerful causal analytics at your fingertips help you to build a more complete regulatory picture and a better understanding of the biology underlying a given gene expression study.
NGS/RNA-Seq Data Analysis
Get a better understanding of the isoform-specific biology resulting from RNA-Seq experiments.
Identify causal variants from human sequencing data
Ingenuity Variant Analysis combines analytical tools and integrated content to help you rapidly identify and prioritize variants by drilling down to a small, targeted subset of compelling variants based both upon published biological evidence and your own knowledge of disease biology. With Variant Analysis, you can interrogate your variants from multiple biological perspectives, explore different biological hypotheses, and identify the most promising variants for follow-up.
Variant Analysis used in NCI-60 Interpretation of Genomic Variants
The NCI-60 Data Set offers tremendous promise in the development and prescription of cancer drugs
97% of surveyed researchers are satisfied with the ease of use of Ingenuity Variant Analysis and we are honored that they chose to share the data through our Publish tool.
“Being a bioinformatician, I appreciated the speed and the complexity of analysis. Without Variant Analysis, I couldn’t have completed the analysis of 700 exomes in such a short time …. I found Variant Analysis very intuitive and easy to use.”
Francesco Lescai, Senior Research Associate in Genome Analysis, University College of London.
This appears to be the new rocky road to verification for validity in diagnostic and treatment application.
The Vibrant Philly Biotech Scene: Focus on KannaLife Sciences and the Discipline and Potential of Pharmacognosy
Curator and Interviewer: Stephen J. Williams, Ph.D.
Article ID #167: The Vibrant Philly Biotech Scene: Focus on KannaLife Sciences and the Discipline and Potential of Pharmacognosy. Published on 2/19/2015
WordCloud Image Produced by Adam Tubman
This post is the third in a series of posts highlighting interviews with Philadelphia area biotech startup CEO’s and show how a vibrant biotech startup scene is evolving in the city as well as the Delaware Valley area. Philadelphia has been home to some of the nation’s oldest biotechs including Cephalon, Centocor, hundreds of spinouts from a multitude of universities as well as home of the first cloned animal (a frog), the first transgenic mouse, and Nobel laureates in the field of molecular biology and genetics. Although some recent disheartening news about the fall in rankings of Philadelphia as a biotech hub and recent remarks by CEO’s of former area companies has dominated the news, biotech incubators like the University City Science Center and Bucks County Biotechnology Center as well as a reinvigorated investment community (like PCCI and MABA) are bringing Philadelphia back. And although much work is needed to bring the Philadelphia area back to its former glory days (including political will at the state level) there are many bright spots such as the innovative young companies as outlined in these posts.
Below is the interview with Dr. Kinney and Mr. Kikis of KannaLife Sciences and Leaders in Pharmaceutical Business Intelligence (LPBI)
PA Biotech Questions answered by Dr. William Kinney, Chief Scientific Officer of KannaLife Sciences
LPBI: Your parent company is based in New York. Why did you choose the Bucks County Pennsylvania Biotechnology Center?
Dr. Kinney: The Bucks County Pennsylvania Biotechnology Center has several aspects that were attractive to us. They have a rich talent pool of pharmaceutically trained medicinal chemists, an NIH trained CNS pharmacologist, a scientific focus on liver disease, and a premier natural product collection.
LBPI: The Blumberg Institute and Natural Products Discovery Institute has acquired a massive phytochemical library. How does this resource benefit the present and future plans for KannaLife?
Dr. Kinney: KannaLife is actively mining this collection for new sources of neuroprotective agents and is in the process of characterizing the active components of a specific biologically active plant extract. Jason Clement of the NPDI has taken a lead on these scientific studies and is on our Advisory Board.
LPBI: Was the state of Pennsylvania and local industry groups support KannaLife’s move into the Doylestown incubator?
Dr. Kinney: The move was not State influenced by state or industry groups.
LPBI: Has the partnership with Ben Franklin Partners and the Center provided you with investment opportunities?
Dr. Kinney: Ben Franklin Partners has not yet been consulted as a source of capital.
LPBI: The discipline of pharmacognosy, although over a century old, has relied on individual investigators and mainly academic laboratories to make initial discoveries on medicinal uses of natural products. Although there have been many great successes (taxol, many antibiotics, glycosides, etc.) many big pharmaceutical companies have abandoned this strategy considering it a slow, innefective process. Given the access you have to the chemical library there at Buck County Technology Center, the potential you had identified with cannabanoids in diseases related to oxidative stress, how can KannaLife enhance the efficiency of finding therapeutic and potential preventive uses for natural products?
Dr. Kinney: KannaLife has the opportunity to improve upon natural molecules that have shown medically uses, but have limitations related to safety and bioavailability. By applying industry standard medicinal chemistry optimization and assay methods, progress is being made in improving upon nature. In addition KannaLife has access to one of the most commercially successful natural products scientists and collections in the industry.
LPBI: How does the clinical & regulatory experience in the Philadelphia area help a company like Kannalife?
Dr. Kinney: Within the region, KannaLife has access to professionals in all areas of drug development either by hiring displaced professionals or partnering with regional contract research organizations.
LPBI You are focusing on an interesting mechanism of action (oxidative stress) and find your direction appealing (find compounds to reverse this, determine relevant disease states {like HCE} then screen these compounds in those disease models {in hippocampal slices}). As oxidative stress is related to many diseases are you trying to develop your natural products as preventative strategies, even though those type of clinical trials usually require massive numbers of trial participants or are you looking to partner with a larger company to do this?
Dr. Kinney: Our strategy is to initially pursue Hepatic Encephalophy (HE) as the lead orphan disease indication and then partner with other organizations to broaden into other areas that would benefit from a neuroprotective agent. It is expected the HE will be responsive to an acute treatment regimen. We are pursuing both natural products and new chemical entities for this development path.
General Questions answered by Thoma Kikis, Founder/CMO of KannaLife Sciences
LPBI: How did KannaLife get the patent from the National Institutes of Health?
My name is Thoma Kikis I’m the co-founder of KannaLife Sciences. In 2010, my partner Dean Petkanas and I founded KannaLife and we set course applying for the exclusive license of the ‘507 patent held by the US Government Health and Human Services and National Institutes of Health (NIH). We spent close to 2 years working on acquiring an exclusive license from NIH to commercially develop Patent 6,630,507 “Cannabinoids as Antioxidants and Neuroprotectants.” In 2012, we were granted exclusivity from NIH to develop a treatment for a disease called Hepatic Encephalopathy (HE), a brain liver disease that stems from cirrhosis.
Cannabinoids are the chemicals that compose the Cannabis plant. There are over 85 known isolated Cannabinoids in Cannabis. The cannabis plant is a repository for chemicals, there are over 400 chemicals in the entire plant. We are currently working on non-psychoactive cannabinoids, cannabidiol being at the forefront.
As we started our work on HE and saw promising results in the area of neuroprotection we sought out another license from the NIH on the same patent to treat CTE (Chronic Traumatic Encephalopathy), in August of 2014 we were granted the additional license. CTE is a concussion related traumatic brain disease with long term effects mostly suffered by contact sports players including football, hockey, soccer, lacrosse, boxing and active military soldiers.
To date we are the only license holders of the US Government held patent on cannabinoids.
LPBI: How long has this project been going on?
We have been working on the overall project since 2010. We first started work on early research for CTE in early-2013.
LPBI: Tell me about the project. What are the goals?
Our focus has always been on treating diseases that effect the Brain. Currently we are looking for solutions in therapeutic agents designed to reduce oxidative stress, and act as immuno-modulators and neuroprotectants.
KannaLife has an overall commitment to discover and understand new phytochemicals. This diversification of scientific and commercial interests strongly indicates a balanced and thoughtful approach to our goals of providing standardized, safer and more effective medicines in a socially responsible way.
Currently our research has focused on the non-psychoactive cannabidiol (CBD). Exploring the appropriate uses and limitations and improving its safety and Metered Dosing. CBD has a limited therapeutic window and poor bioavailability upon oral dosing, making delivery of a consistent therapeutic dose challenging. We are also developing new CBD-like molecules to overcome these limitations and evaluating new phytochemicals from non-regulated plants.
KannaLife’s research is led by experienced pharmaceutically trained professionals; Our Scientific team out of the Pennsylvania Biotechnology Center is led by Dr. William Kinney and Dr. Douglas Brenneman both with decades of experience in pharmaceutical R&D.
LPBI: How do cannabinoids help neurological damage? -What sort of neurological damage do they help?
So far our pre-clinical results show that cannabidiol is a good candidate as a neuroprotectant as the patent attests to. Our current studies have been to protect neuronal cells from toxicity. For HE we have been looking specifically at ammonia and ethanol toxicity.
– How did it go from treating general neurological damage to treating CTE? Is there any proof yet that cannabinoids can help prevent CTE? What proof?
We started examining toxicity first with ammonia and ethanol in HE and then posed the question; If CBD is a neuroprotectant against toxicity then we need to examine what it can do for other toxins. We looked at CTE and the toxin that causes it, tau. We just acquired the license in August from the NIH for CTE and are beginning our pre-clinical work in the area of CTE now with Dr. Ron Tuma and Dr. Sara Jane Ward at Temple University in Philadelphia.
LPBI: How long until a treatment could be ready? What’s the timeline?
We will have research findings in the coming year. We plan on filing an IND (Investigational New Drug application) with the FDA for CBD and our molecules in 2015 for HE and file for CTE once our studies are done.
LPBI: What other groups are you working with regarding CTE?
We are getting good support from former NFL players who want solutions to the problem of concussions and CTE. This is a very frightening topic for many players, especially with the controversy and lawsuits surrounding it. I have personally spoken to several former NFL players, some who have CTE and many are frightened at what the future holds.
We enrolled a former player, Marvin Washington. Marvin was an 11 year NFL vet with NY Jets, SF 49ers and won a SuperBowl on the 1998 Denver Broncos. He has been leading the charge on KannaLife’s behalf to raise awareness to the potential solution for CTE.
We tried approaching the NFL in 2013 but they didn’t want to meet. I can understand that they don’t want to take a position. But ultimately, they’re going to have to make a decision and look into different research to treat concussions. They have already given the NIH $30 Million for research into football related injuries and we hold a license with the NIH, so we wanted to have a discussion. But currently cannabinoids are part of their substance abuse policy connected to marijuana. Our message to the NFL is that they need to lead the science, not follow it.
Can you imagine the NFL’s stance on marijuana treating concussions and CTE? These are topics they don’t want to touch but will have to at some point.
LPBI: Thank you both Dr. Kinney and Mr. Kikis.
Please look for future posts in this series on the Philly Biotech Scene on this site
Also, if you would like your Philadelphia biotech startup to be highlighted in this series please contact me or
Why did this occur? The matter of Individual Actions Undermining Trust, The Patent Dilemma and The Value of a Clinical Trials
Reporter and Curator: Larry H. Bernstein, MD, FCAP
he large amount of funding tied to continued research and support of postdoctoral fellows leads one to ask how following the money can lead to discredited work in th elite scientific community.
Moreover, the pressure to publish in prestigious journals with high impact factors is a road to academic promotion. In the last twenty years, it is unusual to find submissions for review with less than 6-8 authors, with the statement that all contributed to the work. These factors can’t be discounted outright, but it is easy for work to fall through the cracks when a key investigator has over 200 publications and holds tenure in a great research environment. But that is where we find ourselves today.
There is another issue that comes up, which is also related to the issue of carrying out research, and then protecting the work for commercialization. It is more complicated in the sense that it is necessary to determine whether there is prior art, and then there is the possibility that after the cost of filing patent and a 6 year delay in obtaining protection, there is as great a cost in bringing the patent to finasl production.
I. Individual actions undermining trust.
II. The patent dilemma.
III. The value of a clinical trial.
IV. The value contributions of RAP physicians
(radiologists, anesthesiologists, and pathologists – the last for discussion)
Those who maintain and inform the integrity of medical and surgical decisions
Science 18 July 2014: Vol. 345 no. 6194 p. 254 DOI: 10.1126/science.345.6194.25
In the study of cardiac regeneration, Piero Anversa is among the heavy hitters. His research into the heart’s repair mechanisms helped kick-start the field of cardiac cell therapy (see main story). After more than 4 decades of research and 350 papers, he heads a lab at Harvard Medical School’s Brigham and Women’s Hospital (BWH) in Boston that has more than $6 million in active grant funding from the National Institutes of Health (NIH). He is also an outspoken voice in a field full of disagreement.
So when an ongoing BWH investigation of the lab came to light earlier this year, Anversa’s colleagues were transfixed. “Reactions in the field run the gamut from disbelief to vindication,” says Mark Sussman, a cardiovascular researcher at San Diego State University in California who has collaborated with Anversa. By Sussman’s account, Anversa’s reputation for “pushing the envelope” and “challenging existing dogma” has generated some criticism. Others, however, say that the disputes run deeper—to doubts about a cell therapy his lab has developed and about the group’s scientific integrity. Anversa told Science he was unable to comment during the investigation.
“People are talking about this all the time—at every scientific meeting I go to,” says Charles Murry, a cardiovascular pathologist at the University of Washington, Seattle. “It’s of grave concern to people in the field, but it’s been frustrating,” because no information is available about BWH’s investigation. BWH would not comment for this article, other than to say that it addresses concerns about its researchers confidentially.
In April, however, the journal Circulation agreed to Harvard’s request to retract a 2012 paper on which Anversa is a corresponding author, citing “compromised” data. The Lancet also issued an “Expression of Concern” about a 2011 paper reporting results from a clinical trial, known as SCIPIO, on which Anversa collaborated. According to a notice from the journal, two supplemental figures are at issue.
For some, Anversa’s status has earned him the benefit of the doubt. “Obviously, this is very disconcerting,” says Timothy Kamp, a cardiologist at the University of Wisconsin, Madison, but “I would be surprised if it was an implication of a whole career of research.”
Throughout that career, Anversa has argued that the heart is a prolific, lifelong factory for new muscle cells. Most now accept the view that the adult heart can regenerate muscle, but many have sparred with Anversa over his high estimates for the rate of this turnover, which he maintained in the retracted Circulation paper.
Anversa’s group also pioneered a method of separating cells with potential regenerative abilities from other cardiac tissue based on the presence of a protein called c-kit. After publishing evidence that these cardiac c-kit+cells spur new muscle growth in rodent hearts, the group collaborated in the SCIPIO trial to inject them into patients with heart failure. In The Lancet, the scientists reported that the therapy was safe and showed modest ability to strengthen the heart—evidence that many found intriguing and provocative. Roberto Bolli, the cardiologist whose group at the University of Louisville in Kentucky ran the SCIPIO trial, plans to test c-kit+ cells in further clinical trials as part of the NIH-funded Cardiovascular Cell Therapy Research Network.
But others have been unable to reproduce the dramatic effects Anversa saw in animals, and some have questioned whether these cells really have stem cell–like properties. In May, a group led by Jeffery Molkentin, a molecular biologist at Cincinnati Children’s Hospital Medical Center in Ohio, published a paper in Nature tracing the genetic lineage of c-kit+ cells that reside in the heart. He concluded that although they did make new muscle cells, the number is “astonishingly low” and likely not enough to contribute to the repair of damaged hearts. Still, Molkentin says that he “believe[s] in their therapeutic potential” and that he and Anversa have discussed collaborating.
Now, an anonymous blogger claims that problems in the Anversa lab go beyond controversial findings. In a letter published on the blog Retraction Watch on 30 May, a former research fellow in the Anversa lab described a lab culture focused on protecting the c-kit+ cell hypothesis: “[A]ll data that did not point to the ‘truth’ of the hypothesis were considered wrong,” the person wrote. But another former lab member offers a different perspective. “I had a great experience,” says Federica Limana, a cardiovascular disease researcher at IRCCS San Raffaele Pisana in Rome who spent 2 years of her Ph.D. work with the group in 1999 and 2000, as it was beginning to investigate c-kit+ cells. “In that period, there was no such pressure” to produce any particular result, she says.
Accusations about the lab’s integrity, combined with continued silence from BWH, are deeply troubling for scientists who have staked their research on theories that Anversa helped pioneer. Some have criticized BWH for requesting retractions in the midst of an investigation. “Scientific reputations and careers hang in the balance,” Sussman says, “so everyone should wait until all facts are clearly and fully disclosed.”
II. Trolling Along: Recent Commotion About Patent Trolls
July 17, 2014
PriceWaterhouseCoopers recently released a study about 2014 Patent Litigation. PwC’s ultimate conclusion was that case volume increased vastly and damages continue a general decline, but what’s making headlines everywhere is that “patent trolls” now account for 67% of all new patent lawsuits (see, e.g., Washington Post and Fast Company).
Surprisingly, looking at PwC’s study, the word “troll” is not to be found. So, with regard to patent trolls, what does this study really mean for companies, patent owners and casual onlookers?
First of all, who are these trolls?
“Patent Troll” is a label applied to patent owners who do not make or manufacture a product, or offer a service. Patent trolls live (and die) by suing others for allegedly practicing an invention that is claimed by their patents.
The politically correct term is Non-practicing Entity (NPE). PwC solely uses the term NPE, which it defines as an entity that does not have the capability to design, manufacture, or distribute products with features protected by the patent.
So, what’s so bad about them?
The common impression of an NPEs is a business venture looking to collect and monetize assets (i.e., patents). In the most basic strategy, an NPE typically buys patents with broad claims that cover a wide variety of technologies and markets, and then sues a large group of alleged patent infringers in the hope to collect a licensing royalty or a settlement. NPEs typically don’t want to spend money on a trial unless they have to, and one tactic uses settlements with smaller businesses to build a “war chest” for potential suits with larger companies.
NPEs initiating a lawsuit can be viewed positively, such as a just defense of the lowly inventor who sold his patent to someone (with deeper pockets) who could fund the litigation to protect the inventor’s hard work against a mega-conglomerate who ripped off his idea.
Or NPE litigation can be seen negatively, such as an attorney’s demand letter on behalf of an anonymous shell corporation to shake down dozens of five-figure settlements from all the local small businesses that have ever used a fax machine.
NPEs can waste a company’s valuable time and resources with lawsuits, yet also bring value to their patent portfolios by energizing a patent sales and licensing market. There are unscrupulous NPEs, but it’s hardly the black and white situation that some media outlets are depicting.
What did PwC say about trolls?
Well, the PwC study looked at the success rates and awards of patent litigation decisions. One conclusion is that damages awards for NPEs averaged more than triple those for practicing entities over the last four years. We’ll come back to this statistic.
Another key observation is that NPEs have been successful 25% of the time overall, versus 35% for practicing entities. This makes sense because of the burden of proof the NPEs carry as a plaintiff at trial and the relative lack of success for NPEs at summary judgment. However, PwC’s report states that both types of entities win about two-thirds of their trials.
But what about this “67% of all patent trials are initiated by trolls” discussion?
The 67% number comes from the RPX Corporation’s litigation report (produced January 2014) that quantified the percentage of NPE cases filed in 2013 as 67%, compared to 64% in 2012, 47% in 2011, 30% in 2010 and 28% in 2009.
PwC refers to the RPX statistics to accentuate that this new study indicates that only 20% ofdecisions in 2013 involved NPE-filed cases, so the general conclusion would be that NPE cases tend to settle or be dismissed prior to a court’s decision. Admittedly, this is indicative of the prevalent “spray and pray” strategy where NPEs prefer to collect many settlement checks from several “targets” and avoid the courtroom.
In this study, who else is an NPE?
If someone were looking to dramatize the role of “trolls,” the name can be thrown around liberally (and hurtfully) to anyone who owns and asserts a patent without offering a product or a service. For instance, colleges and universities fall under the NPE umbrella as their research and development often ends with a series of published papers rather than a marketable product on an assembly line.
In fact, PwC distinguishes universities and non-profits from companies and individuals within their NPE analysis, with only about 5% of the NPE cases from 1995 to 2013 being attributed to universities and non-profits. Almost 50% of the NPE cases are attributed to an “individual,” who could be the listed inventor for the patent or a third-party assignee.
The word “troll” is obviously a derogatory term used to connote greed and hiding (under a bridge), but the term has adopted a newer, meme-like status as trolls are currently depicted as lacking any contribution to society and merely living off of others’ misfortunes and fears. [Three Billy Goats Gruff]. This is not always the truth with NPEs (e.g., universities).
No one wants to be called a troll—especially in front of a jury—so we’ve even recently seen courts bar defendants from referring to NPEs as such colorful terms as a “corporate shell,” “bounty hunter,” “privateer,” or someone “playing the lawsuit lottery.” [Judge Koh Bans Use Of Term ” Patent Troll” In Apple Jury Trial]
Regardless of the portrayal of an NPE, most people in the patent world distinguish the “trolls” by the strength of the patent, merits of the alleged infringement and their behavior upon notification. Often these are expressed as “frivolity” of the case and “gamesmanship” of the attorneys. Courts are able to punish plaintiffs who bring frivolous claims against a party and state bar associations are tasked with monitoring the ethics of attorneys. The USPTO is tasked with working to strengthen the quality of patents.
What’s the take-away from this study regarding NPEs?
The study focuses on patent litigation that produced a decision, therefore the most important and relevant conclusion is that, over the last four years, average damages awards for NPEs are more than triple the damages for practicing entities. Everything else in these articles, such as the initiation of litigation by NPEs, settlement percentages, and the general behavior of patent trolls is pure inference beyond the scope of the study.
This may sound sympathetic to trolls, but keep in mind that the study highlights that NPEs have more than triple the damages on average compared to practicing entities and it is meant to shock the reader a bit. One explanation for this is that NPEs are in the best position to choose the patents they want to assert and choose the targets they wish to sue—especially when the NPE is willing to ride that patent all the way to the end of a long, expensive trial. Sometimes settling is not an option. Chart 2b indicates that the disparity in the damages awarded to NPEs relative to practicing entities has always been big (since 2000), but perhaps going from two-fold from 2000 – 2009 to three times as much in the past 4 years indicates that NPEs are improving at finding patents and/or picking battles to take all the way to a court decision. More than anything, this seems to reflect the growth in the concept of patents as a business asset.
The PwC report is chock full of interesting patterns and trends of litigation results, so it’s a shame that the 67% number makes the headlines—far more interesting are the charts comparing success rates by 4-year periods (Chart 6b) or success rates for NPEs and practicing entities in front of a jury verusin front of a bench (Chart 6c), as well as other tables that reveal statistics for specific districts of the federal courts. Even the stats that look at the success rates of each type of NPE are telling because the reader sees that universities and non-profits have a higher success rate than non-practicing companies or individuals.
What do we do about the trolls?
The White House has recently called for Congress to do something about the trolls as horror stories of scams and shake-downs are shared. A bill was gaining momentum in the Senate, when Senator Leahy took it off the agenda in early July. That bill had miraculously passed 325-91 in the House and President Obama was willing to sign it if the Senate were to pass it. The bill was opposed by trial attorneys, universities, and bio-pharmaceutical businesses who felt as though the law would severely inhibit everyone’s access to the courts in order to hinder just the trolls. Regardless, most people think that the sitting Congressmen merely wanted a “win” prior to the mid-term elections and that patent reform is unlikely to reappear until next term.
In the meantime, the Supreme Court has recently reiterated rules concerning attorney fee-shifting on frivolous patent cases, as well as clarifying the validity of software patents. Time will tell if these changes have any effects on the damages awards that PwC’s study examined or even if they cause a chilling of the number of patent lawsuit filings.
Furthermore, new ways to challenge the validity of asserted patents have been initiated via the America Invents Act. For example, the Inter Partes Review (IPR) has yielded frightening preliminary statistics as to slowing, if not killing, patents that have been asserted in a suit. While these administrative trials are not cheap, many view these new tools at the Patent Trial and Appeals Board as anti-troll measures. It will be interesting to watch how the USPTO implements these procedures in the near future, especially while former Google counsel, Acting Director Michelle K. Lee, oversees the office.
In the private sector, Silicon Valley has recently seen a handful of tech companies come together as the License on Transfer Network, a group hoping to disarm the “Patent Assertion Entities.” Joining the LOT Network comes via an agreement that creates a license for use of a patent by anyone in the LOT network once that patent is sold. The thought is that the NPEs who consider purchasing patents from companies in the LOT Network will have fewer companies to sue since the license to the other active LOT participants will have triggered upon the transfer and, thus, the NPE will not be as inclined to “troll.” For instance, if a member-company such as Google were to sell a patent to a non-member company and an NPE bought that patent, the NPE would not be able to sue any members of the LOT Network with that patent.
Other notes
NPEs are only as evil as the people who run them—that being said, there are plenty of horror stories of small businesses receiving phantom demand letters that threaten a patent infringement suit without identifying themselves or the patent. This is an out-and-out scam and a plague on society that results in wasted time and resource, and inevitably higher prices on the consumer end.
It is a sin and a shame that patent rights can be misused in scams and shake-downs of businesses around us, but there is a reason that U.S. courts are so often used to defend patent rights. The PwC study, at minimum, reflects the high stakes of the patent market and perhaps the fragility. Nevertheless, merely monitoring the courts may not keep the trolls at bay.
I’d love to hear your thoughts.
*This is provided for informational purposes only, and does not constitute legal or financial advice. The information expressed is subject to change at any time and should be checked for completeness, accuracy and current applicability. For advice, consult a suitably licensed attorney or patent agent.
III. Large-scale analysis finds majority of clinical trials don’t provide meaningful evidence
DURHAM, N.C.— The largest comprehensive analysis of ClinicalTrials.gov finds that clinical trials are falling short of producing high-quality evidence needed to guide medical decision-making. The analysis, published today in JAMA, found the majority of clinical trials is small, and there are significant differences among methodical approaches, including randomizing, blinding and the use of data monitoring committees.
“Our analysis raises questions about the best methods for generating evidence, as well as the capacity of the clinical trials enterprise to supply sufficient amounts of high quality evidence to ensure confidence in guideline recommendations,” said Robert Califf, M.D., first author of the paper, vice chancellor for clinical research at Duke University Medical Center, and director of the Duke Translational Medicine Institute.
The analysis was conducted by the Clinical Trials Transformation Initiative (CTTI), a public private partnership founded by the Food and Drug Administration (FDA) and Duke. It extends the usability of the data in ClinicalTrials.gov for research by placing the data through September 27, 2010 into a database structured to facilitate aggregate analysis. This publically accessible database facilitates the assessment of the clinical trials enterprise in a more comprehensive manner than ever before and enables the identification of trends by study type.
The National Library of Medicine (NLM), a part of the National Institutes of Health, developed and manages ClinicalTrials.gov. This site maintains a registry of past, current, and planned clinical research studies.
“Since 2007, the Food and Drug Administration Amendment Act has required registration of clinical trials, and the expanded scope and rigor of trial registration policies internationally is producing more complete data from around the world,” stated Deborah Zarin, MD, director, ClinicalTrials.gov, and assistant director for clinical research projects, NLM. “We have amassed over 120,000 registered clinical trials. This rich repository of data has a lot to say about the national and international research portfolio.”
This CTTI project was a collaborative effort by informaticians, statisticians and project managers from NLM, FDA and Duke. CTTI comprises more than 60 member organizations with the goal of identifying practices that will improve the quality and efficiency of clinical trials.
“Since the ClinicalTrials.gov registry contains studies sponsored by multiple entities, including government, industry, foundations and universities, CTTI leaders recognized that it might be a valuable source for benchmarking the state of the clinical trials enterprise,” stated Judith Kramer, MD, executive director of CTTI.
The project goal was to produce an easily accessible database incorporating advances in informatics to permit a detailed characterization of the body of clinical research and facilitate analysis of groups of studies by therapeutic areas, by type of sponsor, by number of participants and by many other parameters.
“Analysis of the entire portfolio will enable the many entities in the clinical trials enterprise to examine their practices in comparison with others,” says Califf. “For example, 96% of clinical trials have ≤1000 participants, and 62% have ≤ 100. While there are many excellent small clinical trials, these studies will not be able to inform patients, doctors and consumers about the choices they must make to prevent and treat disease.”
The analysis showed heterogeneity in median trial size, with cardiovascular trials tending to be twice as large as those in oncology and trials in mental health falling in the middle. It also showed major differences in the use of randomization, blinding, and data monitoring committees, critical issues often used to judge the quality of evidence for medical decisions in clinical practice guidelines and systematic overviews.
“These results reinforce the importance of exploration, analysis and inspection of our clinical trials enterprise,” said Rachel Behrman Sherman, MD, associate director for the Office of Medical Policy at the FDA’s Center for Drug Evaluation and Research. “Generation of this evidence will contribute to our understanding of the number of studies in different phases of research, the therapeutic areas, and ways we can improve data collection about clinical trials, eventually improving the quality of clinical trials.”
Eighty-nine members of Congress have asked the Centers for Medicare & Medicaid Services to give pathologists a break and extend the hardship exemption they currently enjoy for all of Stage 3 of the Meaningful Use program.In the letter–dated July 10 and addressed to CMS Administrator Marilyn Tavenner–the lawmakers point out that CMS had recognized in its 2012 final rule implementing Stage 2 of the program that it was difficult for pathologists to meet the Meaningful Use requirements and granted a one year exception for 2015, the first year that penalties will be imposed. They now are asking that the exception be expanded to include the full five-year maximum allowed under the American Recovery and Reinvestment Act.
“Pathologists have limited direct contact with patients and do not operate in EHRs,” the letter states. “Instead, pathologists use sophisticated computerized laboratory information systems (LISs) to support the work of analyzing patient specimens and generating test results. These LISs exchange laboratory and pathology data with EHRs.”
Interestingly, the lawmakers’ exemption request is only on behalf of pathologists, even though CMS had granted the one-year hardship exception to pathologists, radiologists and anesthesiologists.
However, CMS also noted in the 2012 rule granting the one-year exception that it was granting the exception in large part because of the then-current lack of health information exchange and that “physicians in these three specialties should not expect that this exception will continue indefinitely, nor should they expect that we will grant the exception for the full 5-year period permitted by statute.”



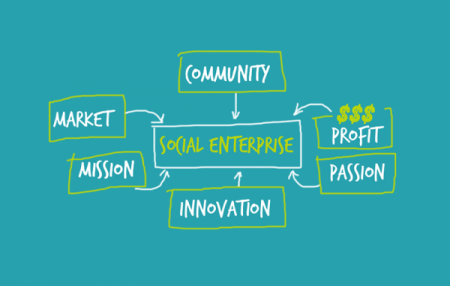
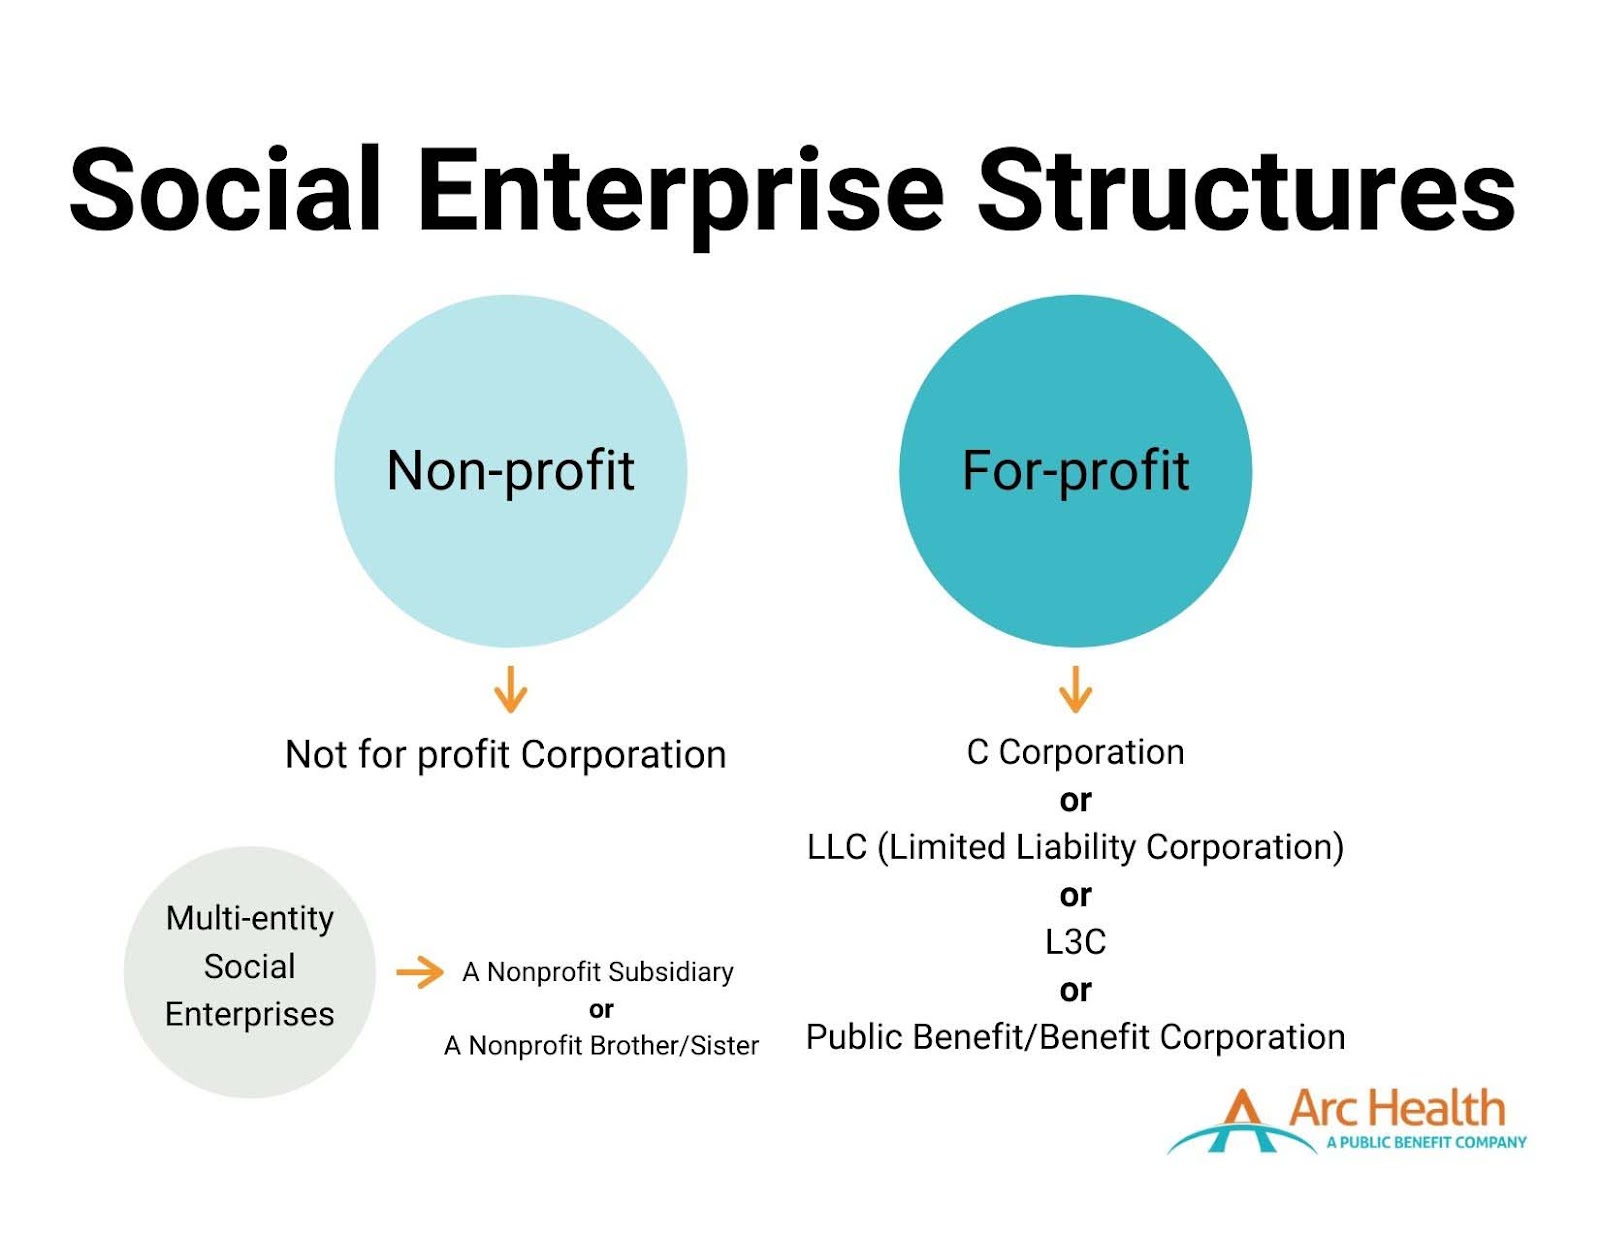



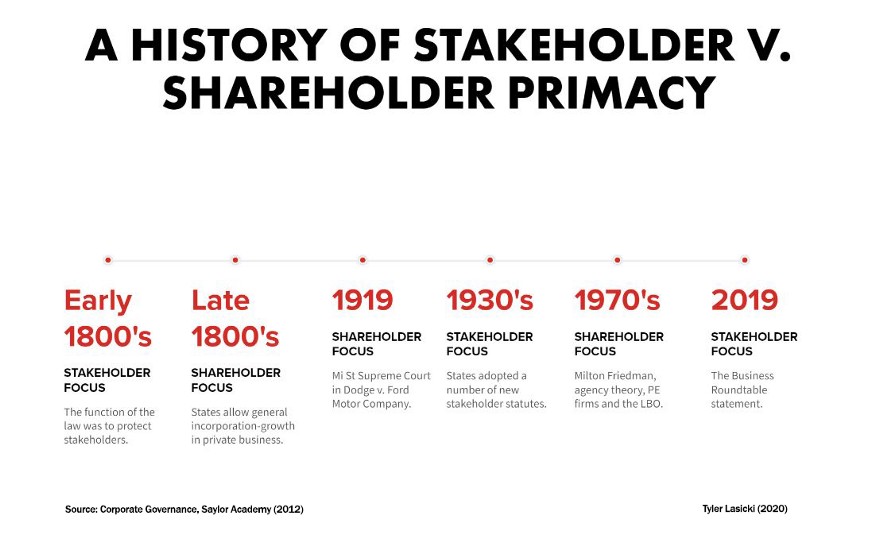




 2012pharmaceutical
 sjwilliamspa
