Feeds:
Posts
Comments

Archive for the ‘Proteomics’ Category

Brain Biobank and studies of disease structure correlates

Larry H. Bernstein, MD, FCAP, Curator

LPBI


Unveiling Psychiatric Diseases

Researchers create neuropsychiatric cellular biobank

Image: iStock/mstroz
Researchers from Harvard Medical School and Massachusetts General Hospital have completed the first stage of an important collaboration aimed at understanding the intricate variables of neuropsychiatric disease—something that currently eludes clinicians and scientists.

The research team, led by Isaac Kohane at HMS and Roy Perlis at Mass General, has created a neuropsychiatric cellular biobank—one of the largest in the world.

It contains induced pluripotent stem cells, or iPSCs, derived from skin cells taken from 100 people with neuropsychiatric diseases such as schizophrenia, bipolar disorder and major depression, and from 50 people without neuropsychiatric illness.

In addition, a detailed profile of each patient, obtained from hours of in-person assessment as well as from electronic medical records, is matched to each cell sample.

As a result, the scientific community can now for the first time access cells representing a broad swath of neuropsychiatric illness. This enables researchers to correlate molecular data with clinical information in areas such as variability of drug reactions between patients. The ultimate goal is to help treat, with greater precision, conditions that often elude effective management.

The cell collection and generation was led by investigators at Mass General, who in collaboration with Kohane and his team are working to characterize the cell lines at a molecular level. The cell repository, funded by the National Institutes of Health, is housed at Rutgers University.

“This biobank, in its current form, is only the beginning,” said Perlis, director of the MGH Psychiatry Center for Experimental Drugs and Diagnostics and HMS associate professor of psychiatry. “By next year we’ll have cells from a total of four hundred patients, with additional clinical detail and additional cell types that we will share with investigators.”

A current major limitation to understanding brain diseases is the inability to access brain biopsies on living patients. As a result, researchers typically study blood cells from patients or examine post-mortem tissue. This is in stark contrast with diseases such as cancer, for which there are many existing repositories of highly characterized cells from patients.

The new biobank offers a way to push beyond this limitation.


A Big Step Forward

While the biobank is already a boon to the scientific community, researchers at MGH and the HMS Department of Biomedical Informatics will be adding additional layers of molecular data to all of the cell samples. This information will include whole genome sequencing and transcriptomic and epigenetic profiling of brain cells made from the stem cell lines.

Collaborators in the HMS Department of Neurobiology, led by Michael Greenberg, department chair and Nathan Marsh Pusey Professor of Neurobiology,  will also work to examine characteristics of other types of neurons derived from these stem cells.

“This can potentially alter the entire way we look at and diagnose many neuropsychiatric conditions,” said Perlis.

One example may be to understand how the cellular responses to medication correspond to the patient’s documented responses, comparing in vitro with in vivo. “This would be a big step forward in bringing precision medicine to psychiatry,” Perlis said.

“It’s important to recall that in the field of genomics, we didn’t find interesting connections to disease until we had large enough samples to really investigate these complex conditions,” said Kohane, chair of the HMS Department of Biomedical Informatics.

“Our hypothesis is that here we will require far fewer patients,” he said. “By measuring the molecular functioning of the cells of each patient rather than only their genetic risk, and combining that all that’s known of these people in terms of treatment response and cognitive function, we will discover a great deal of valuable information about these conditions.”

Added Perlis, “In the early days of genetics, there were frequent false positives because we were studying so few people. We’re hoping to avoid the same problem in making cellular models, by ensuring that we have a sufficient number of cell lines to be confident in reporting differences between patient groups.”

The generation of stem cell lines and characterization of patients and brain cell lines is funded jointly by the the National Institute of Mental Health, the National Human Genome Research Institute and a grant from the Centers of Excellence in Genomic Science program.


On C.T.E. and Athletes, Science Remains in Its Infancy

Se Hoon Choi, Young Hye Kim, Matthias Hebisch, et al.

http://www.nature.com/articles/nature13800.epdf

Alzheimer’s disease is the most common form of dementia, characterized by two pathological hallmarks: amyloid-β plaques and neurofibrillary tangles1. The amyloid hypothesis of Alzheimer’s disease posits that the excessive accumulation of amyloid-β peptide leads to neurofibrillary tangles composed of aggregated hyperphosphorylated tau2, 3. However, to date, no single disease model has serially linked these two pathological events using human neuronal cells. Mouse models with familial Alzheimer’s disease (FAD) mutations exhibit amyloid-β-induced synaptic and memory deficits but they do not fully recapitulate other key pathological events of Alzheimer’s disease, including distinct neurofibrillary tangle pathology4, 5. Human neurons derived from Alzheimer’s disease patients have shown elevated levels of toxic amyloid-β species and phosphorylated tau but did not demonstrate amyloid-β plaques or neurofibrillary tangles6, 7, 8, 9, 10, 11. Here we report that FAD mutations in β-amyloid precursor protein and presenilin 1 are able to induce robust extracellular deposition of amyloid-β, including amyloid-β plaques, in a human neural stem-cell-derived three-dimensional (3D) culture system. More importantly, the 3D-differentiated neuronal cells expressing FAD mutations exhibited high levels of detergent-resistant, silver-positive aggregates of phosphorylated tau in the soma and neurites, as well as filamentous tau, as detected by immunoelectron microscopy. Inhibition of amyloid-β generation with β- or γ-secretase inhibitors not only decreased amyloid-β pathology, but also attenuated tauopathy. We also found that glycogen synthase kinase 3 (GSK3) regulated amyloid-β-mediated tau phosphorylation. We have successfully recapitulated amyloid-β and tau pathology in a single 3D human neural cell culture system. Our unique strategy for recapitulating Alzheimer’s disease pathology in a 3D neural cell culture model should also serve to facilitate the development of more precise human neural cell models of other neurodegenerative disorders.


Figure 2: Robust increases of extracellular amyloid-β deposits in 3D-differentiated hNPCs with FAD mutations.close

Robust increases of extracellular amyloid-[bgr] deposits in 3D-differentiated hNPCs with FAD mutations.

a, Thin-layer 3D culture protocol. HC, histochemistry; IF, immunofluorescence; IHC, immunohistochemistry. b, Amyloid-β deposits in 6-week differentiated control and FAD ReN cells in 3D Matrigel (green, GFP; blue, 3D6; scale bar, …


Stem Cell-Based Spinal Cord Repair Enables Robust Corticospinal Regeneration


Novel use of EPR spectroscopy to study in vivo protein structure

http://www.news-medical.net/whitepaper/20160315/Novel-use-of-EPR-spectroscopy-to-study-in-vivo-protein-structure.aspx

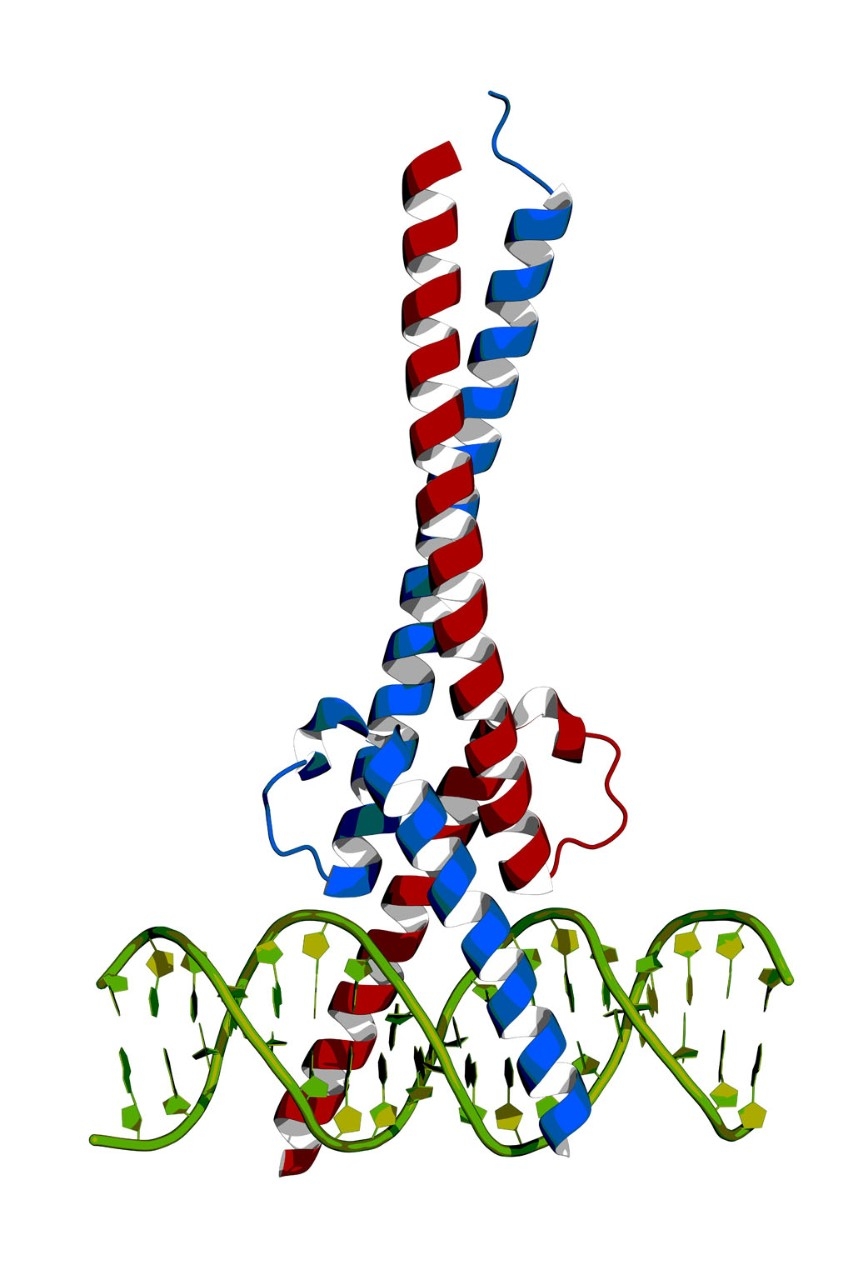
α-synuclein

α-synuclein is a protein found abundantly throughout the brain. It is present mainly at the neuron ends where it is thought to play a role in ensuring the supply of synaptic vesicles in presynaptic terminals, which are required for the release of neurotransmitters to relay signals between neurons. It is critical for normal brain function.

However, α-synuclein is also the primary protein component of the cerebral amyloid deposits characteristic of Parkinson’s disease and its precursor is found in the amyloid plaques of Alzheimer’s disease. Although α-synuclein is present in all areas of the brain, these disease-state amyloid plaques only arise in distinct areas.

Alpha-synuclein protein. May play role in Parkinson’s and Alzheimer’s disease.  © molekuul.be / Shutterstock.com

Imaging of isolated samples of α-synuclein in vitro indicate that it does not have the precise 3D folded structure usually associated with proteins. It is therefore classed as an intrinsically disordered protein. However, it was not known whether the protein also lacked a precise structure in vivo.

There have been reports that it can form helical tetramers. Since the 3D structure of a biological protein is usually precisely matched to the specific function it performs, knowing the structure of α-synuclein within a living cell will help elucidate its role and may also improve understanding of the disease states with which it is associated.

If α-synuclein remains disordered in vivo, it may be possible for the protein to achieve different structures, and have different properties, depending on its surroundings.

Techniques for determining protein structure

It has long been known that elucidating the structure of a protein at an atomic level is fundamental for understanding its normal function and behavior. Furthermore, such knowledge can also facilitate the development of targeted drug treatments. Unfortunately, observing the atomic structure of a protein in vivo is not straightforward.

X-ray diffraction is the technique usually adopted for visualizing structures at atomic resolution, but this requires crystals of the molecule to be produced and this cannot be done without separating the molecules of interest from their natural environment. Such processes can modify the protein from its usual state and, particularly with complex structures, such effects are difficult to predict.

The development of nuclear magnetic resonance (NMR) spectroscopy improved the situation by making it possible for molecules to be analyzed under in vivo conditions, i.e. same pH, temperature and ionic concentration.

More recently, increases in the sensitivity of NMR and the use of isotope labelling have enabled determinations of the atomic level structure and dynamics of proteins to be determined within living cells1. NMR has been used to determine the structure of a bacterial protein within living cells2 but it is difficult to achieve sufficient quantities of the required protein within mammalian cells and to keep the cells alive for NMR imaging to be conducted.

Electron paramagnetic resonance (EPR) spectroscopy for determining protein structure

Recently, researchers have managed to overcome these obstacles by using in-cell NMR and electron paramagnetic resonance (EPR) spectroscopy. EPR spectroscopy is a technique that is similar to NMR spectroscopy in that it is based on the measurement and interpretation of the energy differences between excited and relaxed molecular states.

In EPR spectroscopy it is electrons that are excited, whereas in NMR signals are created through the spinning of atomic nuclei. EPR was developed to measure radicals and metal complexes, but has also been utilized to study the dynamic organization of lipids in biological membranes3.

EPR has now been used for the first time in protein structure investigations and has provided atomic-resolution information on the structure of α-synuclein in living mammalians4,5.

Bacterial forms of the α-synuclein protein labelled with 15N isotopes were introduced into five types of mammalian cell using electroporation. Concentrations of α-synuclein close to those found in vivo were achieved and the 15N isotopes allowed the protein to be clearly defined from other cellular components by NMR. The conformation of the protein was then determined using electron paramagnetic resonance (EPR).

The results showed that within living mammalian cells α-synuclein remains as a disordered and highly dynamic monomer. Different intracellular environments did not induce major conformational changes.

Summary

The novel use of EPR spectroscopy has resolved the mystery surrounding the in vivo conformation of α-synuclein. It showed that α-synuclein maintains its disordered monomeric form under physiological cell conditions. It has been demonstrated for the first time that even in crowded intracellular environments α-synuclein does not form oligomers, showing that intrinsic structural disorder can be sustained within mammalian cells.

References

  1. Freedberg DI and Selenko P. Live cell NMR Annu. Rev. Biophys. 2014;43:171–192.
  2. Sakakibara D, et al. Protein structure determination in living cells by in-cell NMR spectroscopy. Nature 2009;458:102–105.
  3. Yashroy RC. Magnetic resonance studies of dynamic organisation of lipids in chloroplast membranes. Journal of Biosciences 1990;15(4):281.
  4. Alderson TA and Bax AD. Parkinson’s Disease. Disorder in the court. Nature 2016; doi:10.1038/nature16871.
  5. Theillet FX, et al. Structural disorder of monomeric α-synuclein persists in mammalian cells. Nature 2016; doi:10.1038/nature16531.


Read Full Post »

Water Absorption Effects on Amino Acids Structure

Author: Danut Dragoi, PhD

Biological process utilize amino acids almost uniquely one chiral form or the other. In terrestrial biology, only the L-amino acids is common in biological processes. If signature of life existed elsewhere in the D form it then be concluded that life had evolutionary beginning on that body. Detection of an enantiomeric excess of L over D would also be a powerful sign that life had existed on that body at one time, see link in here .

As we know powder XRD pattern of both the L- or D-amino acids are basically identical. This is primarily due to the fact that the chirality of the amino acids does not favor a specific orientation on the sample holder in the powder form. However, when the amino acids are crystallized in moisture environment, water molecule enters in the unit cell of the amino acid by changing its structure. In order to determine structural changes using x-ray diffraction, two samples of both L- and D-phenylalanine (min 98% and >99% purity, respectively; purchased from Sigma Aldrich Co. St. Louis Mo) directly on the x-ray sample holder, alumina single crystal (0001) face, see link in here. The picture below shows an example of the diffraction pattern for two specimens of D- and L- phenylalanine, fresh crystallized in pure water under the same conditions.

L and D Phenilalanine-XRD

Image SOURCE: http://webapp1.dlib.indiana.edu/virtual_disk_library/index.cgi/1185879/FID1164/ABSTRACTS/1401-1800/1682.pdf.

As we see from the picture above, the two peaks L and D do not have same position. For raw phenylalanine D and L enantiomers the laboratory x-ray diffraction pattern matches, despite the fact that Powder Diffraction File (PDF) that correspond to PDF# 11-0827 for D form and PDF# 37-1771 indicates detectable differences. This is due to a structure factor, which is invariant for both D and L forms. For fresh crystallized specimens of D and L forms, a difference can be distinguished. The diffraction peak D of D-Phenylalanine has a less d-spacing suggesting a more compact structure than L-Phenylalanine.

Comparing diffraction pattern for the entire range produced by L and D crystallized Phenylalanine in pure water, shifts occur in peak position and intensity. These differences are possibly due to stereo-specific interactions of D- and L- phenylalanine molecules with water molecules. The x-ray diffraction pattern for D and L form, a small part shown in the picture above, reflects new structural configurations such as rotation, slight deformation and/or translation of the phenylalanine molecule inside the unit cell. It is possible that D form crystallizes with more molecules of water than L form. Structural solution for freshly crystallized phenylalanine can be found using Rietveld refinement technique.

The implications of water effect on the structure of the amino acids can lead to similar effects on DNA structure as well as proteins and cells in human body.

SOURCE

http://webapp1.dlib.indiana.edu/virtual_disk_library/index.cgi/1185879/FID1164/ABSTRACTS/1401-1800/1682.pdf.

Read Full Post »

Best in Precision Medicine: RNA May Surpass DNA in Precision Medicine

Curator: Larry H. Bernstein, MD, FCAP

2.1.5.21

2.1.5.21   Best in Precision Medicine: RNA May Surpass DNA in Precision Medicine, Volume 2 (Volume Two: Latest in Genomics Methodologies for Therapeutics: Gene Editing, NGS and BioInformatics, Simulations and the Genome Ontology), Part 2: CRISPR for Gene Editing and DNA Repair

  • “A more complicated application of CRISPR technology is to use it for gene activation,” adds Dr. Tedesco. “Cellecta plans to optimize this application to bring forth highly efficient, inexpensive, high-throughput genetic screens based on their pooled libraries.

RNA May Surpass DNA in Precision Medicine

http://www.genengnews.com/gen-news-highlights/rna-may-surpass-dna-in-precision-medicine/81252507/

http://www.genengnews.com/Media/images/GENHighlight/thumb_Mar22_2016_Rgocs_RNASeqAlignment1872484040.jpg

Scientists based at the Translational Genomics Research Institute have published a review heralding the promise of RNA sequencing (RNA-seq) for precision medicine. The scientists also note that progress will be needed on analytical, bioinformatics, and regulatory fronts, particularly in light of the transcriptome’s variety, dynamism, and wealth of detail. In this image, one aspect of RNA-seq is shown, the alignment with intron-split short reads. It reflects the alignment of mRNA sequence obtained via high-throughput sequencing and the expected behavior of the alignment to the reference genome when the read falls in an exon–exon junction. [Rgocs, Wikipedia]

It’s not an either/or situation. Both DNA sequencing and RNA sequencing hold clinical promise—diagnostically, prognostically, and therapeutically. It must be said, however, that RNA sequencing reflects the dynamic nature of gene expression, shifting with the vagaries of health and disease. Also, RNA sequencing captures more biochemical complexity, in the sense that it allows for the detection of a wide variety of RNA species, including mRNA, noncoding RNA, pathogen RNA, chimeric gene fusions, transcript isoforms, and splice variants, and provides the capability to quantify known, predefined RNA species and rare RNA transcript variants within a sample.

All these potential advantages were cited in a paper that appeared March 21 in Nature Reviews Genetics, in an article entitled, “Translating RNA Sequencing into Clinical Diagnostics: Opportunities and Challenges.” The paper, contributed by scientists based at the Translational Genomics Research Institute (TGen), was definitely optimistic about the clinical utility of RNA sequencing, but it also highlighted the advances that would have to occur if RNA sequencing is to achieve its promise.

In general, the very things that make RNA sequencing so interesting are the same things that make it so challenging. RNA sequencing would take the measure of a world—the transcriptome—that is incredibly rich. To capture all the relevant subtleties of the transcriptome, scientists will have to develop sensitive, precise, and trustworthy analytical techniques. What’s more, scientists will need to find efficient and reliable means of processing and interpreting all of the transcriptome data they will collect. Finally, they will need to continue integrating RNA-based knowledge with DNA-based knowledge. That is, RNA sequencing results can be used to guide the interpretation of DNA sequencing results.

In their Nature Reviews Genetics paper, the TGen scientists review the state of RNA sequencing and offer specific recommendations to enhance its clinical utility. The TGen scientists make a special point about the promise held by extracellular RNA (exRNA). Because exRNA can be monitored by simply taking a blood sample, as opposed to taking a tumor biopsy, it could serve as a noninvasive diagnostic indicator of disease.

“Detection of gene fusions and differential expression of known disease-causing transcripts by RNA-seq represent some of the most immediate opportunities,” wrote the authors. “However, it is the diversity of RNA species detected through RNA-seq that holds new promise for the multi-faceted clinical applicability of RNA-based measures, including the potential of extracellular RNAs as non-invasive diagnostic indicators of disease.”

The first test measuring exRNA was released earlier this year, the paper said, for use measuring specific exRNAs in lung cancer patients. And, the potential for using RNA-seq in cancer is expanding rapidly. Commercial RNA-seq tests are now available, and they provide the opportunity for clinicians to profile cancer more comprehensively and use this information to guide treatment selection for their patients.

In addition, the authors reported on several recent applications for RNA-seq in the diagnosis and management of infectious diseases, such as monitoring for drug-resistant populations during therapy and tracking the origin and spread of the Ebola virus.

Despite these advances, the authors also sounded a few cautionary notes. “There are currently few agreed upon methods for isolation or quantitative measurements and a current lack of quality controls that can be used to test platform accuracy and sample preparation quality,” they wrote. “Analytical, bioinformatics, and regulatory challenges exist, and ongoing efforts toward the establishment of benchmark standards, assay optimization for clinical conditions and demonstration of assay reproducibility are required to expand the clinical utility of RNA-seq.”

Overall, the authors remain hopeful that precision medicine will embrace RNA sequencing. For example, lead author Sara Byron, research assistant professor in TGen’s Center for Translational Innovation, said, “RNA is a dynamic and diverse biomolecule with an essential role in numerous biological processes. From a molecular diagnostic standpoint, RNA-based measurements have the potential for broad application across diverse areas of human health, including disease diagnosis, prognosis, and therapeutic selection.”

Gene Editing Casts a Wide Net   

With CRISPR, Gene Editing Can Trawl the Murk, Catching Elusive Phenotypes amidst the Epigenetic Ebb and Flow

http://www.genengnews.com/gen-articles/gene-editing-casts-a-wide-net/5713/

http://www.genengnews.com/Media/images/Article/thumb_Marusina_iStock_52289586_GeneticCodeDNA1830871003.jpg

Gene-editing advances will not only open new avenues toward curing genetic diseases but will also rapidly increase the pace of new scientific discoveries about human and other types of genomes. [iStock/adventtr]

  • Genome editing, a much-desired means of accomplishing gene knockout, gene activation, and other tasks, once seemed just beyond the reach of most research scientists and drug developers. But that was before the advent of CRISPR technology, an easy, versatile, and dependable means of implementing genetic modifications. It is in the process of democratizing genome editing.

    CRISPR stands for “clustered, regularly interspaced, short palindromic repeats,” segments of DNA that occur naturally in many types of bacteria. These segments function as part of an ancient immune system. Each segment precedes “spacer DNA,” a short base sequence that is derived from a fragment of foreign DNA. Spacers serve as reminders of past encounters with phages or plasmids.

    The CRISPR-based immune system encompasses several mechanisms, including one in which CRISPR loci are transcribed into small RNAs that may complex with a nuclease called CRISPR-associated protein (Cas). Then the RNA guides Cas, which cleaves invading DNA on the basis of sequence complementarity.

    In the laboratory, CRISPR sequences are combined with a short RNA complementary to a target gene site. The result is a complex in which the RNA guides Cas to a preselected target.

    Cas produces precise site-specific DNA breaks, which, with imperfect repair, cause gene mutagenesis. In more recent applications, Cas can serve as an anchor for other proteins, such as transcriptional factors and epigenetic enzymes. This system, it seems, has almost limitless versatility.

  • Edited Stem Cells

    The Sanger Institute Mouse Genetic Program, along with other academic institutions around the world, provides access to thousands of genetically modified mouse strains. “Genetic engineering of mouse embryonic stem (ES) cells by homologous recombination is a powerful technique that has been around since the 1980s,” says William Skarnes, Ph.D., senior group leader at the Wellcome Trust Sanger Institute.

    “A significant drawback of the ES technology is the time required to achieve a germline transmission of the modified genetic locus,” he continues. “While we have an exhaustive collection of modified ES cells, only about 5,000 knockout mice, or a quarter of mouse genome, were derived on the basis of this methodology.”

    The dominant position of the mouse ES cell engineering is now effectively challenged by the CRISPR technology. Compared with very low rates of homologous recombination in fertilized eggs, CRISPR generates high levels of mutations, and off-target effects may be so few as to be undetectable.

    “We used the whole-genome sequencing to thoroughly assess off-target mutations in the offspring of CRISPR-engineered founder animals,” informs Dr. Skarnes. “A mutated Cas9 nuclease was deployed to increase specificity, resulting in nearly perfect targeting.”

    Dr. Skarnes explains that the major mouse genome centers are now switching to CRISPR to complete the creation of the world-wide repository of mouse knockouts. His own research is now focused on genetically engineered induced pluripotent stem cells (iPSCs). These cells are adult cells that have been reprogrammed to an embryonic stem cell–like state, and are thus devoid of ethical issues associated with research on human embryonic stem cells. The ultimate goal is to establish a world-wide panel of reference iPSCs created by high-throughput genetic editing of every single human gene.

    “We are poised to begin a large-scale phenotypic analysis of human genes,” declares Dr. Skarnes. His lab is releasing the first set of functional data on 100 DNA repair genes. “By knocking out individual proteins involved in DNA repair and sequencing the genomes of mutant cells,” declares Dr. Skarnes, “we hope to better understand the mutational signatures that occur in cancer.”

  • Pooled CRISPR Libraries

    Researchers hope to gain a better understanding of the mutational signatures found in cancers by using CRISPR techniques to knock out individual proteins involved in DNA repair and then sequencing the genomes of mutant cells. [iStock/zmeel]

    Connecting a phenotype to the underlying genomics requires an unbiased screening of multiple genes at once. “Pooled CRISPR libraries provide an opportunity to cast a wide net at a reasonably low cost,” says Donato Tedesco, Ph.D., lead research scientist at Cellecta. “Screening one gene at a time on genome scale is a significant investment of time and money that not everyone can afford, especially when looking for common genetic drivers across many cell models.”

    Building on years of experience with shRNA libraries, Cellecta is uniquely positioned to prepare pooled CRISPR libraries for genome-wide or targeted screens of gene families. While shRNA interferes with gene translation, CRISPR disrupts a gene and the genomic level due to imperfections in the DNA repair mechanism.

    To determine if these different mechanisms for inactivating genes affect the results of genetic screens, the team conducted a side-by-side comparison of Cellecta’s Human Genome-Wide Module 1 shRNA Library, which expresses 50,000 shRNA targeting 6,300 human genes, with the library of 50,000 gRNA targeting the same gene set. The concordance between approaches was very high, suggesting that these technologies may be complementary and used for cross-confirmation of results.

    Also, a recently completed Phase I NIH SBIR Grant was used to create and test guiding strand RNA (sgRNA) structures to drastically improve efficiency of gene targeting. For this work, Cellecta used a pool library strategy to simultaneously test multiple sgRNA structures for their efficiency and specificity. An early customized Cellecta pooled gRNA library was successfully utilized for screening for epigenetic genes. This particular screen is highly dependent on a complete loss of function, and could not have been accomplished by shRNA inhibition.

    Scientists from Epizyme interrogated 600 genes in a panel of 100 cell lines and, in addition to finding many epigenetic genes required for proliferation in nearly all cell lines, were able to identify validate several essential epigenetic genes required only in subsets of cells with specific genetic lesions. In other words, pooled cell line screening was able to distinguish targets that are likely to produce toxic side effects in certain types of cancer cells from gene targets that are essential in most cells.

    “A more complicated application of CRISPR technology is to use it for gene activation,” adds Dr. Tedesco. “Cellecta plans to optimize this application to bring forth highly efficient, inexpensive, high-throughput genetic screens based on their pooled libraries.

  • Chemically Modified sgRNA

    Scientists based at Agilent Research Laboratories and Stanford University worked together to demonstrate that chemically modified single guide RNA can be used to enhance the genome editing of primary hepatopoietic stem cells and T cells. This image, which is from the Stanford laboratory of Matthew Porteus, M.D., Ph.D., shows CD34+ human hematopoietic stem cells that were edited to turn green. Editing involved inserting a construct for green fluorescent protein. About 1,000 cells are pictured here.

    Researchers at Agilent Technologies applied their considerable experience in DNA and RNA synthesis to develop a novel chemical synthesis method that can generate long RNAs of 100 nucleotides or more, such as single guide RNAs (sgRNAs) for CRISPR genome editing. “We have used this capability to design and test numerous chemical modifications at different positions of the RNA molecule,” said Laurakay Bruhn, Ph.D., section manager, biological chemistry, Agilent.

    Agilent Research Laboratories worked closely with the laboratory of Matthew Porteus, M.D., Ph.D., an associate professor of pediatrics and stem cell transplantation at Stanford University. The Agilent and Stanford researchers collaborated to further explore the benefits of chemically modified sgRNAs in genome editing of primary hematopoetic stem cells and T cells.

    Dr. Porteus’ lab chose three key target genes implicated in the development of severe combined immunodeficiency (SCID), sickle cell anemia, and HIV transmission. Editing these genes in the patient-derived cells offers an opportunity for novel precision therapies, as the edited cells can renew, expand, and colonize the donor’s bone marrow.

    Dr. Bruhn emphasized the importance of editing specificity, so that no other cellular function is affected by the change. The collaborators focused on three chemical modifications strategically placed at each end of sgRNAs that Agilent had previously tested to show they maintained sgRNA function. A number of other optimization strategies in cell culturing and transfection were explored to ensure high editing yields.

    “Primary cells are difficult to manipulate and edit in comparison with cell lines already adapted to cell culture,” maintains Dr. Bruhn. Widely varied cellular properties of primary cells may require experimental adaptation of editing techniques for each primary cell type.

    The resulting data showed that chemical modifications can greatly enhance efficiency of gene editing. The next step would translate these findings into animal models. Another advantage of chemical synthesis of RNA is that it can potentially be used to make large enough quantities for therapeutics.

    “We are working with Agilent’s Nucleic Acid Solution Division—a business focused on GMP manufacturing of oligonucleotides for therapeutics—to engage with customers interested in this capability and better understand how we might be able to help them accomplish their goals,” says Dr. Bruhn.

  • Customized Animal Models

    “Given their gene-knockout capabilities, zinc-finger-based technologies and CRISPR-based technologies opened the doors for creation of animal models that more closely resemble human disease than mouse models,” says Myung Shin, Ph.D., senior principal scientist, Merck & Co. Dr. Shin’s team supports Merck’s drug discovery and development program by creating animal models mimicking human genetics.

    For example, Dr. Shin’s team has worked with the Dahl salt-sensitive strain of rats, a widely studied model of hypertension. “We used zinc-finger nucleases to generate a homozygous knockout of a renal outer medullary potassium channel (ROMK) gene,” elaborates Dr. Shin. “The resulting model represents a major advance in elucidating the role of ROMK gene.”

    According to Dr. Shin, the model may also provide a bridge between genetics and physiology, particularly in studies of renal regulation and blood pressure. In one study, the model generated animal data that suggest ROMK plays a key role in kidney development and sodium absorption. Work along these lines may lead to a pharmacological strategy to manage hypertension.

    In another study, the team applied zinc-finger nuclease strategy to knockout the coagulation Factor XII, and thoroughly characterize them in thrombosis and hemostasis studies. Results confirmed and extended previous literature findings suggesting Factor XII as a potential target for antithrombotic therapies that carry minimal bleeding risk. The model can be further utilized to study safety profiles and off-target effects of such novel Factor XII inhibitors.

    “We use one-cell embryos to conduct genome editing with zinc-fingers and CRISPR,” continues Dr. Shin. “The ease of this genetic manipulation speeds up generation of animal models for testing of various hypotheses.”

    A zinc finger–generated knockout of the multidrug resistance protein MDR 1a P-glycoprotein became an invaluable tool for evaluating drug candidates for targets located in the central nervous system. For example, it demonstrated utility in pharmacological analyses.

    Dr. Shin’s future research is directed toward preclinical animal models that would contain specific nucleotide changes corresponding to those of humans. “CRISPR technology,” insists Dr. Shin, “brings an unprecedented power to manipulate genome at the level of a single nucleotide, to create gain- or loss-of-function genetic alterations, and to deeply understand the biology of a disease.”

  • Transcriptionally Active dCas9

    “Epigenome editing is important for several reasons,” says Charles Gersbach, Ph.D., an associate professor of biomedical engineering at Duke University. “It is a tool that helps us answer fundamental questions about biology. It advances disease modeling and drug screening. And it may, in the future, serve as mode of genetic therapy.”

    “One part of our research focuses on studying the function of epigenetic marks,” Dr. Gersback continues. “While many of these marks are catalogued, and some have been associated with the certain gene-expression states, the exact causal link between these marks and their effect on gene expression is not known. CRISPR technology can potentially allow for targeted direct manipulation of each epigenetic mark, one at a time.”

    Dr. Gersback’s team mutated the Cas9 nuclease to create deactivated Cas9 (dCas9), which is devoid of endonuclease activity. Although the dCas9 protein lacks catalytic activity, it may still serve as an anchor for a plethora of other important proteins, such as transcription factors and methyltransferases.

    In an elegant study, Dr. Gersbach and colleagues demonstrated that recruitment of a histone acetyltransferase by dCas9 to a genomic site activates nearby gene expression. Moreover, the activation occurred even when the acetyltransferase domain was targeted to a distal enhancer. Similarly, recruitment of KRAB repressor to a distant site silenced the target gene in a very specific manner. These findings support the important role of three-dimensional chromatin structures in gene activation.

    “Genome regulation by epigenetic markers is not static,” maintains Dr. Gersbach. “It responds to changes in the environment and other stimuli. It also changes during cell differentiation. We designed an inducible system providing us with an ability to execute dynamic control over the target genes.”

    In a light-activated CRISPR-Cas9 effector (LACE) system, blue light may be used to control the recruitment of the transcriptional factor VP64 to target DNA sequences. The system has been used to provide robust activation of four target genes with only minimal background activity. Selective illumination of culture plates created a pattern of gene expression in a population of cells, which could be used to mimic what is observed in natural tissues.

    Together with collaborators at Duke University, Dr. Gersbach intends to carry out the high-throughput analysis of all currently identified regulatory elements in the genome. “Our ultimate goal,” he declares, “is to assign function to all of these elements.”

Read Full Post »

The late Cambridge Mayor Alfred Vellucci welcomed Life Sciences Labs to Cambridge, MA – June 1976

Reporter: Aviva Lev-Ari, PhD, RN

How Cambridge became the Life Sciences Capital

Worth watching is the video below, which captures the initial Cambridge City Council hearing on recombinant DNA research from June 1976. The first speaker is the late Cambridge mayor Alfred Vellucci.

Vellucci hoped to pass a two-year moratorium on gene splicing in Cambridge. Instead, the council passed a three-month moratorium, and created a board of nine Cambridge citizens — including a nun and a nurse — to explore whether the work should be allowed, and if so, what safeguards would be necessary. A few days after the board was created, the pro and con tables showed up at the Kendall Square marketplace.

At the time, says Phillip Sharp, an MIT professor, Cambridge felt like a manufacturing town that had seen better days. He recalls being surrounded by candy, textile, and leather factories. Sharp hosted the citizens review committee at MIT, explaining what the research scientists there planned to do. “I think we built a relationship,” he says.

By early 1977, the citizens committee had proposed a framework to ensure that any DNA-related experiments were done under fairly stringent safety controls, and Cambridge became the first city in the world to regulate research using genetic material.


WATCH VIDEO

http://www.betaboston.com/news/2016/03/17/how-cambridge-became-the-life-sciences-capital/

Scott Kirsner can be reached at kirsner@pobox.com. Follow him on Twitter@ScottKirsner and on betaboston.com.

SOURCE

How Cambridge became the life sciences capital

http://www.betaboston.com/news/2016/03/17/how-cambridge-became-the-life-sciences-capital/

Read Full Post »

Deciphering Mode of Action of Functionally Important Regions

Larry H. Bernstein, MD, FCAP, Curator

LPBI


Deciphering Mode of Action of Functionally Important Regions in the Intrinsically Disordered Paxillin (Residues 1-313) Using Its Interaction with FAT (Focal Adhesion Targeting Domain of Focal Adhesion Kinase)

Intrinsically disordered proteins (IDPs) play a major role in various cellular functions ranging from transcription to cell migration. Mutations/modifications in such IDPs are shown to be associated with various diseases. Current strategies to study the mode of action and regulatory mechanisms of disordered proteins at the structural level are time consuming and challenging. Therefore, using simple and swift strategies for identifying functionally important regions in unstructured segments and understanding their underlying mechanisms is critical for many applications. Here we propose a simple strategy that employs dissection of human paxillin (residues 1–313) that comprises intrinsically disordered regions, followed by its interaction study using FAT (Focal adhesion targeting domain of focal adhesion kinase) as its binding partner to retrace structural behavior. Our findings show that the paxillin interaction with FAT exhibits a masking and unmasking effect by a putative intra-molecular regulatory region. This phenomenon suggests how cancer associated mutations in paxillin affect its interactions with Focal Adhesion Kinase (FAK). The strategy could be used to decipher the mode of regulations and identify functionally relevant constructs for other studies.
Neerathilingam M, Bairy SG, Mysore S (2016) Deciphering Mode of Action of Functionally Important Regions in the Intrinsically Disordered Paxillin (Residues 1-313) Using Its Interaction with FAT (Focal Adhesion Targeting Domain of Focal Adhesion Kinase). PLoS ONE 11(2): e0150153. doi:10.1371/journal.pone.0150153

Genomic data suggests that a large proportion of eukaryotic proteins appear to adopt disordered structures in physiological conditions [1, 2]. Mutations/modifications in such IDPs are shown to be associated with various diseases (like cancer) [3]; therefore, understanding their structural behavior is critical for various applications like drug-targeting, mapping protein interactions, deciphering mode of action and finding functional relevance. However, deciphering mode of action in IDPs has been challenging given that unstructured segments render poor chemical shift dispersions and electron density in major techniques like NMR and X-ray, respectively [4]. For example, it took almost 10 years to decipher the mode of action of Sic1, a disordered protein involved in inhibition of a cyclin-dependent kinase [5]. One way to map and study the functional regions is to make truncated constructs by dissecting the whole construct rationally. A limited number of dissection constructs are usually generated; this is due to the time-consuming and challenging process of generating soluble and functionally relevant constructs when studies are performed in-vivo and constructs are prepared and tested sequentially. Here we present a simple high throughput (HTP) screening strategy (Fig 1a), which focuses on finding functionally relevant regions in IDPs based upon its interaction with a binding partner. Close to thirty dissection constructs of the IDP were generated and studied in parallel to understand the importance and functionality of the various regions of the protein. We perform cell-free expression followed by solubility check and GST pull-down interaction study in HTP format. Though both cell-free expression and GST pull-down assay have been individually performed in HTP format [6, 7], we did not find previous studies that combine the two methods in HTP format. Although the nature of interaction of IDPs with respective binding partners may vary, our strategy may be used to derive crucial insights into “structural behavior” of the unstructured segments in modulating the interaction. The strategy can also be used to identify functionally important regions in the IDP that would be suitable for further structural studies.

thumbnail

Fig 1. Dissection of paxillin constructs (residues 1–313) followed by expression and interaction studies.

(a) Timeline for overall-strategy. (b) Illustration of solubility and activity level of linear dissected human paxillin (residues 1–313). (c) Phosphor screen image of filter assay for optimization of temperature for paxillin constructs (left). Tabular representation of paxillin constructs, negative and positive controls corresponding to each well in filter assay [1].(d) Phosphor screen image of 10% SDS PAGE of 35S labeled cell-free expressed samples after GST pull-down assay of the paxillin constructs A1–E1; The right panel shows fraction of interaction of each construct with respect to B2 (since B2 showed maximum level of interaction) (e) Illustration of solubility and activity of dissected C3 constructs. All experiments were performed in triplicates and averaged. To rule out non-specific interactions that might occur with GST tagged FAT, GFP that was expressed in cell-free system and a reaction without DNA template were used as negative controls.    http://dx.doi.org:/10.1371/journal.pone.0150153.g001

Disorder/Intrinsic disorder seems to be a common feature of hub proteins in eukaryotes [2], thus highlighting the need for studying the mode of action of unstructured segments in such proteins. Here we used paxillin (residues 1–313), an intrinsically disordered construct, for demonstrating this approach. Paxillin (residues 1–313) consists of multiple protein interaction sites that are connected by flexible disordered sequences [8]. The disordered regions in paxillin have been detrimental in efforts to study the complete structure of the protein due to the demerits mentioned previously. This explains the lack of structural details of regulation of paxillin binding. Residues 1–313 of paxillin consist of five leucine-rich sequences LD1-LD5 (with consensus sequence: LDXLLXXL), termed LD motifs, which are highly conserved between species and other family members such as Hic-5, leupaxin and PAXB [8]. Paxillin interacts with multiple proteins involved in cell migration, actin rearrangements and cell proliferation [9]. Mutations in paxillin are shown to be associated with lung cancer [3, 10]; and the differential expression of paxillin is associated with various forms of cancer and other diseases such as Alzheimer’s and inflammation [11–13]. This implies the importance of studying the structural and functional characteristics of paxillin. Most paxillin studies focus on interactions of LD motifs with proteins such as focal adhesion kinase (FAK), vinculin and v-crk, providing clues towards their importance in deciphering the functionality of paxillin [8, 14, 15]. Though regions of paxillin that bind to various partners were deciphered through previous studies, the basis of effect of mutations in paxillin on binding its partners was not explained. Mutations in paxillin, some that were observed to be associated with cancer were positioned in the intrinsically disordered regions between the LD motifs and not on the motifs themselves [3, 10]. For example, P30S, G105A and A127T mutations lie between LD1 and LD2 motif; P233L and T255I mutations lie between LD3 and LD4 motifs. This shows that the LD motifs alone do not govern the functionality, but unstructured regions linking the LD motifs could play a major role. In normal conditions, FAT (Focal adhesion targeting domain of FAK) binds hydrophobically through its HP1 (Hydrophobic patch 1) and HP2 (Hydrophobic patch 2) sites to paxillin LD motifs—LD2 and LD4 [16, 17], which lead to activation of binding sites for other proteins on paxillin. LD2 preferentially binds to the HP2 site, whereas LD4 preferentially binds to the HP1 site [18]. In a state of cancer caused by mutations in paxillin, the LD interactions could be hindered, as mutations in the unstructured segments result in abnormal binding of FAK to either of the LD motifs [9]. Here we wanted to locate the region involved in the structural modulation of paxillin-FAT interaction by adopting a simple approach (Fig 1) that involves dissected proteins generated using cell-free protein expression coupled with protein-protein interaction study. We map the disordered proteins’ structural importance to understand the function and modulation of paxillin-FAT interaction in days rather than months (Fig 1a).

Dissection and identification of fragments of paxillin (residues 1–313) with functional relevance

We dissected paxillin (residues 1–313) (Fig 1b) into nested sets using PCR such that each of the constructs had either or both LD2 and LD4 motifs (S1 Fig and S1 Table). Further, these constructs were expressed in soluble form using small-scale cell-free expression system in a 96 well format (Fig 1c). However, all constructs except A6, B6, C4 and C5 expressed detectable amounts of protein (S2a Fig and S2 Table). The failure in expression of the above constructs could be due to the instability of the smaller peptide fragments that might be susceptible to proteolytic cleavage [19]. Soluble protein from small-scale expression of the dissected constructs namely A1, A2, A3, A4, A5, B1, B2, B3, B4, B5, C1, C2, C3, D1, D2, and E1 were pulled down and analysed (Fig 1d). Although constructs A1–A5, B1–B5, C1, C2, D1 and E1 interacted successfully, C3 (containing LD2) and D2 (containing LD4) failed to interact (Fig 2c) despite containing LD motifs. However, based on previous reports [8, 16, 17], we expected all constructs containing either LD2 and/or LD4 to interact with the FAT domain. Therefore, this led us to suspect that intra-molecular auto-inhibition in unstructured segments modulated binding of FAT to LD motifs in paxillin.

thumbnail

Fig 2. Regulatory and masking regions around paxillin’s LD2 and LD4 and their circular dichroism spectra.

(a) CD spectra of paxillin LD peptides (LD1-LD5) and constructs: B2, C3, C35 and D2. CD spectra of LD2, LD4, C35 and D2 constructs showed negative bands at 222nm and 206nm and a positive band at 192nm that confirms the presence of alpha helical content thus may behave as folded effector binding sites. However, LD1, LD3, LD5, B2 and C3 do not show the characteristic peaks of secondary structures, thus may behave as unfolded effector binding sites. (b) LD2 regulatory region (54–130) and masking region (167–224) evidenced by constructs B3, B4 and B5. (c) LD4 regulatory region (216–257) and masking region (280–313) evidenced by constructs D1, D2 and E1.
http://dx.doi.org:/10.1371/journal.pone.0150153.g002

Identification of regulatory regions and their mechanisms

To investigate the non-interaction of C3, a series of C3 deleted constructs (C31 –C310) (Fig 1e,S1 Table) were generated to determine the internal region that influenced the non-functioning of C3. C36 linear template could not be amplified for expression. As solubility of C3 could play a critical role in determining interaction, the homogeneity of the sample was confirmed by capillary electrophoresis under non-reducing conditions [20] (See S3 Fig). The linear templates—C31, C32, C33, C34 and C35 were successfully expressed in soluble form, The other C3 deleted constructs did not express due to issues related to small size as described earlier. Surprisingly, none of the C3 deleted constructs interacted with FAT despite the presence of the LD2 motif, although constructs such as B3, B4 and B5 that contain regions overlapping with C3 showed interaction (S2b and S2c Fig, Fig 1d and 1e). Here B3 that included the whole of C3 and unstructured segment 54–130 showed interaction (Fig 1b). Constructs B4 and B5 also containing residues 54–130 showed interaction despite differing from B3 by lacking regions 167–224 and 155–224, respectively. Interestingly, the non-interacting constructs C3 and C35 do not contain 54–130 residues, but include the regions 167–224 and 167–189, respectively (Fig 1b). Here constructs containing region 167–189 but lacking 54–130 did not interact with FAT despite LD motif alone showing interaction (switch off) (Fig 3a). Whereas, if 54–130 was included, interaction was reinstated (switch on) (Fig 3a). This clearly shows that interaction of LD2 in construct C35 is masked by residues 167–189 (masking region) (Fig 2b). The constructs B3 and B4 binding to FAT despite the presence of the masking region led us to conclude that the region 54–130 (regulatory region) acts to remove the masking effect (Fig 2b).
thumbnail
Fig 3. Binding studies of paxillin constructs using Bio-layer Interferometry on OctetRed96.

(a) Switch off in C3 and D2 on LD2 and LD4 respectively; Hypothesis of partial switch on when regulatory region of LD2 is absent, as evidenced in C2. (b) Concentration calibration curves depicting binding of constructs B2, C35, ‘54–189’, ‘79–189’, ‘105–189’ with GST-FAT. The data is representative of a single experiment. Each experiment was performed at-least thrice. (c) Illustrations of C35, C35_1, C35_2 and C35_3.  http://dx.doi.org:/10.1371/journal.pone.0150153.g003

Similar to LD2, LD4 in construct D2 containing 216–257 (masking region) requires additional residues of paxillin 280–313 (regulatory region) for FAT binding (Fig 2c), which was demonstrated by showing the interaction with constructs D1 (spanning region 216–313) (Fig 1b) and E1 (spanning region 258–313). To visualize the non-binding of FAT to C35, in-silico methods were employed to model the C35 construct and docked with the crystal structure of FAT (1K05, residues 916–1050 [21]) (Fig 4). The docking results showed a clear masking effect in the C35 construct by the 167–189 (masking region) residues. The constructs B2, C3 and C35 were also structurally characterized using CD analysis (Large scale cell-free expression was performed for this purpose, see S3 Fig). The percentage of alpha helical content was found to be much higher in C35 (95.32%) as compared to B2 (12.43%) (Fig 2a, S3 Table). Therefore, the dissection(s) of B2 to C35 allowed the identification of structured regions (C35) as compared to the disordered B2. Further, it showed that the LD2 peptide and C35 have significant alpha-helical structures that do not translate into functional similarity as evidenced by the inability of C3, C35 and D2 to bind to FAT. Moreover, LD2 peptide binds to FAT while C35 does not (Fig 1e and S2b and S2c Fig). A similar observation was made when comparing the ability of LD4 peptide and the inability of D2 to bind to FAT despite both having detectable α-helical content (Fig 1b). Thus, these results confirm the existence of masking and regulatory regions (Fig 2b and 2c) that determine switch on and off and in turn, intra-molecular auto-inhibition. C2 showed activity despite missing regulatory regions for both LD2 and LD4 (similar activity observed in C1). This could be because the unfolded nature of LD3 effector binding site that is located between LD2 and LD4 is flexible to mask only a single LD motif but not both (Partial switch on, Fig 3a).

thumbnail

Fig 4. In-silico analysis of non-binding of C35.

(a) LD2 crystal structure from PDB id: 1K05 (left) being compared with the LD2 structure in the side view and top view of C35 structure showing the masking of the hydrophobic binding region predicted through HMM based SAM-T08 software. The LD2 binding region and the masking regions are depicted by the bracketed region. (b) Docking control showing FAT (co-ordinates from PDB id: 1K05) and LD2 (co-ordinates from PDB id: 2L6F, NMR model # 1) interaction using Hex 6.3 software. (c) Docking of C35 with FAT showing non-interaction due to masking effect. The sidechains of the active residues are shown as red sticks. The hydrophobic patch—HP2 in FAT molecule, which preferentially binds to LD2 is shown as a space filling model in orange (part of helix 1 of FAT) and grey (part of helix 4 of FAT) colors.   http://dx.doi.org:/10.1371/journal.pone.0150153.g004

To predict the influence of this structural modulation, the state of LD motifs structurally before and after binding to FAT had to be understood. CD spectra of LD1, LD3 and LD5 peptides showed characteristics of random coil (Fig 2a, S3 Table) thus validating that the LD1, LD3 and LD5 motifs could exist as unfolded effector binding sites (not available for interaction) in our study and could fold upon undergoing allosteric changes after binding to their respective targets.

Validation of protein-protein interaction study using bio-layer interferometry studies

Bio-layer interferometry studies were performed to further validate the interaction studies and also to get insights into the binding affinities. Here apart from constructs B2 and C35, three other constructs that include different lengths of the regulatory region along with the C35 region were used for the studies, namely—Construct C35_1(54–189); Construct C35_2 (79–189) and Construct C35_3 (105–189) (See Fig 3b and S4 Fig). As seen in Fig 3c and Table 1, B2 shows maximum binding with KD value in the nano-molar range and the curves fit into a 1:1 binding model. C35 shows negligible binding and the rest of the constructs show binding lower than B2 with KD values in micro-molar range and the curves fit into a 2:1 binding model (See S5 Fig).

According to previous reports, FAK has to bind to both LD2 and LD4, failing which phosphorylation during signalling is reduced [8], which is observed in case of cancer [3], thus resulting in abnormal functioning of paxillin. We investigated this by analysing B2, which showed higher interaction than B1, despite missing the regulatory region of LD4 (Fig 1b). Similarly, C2 showed activity despite missing regulatory regions for both LD2 and LD4 and the presence of masking regions (similar activity observed in C1). This suggests that the masking region that is located between LD2 and LD4 is flexible to mask only a single LD motif but not both (Fig 3a). Interestingly, paxillin mutations associated with lung cancer were observed in the unstructured segments, particularly the regulatory region of LD2 and masking region of LD4 [3]. We hypothesize that these mutations prevent proper functioning of the regulatory regions, thus resulting in masking of either of the LD motifs causing abnormal functioning of paxillin. Evidence that these regions regulate FAT-paxillin binding was further provided in our study in the form of the bio-layer interferometry results; where C35 did not show any binding, but the constructs that included different lengths of the regulatory region along with the C35 region showed binding with KD values in the micro-molar range. This suggests that the LD2 region in these constructs is not masked, since it is seen in previous studies that the KD value for FAT binding to a single LD motif of paxillin is in micro-molar range. It also suggests that the region between residues 105–131 is sufficient for preventing the masking of LD2 region, thus allowing interaction with FAT (See illustrations in Fig 3b). Except B2 (that had a 1:1 binding stoichiometry and higher binding affinity), all other constructs (C35_1, C35_2, C35_3) showed a 2:1 binding stoichiometry. This suggests that both LD motifs of B2 engage both the FAT HP sites thus resulting in higher affinity; whereas in the other 3 constructs (C35_1, C35_2, C35_3), each FAT HP site (HP1 and HP2) interacts with individual molecules thus giving a 2:1 stoichiometry. This is in agreement with previous studies where both the LD motifs were found to interact with both HP1 and HP2 hydrophobic patches of FAT [16]. The higher affinity of B2 to FAT could be due to presence of both LD2 and LD4; the proposed intra-molecular regulatory regions could also play a role in the increased affinity. Therefore, we understand that the abnormal modulation in cancer involves redirection of FAK to a single LD motif; and targeting drugs for re-establishing the function at regulatory regions could be critical.

Unlike many existing techniques like array based yeast two hybrid assay, phage display method and tandem affinity purification; the strategy used here (combination of cell-free expression, filter based solubility assay and interaction study in HTP format) facilitated quick identification of the role of unstructured regions involved in paxillin-FAT interaction in HTP format. Particularly, in paxillin-FAK interactions, which determine focal adhesion and cellular signalling, we understood the structural masking and unmasking behaviour of unstructured segments in paxillin to determine FAK interaction. The structure of paxillin is not yet elucidated due to difficulties with respect to its disordered nature. In this study, the templates that we generated using the high throughput dissection strategy allowed us to analyze various regions of paxillin, with respect to structure, solubility and function. To our knowledge, this study is the first report of switch on and off mechanisms working together in controlling allosteric modulation/auto-inhibition in a human hub protein. As many eukaryotic proteins are disordered, our study opens avenues for analyzing novel modulations at allosteric sites using appropriate interaction studies, which could lead to identification of new drug target sites. In this regard, we hope the above strategy will be instrumental in understanding mechanisms of other disordered proteins as well, in days rather than months. This strategy could also be used as an initial screening method for techniques like SAXS, smFRET and others.

Read Full Post »

Myc and Cancer Resistance

Curator: Larry H. Bernstein, MD, FCAP


Myc (c-Myc) is a regulator gene that codes for atranscription factor. The protein encoded by this gene is a multifunctional, nuclear phosphoprotein that plays a role in cell cycle progression, apoptosis and cellular transformation.[1]

Myc gene was first discovered in Burkitt lymphoma patients. In Burkitt lymphoma, cancer cells showchromosomal translocations, in which Chromosome 8 is frequently involved. Cloning the break-point of the fusion chromosomes revealed a gene that was similar to myelocytomatosis viral oncogene (v-Myc). Thus, the newfound cellular gene was named c-Myc.

http://www.ncbi.nlm.nih.gov/gene/17869


Protein increases signals that protect cancer cells

Researchers have identified a link between the expression of a cancer-related gene and cell-surface molecules that protect tumors from the immune system

http://med.stanford.edu/news/all-news/2016/03/protein-increases-signals-that-protect-cancer-cells.html

Depiction of the Myc protein

http://med.stanford.edu/news/all-news/2016/03/protein-increases-signals-that-protect-cancer-cells/_jcr_content/main/image.img.full.high.jpg

The Myc protein, depicted here, is mutated in more than half of all human cancers.   Petarg/Shutterstock


A cancer-associated protein called Myc directly controls the expression of two molecules known to protect tumor cells from the host’s immune system, according to a study by researchers at the Stanford University School of Medicine.

The finding is the first to link two critical steps in the development of a successful tumor: uncontrolled cell growth — when mutated or misregulated, Myc causes an increase in the levels of proteins that promote cell division — and an ability to outwit the immune molecules meant to stop it.

The study was published online March 10 inScience. Dean Felsher, MD, PhD, a professor of oncology and of pathology, is the senior author. The lead author is postdoctoral scholar Stephanie Casey, PhD. The work was conducted in collaboration with researchers at the University of Wurzburg.

“Our findings describe an intimate, causal connection between how oncogenes like Myc cause cancer and how those cancer cells manage to evade the immune system,” Felsher said.

‘Don’t eat me’ and ‘don’t find me’

One of the molecules is the CD47 protein, which researchers in the Stanford laboratory of Irving Weissman, MD, have discovered serves as a “don’t eat me” signal to ward off cancer-gobbling immune cells called macrophages. Weissman is the Virginia and D.K. Ludwig Professor for Clinical Investigation in Cancer Research and the director of Stanford’s Institute for Stem Cell Biology and Regenerative Medicine.

Nearly all human cancers express high levels of CD47 on their surfaces, and an antibody targeting the CD47 protein is currently in phase-1 clinical trials for a variety of human cancers.

The other molecule is a “don’t find me” protein called PD-L1, known to suppress the immune system during cancer and autoimmune diseases but also in normal pregnancy. It’s often overexpressed on human tumor cells. An antibody that binds to PD-L1 has been approved by the U.S. Food and Drug Administration to treat bladder and non-small-cell lung cancer, but it has been shown to be effective in the treatment of many cancers.

Dean Felsher

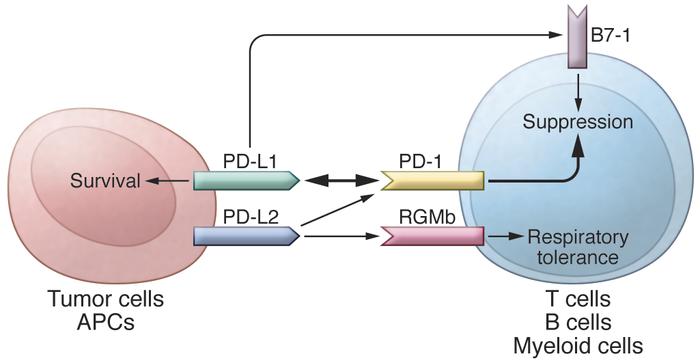
Programmed death-ligand 1 (PD-L1): an inhibitory immune pathway exploited by cancer

Image of PD-L1 binding to B7.1 and PD-1, deactivating T cell]

http://www.researchcancerimmunotherapy.com/images/pathways/pd-l1-hero.jpg

In cancer, Myc a usual suspect

Researchers in Felsher’s laboratory have been studying the Myc protein for more than a decade. It is encoded by a type of gene known as an oncogene. Oncogenes normally perform vital cellular functions, but when mutated or expressed incorrectly they become powerful cancer promoters. The Myc oncogene is mutated or misregulated in over half of all human cancers.

In particular, Felsher’s lab studies a phenomenon known as oncogene addiction, in which tumor cells are completely dependent on the expression of the oncogene. Blocking the expression of the Myc gene in these cases causes the complete regression of tumors in animals.

In 2010, Felsher and his colleagues showed that this regression could only occur in animals with an intact immune system, but it wasn’t clear why.

“Since then, I’ve had it in the back of my mind that there must be a relationship between Myc and the immune system,” said Felsher.

Turning off Myc expression

Casey and Felsher decided to see if there was a link between Myc expression and the levels of CD47 and PD-L1 proteins on the surface of cancer cells. To do so, they investigated what would happen if they actively turned off Myc expression in tumor cells from mice or humans. They found that a reduction in Myc caused a similar reduction in the levels of CD47 and PD-L1 proteins on the surface of mouse and human acute lymphoblastic leukemia cells, mouse and human liver cancer cells, human skin cancer cells, and human non-small-cell lung cancer cells. In contrast, levels of other immune regulatory molecules found on the surface of the cells were unaffected.

I’ve had it in the back of my mind that there must be a relationship between Myc and the immune system.

In publicly available gene expression data on tumor samples from hundreds of patients, they found that the levels of Myc expression correlated strongly with expression levels of CD47 and PD-L1 genes in liver, kidney and colorectal tumors.

The researchers then looked directly at the regulatory regions in the CD47 and PD-L1 genes. They found high levels of the Myc protein bound directly to the promoter regions of both CD47 and PD-L1 in mouse leukemia cells, as well as in a human bone cancer cell line. They were also able to verify that this binding increased the expression of the CD47 gene in a human blood cell line.

Possible treatment synergy

Finally, Casey and Felsher engineered mouse leukemia cells to constantly express CD47 or PD-L1 genes regardless of Myc expression status. These cells were better able than control cells to evade the detection of immune cells like macrophages and T cells, and, unlike in previous experiments from Felsher’s laboratory, tumors arising from these cells did not regress when Myc expression was deactivated.

“What we’re learning is that if CD47 and PD-L1 are present on the surfaces of cancer cells, even if you shut down a cancer gene, the animal doesn’t mount an adequate immune response, and the tumors don’t regress,” said Felsher.

The work suggests that a combination of therapies targeting the expression of both Myc and CD47 or PD-L1 could possibly have a synergistic effect by slowing or stopping tumor growth, and also waving a red flag at the immune system, Felsher said.

“There is a growing sense of tremendous excitement in the field of cancer immunotherapy,” said Felsher. “In many cases, it’s working. But it’s not been clear why some cancers are more sensitive than others. Our work highlights a direct link between oncogene expression and immune regulation that could be exploited to help patients.”

The research is an example of Stanford Medicine’s focus on precision health, the goal of which is to anticipate and prevent disease in the healthy and precisely diagnose and treat disease in the ill.

Other Stanford co-authors of the paper are oncology instructor Yulin Li, MD, PhD; postdoctoral scholars Ling Tong, PhD, Arvin Gouw, PhD, and Virginie Baylot, PhD; former research assistant Kelly Fitzgerald; and undergraduate student Rachel Do.

The research was supported by the National Institutes of Health (grants RO1CA089305, CA170378, CA184384, CA105102, P50 CA114747, U56CA112973, U01CA188383, 1F32CA177139 and 5T32AI07290).


The PD-L1 pathway downregulates cytotoxic T-cell activity to maintain immune homeostasis

Under normal conditions, the inhibitory ligands PD-L1 and PD-L2 play an important role in maintaining immune homeostasis.1 PD-L1 and PD-L2 bind to specific receptors on T cells. When bound to their receptors, cytotoxic T-cell activity is downregulated, thereby protecting normal cells from collateral damage.1,2

Image showing PD-L1 binding to B7.1 and PD-1 to deactivate T cells during immune response]

PD-L1

Broadly expressed in multiple tissue types, including hematopoietic, endothelial, and epithelial cells1,4

B7.1

Receptor expressed on activated T cells and dendritic cells3

PD-1

Receptor expressed primarily on activated T cells3

CONVERSELY, PD-L2 BINDS PRIMARILY TO PD-13

Image showing PD-L1 binding to B7.1 and PD-1 to deactivate T cells during immune response]

PD-L2

Restricted expression on immune cells and in some organs, such as the lung and colon1,4,5

PD-1

Receptor expressed primarily on activated T cells3


Many tumors can exploit the PD-L1 pathway to inhibit the antitumor response

In cancer, the PD-L1/B7.1 and PD-L1/PD-1 pathways can protect tumors from cytotoxic T cells, ultimately inhibiting the antitumor immune response in 2 ways.1-3

  • Deactivating cytotoxic T cells in the tumor microenvironment
  • Preventing priming and activation of new T cells in the lymph nodes and subsequent recruitment to the tumor


PD-L1 MAY INHIBIT CYTOTOXIC T-CELL ACTIVITY IN THE TUMOR MICROENVIRONMENT

Upregulation of PD-L1 can inhibit the last stages of the cancer immunity cycle by deactivating cytotoxic T cells in the tumor microenvironment.1

Activated T cells in the tumor microenvironment release interferon gamma.2

As a result, tumor cells and tumor-infiltrating immune cells overexpress PD-L1.2

PD-L1 binds to T-cell receptors B7.1 and PD-1, deactivating cytotoxic T cells. Once deactivated, T cells remain inhibited in the tumor microenvironment.1,2

PD-L1 MAY INHIBIT CANCER IMMUNITY CYCLE PROPAGATION IN THE LYMPH NODES

PD-L1 overexpression can also inhibit propagation of the cancer immunity cycle by preventing the priming and activation of T cells in the lymph nodes.1-3

PD-L1 expression is upregulated on dendritic cells within the tumor microenvironment.2,3

PD-L1–expressing dendritic cells travel from the tumor site to the lymph node.4

PD-L1 binds to B7.1 and PD-1 receptors on cytotoxic T cells, leading to their deactivation.3

http://www.researchcancerimmunotherapy.com/pathways/pd-l1-immune-evasion


The cancer immunity cycle characterizes the complex interactions between the immune system and cancer

The cancer immunity cycle describes a process of how one’s own immune system can protect the body against cancer. When performing optimally, the cycle is self-sustaining. With subsequent revolutions of the cycle, the breadth and depth of the immune response can be increased.1


STEPS 1-3: INITIATING AND PROPAGATING ANTICANCER IMMUNITY1

  • Oncogenesis leads to the expression of neoantigens that can be captured by dendritic cells
  • Dendritic cells can present antigens to T cells, priming and activating cytotoxic T cells to attack the cancer cells

STEPS 4-5: ACCESSING THE TUMOR1

  • Activated T cells travel to the tumor and infiltrate the tumor microenvironment

STEPS 6-7: CANCER-CELL RECOGNITION AND INITIATION OF CYTOTOXICITY1

  • Activated T cells can recognize and kill target cancer cells
  • Dying cancer cells release additional cancer antigens, propagating the cancer immunity cycle


Image of immunity cycle; explore Genentech cancer immunotherapy research on the cancer immunity cycle

http://www.researchcancerimmunotherapy.com/pathways/pd-l1


REFERENCES

  1. Chen DS, Mellman I. Oncology meets immunology: the cancer-immunity cycle. Immunity. 2013;39:1-10. PMID: 23890059
  2. Chen DS, Irving BA, Hodi FS. Molecular pathways: next-generation immunotherapy—inhibiting programmed death-ligand 1 and programmed death-1. Clin Cancer Res. 2012;18:6580-6587. PMID: 23087408
  3. Keir ME, Butte MJ, Freeman GJ, Sharpe AH. PD-1 and its ligands in tolerance and immunity. Annu Rev Immunol. 2008;26:677-704. PMID: 18173375
  4. Motz GT, Coukos G. Deciphering and reversing tumor immune suppression. Immunity. 2013;39:61-73. PMID: 23890064


MYC regulates the antitumor immune response through CD47 and PD-L1

The clinical efficacy of monoclonal antibodies as cancer therapeutics is largely dependent upon their ability to target the tumor and induce a functional antitumor immune response. This two-step process of ADCC utilizes the response of innate immune cells to provide antitumor cytotoxicity triggered by the interaction of the Fc portion of the antibody with the Fc receptor on the immune cell. Immunotherapeutics that target NK cells, γδ T cells, macrophages and dendritic cells can, by augmenting the function of the immune response, enhance the antitumor activity of the antibodies. Advantages of such combination strategies include: the application to multiple existing antibodies (even across multiple diseases), the feasibility (from a regulatory perspective) of combining with previously approved agents and the assurance (to physicians and trial participants) that one of the ingredients – the antitumor antibody – has proven efficacy on its own. Here we discuss current strategies, including biologic rationale and clinical results, which enhance ADCC in the following ways: strategies that increase total target–monoclonal antibody–effector binding, strategies that trigger effector cell ‘activating’ signals and strategies that block effector cell ‘inhibitory’ signals.

Keywords: γδ T cells, ADCC, cancer, cytokines, IMiD, immunocytokines, immunomodulators, interleukins, monoclonal antibodies, NK cells, passive immunotherapy

Monoclonal antibodies (mAbs) can target tumor antigens on the surface of cancer cells and have a favorable toxicity profile in comparison with cytotoxic chemotherapy. Expression of tumor antigens is dynamic and inducible through agents such as Toll-like receptor (TLR) agonists, immunomodulatory drugs (IMiDs) and hypomethylating agents [1]. Following binding of the mAb to the tumor antigen, the Fc portion of the mAb interacts with the Fc receptor (FcR) on the surface of effector cells (i.e., NK cells, γδ T cells and macrophages), leading to antitumor cytotoxicity and/or phagocytosis of the tumor cell. FcR interactions can be stimulatory or inhibitory to the killer cell, depending on which FcR is triggered and on which cell. Stimulatory effects are mediated through FcγRI on macrophages, dendritic cells (DCs) and neutrophils, and FcγRIIIa on NK cells, DCs and macrophages. In murine models, the cytotoxicity resulting from FcR activation on a NK cell, γδ T cell and macrophage is responsible for antitumor activity [2]. The role of DCs should be noted: although not considered to be primary ADCC effector cells, they can respond to mAb-bound tumor cells via their own FcR-mediated activation and probably play a significant role in activating effector cells. Preclinical models have shown that, although not the effector cell, DCs are critical to the efficacy of mAb-mediated tumor elimination [3]. Equally, mAb-activated ADCC effector cells can induce DC activation [4] and the importance of this crosstalk is an increasing focus of study [5].

The antitumor effects of mAbs are caused by multiple mechanisms of action, including cell signaling agonism/antagonism, complement activation and ligand sequestration, although ADCC probably plays a predominant role in the efficacy of some mAbs. In a clinical series, a correlation between the affinity of the receptor FcγRIIIa (determined by inherited FcR polymorphisms) and the clinical response to mAb therapy, supporting the significance of the innate immune response [6–10]. Several strategies could potentially improve the innate response following FcR activation by a mAb (Figure 1):

Quantitatively increasing the density of the bound target, mAb or the effector cells;

Stimulation of the effector cell by targeting the NK cell, γδ T cell and/or macrophage with small molecules, cytokines or agonistic antibodies;

Blocking an inhibitory interaction between the NK cell or macrophage and the tumor cell.


An external file that holds a picture, illustration, etc. Object name is nihms384451f1.jpg

http://www.ncbi.nlm.nih.gov/pmc/articles/PMC3386352/bin/nihms384451f1.jpg

Enhancing ADCC

FcR: Fc receptor; HDACi: Histone deacetylase inhibitor; IMiD: Immunomodulator; KIR: Killer immunoglobulin-like receptor;

The ability of the combination approaches to enhance ADCC is largely determined by the capacity of the mAb to induce ADCC. Since the approval of the first mAb for the treatment of non-Hodgkin’s lymphoma, rituximab (RTX), in 1997, several mAbs have become standard of care for the treatment of both solid tumors and hematologic malignancies, including trastuzumab (TRAST), alemtuzumab, cetuximab, panitumumab and ofatumumab [11]. As noted above, clinical series among lymphoma patients treated with an anti-CD20 mAb (RTX) [6,7], HER2-expressing breast cancer receiving anti-HER2 mAb therapy (TRAST) [8] or colorectal cancer patients treated with an anti-EGFR mAb (cetuximab) [9,10] observed a correlation between clinical benefit and FcγRIIIa genotype, with patients who have higher-affinity polymorphisms demonstrating superior clinical outcomes. By contrast, the anti-EGFR mAb panitumumab does not induce ADCC, owing to a different Fc isotype that does not bind to the FcγRIIIa. Therefore, when considering enhancement of ADCC, such approaches are limited to combinations with mAbs that activate the FcR. Nonetheless, an advantage of this dual therapy strategy is that mAbs yet to be discovered against currently unknown tumor antigens may be combined with the therapeutics discussed herein.

Increasing target–mAb–effector binding

As the central element in the target–mAb–effector cell unit, the mAb seems to be a probable candidate for improvements, either in its antigen-binding or its Fc-binding domains. This approach has been heavily pursued with some degree of success [12–15]. Antibody engineering to improve interaction between the target or FcR requires that each new antibody be individually developed and tested as a new entity.

Increasing the antigen target

Tumor cells with a lower density of antigen targets are less responsive to mAbs than higher antigen-expressing diseases [16]. Therefore, it seems logical to try to increase the expression of the target on tumor cells. Antigen expression can be upregulated by cytokines [17], ionizing radiation [18], natural metabolites [19] and hypomethylating agents such as decitabine [20]. In addition, the family of TLR9 agonists known as CpG oligodeoxynucleotides (CpG ODN) can induce CD20 expression on malignant B cells [21–23]. Taken together with data showing the activating effect of CpG ODN on effector cells (discussed below), it seems reasonable that the combination of CpG ODN with mAb might have synergistic efficacy. Clinical series, however, have tested CpG ODN administered intravenously or subcutaneously and have observed little efficacy in Phase I and II studies [24–26] in low-grade lymphoma. One possible limitation of these studies has been their application to diseases (primarily follicular and mantle cell lymphoma) known to already have high expression of the relevant antigen (CD20). It is plausible that increasing antigen expression on low antigen-expressing diseases such as chronic lymphocytic leukemia could have a greater increase in relative efficacy. To this end, monotherapy studies have recently been undertaken [27,301] and should lead to combination trials.

……

Effector cells: γδ T cells

The role of NK cells and macrophages in mediating ADCC has been well established; however, only recently have γδ T cells been found to play a role as ADCC effectors. Typically, this population is considered as a minor subset (<5% of circulating T cells), although they may infiltrate tumors of epithelial origin preferentially and constitute a large portion of the tumor-infiltrating lymphocytes in cancers such as breast carcinoma. The combination of HLA-unrestricted cytotoxicity against multiple tumor cell lines of various histologies, secretion of cytolytic granules and proinflammatory cytokines such as TNF-α, IL-17 and IFN-γ make γδ T cells potentially potent antitumor effectors [32,33].

……

TLR agonists    

In addition to its aforementioned induction of CD20, CpG ODN also indirectly augments innate immune function. TLRs are specialized to recognize pathogen-associated molecular patterns; they stimulate plasmacytoid DCs and B cells [53], and one of many plasmacytoid DC responses to stimulation by CpG ODNs is activation of local NK cells, thus improving spontaneous cytotoxicity and ADCC [54]. CpG ODN effects on NK cells appeared to be indirect and IFN-γ production by T cells (possibly in response to plasmacytoid DC activation) has been hypothesized as the intermediary of NK cell activation.

…..

Immunomodulatory drugs

IMiDs have shown clinical activity in multiple hematologic malignancies despite their primary mechanism of action being unclear. Among their biologic effects (particularly lenalidomide) there are demonstrable and pleiotropic effects on immune cells and signaling molecules. These include enhancement of in vitro NK cell- and monocyte-mediated ADCC on RTX-coated [68] as well as TRAST- and cetuximab-coated tumor cells [69]. In vivo studies in a human lymphoma severe combined immune deficiency mouse model demonstrated significant increases in NK cell recruitment to tumors mediated via microenvironment cytokine changes and augmented RTX-associated ADCC [70]. Studies suggest that IMiD activation of NK cells occurs indirectly; partly via IL-2 induction by T cells [71]. Clinically, a recent study noted significant increases in peripheral blood NK cells, NK cell cytotoxicity and serum IL-2, IL-15 and GM-CSF [72], the potential ADCC-promoting effects of which are discussed below.

…..

PD-1

PD-1 is a negative regulatory member of the CD28 superfamily expressed on the surface of activated T cells, B cells, NK cells and macrophages, similar to but more broadly regulatory than CTLA-4. Its two known ligands, PD-L1 and PD-L2, are both expressed on a variety of tumor cell lines. The PD-1–PD-L1 axis modulates the NK cell versus multiple myeloma effect, as seen by its blockade enhancing NK cell function against autologous primary myeloma cells, seemingly through effects on NK cell trafficking, immune complex formation with myeloma cells and cytotoxicity specifically toward PD-L1(+) tumor cells [179]. Two anti-PD-1 mAbs (BMS-936558 and CT-011) are currently in clinical trials, the latter in a combination study with RTX for patients with low-grade follicular lymphoma [314].

ConclusionThe recent approval of an anti-CTLA4 mAb has demonstrated that modulating the immune response can improve patient survival [180,181]. As the immune response is a major determinant of mAb efficacy, the opportunity now exists to combine mAb therapy with IMiDs to enhance their antitumor efficacy. Remarkable advances in the basic science of cellular immunology have increased our understanding of the effector mechanisms of mAb antitumor efficacy. Whereas the earliest iterations of such combinations, for example IL-2 and GM-CSF, may have augmented both effector and suppressive cells, newer approaches such as IL-15 and TLR agonists may more efficiently activate effector cells while minimizing the influence of suppressive cells. Despite these encouraging rationale and preliminary data, clinical evidence is still required to demonstrate whether combination therapies will increase the antitumor effects of mAb.

Still, this approach is unique in combining a tumor-targeting therapy, the mAb, with an immune-enhancing therapy. If successful, these therapies may be combined with multiple mAbs in routine practice, as well as novel mAbs yet to be developed. Various approaches including augmenting antigen expression, stimulating the innate response and blocking inhibitory signals are being explored to determine the optimal synergy with mAb therapies. Therapies targeting NK cells, γδ T cells, macrophages and DCs may ultimately be used in combination to further augment ADCC. Encouraging preclinical studies have led to a number of promising therapeutics, and the results of proof-of-concept clinical trials are eagerly awaited.

PD-L1, other targeted therapies await more standardized IHC

February 2016—Immunohistochemistry is heading down a path toward more standardization, and that’s essential as it plays an increasing role in rapidly expanding immunotherapy, says David L. Rimm, MD, PhD, professor of pathology and of medicine (oncology) and director of translational pathology at Yale University School of Medicine. As a co-presenter of a webinar produced by CAP TODAY in collaboration with Horizon Diagnostics, titled “Immunohistochemistry Through the Lens of Companion Diagnostics” (http://j.mp/ihclens_webinar), he analyzes the core challenges of IHC’s adaptation to the needs of precision medicine: binary versus continuous IHC, measuring as opposed to counting or viewing by the pathologist, automation, and assay performance versus protein measurement.

“Immunohistochemistry is 99 percent binary already,” Dr. Rimm points out. “There are only a few assays in our labs—ER, PR, HER2, Ki-67, and maybe a few more—where we really are looking at a continuous curve or a level of expression.”

Two criteria in the 2010 ASCO/CAP guidelines on ER and PR testing in breast cancer patients are key, he says: 1) the percentage of cells staining and 2) any immunoreactivity. “The first is hard to estimate, but the guidelines recommend the use of greater than or equal to one percent of cells that are immunoreactive. That means they could have a tiny bit of signal or they could have a huge amount of signal and they would be considered immunoreactive, which thereby makes this a binary test.”

Having the test be binary can be a problem for companion diagnostic purposes because any immunoreactivity is dependent on the laboratory threshold and counterstain. For example, if two of the same spots, serial sections on a tissue microarray, were shown side by side, one with and one without the hematoxylin counterstain, “you might see the counterstain make this positive test into a negative by eye, which is a potential problem with IHC when you have a binary stain.” (Fig. 1).

Fig1

http://www.captodayonline.com/wordpress/wp-content/uploads/2016/02/Fig1.jpg

Dr. Rimm describes a small study done with three different CLIA-certified labs, each using a different FDA-approved antibody and measuring about 500 breast cancer cases on a tissue microarray. The study showed there can be fairly significant discordance between labs—between 18 and 30 percent discordance—in terms of the cases that were positive. “In fact, if we look at outcome, 18 percent of the cases were called positive in Lab Two but were negative in Lab Three. Lab Three showed outcomes similar to the double positives whereas Lab Two had false-negatives.” This is an important problem that occurs when we try to binarize our immunohistochemistry, he says.

Counting is more variable in a real-world setting due to the variability of the threshold for considering a case positive. “You can easily calculate that if your threshold was five percent, then you’d have 70 percent positive cells. And you would easily call this positive. But if you added more hematoxylin because that’s how your pathologist liked it, then perhaps you’d only have 30 percent positive. So this is the risk of using thresholds.” (Fig. 2).

Fig2

http://www.captodayonline.com/wordpress/wp-content/uploads/2016/02/Fig2.gif

Although this is done in all of immunohistochemistry today, Dr. Rimm thinks it is an important consideration as IHC transitions to more standardized form. “An H score—intensity times area, which has been attempted many times, can’t be done by human beings. Pathologists try but have failed.”

“We can’t do those intensities by eye. We have to measure them with a machine. But we get a very different piece of information content when we measure intensity, as opposed to measuring the percentage of cells above a threshold. In sum, more information is present in a measurement than in counting.”

Pathologists read slides for a living, so it’s uncomfortable to think about giving that up in order to use a machine to measure the slides. “But I think if we want to serve our clients and our patients, we really owe them the accuracy of the 21st century as opposed to the methods of the 20th century.” (Fig. 3).

A shows comparison of a quantitative fluorescence score on the x axis versus an H-score on the y axis. Note the noncontinuous nature of human estimation of intensity times area (H-score). B) The survival curve in a population of lung cancer cases using the H-score. C) The survival curve in the same population using the quantitative score. (Source: David Rimm, MD, PhD)

http://www.captodayonline.com/wordpress/wp-content/uploads/2016/02/Fig3.gif

A shows comparison of a quantitative fluorescence score on the x axis versus an H-score on the y axis. Note the noncontinuous nature of human estimation of intensity times area (H-score). B) The survival curve in a population of lung cancer cases using the H-score. C) The survival curve in the same population using the quantitative score. (Source: David Rimm, MD, PhD)

Among the currently available quantitative measuring devices are the Visiopharm, VIAS (Ventana), Aperio (Leica), InForm (Perkin-Elmer), and Definiens platforms. “We use the platform invented in my lab, called Aqua [Automated Quantitative Analysis], but this is now owned by Genoptix/Novartis. Genoptix intends to provide commercial tests using Aqua internally,” Dr. Rimm says, “as well as enable platform and commercial testing through partnership with additional reference lab providers.

“There are many quantification platforms,” he adds, “and I believe that any of them, used properly, can be effective in measurement.”

(Of the 265 participants in the CAP PM2 Survey, 2015 B mailing, who reported using an imaging system for quantification, 4.6 percent use VIAS, 4.1 percent use ACIS, 0.8 use Applied Imaging, and 10 percent use “other” imaging systems. Of the 1,359 Survey participants who responded to the question about use of an imaging system to analyze hormone receptor slides, 1,094, or 80.5 percent, reported not using any imaging system for quantification.)

Says Dr. Rimm: “The first platform we used to try to quantitate some DAB stain slides was actually the Aperio Nuclear Image Analysis algorithm. But the problem with DAB is that you can’t see through it. And so inherently it’s physically flawed as a method for accurate measurement.” He compares DAB to looking at stacks of pennies from above, where their height and quantity can’t be surmised, as opposed to from the side, where their numbers can be accurately estimated. “This is why I don’t use, in general, DAB-type technologies or any chromogen.”

Fluorescence doesn’t have this problem, and that is the reason Dr. Rimm began using fluorescence as a quantitative method. “We try to be entirely quantitative without any feature extraction. So we define epithelial tumors using a mask of cytokeratin. We define a mask by bleeding and dilating, filling some holes, and then ultimately measure the intensity of each cell, or of each target we’re looking for. In this case, in a molecularly defined compartment.”

Compartments can be defined by any type of molecular interactions. “We defined DAPI-positive pixels as nuclei, and we measure the intensity of the estrogen receptor within the compartment. And that gives us an intensity over an area or the equivalent of a concentration.” Many other fluorescent tools can be used in this same manner, but he cautions against use of fluorescent tools that group and count. “That’s a second approach that can be used, but the result gives you a count instead of a measurement.”

When comparing a pathologist’s reading versus a quantitative immunofluorescence score, he notes, pathologists actually don’t generate a continuous score. Instead, pathologists tend to use groups. “We tend to use a 100 or a 200 or an even number. We never say, ‘Well, it’s 37 percent positive.’ We say, ‘It’s 40 percent positive,’ because we know we can’t reproducibly tell 37 from 38 from 40 percent positive.”

The result of that is a noncontinuous scoring result, which doesn’t give the information content of quantitative measurement. A comparison between the two methods shows that at times, where quantitative measurement shows a significant difference in outcome, nonquantitative measure or an H-score difference may not show a difference in outcome. (Fig. 3 illustrates this concept.)

“Pathologists tend to group things, and we also tend to overestimate. It’s not that pathologists are bad readers. It’s just the tendency of the human eye because of our ability to distinguish different intensities and the subtle difference between intensities. But even if you compare two quantitative methods, you can see that the method where light absorbance occurs—that is the percent positive nuclei by Aperio, which is a chromogen-based method—tends to saturate. This is, in fact, amplified dramatically when you look at something with a wide dynamic range like HER2.” (Fig. 4).

Fig4

http://www.captodayonline.com/wordpress/wp-content/uploads/2016/02/Fig4.gif

In one study, researchers found less than one percent discordance—essentially no discordance—between two antibodies (Dekker TJ, et al. Breast Cancer Res. 2012;14[3]:R93). But looking at these results graphed quantitatively, you would see a very different result, Dr. Rimm says. “You can see a whole group of cases down below where there’s very low extracellular domain and very high cytoplasmic domain. In fact, some of these cases have essentially no extracellular domain, but high levels of cytoplasmic domain, and other cases have roughly equal levels of each” (Carvajal-Hausdorf DE, et al. J Natl Cancer Inst.2015;107[8]:pii:djv136).

Recent studies by Dr. Rimm’s group have shown this to have clinical implications. He looked at patients treated with trastuzumab in the absence of chemotherapy, in an unusual study called the HeCOG (Hellenic Cooperative Oncology Group) trial.

“We found that patients who had high levels of both extracellular and intracellular domain have much more benefit than patients who are missing the extracellular domain and thereby missing the trastuzumab binding site.” Follow-up studies are being done to validate this finding in larger cohorts.

Preanalytical variables, Dr. Rimm emphasizes, can have significant effects on IHC results, and more than 175 of them have been identified. “These are basically all the things we can’t control, which is the ultimate argument for standardization.”

In a surprising study by Flory Nkoy, et al., he says, it was shown that breast cancer specimens were more likely to be ER negative if the patient’s surgery was on a Friday because there was a higher ER-negative rate on Friday than on Monday. “So how could that be? Well, it was clearly the fact that the tissue was sitting over the weekend. And when it sat over the weekend, the ER positivity rate was going down” (Arch Pathol Lab Med. 2010;134:606–612).

Another study showed that after one hour, four hours, and eight hours of storage at room temperature, you lose significant amounts of staining, Dr. Rimm says. “And perhaps the best nonquantitative study or H-score-based study of this phenomenon was done by Isil Yildiz-Aktas, et al., where a significant decrease in the estrogen receptor score was found after only three hours in delay to fixation” (Mod Pathol. 2012;25:1098–1105).

How long the slide is left to sit after it is cut is another preanalytical variable to be concerned with. “In the clinical lab, that’s not often a problem since we cut them, then stain them right away. But in a research setting, a fresh-cut slide can look very different from a slide that’s two days old, six days old, or 30 days old, where a 2+ spot on a breast cancer patient becomes negative after 30 days sitting on a lab bench. So those are both key variables to be mindful of.”

One solution for those preanalytic variables is trying to prevent delayed time to fixation. “And probably time to fixation is one of the main preanalytic variables, although it’s only one of the many hundreds of variables. The method we use to try to get around this problem is to use core biopsies or allow rapid and complete fixation, and then other things can be done.”

Finally, he warns, don’t cut your tissue until right before you stain it. “If you’re asked to send a tissue out to a collaborator or someone who is going to use it for research purposes later, we recommend coring and re-embedding the core, or sending the whole block. Unstained sections, when not properly stored in a vacuum, will ultimately be damaged by hydration or oxidation, both of which lead to loss of antigenicity.”

The crux of the matter is assay performance versus protein measurement, Dr. Rimm says. “In the last six to nine months, we really are faced with this problem in spades, as PD-L1 has become a very important companion diagnostic.”

There are now four PD-L1 drugs with complementary or companion diagnostic tests (Fig. 5). One of the FDA-approved drugs, nivolumab (Opdivo, Bristol-Myers Squibb), for example, uses a clone called 28-8, which is provided by Dako in an assay, a complementary diagnostic assay, and with the following suggested scoring system: one percent, five percent, or 10 percent. In contrast, pembrolizumab (Keytruda, Merck) is also now FDA-approved but requires a companion diagnostic test that uses a different antibody, although the same Dako Link 48 platform. This diagnostic has a different scoring system of less than one percent, one to 49 percent, and 50 percent and over.

http://www.captodayonline.com/wordpress/wp-content/uploads/2016/02/Fig5.gif

Two other companies, Roche/Genentech and AstraZeneca, also have drugs in trials that may or may not have companion diagnostic testing, though both have already identified a partner and a unique antibody (neither of those listed above) and companion diagnostic testing scores used in their clinical trials.

“So what’s a pathologist to do?” Dr. Rimm says. “Well, there are a few problems with this. First of all, what we really should be doing is measuring PD-L1. That’s the target and that’s what should ultimately predict response. But instead what we’re stuck with, through the intricacies of the way our field has grown and our legacy, is closed-system assays. While these probably do measure PD-L1, we do not know how these compare to each other.” Two parallel large multi-institutional studies are addressing this issue now, he says.

There are solutions for managing these closed-system assays to be sure the assay is working in your lab and that you can get the right answer, Dr. Rimm says. His laboratory uses a closed-system assay for PD-L1, relying not on the defined system but rather on a test system it has developed in doing a study with different investigators.

Sample runs by these different investigators show the potentially high variability, he says. “In a scan of results, no one would deny which spots are the positive spots and which are the negative.” But the difference in staining prevents accurate measurement of these things and shows the variability inherent even in a closed-box system.

A comparison of two closed-box systems, the SP1 run on the Discovery Ultra on Ventana, and the SP1, same antibody, run on the Dako closed-box system, also shows that, in fact, there’s not 100 percent agreement using same-day, same-FDA-cleared antibody staining and different autostainers. So automation may not solve the problem, Dr. Rimm notes (Fig. 6).
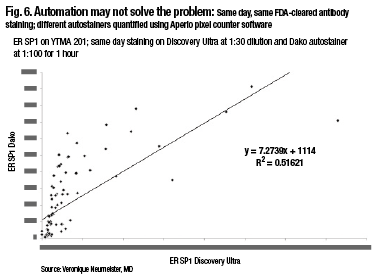
Fig6

“When running these in a quantitative fashion and measuring them quantitatively, there are actually differences in the way these closed-box systems run. And so you, as the pathologist, have to be the one who makes sure your assays are correct, your thresholds are correct, and your measurements are accurate.”

The way to do that, he believes, is to use standardization or index arrays. An index array of HER2 that his laboratory developed has 3+ amplified, 2+ amplified, not amplified, and so on from 80 cases in the lab’s archive, shown stained with immunofluorescence and quantitative and DAB stain. “It was only with this standardization array, run every time we ran our stainer, that we were able to draw the conclusions in the previous study about extracellular versus cytoplasmic domain.”

Companies have realized the importance of this, and specifically companies like NantOmics (formerly OncoPlexDx) have realized they can exactly quantitate the amount of tissue on a slide using a specialized mass spectrometry method, he says. “They can actually give you amol/µg of total protein.”

He and colleagues are working with NantOmics now to try to convert from amols to protein to average quantitative fluorescent scores to help build these standards and make standard arrays more accurate. “This is still a work in progress, but I believe this is ultimately the kind of accuracy that can standardize all of our labs. We have shown that the quantitative fluorescence system is truly linear and quantitative for EGFR measurements when using mass spectrometry as a gold standard.” They are preparing to submit a manuscript with this data.

In the interim, Dr. Rimm’s laboratory has begun working also with Horizon Diagnostics, employing Horizon’s experimental 15-spot positive-control array. “When you use this array and quantitate it with quantitative fluorescence, you get a very interesting profile. If a cut point is set at one point, you would see three clearly positive cells or spots and 12 clearly negative spots with two different antibodies. But is that the threshold?”

“In fact, using a little higher score and a very quantitative test, you might find that the threshold may, in fact, be a little bit lower than that.” It turns out that only three of these 12 spots are true negatives. The others at least have some level of RNA, and some have a lot. “So how do we handle these? And are these behaving the same way with multiple antibodies?” Parallel results, finding nearly the same threshold case, have been found using SP142 from Ventana, E1L3N from Cell Signaling, and SP263 from Ventana.

Studies to address those issues are still in the early stage, he says. He cautions that there is variance in these assays, and more work is being done to reproduce the data. “But I think the important point is that, using these kinds of arrays, you can definitively determine whether your lab has the same cut point as every other lab. And were we to quantitate this with mass spectrometry, we would know exactly the break point for use in the future.”

Dr. Rimm’s laboratory has also built its own PD-L1 index tissue microarray with a number of its own tumor slides ranging from very low to very high expressors, a series of cell lines, and including some placenta-positive controls on normal tumor. He has found that generating an index array has advantages, and he encourages other laboratories to prepare their own index arrays to increase the accuracy and reproducibility of their laboratory-developed tests. “You can produce these in your own lab so that you can be sure you can standardize your tests run in your clinical lab from day to day and week to week as part of an LDT.”

“If we think about it, there really are no clinical antibodies today that are truly quantitative,” Dr. Rimm says. “And when there are, new protocols will be required, but I believe those protocols are now in existence. We just await the clinical trials that require truly quantitative protein measurement or in situ proteomics.”

In that process of moving toward in situ proteomics, suggests web-inar co-presenter Clive Taylor, MD, DPhil, professor of pathology in the Keck School of Medicine at the University of Southern California, FDA approval, per se, will not solve any of the problems discussed in the webinar. (See the January 2016 issue for the full report of Dr. Taylor’s presentation.) “I think what the FDA approval will do is demand that we find solutions to these problems ourselves. The FDA’s attitude is, to a large degree, dependent on the claim. So if we just use immunohistochemistry as a simple stain, then the FDA classes that as sort of class I, level 1. And we can do that [IHC stain] without having to get preapproval by the FDA.

“On the other hand, if we take something like the well-established HercepTest, where based on the result of that test alone, it’s decided whether or not the patient gets treatment, treatment that’s very expensive and treatment that has benefits and…side effects. That claim is, in fact, a very high-level claim. And for that, the FDA is demanding high-level data, which I think is entirely appropriate,” Dr. Taylor says.

Most of these upcoming companion diagnostics, if not all, he says, will be regarded by the FDA as class III, high level or high complexity. They will require a premarket approval study in conjunction with a clinical trial. And the FDA will demand high standards of control and performance, eventually. “There are not many labs that can produce those high standards as in-house or lab-developed tests today. And even the companies currently in trials are not producing the improved performance level for these tests that we are talking about today, as being required for high-quality quantitative and reproducible companion diagnostics. Eventually, I am convinced we will have to do that. It’s just that it will take time to get there.”

The FDA can only approve what is brought to it, Dr. Rimm points out. And so a true, fully quantitative IHC-based assay has presumably never been submitted, or at least never been approved by the FDA. “What we’re seeing instead are the assays that the FDA has approved, which are well defined and rigorously submitted. However, the result is a closed system that we use, which may or may not accurately measure PD-L1 on the slide, depending upon preanalytic variables and individual laboratories’ methods.”

“So questions keep popping up. And I can only say that we, as pathologists, have the final responsibility to our patients. And while it may not be recommended and it may change in the future, right now lab-derived tests or LDTs may be more accurate than FDA-approved platforms.”

“If you think about it, in molecular diagnostics where I’m familiar with EFGR and BRAF and KRAS tests, in that testing setting, less than 25 percent of the labs that do that test actually use the FDA-approved test,” Dr. Rimm says. “The remainder of the labs do their own LDTs, including our labs here at Yale.”

It wouldn’t surprise him if the same thing happens for PD-L1. “I’m aware of at least two labs—and we probably will be the third—that devise our own LDT for PD-L1 testing using the standards I’ve discussed, using array-type controls to be sure that our levels are correct, and then using a scoring system that we derived.”

“We aren’t really in a position to know at the time that we receive a piece of lung cancer tissue whether the oncologist is going to use pembrolizumab, which requires a companion diagnostic, or nivolumab, or the other drugs, which may or may not require a companion diagnostic. So in that sense, we’re almost bound to use an LDT,” Dr. Rimm says, since his lab can’t actually run four different potentially incongruent, though FDA-approved, tests for PD-L1.

Until a truly quantitative approach is developed and submitted to the FDA and approved, Dr. Taylor believes we won’t see things changing. “The algorithms that currently are approved have been approved on the basis that they can produce a similar result to a consensus group of pathologists. So they’re only as good as the pathologists.”

“As Dr. Rimm has discussed, I actually believe we can get a much better result than the pathologists can get with their naked eye. We have to get away from comparing it to what we currently can do and start to try to construct a proper test, just like we did in the clinical lab 30 years ago when we automated the clinical lab,” Dr. Taylor says. “We need to automate anatomic pathology, including the sample preparation, the assay process, and the reading, all three together in a closed system. And we’re nibbling away at the edges of it. We’ll get there, but it’ll take some time.”

Dr. Rimm is skeptical that the diagnostics field has learned any lessons from HercepTest and the companion diagnostics world of almost 20 years ago. “The submissions to the FDA for PD-L1 look very similar to what was submitted in 1998 for the HercepTest, the companion diagnostic test for trastuzumab [Herceptin]. And that’s disappointing. I think that is 20-year-old technology and we can do better. But even if we want to use the 20- or 40-year-old DAB-based technology, we should still be standardizing it and having a mechanism for standardization and having defined thresholds.”

As future FDA submissions come in, Dr. Rimm hopes that “even if they’re not quantitated, they can be standardized as to where the thresholds occur, so that we can be sure we deliver the best possible care to patients. And in the interim, I think we, as pathologists, will have to do that standardization with an LDT to be sure we’re giving our best results.”

Dr. Taylor warns that there is only a limited number of labs in the country and in the world that will be able to produce these LDTs, because of the complexity. “The FDA has already said in a position paper that it believes it may have to regulate LDTs to some extent. And what that will mean is that in the validation process, your own LDT will start to approach what is required for an FDA-approved test. And most labs are in no position to be able to do that.”

“So I think we’re going to come to a blending here, all forced by companion diagnostics. This is in situ proteomics,” Dr. Taylor says. “It’s a new test, essentially. It’s not straightforward immunohistochemistry, but a new test. And I think the fluorescence approach that Dr. Rimm has used has a lot of advantages in relating signal to target in terms of figure out what the best test is and stop comparing it to the pathologists. We should compare it to the best assay we can produce.”

With respect to the PD-L1 problem, Dr. Rimm notes, “I would point out that there is a so-called ‘Blueprint’ for comparison of the different antibodies and the different FDA assays, or potentially FDA-submitted tests anyway, to see how equivalent they are.” Similarly, he adds, the National Comprehensive Cancer Network recently issued a press release describing a multi-institutional study to assess the FDA-approved assay but also including an LDT (the Cell Signaling antibody E1L3N using the Leica Bond staining platform).

He points to a newly published study by his group (McLaughlin J, et al. JAMA Oncol. 2016;2[1]:46–54), finding that objective determination of PD-L1 protein levels in non-small cell lung cancer reveals heterogeneity within tumors and prominent interassay variability or discordance. The authors concluded that future studies measuring PD-L1 quantitatively in patients treated with anti-PD-1 and anti PD-L1 therapies may better address the prognostic or predictive value of these biomarkers. With future rigorous studies, including tissues with known responses to anti-PD-1 and anti-PD-L1 therapies, researchers could determine the optimal assay, PD-L1 antibody, and the best cut point for PD-L1 positivity.

Other work that will probably come out in mid-2016 from Dr. Rimm’s group has shown that expression of PD-L1 is largely bimodal, he says. “That is, there’s a group of patients that express a lot, and then there’s another group of patients that expresses a little or none.”

So time will tell how PD-L1 will be scored. “But if you look at the data from the Merck study and their cut point of greater than 50 percent, or even the cut point from the AstraZeneca studies of greater than 25 percent, you’re really dichotomizing the population into patients who are truly PD-LI positive from patients who are negative or almost negative.”

“Of course, we don’t want to miss patients in that negative to almost-negative group who will respond,” Dr. Rimm says. “On the other hand, we probably will have fairly good specificity and sensitivity with the assay defined by Merck and Dako with 22C3 as was recently published” (Robert C, et al. N Engl J Med. 2015;372[26]:2521–2532).

Many difficulties lie ahead, as researchers try to weigh the merits of different drugs with different approved tests on different platforms, involving different antibodies, Dr. Taylor says. “Does the lab try to set up four different PD-L1s, and if we only have one platform and not another, what do we do about that?” He thinks the tests may often be sent out to larger reference labs or academic centers as a result.

Dr. Rimm confirms that his own lab’s LDT—although literally thousands of PD-L1 tests have been conducted using it—is not yet up and running in the Yale CLIA laboratory, and in the meantime the IHC slides are being sent out to a commercial vendor.

Eventually, Dr. Taylor believes, the pressure of these dilemmas will lead the diagnostics field to develop an immunoassay on tissue sections. “We’ve never been forced to do that before, but once we are, that will produce a huge change in diagnostic capability and research capability.”

Anti–PD-1/PD-L1 therapy of human cancer: past, present, and future

Lieping Chen and  http://www.jci.org/articles/view/80011

The cDNA of programmed cell death 1 (PD-1) was isolated in 1992 from a murine T cell hybridoma and a hematopoietic progenitor cell line undergoing apoptosis (1). Genetic ablation studies showed that deficiencies in PD-1 resulted in different autoimmune phenotypes in various mouse strains (2, 3). PD-1–deficient allogeneic T cells with transgenic T cell receptors exhibited augmented responses to alloantigens, indicating that the PD-1 on T cells plays a negative regulatory role in response to antigen (2).

Several studies contributed to the discovery of the molecules that interact with PD-1. In 1999, the B7 homolog 1 (B7-H1, also called programmed death ligand-1 [PD-L1]) was identified independently from PD-1 using molecular cloning and human expressed-sequence tag database searches based on its homology with B7 family molecules, and it was shown that PD-L1 acts as an inhibitor of human T cell responses in vitro (4). These two independent lines of study merged one year later when Freeman, Wood, and Honjo’s laboratories showed that PD-L1 is a binding and functional partner of PD-1 (5). Next, it was determined that PD-L1–deficient mice (Pdl1 KO mice) were prone to autoimmune diseases, although this strain of mice did not spontaneously develop such diseases (6). It became clear later that the PD-L1/PD-1 interaction plays a dominant role in the suppression of T cell responses in vivo, especially in the tumor microenvironment (7, 8).

In addition to PD-L1, another PD-1 ligand called B7-DC (also known as PD-L2) was also identified by the laboratories of Pardoll (9) and Freeman (10). This PD-1 ligand was found to be selectively expressed on DCs and delivered its suppressive signal by binding PD-1. Mutagenesis studies of PD-L1 and PD-L2 molecules guided by molecular modeling revealed that both PD-L1 and PD-L2 could interact with other molecules in addition to PD-1 and suggested that these interactions had distinct functions (11). The functional predictions from these mutagenesis studies were later confirmed when PD-L1 was found to interact with CD80 on activated T cells to mediate an inhibitory signal (12, 13). This finding came as a surprise because CD80 had been previously identified as a functional ligand for CD28 and cytotoxic T lymphocyte antigen-4 (CTLA-4) (14, 15). PD-L2 was also found to interact with repulsive guidance molecule family member b (RGMb), a molecule that is highly enriched in lung macrophages and may be required for induction of respiratory tolerance (16). With at least five interacting molecules in the PD-1/PD-L1 pathway (referred to as the PD pathway) (Figure 1), further studies will be required to understand the relative contributions of these molecules during activation or suppression of T cells.
The PD pathway. The PD pathway has at least 5 interacting molecules. PD-...

http://dm5migu4zj3pb.cloudfront.net/manuscripts/80000/80011/medium/JCI80011.f1.jpg

The PD pathway.

The PD pathway has at least 5 interacting molecules. PD-L1 and PD-L2, with different expression patterns, were identified as ligands of PD-1, and the interaction of PD-L1 or PD-L2 with PD-1 may induce T cell suppression. PD-L1 was found to interact with B7-1 (CD80) on activated T cells and inhibit T cell activity. PD-L2 has a second receptor, RGMb; initially, this interaction activates T cells, but it subsequently induces respiratory tolerance. PD-L1 on tumor cells can also act as a receptor, and the signal delivered from PD-1 on T cells can protect tumor cells from cytotoxic lysis.

The discovery of the PD pathway did not automatically justify its application to cancer therapy, especially after the initial PD-1–deficient mouse studies, which suggested that PD-1 deficiency increases the incidence of autoimmune diseases (2, 3). In our initial work to characterize PD-L1 and its function, PDL1 mRNA was found to be broadly expressed in various tissues (17). However, normal human tissues seldom express PD-L1 protein on their cell surface, with the exception of tonsil (17), placenta (18), and a small fraction of macrophage-like cells in lung and liver (17), suggesting that, under normal physiological conditions, PDL1 mRNA is under tight posttranscriptional regulation. In sharp contrast, PD-L1 protein is abundantly expressed on the cell surface in various human cancers, as indicated by immunohistochemistry in frozen human tumor sections. Additionally, the pattern of PD-L1 expression was found to be focal rather than diffuse in most human cancers (17). In fact, the majority of in vitro–cultured tumor lines of both human and mouse origin are PD-L1–negative on the cell surface, despite overwhelming PD-L1 signal in specimens that are freshly isolated from patients with cancer (17, 19). This discrepancy was explained by the finding that IFN-γ upregulates PD-L1 on the cell surface of normal tissues and in various tumor lines (7, 17, 19). It was widely thought that IFN-γ typically promotes, rather than suppresses, T cell responses by stimulating antigen processing and presentation machinery (20, 21); therefore, the role of IFN-γ in downregulating immune responses in the tumor microenvironment via induction of PD-L1 was not well accepted until more recently. This finding is vital to our current understanding of the unique immunology that takes place in the tumor microenvironment and provided an important clue that led to the “adaptive resistance” hypothesis (see below) that explains this pathway’s mechanism of action to evade tumor immunity.

Due to the lack of cell surface expression of PD-L1 on most cultured tumor lines, it is necessary to reexpress PD-L1 on the surface using transfection to recapitulate the effects of cell surface PD-L1 in human cancers and to create models to study how tumor-associated PD-L1 interacts with immune cells. We now know that cancer cells and other cells in the tumor microenvironment can upregulate the expression of PD-L1 after encountering T cells, mostly via IFN-γ, which may make the transfection-mediated expression of PD-L1 unnecessary in some tumor models. Nevertheless, our results demonstrated that PD-L1+ human tumor cells could eliminate activated effector T cells (Teffs) via apoptosis in coculture systems, and this effect could be blocked by inclusion of an anti-human PD-L1 mAb (clone 2H1). Next, we generated a hamster mAb (clone 10B5) against mouse PD-L1 to block its interaction with T cells and test its role in tumor immunity in vitro and in vivo. We demonstrated that progressive growth of PD-L1+ murine P815 tumors in syngeneic mice could be suppressed using anti–PD-L1 mAb (17). Altogether, these studies represented the initial attempt at using mAb to block the PD pathway as an approach for cancer therapy. These proof-of-concept studies (17) were confirmed by several subsequent studies. A study from Nagahiro Minato’s laboratory showed that the J558L mouse myeloma line constitutively expressed high levels of cell surface PD-L1 and the growth of these cells in syngeneic BALB/c mice could be partially suppressed by administering anti–PD-L1 mAb (22). Our laboratory showed that regression of progressively growing squamous cell carcinomas in syngeneic mice could also be suppressed using a combination of adoptively transferred tumor-draining lymphocytes and anti–PD-L1 mAb (23). Furthermore, the Zou laboratory demonstrated that ovarian cancer–infiltrating human T cells could be activated in vitro using DCs, which showed enhanced activity in the presence of anti–PD-L1 mAb; upon transfer, these cells could eliminate established human ovarian cancers in immune-deficient mice (24). These early studies established the concept that the PD pathway could be used by tumors to escape immune attack in the tumor microenvironment. More importantly, these studies built a solid foundation for the development of anti-PD therapy for the treatment of human cancers.  …..

Anti-PD therapy has taken center stage in immunotherapies for human cancer, especially for solid tumors. This therapy is distinct from the prior immune therapeutic agents, which primarily boost systemic immune responses or generate de novo immunity against cancer; instead, anti-PD therapy modulates immune responses at the tumor site, targets tumor-induced immune defects, and repairs ongoing immune responses. While the clinical success of anti-PD therapy for the treatment of a variety of human cancers has validated this approach, we are still learning from this pathway and the associated immune responses, which will aid in the discovery and design of new clinically applicable approaches in cancer immunotherapy.


PD-1 Pathway Inhibitors: Changing the Landscape of Cancer Immunotherapy

Dawn E. Dolan, PharmD, and Shilpa Gupta, MD

Background: Immunotherapeutic approaches to treating cancer have been evaluated during the last few decades with limited success. An understanding of the checkpoint signaling pathway involving the programmed death 1 (PD-1) receptor and its ligands (PD-L1/2) has clarified the role of these approaches in tumor-induced immune suppression and has been a critical advancement in immunotherapeutic drug development. Methods: A comprehensive literature review was performed to identify the available data on checkpoint inhibitors, with a focus on anti–PD-1 and anti–PD-L1 agents being tested in oncology. The search included Medline, PubMed, the ClinicalTrials.gov registry, and abstracts from the American Society of Clinical Oncology meetings through April 2014. The effectiveness and safety of the available anti–PD-1 and anti–PD-L1 drugs are reviewed. Results: Tumors that express PD-L1 can often be aggressive and carry a poor prognosis. The anti–PD-1 and anti–PD-L1 agents have a good safety profile and have resulted in durable responses in a variety of cancers, including melanoma, kidney cancer, and lung cancer, even after stopping treatment. The scope of these agents is being evaluated in various other solid tumors and hematological malignancies, alone or in combination with other therapies, including other checkpoint inhibitors and targeted therapies, as well as cytotoxic chemotherapy. Conclusions: The PD-1/PD-L1 pathway in cancer is implicated in tumors escaping immune destruction and is a promising therapeutic target. The development of anti–PD-1 and anti–PD-L1 agents marks a new era in the treatment of cancer with immunotherapies. Early clinical experience has shown encouraging activity of these agents in a variety of tumors, and further results are eagerly awaited from completed and ongoing studies.

……

Role of PD-1/PD-L1 Pathway PD-1 is an immunoinhibitory receptor that belongs to the CD28 family and is expressed on T cells, B cells, monocytes, natural killer cells, and many tumor-infiltrating lymphocytes (TILs)10; it has 2 ligands that have been described (PD-L1 [B7H1] and PD-L2 [B7-DC]).11 Although PD-L1 is expressed on resting T cells, B cells, dendritic cells, macrophages, vascular endothelial cells, and pancreatic islet cells, PD-L2 expression is seen on macrophages and dendritic cells alone.10 Certain tumors have a higher expression of PD-L1.12 PD-L1 and L2 inhibit T-cell proliferation, cytokine production, and cell adhesion.13 PD-L2 controls immune T-cell activation in lymphoid organs, whereas PD-L1 appears to dampen T-cell function in peripheral tissues.14 PD-1 induction on activated T cells occurs in response to PD-L1 or L2 engagement and limits effector T-cell activity in peripheral organs and tissues during inflammation, thus preventing autoimmunity. This is a crucial step to protect against tissue damage when the immune system is activated in response to infection.15-17 Blocking this pathway in cancer can augment the antitumor immune response.18 Like the CTLA-4, the PD-1 pathway down-modulates Tcell responses by regulating overlapping signaling proteins that are part of the immune checkpoint pathway; however, they function slightly differently.14,16 Although the CTLA-4 focuses on regulating the activation of T cells, PD-1 regulates effector T-cell activity in peripheral tissues in response to infection or tumor progression.16 High levels of CTLA-4 and PD-1 are expressed on regulatory T cells and these regulatory T cells and have been shown to have immune inhibitory activity; thus, they are important for maintaining self-tolerance.16 The role of the PD-1 pathway in the interaction of tumor cells with the host immune response and the PD-L1 tumor cell expression may provide the basis for enhancing immune response through a blockade of this pathway.16 Drugs targeting the PD-1 pathway may provide antitumor immunity, especially in PD-L1 positive tumors. Various cancers, such as melanoma, hepatocellular carcinoma, glioblastoma, lung, kidney, breast, ovarian, pancreatic, and esophageal cancers, as well as hematological malignancies, have positive PD-L1 expression, and this expression has been correlated with poor prognosis.8,19 Melanoma and kidney cancer are prototypes of immunogenic tumors that have historically been known to respond to immunotherapeutic approaches with interferon alfa and interleukin 2. The CTLA-4 antibody ipilimumab is approved by the US Food and Drug Administration for use in melanoma. Clinical activity of drugs blocking the PD-1/PD-L1 pathway has been demonstrated in melanoma and kidney cancer.20-24 In patients with kidney cancer, tumor, TIL-associated PD-L1 expression, or both were associated with a 4.5-fold increased risk of mortality and lower cancer-specific survival rate, even after adjusting for stage, grade, and performance status.18,19,25,26 A correlation between PD-L1 expression and tumor growth has been described in patients with melanoma, providing the rationale for using drugs that block the PD-1/PD-L1 pathway.19,27 Historically, immunotherapy has been ineffective in cases of non–small-cell lung cancer (NSCLC), which has been thought to be a type of nonimmunogenic cancer; nevertheless, lung cancer can evade the immune system through various complex mechanisms.28 In patients with advanced lung cancer, the peripheral and tumor lymphocyte counts are decreased, while levels of regulatory T cells (CD4+), which help suppress tumor immune surveillance, have been found at higher levels.29-32 Immune checkpoint pathways involving the CTLA-4 or the PD-1/PD-L1 are involved in regulating T-cell responses, providing the rationale for blocking this pathway in NSCLC with antibodies against CTLA-4 and the PD-1/PD-L1 pathway.32 Triple negative breast cancer (TNBC) is an aggressive subset of breast cancer with limited treatment options. PD-L1 expression has been reported in patients with TNBC. When PD-L1 expression was evaluated in TILs, it correlated with higher grade and larger-sized tumors.33 Tumor PD-L1 expression also correlates with the infiltration of T-regulatory cells in TNBC, findings that suggest the role of PD-L1–expressing tumors and the PD-1/PD-L1–expressing TILs in regulating immune response in TNBC.34

…….

Preclinical evidence exists for the complementary roles of CTLA-4 and PD-1 in regulating adaptive immunity, and this provides rationale for combining drugs targeting these pathways.44-46 Paradoxically and originally believed to be immunosuppressive, new data allow us to recognize that cytotoxic agents can antagonize immunosuppression in the tumor microenvironment, thus promoting immunity based on the concept that tumor cells die in multiple ways and that some forms of apoptosis may lead to an enhanced immune response.8,15 For example, nivolumab was combined with ipilimumab in a phase 1 trial of patients with advanced melanoma.46 The combination had a manageable safety profile and produced clinical activity in the majority of patients, with rapid and deep tumor regression seen in a large proportion of patients. Based on the results of this study, a phase 3 study is being undertaken to evaluate whether this combination is better than nivolumab alone in melanoma (NCT01844505). Several other early-phase studies are underway to explore combinations of various anti–PD-1/PD-L1 drugs with other therapies across a variety of tumor types (see Tables 1 and 2), possibly paving the way for future combination studies.


Development of PD-1/PD-L1 Pathway in Tumor Immune Microenvironment and Treatment for Non-Small Cell Lung Cancer

Jiabei He, Ying Hu, Mingming Hu & Baolan Li

Lung cancer is currently the leading cause of cancer-related death in worldwide, non-small cell lung cancer (NSCLC) accounts for about 85% of all lung cancers. Surgery, platinum-based chemotherapy, molecular targeted agents and radiotherapy are the main treatment of NSCLC. With the strategies of treatment constantly improving, the prognosis of NSCLC patients is not as good as before, new sort of treatments are needed to be exploited. Programmed death 1 (PD-1) and its ligand PD-L1 play a key role in tumor immune escape and the formation of tumor microenvironment, closely related with tumor generation and development. Blockading the PD-1/PD-L1 pathway could reverse the tumor microenvironment and enhance the endogenous antitumor immune responses. Utilizing the PD-1 and/or PD-L1 inhibitors has shown benefits in clinical trials of NSCLC. In this review, we discuss the basic principle of PD-1/PD-L1 pathway and its role in the tumorigenesis and development of NSCLC. The clinical development of PD-1/PD-L1 pathway inhibitors and the main problems in the present studies and the research direction in the future will also be discussed.

Lung cancer is currently the leading cause of cancer-related death in the worldwide. In China, the incidence and mortality of lung cancer is 5.357/10000, 4.557/10000 respectively, with nearly 600,000 new cases every year1. Non-small cell lung cancer (NSCLC) accounts for about 85% of all lung cancers, the early symptoms of patients with NSCLC are not very obvious, especially the peripheral lung cancer. Though the development of clinic diagnostic techniques, the majority of patients with NSCLC have been at advanced stage already as they are diagnosed. Surgery is the standard treatment in the early stages of NSCLC, for the advanced NSCLC, the first-line therapy is platinum-based chemotherapy. In recent years, patients with specific mutations may effectively be treated with molecular targeted agents initially. The prognosis of NSCLC patients is still not optimistic even though the projects of chemotherapy as well as radiotherapy are continuously ameliorating and the launch of new molecular targeted agents is never suspended, the five-year survival rate of NSCLC patients is barely more than 15%2, the new treatment is needed to be opened up.

During the last few decades, significant efforts of the interaction between immune system and immunotherapy to NSCLC have been acquired. Recent data have indicated that the lack of immunologic control is recognized as a hallmark of cancer currently. Programmed death-1 (PD-1) and its ligand PD-L1 play a key role in tumor immune escape and the formation of tumor microenvironment, closely related with tumor generation and development. Blockading the PD-1/PD-L1 pathway could reverse the tumor microenvironment and enhance the endogenous antitumor immune responses.

In this review, we will discuss the PD-1/PD-L1 pathway from the following aspects: the basic principle of PD-1/PD-L1 pathway and its role in the tumorigenesis and development of NSCLC, the clinical development of several anti-PD-1 and anti-PD-L1 drugs, including efficacy, toxicity, and application as single agent, or in combination with other therapies, the main problems in the present studies and the research direction in the future.


Cancer as a chronic, polygene and often inflammation-provoking disease, the mechanism of its emergence and progression is very complicated. There are many factors which impacted the development of the disease, such as: environmental factors, living habits, genetic mutations, dysfunction of the immune system and so on. At present, increasing evidence has revealed that the development and progression of tumor are accompanied by the formation of special tumor immune microenvironment. Tumor cells can escape the immune surveillance and disrupt immune checkpoint of host in several methods, therefore, to avoid the elimination from the host immune system. Human cancers contain a number of genetic and epigenetic changes, which can produce neoantigens that are potentially recognizable by the immune system3, thus trigger the body’s T cells immune response. The T cells of immune system recognize cancer cells as abnormal primarily, generate a population of cytotoxic T lymphocytes (CTLs) that can traffic to and infiltrate cancers wherever they reside, and specifically bind to and then kill cancer cells. Effective protective immunity against cancer depends on the coordination of CTLs4. Under normal physiological conditions, there is a balance status in the immune checkpoint molecule which makes the immune response of T cells keep a proper intensity and scope in order to minimize the damage to the surrounding normal tissue and avoid autoimmune reaction. However, numerous pathways are utilized by cancers to up-regulate the negative signals through cell surface molecules, thus inhibit T-cell activation or induce apoptosis and promote the progression and metastasis of cancers5. Increasing experiments and clinical trails show that immunotherapeutic approaches utilizing antagonistic antibodies to block checkpoint pathways, can release cancer inhibition and facilitate antitumor activity, so as to achieve the purpose of treating cancer.

The present research of immune checkpoint molecules are mainly focus on cytotoxic T lymphocyte-associated antigen 4 (CLTA-4), Programmed death-1 (PD-1) and its ligands PD-L1 (B7H1) and PD-L2 (B7-DC). CTLA-4 regulates T cell activity in the early stage predominantly, and PD-1 mainly limits the activity of T-cell in the tumor microenvironment at later stage of tumor growth6. Utilizing the immune checkpoint blockers to block the interactions between PD-1 and its ligands has shown benefits in clinical trials, including the NSCLC patients. PD-1 and its ligands have been rapidly established as the currently most important breakthrough targets in the development of effective immunotherapy.

PD-1/PD-L1 pathway and its expression, regulation

PD-1 is a type 1 trans-membrane protein that encoded by the PDCD1 gene7. It is a member of the extended CD28/CTLA-4 immunoglobulin family and one of the most important inhibitory co-receptors expressed by T cells. The structure of the PD-1 includes an extracellular IgV domain, a hydrophobic trans-membrane region and an intracellular domain. The intracellular tail includes separate potential phosphorylation sites that are located in the immune receptor tyrosine-based inhibitory motif (ITIM) and in the immunoreceptor tyrosine-based switch motif (ITSM). Mutagenetic researches indicated that the activated ITSM is essential for the PD-1 inhibitory effect on T cells8. PD-1 is expressed on T cells, B cells, monocytes, natural killer cells, dendritic cells and many tumor-infiltrating lymphocytes (TILs)9. In addition, the research of Francisoet et al. showed that PD-1 was also expressed on regulatory T cells (Treg) and able to facilitate the proliferation of Treg and restrain immune response10.

PD-1 has two ligands: PD-L1 (also named B7-H1; CD274) and PD-L2 (B7-DC; CD273), that are both coinhibitory. PD-L1 is expressed on resting T cells, B cells, dendritic cells, macrophage, vascular endothelial cells and pancreatic islet cells. PD-L2 expression is seen on macrophages and dendritic cells alone and is far less prevalent than PD-L1 across tumor types. It shows much more restricted expression because of its more restricted tissue distribution. Differences in expression patterns suggest distinct functions in immune regulation across distinct cell types. The restricted expression of PD-L2, largely to antigen-presenting cells, is consistent with a role in regulating T-cell priming or polarization, whereas broad distribution of PD-L1 suggests a more general role in protecting peripheral tissues from excessive inflammation.

PD-L1 is expressed in various types of cancers, especially in NSCLC11,12, melanoma, renal cell carcinoma, gastric cancer, hepatocellular as well as cutaneous and various leukemias, multiple myeloma and so on13,14,15. It is present in the cytoplasm and plasma membrane of cancer cells, but not all cancers or all cells within a cancer express PD-L116,17. The expression of PD-L1 is induced by multiple proinflammatory molecules, including types I and II IFN-γ, TNF-α, LPS, GM-CSF and VEGF, as well as the cytokines IL-10 and IL-4, with IFN-γ being the most potent inducer18,19. IFN-γ and TNF-α are produced by activated type 1 T cells, and GM-CSF and VEGF are produced by a variety of cancer stromal cells, the tumor microenvironment upregulates PD-L1 expression, thereby, promotes immune suppression. This latter effect is called “adaptive immune resistance”, because the tumor protects itself by inducing PD-L1 in response to IFN-γ produced by activated T cells17. PD-L1 is regulated by oncogenes, also known as the inherent immune resistance. PD-L1 expression is suppressed by the tumor suppressor gene: PTEN (phosphatase and tension homolog deleted on chromosome ten) gene. Cancer cells frequently contain mutated PTEN, which can activate the S6K1 gene, thus results in PD-L1 mRNA to polysomes increase greatly20, hence increases the translation of PD-L1 mRNA and plasma membrane expression of PD-L1. Parsa et al.’s research also demonstrated that neuroglioma with PTEN gene deletion regulate PD-L1 expression at the translational level by activating the PI3K/AKT downstream mTOR-S6K1signal pathway and, hence increase the PD-L1 expression21. Micro-RNAs also translationally regulate PD-L1 expression. MiRNA-513 is complementary to the 3′ untranslated region of PD-L1 and prevents PD-L1 mRNA translation22. In addition, a later literature reported that in the model of melanoma, the up-regulation of PD-L1 is closely related to the CD8 T cell, independent of regulation by oncogenes13. Noteworthily, the PD-L1 can bind to T cell expressed CD80, and at this point CD80 is a receptor instead of ligand to transmit negative regulated signals23.


PD-1/PD-L1 mediate immune suppression by multiple mechanisms

Like the CTLA-4, the PD-1/PD-L1 pathway down-modulates T-cell response by regulating overlapping signal proteins in the immune checkpoint pathway. However, their functions are slightly different24. The CTLA-4 focuses on regulating the activation of T cells, while PD-1 regulates effector T-cell activity in peripheral tissues in response to infection or tumor progression25. Tregs that high-level expression of PD-1 have been shown to have immune inhibitory activity, thus, they are important for maintaining self-tolerance. In normal human bodies, this is a crucial step to protect against tissue damage when the immune system is activated in response to infection26. However, in response to immune attack, cancer cells overexpress PD-L1 and PD-L2. They bind to PD-1 receptor on T cells, inhibiting the activation of T-cells, thus suppressing T-cell attack and inducing tumor immune escape. Thus tumor cells effectively form a suitable tumor microenvironment and continue to proliferate27. PD-1/PD-L1 pathway regulates immune suppression by multiple mechanisms, specific performance of the following: ① Induce apoptosis of activated T cells: PD-1 reduces T cell survival by impacting apoptotic genes. During T cell activation, CD28 ligation sustains T cell survival by driving expression of the antiapoptotic gene Bcl-xL. PD-1 prevents Bcl-xL expression by inhibiting PI3K activation, which is essential for upregulation of Bcl-xL. Early studies demonstrated that PD-L1+ murine and human tumor cells induce apoptosis of activated T cells and that antibody blocking of PD-L1 can decrease the apoptosis of T cells and facilitate antitumor immunity28,16. ② Facilitate T cell anergy and exhaustion: A research shown that the occurrence of tumor is associated with chronic infection29. According to the study of chronic infection, PD-1 overexpressed on the function exhausted T cells, blocking the PD-1/PD-L1 pathway can restore the proliferation, secretion and cytotoxicity30. In addition, later research demonstrated that the exhaustion of TILs in the tumor microenvironment is closely related to the PD-L1 expression of tumor cells, myeloid cells derived from tumor31. ③ Enhance the function of regulatory T cells: PD-L1 can promote the generation of induced Tregs by down-regulating the mTOR, AKT, S6 and the phosphorylation of ERK2 and increasing PTEN, thus restrain the activity of effector T-cell32. Blocking the PD-1/PD-L1 pathway can increase the function of effector CD8 T-cell and inhibt the function of Tregs, bone marrow derived inhibition cells, thus enhance the anti-tumor response. ④ Inhibit the proliferation of T cells: PD-1 ligation also prevents phosphorylation of PKC-theta, which is essential for IL-2 production33, and arrests T cells in the G1 phase, blocking proliferation. PD-1 mediates this effect by activating Smad3, a factor that arrests cycling34. ⑤ Restrain impaired T cell activation and IL-2 production: PD-1/PD-L1 blocks the downstream signaling events triggered by Ag/MHC engagement of the TCR and co-stimulation through CD28, resulting in impaired T cell activation and IL-2 production. Signaling through the TCR requires phosphorylation of the tyrosine kinase ZAP70. PD-1 engagement reduces the phosphorylation of ZAP70 and, hence, inhibits downstream signaling events. In addition, signaling through PD-1 also prevents the conversion of functional CD8+ T effector memory cells into CD8+ central memory cells35 and, thus, reduces long-term immune memory that might protect against future metastatic disease. PD-L1 also promotes tumor progression by reversing signaling through CD80 into T cells. CD80-PD-L1 interactions restrain self-reactive T cells in an autoimmune setting36, therefore, their inhibition may facilitate antitumor immunity.

Researches on the mechanism of PD-1/PD-L1 pathway mediating immune escape are still ongoing, especially the mechanism of PD-L2 is still unclear. These researches provide the theoretical basis and research direction for the further immunotherapy targets research.


Anti-PD-1 antibodies

Nivolumab

Nivolumab (BMS-936558, Brand name: Opdivo) is a human monoclonal IgG4 antibody that essentially lacks detectable antibody-dependent cellular cytotoxicity (ADCC). Inhibition by monoclonal antibody of PD-1 on CD8+ TILs within lung cancers can restore cytokine secretion and T-cell proliferation48. Results of a larger phase I study in 296 patients (236 patients evaluated) reported that the objective response (complete or partial responses) of patients with NSCLC was 18%. A total of 65% of responders had durable responses lasting for more than 1 year. Stable disease lasting 24 weeks was seen in patients with NSCLC. PD-L1expression was tested in 42 patients: 9 of 25(36%) patients whose PD-L1 expression positive were objectively response to PD-1 blockade treatment, while the remaining 17 nonresponsive patients were negative45.

In another early phase I trial of nivolumab49, an objective response was observed in 22 patients (17%; 95% CI, 11%–25%) in a dose-expansion cohort of 129 previously treated patients with advanced NSCLC. Six additional patients who had an unconventional immune-related response were not included. Moreover, the median duration of response was exceptional for 17 months. Although the median PFS in the cohort was 2.3 months and the median overall survival was 9.9 months, it seemed clear that those who responded had sustained benefit. Specifically, the 2-year overall survival rate was 24%, and many remained in remission after completing 96 weeks of continuous therapy.

Single-agent trials of nivolumab are planning or ongoing on NSCLC (NCT01721759, NCT02066636). In addition, there are clinical randomized trials which focus on the comparison of nivolumab and plain-based combination chemotherapy (NCT02041533, NCT01673867). In March 4, 2015, nivolumab was approved by the US Food and Drug Administration for treatment of patients with metastatic NSCLC (squamous cell carcinoma), when progression of their diseases during or after chemotherapy with platinum-based drugs.

Pembrolizumab

Pembrolizumab (MK-3475) is a highly selective, humanized monoclonal antibody with activity against PD-1 that contains a mutation at C228P designed to prevent Fc-mediated ADCC. It is now in the clinical research phases for patients with advanced solid tumors. Its safety and efficacy were evaluated in a phase I clinical trial of KEYNOTE-001. The best response according of 38 cases of patients which initially accepted pembrolizumab 10 mg/kg q3wwas 21% (based on RECIST1.1 evaluation) and the median PFS of responder still has not reached until 62 weeks. The researchers also found that the antitumor activity of pembrolizumab was associated with the PD-L1expression44,50. The critical values of the expression of PD-L1 will be validated in 300 cases of patients which will soon been rolled into the study.

Clinical trial of pembrolizumab monotherapy is ongoing for patients with NSCLC (NCT01840579). Randomized trials comparing pembrolizumab to combination chemotherapy (NCT02142738) or single-agent docetaxel (NCT01905657) are ongoing in PD-L1 positive patients with NSCLC.

Pidilizumab (CT-011)

Pidilizumab is a humanized IgG-1K recombinant anti-PD-1 monoclonal antibody that has demonstrated antitumor activity in mouse cancer models. In a first-in-human phase I dose-escalation study in patients with only advanced hematologic cancers, there is no clinical trials of NSCLC presently51.


Anti-PD-L1 antibodies

Another therapeutic method based on the PD-1/PD-L1 pathway is by specific binding between antibody and PD-L1, thus preventing its activity. It was speculated that utilizing PD-L1 as therapeutic target maybe accompanied by less toxicity in part by modulating the immune response selectively in the tumor microenvironment. However, since PD-L2 expressed by tumor cells or some other tumor-associated molecules may play a role in mediating PD-1-expressing lymphocytes, it is conceivable that the magnitude of the anti-tumor immune response could also be blunted.

BMS-936559

BMS-936559/MDX1105 is a fully humanized, high affinity, IgG4 monoclonal antibody that react specifically with PD-L1, thus inhibiting the binding of PD-L1 and PD-1, CD80 (which binds not only PD-L1 but also CTLA-4 and CD28). Initial results from a multicenter and dose-escalation phase I trial of 207 patients(including 75 cases of patients with NSCLC) showed durable tumor regression (objective response rate of 6%–17%) and prolonged stabilization of disease (12%–41% at 24weeks) in patients with advanced cancers, including NSCLC, melanoma and kidney cancer. In patients with NSCLC, there were five objective responses (in 4 patients with the nonsquamous subtype and 1 with the squamous subtype) at doses of 3 mg/kg and 10 mg/kg, with response rates of 8% and 16%, respectively. Six additional patients with NSCLC had stable disease lasting at least 24 weeks52.

MPDL3280A

MPDL3280A is a human IgG1 antibody that targets PD-L1. Its Fc component has been engineered to not activate antibody-dependent cell cytotoxicity. In a recently reported phase I study, a 21% response rate was noted in patients with metastatic melanoma, RCC or NSCLC53, including several patients who demonstrated shrinkage of tumor within a few days of initiating treatment.

Fifty-two patients were enrolled in an expansion cohort of the phase I trial of MPDL3280A, 62% of them were heavily pretreated NSCLC (≥3 lines of systemic therapy) and the ORR was 22%54. Analysis of biomarker data from archival tumor samples demonstrated a correlation between PD-L1 status and response and lack of progressive disease55.

MEDI4736

MEDI4736 is a human IgG1 antibody that binds specifically to PD-L1, thus preventing PD-L1 binding to PD-1 and CD80. Interim results from a phase I trial reported no colitis or pneumonitis of any grade, with several durable remissions, including NSCLC patients56. An ongoing phase I dose-escalation study (NCT01693562) of MEDI-4736 in 26 patients, 4 partial responses (3 in patients with NSCLC and 1 with melanoma) were observed and 5 additional patients exhibited lesser degrees of tumor shrinkage. The disease control rate at 12 weeks was 46%57. Expansion cohorts was opened in Sep 2013, 10 mg/kg q2w dose. 151 patients was enrolled so far in the expansion cohorts, tumor shrinkage was reported as early as the first assessment at 6 weeks and among the 13 patients with NSCLC, responses were sustained at 10 or more to 14.9 or more months58. In the NSCLC expansion cohort, the response rate was 16% in 58 evaluable patients and the disease control rate at 12 weeks was 35% with responses seen in all histologic subtypes as well as in a smaller proportion of PD-L1- tumors.

On the basis of the favorable toxicity profile and promising activity in a heavily pretreated NSCLC population, a global Phase III placebo controlled trial using the 10 mg/kg biweekly dose has been launched in Stage III patients who have not progressed following chemo-radiation (NCT02125461). The primary outcome measures are overall survival and progression-free survival.

AMP-224

AMP-224 was a B7-DC-Fc fusion protein which can block the PD-1 receptor competitively59. Some NSCLC patients were included in a first-in-man phase I trial of this fusion protein drug. A dose-dependent reduction in PD-1-high TILs was observed at 4 hours and 2 weeks after drug administration60.


A variety of approaches for combining PD-1/PD-L1 pathway inhibitors with other therapeutic methods have been explored over the past few years in an effort to offer more feasible therapeutic options for clinic to improve treatment outcomes. Approaches have included combinations with other immune checkpoint inhibitors, immunostimulatory cytokines (e.g. IFN-y) cytotoxic chemotherapy, platinum-based chemotherapy, radiotherapy, anti-angiogenic inhibitors, tumor vaccine and small-molecule molecularly targeted therapies many with promising results61,62. Studies indicated that PD-1/PD-L1 pathway inhibitors were most effective when combined with treatments that activating the immune system63.

Preclinical evidence exists for the complementary roles of CTLA-4 and PD-1 in regulating adaptive immunity, and this provides rationale for combining drugs targeting these pathways. In a Phase I study in 46 chemotherapy-naive patients with NSCLC, four cohorts of patients received ipilimumab (3 mg/kg) plus nivolumab for four cycles followed by nivolumab 3 mg/kg intravenously every 2 weeks. The ORR was 22% and did not correlate with PD-L1 status64.

In another Phase I study, 56 patients with advanced NSCLC were assigned based on histology to four cohorts to receive nivolumab (5–10 mg/kg) intravenously every 3 weeks plus one of four concurrent standard “platinum doublet” chemotherapy regimens. No dose de-escalation was required for dose-limiting toxicity. The ORR was 33–50% across arms and the 1-year OS rates were promising at 59–87%65.

…..

The research of cancer immunotherapy provides a new wide space for cancer treatment (including NSCLC), and compared with other therapeutic method, immunotherapy has its unique advantages, such as: relative safety, effectivity, less and low grade side effect and so on. Especially with the discovery and continued in-depth study of PD-1/PD-L1 pathway in the immune regulation mechanism, many significative conclusions were reported. Data from many clinical trails suggest that some patients with NSCLC have been benefited from the drugs of anti-PD-1 and anti-PD-L1 already. However, summarized what have been discussed above, only a small fraction of patients benefit from PD-1 or PD-L1 inhibitors treatment. But with the continuous studies on biomarker and combined treatment in PD-1/PD-L1 pathway, new research progress will be acquired as well. We will make significant progress on treatment and in control of NSCLC.


Prospects for Targeting PD-1 and PD-L1 in Various Tumor Types     

Table 1: Selected Anti–PD-1 and Anti–PD-L1 Antibodies
Table 2: Selected Adverse Events
Table 3: Selected Clinical Trials for Metastatic Melanoma
Table: 4 Selected Trials for Metastatic Renal Cell Carcinoma
Table 5: Selected Trials for Non–Small-Cell Lung Cancer (NSCLC )
Table 6: Selected Trials for Other Tumor Types

Immune checkpoints, such as programmed death ligand 1 (PD-L1) or its receptor, programmed death 1 (PD-1), appear to be Achilles’ heels for multiple tumor types. PD-L1 not only provides immune escape for tumor cells but also turns on the apoptosis switch on activated T cells. Therapies that block this interaction have demonstrated promising clinical activity in several tumor types. In this review, we will discuss the current status of several anti–PD-1 and anti–PD-L1 antibodies in clinical development and their direction for the future.

Several PD-1 and PD-L1 antibodies are in clinical development (Table 1). Overall, they are very well tolerated; most did not reach dose-limiting toxicity in their phase I studies. As listed in Table 2, no clinically significant difference in adverse event profiles has been seen between anti–PD-1 and anti–PD-L1 antibodies. Slightly higher rates of infusion reactions (11%) were observed with BMS-936559 (anti–PD-L1) than with BMS-96558 (nivolumab). In an early stage of a nivolumab phase I study, there was concern about fatal pneumonitis.[7] It has been hypothesized that PD-1 interaction with PD-L2 expressed on the normal parenchymal cells of lung and kidney provides unique negative signaling that prevents autoimmunity.[8] Thus, anti–PD-1 antibody blockage of such an interaction may remove this inhibition, allowing autoimmune pneumonitis or nephritis. Anti–PD-L1 antibody, however, would theoretically leave PD-1–PD-L2 interaction intact, preventing the autoimmunity caused by PD-L2 blockade. With implementation of an algorithm to detect early signs of pneumonitis and other immune-related adverse events, many of these side effects have become manageable. However, it does require discerning clinical attention to detect potentially fatal side effects. In terms of antitumor activity, both anti–PD-1 and anti–PD-L1 antibodies have shown responses in overlapping multiple tumor types. Although limited to a fraction of patients, most responses, when observed, were rapid and durable.

– See more at: http://www.cancernetwork.com/oncology-journal/prospects-targeting-pd-1-and-pd-l1-various-tumor-types#sthash.an8uOYLi.dpuf


Immune Checkpoint Blockade in Cancer Therapy

Michael A. Postow, Margaret K. Callahan and Jedd D. Wolchok
http://jco.ascopubs.org/content/early/2015/01/20/JCO.2014.59.4358.full
 http://dx.doi.org:/10.1200/JCO.2014.59.4358

Immunologic checkpoint blockade with antibodies that target cytotoxic T lymphocyte–associated antigen 4 (CTLA-4) and the programmed cell death protein 1 pathway (PD-1/PD-L1) have demonstrated promise in a variety of malignancies. Ipilimumab (CTLA-4) and pembrolizumab (PD-1) are approved by the US Food and Drug Administration for the treatment of advanced melanoma, and additional regulatory approvals are expected across the oncologic spectrum for a variety of other agents that target these pathways. Treatment with both CTLA-4 and PD-1/PD-L1 blockade is associated with a unique pattern of adverse events called immune-related adverse events, and occasionally, unusual kinetics of tumor response are seen. Combination approaches involving CTLA-4 and PD-1/PD-L1 blockade are being investigated to determine whether they enhance the efficacy of either approach alone. Principles learned during the development of CTLA-4 and PD-1/PD-L1 approaches will likely be used as new immunologic checkpoint blocking antibodies begin clinical investigation.

CTLA-4 was the first immune checkpoint receptor to be clinically targeted (Fig 1) Normally, after T-cell activation, CTLA-4 is upregulated on the plasma membrane where it functions to downregulate T-cell function through a variety of mechanisms, including preventing costimulation by outcompeting CD28 for its ligand, B7, and also by inducing T-cell cycle arrest.1–5 Through these mechanisms and others, CTLA-4 has an essential role in maintaining normal immunologic homeostasis, as evidenced by the fact that mice deficient in CTLA-4 die from fatal lymphoproliferation.6,7 Recognizing the role of CTLA-4 as a negative regulator of immunity, investigators led studies demonstrating that antibody blockade of CTLA-4 could result in antitumor immunity in preclinical models.8,9

Fig 1.

IMAGE SOURCE:

http://ascopubs.org/doi/figure/10.1200/JCO.2014.59.4358

Article SOURCE:

http://jco.ascopubs.org/content/early/2015/01/20/JCO.2014.59.4358/F1.medium.gif

Fig 1.

The cytotoxic T lymphocyte–associated antigen 4 (CTLA-4) immunologic checkpoint. T-cell activation requires antigen presentation in the context of a major histocompatibility complex (MHC) molecule in addition to the costimulatory signal achieved when B7 on an antigen-presenting cell (dendritic cell shown) interacts with CD28 on a T cell. Early after activation, to maintain immunologic homeostasis, CTLA-4 is translocated to the plasma membrane where it downregulates the function of T cells.

On the basis of this preclinical rationale, two antibodies targeting CTLA-4, ipilimumab (Bristol-Myers Squibb, Princeton, NJ) and tremelimumab (formerly Pfizer, currently MedImmune/AstraZeneca, Wilmington, DE), entered clinical development. Early reports of both agents showed durable clinical responses in some patients.10–12Unfortunately, despite a proportion of patients experiencing a durable response, tremelimumab did not statistically significantly improve overall survival, which led to a negative phase III study comparing tremelimumab to dacarbazine/temozolomide in patients with advanced melanoma.13 It is possible that the lack of an overall survival benefit was a result of the crossover of patients treated with chemotherapy to an expanded access ipilimumab program or a result of the dosing or scheduling considerations of tremelimumab.

Ipilimumab, however, was successful in improving overall survival in two phase III studies involving patients with advanced melanoma.14,15 Although the median overall survival was only improved by several months in each of these studies, landmark survival after treatment initiation favored ipilimumab; in the first phase III study, 18% of patients were alive after 2 years compared with 5% of patients who received the control treatment of gp100 vaccination.14 More recently reported pooled data from clinical trials of ipilimumab confirm that approximately 20% of patients will have long-term survival of at least 3 years after ipilimumab therapy, with the longest reported survival reaching 10 years.16–18

For patients with other malignancies, CTLA-4 antibody therapy has also shown some benefits. Ipilimumab, in combination with carboplatin and paclitaxel in a phased treatment schedule, showed improved progression-free survival compared with carboplatin and paclitaxel alone for patients with non–small-cell lung cancer.19Several patients with pancreatic cancer had declines in CA 19-9 when ipilimumab was given with GVAX (Aduro, Berkeley, CA),20and ipilimumab has also resulted in responses in patients with prostate cancer.21 Unfortunately, a phase III study in patients with castrate-resistant prostate cancer who experienced progression on docetaxel chemotherapy demonstrated that after radiotherapy, ipilimumab did not improve overall survival compared with placebo.22 Although this study is felt to have been a negative study, ipilimumab may have conferred a benefit to patients with favorable prognostic features, such as the absence of visceral metastases, but this requires further study. Another CTLA-4–blocking antibody, tremelimumab, has shown responses in patients with mesothelioma, and ongoing trials are under way.23

CTLA-4 blockade has also been administered together with other immunologic agents, such as the indoleamine 2,3-dioxygenase inhibitor INCB024360,106 the oncolytic virus talimogene laherparepvec,107 and granulocyte-macrophage colony-stimulating factor,108 with encouraging early results. We expect subsequent studies involving engineered T-cell–based therapies and checkpoint blockade.

Other promising data involve CTLA-4 combinations with PD-1 blockade. A phase I study of ipilimumab and nivolumab in patients with melanoma resulted in a high durable response rate and impressive overall survival compared with historical data.109,110Although the most recently reported grade 3 or 4 toxicity rate in patients with melanoma was 64%, which is higher than either ipilimumab or nivolumab individually,111 the vast majority of these irAEs were asymptomatic laboratory abnormalities of unclear clinical consequence. For example, elevations in amylase or lipase were reported in 21% of patients, none of whom met clinical criteria for a diagnosis of pancreatitis. The rate of grade 3 or 4 diarrhea was 7%, which is approximately similar to the rate of grade 3 or 4 diarrhea with ipilimumab monotherapy at 3 mg/kg. Whether ipilimumab and nivolumab improve overall survival compared with either nivolumab or ipilimumab alone remains the subject of an ongoing phase III randomized trial, and investigations of the combination of ipilimumab and nivolumab (and tremelimumab and MEDI4736) are ongoing in many other cancers.

Immunotherapy with checkpoint-blocking antibodies targeting CTLA-4 and PD-1/PD-L1 has improved the outlook for patients with a variety of malignancies. Despite the promise of this approach, many questions remain, such as the optimal management of irAEs and how best to evaluate combination approaches to determine whether they will increase the efficacy of CTLA-4 or PD-1/PD-L1 blockade alone. Themes from the experience with CTLA-4 and PD-1/PD-L1 will likely be relevant for investigations of novel immunologic checkpoints in the future.

This is a very important article, Dr. Larry.

It fits so beautiful with our work on Molecules in Development Table.

Thank you


This image depicts the process of metastasis in a mouse tumor, where tumor cells (green) have helped to reorganize the collagen into aligned fibers (blue) that provide the structural support for motility. This helps the tumor cells to enter blood vessels (red), ultimately leading to the formation of metastases in other organs.

http://news.mit.edu/sites/mit.edu.newsoffice/files/styles/news_article_image_top_slideshow/public/images/2016/MIT-Cancer-Migration-1_0.jpg?itok=aEOCRQpn

This image depicts the process of metastasis in a mouse tumor, where tumor cells (green) have helped to reorganize the collagen into aligned fibers (blue) that provide the structural support for motility. This helps the tumor cells to enter blood vessels (red), ultimately leading to the formation of metastases in other organs.  Image: Madeleine Oudin and Jeff Wyckoff

Paving the way for metastasis

Cancer cells remodel their environment to make it easier to reach nearby blood vessels.

Anne Trafton | MIT News Office     March 15, 2016


A new study from MIT reveals how cancer cells take some of their first steps away from their original tumor sites. This spread, known as metastasis, is responsible for 90 percent of cancer deaths.

Studying mice, the researchers found that cancer cells with a particular version of the Mena protein, called MenaINV (invasive), are able to remodel their environment to make it easier for them to migrate into blood vessels and spread through the body. They also showed that high levels of this protein are correlated with metastasis and earlier deaths among breast cancer patients.

Finding a way to block this protein could help to prevent metastasis, says Frank Gertler, an MIT professor of biology and a member of the Koch Institute for Integrative Cancer Research.

“That’s something that I think would be very promising, because we know that when we genetically remove MenaINV, the tumors become nonmetastatic,” says Gertler, who is the senior author of a paper describing the findings in the journal Cancer Discovery.

Madeleine Oudin, a postdoc at the Koch Institute, is the paper’s lead author.

On the move

For cancer cells to metastasize, they must first become mobile and then crawl through the surrounding tissue to reach a blood vessel. In the new study, the MIT team found that cancer cells follow the trail of fibronectin, a protein that is part of the “extracellular matrix” that provides support for surrounding cells. Fibronectin is found in particularly high concentrations around the edges of tumors and near blood vessels.

“Cancer cells within a tumor environment are constantly faced with differences in fibronectin concentrations, and they need to be able to move from low to high concentrations to reach the blood vessels,” Oudin says.

MenaINV, an alternative form of the normal Mena protein, is key to this process. MenaINV includes a segment not found in the normal version, and this makes it bind more strongly to a receptor known as alpha-5 integrin, which is found on the surfaces of tumor cells and nearby supporting cells, and recognizes fibronectin.

When MenaINV attaches to this receptor, it promotes the binding of fibronectin to the same receptors. Fibronectin is normally a tangled protein, but when it binds to cell surfaces, it gets stretched out into long bundles. This stimulates the organization of collagen, another extracellular matrix protein, into stiff fibrils that radiate from the edges of the tumor.

This pattern, which is typically seen in tumors that are more aggressive, essentially paves the way for tumor cells to move toward blood vessels.

“If you have curly, coiled collagen, that’s associated with a good outcome, but if it gets realigned into these really straight long fibers, that provides highways for these cells to migrate on,” Oudin says.

In studies of mice, cells with the invasive form of Mena were better able to recognize and crawl toward higher concentrations of fibronectin, moving along the collagen pathways, while cells without MenaINV did not move toward the higher concentrations.

Predicting metastasis

The researchers also looked at data from breast cancer patients and found that high levels of MenaINV and fibronectin are associated with metastasis and earlier death. However, there was no link between the normal version of Mena and earlier death.

Gertler’s lab had previously developed antibodies that can detect the normal and invasive forms of Mena, which are now being developed for testing patient biopsy samples. Such tests could help doctors to determine whether a patient’s tumor is likely to spread or not, and possibly to guide the patient’s treatment. In addition, scientists may be able to develop drugs that inhibit MenaINV, which could be useful for treating cancer or preventing it from metastasizing.

The researchers now hope to study how MenaINV may contribute to other types of cancers. Preliminary studies suggest that it plays a similar role in lung and colon cancers as that seen in breast cancer. They are also investigating how the choice between the two forms of the Mena protein is regulated, and how other proteins found in the extracellular matrix might contribute to cancer cell migration.

Facilitating Tumor Cell Migration

Researchers identify a modified form of a migration-regulating protein in cancer cells that remodels the tumor microenvironment to promote metastasis.
By Catherine Offord | March 16, 2016

Emerging evidence suggests that metastasis—the spread of cancer from one organ or tissue to another—is aided by a significant remodeling of the cancer cells’ surroundings. Now, researchers at MIT have made progress toward understanding the mechanisms involved in this process by highlighting the role of a protein that reorganizes the tumor’s extracellular matrix to facilitate cellular migration into blood vessels. The findings were published yesterday (March 15) in Cancer Discovery.

Using a mouse model, the team showed that a cancer-cell-expressed protein called MenaINV—a mutated, “invasive” form of the cell-migration-modulator Mena—binds more strongly than its normal equivalent to a receptor on tumor and nearby support cells. The binding rearranges fibronectin in the tumor microenvironment, which in turn triggers the reorganization of collagen in the extracellular matrix into linear fibers radiating from the tumor.

This collagen restructuring is key in facilitating the migration of tumor cells to the blood vessels, from where they can disseminate throughout the body.

Tumor cell-driven extracellular matrix remodeling enables haptotaxis during metastatic progression

Madeleine J. Oudin1, Oliver Jonas1, Tatsiana Kosciuk1, Liliane C. Broye1, Bruna C. Guido1, Jeff Wyckoff1, …., James E. Bear2 and Frank B. Gertler1,*
Cancer Discov CD-15-1183  Jan 25, 2016  http://dx.doi.org:/10.1158/2159-8290.CD-15-1183

Fibronectin (FN) is a major component of the tumor microenvironment, but its role in promoting metastasis is incompletely understood. Here we show that FN gradients elicit directional movement of breast cancer cells, in vitro and in vivo. Haptotaxis on FN gradients requires direct interaction between α5β1 integrin and Mena, an actin regulator, and involves increases in focal complex signaling and tumor-cell-mediated extracellular matrix (ECM) remodeling. Compared to Mena, higher levels of the pro-metastatic MenaINV isoform associate with α5, which enables 3D haptotaxis of tumor cells towards the high FN concentrations typically present in perivascular space and in the periphery of breast tumor tissue. MenaINV and FN levels were correlated in two breast cancer cohorts, and high levels of MenaINV were significantly associated with increased tumor recurrence as well as decreased patient survival. Our results identify a novel tumor-cell-intrinsic mechanism that promotes metastasis through ECM remodeling and ECM guided directional migration.


Researchers Find Link Between Death of Tumor-support Cells and Cancer Metastasis       Fri, 02/19/2016
http://www.dddmag.com/news/2016/02/researchers-find-link-between-death-tumor-support-cells-and-cancer-metastasis#.VuatbTol_kI.linkedin

The images show tumors that have metastasized to the lungs (image b) and bones (image d) in mice that had CAFs eliminated after 10 days. (Credit: Biju Parekkadan, Massachusetts General Hospital)

http://www.dddmag.com/sites/dddmag.com/files/20160219-metastasized-cells%20%281%29.jpg

The images show tumors that have metastasized to the lungs (image b) and bones (image d) in mice that had CAFs eliminated after 10 days. (Credit: Biju Parekkadan, Massachusetts General Hospital)

Researchers have discovered that eliminating cells thought to aid tumor growth did not slow or halt the growth of cancer tumors. In fact, when the cancer-associated fibroblasts (CAFs), were eliminated after 10 days, the risk of metastasis of the primary tumor to the lungs and bones of mice increased dramatically. Scientists used bioengineered CAFs equipped with genes that caused those cells to self-destruct at defined moments in tumor progression. The study, published in Scientific Reports on Feb. 19, was conducted by researchers funded by the National Institute of Biomedical Imaging and Bioengineering (NIBIB) at Massachusetts General Hospital (MGH). NIBIB is part of the National Institutes of Health.

What causes cancer to grow and metastasize is not well understood by scientists. CAFs are thought to be fibroblast cells native to the body that cancer cells hijacks and use to sustain their growth. However, because fibroblasts are found throughout the human body, it can be difficult to follow and study cancer effects on these cells.

“This work underscores two important things in solving the puzzle that is cancer,” said Rosemarie Hunziker, Ph.D., program director for Tissue Engineering at NIBIB. “First, we are dealing with a complex disease with so many dimensions that we are really only just beginning to describe it.  Second, this approach shows the power of cell engineering — manipulating a key cell in the cancer environment has led to a significant new understanding of how cancer grows and how it might be controlled in the future.”

Biju Parekkadan, Ph.D., assistant professor of surgery and bioengineering at MGH, and his team designed an experiment with the goal of better understanding the cellular environment in which tumors exist (called tumor microenvironment or TME), and the role of CAFs in tumor growth. In an effort to understand whether targeting CAFs could limit the growth of breast cancer tumors implanted in mice, they bioengineered CAFs with a genetic “kill switch.” The cells were designed to die when exposed to a compound that was not toxic to the surrounding cells.

Parekkadan and his team chose two different stages of tumor growth in which the CAFs were killed off after the tumor was implanted. When the CAFs were eliminated on the third or fourth day, they found no major difference in tumor growth or risk of metastasis compared with the tumors where the CAFs remained. However, there was an increase in tumor-associated macrophages — cells that have been associated with metastasis — in this early stage.

When the team waited to eliminate the CAFs until the 10th or 11th day, they discovered that in addition to the increase in macrophages, the cancer was more likely to spread to the lungs and bones of the mice. The unexpected results from this experiment could spur more research into the role of CAFs in cancer growth and metastasis.

More research may reveal whether or not there is a scientific basis for targeting CAFs for destruction — and if so, the awareness that timing matters when it comes to the response of the tumor. While neither treatment affected the growth of the initial tumor, it is important to understand that most cancer deaths result from metastases to vital organs rather than from the direct effects of the primary tumor.


Read Full Post »

Dopamine-β-Hydroxylase Functional Variants

Curator: Larry H. Bernstein, MD, FCAP


Deep sequencing identifies novel regulatory variants in the distal promoter region of the dopamine-β-hydroxylase gene.

OBJECTIVE:

Dopamine-β-hydroxylase (DBH), an enzyme that converts dopamine into norepinephrine, is a drug target in cardiovascular and neuropsychiatric disorders. We aimed to identify functional variants in this gene by deep sequencing and enzyme phenotyping in an Indian cohort.

MATERIALS AND METHODS:

Targeted resequencing of 12 exons and 10 kb upstream sequences of DBH in healthy volunteers (n=50) was performed using the Ion Personal Genome Machine System. Enzyme quantity and activity in their sera samples were determined by ELISA and ultra performance liquid chromatography, respectively. The association of markers with phenotypes was determined using Matrix eQTL. Global P-values for haplotypes generated using UNPHASED 3.1.5 were graphed using GrASP v.082 beta.

RESULTS:

Of the 49 variants identified, nine were novel (minor allele frequency≥0.01). Though individual markers associated with enzyme quantity did not withstand multiple corrections, a novel distal promoter block driven by rs113249250 (global P=1.5×10) was associated. Of the nine single nucleotide polymorphisms (SNPs) associated with enzyme activity, rs3025369, rs1076151 and rs1611115, all from the upstream region, withstood false discovery rate correction (false discovery rate=0.03, 0.03 and 2.9×10, respectively). Conditioning for rs1611115 identified rs1989787 also to affect activity. Importantly, we report an association of a novel haplotype block distal to rs1076151 driven by rs3025369 (global P=8.9×10) with enzyme activity. This regulatory SNP explained 4.9% of the total 46.1% of variance in DBH activity caused by associated SNPs.

CONCLUSION:

This first study combining deep sequencing and enzyme phenotyping identified yet another regulatory SNP suggesting that regulatory variants may be central in the physiological or metabolic role of this gene of therapeutic and pharmacological relevance.


Correlation of plasma dopamine beta-hydroxylase activity with polymorphisms in DBH gene: a study on Eastern Indian population.

Plasma dopamine beta-hydroxylase activity (plDbetaH) is tightly regulated by the DBH gene and several genetic polymorphisms have been found to independently exert their influence. In the present investigation, association of four DBH polymorphisms, DBH-STR, rs1611115, rs1108580, and rs2519152 with plDbetaH was examined in blood samples from 100 unrelated individuals belonging to the state of West Bengal, Eastern India. Genotypes obtained after PCR amplification and restriction digestion were used for statistical analyses. plDbetaH was measured using a photometric assay and its correlation with the genetic polymorphisms was analyzed using analysis of variance and linear regression. Moderate linkage disequilibrium (LD) was observed between DBH-STR and rs1611115, while rs1108580 and rs2519152 were in strong LD. ‘T’ allele of rs1611115 showed strong negative correlation with plDbetaH, whereas DBH-STR, rs1108580 and rs2519152 had no major effect. Four haplotypes showed significant influence on plDbetaH. This is the first report on the effect of genetic polymorphisms on plDbetaH from the Indian sub-continent. rs1611115 was the only polymorphism that showed substantial control over plDbetaH. Other polymorphisms which did not show individual effects could possibly be part of larger haplotype blocks that carry the functional polymorphisms controlling plDbetaH.
Polymorphisms and low plasma activity of dopamine-beta-hydroxylase in ADHD children.
Attention-deficit Hyperactivity disorder (ADHD) is a multifactorial disorder clinically characterized by inattentiveness, impulsivity and hyperactivity. The occurrence of this disorder is between 3 and 6% of the children population, with boys predominating over girls at a ratio of 3:1 or more. The research of some candidate genes (DRD4, DAT, DRD5, DBH, 5HTT, HTR1B and SNAP25) brought consistent results confirming the heredity of ADHD syndromes. Dopamine-beta-hydroxylase (DBH) is an enzyme responsible for the conversion of dopamine into noradrenaline. Alteration of the dopamine/noradrenaline levels can result in hyperactivity. The DBH protein is released in response to stimulation. DBH activity, derived largely from sympathetic nerves, can be measured in human plasma. Patients with ADHD showed decreased activities of DBH in serum and urine. Low DBH levels correlate indirectly with the seriousness of the hyperkinetic syndrome in children [19,20]. In the DBH gene, the G444A, G910T, C1603T, C1912T, C-1021T, 5 -ins/del and TaqI polymorphisms occur frequently and may affect the function of gene products or modify gene expression and thus influence the progression of ADHD. This article reviews the DBH itself and polymorphisms in the DBH gene that influence the DBH activity in the serum and the CSF level of DBH. All those are evaluated in connection with ADHD.
Candidate gene studies of attention-deficit/hyperactivity disorder.
A growing body of behavioral and molecular genetics literature has indicated that the development of attention-deficit/hyperactivity disorder (ADHD) may be attributed to both genetic and environmental factors. Family, twin, and adoption studies provide compelling evidence that genes play a strong role in mediating susceptibility to ADHD. Molecular genetic studies suggest that the genetic architecture of ADHD is complex, while the handful of genome-wide scans conducted thus far is not conclusive. In contrast, the many candidate gene studies of ADHD have produced substantial evidence implicating several genes in the etiology of the disorder. For the 8 genes for which the same variant has been studied in 3 or more case-control or family-based studies, 7 show statistically significant evidence of association with ADHD based on pooled odds ratios across studies: the dopamine D4 receptor gene (DRD4), the dopamine D5 receptor gene (DRD5), the dopamine transporter gene (DAT), the dopamine beta-hydroxylase gene (DBH), the serotonin transporter gene (5-HTT), the serotonin receptor 1B gene (HTR1B), and the synaptosomal-associated protein 25 gene (SNAP25). Recent pharmacogenetic studies have correlated treatment nonresponse with particular gene markers, while preclinical studies have increased our understanding of gene expression paradigms and potential analogs for human trials. This literature review discusses the relevance and implications of genetic associations with ADHD for clinical practice and future research
Lack of significant association between -1021C–>T polymorphism in the dopamine beta hydroxylase gene and attention deficit hyperactivity disorder.
Recent trends in medications for attention deficit hyperactivity disorder (ADHD) suggest that norepinephrine (NE) deficiency may contribute to the disease etiology. Dopamine beta hydroxylase (DBH) is the key enzyme which converts dopamine to NE and since DBH gene is considered a major quantitative trait locus for plasma DBH activity, genetic polymorphism may lead to altered NE neurotransmission. Several polymorphisms including a 5′ flanking -1021C–>T polymorphism, was reported to be associated with changed DBH activity and an association between -1021C–>T polymorphism with ADHD was observed in Han Chinese children. We have carried out family-based studies with three polymorphisms in the DBH gene, -1021C–>T polymorphism, exon 2*444g/a and intron 5 TaqI RFLP, to explore their association with Indian ADHD cases. Allele and genotype frequency of these polymorphisms in ADHD cases were compared with that of their parents and a control group. Haplotypes obtained were analyzed for linkage disequilibrium (LD). Haplotype-based haplotype relative risk analysis and transmission disequilibrium test showed lack of significant association between transmission of the polymorphisms and ADHD. A haplotype comprising of allele 1 of all polymorphisms showed a slight positive trend towards transmission from parents to ADHD probands. Strong LD was observed between *444g/a and TaqI RFLP in all the groups. However, low D’ values and corresponding log of odds scores in the control group as compared to the ADHD families indicated that, the incidence of the two polymorphisms being transmitted together could be higher in ADHD families.
Association of the dopamine beta hydroxylase gene with attention deficit hyperactivity disorder: genetic analysis of the Milwaukee longitudinal study.
Attention deficit hyperactivity disorder (ADHD) is a highly heritable and common disorder that partly reflects disturbed dopaminergic function in the brain. Recent genetic studies have shown that candidate genes involved in dopamine signaling and metabolism contribute to ADHD susceptibility. We have initiated genetic studies in a unique cohort of 158 ADHD and 81 control adult subjects who have been followed longitudinally since childhood in the Milwaukee study of ADHD. From this cohort, genetic analysis was performed in 105 Caucasian subjects with ADHD and 68 age and ethnicity-matched controls for the DRD4 exon 3 VNTR, the SLC6A3 (DAT1) 3′ UTR VNTR, dopamine beta hydroxylase (DBH) TaqI A polymorphism, and the DBH GT microsatellite repeat polymorphism that has been quantitatively associated with serum levels of DBH activity, but not previously studied in ADHD. Results indicate a significant association between the DBH TaqI A1 allele and ADHD (P = 0.018) with a relative risk of 1.33. The DBH GT repeat 4 allele, which is associated with high serum levels of DBH, occurred more frequently in the ADHD group than controls, but the difference did not reach statistical significance. Associations were not found with the SLC6A3 10 repeat or DRD4 7 repeat alleles. These results indicate that the DBH TaqI A allele, or another polymorphism in linkage disequilibrium with this allele, may confer increased susceptibility towards ADHD.
Polymorphisms of the dopamine transporter gene: influence on response to methylphenidate in attention deficit-hyperactivity disorder.
Attention deficit-hyperactivity disorder (ADHD) is a very common and heterogeneous childhood-onset psychiatric disorder, affecting between 3% and 5% of school age children worldwide. Although the neurobiology of ADHD is not completely understood, imbalances in both dopaminergic and noradrenergic systems have been implicated in the origin and persistence of core symptoms, which include inattention, hyperactivity, and impulsivity. The role of a genetic component in its etiology is strongly supported by genetic studies, and several investigations have suggested that the dopamine transporter gene (DAT1; SLC6A3 locus) may be a small-effect susceptibility gene for ADHD. Stimulant medication has a well-documented efficacy in reducing ADHD symptoms. Methylphenidate, the most prescribed stimulant, seems to act mainly by inhibiting the dopamine transporter protein and dopamine reuptake. In fact, its effect is probably related to an increase in extracellular levels of dopamine, especially in brain regions enriched in this protein (i.e. striatum). It is also important to note that dopamine transporter densities seem to be particularly elevated in the brain of ADHD patients, decreasing after treatment with methylphenidate. Altogether, these observations suggest that the dopamine transporter does play a major role in ADHD. Among the several polymorphisms already described in the SLC6A3 locus, a 40 bp variable number of tandem repeats (VNTR) polymorphism has been extensively investigated in association studies with ADHD. Although there are some negative results, the findings from these reports indicate the allele with ten copies of the 40 bp sequence (10-repeat allele) as the risk allele for ADHD. Some investigations have suggested that this polymorphism can be implicated in dopamine transporter gene expression in vitro and dopamine transporter density in vivo, even though it is located in a non-coding region of the SLC6A3 locus. Despite all these data, few studies have addressed the relationship between genetic markers (specifically the VNTR) at the SLC6A3 locus and response to methylphenidate in ADHD patients. A significant effect of the 40 bp VNTR on response to methylphenidate has been detected in most of these reports. However, the findings are inconsistent regarding both the allele (or genotype) involved and the direction of this influence (better or worse response). Thus, further investigations are required to determine if genetic variation due to the VNTR in the dopamine transporter gene is able to predict different levels of clinical response and palatability to methylphenidate in patients with ADHD, and how this information would be useful in clinical practice.
Pharmacogenomics in psychiatry: the relevance of receptor and transporter polymorphisms.
The treatment of severe mental illness, and of psychiatric disorders in general, is limited in its efficacy and tolerability. There appear to be substantial interindividual differences in response to psychiatric drug treatments that are generally far greater than the differences between individual drugs; likewise, the occurrence of adverse effects also varies profoundly between individuals. These differences are thought to reflect, at least in part, genetic variability. The action of psychiatric drugs primarily involves effects on synaptic neurotransmission; the genes for neurotransmitter receptors and transporters have provided strong candidates in pharmacogenetic research in psychiatry. This paper reviews some aspects of the pharmacogenetics of neurotransmitter receptors and transporters in the treatment of psychiatric disorders. A focus on serotonin, catecholamines and amino acid transmitter systems reflects the direction of research efforts, while relevant results from some genome-wide association studies are also presented. There are many inconsistencies, particularly between candidate gene and genome-wide association studies. However, some consistency is seen in candidate gene studies supporting established pharmacological mechanisms of antipsychotic and antidepressant response with associations of functional genetic polymorphisms in, respectively, the dopamine D2 receptor and serotonin transporter and receptors. More recently identified effects of genes related to amino acid neurotransmission on the outcome of treatment of schizophrenia, bipolar illness or depression reflect the growing understanding of the roles of glutamate and γ-aminobutyric acid dysfunction in severe mental illness. A complete understanding of psychiatric pharmacogenomics will also need to take into account epigenetic factors, such as DNA methylation, that influence individual responses to drugs.
Pharmacogenetics of psychotropic drug response.

OBJECTIVE:

Molecular genetic approaches provide a novel method of dissecting the heterogeneity of psychotropic drug response. These pharmacogenetic strategies offer the prospect of identifying biological predictors of psychotropic drug response and could provide the means of determining the molecular substrates of drug efficacy and drug-induced adverse events.

METHOD:

The authors discuss methods issues in executing pharmacogenetic studies, review the first generation of pharmacogenetic studies of psychotropic drug response, and consider future directions for this rapidly evolving field.

RESULTS:

Pharmacogenetics has been most commonly used in studies of antipsychotic drug efficacy, antidepressant drug response, and drug-induced adverse effects. Data from antipsychotic drug studies indicate that polymorphisms within the serotonin 2A and dopamine receptor 2 genes may influence drug efficacy in schizophrenia. Moreover, a growing body of data suggests a relationship between the serotonin transporter gene and clinical effects of the selective serotonin reuptake inhibitors used to treat depression. A significant relationship between genetic variation in the cytochrome P450 system and drug-induced adverse effects may exist for certain medications. Finally, a number of independent studies point to a significant effect of a dopamine D(3) receptor polymorphism on susceptibility to tardive dyskinesia.

CONCLUSIONS:

Initial research into the pharmacogenetics of psychotropic drug response suggests that specific genes may influence phenotypes associated with psychotropic drug administration. These results remain preliminary and will require further replication and validation. New developments in molecular biology, human genomic information, statistical methods, and bioinformatics are ongoing and could pave the way for the next generation of pharmacogenetic studies in psychiatry.

OBJECTIVE: Molecular genetic approaches provide a novel method of dissecting the heterogeneity of psychotropic drug response. These pharmacogenetic strategies offer the prospect of identifying biological predictors of psychotropic drug response and could provide the means of determining the molecular substrates of drug efficacy and drug-induced adverse events. METHOD: The authors discuss methods issues in executing pharmacogenetic studies, review the first generation of pharmacogenetic studies of psychotropic drug response, and consider future directions for this rapidly evolving field. RESULTS: Pharmacogenetics has been most commonly used in studies of antipsychotic drug efficacy, antidepressant drug response, and drug-induced adverse effects. Data from antipsychotic drug studies indicate that polymorphisms within the serotonin 2A and dopamine receptor 2 genes may influence drug efficacy in schizophrenia. Moreover, a growing body of data suggests a relationship between the serotonin transporter gene and clinical effects of the selective serotonin reuptake inhibitors used to treat depression. A significant relationship between genetic variation in the cytochrome P450 system and drug-induced adverse effects may exist for certain medications. Finally, a number of independent studies point to a significant effect of a dopamine D3 receptor polymorphism on susceptibility to tardive dyskinesia. CONCLUSIONS: Initial research into the pharmacogenetics of psychotropic drug response suggests that specific genes may influence phenotypes associated with psychotropic drug administration. These results remain preliminary and will require further replication and validation. New developments in molecular biology, human genomic information, statistical methods, and bioinformatics are ongoing and could pave the way for the next generation of pharmacogenetic studies in psychiatry.

Read Full Post »

Tracking protein expression

Larry H. Bernstein, MD, FCAP, Curator

LPBI


Protein Counting in Single Cancer Cells

Stephanie M. Schubert, Stephanie R. Walter, Mael Manesse, and David R. Walt*
Analytical Chemistry  Anal. Chem., 2016, 88 (5), pp 2952–2957   http://dx.doi.org:/10.1021/acs.analchem.6b00146


Abstract Image


The cell is the basic unit of biology and protein expression drives cellular function. Tracking protein expression in single cells enables the study of cellular pathways and behavior, but requires methodologies sensitive enough to detect low numbers of protein molecules with a wide dynamic range to distinguish unique cells and quantify population distributions. This study presents an ultrasensitive and automated approach for quantifying phenotypic responses with single cell resolution using single molecule array (Simoa) technology. We demonstrate how prostate specific antigen (PSA) expression varies over several orders of magnitude between single prostate cancer cells, and how PSA expression shifts with genetic drift. Single cell Simoa intduces a straightforward process that is capable of detecting both high and low protein expression levels. This technique could be useful for understanding fundamental biology and may eventually enable both earlier disease detection and targeted therapy.


Quanterix’s proprietary Simoa™ technology (named for single molecule array) is based upon the isolation of individual immunocomplexes on paramagnetic beads using standard ELISA reagents. The main difference between Simoa and conventional immunoassays lies in the ability to trap single molecules in femtoliter-sized wells, allowing for a “digital” readout of each individual bead to determine if it is bound to the target analyte or not.

The digital nature of the technique allows an average of 1000x sensitivity increase over conventional assays with CVs <10%.


A. Single protein molecules are captured and labeled on beads using standard ELISA reagents.


B. Tens of thousands of beads – with or without immunoconjugate – are mixed with enzyme substrate and loaded into individual femtoliter-sized wells.


C. The microwells are sealed with oil.


D. Fluorophore concentration in the small sample volume of wells containing the target analyte rapidly reach detectable limits using conventional fluorescence imaging and can be digitally counted.

E. The percentage of beads containing labelled immunocomplexes can be computed at low concentration because they follow a Poisson distribution; at higher concentrations the intensity of the aggregate signal provides an analog measurement.


Clin Chem Lab Med. 2015 Oct 23. pii: /j/cclm.ahead-of-print/cclm-2015-0733/cclm-2015-0733.xml. http://dx.doi.org:/10.1515/cclm-2015-0733. [Epub ahead of print]
Assessing the commutability of reference material formats for the harmonization of amyloid beta measurements.

The cerebrospinal fluid (CSF) amyloid-β (Aβ42) peptide is an important biomarker for Alzheimer’s disease (AD). Variability in measured Aβ42 concentrations at different laboratories may be overcome by standardization and establishing traceability to a reference system. Candidate certified reference materials (CRMs) are validated herein for this purpose.

METHODS:

Commutability of 16 candidate CRM formats was assessed across five CSF Aβ42 immunoassays and one mass spectrometry (MS) method in a set of 48 individual clinical CSF samples. Promising candidate CRM formats (neat CSF and CSF spiked with Aβ42) were identified and subjected to validation across eight (Elecsys, EUROIMMUN, IBL, INNO-BIA AlzBio3, INNOTEST, MSD, Simoa, and Saladax) immunoassays and the MS method in 32 individual CSF samples. Commutability was evaluated by Passing-Bablok regression and the candidate CRM termed commutable when found within the prediction interval (PI). The relative distance to the regression line was assessed.

RESULTS:

The neat CSF candidate CRM format was commutable for almost all method comparisons, except for the Simoa/MSD, Simoa/MS and MS/IBL where it was found just outside the 95% PI. However, the neat CSF was found within 5% relative distance to the regression line for MS/IBL, between 5% and 10% for Simoa/MS and between 10% and 15% for Simoa/MSD comparisons.

CONCLUSIONS:

The neat CSF candidate CRM format was commutable for 33 of 36 method comparisons, only one comparison more than expected given the 95% PI acceptance limit. We conclude that the neat CSF candidate CRM can be used for value assignment of the kit calibrators for the different Aβ42 methods.


Nature Neuroscience18, 1559–1561(2015)    http://dx.doi.org:/10.1038/nn.4117

Cerebral β-amyloidosis is induced by inoculation of Aβ seeds into APP transgenic mice, but not into App−/− (APP null) mice. We found that brain extracts from APP null mice that had been inoculated with Aβ seeds up to 6 months previously still induced β-amyloidosis in APP transgenic hosts following secondary transmission. Thus, Aβ seeds can persist in the brain for months, and they regain propagative and pathogenic activity in the presence of host Aβ.


Induced amyloid lesions are partly congophilic and surrounded by activated microglia and dystrophic boutons.

Induced amyloid lesions are partly congophilic and surrounded by activated microglia and dystrophic boutons.

(a) Congo red-positive amyloid deposits induced in the dentate gyrus were surrounded by Iba1-positive microglia (black). (b) Congo red-positive plaque with surrounding hypertrophic microglial cell bodies and processes at higher magnification


Glial fibrillary acidic protein is a body fluid biomarker for glial pathology in human disease

Brain Research  Volume 1600, 10 March 2015, Pages 17–31    doi:10.1016/j.brainres.2014.12.027

Highlights

• Reviewing 45 years of Glial fibrillary acidic protein (Gfap).
•Gfap discovered in multiple sclerosis brain tissue.
•From Gfap genetics to post-translational modifications.
•Ninety-nine ways to quantify Gfap and related immune phenomena.
•Emergence of Gfap as a body fluid biomarker in human disease.

This review on the role of glial fibrillary acidic protein (GFAP) as a biomarker for astroglial pathology in neurological diseases provides background to protein synthesis, assembly, function and degeneration. Qualitative and quantitative analytical techniques for the investigation of human tissue and biological fluid samples are discussed including partial lack of parallelism and multiplexing capabilities. Pathological implications are reviewed in view of immunocytochemical, cell-culture and genetic findings. Particular emphasis is given to neurodegeneration related to autoimmune astrocytopathies and to genetic gain of function mutations. The current literature on body fluid levels of GFAP in human disease is summarised and illustrated by disease specific meta-analyses. In addition to the role of GFAP as a diagnostic biomarker for chronic disease, there are important data on the prognostic value for acute conditions. The published evidence permits to classify the dominant GFAP signatures in biological fluids. This classification may serve as a template for supporting diagnostic criteria of autoimmune astrocytopathies, monitoring disease progression in toxic gain of function mutations, clinical treatment trials (secondary outcome and toxicity biomarker) and provide prognostic information in neurocritical care if used within well defined time-frames.


The GFAP isoforms. A schematic drawing of the protein structures of the GFAP ...


Modelled structure of GFAP. Reprinted with permission from Biswas et al. (2011).


CSF and Plasma Amyloid-b Temporal Profiles and Relationships with Neurological Status and Mortality after Severe Traumatic Brain Injury

http://www.quanterix.com/literature/publications/neurology/item/482-csf-and-plasma-amyloid-b-temporal-profiles-and-relationships-with-neurological-status-and-mortality-after-severe-traumatic-brain-injury

by Stefania Mondello, Andras Burk, Pal Barzo, Jeff Randall, Gail Provuncher, David Hanlon, David Wilson, Firas Kobeissy & Andreas Jeromin


The role of amyloid-b (Ab) neuropathology and its significant changes in biofluids after traumatic braininjury (TBI) is still debated. We used ultrasensitive digital  ELISA approach to assess amyloid-b1-42 (Ab42) concentrations and time-course in cerebrospinal fluid (CSF) and in plasma of patients with severe TBI and
investigated their relationship to injury characteristics, neurological status and clinical outcome. We found decreased CSF Ab42 levels in TBI patients acutely after injury with lower levels in patients who died 6 months post-injury than in survivors. Conversely, plasma Ab42 levels were significantly increased in TBI
with lower levels in patients who survived. A trend analysis showed that both CSF and plasma Ab42 levels strongly correlated with mortality. A positive correlation between changes in CSF Ab42 concentrations and neurological status as assessed by Glasgow Coma Scale (GCS) was identified. Our results suggest that determination of Ab42 may be valuable to obtain prognostic information in patients with severe TBI as well as in monitoring the response of the brain to injury.
Plasma tau levels in Alzheimer’s disease
Henrik Zetterberg, David Wilson, Ulf Andreasson, Lennart Minthon, Kaj Blennow, Jeffrey Randall and Oskar Hansson
Alzheimer’s Research & Therapy 2013; 5:9   http://dx.doi.org:/10.1186/alzrt163

Efforts to find reliable blood biomarkers for Alzheimer’s disease (AD) in a highly warranted clinical laboratory test have met with little success. There is no clear change in plasma β-amyloid in AD, and assays for the axonal injury marker tau have been hampered by a lack of analytical sensitivity for accurate measurement in blood samples [1]. Here, the results of a novel ultra-sensitive assay for tau in peripheral blood are reported.

We have developed an ultra-sensitive assay for tau in peripheral blood [2]. In brief, the assay is based on digital array technology [3] and uses the Tau5 monoclonal antibody for capture (Covance, Princeton, NJ, USA) and HT7 and BT2 monoclonal antibodies for detection (Pierce, now part of Thermo Fisher Scientific Inc., Waltham, MA, USA). This combination reacts with both normal and phosphorylated tau with epitopes in the mid-region of the molecule, making the assay sensitive to all known tau isoforms. The calibrator was recombinant tau 381 (EMD Millipore Corporation, Billerica, MA, USA). To minimize matrix effects, all samples were diluted 1:4 in phosphate-buffered saline with 2% bovine serum albumin diluent prior to assay. The limit of detection of the assay, which requires 30 μL of plasma, is 0.02 pg/mL [2], which is more than 1,000-fold more sensitive than conventional immunoassays.

Here, we assess the association of plasma tau levels with AD in a cross-sectional study of 54 patients with AD dementia [4], 75 patients with mild cognitive impairment (MCI) [5], and 25 cognitively normal controls (Table 1). All participants were recruited at the specialized memory clinic at Skåne University Hospital in Malmö, Sweden, and underwent extensive clinical evaluation, including cerebrospinal fluid (CSF) sampling by lumbar puncture, in addition to venipuncture and collection of blood in ethylenediaminetetraacetic acid (EDTA) tubes for plasma preparation by centrifugation within 15 minutes from sampling. Plasma samples were aliquoted into cryo tubes and stored at -80°C pending analysis, which was performed on one occasion by using one batch of reagents with an average coefficient of variation of 9.7% for triplicate measurements of each sample. The patients with MCI were cognitively stable for an average of 101 months (n = 36) or developed AD dementia (n = 35) or other types of dementias – vascular dementia (n = 3) and semantic dementia (n = 1) – during follow-up. The study was approved by the regional ethics committee at Lund University and complied with the Declaration of Helsinki. Informed consent was obtained from all study participants.
Tau levels in plasma were significantly higher in AD patients compared with both controls and MCI patients (Figure 1a). MCI patients who developed AD during follow-up had tau levels similar to those of patients with stable MCI and cognitively normal controls (Figure 1b). There was no correlation between tau levels in plasma and CSF in any diagnostic group (Figure 1c).
https://static-content.springer.com/image/art%3A10.1186%2Falzrt163/MediaObjects/13195_2013_Article_139_Fig1_HTML.jpg

Figure 1

Elevated tau levels in plasma from patients with Alzheimer’s disease (AD). (a) Plasma levels of tau are elevated in patients with AD compared with cognitively normal controls and patients with mild cognitive impairment (MCI). (b) MCI patients who developed AD (MCI-AD) during follow-up had baseline tau levels similar to those of patients with stable MCI (SMCI). (c) There was no correlation between tau levels in plasma and cerebrospinal fluid (CSF) in any diagnostic group. Thin horizontal lines in panels (a) and (b) indicate medians. A nonparametric Kruskal-Wallis test followed by Mann-Whitney was performed to test for statistical significance. Spearman’s rank correlation coefficient was used to assess the relationship between plasma and CSF tau concentrations in panel (c), where open circles, gray squares, and black triangles represent AD, MCI, and controls, respectively.

The results of this study have several important implications. First, plasma tau levels are elevated in AD but with overlapping ranges across diagnostic groups. This overlap diminishes the utility of plasma tau as a diagnostic test. However, further studies are needed to evaluate plasma tau as a first-in-line screening tool (for example, in the primary care setting and perhaps together with other markers in a biomarker panel). Second, normal plasma tau levels in the MCI stage of AD suggest that plasma tau is a late marker, requiring substantial axonal injury before increasing to abnormal levels. In this context, other neurodegenerative diseases (for example, Creutzfeldt-Jakob disease) as well as acute conditions (for example, stroke and brain trauma) should be tested. Third, the lack of correlation of tau levels in plasma and CSF suggests that steady-state concentrations of tau in these two body fluids are differentially regulated. In our earlier study of patients with hypoxic brain injury following cardiac arrest, tau was rapidly (within 24 hours) cleared from blood in patients with good neurological outcome [2], indicating potent clearance mechanisms for this marker in the bloodstream. This may obscure any correlation with CSF tau levels, which stay elevated for weeks following an acute neurological insult [6].

Researchers Use CRISPR-based Method to Track RNA In Vivo

A research team led by researchers from the University of California has modified the CRISPR/Cas9 system to demonstrate the ability to track specific RNA sequences and processes in vivo.

As described in a paper published today in Cell, the investigators were able to use their system to visualize specific RNA molecules accumulating in stress granules — dense aggregations of proteins and RNA that form in the cytosol in response to cellular stress and have been linked to neurodegenerative disorders such as amyotrophic lateral sclerosis.

They also found that they could use Cas9 to target an mRNA without altering mRNA abundance or the amount of translated protein.

“We are just beginning to see the implications of genome engineering using the CRISPR technology, but many diseases, including cancer and autism, are linked to problems with another fundamental biological molecule: RNA,” Gene Yeo, senior study author and an associate professor at the University of California, San Diego, said in a statement.

The researchers began their project based on a modification attempted in the lab of co-author Jennifer Doudna from the University of California, Berkeley. Inthat study, the researchers found that it was possible to design a protospacer adjacent motif (PAM) as part of an oligonucleotide (PAMmer) which binds to the single-stranded RNA, allowing Cas9 to efficiently recognize and cleave RNA rather than DNA (RCas9). The researchers determined that with a few further modifications, they could use this method to not only recognize RNA instead of DNA but actually track its movements through cells.

Previously, researchers have attempted to use molecular beacons to track RNA sequences, however, these are limited to imaging applications and are difficult to deliver into cells. Researchers have also attempted to use aptamers to enable RNA tracking in living cells, but these are limited in the number of RNA sequences that they can recognize.

CRISPR/Cas9, however, has thus far proved extremely useful in the genome engineering field and the research team thought that it would be an ideal base to create a better RNA tracking tool.

To prove their concept, the team tested whether a dead Cas9 (dCas9) that was tagged with the fluorescent protein mCherry and contained a nuclear localization signal could be co-exported from the nucleus with a messenger RNA in the presence of a single-guide RNA (sgRNA) and PAMmer designed to recognize that specific mRNA.

The experiment succeeded and the researchers were also able to observe accumulation of ACTB, CCNA2, and TFRC mRNAs in RNA granules that correlated with fluorescence in situ hybridization visualization using image analysis software.

Once they had established that their method was effective, the researchers showed that they could use the sgRNA and PAMmer targeting sequences to track mRNA trafficking to stress granules.

The researchers demonstrated that they could take time-resolved measurements of ACTB mRNA trafficking to stress granules over a period of 30 minutes. They noted in the paper that RCas9 was capable of measuring the association of CCNA2 and TFRC mRNA trafficking to stress granules, as well.

Based on their results, the investigators believe they have established RCas9 as a means to track RNA in living cells in a programmable manner that doesn’t require genetically encoded tags.

“One potential application of this technique is to track RNA transport in diseased neurons over time in order to identify the molecular features of these diseases and support the developments of therapies,” David Nelles, first author on the study and a researcher at the University of California, San Diego, said in a statement. “Just as CRISPR-Cas9 is making genetic engineering accessible to any scientists with access to basic equipment, RNA-targeted Cas9 may support countless other efforts for studying the role of RNA processing in disease or for identifying drugs that reverse defects in RNA processing.”


Programmable RNA Tracking in Live Cells with CRISPR/Cas9

David A. Nelles, Mark Y. Fang, Mitchell R. O’Connell, Jia L. Xu, Sebastian J. Markmiller, Jennifer A. Doudna, Gene W. Yeo
Publication stage: In Press Corrected Proof
Figure thumbnail fx1

Clustered regularly-interspaced short palindromic repeats (CRISPRs) form the basis of adaptive immune systems in bacteria and archaea by encoding CRISPR RNAs that guide CRISPR-associated (Cas) nucleases to invading genetic material (Wiedenheft et al., 2012). Cas9 from the type II CRISPR system ofS. pyogenes has been repurposed for genome engineering in eukaryotic organisms (Hwang et al., 2013, Li et al., 2013a, Mali et al., 2013, Nakayama et al., 2013, Sander and Joung, 2014, Yang et al., 2014) and is rapidly proving to be an efficient means of DNA targeting for other applications such as gene expression modulation (Qi et al., 2013) and imaging (Chen et al., 2013). Cas9 and its associated single-guide RNA (sgRNA) require two critical features to target DNA: a short DNA sequence of the form 5′-NGG-3′ (where “N” = any nucleotide) known as the protospacer adjacent motif (PAM) and an adjacent sequence on the opposite DNA strand that is antisense to the sgRNA. By supporting DNA recognition with specificity determined entirely by a short spacer sequence within the sgRNA, CRISPR/Cas9 provides uniquely flexible and accessible manipulation of the genome. Manipulating cellular RNA content, in contrast, remains problematic. Whereas there exist robust means of attenuating gene expression via RNAi and antisense oligonucleotides, other critical aspects of post-transcriptional gene expression regulation such as subcellular trafficking, alternative splicing or polyadenylation, and spatiotemporally restricted translation are difficult to measure in living cells and are largely intractable.

Analogous to the assembly of zinc finger nucleases (Urnov et al., 2010) and transcription activator-like effector nucleases (TALEN) to recognize specific DNA sequences, efforts to recognize specific RNA sequences have focused on engineered RNA-binding domains. Pumilio and FBF homology (PUF) proteins carry well-defined modules capable of recognizing a single base each and have supported successful targeting of a handful of transcripts for imaging and other manipulations (Filipovska et al., 2011, Ozawa et al., 2007, Wang et al., 2009). PUF proteins can be fused to arbitrary effector domains to alter or tag target RNAs, but PUFs must be redesigned and validated for each RNA target and can only recognize eight contiguous bases, which does not allow unique discrimination in the transcriptome. Molecular beacons are self-quenched synthetic oligonucleotides that fluoresce upon binding to target RNAs and allow RNA detection without construction of a target-specific protein (Sokol et al., 1998). But molecular beacons must be microinjected to avoid the generation of excessive background signal associated with endosome-trapped probes and are limited to imaging applications. An alternative approach to recognition of RNA substrates is to introduce RNA aptamers into target RNAs, enabling specific and strong association of cognate aptamer-binding proteins such as the MS2 coat protein (Fouts et al., 1997). This approach has enabled tracking of RNA localization in living cells over time with high sensitivity (Bertrand et al., 1998) but relies upon laborious genetic manipulation of the target RNA and is not suitable for recognition of arbitrary RNA sequences. Furthermore, insertion of exogenous aptamer sequence has the potential to interfere with endogenous RNA functions. Analogous to CRISPR/Cas9-based recognition of DNA, programmable RNA recognition based on nucleic acid specificity alone without the need for genetic manipulation or libraries of RNA-binding proteins would greatly expand researchers’ ability to modify the mammalian transcriptome and enable transcriptome engineering.

Although the CRISPR/Cas9 system has evolved to recognize double-stranded DNA, recent in vitro work has demonstrated that programmable targeting of RNAs with Cas9 is possible by providing the PAM as part of an oligonucleotide (PAMmer) that hybridizes to the target RNA (O’Connell et al., 2014). By taking advantage of the Cas9 target search mechanism that relies on PAM sequences (Sternberg et al., 2014), a mismatched PAM sequence in the PAMmer/RNA hybrid allows exclusive targeting of RNA and not the encoding DNA. The high affinity and specificity of RNA recognition by Cas9 in cell-free extracts and the success of genome targeting with Cas9 indicate the potential of CRISPR/Cas9 to support programmable RNA targeting in living cells.

To assess the potential of Cas9 as a programmable RNA-binding protein in live cells, we used a modified sgRNA scaffold with improved expression and Cas9 association (Chen et al., 2013) with a stabilized PAMmer oligonucleotide that does not form a substrate for RNase H. We measured the degree of nuclear export of a nuclear localization signal-tagged nuclease-deficient Cas9-GFP fusion and demonstrate that the sgRNA alone is sufficient to promote nuclear export of Cas9 without influencing the abundance of the targeted mRNA or encoded protein. In order to evaluate whether RNA-targeting Cas9 (RCas9) signal patterns correspond with an established untagged RNA-labeling method, we compared distributions of RCas9 and fluorescence in situ hybridization (FISH) targeting ACTB mRNA. We observed high correlation among FISH and RCas9 signal that was dependent on the presence of a PAMmer, indicating the importance of the PAM for efficient RNA targeting. RNA trafficking and subcellular localization are critical to gene expression regulation and reaction to stimuli such as cellular stress. To address whether RCas9 allows tracking of RNA to oxidative stress-induced RNA/protein accumulations called stress granules, we measured ACTB, TFRC, and CCNA2 mRNA association with stress granules in cells subjected to sodium arsenite. Finally, we demonstrated the ability of RCas9 to track trafficking of ACTB mRNA to stress granules over time in living cells. This work establishes the ability of RCas9 to bind RNA in live cells and sets the foundation for manipulation of the transcriptome in addition to the genome by CRISPR/Cas9.

Thumbnail image of Figure 1. Opens large image

http://www.cell.com/cms/attachment/2050893021/2059121638/gr1.jpg

Figure 1

Targeting mRNA in Living Cells with RCas9

(A) Components required for RNA-targeting Cas9 (RCas9) recognition of mRNA include a nuclear localization signal-tagged nuclease-inactive Cas9 fused to a fluorescent protein such as GFP, a modified sgRNA with expression driven by the U6 polymerase III promoter, and a PAMmer composed of DNA and 2′-O-methyl RNA bases with a phosphodiester backbone. The sgRNA and PAMmer are antisense to adjacent regions of the target mRNA whose encoding DNA does not carry a PAM sequence. After formation of the RCas9/mRNA complex in the nucleus, the complex is exported to the cytoplasm.

(B) RCas9 nuclear co-export with GAPDH mRNA. The RCas9 system was delivered to U2OS cells with a sgRNA and PAMmer targeting the 3′ UTR of GAPDH or sgRNA and PAMmer targeting a sequence from λ bacteriophage that should not be present in human cells (“N/A”). Cellular nuclei are outlined with a dashed white line. Scale bars represent 5 microns.

(C) Fraction of cells with cytoplasmic RCas9 signal. Mean values ± SD (n = 50).

(D) A plasmid carrying the Renilla luciferase open reading frame with a β-globin 3′ UTR containing a target site for RCas9 and MS2 aptamer. A PEST protein degradation signal was appended to luciferase to reveal any translational effects of RCas9 binding to the mRNA.

(E) RNA immunoprecipitation of EGFP after transient transfection of the RCas9 system in HEK293T cells targeting the luciferase mRNA compared to non-targeting sgRNA and PAMmer or EGFP alone. Mean values ± SD (n = 3).

(F and G) Renilla luciferase mRNA (F) and protein (G) abundances were compared among the targeting and non-targeting conditions. Mean values ± SD (n = 4).

p values are calculated by Student’s t test, and one, two, and three asterisks represent p values less than 0.05, 0.01, and 0.001, respectively. See also Figure S1.

Correlation of RNA-Targeting Cas9 Signal Distributions with an Established Untagged RNA Localization Measurement

 Tracking RNA Trafficking to Stress Granules over Time
Effective RNA recognition by Cas9 in living cells while avoiding perturbation of the target transcript relies on careful design of the PAMmer and delivery of Cas9 and its cognate guide RNA to the appropriate cellular compartments. Binding of Cas9 to nucleic acids requires two critical features: a PAM DNA sequence and an adjacent spacer sequence antisense to the Cas9-associated sgRNA. By separating the PAM and sgRNA target among two molecules (the PAMmer oligonucleotide and the target mRNA) that only associate in the presence of a target mRNA, RCas9 allows recognition of RNA while avoiding the encoding DNA. To avoid unwanted degradation of the target RNA, the PAMmer is composed of a mixed 2′OMe RNA and DNA that does not form a substrate for RNase H. Further, the sgRNA features a modified scaffold that removes partial transcription termination sequences and a modified structure that promotes association with Cas9 (Chen et al., 2013). Other CRISPR/Cas systems have demonstrated RNA binding in bacteria (Hale et al., 2009, Sampson et al., 2013) or eukaryotes (Price et al., 2015), although these systems cannot discriminate RNA from DNA targets, feature RNA-targeting rules that remain unclear, or rely on large protein complexes that may be difficult to reconstitute in mammalian cells.

In this work, we demonstrate RCas9-based recognition of GAPDH, ACTB,CCNA2, and TFRC mRNAs in live cells. Because the U6-driven sgRNA is largely restricted to the nucleus, the NLS-tagged dCas9 allows association with its sgRNA and subsequent interaction with the target mRNA before nuclear co-export with the target mRNA. As an initial experiment, we evaluated the potential of RNA recognition with Cas9 by targeting GAPDH mRNA and evaluating degree of nuclear export of dCas9-mCherry (Figure 1B). Robust cytoplasmic localization of dCas9-mCherry in the presence of a sgRNA-targeting GAPDH mRNA compared to nuclear retention in the presence of a non-targeting sgRNA indicated that Cas9 association with the mRNA was sufficiently stable to support co-export from the nucleus.

RCas9 as an RNA-imaging reagent requires that RNA recognition by RCas9 does not interfere with normal RNA metabolism. Here, we show that RCas9 binding within the 3′ UTR of Renilla luciferase does not affect its mRNA abundance and translation (Figures 1F and 1G). The utility of RCas9 for imaging and other applications hinges on the recognition of endogenous transcripts, so we evaluated the influence of RCas9 targeting on GAPDH and ACTB mRNAs and observed no significant differences among the mRNA and protein abundances by western blot analysis and qRT-PCR (Figure S1). These results indicate that RCas9 targeting these 3′ UTRs does not perturb the levels of mRNA or encoded protein.

We also evaluated the ability of RCas9 to reveal RNA localization by comparing RCas9 signal patterns to FISH. We utilized a FISH probe set composed of tens of singly labeled probes targeting ACTB mRNA and compared FISH signal distributions to a single dCas9-GFP/sgRNA/PAMmer that recognizes the ACTBmRNA. Our findings indicate that the sgRNA primarily determines the degree of overlap among the FISH and RCas9 signals whereas the PAMmer plays a significant but secondary role. Importantly, in contrast to other untagged RNA localization determination methods such as FISH and molecular beacons, RCas9 is compatible with tracking untagged RNA localization in living cells and can be delivered rapidly to cells using established transfection methods. We also note that the distribution of ACTB mRNA was visualized using a single EGFP tag per transcript, and higher-sensitivity RNA tracking or single endogenous RNA molecule visualization may be possible in the future with RCas9 targeting multiple sites in a transcript or with a multiply tagged dCas9 protein.

Stress granules are translationally silent mRNA and protein accumulations that form in response to cellular stress and are increasingly thought to be involved with neurodegeneration (Li et al., 2013b). There are limited means that can track the movement of endogenous RNA to these structures in live cells (Bertrand et al., 1998). In addition to ACTB mRNA, we demonstrate that RCas9 is capable of measuring association of CCNA2 and TFRC mRNA trafficking to stress granules (Figure 3A). Upon stress induction with sodium arsenite, we observed that 50%, 39%, and 23% of stress granules featured overlapping RCas9 foci when targeting ACTB, TFRC, and CCNA2 mRNAs, respectively (Figure 3C). This result correlates with the expression levels of these transcripts (Figure S3) asACTB is expressed about 8 and 11 times more highly than CCNA2 and TFRC, respectively. We also observed that RCas9 is capable of tracking RNA localization over time as ACTB mRNA is trafficked to stress granules over a period of 30 min (Figure 3B). We noted a dependence of RCas9 signal accumulation in stress granules on stressor concentration (Figure 3D). This approach for live-cell RNA tracking stands in contrast to molecular beacons and aptamer-based RNA-tracking methods, which suffer from delivery issues and/or require alteration of the target RNA sequence via incorporation of RNA tags.

Future applications of RCas9 could allow the measurement or alteration of RNA splicing via recruitment of split fluorescent proteins or splicing factors adjacent to alternatively spliced exons. Further, the nucleic-acid-programmable nature of RCas9 lends itself to multiplexed targeting (Cong et al., 2013) and the use of Cas9 proteins that bind orthogonal sgRNAs (Esvelt et al., 2013) could support distinct activities on multiple target RNAs simultaneously. It is possible that the simple RNA targeting afforded by RCas9 could support the development of sensors that recognize specific healthy or disease-related gene expression patterns and reprogram cell behavior via alteration of gene expression or concatenation of enzymes on a target RNA (Delebecque et al., 2011, Sachdeva et al., 2014). Efforts toward Cas9 delivery in vivo are underway (Dow et al., 2015,Swiech et al., 2015, Zuris et al., 2015), and these efforts combined with existing oligonucleotide chemistries (Bennett and Swayze, 2010) could support in vivo delivery of the RCas9 system for targeted modulation of many features of RNA processing in living organisms.

RNA is subject to processing steps that include alternative splicing, nuclear export, subcellular transport, and base or backbone modifications that work in concert to regulate gene expression. The development of a programmable means of RNA recognition in order to measure and manipulate these processes has been sought after in biotechnology for decades. This work is, to our knowledge, the first demonstration of nucleic-acid-programmed RNA recognition in living cells with CRISPR/Cas9. By relying upon a sgRNA and PAMmer to determine target specificity, RCas9 supports versatile and unambiguous RNA recognition analogous to DNA recognition afforded by CRISPR/Cas9. The diverse applications supported by DNA-targeted CRISPR/Cas9 range from directed cleavage, imaging, transcription modulation, and targeted methylation, indicating the utility of both the native nucleolytic activity of Cas9 as well as the range of activities supported by Cas9-fused effectors. In addition to providing a flexible means to track this RNA in live cells, future developments of RCas9 could include effectors that modulate a variety of RNA-processing steps with applications in synthetic biology and disease modeling or treatment.

Study Unlocks Multiple Functions of CRISPR/Cas9 by Varying Guide RNAs

https://www.genomeweb.com/genetic-research/study-unlocks-multiple-functions-crisprcas9-varying-guide-rnas

Read Full Post »

Inflammatory Disorders: Articles published @ pharmaceuticalintelligence.com

Curators: Larry H. Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN

This is a compilation of articles on Inflammatory Disorders that were published 

@ pharmaceuticalintelligence.com, since 4/2012 to date

There are published works that have not been included.  However, there is a substantial amount of material in the following categories:

  1. The systemic inflammatory response
    http://pharmaceuticalintelligence.com/2014/11/08/introduction-to-impairments-in-pathological-states-endocrine-disorders-stress-hypermetabolism-cancer/

    Summary and Perspectives: Impairments in Pathological States: Endocrine Disorders, Stress Hypermetabolism and Cancer

    Neutrophil Serine Proteases in Disease and Therapeutic Considerations

    What is the key method to harness Inflammation to close the doors for many complex diseases?

    Therapeutic Targets for Diabetes and Related Metabolic Disorders

    A Second Look at the Transthyretin Nutrition Inflammatory Conundrum

    Zebrafish Provide Insights Into Causes and Treatment of Human Diseases

    IBD: Immunomodulatory Effect of Retinoic Acid – IL-23/IL-17A axis correlates with the Nitric Oxide Pathway

    Role of Inflammation in Disease


    http://pharmaceuticalintelligence.com/2013/03/06/can-resolvins-suppress-acute-lung-injury/
    http://pharmaceuticalintelligence.com/2015/02/26/acute-lung-injury/

  2. sepsis
    http://pharmaceuticalintelligence.com/2012/10/20/nitric-oxide-and-sepsis-hemodynamic-collapse-and-the-search-for-therapeutic-options/
  3. vasculitis
    http://pharmaceuticalintelligence.com/2015/02/26/acute-lung-injury/

    The Molecular Biology of Renal Disorders: Nitric Oxide – Part III


    http://pharmaceuticalintelligence.com/2012/11/20/the-potential-for-nitric-oxide-donors-in-renal-function-disorders/

  4. neurodegenerative disease
    http://pharmaceuticalintelligence.com/2013/02/27/ustekinumab-new-drug-therapy-for-cognitive-decline-resulting-from-neuroinflammatory-cytokine-signaling-and-alzheimers-disease/

    Amyloid and Alzheimer’s Disease

    Alzheimer’s Disease – tau art thou, or amyloid

    Beyond tau and amyloid

    Remyelination of axon requires Gli1 inhibition

    Neurovascular pathways to neurodegeneration

    New Alzheimer’s Protein – AICD

    impairment of cognitive function and neurogenesis


    http://pharmaceuticalintelligence.com/2014/05/06/bwh-researchers-genetic-variations-can-influence-immune-cell-function-risk-factors-for-alzheimers-diseasedm-and-ms-later-in-life/

  5. cancer immunology
    http://pharmaceuticalintelligence.com/2013/04/12/innovations-in-tumor-immunology/

    Signaling of Immune Response in Colon Cancer

    Vaccines, Small Peptides, aptamers and Immunotherapy [9]

    Viruses, Vaccines and Immunotherapy

    Gene Expression and Adaptive Immune Resistance Mechanisms in Lymphoma

    The Delicate Connection: IDO (Indolamine 2, 3 dehydrogenase) and Cancer Immunology


  6. autoimmune diseases: rheumatoid arthritis, colitis, ileitis, …
    http://pharmaceuticalintelligence.com/2016/02/11/intestinal-inflammatory-pharmaceutics/
    http://pharmaceuticalintelligence.com/2016/01/07/two-new-drugs-for-inflammatory-bowel-syndrome-are-giving-patients-hope/
    http://pharmaceuticalintelligence.com/2015/12/16/contribution-to-inflammatory-bowel-disease-ibd-of-bacterial-overgrowth-in-gut-on-a-chip/

    Cytokines in IBD

    Autoimmune Inflammtory Bowel Diseases: Crohn’s Disease & Ulcerative Colitis: Potential Roles for Modulation of Interleukins 17 and 23 Signaling for Therapeutics

    Autoimmune Disease: Single Gene eliminates the Immune protein ISG15 resulting in inability to resolve Inflammation and fight Infections – Discovery @Rockefeller University

    Diarrheas – Bacterial and Nonbacterial

    Intestinal inflammatory pharmaceutics

    Biologics for Autoimmune Diseases – Cambridge Healthtech Institute’s Inaugural, May 5-6, 2014 | Seaport World Trade Center| Boston, MA

    Rheumatoid arthritis update


    http://pharmaceuticalintelligence.com/2013/08/04/the-delicate-connection-ido-indolamine-2-3-dehydrogenase-and-immunology/

    Confined Indolamine 2, 3 dioxygenase (IDO) Controls the Hemeostasis of Immune Responses for Good and Bad

    Tofacitinib, an Oral Janus Kinase Inhibitor, in Active Ulcerative Colitis

    Approach to Controlling Pathogenic Inflammation in Arthritis

    Rheumatoid Arthritis Risk


    http://pharmaceuticalintelligence.com/2012/07/08/the-mechanism-of-action-of-the-drug-acthar-for-systemic-lupus-erythematosus-sle/

  7. T cells in immunity
    http://pharmaceuticalintelligence.com/2015/09/07/t-cell-mediated-immune-responses-signaling-pathways-activated-by-tlrs/

    Allogeneic Stem Cell Transplantation [9.3]

    Graft-versus-Host Disease

    Autoimmune Disease: Single Gene eliminates the Immune protein ISG15 resulting in inability to resolve Inflammation and fight Infections – Discovery @Rockefeller University

    Immunity and Host Defense – A Bibliography of Research @Technion

    The Delicate Connection: IDO (Indolamine 2, 3 dehydrogenase) and Cancer Immunology

    Confined Indolamine 2, 3 dioxygenase (IDO) Controls the Hemeostasis of Immune Responses for Good and Bad


    http://pharmaceuticalintelligence.com/2013/04/14/immune-regulation-news/

Proteomics, metabolomics and diabetes

http://pharmaceuticalintelligence.com/2015/11/16/reducing-obesity-related-inflammation/

http://pharmaceuticalintelligence.com/2015/10/25/the-relationship-of-stress-hypermetabolism-to-essential-protein-needs/

http://pharmaceuticalintelligence.com/2015/10/24/the-relationship-of-s-amino-acids-to-marasmic-and-kwashiorkor-pem/

http://pharmaceuticalintelligence.com/2015/10/24/the-significant-burden-of-childhood-malnutrition-and-stunting/

http://pharmaceuticalintelligence.com/2015/04/14/protein-binding-protein-protein-interactions-therapeutic-implications-7-3/

http://pharmaceuticalintelligence.com/2015/03/07/transthyretin-and-the-stressful-condition/

http://pharmaceuticalintelligence.com/2015/02/13/neural-activity-regulating-endocrine-response/

http://pharmaceuticalintelligence.com/2015/01/31/proteomics/

http://pharmaceuticalintelligence.com/2015/01/17/proteins-an-evolutionary-record-of-diversity-and-adaptation/

http://pharmaceuticalintelligence.com/2014/11/01/summary-of-signaling-and-signaling-pathways/

http://pharmaceuticalintelligence.com/2014/10/31/complex-models-of-signaling-therapeutic-implications/

http://pharmaceuticalintelligence.com/2014/10/24/diabetes-mellitus/

http://pharmaceuticalintelligence.com/2014/10/16/metabolomics-summary-and-perspective/

http://pharmaceuticalintelligence.com/2014/10/14/metabolic-reactions-need-just-enough/

http://pharmaceuticalintelligence.com/2014/11/03/introduction-to-protein-synthesis-and-degradation/

http://pharmaceuticalintelligence.com/2015/09/25/proceedings-of-the-nyas/

http://pharmaceuticalintelligence.com/2014/10/31/complex-models-of-signaling-therapeutic-implications/

http://pharmaceuticalintelligence.com/2014/03/21/what-is-the-key-method-to-harness-inflammation-to-close-the-doors-for-many-complex-diseases/

http://pharmaceuticalintelligence.com/2013/03/05/irf-1-deficiency-skews-the-differentiation-of-dendritic-cells/

http://pharmaceuticalintelligence.com/2012/11/26/new-insights-on-no-donors/

http://pharmaceuticalintelligence.com/2012/11/20/the-potential-for-nitric-oxide-donors-in-renal-function-disorders/


Read Full Post »

A Reconstructed View of Personalized Medicine

Author: Larry H. Bernstein, MD, FCAP


There has always been Personalized Medicine if you consider the time a physician spends with a patient, which has dwindled. But the current recognition of personalized medicine refers to breakthrough advances in technological innovation in diagnostics and treatment that differentiates subclasses within diagnoses that are amenable to relapse eluding therapies.  There are just a few highlights to consider:

  1. We live in a world with other living beings that are adapting to a changing environmental stresses.
  2. Nutritional resources that have been available and made plentiful over generations are not abundant in some climates.
  3. Despite the huge impact that genomics has had on biological progress over the last century, there is a huge contribution not to be overlooked in epigenetics, metabolomics, and pathways analysis.

A Reconstructed View of Personalized Medicine

There has been much interest in ‘junk DNA’, non-coding areas of our DNA are far from being without function. DNA has two basic categories of nitrogenous bases: the purines (adenine [A] and guanine [G]), and the pyrimidines (cytosine [C], thymine [T], and  no uracil [U]),  while RNA contains only A, G, C, and U (no T).  The Watson-Crick proposal set the path of molecular biology for decades into the 21st century, culminating in the Human Genome Project.

There is no uncertainty about the importance of “Junk DNA”.  It is both an evolutionary remnant, and it has a role in cell regulation.  Further, the role of histones in their relationship the oligonucleotide sequences is not understood.  We now have a large output of research on noncoding RNA, including siRNA, miRNA, and others with roles other than transcription. This requires major revision of our model of cell regulatory processes.  The classic model is solely transcriptional.

  • DNA-> RNA-> Amino Acid in a protein.

Redrawn we have

  • DNA-> RNA-> DNA and
  • DNA->RNA-> protein-> DNA.

Neverthess, there were unrelated discoveries that took on huge importance.  For example, since the 1920s, the work of Warburg and Meyerhoff, followed by that of Krebs, Kaplan, Chance, and others built a solid foundation in the knowledge of enzymes, coenzymes, adenine and pyridine nucleotides, and metabolic pathways, not to mention the importance of Fe3+, Cu2+, Zn2+, and other metal cofactors.  Of huge importance was the work of Jacob, Monod and Changeux, and the effects of cooperativity in allosteric systems and of repulsion in tertiary structure of proteins related to hydrophobic and hydrophilic interactions, which involves the effect of one ligand on the binding or catalysis of another,  demonstrated by the end-product inhibition of the enzyme, L-threonine deaminase (Changeux 1961), L-isoleucine, which differs sterically from the reactant, L-threonine whereby the former could inhibit the enzyme without competing with the latter. The current view based on a variety of measurements (e.g., NMR, FRET, and single molecule studies) is a ‘‘dynamic’’ proposal by Cooper and Dryden (1984) that the distribution around the average structure changes in allostery affects the subsequent (binding) affinity at a distant site.

What else do we have to consider?  The measurement of free radicals has increased awareness of radical-induced impairment of the oxidative/antioxidative balance, essential for an understanding of disease progression.  Metal-mediated formation of free radicals causes various modifications to DNA bases, enhanced lipid peroxidation, and altered calcium and sulfhydryl homeostasis. Lipid peroxides, formed by the attack of radicals on polyunsaturated fatty acid residues of phospholipids, can further react with redox metals finally producing mutagenic and carcinogenic malondialdehyde, 4-hydroxynonenal and other exocyclic DNA adducts (etheno and/or propano adducts). The unifying factor in determining toxicity and carcinogenicity for all these metals is the generation of reactive oxygen and nitrogen species. Various studies have confirmed that metals activate signaling pathways and the carcinogenic effect of metals has been related to activation of mainly redox sensitive transcription factors, involving NF-kappaB, AP-1 and p53.

I have provided mechanisms explanatory for regulation of the cell that go beyond the classic model of metabolic pathways associated with the cytoplasm, mitochondria, endoplasmic reticulum, and lysosome, such as, the cell death pathways, expressed in apoptosis and repair.  Nevertheless, there is still a missing part of this discussion that considers the time and space interactions of the cell, cellular cytoskeleton and extracellular and intracellular substrate interactions in the immediate environment.

There is heterogeneity among cancer cells of expected identical type, which would be consistent with differences in phenotypic expression, aligned with epigenetics.  There is also heterogeneity in the immediate interstices between cancer cells.  Integration with genome-wide profiling data identified losses of specific genes on 4p14 and 5q13 that were enriched in grade 3 tumors with high microenvironmental diversity that also substratified patients into poor prognostic groups. In the case of breast cancer, there is interaction with estrogen , and we refer to an androgen-unresponsive prostate cancer.

Finally,  the interaction between enzyme and substrates may be conditionally unidirectional in defining the activity within the cell.  The activity of the cell is dynamically interacting and at high rates of activity.  In a study of the pyruvate kinase (PK) reaction the catalytic activity of the PK reaction was reversed to the thermodynamically unfavorable direction in a muscle preparation by a specific inhibitor. Experiments found that in there were differences in the active form of pyruvate kinase that were clearly related to the environmental condition of the assay – glycolitic or glyconeogenic. The conformational changes indicated by differential regulatory response were used to present a dynamic conformational model functioning at the active site of the enzyme. In the model, the interaction of the enzyme active site with its substrates is described concluding that induced increase in the vibrational energy levels of the active site decreases the energetic barrier for substrate induced changes at the site. Another example is the inhibition of H4 lactate dehydrogenase, but not the M4, by high concentrations of pyruvate. An investigation of the inhibition revealed that a covalent bond was formed between the nicotinamide ring of the NAD+ and the enol form of pyruvate.  The isoenzymes of isocitrate dehydrogenase, IDH1 and IDH2 mutations occur in gliomas and in acute myeloid leukemias with normal karyotype. IDH1 and IDH2 mutations are remarkably specific to codons that encode conserved functionally important arginines in the active site of each enzyme. In this case, there is steric hindrance by Asp279 where the isocitrate substrate normally forms hydrogen bonds with Ser94.

Personalized medicine has been largely viewed from a lens of genomics.  But genomics is only the reading frame.  The living activities of cell processes are dynamic and occur at rapid rates.  We have to keep in mind that personalized in reference to genotype is not complete without reconciliation of phenotype, which is the reference to expressed differences in outcomes.


Read Full Post »

« Newer Posts - Older Posts »