Healthcare analytics, AI solutions for biological big data, providing an AI platform for the biotech, life sciences, medical and pharmaceutical industries, as well as for related technological approaches, i.e., curation and text analysis with machine learning and other activities related to AI applications to these industries.
Numerous studies have documented a strong association between diabetes and Alzheimer’s disease (AD). The nature of the relationship, however, has remained a puzzle, in part because of seemingly incongruent findings. For example, some studies have concluded that insulin deficiency is primarily at fault, suggesting that intranasal insulin or inhibiting the insulin-degrading enzyme (IDE) could be beneficial. Other research has concluded that hyperinsulinemia is to blame, which implies that intranasal insulin or the inhibition of IDE would exacerbate the disease. Such antithetical conclusions pose a serious obstacle to making progress on treatments. However, careful integration of multiple strands of research, with attention to the methods used in different studies, makes it possible to disentangle the research on AD. This integration suggests that there is an important relationship between insulin, IDE, and AD that yields multiple pathways to AD depending on the where deficiency or excess in the cycle occurs. I review evidence for each of these pathways here. The results suggest that avoiding excess insulin, and supporting robust IDE levels, could be important ways of preventing and lessening the impact of AD. I also describe what further tests need to be conducted to verify the arguments made in the paper, and their implications for treating AD.
Alzheimer’s disease (AD) is a devastating, fatal disease that affects an estimated 5.2 million Americans, and 44 million people worldwide. It is a disease that is often harder on the families and caregivers of the patient than on the patient themselves. The direct costs to the US of AD in 2014 were estimated to total $214 billion [1]. Adding in the informal costs (the costs of family members and friends providing unpaid care to those with dementia) doubles those figures. The bulk of the financial burden of AD is not due to the cost of drugs or doctor’s visits; instead, the vast majority (75–84%) of the expenses go to nursing home care, plus formal and informal home care [2]. The drugs currently available for AD (primarily cholinesterase inhibitors and memantine) offer only incremental improvements in symptoms— they do not stop the progression of the disease [3–6]. Analysts estimate that AD will cost $1.5 trillion per year US by 2050 if a more effective treatment is not developed [7].
AD has been a difficult puzzle to solve, in part because of an abundance of seemingly incongruent findings. For example, though many studies have identified a significant association between type 2 diabetes mellitus (T2DM) and AD (see the review provided inTable 1), these studies have often come to different conclusions about the causal mechanism and its implications for treatment. Some studies, for example, have concluded that insulin deficiency is primarily at fault, suggesting that intranasal insulin or inhibiting the insulin-degrading enzyme (IDE) could be beneficial [8–11]. Other research has concluded that hyperinsulinemia is to blame, which implies that intranasal insulin or the inhibition of IDE could exacerbate the disease [12–16]. Similarly, recent studies have found a strong association between AD and amylin, a peptide hormone co-secreted with insulin [17–20]. Jackson et al. and Srodulski et al. found that amylin, like the amyloid-β (Aβ) protein thought to be central to the pathology of AD, forms amyloid plaques in the brain, leading them to conclude that amylin might be another amyloid with a causal role in dementia. Oskarsson et al. similarly found that amylin and Aβ were colocalized in plaques in the brain, leading them to draw similar conclusions. However, two other recent studies came to an opposite conclusion: they obtained results suggesting that amylin provides a neuroprotective effect that reduces the symptoms of AD [21, 22].
Despite these seemingly incongruent results, careful integration of multiple strands of research (with attention to the methods used in different studies) makes it possible to disentangle the research on AD. Such an integration points to the likelihood of a relationship between insulin, IDE, and AD that yields multiple pathways to the disease depending on the where deficiency or excess in the cycle occurs.
I posit that the weight of the evidence suggests that under normal circumstances, insulin upregulates the expression of IDE, which subsequently breaks insulin down [23, 24]. IDE, however, also plays important roles in breaking down Aβ and other amyloidogenic peptides. This system can malfunction and lead to AD in at least four different ways as outlined below (see Fig. 1) Evidence for each of these will be reviewed in turn in the sections that follow:
1) An individual with severe insulin deficiency (e.g., undertreated type 1 diabetes mellitus, T1DM) may have inadequate IDE activity, resulting in the accumulation of Aβ (and other protein aggregates) in the brain [23, 25, 26].
2) An individual with diminished IDE (or similar protease) production may end up with accumulation of Aβ and amylin plaques in the brain [27–32].
3) If an individual has exceptionally high levels of insulin (and amylin) in the body (e.g., due to early stages of T2DM), the insulin and amylin may competitively inhibit the breakdown of Aβ, resulting in AD [30, 33–35].
4) An individual may produce more than a typical level of an amyloidogenic peptide, or experience synergistic interactions between amyloidogenic peptides, leading to deposition that outpaces clearing by IDE and similar proteases [17–19, 36–42].
INSULIN, INSULIN DEGRADING ENZYME, AND ALZHEIMER’S DISEASE
The potential roles of insulin and insulin degrading enzyme in AD and other dementias came under scrutiny because of the strong association between T2DM and AD. I thus begin here by briefly reviewing the research on the relationship between T2DM and AD, and I will then review the evidence (summaries are provided in Table 1) for the pathway proposed inFig. 1 and its possible malfunctions.
Type 2 diabetes and Alzheimer’s disease
There is an abundance of studies suggesting that T2DM has a positive association with AD. Some of the most well known research in this area was based on a large population study in Rotterdam [43, 44]. The longitudinal results from this study suggested that diabetes increased the risk of dementia by 1.9 fold, and that diabetic patients treated with insulin were at even greater risk (4.3 fold). Another longitudinal cohort study from the same time frame found that T2DM was associated with an increased risk for all dementias (1.66), and AD in particular (2.27 fold for men, 1.37 fold for women) [45]. Several other longitudinal cohort studies followed, with nearly all concluding that T2DM increased the risk of AD between 1.3 fold and 1.8 fold [46–49].
When cognitive testing is used to assess AD, there is a risk that other types of dementias (notably vascular dementia) will be labeled AD. A diagnosis of AD may often be the result of multiple pathologies [50]. Using autopsies, Schneider et al., for example, found that of 179 probable AD cases, almost half exhibited mixed pathologies— most commonly vascular dementia as a result of cerebral infarctions or neocortical Lewy bodies [51]. Notably, many studies have also implicated T2DM in an increased risk of vascular dementia [46, 52, 53], and, as I will explain later, we have reason to suspect that T2DM could also increase the risk of Lewy bodies.
As noted previously, there is considerable disagreement about the mechanism by which T2DM increases the risk of AD. One line of research posits that it is the excess of insulin or glucose from T2DM that leads to AD. Several studies have found that people with AD have significantly higher levels of insulin and glucose than healthy controls [13, 15, 54]. In a large sample longitudinal study of elderly subjects, Luchsinger et al. conclude that 39% of AD in their sample was attributable to hyperinsulinemia or diabetes [55]. This is also consistent with earlier findings of Ott et al. that diabetics that were treated with insulin had far greater risk of AD [43, 44].
Another line of research, however, suggests that it is insulin deficiency (either by the relative deficiency that results from insulin resistance in early stages of T2DM, or absolute deficiency that occurs when beta cell dysfunction occurs in full-blown T2DM) that causes AD by impairing insulin’s ability to perform its roles in the brain [8, 56–61]. Insulin and its signaling pathways have been found to affect learning and memory [62, 63]. For example, some research has found that administering insulin growth factors in rats and mice enhances memory retention [63, 64], and depleting it impairs learning [65]. However, the mechanisms of insulin’s roles in the brain remain poorly understood [66]. The potential roles of insulin deficiency in AD has led some researchers to conclude that administration of intranasal insulin, or insulin sensitizers, would attenuate neurological deficits. For example, in several studies, Reger et al. found that moderate doses of intranasal insulin improved some memory symptoms in older adults with AD or mild cognitive impairment [57–59]. However, it is important to note first that patients with diabetes were excluded from the study, and second that the results were nonmonotonic in the dosages of insulin. That is, at higher levels, insulin administration impaired performance.
If insulin deficiency is one of the main culprits in AD, then we would expect a very strong relationship between undertreated T1DM (whereby an individual does not produce insulin or amylin at all) and AD. However, T1DM is much rarer than T2DM, and in the past it often resulted in much earlier mortality. Furthermore, survival of T1DM requires individuals to be treated with insulin, confounding our ability to analyze its relationship with AD. In a few studies, T1DM was induced in mice via administration of streptozotocin, and these mice exhibited AD (or AD-like) pathology [11, 24, 67, 68]1. For example, in the study by Wang et al., inducing T1DM in mice via administration of streptozotocin resulted in increased Aβ generation, neuritic plaque formation, and spatial memory deficits in mice engineered to exhibit AD [11]. Similarly, a study by Clodfelder-Miller et al. found that within three days of insulin depletion by streptozotocin, mice exhibited a five-fold increase in tau phosphorylation [68]. There is also some evidence to suggest that having a severe insulin deficiency, as in T1DM, could result in inadequate upregulation of proteases that break down Aβ [71]. This leads, then, to the first malfunction pathway proposed above.
MALFUNCTION 1. SEVERE INSULIN DEFICIENCY MAY LEAD TO INADEQUATE PROTEASE PRODUCTION OR ACTIVITY
There is a paucity of information about what stimulates IDE and other amyloid proteases, however, the studies that do exist suggest that insulin is a primary regulator of IDE [23, 24, 26]. For example, in one study, Zhao et al. conclude that IDE upregulation requires insulin-mediated Akt (also known as protein kinase B) activation [23], and mice induced to have T1DM (and thus do not produce insulin) expressed significantly less IDE [24]. Rezende et al. also found that when insulin secretion levels were dramatically reduced in mice through protein secretion, there was a concomitant dramatic decrease in IDE expression in the liver [72]. This suggests that a severe insulin deficiency could possibly be accompanied by an IDE deficiency that could lead to or exacerbate AD. However, because severe insulin deficiency is typically fatal if untreated, this malfunction pathway is probably the least likely to be observed in situ. Furthermore, there are other proteases known to act upon Aβ (e.g., cathepsin D, endothelin-converting enzyme, neprilysin [73–77]) that may not be as reliant upon insulin, and we know relatively little about how these proteases are stimulated, which ones act on Aβ in vivo, and how they may compensate for each other. This area thus requires much further research.
MALFUNCTION 2. DIMINISHED PROTEASE PRODUCTION OR ACTIVITY RESULTS IN AMYLOID ACCUMULATION
IDE is one of the most widely studied proteases in studies of the relationship between insulin and Aβ. It is a ubiquitously expressed zinc metalloprotease that breaks down or irreversibly binds insulin [27, 33, 36, 78, 79], amylin [36], Aβ [27–31, 33, 80–86], and other amyloidogenic peptides [34, 36], including alpha synuclein [87, 88], which is implicated in Parkinson’s disease and Lewy body dementia. An individual with diminished IDE production (for example, due to the excess of an IDE inhibitor such as nitric oxide [89], or an inadequacy of zinc) might thus end up with accumulation of Aβ, amylin plaques, and alpha synuclein in the brain.
There are numerous studies showing that diminished IDE can result in accumulation of Aβ and memory deficits [27, 90, 91]. For example, Farris et al. found that IDE knockout mice had a greater than 50% decrease in Aβ degradation in both brain membrane fractions and primary neuronal cultures. [27] The mice exhibited an increase in cerebral accumulation of endogenous Aβ (consistent with AD), hyperinsulinemia, and glucose intolerance. Madani et al. found that neprilysin knockout mice had increased Aβ deposition [91], and Miller et al. found that IDE knockout mice had significantly increased levels of Aβ in the brain [92]. Vingtdeux et al. found that CALHM1 potentiates IDE activity, and CALHM1 knockout mice exhibited roughly a 50% increase in endogenous Aβ concentrations in the whole brain and primary neurons [85].
There is also research suggesting that deficiency in IDE might lead to an accumulation of insulin in the brain (hyperinsulinemia), leading to insulin resistance and glucose intolerance [27, 32]. Though the possibility of IDE regulating insulin in the brain remains to be directly tested, this possibility suggests that one of the reasons that AD and T2DM are closely associated might be because they can be caused by the same mechanism.
Diminished IDE production may also account for at least part of the association between the ApoE4 allele and AD. ApoE4 is a well-established risk factor for AD; most estimates suggest that roughly 20–25% of the population has the ApoE4 allele, yet roughly 50% of the AD population has the ApoE4 allele [21, 93, 94]. Furthermore, in their longitudinal study of 2,574 Japanese-American men (and 216 autopsies), Peila et al. found that the combination of diabetes and having one or more copies of the ApoE4 allele resulted in a dramatically higher risk of AD— 5.5 fold— than either risk alone [46]. Having a single copy of the allele is thought to triple the risk for late-onset AD; having two copies of the allele is thought to increase the risk of AD 12 fold [94]. Importantly, Cook et al. found that AD patients with the ApoE4 allele had a 50% reduction in expression of IDE compared to AD patients without the ApoE4 allele, suggesting that the ApoE4 allele may play a role in IDE deficiency leading to AD [95]. The mechanisms that underlie ApoE4’s relationship to AD remain to be more fully explored, however.
Qiu et al.’s study, and a review by Qiu and Folstein, suggest that IDE is likely to be an important protease involved in Aβ degradation [30, 35]. Furthermore, since the IDE gene plays a significant role also in diabetes, this would help to explain the strong relationship between the two pathologies. However, it is important to note that are other proteases that appear to play roles in breaking down or binding Aβ such as neprilysin, endothelin-converting enzyme, cathepsin B, or cathepsin D [73, 83, 96]. The role of these proteases in Aβ degradation and AD pathology have thus far received far less attention and warrant further study.
MALFUNCTION 3. EXCESS INSULIN OR AMYLIN COMPETITIVELY INHIBITS BREAKDOWN OF Aβ
Though IDE can break down a range of amyloidogenic peptides [34], it has a preferential affinity for insulin [33, 36]. This suggests the possibility that, consistent with Qiu et al.’s hypothesis, one of the causal mechanisms leading to sporadic AD may be the competitive inhibition of Aβ by insulin or amylin [30]. Numerous studies have shown that insulin completely competitively inhibits the breakdown of both Aβ [30, 33, 35] and amylin [36]. Furthermore, though insulin upregulates the expression of IDE, it has been shown that its ability to increase IDE diminishes at high levels [23]. This suggests that in the hyperinsulinemia of early T2DM (or obesity) [97, 98], insulin levels could outstrip IDE’s ability to break it down. If IDE preferentially targets insulin and insulin levels are outpacing IDE production, IDE’s ability to breakdown other amyloidogenic proteins will be markedly reduced. As eloquently stated in Bennett et al., “Normally, a balance exists between deposition and degradation of the amyloidogenic peptide. When the levels of the peptide exceed the capacity to degrade them, either by increased expression of the peptide, or decreased expression of the enzymatic activity of IDE, the balance is shifted from degradation to deposition.” [36] The chronic hyperinsulinemia of early T2DM and its potential to competitively inhibit the breakdown of Aβ thus likely explains a large portion of the association between T2DM and AD.
This competitive inhibition of degradation among different IDE substrates brings us to the recent amylin studies. In 2013, Jackson et al. found patients with AD had large amylin plaque deposits and mixed amylin and Aβ deposits in their brains [17]. They concluded that amylin may play a causal role in AD. Then in 2014, Srodulski et al. found that rats that were genetically modified to express human amylin accumulated amylin oligomers in their brains, and exhibited neurological deficits [18]. Oskarsson et al. also found that amylin and Aβ were colocalized in the brains of human AD patients [19]. If amylin, which is co-secreted with insulin, competes with Aβ for degradation, promotes the deposition of Aβ, or accumulates in plaques on the brain itself, this is another strong mechanism by which T2DM and dementia may be linked.
Remarkably, another set of recent studies appeared to directly counter this conclusion by finding that amylin exhibited a neuroprotective effect [21, 99, 100]. These studies found that injection of pramlintide (an amylin analog), or rat/mouse amylin, appeared to improve memory symptoms in mice engineered to exhibit AD or accelerated senescence. Furthermore, administration of pramlintide to humans appeared to improve some learning and memory measures. However, two important features of these recent studies must be noted. First, the studies used rat/mouse amylin, or pramlintide (synthetic amylin), both of which have proline substitutions at positions 25, 28, and 29 that limit amylin’s self-aggregating properties, thus rendering it non-amyloidogenic. Second, in all the studies except for Qiu et al.’s study of homebound elderly [22], the subjects were diabetes free, and thus likely had no deficiency in their IDE system or excess of competing insulin. In the Qiu et al. study of homebound elderly, the researchers found some differences in memory scores across quartiles of amylin levels across all subjects (including those with diabetes), however these differences were not monotonically increasing. Furthermore, the significant differences they report in amylin levels across AD patients, mild cognitive impairment patients, and healthy persons were only for patients without diabetes.
The preceding suggests that pramlintide might have beneficial effects for people without diabetes. This could be due to its role in preventing post-prandial glucose spikes or by inhibiting glucagon, both of which would collectively lessen insulin demand. These mechanisms of potential benefit, however, are speculative; the mechanism of pramlintide’s potential neuroprotective effect is unclear. For people with diabetes, however, pramlintide seems far less likely to be beneficial in AD. In people with diabetes, insulin and amylin levels are already high, and may have already exhausted their capacity for stimulating IDE production and activity.
MALFUNCTION 4. EXCESS PRODUCTION OF AN AMYLOIDOGENIC PROTEIN, OR POSITIVE INTERACTIONS BETWEEN AMYLOIDOGENIC PROTEINS, RESULT IN AMYLOID ACCUMULATION
Excess production of an amyloidogenic protein can result in amyloid deposition outpacing amyloid degradation, resulting in amyloid accumulation [36]. For example, mutations in the amyloid precursor protein gene (the gene associated with early-onset AD) can increase the relative production of Aβ42, leading to amyloid deposition [37, 38]. Similarly, excess production of amylin (as in T2DM) may directly cause a build-up of amylin plaques on the brain [17]. There is also growing evidence that some amyloidogenic proteins can foster the formation of amyloids of other proteins, in a process known as “cross-seeding” [39–41]. For example, alpha synuclein can initiate tau amyloid formation, and then the two peptides can increase the polymerization of each other [42]. Similarly, amylin may interact with Aβ to increase its formation of plaques [17–19].
IMPLICATIONS
The implications of the preceding are very important, because the mechanism by which AD arises strongly determines what treatments are likely to be effective. If insulin deficiency is the main culprit, for example, then intranasal insulin might be of significant benefit. If, however, hyperinsulinemia and/or competitive inhibition of degradation of Aβ by a degrading protease is the main cause, then administering intranasal insulin could exacerbate the disease. Furthermore, there is evidence that hyperinsulinemia precedes the hyperglycemia of T2DM by many years and it is likely the chronic overstimulation of insulin receptors that leads to insulin resistance [35, 97, 101]. This suggests that extreme caution should be exercised in giving a diabetic or pre-diabetic individual extra insulin— it may just add fuel to the fire.
The evidence overwhelmingly suggests that testing for glucose tolerance should occur early and often. There is no downside to glucose tolerance testing other than minor cost, and the upside could be the earlier identification and treatment of pre-diabetes and diabetes. Given the evidence of a very strong association between hyperinsulinemia and AD (and other forms of dementia), every patient with AD or mild cognitive impairment should be regularly tested for glucose intolerance. Furthermore, obesity is also strongly associated with hyperinsulinemia [97] and diabetes [102], and thus, not surprisingly, increases the risk of AD [103]. Given the widespread prevalence of obesity, pre-diabetes, and diabetes, glucose intolerance testing should become a standard part of regular health screening in the broader population. According to the American Diabetes Association, of the 29.1 million Americans with diabetes in 2012, 8.1 million (28%) were undiagnosed. Furthermore, 86 million Americans are estimated to be pre-diabetic (i.e., have impaired glucose tolerance) and most will have no symptoms that are recognizable without medical testing [104]. Early identification of, and intervention for, diabetes and prediabetes could significantly lessen the impact of both diabetes and AD.
The review and arguments here suggest a few necessary future studies:
1. Insulin Deficiency versus Hyperinsulinemia
First, to test the competing hypotheses that it is insulin deficiency versus hyperinsulinemia that create or exacerbate AD (and thus the appropriateness of administering intranasal insulin) mice (including wild type, mice altered to develop AD, and mice altered to develop both AD and hyperinsulinemia) should be given chronic intranasal insulin and then subjected to both cognitive testing and quantification of amyloid burden and tauopathy. If the pathways to AD posed in this paper are correct, intranasal insulin should make AD in hyperinsulinemic mice worse. Its effects on the other mice should be very informative: if it yields moderate neurological improvements in the AD mice, this would support its use in non-hyperinsulinemic AD patients. It might, however, induce hyperinsulinemia and insulin resistance leading to T2DM in the wild type mice, and both T2DM and worsening of AD in the AD mice by competitively inhibiting the breakdown of Aβ. Ideally a range of doses of insulin will be used to assess potential curvilinear effects.
2. Neuroprotective versus Competitive Inhibition Effects of Amylin and Pramlintide
Next, to assess the neuroprotective versus competitive inhibition effects of amylin and pramlintide, in vitro studies should first be conducted to assess the degree to which pramlintide (rather than human amylin) competitively inhibits the breakdown of Aβ. If IDE responds primarily to the amyloidogenic motif rather than particular amino acid sequences, as suggested by Kurochkin [34] and others, perhaps pramlintide competes less for breakdown of IDE compared to human amylin. Next different groups of mice (wild type, mice altered to develop AD and hyperinsulinemia, mice altered to develop AD but without hyperinsulinemia, and IDE knockout mice altered to develop AD) should be chronically treated with different amylins (pramlintide, human amylin), at different dosage levels to observe the potential differential effects of amylin and pramlintide depending on the state of the insulin-IDE system of the subject. IDE inhibitors that can decrease (rather than eliminate) IDE could also be used to more precisely explore the relationships between intranasal insulin, pramlintide, IDE, and AD [32, 105]. This should be followed by cognitive testing and quantification of amyloid burden and tauopathy. If the arguments about competitive inhibition presented earlier are correct, the administration of human amylin should exacerbate AD in all but the wild-type mice. I was unable to find any studies of whether pramlintide competitively inhibits the breakdown of Aβ, so it is impossible to predict the outcome of the tests with pramlintide. If, however, it turns out that pramlintide does competitively inhibit the breakdown of Aβ, then its administration should also exacerbate AD in all but the wild-type mice.
If the results of the first set of studies above find that hyperinsulinemia rather than insulin deficiency exacerbates AD, then this implies that we should be able to significantly lower rates of AD through educating people about how to better manage their blood sugar and insulin. A very large portion of the population has little understanding of the glycemic index of carbohydrates. Furthermore, very few people know that some artificial sweeteners produce an insulin response. This also yields a potential policy implication that perhaps food should be labeled with a measure of its effect on insulin. The results of the second study should help us to identify any AD risks of administering pramlintide (which is already given to many diabetic patients in addition to insulin sensitizers) and help us to assess the overall reliability, efficacy, and safety of administering these drugs.
If the results of future studies support the arguments made in this paper, then this suggests that much more research should be done to identify the different proteases that degrade Aβin vivo, to better understand their promoters and inhibitors, and to evaluate the safety and efficacy of increasing the availability of such proteases in both AD and diabetes. Relatedly, it would be valuable to develop easily administered diagnostic tests to identify protease deficiencies.
Finally, the work here hints at some very fruitful opportunities for extending the findings in AD to better understand other neurodegenerative diseases that involve protein aggregation in the brain. For example, many of the studies cited here with IDE knockout or IDE upregulated mice should be adapted for studies of Parkinson’s disease, Lewy body dementia, and Huntington’s disease. These latter diseases have longer peptide sequences than IDE is thought to degrade (IDE has been shown to only cleave peptides of 50 amino acids or shorter [106]), but recent studies indicate that IDE nonproteolytically inhibits alpha synuclein fibril formation by binding to alpha synuclein oligomers and preventing them from forming amyloids [88], suggesting there could be great promise in this research pathway.
It should be noted that there is disagreement about the validity of a Type 1 diabetes model based on the administration of streptozotocin. Some studies have suggested that streptozotocin is neurotoxic per se [69] while others have found that streptozotocin is not directly neurotoxic [70].
Hurd MD , Martorell P , Delavande A , Mullen KJ , Langa KM ((2013) ) Monetary costs of dementia in the United States. N Engl J Med 368: , 1326–1334.
[3]
Kavirajan H , Schneider LS ((2007) ) Efficacy and adverse effects of cholinesterase inhibitors and memantine in vascular dementia: A meta-analysis of randomised controlled trials. Lancet Neurol 6: , 782–792.
[4]
Korczyn AD ((2012) ) Why have we failed to cure Alzheimer’s disease?. J Alzheimers Dis 29: , 275–282.
[5]
Trinh NH , Hoblyn J , Mohanty SU , Yaffe K ((2003) ) Efficacy of cholinesterase inhibitors in the treatment of neuropsychiatric symptoms and functional impairment in Alzheimer disease – A meta-analysis. JAMA 289: , 210–216.
[6]
Lanctot KL , Herrmann N , Yau KK , Khan LR , Liu BA , Loulou MM , Einarson TR ((2003) ) Efficacy and safety of cholinesterase inhibitors in Alzheimer’s disease: A meta-analysis. Can Med Assoc J 169: , 557–564.
[7]
Zissimopoulos J , Crimmins E , Clair P St. ((2014) ) The value of delaying Alzheimer disease onset. Conference: Forum for Health Economics and Policy
[8]
de la Monte SM ((2012) ) Brain insulin resistance and deficiency as therapeutic targets in Alzheimer’s disease. Curr Alzheimer Res 9: , 35–66.
[9]
de la Monte SM ((2012) ) Contributions of brain insulin resistance and deficiency in amyloid-related neurodegeneration in Alzheimer’s disease. Drugs 72: , 49–66.
[10]
Devi L , Alldred MJ , Ginsberg SD , Ohno M ((2012) ) Mechanisms underlying insulin deficiency-induced acceleration of beta-amyloidosis in a mouse model of Alzheimer’s Disease.e. PLoS One 7: , e32792.
Pinchas Cohen led a team that identified tiny proteins that appear to play a role in controlling how the body ages. (Photo/Beth Newcomb)
A group of six newly discovered proteins may help to divulge secrets of how we age, potentially unlocking insights into diabetes, Alzheimer’s, cancer and other aging-related diseases.
The tiny proteins appear to play several big roles in our bodies’ cells, from decreasing the amount of damaging free radicals and controlling the rate at which cells die to boosting metabolism and helping tissues throughout the body respond better to insulin. The naturally occurring amounts of each protein decrease with age, leading researchers to believe that they play an important role in the aging process and the onset of diseases linked to older age.
The research team led by Pinchas Cohen, dean of the USC Davis School of Gerontology, identified the tiny proteins for the first time and observed their surprising origin from organelles in the cell called mitochondria and their game-changing roles in metabolism and cell survival. This latest finding builds upon prior research by Cohen and his team that uncovered two significant proteins, humanin and MOTS-c, hormones that appear to have significant roles in metabolism and diseases of aging.
Unlike most other proteins, humanin and MOTS-c are encoded in mitochondria, the structure within cells that produces energy from food, instead of in the cell’s nucleus where most genes are contained.
Key functions
Mitochondria have their own small collection of genes, which were once thought to play only minor roles within cells but now appear to have important functions throughout the body. Cohen’s team used computer analysis to see if the part of the mitochondrial genome that provides the code for humanin was coding for other proteins as well. The analysis uncovered the genes for six new proteins, which were dubbed small humanin-like peptides, or SHLPs, 1 through 6 (the name of this hardworking group of proteins is appropriately pronounced “schlep”).
After identifying the six SHLPs and successfully developing antibodies to test for several of them, the team examined both mouse tissues and human cells to determine their abundance in different organs as well as their functions. The proteins were distributed quite differently among organs, which suggests that the proteins have varying functions based on where they are in the body.
Of particular interest is SHLP 2, Cohen said. The protein appears to have profound insulin-sensitizing, anti-diabetic effects as well as potent neuro-protective activity that may emerge as a strategy to combat Alzheimer’s disease. He added that SHLP 6 is also intriguing, with a unique ability to promote cancer cell death and thus potentially target malignant diseases.
“Together with the previously identified mitochondrial peptides, the newly recognized SHLP family expands the understanding of the mitochondria as an intracellular signaling organelle that communicates with the rest of the body to regulate metabolism and cell fate,” Cohen said. “The findings are an important advance that will be ripe for rapid translation into drug development for diseases of aging.”
The study first appeared online in the journal Aging on April 10. Cohen’s research team included collaborators from the Albert Einstein College of Medicine; the findings have been licensed to the biotechnology company CohBar for possible drug development.
The research was supported by a Glenn Foundation Award and National Institutes of Health grants to Cohen (1P01AG034906, 1R01AG 034430, 1R01GM 090311, 1R01ES 020812) and an Ellison/AFAR postdoctoral fellowship to Kelvin Yen. Study authors Laura Cobb, Changhan Lee, Nir Barzilai and Pinchas Cohen are consultants and stockholders of CohBar Inc.
On a blazingly hot morning this past June, a half-dozen scientists convened in a hotel conference room in suburban Maryland for the dress rehearsal of what they saw as a landmark event in the history of aging research. In a few hours, the group would meet with officials at the U.S. Food and Drug Administration (FDA), a few kilometers away, to pitch an unprecedented clinical trial—nothing less than the first test of a drug to specifically target the process of human aging.
“We think this is a groundbreaking, perhaps paradigm-shifting trial,” said Steven Austad, chairman of biology at the University of Alabama, Birmingham, and scientific director of the American Federation for Aging Research (AFAR). After Austad’s brief introductory remarks, a scientist named Nir Barzilai tuned up his PowerPoint and launched into a practice run of the main presentation.
Barzilai is a former Israeli army medical officer and head of a well-known study of centenarians based at the Albert Einstein College of Medicine in the Bronx, New York. To anyone who has seen the ebullient scientist in his natural laboratory habitat, often in a short-sleeved shirt and always cracking jokes, he looked uncharacteristically kempt in a blue blazer and dress khakis. But his practice run kept hitting a historical speed bump. He had barely begun to explain the rationale for the trial when he mentioned, in passing, “lots of unproven, untested treatments under the category of anti-aging.” His colleagues pounced.
“Nir,” interrupted S. Jay Olshansky, a biodemographer of aging from the University of Illinois, Chicago. The phrase “anti-aging … has an association that is negative.”
“I wouldn’t dignify them by calling them ‘treatments,’” added Michael Pollak, director of cancer prevention at McGill University in Montreal, Canada. “They’re products.”
Barzilai, a 59-year-old with a boyish mop of gray hair, wore a contrite grin. “We know the FDA is concerned about this,” he conceded, and deleted the offensive phrase.
Then he proceeded to lay out the details of an ambitious clinical trial. The group—academics all—wanted to conduct a double-blind study of roughly 3000 elderly people; half would get a placebo and half would get an old (indeed, ancient) drug for type 2 diabetes called metformin, which has been shown to modify aging in some animal studies. Because there is still no accepted biomarker for aging, the drug’s success would be judged by an unusual standard—whether it could delay the development of several diseases whose incidence increases dramatically with age: cardiovascular disease, cancer, and cognitive decline, along with mortality. When it comes to these diseases, Barzilai is fond of saying, “aging is a bigger risk factor than all of the other factors combined.”
But the phrase “anti-aging” kept creeping into the rehearsal, and critics kept jumping in. “Okay,” Barzilai said with a laugh when it came up again. “Third time, the death penalty.”
The group’s paranoia about the term “anti-aging” captured both the audacity of the proposed trial and the cultural challenge of venturing into medical territory historically associated with charlatans and quacks. The metformin initiative, which Barzilai is generally credited with spearheading, is unusual by almost any standard of drug development. The people pushing for the trial are all academics, none from industry (although Barzilai is co-founder of a biotech company, CohBar Inc., that is working to develop drugs targeting age-related diseases). The trial would be sponsored by the nonprofit AFAR, not a pharmaceutical company. No one stood to make money if the drug worked, the scientists all claimed; indeed, metformin is not only generic, costing just a few cents a dose, but belongs to a class of drugs that has been part of the human apothecary for 500 years. Patient safety was unlikely to be an issue; millions of diabetics have taken metformin since the 1960s, and its generally mild side effects are well-known.
Finally, the metformin group insisted they didn’t need a cent of federal money to proceed (although they do intend to ask for some). Nor did they need formal approval from FDA to proceed. But they very much wanted the agency’s blessing. By recognizing the merit of such a trial, Barzilai believes, FDA would make aging itself a legitimate target for drug development.
By the time the scientists were done, the rehearsal—which was being filmed for a television documentary—had the feel of a pep rally. They spoke with unguarded optimism. “What we’re talking about here,” Olshansky said, “is a fundamental sea change in how we look at aging and disease.” To Austad, it is “the key, potentially, to saving the health care system.”
As the group piled into a van for the drive to FDA headquarters, there was more talk about setting precedents and opening doors. So it was a little disconcerting when Austad led the delegation up to the main entrance of FDA—and couldn’t get the door open. ……
Mitochondrial Peptides Found in a Preclinical Study Seen to Control Cell Metabolism
CohBar, a developer of mitochondria-based therapeutics, announced that preclinical research by its academic collaborators has found small humanin-like peptides (SHLPs) that can control metabolism and cell survival. The findings have implications for age-related diseases such as Alzheimer’s and cancer.
Researchers discovered the SHLPs by examining the genome of mitochondria with the help of a bioinformatics approach, which identified six peptides. The team then verified the presence of the factors and explored their function in laboratory animals.
CohBar, who have the exclusive license to develop SHLPs into therapeutics, works closely with its academic partners to explore the peptides in preclinical models.
While it was previously believed that mitochondria only have 37 genes, research has revealed that the mitochondrial genome is far more versatile, potentially harboring a multitude of new genes, which can encode peptides acting as cellular signaling factors. The peptides, it has turned out, have shown neuroprotective and anti-inflammatory effects, and act to protect cells in disease-modifying ways in preclinical models of aging.
CohBar’s goal is to bring these peptides to the market as therapies for age-related diseases, such as obesity, type 2 diabetes, cancer, atherosclerosis and neurodegenerative disorders.
“Together with the previously described mitochondrial-derived peptides humanin and MOTS-c, the SHLP family expands our understanding of the role that these peptides play in intracellular signaling throughout the body to regulate both metabolism and cell survival,” Pinchas Cohen, dean of the USC Leonard Davis School of Gerontology, founder and director of CohBar, and the study’s senior author, said in a press release. “These findings further illustrate the enormous potential that mitochondria-based therapeutics could have on treating age-associated diseases like Alzheimer’s and cancer.”
“The pre-clinical evidence continues to confirm that these peptides represent a new class of naturally occurring metabolic regulators,” added Simon Allen, CohBar’s CEO. “They form the foundation of our pipeline of first-in-class treatments for age-related diseases, and we are committed to rapidly advancing them through pre-clinical and clinical activities as we move forward.”
Naturally occurring mitochondrial-derived peptides are age-dependent regulators of apoptosis, insulin sensitivity, and inflammatory markers
Laura J. Cobb1,5, Changhan Lee2, Jialin Xiao2, Kelvin Yen2, Richard G. Wong2, Hiromi K. Nakamura1, ….., Derek M. Huffman4, Junxiang Wan2, Radhika Muzumdar3, Nir Barzilai4 , and Pinchas Cohen2 http://www.impactaging.com/papers/v8/n4/full/100943.html
Mitochondria are key players in aging and in the pathogenesis of age-related diseases. Recent mitochondrial transcriptome analyses revealed the existence of multiple small mRNAs transcribed from mitochondrial DNA (mtDNA). Humanin (HN), a peptide encoded in the mtDNA 16S ribosomal RNA region, is a neuroprotective factor. An in silico search revealed six additional peptides in the same region of mtDNA as humanin; we named these peptides small humanin-like peptides (SHLPs). We identified the functional roles for these peptides and the potential mechanisms of action. The SHLPs differed in their ability to regulate cell viability in vitro. We focused on SHLP2 and SHLP3 because they shared similar protective effects with HN. Specifically, they significantly reduced apoptosis and the generation of reactive oxygen species, and improved mitochondrial metabolism in vitro. SHLP2 and SHLP3 also enhanced 3T3-L1 pre-adipocyte differentiation. Systemic hyperinsulinemic-euglycemic clamp studies showed that intracerebrally infused SHLP2 increased glucose uptake and suppressed hepatic glucose production, suggesting that it functions as an insulin sensitizer both peripherally and centrally. Similar to HN, the levels of circulating SHLP2 were found to decrease with age. These results suggest that mitochondria play critical roles in metabolism and survival through the synthesis of mitochondrial peptides, and provide new insights into mitochondrial biology with relevance to aging and human biology.
Human mitochondrial DNA (mtDNA) is a double-stranded, circular molecule of 16,569 bp and contains 37 genes encoding 13 proteins, 22 tRNAs, and 2 rRNAs. Recent mitochondrial transcriptome analyses revealed the existence of small RNAs derived from mtDNA [1]. In 2001, Nishimoto and colleagues identified humanin (HN), a 24-amino-acid peptide encoded from the 16S ribosomal RNA (rRNA) region of mtDNA. HN is a potent neuroprotective factor capable of antagonizing Alzheimer’s disease (AD)-related cellular insults [2]. HN is a component of a novel retrograde signaling pathway from the mitochondria to the nucleus, which is distinct from mitochondrial signaling pathways, such as the SIRT4-AMPK pathway [3]. HN-dependent cellular protection is mediated in part by interacting with and antagonizing pro-apoptotic Bax-related peptides [4] and IGFBP-3 (IGF binding protein 3) [5].
Because of their involvement in energy production and free radical generation, mitochondria likely play a major role in aging and age-related diseases [6–8]. In fact, improvement of mitochondrial function has been shown to ameliorate age-related memory loss in aged mice [9]. Recent studies have shown that HN levels decrease with age, suggesting that HN could play a role in aging and age-related diseases, such as Alzheimer’s disease (AD), atherosclerosis, and diabetes. Along with lower HN levels in the hypothalamus, skeletal muscle, and cortex of older rodents, the circulating levels of HN were found to decline with age in both humans and mice [10]. Notably, circulating HN levels were found to be (i) significantly higher in long-lived Ames dwarf mice but lower in short-lived growth hormone (GH) transgenic mice, (ii) significantly higher in a GH-deficient cohort of patients with Laron syndrome, and (iii) reduced in mice and humans treated with GH or IGF-1 (insulin-like growth factor 1) [11]. Age-dependent declines in the circulating HN levels may be due to higher levels of reactive oxygen species (ROS) that contribute to atherosclerosis development. Using mouse models of atherosclerosis, it was found that HN-treated mice had a reduced disease burden and significant health improvements [12,13]. In addition, HN improved insulin sensitivity, suggesting clinical potential for mitochondrial peptides in diseases of aging [10]. The discovery of HN represents a unique addition to the spectrum of roles that mitochondria play in the cell [14,15]. A second mitochondrial-derived peptide (MDP), MOTS-c (mitochondrial open reading frame of the 12S rRNA-c), has also been shown to have metabolic effects on muscle and may also play a role in aging [16].
We further investigated mtDNA for the presence of other MDPs. Recent technological advances have led to the identification of small open reading frames (sORFs) in the nuclear genomes ofDrosophila[17,18] and mammals [19,20]. Therefore, we attempted to identify novel sORFs using the following approaches: 1) in silico identification of potential sORFs; 2) determination of mRNA expression levels; 3) development of specific antibodies against these novel peptides to allow for peptide detection in cells, organs, and plasma; 4) elucidating the actions of these peptides by performing cell-based assays for mitochondrial function, signaling, viability, and differentiation; and 5) delivering these peptides in vivo to determine their systemic metabolic effects. Focusing on the 16S rRNA region of the mtDNA where the humanin gene is located, we identified six sORFs and named them small humanin-like peptides (SHLPs) 1-6. While surveying the biological effects of SHLPs, we found that SHLP2 and SHLP3 were cytoprotective; therefore, we investigated their effects on apoptosis and metabolism in greater detail. Further, we showed that circulating SHLP2 levels declined with age, similar to HN, suggesting that SHLP2 is involved in aging and age-related disease progression.
SHLP2 and SHLP3 regulate the expression of metabolic and inflammatory markers
Epidemiological studies have demonstrated that increased levels of mediators of inflammation and acute-phase reactants, such as fibrinogen, C-reactive protein (CRP), and IL-6, correlate with the incidence of type 2 diabetes mellitus (T2DM) [34–36]. In humans, anti-inflammatory drugs, such as aspirin and sodium salicylate, reduce fasting plasma glucose levels and ameliorate the symptoms of T2DM. In addition, anti-diabetic drugs, such as fibrates [37] and thiazolidinediones [38], have been found to lower some markers of inflammation. SHLP2 increased the levels of leptin, which is known to improve insulin sensitivity, but had no effect on the levels of the pro-inflammatory cytokines IL-6 and MCP-1. SHLP3 significantly increased the leptin levels, but also elevated IL-6 and MCP-1 levels, which could explain the lack of an in vivo insulin-sensitizing effect of SHLP3. The mechanism by which SHLPs regulate the expression of metabolic and inflammatory markers remains unclear and needs to be further investigated. Furthermore, SHLPs have different effects on inflammatory marker expression, suggesting differential regulation and function of individual SHLPs.
SHLP2 in aging
Mitochondria have been implicated in increased lifespan in several life-extending treatments [39,40]; however, it is not known whether the relationship is correlative or causative [40]. Additionally, it is well known that hormone levels change with aging. For example, levels of aldosterone, calcitonin, growth hormone, and IGF-I decrease with age. Circulating HN levels decline with age in humans and rodents, specifically in the hypothalamus and skeletal muscle of older rats. These changes parallel increases in the incidence of age-associated diseases such as AD and T2DM. The decline in circulating SHLP2 levels with age (Fig. 6), the anti-oxidative stress function of SHLP2 (Fig. 3C), and its neuroprotective effect (Fig. 6B) indicate that SHLP2 has a role in the regulation of aging and age-related diseases.
Conclusion
By analyzing the mitochondrial transcriptome, we found that sORFs from mitochondrial DNA encode functional peptides. We identified many mRNA transcripts within 13 protein-coding mitochondrial genes [1]. Such previously underappreciated sORFs have also been described in the nuclear genome [41]. The MDPs we describe here may represent retrograde communication signals from the mitochondria to the nucleus and may explain important aspects of mitochondrial biology that are implicated in health and longevity.
Larry, John Walker is working on mt proteins dynamics. His rotor – stator mechanism in ATPase synthase, a ‘complex’ that biologist accepted as energy generator is likely wrong. I was suppose to have met him in Germany few years ago. Energy in biological systems has nothing to do with heat. Heat is an outcome of a reaction, meaning that IR spectra accordingly to wave theory is a source of information memorized in water interference with carbon open systems within protein and glyo-proteins complexes as well as genome space-time outcomes. Physically speaking from a pure perspective of science ATP is highly unstable form of phosphate ‘chains’. It cannot hold energy, it is actually in contrary, it is like a resonator, trapping negativity, thus functioning as space propeller by expanding carbon skeleton of protein ‘machines’ Now, we don’t know what is ‘aging’ in a pure physical sense, except that we observe structural changes in what we call complexes. We we know is that proteins are not stationary structures, but highly dynamic forms of matter, seemingly occupying discrete and relative spaces. A piece of mt ATP ase could be discovered in the nucleus as transcription factor. Our notion of operational space in terms of electro dynamics from a motor – stator perspective is now translated toward defining semi conducting and supracoductive strings. The reality of which is so much more fascinating and beautiful as time progresses overally. There are spaces where time does not change, and there are spaces where time walks, and there are spaces, where time flies, and there are spaces where time runs. Amazing, indeed! The story of aging gets a lot deeper that science could even imagine, probably to roots of immortal energy- spaces. We know that matter is transient, that is nearly all living matter, replenishes of about 3 to 7 weeks.
Take a glass full of some kind of liquid, you know the mass of the glass and the mass of the liquid (say wine, beer, water, or milk) You also know to an approximate reality the composition of both. Now lift the glass full of liquid and let it break on a surface of your choice. Depending on the surface pieces of the glass would travel differential from a center projected by the vertical axis of your hand. What technology does today is recollecting those pieces and modelling them to fit in a form again that would resemble a holding device, a glass. The liquid we don’t know exactly how it spilled due the nature of its absorbancy of both surface physics and physical ‘state’ properties. Thus we can say how much approximate energy we have held thinking of m/z as time flight objectives. Each technology can read 1D and approximate the 2D, absolutely lacking computational methodology for 3D dynamic reality. Many scientists confuse space and volume. Volume is a one dimensional characteristic! So is crystalography! BY taking quantum chemical method computing principles following imaginative rules we could approach 2D, however , that is not enough to define 3D. Time we use as a reference frame of clocks we have invented in order to keep track of a sense to observable ‘change’ . But remember, time is absolute and parallel in continuity while energy is discrete , coming in quantum packages, realization of accumulated information. Information is highly redundant we see, so annotating information is an objective to modern days simulations that could predict outcomes of possible parallel realities we call worlds. One could ‘jump’ from one reality to another through guidance of light and water, but what remains unsolved is why people make mistakes, constantly by accusing in name of greed and power , or disobedience of commandments of the Lord!
On Thu, Apr 21, 2016 at 3:41 AM, Leaders in Pharmaceutical Business Intelligence (LPBI) Group wrote:
> larryhbern posted: “New Insights into mtDNA, mitochondrial proteins, > aging, and metabolic control Larry H. Bernstein, MD, FCAP, Curator LPBI > Newly discovered proteins may protect against age-related illnesses The > proteins could play a key role in the ” >
Metabolic features of the cell danger response
– Mitochondria in Health and Disease
The Cell Danger Response (CDR) is defined in terms of an ancient metabolic response to threat.
The CDR encompasses inflammation, innate immunity, oxidative stress, and the ER stress response.
The CDR is maintained by extracellular nucleotide (purinergic) signaling.
Abnormal persistence of the CDR lies at the heart of many chronic diseases.
Antipurinergic therapy (APT) has proven effective in many chronic disorders in animal models
The cell danger response (CDR) is the evolutionarily conserved metabolic response that protects cells and hosts from harm. It is triggered by encounters with chemical, physical, or biological threats that exceed the cellular capacity for homeostasis. The resulting metabolic mismatch between available resources and functional capacity produces a cascade of changes in cellular electron flow, oxygen consumption, redox, membrane fluidity, lipid dynamics, bioenergetics, carbon and sulfur resource allocation, protein folding and aggregation, vitamin availability, metal homeostasis, indole, pterin, 1-carbon and polyamine metabolism, and polymer formation. The first wave of danger signals consists of the release of metabolic intermediates like ATP and ADP, Krebs cycle intermediates, oxygen, and reactive oxygen species (ROS), and is sustained by purinergic signaling. After the danger has been eliminated or neutralized, a choreographed sequence of anti-inflammatory and regenerative pathways is activated to reverse the CDR and to heal. When the CDR persists abnormally, whole body metabolism and the gut microbiome are disturbed, the collective performance of multiple organ systems is impaired, behavior is changed, and chronic disease results. Metabolic memory of past stress encounters is stored in the form of altered mitochondrial and cellular macromolecule content, resulting in an increase in functional reserve capacity through a process known as mitocellular hormesis. The systemic form of the CDR, and its magnified form, the purinergic life-threat response (PLTR), are under direct control by ancient pathways in the brain that are ultimately coordinated by centers in the brainstem. Chemosensory integration of whole body metabolism occurs in the brainstem and is a prerequisite for normal brain, motor, vestibular, sensory, social, and speech development. An understanding of the CDR permits us to reframe old concepts of pathogenesis for a broad array of chronic, developmental, autoimmune, and degenerative disorders. These disorders include autism spectrum disorders (ASD), attention deficit hyperactivity disorder (ADHD), asthma, atopy, gluten and many other food and chemical sensitivity syndromes, emphysema, Tourette’s syndrome, bipolar disorder, schizophrenia, post-traumatic stress disorder (PTSD), chronic traumatic encephalopathy (CTE), traumatic brain injury (TBI), epilepsy, suicidal ideation, organ transplant biology, diabetes, kidney, liver, and heart disease, cancer, Alzheimer and Parkinson disease, and autoimmune disorders like lupus, rheumatoid arthritis, multiple sclerosis, and primary sclerosing cholangitis.
This is a confocal microscopy image of human fibroblasts derived from embryonic stem cells. The nuclei appear in blue, while smaller and more numerous mitochondria appear in red. [Shoukhrat Mitalipov]
Mutations in our mitochondrial DNA tend to be inconspicuous, but they can become more prevalent as we age. They can even vary in frequency from cell to cell. Naturally, some cells will be relatively compromised because they happen to have a higher percentage of mutated mitochondrial DNA. Such cells make a poor basis for stem cell lines. They should be excluded. But how?
To answer this question, a team of scientists scrutinized skin fibroblasts, blood cells, and induced pluripotent stem cells (iPSCs) for mitochondrial genome integrity. When the scientists tested the samples for mitochondrial DNA mutations, the levels of mutations appeared low. But when the scientists sequenced the iPS cell lines, they found higher numbers of mitochondrial DNA mutations, particularly in cells from patients over 60.
The scientists were led by Shoukhrat Mitalipov, Ph.D., director of the Center for Embryonic Cell and Gene Therapy at Oregon Health & Science University, and Taosheng Huang, M.D., a medical geneticist and director of the Mitochondrial Medicine Program at Cincinnati Children’s Hospital. The Mitalipov/Huang-led team also found higher percentages of mitochondria containing mutations within a cell. The higher the load of mutated mitochondrial DNA in a cell, the more compromised the cell’s function.
Since each iPSC line is created from a different cell, each line may contain different types of mitochondrial DNA mutations and mutation loads. To choose the least damaged line, the authors recommend screening multiple lines per patient. “It’s a good idea to check the iPS clones for mitochondrial DNA mutations and make sure you pick a good cell line,” said Dr. Huang.
This recommendation appeared April 14 in the journal Cell Stem Cell, in an article entitled, “Age-Related Accumulation of Somatic Mitochondrial DNA Mutations in Adult-Derived Human iPSCs.” This article holds that mitochondrial genome integrity is a vital readout in assessing the proficiency of patient-derived regenerative products destined for clinical applications.
“We found that pooled skin and blood mtDNA contained low heteroplasmic point mutations, but a panel of ten individual iPSC lines from each tissue or clonally expanded fibroblasts carried an elevated load of heteroplasmic or homoplasmic mutations, suggesting that somatic mutations randomly arise within individual cells but are not detectable in whole tissues,” wrote the article’s authors. “The frequency of mtDNA defects in iPSCs increased with age, and many mutations were nonsynonymous or resided in RNA coding genes and thus can lead to respiratory defects.”
Potential therapies using stem cells hold tremendous promise for treating human disease. However, defects in the mitochondria could undermine the iPS cells’ ability to repair damaged tissue or organs.
“If you want to use iPS cells in a human, you must check for mutations in the mitochondrial genome,” declared Dr. Huang. “Every single cell can be different. Two cells next to each other could have different mutations or different percentages of mutations.”
Prior to the creation of a therapeutic iPS cell line, a collection of cells is taken from the patient. These cells will be tested for mutations. If the tester uses Sanger sequencing, older technology that is not as sensitive as newer next-generation sequencing, any mutation that occurs in less than 20% of the sample will go undetected. But mitochondrial DNA mutations might occur in less than 20% of mitochondria in the pooled cells. As a result, mutation rates have not been well understood. “These mitochondrial mutations are actually hidden,” explained Dr. Mitalipov.
The mitochondrial genome is relatively small, containing just 37 genes, so screening should be feasible using next generation sequencing, Dr. Mitalipov added. “It should be relatively cheap and do-able.”
Dr. Mitalipov also commented on a more general point, the implications of the current study on illuminating the mechanisms of age-related disease: “Pathogenic mutations in our mitochondrial DNA have long been thought to be a driving force in aging and age-onset diseases, though clear evidence was missing. This foundational knowledge of how cells are damaged in the natural process of aging may help to illuminate the role of mutated mitochondria in degenerative disease.”
A new paperfrom Shoukhrat Mitalipov’s lab on stem cell mitochondria points to a pattern whereby induced pluripotent stem (IPS) cells tend to have more problems if they are from older patients.
What does this paper mean for the stem cell field and could it impact more specifically the clinical applications of IPS cells?
The new paper Kang, et al is entitled “Age-Related Accumulation of Somatic Mitochondrial DNA Mutations in Adult-Derived Human iPSCs”.
This paper reminds us of the very important realities that mitochondria are key players in stem cell function and that mitochondria have their own genomes that impact that function. A lot of us don’t think about mitochondria and their genome as often as we should.
The paper came to three major scientific conclusions (this from the Highlights section of the paper and also see the graphical abstract for a visual sense of the results overall):
Human iPSC clones derived from elderly adults show accumulation of mtDNA mutations
Fewer mtDNA mutations are present in ESCs and iPSCs derived from younger adults
Accumulated mtDNA mutations can impact metabolic function in iPSCs
Importantly the team looked at IPS cells derived from both blood and skin cells and found that the former were less likely to have mitochondrial mutations.
This study suggests that those teams producing or working with human IPS cells (hIPSCs) should be screening the different lines for mitochondrial mutations. This excellent piece from Sara Reardon on the Mitalipov paper quotes IPS cell expert Jeanne Loring on this very point:
“It’s one of those things most of us don’t think about,” says Jeanne Loring, a stem-cell biologist at the Scripps Research Institute in La Jolla, California. Her lab is working towards using iPS cells to treat Parkinson’s disease, and Loring now plans to go back and examine the mitochondria in her cell lines. She suspects that it will be fairly easy for researchers to screen cells for use in therapies.”
Mitalipov goes further and suggests that his team’s new findings could support the use of human embryonic stem cells (hESC) derived by somatic cell nuclear transfer (SCNT) which would be expected to have mitochondria with fewer mutations. However, as Loring points out in the Reardon article, SCNT is really difficult to successfully perform and only a few labs in the world can do it at present. In that context, working with hIPSC and adding on the additional layer of mitochondrial DNA mutation screening could be more practical.
New York stem cell researcher Dieter Egli, however, is quoted that hIPSC have other differences with hESC as well such as epigenetic differences and he’s quoted in the Reardon piece, “It’s going to be very hard to find a cell line that’s perfect.”
One might reasonably ask both Egli and oneself, “What is a perfect cell line”?
In the end the best approach for use of human pluripotent stem cells of any kind is going to involve a balance between practicality of production and the potentially positive or negative traits of those cells as determined by rigorous validation screening.
With this new paper we’ve just learned more about another layer of screening that is needed. An interesting question is whether adult stem cells such as mesenchymal stromal/stem cells (MSC) also should be screened for mitochondrial mutations. They are often produced from patients who are getting up there in years. I hope that someone will publish on that too.
As to pluripotent cells, I expect that sometimes the best lines, meaning those most perfect for a given clinical application, will be hIPSC (autologous or allogeneic in some instances) and in other cases they may be hESC made from leftover IVF embryos. If SCNT-derived hESC can be more widely produced in an affordable manner and they pass validation as well then those (sometimes called NT-hESC) may also come into play clinically. So far that hasn’t happened for the SCNT cells, but it may over time. …..
Age-Related Accumulation of Somatic Mitochondrial DNA Mutations in Adult-Derived Human iPSCs
In Brief Mitalipov, Huang, and colleagues show that human iPSCs derived from older adults carry more mitochondrial DNA mutations than those derived from younger individuals. Defects in metabolic function caused by mtDNA mutations suggest careful screening of hiPSC clones for mutational load before clinical application.
Highlights
Human iPSC clones derived from elderly adults show accumulation of mtDNA mutations
Fewer mtDNA mutations are present in ESCs and iPSCs derived from younger adults
Accumulated mtDNA mutations can impact metabolic function in iPSCs
The genetic integrity of iPSCs is an important consideration for therapeutic application. In this study, we examine the accumulation of somatic mitochondrial genome (mtDNA) mutations in skin fibroblasts, blood, and iPSCs derived from young and elderly subjects (24–72 years). We found that pooled skin and blood mtDNA contained low heteroplasmic point mutations, but a panel of ten individual iPSC lines from each tissue or clonally expanded fibroblasts carried an elevated load of heteroplasmic or homoplasmic mutations, suggesting that somatic mutations randomly arise within individual cells but are not detectable in whole tissues. The frequency of mtDNA defects in iPSCs increased with age, and many mutations were non-synonymous or resided in RNA coding genes and thus can lead to respiratory defects. Our results highlight a need to monitor mtDNA mutations in iPSCs, especially those generated from older patients, and to examine the metabolic status of iPSCs destined for clinical applications.
Induced pluripotent stem cells (iPSCs) offer an unlimited source for autologous cell replacement therapies to treat age-associated degenerative diseases. Aging is generally characterized by increased DNA damage and genomic instability (Garinis et al., 2008; Lombard et al., 2005); thus, iPSCs derived from elderly subjects may harbor point mutations and larger genomic rearrangements. Indeed, iPSCs display increased chromosome aberrations (Mayshar et al., 2010), subchromosomal copy number variations (CNVs) (Abyzov et al., 2012; Laurent et al., 2011), and exome mutations (Johannesson et al., 2014), compared to natural embryonic stem cell (ESC) counterparts (Ma et al., 2014). The rate of mtDNA mutations is believed to be at least 10- to 20-fold higher than that observed in the nuclear genome (Wallace, 1994), and often both mutated and wild-type mtDNA (heteroplasmy) can coexist in the same cell (Rossignol et al., 2003). Large deletions are most frequently observed mtDNA abnormalities in aged post-mitotic tissues such as brain, heart, and muscle (Bender et al., 2006; Bua et al., 2006; Corral-Debrinski et al., 1992; Cortopassi et al., 1992; Mohamed et al., 2006) and have been implicated in aging and diseases such as Alzheimer’s disease (AD), Parkinson’s disease (PD), amyotrophic lateral sclerosis (ALS), and diabetes (Larsson, 2010; Lin and Beal, 2006; Petersen et al., 2003; Wallace, 2005). In addition, mtDNA point mutations were reported in some tumors and replicating tissues (Chatterjee et al., 2006; Ju et al., 2014; Michikawa et al., 1999; Taylor et al., 2003). However, the extent of mtDNA defects in proliferating peripheral tissues commonly used for iPSC induction, such as skin and blood, is thought to be low and limited to common non-coding variants (Schon et al., 2012; Yao et al., 2015). Accumulation of mtDNA variants in these tissues with age was insignificant (Greaves et al., 2010; Hashizume et al., 2015). Several point mutations were identified in iPSCs generated from the newborn foreskin fibroblasts, although most of these variants were non-coding, common for the general population, and did not affect their metabolic activity (Prigione et al., 2011). Somatic mtDNA mutations may be under-reported secondary to the level of sample interrogation. …..
Figure 2. mtDNA Mutations in Skin Fibroblasts, Blood, and the iPSCs of a 72-YearOld B Subject (A) Sixteen mutations at low heteroplasmy levels were detected in the DNA of PF, while a panel of ten FiPSC lines carried nine mutations, including four that were homoplasmic. Gray rectangles define the mutations shared between PF and FiPSCs. (B) Venn diagram showing only one mutation in FiPSCs shared with PF. (C) All ten FiPSC lines carried between one and five high-heteroplasmy (>15%) mutations. (D) Mutation distribution in whole blood and BiPSCs was similar to that in PF and FiPSCs. Six mutations at low-heteroplasmy levels were observed in blood, while BiPSC lines displayed 21 mutations, including four over the 80% heteroplasmy level. (E) Venn diagram showing four mutations in BiPSCs shared with whole blood and the 17 novel variants. (F) Distribution of mutations in individual BiPSC lines. See also Figures S2 and S3; Table S1; Table S3, sheet 2; and Table S4, sheet 1 ….
Figure 4. Transmission and Distribution of Somatic mtDNA Mutations to iPSCs (A) A total of 112 mtDNA mutations were discovered in parental cells (PF, CF, and blood) from 11 subjects. Of these, 39 variants (35%) were found in corresponding 130 iPSC lines. Among non-transmitted, transmitted, and novel mutations in iPSCs, comparable percentages of variants (68%, 69%, and 79%, respectively) were coding mutations in protein, rRNA, or tRNA genes. This suggests that most pathogenic mutations do not affect iPSC induction. However, certain coding mutations including in ND3, ND4L, and 14 tRNA genes were not detected in iPSCs, suggesting possible pathogenicity. n, the number of mtDNA mutations. Blue font genes were detected in parental cells. (B–D) A total of 80 high heteroplasmic (>15%) variants were detected in the present study in 130 FiPSC or BiPSC lines from 11 subjects. (B) The majority of these variants (76%) were non-synonymous or frame-shift mutations in protein-coding genes or affected rRNA and tRNA genes. (C) More than half of the mutations (56%) were never reported in a database containing whole mtDNA sequences from 26,850 healthy subjects representing the general human population (http://www.mitomap.org/MITOMAP). (D) Most mutations (90%) were never reported in a database containing sequences from healthy subjects with corresponding mtDNA haplotypes. freq., frequent. See also Figure S5 and Tables S3 and S4. ….
sjwilliamspa
Mutations will accumulate over age in mitochondrial DNA, however the current study has the difficulty that the authors could not use patient-age-matched controls, in essence they could only compare induced pluripotent stem cells derived from different patients. This could confound the results but the result with higher frequency of mutation in mtDNA in cells reprogrammed from younger patients is interesting but might limit the ability of autologous regenerative therapy in older patients. However reprogramming, although the method not mentioned here although I am assuming by transfection with lentivirus is a rough procedure, involving multiple dedifferentiation steps. Therefore it is very understandable that cells obtained from elderly patients would respond less favorably to such a rough reprogramming regimen, especially if it produced a higher degree of ROS, which has been shown to alter mtDNA. This is why I feel it is more advantageous to obtain a stem cell population from fat cells and forgo the Oct4, htert, reprogramming with lentiviral vectors.
Salk scientists show how immune receptors clear dead and dysfunctional brain cells and how they might be targets for treating neurodegenerative diseases
By adolescence, your brain already contains most of the neurons that you’ll have for the rest of your life. But a few regions continue to grow new nerve cells—and require the services of cellular sentinels, specialized immune cells that keep the brain safe by getting rid of dead or dysfunctional cells.
Now, Salk scientists have uncovered the surprising extent to which both dying and dead neurons are cleared away, and have identified specific cellular switches that are key to this process. The work was detailed in Nature on April 6, 2016.
“We discovered that receptors on immune cells in the brain are vital for both healthy and injured states,” says Greg Lemke, senior author of the work, a Salk professor of molecular neurobiology and the holder of the Françoise Gilot-Salk Chair. “These receptors could be potential therapeutic targets for neurodegenerative conditions or inflammation-related disorders, such as Parkinson’s disease.”
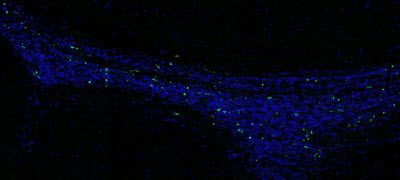
An accumulation of dead cells (green spots) is seen in the subventricular zone (SVZ)—a neurogenic region—of the brain in a mouse lacking the receptors Mer and Axl. (Blue staining marks all cells.) No green spots are seen in the SVZ from a normal mouse. IMAGE CREDIT: SALK INSTITUTE
Two decades ago, the Lemke lab discovered that immune cells express critical molecules called TAM receptors, which have since become a focus for autoimmune and cancer research in many laboratories. Two of the TAM receptors, dubbed Mer and Axl, help immune cells called macrophages act as garbage collectors, identifying and consuming the over 100 billion dead cells that are generated in a human body every day.
For the current study, the team asked if Mer and Axl did the same job in the brain. Specialized central nervous system macrophages called microglia make up about 10 percent of cells in the brain, where they detect, respond to and destroy pathogens. The researchers removed Axl and Mer in the microglia of otherwise healthy mice. To their surprise, they found that the absence of the two receptors resulted in a large pile-up of dead cells, but not everywhere in the brain. Cellular corpses were seen only in the small regions where the production of new neurons—neurogenesis—is observed.
Many cells die normally during adult neurogenesis, but they are immediately eaten by microglia. “It is very hard to detect even a single dead cell in a normal brain, because they are so efficiently recognized and cleared by microglia,” says Paqui G. Través, a co-first author on the paper and former Salk research associate. “But in the neurogenic regions of mice lacking Mer and Axl, we detected many such cells.”
When the researchers more closely examined this process by tagging the newly growing neurons in mice’s microglia missing Mer and Axl, they noticed something else interesting. New neurons that migrate to the olfactory bulb, or smell center, increased dramatically without Axl and Mer around. Mice lacking the TAM receptors had a 70 percent increase in newly generated cells in the olfactory bulb than normal mice.
How—and to what extent—this unchecked new neural growth affects a mouse’s sense of smell is not yet known, according to Lemke, though it is an area the lab will explore. But the fact that so many more living nerve cells were able to migrate into the olfactory bulb in the absence of the receptors suggests that Mer and Axl have another role aside from clearing dead cells—they may actually also target living, but functionally compromised, cells.
“It appears as though a significant fraction of cell death in neurogenic regions is not due to intrinsic death of the cells but rather is a result of the microglia themselves, which are killing a fraction of the cells by engulfment,” says Lemke. “In other words, some of these newborn neuron progenitors are actually being eaten alive.”
This isn’t necessarily a bad thing in the healthy brain, Lemke adds. The brain produces more neurons than it can use and then prunes back the cells that aren’t needed. However, in an inflamed or diseased brain, the destruction of living cells may backfire.
The Lemke lab did one more series of experiments to understand the role of TAM receptors in disease: they looked at the activity of Axl and Mer in a mouse model of Parkinson’s disease. This model produces a human protein present in an inherited form of the disease that results in a slow degeneration of the brain. The team saw that Axl was far more active in this setting, consistent with other studies showing that increased Axl is a reliable indicator of inflammation in tissues.
In the area of a brain lacking Mer and Axl a ‘trail of death’ is apparent from the migratory pathway from the neurogenic region to the olfactory bulb (smell center of the brain). Blue staining marks all cells, and green spots are dead cells. No green spots are seen in the same section from a normal mouse. IMAGE CREDIT: SALK INSTITUTE
“It seems that we can modify the course of the disease in an animal model by manipulating Axl and Mer,” says Lawrence Fourgeaud, a co-first author on the paper and former Salk research associate. The team cautions that more research needs to be done to determine if modulating the TAM receptors could be a viable therapy for neurodegenerative disease involving microglia.
Other researchers on the paper were Yusuf Tufail, Humberto Leal-Bailey, Erin D. Lew, Patrick G. Burrola, Perri Callaway, Anna Zagórska and Axel Nimmerjahn of the Salk Institute; and Carla V. Rothlin of the Yale University School of Medicine.
Microglia are damage sensors for the central nervous system (CNS), and the phagocytes responsible for routine non-inflammatory clearance of dead brain cells1. Here we show that the TAM receptor tyrosine kinases Mer and Axl2 regulate these microglial functions. We find that adult mice deficient in microglial Mer and Axl exhibit a marked accumulation of apoptotic cells specifically in neurogenic regions of the CNS, and that microglial phagocytosis of the apoptotic cells generated during adult neurogenesis3, 4 is normally driven by both TAM receptor ligands Gas6 and protein S5. Using live two-photon imaging, we demonstrate that the microglial response to brain damage is also TAM-regulated, as TAM-deficient microglia display reduced process motility and delayed convergence to sites of injury. Finally, we show that microglial expression of Axl is prominently upregulated in the inflammatory environment that develops in a mouse model of Parkinson’s disease6. Together, these results establish TAM receptors as both controllers of microglial physiology and potential targets for therapeutic intervention in CNS disease.
CRISPR/Cas9, Familial Amyloid Polyneuropathy (FAP) and Neurodegenerative Disease, Volume 2 (Volume Two: Latest in Genomics Methodologies for Therapeutics: Gene Editing, NGS and BioInformatics, Simulations and the Genome Ontology), Part 2: CRISPR for Gene Editing and DNA Repair
CRISPR/Cas9, Familial Amyloid Polyneuropathy ( FAP) and Neurodegenerative Disease
Curator: Larry H. Bernstein, MD, FCAP
CRISPR/Cas9 and Targeted Genome Editing: A New Era in Molecular Biology
The development of efficient and reliable ways to make precise, targeted changes to the genome of living cells is a long-standing goal for biomedical researchers. Recently, a new tool based on a bacterial CRISPR-associated protein-9 nuclease (Cas9) from Streptococcus pyogenes has generated considerable excitement (1). This follows several attempts over the years to manipulate gene function, including homologous recombination (2) and RNA interference (RNAi) (3). RNAi, in particular, became a laboratory staple enabling inexpensive and high-throughput interrogation of gene function (4, 5), but it is hampered by providing only temporary inhibition of gene function and unpredictable off-target effects (6). Other recent approaches to targeted genome modification – zinc-finger nucleases [ZFNs, (7)] and transcription-activator like effector nucleases [TALENs (8)]– enable researchers to generate permanent mutations by introducing doublestranded breaks to activate repair pathways. These approaches are costly and time-consuming to engineer, limiting their widespread use, particularly for large scale, high-throughput studies.
The Biology of Cas9
The functions of CRISPR (Clustered Regularly Interspaced Short Palindromic Repeats) and CRISPR-associated (Cas) genes are essential in adaptive immunity in select bacteria and archaea, enabling the organisms to respond to and eliminate invading genetic material. These repeats were initially discovered in the 1980s in E. coli (9), but their function wasn’t confirmed until 2007 by Barrangou and colleagues, who demonstrated that S. thermophilus can acquire resistance against a bacteriophage by integrating a genome fragment of an infectious virus into its CRISPR locus (10).
Three types of CRISPR mechanisms have been identified, of which type II is the most studied. In this case, invading DNA from viruses or plasmids is cut into small fragments and incorporated into a CRISPR locus amidst a series of short repeats (around 20 bps). The loci are transcribed, and transcripts are then processed to generate small RNAs (crRNA – CRISPR RNA), which are used to guide effector endonucleases that target invading DNA based on sequence complementarity (Figure 1) (11).
Figure 1. Cas9 in vivo: Bacterial Adaptive Immunity
In the acquisition phase, foreign DNA is incorporated into the bacterial genome at the CRISPR loci. CRISPR loci is then transcribed and processed into crRNA during crRNA biogenesis. During interference, Cas9 endonuclease complexed with a crRNA and separate tracrRNA cleaves foreign DNA containing a 20-nucleotide crRNA complementary sequence adjacent to the PAM sequence. (Figure not drawn to scale.)
One Cas protein, Cas9 (also known as Csn1), has been shown, through knockdown and rescue experiments to be a key player in certain CRISPR mechanisms (specifically type II CRISPR systems). The type II CRISPR mechanism is unique compared to other CRISPR systems, as only one Cas protein (Cas9) is required for gene silencing (12). In type II systems, Cas9 participates in the processing of crRNAs (12), and is responsible for the destruction of the target DNA (11). Cas9’s function in both of these steps relies on the presence of two nuclease domains, a RuvC-like nuclease domain located at the amino terminus and a HNH-like nuclease domain that resides in the mid-region of the protein (13).
To achieve site-specific DNA recognition and cleavage, Cas9 must be complexed with both a crRNA and a separate trans-activating crRNA (tracrRNA or trRNA), that is partially complementary to the crRNA (11). The tracrRNA is required for crRNA maturation from a primary transcript encoding multiple pre-crRNAs. This occurs in the presence of RNase III and Cas9 (12).
During the destruction of target DNA, the HNH and RuvC-like nuclease domains cut both DNA strands, generating double-stranded breaks (DSBs) at sites defined by a 20-nucleotide target sequence within an associated crRNA transcript (11, 14). The HNH domain cleaves the complementary strand, while the RuvC domain cleaves the noncomplementary strand.
The double-stranded endonuclease activity of Cas9 also requires that a short conserved sequence, (2–5 nts) known as protospacer-associated motif (PAM), follows immediately 3´- of the crRNA complementary sequence (15). In fact, even fully complementary sequences are ignored by Cas9-RNA in the absence of a PAM sequence (16).
Cas9 and CRISPR as a New Tool in Molecular Biology
The simplicity of the type II CRISPR nuclease, with only three required components (Cas9 along with the crRNA and trRNA) makes this system amenable to adaptation for genome editing. This potential was realized in 2012 by the Doudna and Charpentier labs (11). Based on the type II CRISPR system described previously, the authors developed a simplified two-component system by combining trRNA and crRNA into a single synthetic single guide RNA (sgRNA). sgRNAprogrammed Cas9 was shown to be as effective as Cas9 programmed with separate trRNA and crRNA in guiding targeted gene alterations (Figure 2A).
To date, three different variants of the Cas9 nuclease have been adopted in genome-editing protocols. The first is wild-type Cas9, which can site-specifically cleave double-stranded DNA, resulting in the activation of the doublestrand break (DSB) repair machinery. DSBs can be repaired by the cellular Non-Homologous End Joining (NHEJ) pathway (17), resulting in insertions and/or deletions (indels) which disrupt the targeted locus. Alternatively, if a donor template with homology to the targeted locus is supplied, the DSB may be repaired by the homology-directed repair (HDR) pathway allowing for precise replacement mutations to be made (Figure 2A) (17, 18).
Cong and colleagues (1) took the Cas9 system a step further towards increased precision by developing a mutant form, known as Cas9D10A, with only nickase activity. This means it cleaves only one DNA strand, and does not activate NHEJ. Instead, when provided with a homologous repair template, DNA repairs are conducted via the high-fidelity HDR pathway only, resulting in reduced indel mutations (1, 11, 19). Cas9D10A is even more appealing in terms of target specificity when loci are targeted by paired Cas9 complexes designed to generate adjacent DNA nicks (20) (see further details about “paired nickases” in Figure 2B).
The third variant is a nuclease-deficient Cas9 (dCas9, Figure 2C) (21). Mutations H840A in the HNH domain and D10A in the RuvC domain inactivate cleavage activity, but do not prevent DNA binding (11, 22). Therefore, this variant can be used to sequence-specifically target any region of the genome without cleavage. Instead, by fusing with various effector domains, dCas9 can be used either as a gene silencing or activation tool (21, 23–26). Furthermore, it can be used as a visualization tool. For instance, Chen and colleagues used dCas9 fused to Enhanced Green Fluorescent Protein (EGFP) to visualize repetitive DNA sequences with a single sgRNA or nonrepetitive loci using multiple sgRNAs (27).
Wild-type Cas9 nuclease site specifically cleaves double-stranded DNA activating double-strand break repair machinery. In the absence of a homologous repair template non-homologous end joining can result in indels disrupting the target sequence. Alternatively, precise mutations and knock-ins can be made by providing a homologous repair template and exploiting the homology directed repair pathway.
B. Mutated Cas9 makes a site specific single-strand nick. Two sgRNA can be used to introduce a staggered double-stranded break which can then undergo homology directed repair.
C. Nuclease-deficient Cas9 can be fused with various effector domains allowing specific localization. For example, transcriptional activators, repressors, and fluorescent proteins.
Targeting Efficiency and Off-target Mutations
Targeting efficiency, or the percentage of desired mutation achieved, is one of the most important parameters by which to assess a genome-editing tool. The targeting efficiency of Cas9 compares favorably with more established methods, such as TALENs or ZFNs (8). For example, in human cells, custom-designed ZFNs and TALENs could only achieve efficiencies ranging from 1% to 50% (29–31). In contrast, the Cas9 system has been reported to have efficiencies up to >70% in zebrafish (32) and plants (33), and ranging from 2–5% in induced pluripotent stem cells (34). In addition, Zhou and colleagues were able to improve genome targeting up to 78% in one-cell mouse embryos, and achieved effective germline transmission through the use of dual sgRNAs to simultaneously target an individual gene (35).
A widely used method to identify mutations is the T7 Endonuclease I mutation detection assay (36, 37) (Figure 3). This assay detects heteroduplex DNA that results from the annealing of a DNA strand, including desired mutations, with a wildtype DNA strand (37).
Figure 3. T7 Endonuclease I Targeting Efficiency Assay
Genomic DNA is amplified with primers bracketing the modified locus. PCR products are then denatured and re-annealed yielding 3 possible structures. Duplexes containing a mismatch are digested by T7 Endonuclease I. The DNA is then electrophoretically separated and fragment analysis is used to calculate targeting efficiency.
Another important parameter is the incidence of off-target mutations. Such mutations are likely to appear in sites that have differences of only a few nucleotides compared to the original sequence, as long as they are adjacent to a PAM sequence. This occurs as Cas9 can tolerate up to 5 base mismatches within the protospacer region (36) or a single base difference in the PAM sequence (38). Off-target mutations are generally more difficult to detect, requiring whole-genome sequencing to rule them out completely.
Recent improvements to the CRISPR system for reducing off-target mutations have been made through the use of truncated gRNA (truncated within the crRNA-derived sequence) or by adding two extra guanine (G) nucleotides to the 5´ end (28, 37). Another way researchers have attempted to minimize off-target effects is with the use of “paired nickases” (20). This strategy uses D10A Cas9 and two sgRNAs complementary to the adjacent area on opposite strands of the target site (Figure 2B). While this induces DSBs in the target DNA, it is expected to create only single nicks in off-target locations and, therefore, result in minimal off-target mutations.
By leveraging computation to reduce off-target mutations, several groups have developed webbased tools to facilitate the identification of potential CRISPR target sites and assess their potential for off-target cleavage. Examples include the CRISPR Design Tool (38) and the ZiFiT Targeter, Version 4.2 (39, 40).
Applications as a Genome-editing and Genome Targeting Tool
Following its initial demonstration in 2012 (9), the CRISPR/Cas9 system has been widely adopted. This has already been successfully used to target important genes in many cell lines and organisms, including human (34), bacteria (41), zebrafish (32), C. elegans (42), plants (34), Xenopus tropicalis (43), yeast (44), Drosophila (45), monkeys (46), rabbits (47), pigs (42), rats (48) and mice (49). Several groups have now taken advantage of this method to introduce single point mutations (deletions or insertions) in a particular target gene, via a single gRNA (14, 21, 29). Using a pair of gRNA-directed Cas9 nucleases instead, it is also possible to induce large deletions or genomic rearrangements, such as inversions or translocations (50). A recent exciting development is the use of the dCas9 version of the CRISPR/Cas9 system to target protein domains for transcriptional regulation (26, 51, 52), epigenetic modification (25), and microscopic visualization of specific genome loci (27).
The CRISPR/Cas9 system requires only the redesign of the crRNA to change target specificity. This contrasts with other genome editing tools, including zinc finger and TALENs, where redesign of the protein-DNA interface is required. Furthermore, CRISPR/Cas9 enables rapid genome-wide interrogation of gene function by generating large gRNA libraries (51, 53) for genomic screening.
The Future of CRISPR/Cas9
The rapid progress in developing Cas9 into a set of tools for cell and molecular biology research has been remarkable, likely due to the simplicity, high efficiency and versatility of the system. Of the designer nuclease systems currently available for precision genome engineering, the CRISPR/Cas system is by far the most user friendly. It is now also clear that Cas9’s potential reaches beyond DNA cleavage, and its usefulness for genome locus-specific recruitment of proteins will likely only be limited by our imagination.
Scientists urge caution in using new CRISPR technology to treat human genetic disease
The bacterial enzyme Cas9 is the engine of RNA-programmed genome engineering in human cells. (Graphic by Jennifer Doudna/UC Berkeley)
A group of 18 scientists and ethicists today warned that a revolutionary new tool to cut and splice DNA should be used cautiously when attempting to fix human genetic disease, and strongly discouraged any attempts at making changes to the human genome that could be passed on to offspring.
Among the authors of this warning is Jennifer Doudna, the co-inventor of the technology, called CRISPR-Cas9, which is driving a new interest in gene therapy, or “genome engineering.” She and colleagues co-authored a perspective piece that appears in the March 20 issue of Science, based on discussions at a meeting that took place in Napa on Jan. 24. The same issue of Science features a collection of recent research papers, commentary and news articles on CRISPR and its implications. …..
A prudent path forward for genomic engineering and germline gene modification
Scientists today are changing DNA sequences to correct genetic defects in animals as well as cultured tissues generated from stem cells, strategies that could eventually be used to treat human disease. The technology can also be used to engineer animals with genetic diseases mimicking human disease, which could lead to new insights into previously enigmatic disorders.
The CRISPR-Cas9 tool is still being refined to ensure that genetic changes are precisely targeted, Doudna said. Nevertheless, the authors met “… to initiate an informed discussion of the uses of genome engineering technology, and to identify proactively those areas where current action is essential to prepare for future developments. We recommend taking immediate steps toward ensuring that the application of genome engineering technology is performed safely and ethically.”
Amyloid CRISPR Plasmids and si/shRNA Gene Silencers
Santa Cruz Biotechnology, Inc. offers a broad range of gene silencers in the form of siRNAs, shRNA Plasmids and shRNA Lentiviral Particles as well as CRISPR/Cas9 Knockout and CRISPR Double Nickase plasmids. Amyloid gene silencers are available as Amyloid siRNA, Amyloid shRNA Plasmid, Amyloid shRNA Lentiviral Particles and Amyloid CRISPR/Cas9 Knockout plasmids. Amyloid CRISPR/dCas9 Activation Plasmids and CRISPR Lenti Activation Systems for gene activation are also available. Gene silencers and activators are useful for gene studies in combination with antibodies used for protein detection. Amyloid CRISPR Knockout, HDR and Nickase Knockout Plasmids
CRISPR-Cas9-Based Knockout of the Prion Protein and Its Effect on the Proteome
The molecular function of the cellular prion protein (PrPC) and the mechanism by which it may contribute to neurotoxicity in prion diseases and Alzheimer’s disease are only partially understood. Mouse neuroblastoma Neuro2a cells and, more recently, C2C12 myocytes and myotubes have emerged as popular models for investigating the cellular biology of PrP. Mouse epithelial NMuMG cells might become attractive models for studying the possible involvement of PrP in a morphogenetic program underlying epithelial-to-mesenchymal transitions. Here we describe the generation of PrP knockout clones from these cell lines using CRISPR-Cas9 knockout technology. More specifically, knockout clones were generated with two separate guide RNAs targeting recognition sites on opposite strands within the first hundred nucleotides of the Prnp coding sequence. Several PrP knockout clones were isolated and genomic insertions and deletions near the CRISPR-target sites were characterized. Subsequently, deep quantitative global proteome analyses that recorded the relative abundance of>3000 proteins (data deposited to ProteomeXchange Consortium) were undertaken to begin to characterize the molecular consequences of PrP deficiency. The levels of ∼120 proteins were shown to reproducibly correlate with the presence or absence of PrP, with most of these proteins belonging to extracellular components, cell junctions or the cytoskeleton.
Recent advances in genome engineering technologies based on the CRISPR-associated RNA-guided endonuclease Cas9 are enabling the systematic interrogation of mammalian genome function. Analogous to the search function in modern word processors, Cas9 can be guided to specific locations within complex genomes by a short RNA search string. Using this system, DNA sequences within the endogenous genome and their functional outputs are now easily edited or modulated in virtually any organism of choice. Cas9-mediated genetic perturbation is simple and scalable, empowering researchers to elucidate the functional organization of the genome at the systems level and establish causal linkages between genetic variations and biological phenotypes. In this Review, we describe the development and applications of Cas9 for a variety of research or translational applications while highlighting challenges as well as future directions. Derived from a remarkable microbial defense system, Cas9 is driving innovative applications from basic biology to biotechnology and medicine.
The development of recombinant DNA technology in the 1970s marked the beginning of a new era for biology. For the first time, molecular biologists gained the ability to manipulate DNA molecules, making it possible to study genes and harness them to develop novel medicine and biotechnology. Recent advances in genome engineering technologies are sparking a new revolution in biological research. Rather than studying DNA taken out of the context of the genome, researchers can now directly edit or modulate the function of DNA sequences in their endogenous context in virtually any organism of choice, enabling them to elucidate the functional organization of the genome at the systems level, as well as identify causal genetic variations.
Broadly speaking, genome engineering refers to the process of making targeted modifications to the genome, its contexts (e.g., epigenetic marks), or its outputs (e.g., transcripts). The ability to do so easily and efficiently in eukaryotic and especially mammalian cells holds immense promise to transform basic science, biotechnology, and medicine (Figure 1).
For life sciences research, technologies that can delete, insert, and modify the DNA sequences of cells or organisms enable dissecting the function of specific genes and regulatory elements. Multiplexed editing could further allow the interrogation of gene or protein networks at a larger scale. Similarly, manipulating transcriptional regulation or chromatin states at particular loci can reveal how genetic material is organized and utilized within a cell, illuminating relationships between the architecture of the genome and its functions. In biotechnology, precise manipulation of genetic building blocks and regulatory machinery also facilitates the reverse engineering or reconstruction of useful biological systems, for example, by enhancing biofuel production pathways in industrially relevant organisms or by creating infection-resistant crops. Additionally, genome engineering is stimulating a new generation of drug development processes and medical therapeutics. Perturbation of multiple genes simultaneously could model the additive effects that underlie complex polygenic disorders, leading to new drug targets, while genome editing could directly correct harmful mutations in the context of human gene therapy (Tebas et al., 2014).
Eukaryotic genomes contain billions of DNA bases and are difficult to manipulate. One of the breakthroughs in genome manipulation has been the development of gene targeting by homologous recombination (HR), which integrates exogenous repair templates that contain sequence homology to the donor site (Figure 2A) (Capecchi, 1989). HR-mediated targeting has facilitated the generation of knockin and knockout animal models via manipulation of germline competent stem cells, dramatically advancing many areas of biological research. However, although HR-mediated gene targeting produces highly precise alterations, the desired recombination events occur extremely infrequently (1 in 106–109 cells) (Capecchi, 1989), presenting enormous challenges for large-scale applications of gene-targeting experiments.
Genome Editing Technologies Exploit Endogenous DNA Repair Machinery
To overcome these challenges, a series of programmable nuclease-based genome editing technologies have been developed in recent years, enabling targeted and efficient modification of a variety of eukaryotic and particularly mammalian species. Of the current generation of genome editing technologies, the most rapidly developing is the class of RNA-guided endonucleases known as Cas9 from the microbial adaptive immune system CRISPR (clustered regularly interspaced short palindromic repeats), which can be easily targeted to virtually any genomic location of choice by a short RNA guide. Here, we review the development and applications of the CRISPR-associated endonuclease Cas9 as a platform technology for achieving targeted perturbation of endogenous genomic elements and also discuss challenges and future avenues for innovation. ……
Figure 4Natural Mechanisms of Microbial CRISPR Systems in Adaptive Immunity
…… A key turning point came in 2005, when systematic analysis of the spacer sequences separating the individual direct repeats suggested their extrachromosomal and phage-associated origins (Mojica et al., 2005; Pourcel et al., 2005; Bolotin et al., 2005). This insight was tremendously exciting, especially given previous studies showing that CRISPR loci are transcribed (Tang et al., 2002) and that viruses are unable to infect archaeal cells carrying spacers corresponding to their own genomes (Mojica et al., 2005). Together, these findings led to the speculation that CRISPR arrays serve as an immune memory and defense mechanism, and individual spacers facilitate defense against bacteriophage infection by exploiting Watson-Crick base-pairing between nucleic acids (Mojica et al., 2005; Pourcel et al., 2005). Despite these compelling realizations that CRISPR loci might be involved in microbial immunity, the specific mechanism of how the spacers act to mediate viral defense remained a challenging puzzle. Several hypotheses were raised, including thoughts that CRISPR spacers act as small RNA guides to degrade viral transcripts in a RNAi-like mechanism (Makarova et al., 2006) or that CRISPR spacers direct Cas enzymes to cleave viral DNA at spacer-matching regions (Bolotin et al., 2005). …..
As the pace of CRISPR research accelerated, researchers quickly unraveled many details of each type of CRISPR system (Figure 4). Building on an earlier speculation that protospacer adjacent motifs (PAMs) may direct the type II Cas9 nuclease to cleave DNA (Bolotin et al., 2005), Moineau and colleagues highlighted the importance of PAM sequences by demonstrating that PAM mutations in phage genomes circumvented CRISPR interference (Deveau et al., 2008). Additionally, for types I and II, the lack of PAM within the direct repeat sequence within the CRISPR array prevents self-targeting by the CRISPR system. In type III systems, however, mismatches between the 5′ end of the crRNA and the DNA target are required for plasmid interference (Marraffini and Sontheimer, 2010). …..
In 2013, a pair of studies simultaneously showed how to successfully engineer type II CRISPR systems from Streptococcus thermophilus (Cong et al., 2013) andStreptococcus pyogenes (Cong et al., 2013; Mali et al., 2013a) to accomplish genome editing in mammalian cells. Heterologous expression of mature crRNA-tracrRNA hybrids (Cong et al., 2013) as well as sgRNAs (Cong et al., 2013; Mali et al., 2013a) directs Cas9 cleavage within the mammalian cellular genome to stimulate NHEJ or HDR-mediated genome editing. Multiple guide RNAs can also be used to target several genes at once. Since these initial studies, Cas9 has been used by thousands of laboratories for genome editing applications in a variety of experimental model systems (Sander and Joung, 2014). ……
The majority of CRISPR-based technology development has focused on the signature Cas9 nuclease from type II CRISPR systems. However, there remains a wide diversity of CRISPR types and functions. Cas RAMP module (Cmr) proteins identified in Pyrococcus furiosus and Sulfolobus solfataricus (Hale et al., 2012) constitute an RNA-targeting CRISPR immune system, forming a complex guided by small CRISPR RNAs that target and cleave complementary RNA instead of DNA. Cmr protein homologs can be found throughout bacteria and archaea, typically relying on a 5′ site tag sequence on the target-matching crRNA for Cmr-directed cleavage.
Unlike RNAi, which is targeted largely by a 6 nt seed region and to a lesser extent 13 other bases, Cmr crRNAs contain 30–40 nt of target complementarity. Cmr-CRISPR technologies for RNA targeting are thus a promising target for orthogonal engineering and minimal off-target modification. Although the modularity of Cmr systems for RNA-targeting in mammalian cells remains to be investigated, Cmr complexes native to P. furiosus have already been engineered to target novel RNA substrates (Hale et al., 2009, 2012). ……
Although Cas9 has already been widely used as a research tool, a particularly exciting future direction is the development of Cas9 as a therapeutic technology for treating genetic disorders. For a monogenic recessive disorder due to loss-of-function mutations (such as cystic fibrosis, sickle-cell anemia, or Duchenne muscular dystrophy), Cas9 may be used to correct the causative mutation. This has many advantages over traditional methods of gene augmentation that deliver functional genetic copies via viral vector-mediated overexpression—particularly that the newly functional gene is expressed in its natural context. For dominant-negative disorders in which the affected gene is haplosufficient (such as transthyretin-related hereditary amyloidosis or dominant forms of retinitis pigmentosum), it may also be possible to use NHEJ to inactivate the mutated allele to achieve therapeutic benefit. For allele-specific targeting, one could design guide RNAs capable of distinguishing between single-nucleotide polymorphism (SNP) variations in the target gene, such as when the SNP falls within the PAM sequence.
CRISPR/Cas9: a powerful genetic engineering tool for establishing large animal models of neurodegenerative diseases
Zhuchi Tu, Weili Yang, Sen Yan, Xiangyu Guo and Xiao-Jiang Li
Animal models are extremely valuable to help us understand the pathogenesis of neurodegenerative disorders and to find treatments for them. Since large animals are more like humans than rodents, they make good models to identify the important pathological events that may be seen in humans but not in small animals; large animals are also very important for validating effective treatments or confirming therapeutic targets. Due to the lack of embryonic stem cell lines from large animals, it has been difficult to use traditional gene targeting technology to establish large animal models of neurodegenerative diseases. Recently, CRISPR/Cas9 was used successfully to genetically modify genomes in various species. Here we discuss the use of CRISPR/Cas9 technology to establish large animal models that can more faithfully mimic human neurodegenerative diseases.
Neurodegenerative diseases — Alzheimer’s disease(AD),Parkinson’s disease(PD), amyotrophic lateral sclerosis (ALS), Huntington’s disease (HD), and frontotemporal dementia (FTD) — are characterized by age-dependent and selective neurodegeneration. As the life expectancy of humans lengthens, there is a greater prevalence of these neurodegenerative diseases; however, the pathogenesis of most of these neurodegenerative diseases remain unclear, and we lack effective treatments for these important brain disorders.
CRISPR/Cas9, Non-human primates, Neurodegenerative diseases, Animal model
There are a number of excellent reviews covering different types of neurodegenerative diseases and their genetic mouse models [8–12]. Investigations of different mouse models of neurodegenerative diseases have revealed a common pathology shared by these diseases. First, the development of neuropathology and neurological symptoms in genetic mouse models of neurodegenerative diseases is age dependent and progressive. Second, all the mouse models show an accumulation of misfolded or aggregated proteins resulting from the expression of mutant genes. Third, despite the widespread expression of mutant proteins throughout the body and brain, neuronal function appears to be selectively or preferentially affected. All these facts indicate that mouse models of neurodegenerative diseases recapitulate important pathologic features also seen in patients with neurodegenerative diseases.
However, it seems that mouse models can not recapitulate the full range of neuropathology seen in patients with neurodegenerative diseases. Overt neurodegeneration, which is the most important pathological feature in patient brains, is absent in genetic rodent models of AD, PD, and HD. Many rodent models that express transgenic mutant proteins under the control of different promoters do not replicate overt neurodegeneration, which is likely due to their short life spans and the different aging processes of small animals. Also important are the remarkable differences in brain development between rodents and primates. For example, the mouse brain takes 21 days to fully develop, whereas the formation of primate brains requires more than 150 days [13]. The rapid development of the brain in rodents may render neuronal cells resistant to misfolded protein-mediated neurodegeneration. Another difficulty in using rodent models is how to analyze cognitive and emotional abnormalities, which are the early symptoms of most neurodegenerative diseases in humans. Differences in neuronal circuitry, anatomy, and physiology between rodent and primate brains may also account for the behavioral differences between rodent and primate models.
Mitochondrial dynamics–fusion, fission, movement, and mitophagy–in neurodegenerative diseases
Neurons are metabolically active cells with high energy demands at locations distant from the cell body. As a result, these cells are particularly dependent on mitochondrial function, as reflected by the observation that diseases of mitochondrial dysfunction often have a neurodegenerative component. Recent discoveries have highlighted that neurons are reliant particularly on the dynamic properties of mitochondria. Mitochondria are dynamic organelles by several criteria. They engage in repeated cycles of fusion and fission, which serve to intermix the lipids and contents of a population of mitochondria. In addition, mitochondria are actively recruited to subcellular sites, such as the axonal and dendritic processes of neurons. Finally, the quality of a mitochondrial population is maintained through mitophagy, a form of autophagy in which defective mitochondria are selectively degraded. We review the general features of mitochondrial dynamics, incorporating recent findings on mitochondrial fusion, fission, transport and mitophagy. Defects in these key features are associated with neurodegenerative disease. Charcot-Marie-Tooth type 2A, a peripheral neuropathy, and dominant optic atrophy, an inherited optic neuropathy, result from a primary deficiency of mitochondrial fusion. Moreover, several major neurodegenerative diseases—including Parkinson’s, Alzheimer’s and Huntington’s disease—involve disruption of mitochondrial dynamics. Remarkably, in several disease models, the manipulation of mitochondrial fusion or fission can partially rescue disease phenotypes. We review how mitochondrial dynamics is altered in these neurodegenerative diseases and discuss the reciprocal interactions between mitochondrial fusion, fission, transport and mitophagy.
Applications of CRISPR–Cas systems in Neuroscience
Genome-editing tools, and in particular those based on CRISPR–Cas (clustered regularly interspaced short palindromic repeat (CRISPR)–CRISPR-associated protein) systems, are accelerating the pace of biological research and enabling targeted genetic interrogation in almost any organism and cell type. These tools have opened the door to the development of new model systems for studying the complexity of the nervous system, including animal models and stem cell-derived in vitro models. Precise and efficient gene editing using CRISPR–Cas systems has the potential to advance both basic and translational neuroscience research.
Cellular neuroscience, DNA recombination, Genetic engineering, Molecular neuroscience
Figure 3: In vitro applications of Cas9 in human iPSCs.close
a | Evaluation of disease candidate genes from large-population genome-wide association studies (GWASs). Human primary cells, such as neurons, are not easily available and are difficult to expand in culture. By contrast, induced pluripo…
The development of the CRISPR/Cas9 system has made gene editing a relatively simple task. While CRISPR and other gene editing technologies stand to revolutionize biomedical research and offers many promising therapeutic avenues (such as in the treatment of HIV), a great deal of debate exists over whether CRISPR should be used to modify human embryos. As I discussed in my previous Insight article, we lack enough fundamental biological knowledge to enhance many traits like height or intelligence, so we are not near a future with genetically-enhanced super babies. However, scientists have identified a few rare genetic variants that protect against disease. One such protective variant is a mutation in the APP gene that protects against Alzheimer’s disease and cognitive decline in old age. If we can perfect gene editing technologies, is this mutation one that we should be regularly introducing into embryos? In this article, I explore the potential for using gene editing as a way to prevent Alzheimer’s disease in future generations. Alzheimer’s Disease: Medicine’s Greatest Challenge in the 21st Century Can gene editing be the missing piece in the battle against Alzheimer’s? (Source: bostonbiotech.org) I chose to assess the benefit of germline gene editing in the context of Alzheimer’s disease because this disease is one of the biggest challenges medicine faces in the 21st century. Alzheimer’s disease is a chronic neurodegenerative disease responsible for the majority of the cases of dementia in the elderly. The disease symptoms begins with short term memory loss and causes more severe symptoms – problems with language, disorientation, mood swings, behavioral issues – as it progresses, eventually leading to the loss of bodily functions and death. Because of the dementia the disease causes, Alzheimer’s patients require a great deal of care, and the world spends ~1% of its total GDP on caring for those with Alzheimer’s and related disorders. Because the prevalence of the disease increases with age, the situation will worsen as life expectancies around the globe increase: worldwide cases of Alzheimer’s are expected to grow from 35 million today to over 115 million by 2050.
Despite much research, the exact causes of Alzheimer’s disease remains poorly understood. The disease seems to be related to the accumulation of plaques made of amyloid-β peptides that form on the outside of neurons, as well as the formation of tangles of the protein tau inside of neurons. Although many efforts have been made to target amyloid-β or the enzymes involved in its formation, we have so far been unsuccessful at finding any treatment that stops the disease or reverses its progress. Some researchers believe that most attempts at treating Alzheimer’s have failed because, by the time a patient shows symptoms, the disease has already progressed past the point of no return.
While research towards a cure continues, researchers have sought effective ways to prevent Alzheimer’s disease. Although some studies show that mental and physical exercise may lower ones risk of Alzheimer’s disease, approximately 60-80% of the risk for Alzheimer’s disease appears to be genetic. Thus, if we’re serious about prevention, we may have to act at the genetic level. And because the brain is difficult to access surgically for gene therapy in adults, this means using gene editing on embryos.
With the latest CRISPR/Cas9 advance, the exhortation “turn on, tune in, drop out” comes to mind. The CRISPR/Cas9 gene-editing system was already a well-known means of “tuning in” (inserting new genes) and “dropping out” (knocking out genes). But when it came to “turning on” genes, CRISPR/Cas9 had little potency. That is, it had demonstrated only limited success as a way to activate specific genes.
A new CRISPR/Cas9 approach, however, appears capable of activating genes more effectively than older approaches. The new approach may allow scientists to more easily determine the function of individual genes, according to Feng Zhang, Ph.D., a researcher at MIT and the Broad Institute. Dr. Zhang and colleagues report that the new approach permits multiplexed gene activation and rapid, large-scale studies of gene function.
The new technique was introduced in the December 10 online edition of Nature, in an article entitled, “Genome-scale transcriptional activation by an engineered CRISPR-Cas9 complex.” The article describes how Dr. Zhang, along with the University of Tokyo’s Osamu Nureki, Ph.D., and Hiroshi Nishimasu, Ph.D., overhauled the CRISPR/Cas9 system. The research team based their work on their analysis (published earlier this year) of the structure formed when Cas9 binds to the guide RNA and its target DNA. Specifically, the team used the structure’s 3D shape to rationally improve the system.
In previous efforts to revamp CRISPR/Cas9 for gene activation purposes, scientists had tried to attach the activation domains to either end of the Cas9 protein, with limited success. From their structural studies, the MIT team realized that two small loops of the RNA guide poke out from the Cas9 complex and could be better points of attachment because they allow the activation domains to have more flexibility in recruiting transcription machinery.
Using their revamped system, the researchers activated about a dozen genes that had proven difficult or impossible to turn on using the previous generation of Cas9 activators. Each gene showed at least a twofold boost in transcription, and for many genes, the researchers found multiple orders of magnitude increase in activation.
After investigating single-guide RNA targeting rules for effective transcriptional activation, demonstrating multiplexed activation of 10 genes simultaneously, and upregulating long intergenic noncoding RNA transcripts, the research team decided to undertake a large-scale screen. This screen was designed to identify genes that confer resistance to a melanoma drug called PLX-4720.
“We … synthesized a library consisting of 70,290 guides targeting all human RefSeq coding isoforms to screen for genes that, upon activation, confer resistance to a BRAF inhibitor,” wrote the authors of the Nature paper. “The top hits included genes previously shown to be able to confer resistance, and novel candidates were validated using individual [single-guide RNA] and complementary DNA overexpression.”
A gene signature based on the top screening hits, the authors added, correlated with a gene expression signature of BRAF inhibitor resistance in cell lines and patient-derived samples. It was also suggested that large-scale screens such as the one demonstrated in the current study could help researchers discover new cancer drugs that prevent tumors from becoming resistant.
Familial amyloid polyneuropathy type I is an autosomal dominant disorder caused by mutations in the transthyretin (TTR ) gene; however, carriers of the same mutation exhibit variability in penetrance and clinical expression. We analyzed alleles of candidate genes encoding non-fibrillar components of TTR amyloid deposits and a molecule metabolically interacting with TTR [retinol-binding protein (RBP)], for possible associations with age of disease onset and/or susceptibility in a Portuguese population sample with the TTR V30M mutation and unrelated controls. We show that the V30M carriers represent a distinct subset of the Portuguese population. Estimates of genetic distance indicated that the controls and the classical onset group were furthest apart, whereas the late-onset group appeared to differ from both. Importantly, the data also indicate that genetic interactions among the multiple loci evaluated, rather than single-locus effects, are more likely to determine differences in the age of disease onset. Multifactor dimensionality reduction indicated that the best genetic model for classical onset group versus controls involved the APCS gene, whereas for late-onset cases, one APCS variant (APCSv1) and two RBP variants (RBPv1 and RBPv2) are involved. Thus, although the TTR V30M mutation is required for the disease in Portuguese patients, different genetic factors may govern the age of onset, as well as the occurrence of anticipation.
Autosomal dominant disorders may vary in expression even within a given kindred. The basis of this variability is uncertain and can be attributed to epigenetic factors, environment or epistasis. We have studied familial amyloid polyneuropathy (FAP), an autosomal dominant disorder characterized by peripheral sensorimotor and autonomic neuropathy. It exhibits variation in cardiac, renal, gastrointestinal and ocular involvement, as well as age of onset. Over 80 missense mutations in the transthyretin gene (TTR ) result in autosomal dominant disease http://www.ibmc.up.pt/~mjsaraiv/ttrmut.html). The presence of deposits consisting entirely of wild-type TTR molecules in the hearts of 10– 25% of individuals over age 80 reveals its inherent in vivo amyloidogenic potential (1).
FAP was initially described in Portuguese (2) where, until recently, the TTR V30M has been the only pathogenic mutation associated with the disease (3,4). Later reports identified the same mutation in Swedish and Japanese families (5,6). The disorder has since been recognized in other European countries and in North American kindreds in association with V30M, as well as other mutations (7).
TTR V30M produces disease in only 5–10% of Swedish carriers of the allele (8), a much lower degree of penetrance than that seen in Portuguese (80%) (9) or in Japanese with the same mutation. The actual penetrance in Japanese carriers has not been formally established, but appears to resemble that seen in Portuguese. Portuguese and Japanese carriers show considerable variation in the age of clinical onset (10,11). In both populations, the first symptoms had originally been described as typically occurring before age 40 (so-called ‘classical’ or early-onset); however, in recent years, more individuals developing symptoms late in life have been identified (11,12). Hence, present data indicate that the distribution of the age of onset in Portuguese is continuous, but asymmetric with a mean around age 35 and a long tail into the older age group (Fig. 1) (9,13). Further, DNA testing in Portugal has identified asymptomatic carriers over age 70 belonging to a subset of very late-onset kindreds in whose descendants genetic anticipation is frequent. The molecular basis of anticipation in FAP, which is not mediated by trinucleotide repeat expansions in the TTR or any other gene (14), remains elusive.
Variation in penetrance, age of onset and clinical features are hallmarks of many autosomal dominant disorders including the human TTR amyloidoses (7). Some of these clearly reflect specific biological effects of a particular mutation or a class of mutants. However, when such phenotypic variability is seen with a single mutation in the gene encoding the same protein, it suggests an effect of modifying genetic loci and/or environmental factors contributing differentially to the course of disease. We have chosen to examine age of onset as an example of a discrete phenotypic variation in the presence of the particular autosomal dominant disease-associated mutation TTR V30M. Although the role of environmental factors cannot be excluded, the existence of modifier genes involved in TTR amyloidogenesis is an attractive hypothesis to explain the phenotypic variability in FAP. ….
ATTR (TTR amyloid), like all amyloid deposits, contains several molecular components, in addition to the quantitatively dominant fibril-forming amyloid protein, including heparan sulfate proteoglycan 2 (HSPG2 or perlecan), SAP, a plasma glycoprotein of the pentraxin family (encoded by the APCS gene) that undergoes specific calcium-dependent binding to all types of amyloid fibrils, and apolipoprotein E (ApoE), also found in all amyloid deposits (15). The ApoE4 isoform is associated with an increased frequency and earlier onset of Alzheimer’s disease (Ab), the most common form of brain amyloid, whereas the ApoE2 isoform appears to be protective (16). ApoE variants could exert a similar modulatory effect in the onset of FAP, although early studies on a limited number of patients suggested this was not the case (17).
In at least one instance of senile systemic amyloidosis, small amounts of AA-related material were found in TTR deposits (18). These could reflect either a passive co-aggregation or a contributory involvement of protein AA, encoded by the serum amyloid A (SAA ) genes and the main component of secondary (reactive) amyloid fibrils, in the formation of ATTR.
Retinol-binding protein (RBP), the serum carrier of vitamin A, circulates in plasma bound to TTR. Vitamin A-loaded RBP and L-thyroxine, the two natural ligands of TTR, can act alone or synergistically to inhibit the rate and extent of TTR fibrillogenesis in vitro, suggesting that RBP may influence the course of FAP pathology in vivo (19). We have analyzed coding and non-coding sequence polymorphisms in the RBP4 (serum RBP, 10q24), HSPG2 (1p36.1), APCS (1q22), APOE (19q13.2), SAA1 and SAA2 (11p15.1) genes with the goal of identifying chromosomes carrying common and functionally significant variants. At the time these studies were performed, the full human genome sequence was not completed and systematic singlenucleotide polymorphism (SNP) analyses were not available for any of the suspected candidate genes. We identified new SNPs in APCS and RBP4 and utilized polymorphisms in SAA, HSPG2 and APOE that had already been characterized and shown to have potential pathophysiologic significance in other disorders (16,20–22). The genotyping data were analyzed for association with the presence of the V30M amyloidogenic allele (FAP patients versus controls) and with the age of onset (classical- versus late-onset patients). Multilocus analyses were also performed to examine the effects of simultaneous contributions of the six loci for determining the onset of the first symptoms. …..
The potential for different underlying models for classical and late onset is supported by the MDR analysis, which produces two distinct models when comparing each class with the controls. One could view the two onset classes as unique diseases. If this is the case, then the failure to detect a single predictive genetic model is consistent with two related, but different, diseases. This is exactly what would be expected in such a case of genetic heterogeneity (28). Using this approach, a major gene effect can be viewed as a necessary, but not sufficient, condition to explain the course of the disease. Analyzing the cases but omitting from the analysis of phenotype the necessary allele, in this case TTR V30M, can then reveal a variety of important modifiers that are distinct between the phenotypes.
The significant comparisons obtained in our study cohort indicate that the combined effects mainly result from two and three-locus interactions involving all loci except SAA1 and SAA2 for susceptibility to disease. A considerable number of four-site combinations modulate the age of onset with SAA1 appearing in a majority of significant combinations in late-onset disease, perhaps indicating a greater role of the SAA variants in the age of onset of FAP.
The correlation between genotype and phenotype in socalled simple Mendelian disorders is often incomplete, as only a subset of all mutations can reliably predict specific phenotypes (34). This is because non-allelic genetic variations and/or environmental influences underlie these disorders whose phenotypes behave as complex traits. A few examples include the identification of the role of homozygozity for the SAA1.1 allele in conferring the genetic susceptibility to renal amyloidosis in FMF (20) and the association of an insertion/deletion polymorphism in the ACE gene with disease severity in familial hypertrophic cardiomyopathy (35). In these disorders, the phenotypes arise from mutations in MEFV and b-MHC, but are modulated by independently inherited genetic variation. In this report, we show that interactions among multiple genes, whose products are confirmed or putative constituents of ATTR deposits, or metabolically interact with TTR, modulate the onset of the first symptoms and predispose individuals to disease in the presence of the V30M mutation in TTR. The exact nature of the effects identified here requires further study with potential application in the development of genetic screening with prognostic value pertaining to the onset of disease in the TTR V30M carriers.
If the effects of additional single or interacting genes dictate the heterogeneity of phenotype, as reflected in variability of onset and clinical expression (with the same TTR mutation), the products encoded by alleles at such loci could contribute to the process of wild-type TTR deposition in elderly individuals without a mutation (senile systemic amyloidosis), a phenomenon not readily recognized as having a genetic basis because of the insensitivity of family history in the elderly.
Safety and Efficacy of RNAi Therapy for Transthyretin Amyloidosis
Transthyretin amyloidosis is caused by the deposition of hepatocyte-derived transthyretin amyloid in peripheral nerves and the heart. A therapeutic approach mediated by RNA interference (RNAi) could reduce the production of transthyretin.
Methods We identified a potent antitransthyretin small interfering RNA, which was encapsulated in two distinct first- and second-generation formulations of lipid nanoparticles, generating ALN-TTR01 and ALN-TTR02, respectively. Each formulation was studied in a single-dose, placebo-controlled phase 1 trial to assess safety and effect on transthyretin levels. We first evaluated ALN-TTR01 (at doses of 0.01 to 1.0 mg per kilogram of body weight) in 32 patients with transthyretin amyloidosis and then evaluated ALN-TTR02 (at doses of 0.01 to 0.5 mg per kilogram) in 17 healthy volunteers.
Results Rapid, dose-dependent, and durable lowering of transthyretin levels was observed in the two trials. At a dose of 1.0 mg per kilogram, ALN-TTR01 suppressed transthyretin, with a mean reduction at day 7 of 38%, as compared with placebo (P=0.01); levels of mutant and nonmutant forms of transthyretin were lowered to a similar extent. For ALN-TTR02, the mean reductions in transthyretin levels at doses of 0.15 to 0.3 mg per kilogram ranged from 82.3 to 86.8%, with reductions of 56.6 to 67.1% at 28 days (P<0.001 for all comparisons). These reductions were shown to be RNAi mediated. Mild-to-moderate infusion-related reactions occurred in 20.8% and 7.7% of participants receiving ALN-TTR01 and ALN-TTR02, respectively.
ALN-TTR01 and ALN-TTR02 suppressed the production of both mutant and nonmutant forms of transthyretin, establishing proof of concept for RNAi therapy targeting messenger RNA transcribed from a disease-causing gene.
Alnylam May Seek Approval for TTR Amyloidosis Rx in 2017 as Other Programs Advance
Officials from Alnylam Pharmaceuticals last week provided updates on the two drug candidates from the company’s flagship transthyretin-mediated amyloidosis program, stating that the intravenously delivered agent patisiran is proceeding toward a possible market approval in three years, while a subcutaneously administered version called ALN-TTRsc is poised to enter Phase III testing before the end of the year.
Meanwhile, Alnylam is set to advance a handful of preclinical therapies into human studies in short order, including ones for complement-mediated diseases, hypercholesterolemia, and porphyria.
The officials made their comments during a conference call held to discuss Alnylam’s second-quarter financial results.
ATTR is caused by a mutation in the TTR gene, which normally produces a protein that acts as a carrier for retinol binding protein and is characterized by the accumulation of amyloid deposits in various tissues. Alnylam’s drugs are designed to silence both the mutant and wild-type forms of TTR.
Patisiran, which is delivered using lipid nanoparticles developed by Tekmira Pharmaceuticals, is currently in a Phase III study in patients with a form of ATTR called familial amyloid polyneuropathy (FAP) affecting the peripheral nervous system. Running at over 20 sites in nine countries, that study is set to enroll up to 200 patients and compare treatment to placebo based on improvements in neuropathy symptoms.
According to Alnylam Chief Medical Officer Akshay Vaishnaw, Alnylam expects to have final data from the study in two to three years, which would put patisiran on track for a new drug application filing in 2017.
Meanwhile, ALN-TTRsc, which is under development for a version of ATTR that affects cardiac tissue called familial amyloidotic cardiomyopathy (FAC) and uses Alnylam’s proprietary GalNAc conjugate delivery technology, is set to enter Phase III by year-end as Alnylam holds “active discussions” with US and European regulators on the design of that study, CEO John Maraganore noted during the call.
In the interim, Alnylam continues to enroll patients in a pilot Phase II study of ALN-TTRsc, which is designed to test the drug’s efficacy for FAC or senile systemic amyloidosis (SSA), a condition caused by the idiopathic accumulation of wild-type TTR protein in the heart.
Based on “encouraging” data thus far, Vaishnaw said that Alnylam has upped the expected enrollment in this study to 25 patients from 15. Available data from the trial is slated for release in November, he noted, stressing that “any clinical endpoint result needs to be considered exploratory given the small sample size and the very limited duration of treatment of only six weeks” in the trial.
Vaishnaw added that an open-label extension (OLE) study for patients in the ALN-TTRsc study will kick off in the coming weeks, allowing the company to gather long-term dosing tolerability and clinical activity data on the drug.
Enrollment in an OLE study of patisiran has been completed with 27 patients, he said, and, “as of today, with up to nine months of therapy … there have been no study drug discontinuations.” Clinical endpoint data from approximately 20 patients in this study will be presented at the American Neurological Association meeting in October.
As part of its ATTR efforts, Alnylam has also been conducting natural history of disease studies in both FAP and FAC patients. Data from the 283-patient FAP study was presented earlier this year and showed a rapid progression in neuropathy impairment scores and a high correlation of this measurement with disease severity.
During last week’s conference call, Vaishnaw said that clinical endpoint and biomarker data on about 400 patients with either FAC or SSA have already been collected in a nature history study on cardiac ATTR. Maraganore said that these findings would likely be released sometime next year.
The first medication for a rare and often fatal protein misfolding disorder has been approved in Europe. On November 16, the E gave a green light to Pfizer’s Vyndaqel (tafamidis) for treating transthyretin amyloidosis in adult patients with stage 1 polyneuropathy symptoms. [Jeffery Kelly, La Jolla]
The most clinically advanced RNA interference (RNAi) therapeutic achieved a milestone in April when Alnylam Pharmaceuticals in Cambridge, Massachusetts, reported positive results for patisiran, a small interfering RNA (siRNA) oligonucleotide targeting transthyretin for treating familial amyloidotic polyneuropathy (FAP). …
FAP is characterized by the systemic deposition of amyloidogenic variants of the transthyretin protein, especially in the peripheral nervous system, causing a progressive sensory and motor polyneuropathy.
FAP is caused by a mutation of the TTR gene, located on human chromosome 18q12.1-11.2.[5] A replacement of valine by methionine at position 30 (TTR V30M) is the mutation most commonly found in FAP.[1] The variant TTR is mostly produced by the liver.[citation needed] The transthyretin protein is a tetramer. ….
FAP is caused by a mutation of the TTR gene, located on human chromosome18q12.1-11.2.[5] A replacement of valine by methionine at position 30 (TTR V30M) is the mutation most commonly found in FAP.[1] The variant TTR is mostly produced by the liver.[citation needed] The transthyretin protein is a tetramer. The tetramer has to dissociate into misfolded monomers to aggregate into a variety of structures including amyloid fibrils. Because most patients are heterozygotes, they deposit both mutant and wild type TTR subnits.
FAP is inherited in an autosomal dominant manner.[2] This means that the defective gene responsible for the disorder is located on anautosome (chromosome 18 is an autosome), and only one copy of the defective gene is sufficient to cause the disorder, when inherited from a parent who has the disorder.
ATTRV30M-related amyloidosis
Familial amyloid polyneuropathy type I (Portuguese-Swedish-Japanese Type)
TTR amyloid neuropathy
Transthyretin amyloid neuropathy
Transthyretin amyloid polyneuropathy
Prevalence
Unknown
Inheritance
Autosomal dominant
Age of onset
Adult
Familial amyloid polyneuropathy (FAP) or transthyretin (TTR) amyloid polyneuropathy is a progressive sensorimotor and autonomic neuropathy of adulthood onset. Weight loss and cardiac involvement are frequent; ocular or renal complications may also occur. The prevalence worldwide is unknown, but the prevalence in the general population in Japan has recently been estimated at around 1 per million.
FAP is clinically heterogeneous, with the clinical presentation depending on the genotype and geographic origin. FAP usually presents as a length-dependent sensory polyneuropathy with autonomic disturbances. Inaugural manifestations are paresthesiae, pain or trophic lesions of the feet, gastrointestinal disorders or weight loss. The most pronounced sensory loss involves pain and temperature sensation. Motor loss occurs later. Autonomic features include postural hypotension, and gastrointestinal and genitourinary disorders.
FAP is transmitted as an autosomal dominant trait and is caused by mutations in the TTR gene (18q12.1). 100 TTR mutations have been identified so far and are associated with varying patterns of organ involvement, age of onset and disease progression. The most common variant is the TTR Val30Met substitution for which several endemic foci have been identified most notably from Portugal, Japan and Sweden. However, the Val30Met phenotype varies between these countries.
Detection of amyloid-associated TTR mutations is required for diagnosis. However, identification of a disease-causing mutation is not considered as diagnostic because penetrance is variable. Clinical observation and tissue biopsy (from the nerve or kidney, labial salivary glands, subcutaneous fat tissue or rectal mucosa) are required for a definitive diagnosis: amyloid deposits are characterized by Congo red staining on light microscopy and green birefringence on polarized light microscopy.
The differential diagnosis should include diabetic neuropathy, chronic inflammatory demyelinating polyneuropathy (see this term), and light chain (AL), gelsolin and apolipoprotein A1 amyloidosis (see these terms). Antenatal diagnosis through chorionic villus sampling should be proposed to patients with early-onset (< 40 years) forms of FAP.
Genetic counseling should be offered to affected families and presymptomatic detection of relatives of an index case is important to allow early diagnosis.
Management of FAP should be multidisciplinary, involving a neurologist, geneticist, cardiologist and liver surgeon. Liver transplantation (LT) is currently the only treatment for preventing synthesis of the amyloidogenic variants of TTR. LT can stop progression of the disease during its early stages. Symptomatic treatments are essential for sensorimotor and autonomic neuropathy and visceral complications.
FAP is a severe and disabling disease. Severe cardiac, renal and ocular manifestations may develop. Death occurs within a mean interval of 10.8 years after onset of the inaugural symptoms and may occur suddenly or may be secondary to infections or cachexia.
Familial amyloid polyneuropathies (FAPs) are a group of life-threatening multisystem disorders transmitted as an autosomal dominant trait. Nerve lesions are induced by deposits of amyloid fibrils, most commonly due to mutated transthyretin (TTR). Less often the precursor of amyloidosis is mutant apolipoprotein A-1 or gelsolin. The first identified cause of FAP-the TTR Val30Met mutation-is still the most common of more than 100 amyloidogenic point mutations identified worldwide. The penetrance and age at onset of FAP among people carrying the same mutation vary between countries. The symptomatology and clinical course of FAP can be highly variable. TTR FAP typically causes a nerve length-dependent polyneuropathy that starts in the feet with loss of temperature and pain sensations, along with life-threatening autonomic dysfunction leading to cachexia and death within 10 years on average. TTR is synthesised mainly in the liver, and liver transplantation seems to have a favourable effect on the course of neuropathy, but not on cardiac or eye lesions. Oral administration of tafamidis meglumine, which prevents misfolding and deposition of mutated TTR, is under evaluation in patients with TTR FAP. In future, patients with FAP might benefit from gene therapy; however, genetic counselling is recommended for the prevention of all types of FAP.
The course and prognostic factors of familial amyloid polyneuropathy after liver transplantation
David Adams, Didier Samuel, Catherine Goulon-Goeau, …, Henri Bismuth, Gérard Said
Familial amyloid polyneuropathy (FAP) associated with mutations of the transthyretin (TTR) gene is the most common type of FAP, a devastating disease causing death within 10 years after the first symptoms. Because most of the amyloidogenic mutated TTR is secreted by the liver, transplantation is widely used to treat these patients, but long-term quantitative evaluation of the effects of liver transplantation on the progression of the neuropathy are not available. We have treated 45 patients with symptomatic TTR-FAP, including 43 with the Met30 TTR gene mutation, and report on the results of periodic evaluation of markers of neuropathy in 25 of them, who have been followed for more than 2 years after liver transplantation (mean follow-up 4 years). The overall survival rates at 1 and 5 years were 82 and 60%, respectively. Urinary incontinence and a low Norris score at liver transplantation were associated with poorer outcome. The motor score stabilized in seven of 11 patients (64%) with mild sensorimotor neuropathy (walking unaided) and in two of the eight patients (25%) with severe sensorimotor deficit (walking with aid) at liver transplantation. In five other patients, deterioration of motor deficit occurred only within the first year after liver transplantation, but was progressive after this interval in two patients. None of the six patients with pure sensory neuropathy developed motor loss and superficial sensory loss remained unchanged. Two years after liver transplantation, the rate of myelinated axon loss in nerve biopsy specimens was markedly lower in seven transplanted patients (0.9/mm2 of endoneurial area/month) than in non-transplanted patients (70/mm2 of endoneurial area/month). Symptoms of dysautonomia and quantitated cardiocirculatory autonomic tests remained unchanged. In all patients, serum mutated TTR decreased to 2.5% of pre-liver transplantation values and remained at this level during follow-up. We presently recommend liver transplantation in FAP patients at onset of first symptoms and exclusion of those with a Norris score below 55 and/or with urinary incontinence.
Familial Amyloid Polyneuropathy (Amyloidotic transthyretin related neuropathy [ATTR]
Transthyretin (TTR) amyloidosis is an autosomal dominant disorder caused by the deposition of insoluble amyloid fibrils around peripheral nerves and in various tissues, including the heart muscle. Based on the predominant organ involvement, several distinct subtypes have been reported.
Familial amyloid polyneuropathy (FAP) aka TTR amyloid neuropathy is characterized by slowly progressive, peripheral sensorimotor polyneuropathy and autonomic dysfunction. Disease onset is usually in the third to fourth decade of life. Sensory neuropathy starts in the lower extremities with paresthesia, impaired pain and temperature sensation, followed by loss of motor function. Autonomic neuropathy usually manifests with orthostatic hypotension, constipation alternating with diarrhea, vomiting, impotence or hypohidrosis. Unrelated to neuropathy, other organs manifestations may include cardiomyopathy, vitreous opacities and CNS amyloidosis.
Leptomeningeal amyloidosis aka oculoleptomeningeal amyloidosis affects predominantly the central nervous system, sometimes combined with visual impairment.
Cardiac amyloidosis usually manifests in the sixth decade of life with progressive left ventricular hypertrophy and restrictive cardiomyopathy. In a subset of families with cardiac amyloidosis, peripheral neuropathy may be completely absent or very mild.
Treatment: Currently, the only effective treatment for FAP is an orthotopic liver transplant to stop production of misfolded amyloid protein. In patients with severe amyloid cardiomyopathy, a heart transplant may be necessary. Different drugs designed to prevent or alleviate accumulation of TTR amyloid protein (transthyretin amyloidois inhibitors) are currently under investigation.
The systemic amyloidoses are a family of diseases induced by misfolded or misassembled proteins. Extracellular deposition of these proteins as soluble or insoluble cross β-sheets disrupts vital organ function.1 More than 27 different precursor proteins have the propensity to form amyloid fibrils.2 The particular precursor protein that misfolds to form amyloid fibrils defines the amyloid type and predicts the patient’s clinical course. Several types of amyloid can infiltrate the heart, resulting in progressive diastolic and systolic dysfunction, congestive heart failure, and death. Treatment of cardiac amyloidosis is dictated by the amyloid type and degree of involvement. Consequently, early recognition and accurate classification are essential.3
The diagnosis of amyloidosis requires histological identification of amyloid deposits. Congo Red staining renders amyloid deposits salmon pink by light microscopy, with a characteristic apple green birefringence under polarized light conditions (Figure 1). Additional immunohistochemical staining for precursor proteins identifies the type of amyloidosis (Figure 2).4 Ultimately, immunogold electron microscopy and mass spectrometry confer the greatest sensitivity and specificity for amyloid typing.5,6
Transthyretin participates in beta-amyloid transport from the brain to the liver- involvement of the low-density lipoprotein receptor-related protein 1?
Transthyretin (TTR) binds Aβ peptide, preventing its deposition and toxicity. TTR is decreased in Alzheimer’s disease (AD) patients. Additionally, AD transgenic mice with only one copy of the TTR gene show increased brain and plasma Aβ levels when compared to AD mice with both copies of the gene, suggesting TTR involvement in brain Aβ efflux and/or peripheral clearance. Here we showed that TTR promotes Aβ internalization and efflux in a human cerebral microvascular endothelial cell line, hCMEC/D3. TTR also stimulated brain-to-blood but not blood-to-brain Aβ permeability in hCMEC/D3, suggesting that TTR interacts directly with Aβ at the blood-brain-barrier. We also observed that TTR crosses the monolayer of cells only in the brain-to-blood direction, as confirmed by in vivo studies, suggesting that TTR can transport Aβ from, but not into the brain. Furthermore, TTR increased Aβ internalization by SAHep cells and by primary hepatocytes from TTR+/+ mice when compared to TTR−/− animals. We propose that TTR-mediated Aβ clearance is through LRP1, as lower receptor expression was found in brains and livers of TTR−/− mice and in cells incubated without TTR. Our results suggest that TTR acts as a carrier of Aβ at the blood-brain-barrier and liver, using LRP1.
Transthyretin (Prealbumin) in Health and Disease: Nutritional Implications
Annual Review of Nutrition
Vol. 14: 495-533 (Volume publication date July 1994)
DOI: 10.1146/annurev.nu.14.070194.002431
Y Ingenbleek, and V Young
Plasma Transthyretin as a Biomarker of Lean Body Mass and Catabolic States1,2
Plasma transthyretin (TTR) is a plasma protein secreted by the liver that circulates bound to retinol-binding protein 4 (RBP4) and its retinol ligand. TTR is the sole plasma protein that reveals from birth to old age evolutionary patterns that are closely superimposable to those of lean body mass (LBM) and thus works as the best surrogate analyte of LBM. Any alteration in energy-to-protein balance impairs the accretion of LBM reserves and causes early depression of TTR production. In acute inflammatory states, cytokines induce urinary leakage of nitrogenous catabolites, deplete LBM stores, and cause an abrupt decrease in TTR and RBP4 concentrations. As a result, thyroxine and retinol ligands are released in free form, creating a second frontline that strengthens that primarily initiated by cytokines. Malnutrition and inflammation thus keep in check TTR and RBP4 secretion by using distinct and unrelated physiologic pathways, but they operate in concert to downregulate LBM stores. The biomarker complex integrates these opposite mechanisms at any time and thereby constitutes an ideally suited tool to determine residual LBM resources still available for metabolic responses, hence predicting outcomes of the most interwoven disease conditions.
Evaluating the binding selectivity of transthyretin amyloid fibril inhibitors in blood plasma
Hans E. Purkey, Michael I. Dorrell, and Jeffery W. Kelly*
Department of Chemistry and The Skaggs Institute of Chemical Biology, The Scripps Research Institute, 10550 North Torrey Pines Road, MB12, La Jolla, CA 92037 http://www.pnas.org/content/98/10/5566.full.pdf
Transthyretin (TTR) tetramer dissociation and misfolding facilitate assembly into amyloid fibrils that putatively cause senile systemic amyloidosis and familial amyloid polyneuropathy. We have previously discovered more than 50 small molecules that bind to and stabilize tetrameric TTR, inhibiting amyloid fibril formation in vitro. A method is presented here to evaluate the binding selectivity of these inhibitors to TTR in human plasma, a complex biological fluid composed of more than 60 proteins and numerous small molecules. Our immunoprecipitation approach isolates TTR and bound small molecules from a biological fluid such as plasma, and quantifies the amount of small molecules bound to the protein by HPLC analysis. This approach demonstrates that only a small subset of the inhibitors that saturate the TTR binding sites in vitro do so in plasma. These selective inhibitors can now be tested in animal models of TTR amyloid disease to probe the validity of the amyloid hypothesis. This method could be easily extended to evaluate small molecule binding selectivity to any protein in a given biological fluid without the necessity of determining or guessing which other protein components may be competitors. This is a central issue to understanding the distribution, metabolism, activity, and toxicity of potential drugs.
Amyloid diseases are characterized by the conversion of soluble proteins or peptides into insoluble b-sheet-rich amyloid fibrils. There are currently 17 different human proteins known to form amyloid fibrils in vivo (1–4). These fibrils, or their oligomeric precursors, are thought to cause pathology either through disruption of normal cellular function or by direct toxicity (5–8). X-ray fibril diffraction and electron microscopy reconstruction of amyloid fibrils reveal filaments that have a lamellar cross b-sheet structure wrapped around one another (9–13). Folded proteins form amyloid fibrils through partial unfolding triggered by a change of local environment, a mutation in the protein, or both (8, 14–20).
Transthyretin (TTR) is a tetrameric protein composed of identical 127-aa subunits that fold into a b-sandwich tertiary structure. It is found in both the plasma (3.6 mM) and cerebrospinal fluid (CSF) (0.36 mM) of humans. The TTR tetramer has two negatively cooperative C2 symmetric thyroxine (T4)-binding sites (21–23). In the CSF, it binds and transports the thyroid hormone T4 and the retinol-binding protein (RBP), which in turn transports vitamin A. In the plasma, only 10–15% of TTR has T4 bound to it, as thyroid-binding globulin has an order of magnitude higher affinity for T4 than does TTR (24). TTR fibril formation is linked to two amyloid diseases in which the fibrils are composed of full-length protein. Deposition of wild-type TTR is associated with cardiac dysfunction in the disease senile systemic amyloidosis (SSA) (25, 26). More than 70 different single-site mutants have been linked to early-onset amyloid deposition in diseases with a spectrum of clinical manifestations, collectively referred to as familial amyloid polyneuropathy (FAP) (27–35).
We have discovered compounds, through both screening and structure-based design, that dramatically inhibit TTR amyloid fibril formation in vitro (36–42). To stabilize the TTR tetramer and thus prevent amyloid fibril formation in SSA and FAP, these small molecules must be able to selectively bind to TTR in human blood plasma over all other plasma proteins. Possible competitors include thyroid-binding globulin (TBG), which has an order of magnitude higher affinity for TTR’s natural ligand, T4; and albumin, which binds numerous hydrophobic small molecules and is present at a concentration two orders of magnitude higher than TTR, as well as the other plasma proteins. Historically, one was forced to choose two or three of the most likely protein competitors and evaluate their relative affinities for the small molecule in comparison to the protein of interest. The advantage of the approach outlined within this article is that the binding selectivity of TTR amyloid inhibitors in human plasma is determined without having to make assumptions as to which proteins may competitively bind the TTR ligand. Compounds that bind to TTR selectively in plasma are the best candidates for further evaluation in animal models and, ultimately, in human clinical trials.
Analysis of Nonsteroidal Antiinflammatory Drugs (NSAIDs)
The first compounds evaluated for selective binding to TTR in plasma were the NSAIDs previously identified to be potent TTR amyloid inhibitors in vitro (37, 42). Because these compounds are already approved by the Food and Drug Administration, they could easily be evaluated in human clinical trials for another indication if they proved to be selective TTR binders in human plasma. However, none of the NSAIDs exhibited significant selectivity for binding TTR in human plasma at a concentration of 10.8 mM (Table 1), although most exhibit a submicromolar Kd (37, 50). The most selective NSAIDs, flufenamic acid (1) and mefenamic acid (2), only had 0.2 eq of a maximum of 2 molar eq bound to TTR. However, fenoprofen (7), flurbiprofen (6), flufenamic acid (1), mefenamic acid (2), and diflunisal (4) all have maximal therapeutic plasma concentrations exceeding 20 mM (51, 52). When these compounds were incubated with plasma at their maximal therapeutic concentrations, flufenamic acid and diflunisal showed increased binding selectivity (stoichiometry) to TTR (Table 1). Diflunisal (4) is notable in that its 224 mM maximal therapeutic concentration leads to 0.85 eq of drug bound to TTR. Increasing the concentration of all other NSAIDs to their maximal therapeutic dose did not result in dramatic increases in binding selectivity, likely because of binding to other plasma proteins.
Analysis of the Remaining Lead Compounds. Approximately 40 additional small molecule amyloid inhibitors were evaluated for their ability to bind to TTR in plasma by using our immunoprecipitationyHPLC approach (Fig. 2). These compounds were derived from screening or structure-based design and identified as promising by an in vitro fibril formation assay (refs. 40–42; V. H. Oza, H. M. Petrassi, and J.W.K., unpublished data). Lead compounds having diverse structures including biaryls, biarylamines, stilbenes, and dibenzofurans showed promising selectivity (Table 2). Three compounds from this group (9-11) possess excellent TTR-binding selectivity in plasma. At a concentration of 10.8 mM, they exhibit saturation of .1 of the two possible binding sites in the TTR tetramer. Determination of the TTR-binding affinities of these three compounds in buffer shows that the Kd values do not correlate with the plasma binding selectivity (Table 2). For example, inhibitors 9 and 10 have greater than an order of magnitude difference in Kd but nearly identical binding selectivity (stoichiometry) to TTR in plasma. Moreover, compounds with modest binding selectivity, such as flufenamic acid (1), have been previously determined to have Kd values very similar to those exhibiting excellent selectivities (37). Mass spectrometry confirmed the identity of inhibitors 9-12 isolated by immunoprecipitation HPLC as the compounds that were initially incubated with plasma.
Binding to plasma proteins is an important factor in determining the overall distribution, metabolism, activity, and toxicity of a drug (55). In this particular case, we desire small molecules that bind to the plasma protein TTR over protein competitors whose identities are not known and likely change with the small molecule under evaluation. This binding is known to stabilize TTR’s normally folded state, thus preventing the conformational changes required for amyloidogenicity (14, 36). The immunoprecipitationyHPLCbased binding selectivity method outlined above allows quantification of the stoichiometry of small molecule binding to TTR in human plasma in the presence of all other plasma proteins and numerous competing small molecules without the use of tags, such as radiolabels, on the small molecule. Immunoprecipitation has been used previously to determine the stoichiometry of metal ion binding to specific plasma proteins (56, 57). However, to our knowledge, this is the first use of the technique to determine the binding selectivity of a small molecule to a single protein in human plasma. In principle, this approach is applicable to evaluate the binding selectivity of small molecules to any plasma protein, provided that a highly selective antibody for the protein can be generated, binding does not block the epitope or destroy it by conformational change, and appropriate wash steps can be introduced to avoid nonspecific binding of the small molecule and other proteins to the resin.
The Kelly Group Research
Transthyretin amyloid diseases: understanding the mechanism of proteotoxicity and inhibition of amyloid fibril formation
Figure 1: Three dimensional structure of the flufenamic acid-transthyretin tetramer complex. The small organic molecule, flufenamic acid, inhibits the conformational changes of transthyretin associated with amyloid fibril formation. Courtesy of Steven Johnson.
Transthyretin is a 55 kDa homotetrameric protein (Figure 1) that transports L-thyroxine and holo-retinol binding protein in the serum and cerebrospinal fluid of humans. We discovered that conformational changes alone enable transthyretin aggregation. Transthyretin amyloid formation in vivo is initiated by dissociation of the native tetramer under a denaturation stress of unknown origin. Subsequently, the resulting monomers can partially denature and misassemble into amyloid fibrils and other amorphous aggregates. Aggregation by transthyretin monomers under acidic conditions (conditions that render transthyretin amyloidogenesis fast on a laboratory time scale) occurs via a downhill polymerization mechanism, which means that every step along the amyloid formation pathway is energetically favorable and fast relative to tetramer dissociation. Thus, tetramer dissociation is rate limiting for transthyretin amyloid formation in the case of the wild type protein and for the vast majority of mutants.
Stabilizing the native tetrameric state of transthyretin should ameliorate transthyretin amyloid diseases. This hypothesis is supported by the observation of trans-suppression, in which compound heterozygotes expressing both a disease-associated mutation (e.g., V30M) and a trans-suppressor mutation (e.g., T119M) do not develop transthyretin amyloid disease. We have shown that the trans-suppressor mutation T119M inhibits amyloid formation by kinetically stabilizing (i.e., dramatically slowing the dissociation of) mixed transthyretin tetramers.
We have designed numerous small molecules based on the crystal structures of transthyretin that are now established to avidly bind to the unoccupied L-thyroxine binding sites within transthyretin. We have shown that small molecule binding to these sites inhibits amyloid formation in vitro by selectively stabilizing the native tetrameric state over the dissociative transition state, thus raising the energetic barrier for tetramer dissociation, dramatically slowing the rate-limiting step in the aggregation pathway. Over the past decade, we have identified and synthesized over 1000 small molecule inhibitors of transthyretin amyloid formation that group into half a dozen distinct families. The inhibitors are typically composed of two differentially-substituted aromatic rings connected by linkers of variable chemical composition.
These small molecule kinetic stabilizers either just bind to transthyretin or bind and then react chemoselectively with only one of eight lysine ε-amino groups within transthyretin. In collaboration with Dr. Ian Wilson (The Scripps Research Institute, Department of Molecular Biology), we systematically ranked a myriad of possibilities for the three substructures composing a typical transthyretin kinetic stabilizer. We used these data in a substructure combination strategy to develop very potent and selective transthyretin kinetic stabilizers. In collaboration with Dr. Joel Buxbaum (The Scripps Research Institute, Department of Molecular and Experimental Medicine), these and other compounds are being tested in cell and mouse models.
These data should allow us to be able to predict the structures of potent and selective transthyretin amyloidogenesis inhibitors that are largely devoid of characteristics undesirable for a clinical candidate.
In a recently completed placebo-controlled, double-blind clinical trial carried out by FoldRx Pharmaceuticals (a company that Kelly cofounded), benzoxazoles discovered by the Kelly Laboratory and developed by FoldRx Pharmaceuticals proved safe and effective at halting the progression of familial amyloid polyneuropathy by a myriad of metrics. This transthyretin kinetic stabilizer, now named Tafamidis, provides the first pharmacological evidence that the process of amyloid fibril formation causes the transthyretin amyloid diseases—reinvigorating efforts of other investigators and companies to do the same in other amyloid diseases. In collaboration with Dr. Martha Skinner and Dr. John Berk at Boston University, another kinetic stabilizer discovered by the Kelly Laboratory, diflunisal, is being tested in a second placebo-controlled human clinical trial for familial amyloid polyneuropathy that is currently enrolling patients.
In collaboration with Dr. Bill Balch (The Scripps Research Institute, Department of Cell Biology) and Dr. Luke Wiseman (The Scripps Research Institute, Department of Molecular and Experimental Medicine), we investigated the relationship between the secretion of destabilized transthyretin variants and the pathology of the disease they cause. The earliest onset (onset at 20-30 years of age) and most severe transthyretin amyloid diseases are generally associated with mutations that strongly destabilize the transthyretin tetramer, resulting in facile transthyretin dissociation and misfolded monomer misassembly into aggregates in the peripheral nerves. However, the most destabilized variants characterized to date, A25T and D18G transthyretin, do not cause an early onset systemic amyloid disease because they are intercepted by the degradation component of the proteostasis network within liver cells—the liver is where most of the transthyretin in the blood plasma is produced. Because of endoplasmic reticulum-associated degradation of these highly destabilized transthyretin variants within the secretory pathway of liver cells, the concentration of the destabilized mutant transthyretin in blood plasma would not be high enough to enable the amyloidogenesis responsible for pathology. Interestingly, these mutants lead to a very rare brain disease, with an intermediate age of onset (40-50 years old), because the choroid plexus is more permissive in its ability to secrete highly destabilized transthyretin variants for reasons that we are seeking to understand. These results suggest that endoplasmic reticulum-assisted folding mediated by the proteostasis network determines protein secretion in a tissue-specific manner, and we propose that its competition with endoplasmic reticulum-associated degradation may explain the appearance of tissue-selective amyloid diseases.
Is there a CRISPR alternative?
CRISPR biotech Intellia strikes licensing deal with Regeneron, readies IPO
Intellia Therapeutics, one of several companies working to develop CRISPR/Cas 9 technology commercially, on Monday filed to go public in an initially priced $120 million IPO. Concurrently, the biotech announced a collaboration and licensing deal with Regeneron Pharmaceuticals aimed at advancing up to 10 CRISPR-based programs, focusing primarily on liver diseases.
Regeneron will pay Intellia $75 million upfront, as well as investing $50 million in Intellia’s forthcoming IPO. Additionally, the agreement includes as much as $320 million in milestone payments, according to SEC filing documents.
The first program to be co-developed with Regeneron will target a rare genetic disorder known as ATTR, which can causes severely impaired nerve or cardiac function.
Intellia hopes CRISPR gene-editing can cure the genetic disorder ATTR, which is caused by a buildup of the transthyretin (TTR) protein in tissue. By “knocking out” TTR expression in the liver, Intellia could reduce or eliminate the disease-causing buildup.
A view by Larry H. Bernstein, MD, FCAP
I can only wish them success in a project that may well be a search for the Trojan Horse. TTR is also synthesized in the choroid plexus. In addition, knocking out TTR expression in the liver is not likely to fit a mechanism leading to TTR buildup in tissue. The TTR is a plasma tetrameric transport protein released into the circulation for transport of TH with a bound retinol-binding protein carrying one retinol per tetrameric protein. Other considerations are the nuclear release and the cell binding that have been extensively studied. The buildup in tissues is a misfolded protein – amyloid, which has extensively studied fibrils. Another issue is the actual functional transport of hormone and delivery of retinoid to cross the blood brain barrier.
Transthyretin participates in betaamyloid transport from the brain to the liver- involvement of the lowdensity lipoprotein receptor-related protein 1?
The thyroid hormone binding protein transthyretin (TTR) forms a macromolecular complex with the retinol-specific carrier retinol binding protein (RBP) in the blood of higher vertebrates. Piscine TTR is shown here to exhibit high binding affnity for L-thyroxine and negligible affnity for RBP. The 1.56 A % resolution X-ray structure of sea bream TTR, compared with that of human TTR, reveals a high degree of conservation of the thyroid hormone binding sites. In contrast, some amino acid differences in discrete regions of sea bream TTR appear to be responsible for the lack of protein-protein recognition, providing evidence for the crucial role played by a limited number of residues in the interaction between RBP and TTR. Overall, this study makes it possible to draw conclusions on evolutionary relationships for RBPs and TTRs of phylogenetically distant vertebrates.
Jeffery Kelly, Ph.D., Lita Annenberg Hazen Professor of Chemistry
Chairman, Department of Molecular and Experimental Medicine
California Campus, Scripps Institute
The Skaggs Institute for Chemical Biology
San Diego, CA
Studies directed at understanding the principles of b-sheet folding utilizing rapid kinetic and thermodynamic measurements are ongoing and focused on the WW domain, a 34-residue 3-stranded b-sheet. Chemical synthesis of the WW domain allows us to incorporate unique amino acids into the fold to probe structural determinants of transition state and ground state structure.
Awards & Professional Activities
Searle Scholar Award in Biomedical Sciences, 1991-1994
Camille and Henry Dreyfus Teacher Scholar Award, 1994
Texas A&M University Teacher Scholar Award, 1994-1995
The Biophysical Society National Lecturer, 1999
The Protein Society – Dupont Young Investigator Award, 1999
Alumni Distinguished Achievement Award, State University of New York at Fredonia, 2000
Arthur C. Cope Scholar Award, American Chemical Society, 2001
Selected References
Deechongkit, S.; Nguyen, H.; Dawson, P.E.; Gruebele, M.; Kelly, J.W. “Context Dependent Contributions of Backbone H-Bonding to b-Sheet Folding Energetics” Nature 2004, 430, 101-105.
Cohen,F.: Kelly, J.W. “Therapeutic Approaches to Protein Folding Diseases” Nature, 2003, 426, 905-910.
Hammarstrom, P.; Wiseman, R.L.; Powers, E.T.; Kelly, J.W., “Prevention of Transthyretin Amyloid Disease by Changing Protein Misfolding Energetics” Science 2003, 299, 713-716.
Sawkar, A.; Cheng, W-C.; Beutler, E.; Wong, C.-H.; Balch, W.E.; Kelly, J.W. “Chemical Chaperones Increase the Cellular Activity of N370S β glucosidase; A Therapeutic Strategy for Gaucher’s Disease” Proc.Natl.Acad.Sci., 2002, 99, 15428-15433.
We evaluated the effect of cognitive stimulation (CS) on platelet total phospholipases A2activity (tPLA2A) in patients with mild cognitive impairment (MCI_P). At baseline, tPLA2A negatively correlated with Mini-Mental State Examination score (MMSE_s): patients with MMSE_s <26 (Subgroup 1) had significantly higher activity than those with MMSE_s ≥26 (Subgroup 2), who had values similar to the healthy elderly. Regarding CS effect, Subgroup 1 had a significant tPLA2A reduction, whereas Subgroup 2 did not significantly changes after training. Our results showed for the first time that tPLA2A correlates with the cognitive conditions of MCI_P, and that CS acts selectively on subjects with a dysregulated tPLA2A.
Phospholipases A2 (PLA2) form a superfamily of enzymes that catalyze production of lyso-phospholipids and free fatty acids by the hydrolysis of phospholipids sn-2 ester bond. They play a pivotal role in many physiological processes, including membrane remodelingand cell signaling [1, 2], and are involved in neurodegenerative disorders [3, 4].
PLA2 modulation is a potential therapeutic target [5, 6]; in this context, cognitive stimulation (CS) is particularly promising, not only because in animal models it has effective regulating properties [7], but also because it is non-invasive, has no side effects, and presents no contraindications.
To date, only one study has been performed in humans: in a little cohort of healthy elderly subjects, a memory training intervention was proved to modulate platelet PLA2 activity [8]. The use of platelet PLA2 as peripheral biomarker of the neuronal enzyme is convincing in light of the recent finding that total PLA2 (tPLA2) activity in thrombocytes may mirror thetotal activity in the brain [9]. Moreover, platelets are widely considered “circulating neurons” because of the similarities existing between the two cells in terms of enzymes, receptors, and metabolic products [10, 11].
On these grounds, we evaluated the effects of CS on platelet tPLA2 activity in a cohort of subjects with mild cognitive impairment (MCI).
The present study showed that in subjects with MCI, platelet tPLA2 activity correlates with patients’ cognitive conditions, and that CS acts selectively on the enzyme, i.e., it modulates the parameter only in individuals with deregulated values in comparison to the healthy elderly.
Based on the MMSE score, it was possible to subdivide at baseline the MCI cohort into two subgroups: patients with more evident cognitive impairment (MMSE score <26) and significantly higher tPLA2 activity, and individuals cognitively more preserved (MMSE score ≥26), who had tPLA2 activity similar to the healthy elderly. The finding that the increase of tPLA2 activity and the severity of the global cognitive status impairment are significantly linked suggests a possible role of tPLA2 in MCI progression. PLA2 activity alterations may lead to the synthesis of excessive proinflammatory mediators and peroxidative products [19], and inflammation and oxidative stress may contribute to the pathogenesis of Alzheimer’s disease (AD) [20, 21], of which MCI could be a prodromal condition. It is therefore conceivable that the more deregulated tPLA2 is, the more harmful molecules might be released, and the more severe the pathological consequences might become. The finding that in patients affected by AD tPLA2 activity is significantly higher than in healthy controls [22, 23] as well as in MCI subjects [23] is in line with this hypothesis.
As far as the therapeutic potentialities of CS are concerned, the protocol not only exerted positive effects on several cognitive outcomes, but also counteracted the peripheral enzymatic deregulation. Indeed, CS improved parameters linked to memory, attention, and verbal, confirming the results of others [24]. It is worth noting that CS acts on tPLA2 activity in a “dysfunction-dependent” mode: in subjects with an initial enzymatic activity higher than in the healthy elderly (Subgroup 1), CS reduced the value; in subjects with an initial enzymatic activity similar to the healthy elderly (Subgroup 2) CS did not induce any significant change. Thus, CS seems to have homeostatic properties on tPLA2 activity. This result may seem in contradictionwith the observation that in the healthy elderly CS induces platelet tPLA2 increase [8]. Actually, it is conceivable that, in absence of pathology, increased activity produced by the training improves cell functioning while in MCI, where the increased values might be linked to inflammation and oxidative stress, the protocol acts in the opposite way. Indeed, recent evidence supports the use of specific PLA2 inhibitors as preventive/therapeutic agents for inflammatory disorders [25], and several studies showed that environmental enrichment exert anti-inflammatory and neuromodulatory effects [26]. Thus, in MCI and AD, where the involvement of neuroinflammation is well established [27, 28], CS may produce a down regulation effect in the central nervous system, which might influence also circulation blood components.
In conclusion, this study suggests that platelet tPLA2 activity may be useful as peripheral biomarker to differentiate MCI patients at different pathological stages, and sustains the use of CS as non-pharmacological therapeutic strategy.
JNK: A Putative Link Between Insulin Signaling and VGLUT1 in Alzheimer’s Disease
In the present work, the involvement of JNK in insulin signaling alterations and its role in glutamatergic deficits in Alzheimer’s disease (AD) has been studied. In postmortem cortical tissues, pJNK levels were increased, while insulin signaling and the expression of VGLUT1 were decreased. A significant correlation was found between reduced expression of insulin receptor and VGLUT1. The administration of a JNK inhibitor reversed the decrease in VGLUT1 expression found in a mice model of insulin resistance. It is suggested that activation of JNK in AD inhibits insulin signaling which could lead to a decreased expression of VGLUT1, therefore contributing to the glutamatergic deficit in AD.
Normal Amplitude of Electroretinography and Visual Evoked Potential Responses in AβPP/PS1 Mice
Alzheimer’s disease has been shown to affect vision in human patients and animal models. This may pose the risk of bias in behavior studies and therefore requires comprehensive investigation. We recorded electroretinography (ERG) under isoflurane anesthesia and visual evoked potentials (VEP) in awake amyloid expressing AβPPswe/PS1dE9 (AβPP/PS1) and wild-type littermate mice at a symptomatic age. The VEPs in response to patterned stimuli were normal in AβPP/PS1 mice. They also showed normal ERG amplitude but slightly shortened ERG latency in dark-adapted conditions. Our results indicate subtle changes in visual processing in aged male AβPP/PS1 mice specifically at a retinal level.
Brain Metabolism Correlates of The Free and Cued Selective Reminding Test in Mild Cognitive Impairment
Free and Cued Selective Reminding Test (FCSRT) measures immediate and delayed episodic memory and cueing sensitivity and is suitable to detect prodromal Alzheimer’s disease (AD). The present study aimed at investigating the segregation effect of FCSRT scores on brain metabolism of memory-related structures, usually affected by AD pathology, in the Mild Cognitive Impairment (MCI) stage. A cohort of forty-eight MCI patients underwent FCSRT and 18F-FDG-PET. Multiple regression analysis showed that Immediate Free Recall correlated with brain metabolism in the bilateral anterior cingulate and delayed free recall with the left anterior cingulate and medial frontal gyrus, whereas semantic cueing sensitivity with the left posterior cingulate. FCSRT in MCI is associated with neuro-functional activity of specific regions of memory-related structures connected to hippocampal formation, such as the cingulate cortex, usually damaged in AD.
The Presence of Select Tau Species in Human Peripheral Tissues and Their Relation to Alzheimer’s Disease
Tau becomes excessively phosphorylated in Alzheimer’s disease (AD) and is widely studied within the brain. Further examination of the extent and types of tau present in peripheral tissues and their relation to AD is warranted given recent publications on pathologic spreading. Cases were selected based on the presence of pathological tau spinal cord deposits (n = 18). Tissue samples from sigmoid colon, scalp, abdominal skin, liver, and submandibular gland were analyzed by western blot and enzyme-linked immunosorbent assays (ELISAs) for certain tau species; frontal cortex gray matter was used for comparison. ELISAs revealed brain to have the highest total tau levels, followed by submandibular gland, sigmoid colon, liver, scalp, and abdominal skin. Western blots with antibodies recognizing tau phosphorylated at threonine 231(pT231), serine 396 and 404 (PHF-1), and an unmodified total human tau between residues 159 and 163 (HT7) revealed multiple banding patterns, some of which predominated in peripheral tissues. As submandibular gland had the highest levels of peripheral tau, a second set of submandibular gland samples were analyzed (n = 36; 19 AD, 17 non-demented controls). ELISAs revealed significantly lower levels of pS396 (p = 0.009) and pT231 (p = 0.005) in AD cases but not total tau (p = 0.18). Furthermore, pT231 levels in submandibular gland inversely correlated with Braak neurofibrillary tangle stage (p = 0.04), after adjusting for age at death, gender, and postmortem interval. These results provide evidence that certain tau species are present in peripheral tissues. Of potential importance, submandibular gland pT231 is progressively less abundant with increasing Braak neurofibrillary tangle stage.
Non-Verbal Episodic Memory Deficits in Primary Progressive Aphasias are Highly Predictive of Underlying Amyloid Pathology
Diagnostic distinction of primary progressive aphasias (PPA) remains challenging, in particular for the logopenic (lvPPA) and nonfluent/agrammatic (naPPA) variants. Recent findings highlight that episodic memory deficits appear to discriminate these PPA variants from each other, as only lvPPA perform poorly on these tasks while having underlying amyloid pathology similar to that seen in amnestic dementias like Alzheimer’s disease (AD). Most memory tests are, however, language based and thus potentially confounded by the prevalent language deficits in PPA. The current study investigated this issue across PPA variants by contrasting verbal and non-verbal episodic memory measures while controlling for their performance on a language subtest of a general cognitive screen. A total of 203 participants were included (25 lvPPA; 29 naPPA; 59 AD; 90 controls) and underwent extensive verbal and non-verbal episodic memory testing, with a subset of patients (n = 45) with confirmed amyloid profiles as assessed by Pittsburgh Compound B and PET. The most powerful discriminator between naPPA and lvPPA patients was a non-verbal recall measure (Rey Complex Figure delayed recall), with 81% of PPA patients classified correctly at presentation. Importantly, AD and lvPPA patients performed comparably on this measure, further highlighting the importance of underlying amyloid pathology in episodic memory profiles. The findings demonstrate that non-verbal recall emerges as the best discriminator of lvPPA and naPPA when controlling for language deficits in high load amyloid PPA cases.
Prion and other amyloid-forming diseases represent a group of neurodegenerative disorders that affect both animals and humans. The role of metal ions, especially copper and zinc is studied intensively in connection with these diseases. Their involvement in protein misfolding and aggregation and their role in creation of reactive oxygen species have been shown. Recent data also show that metal ions not only bind the proteins with high affinity, but also modify their biochemical properties, making them important players in prion-related diseases. In particular, the level of zinc ions is tightly regulated by several mechanisms, including transporter proteins and the low molecular mass thiol-rich metallothioneins. From four metallothionein isoforms, metallothionein-3, a unique brain-specific metalloprotein, plays a crucial role only in this regulation. This review critically evaluates the involvement of metallothioneins in prion- and amyloid-related diseases in connection with the relationship between metallothionein isoforms and metal ion regulation of their homeostasis.
Do Microglia Default on Network Maintenance in Alzheimer’s Disease?
Although the cause of Alzheimer’s disease (AD) remains unknown, a number of new findings suggest that the immune system may play a critical role in the early stages of the disease. Genome-wide association studies have identified a wide array of risk-associated genes for AD, many of which are associated with abnormal functioning of immune cells. Microglia are the brain’s immune cells. They play an important role in maintaining the brain’s extracellular environment, including clearance of aggregated proteins such as amyloid-β (Aβ). Recent studies suggest that microglia play a more active role in the brain than initially considered. Specifically, microglia provide trophic support to neurons and also regulate synapses. Microglial regulation of neuronal activity may have important consequences for AD. In this article we review the function of microglia in AD and examine the possible relationship between microglial dysfunction and network abnormalities, which occur very early in disease pathogenesis.
Alzheimer’s disease (AD) is a progressive, neurodegenerative disease that primarily affects the regions of the brain that are associated with high functioning. AD is characterized by progressive dementia that begins with mood changes, memory loss, and reduced cognition [1]. The primary pathogenic process in AD is the accumulation of amyloid-β protein (Aβ) [1–3]. Aβ aggregates into extracellular amyloid plaques that are a hallmark pathological feature of the disease. Aβ is cleaved from the larger amyloid-β protein precursor (AβPP) [4–6]. However, it remains unclear why Aβ, a protein fragment normally only present in small amounts within the brain, is able to accumulate in the AD brain and cause toxicity. In a small percentage (5%) of AD sufferers, the cause of the disease is genetic. Inherited mutations within the AβPP gene itself appear to predispose the protein to Aβ production [7]. Mutations within the presenilin 1 and 2 genes, encoding proteins that form part of the secretase complex that cleaves the Aβ peptide from AβPP, also result in inherited AD due to accumulations of Aβ [8–11].
The cause of AD is largely unknown for the remaining 95% of cases of sporadic AD, which typically develops a decade or two later than familial AD [12]. However, the degenerative processes are nearly identical between the two forms of the disease. Therefore, it is reasonable to assume that the underlying disease process is the same between the two forms of the disease. Genetic studies have identified a number of genetic risk factors for AD. An early discovery was that allelic variants of apolipoprotein E (ApoE) carry inherently different risks of AD [13–15]. In particular, the ɛ4 allele carries a high risk of AD, with risk of disease occurring in a dose-dependent manner based onzygosity. The ApoE ɛ4 allele is associated with increased Aβ aggregation, reduced lipid transport, and reduced receptor-mediated Aβ clearance [16]. Interestingly, ApoE is predominantly expressed by non-neuronal cells— astrocytes and microglia, rather than by neurons [17]. These findings suggested that although clinical AD manifests from neuronal degeneration, other cells of the central nervous system (CNS) may be intimately involved in pathogenesis or disease progression.
More recently, genome-wide association studies (GWAS) have been used to identify a large number of risk genes for AD. In 2013, a mutation in the triggering receptor expressed on myeloid cells 2 (TREM2) was identified [18, 19]. TREM2 is almost exclusively expressed by immune cells within the brain, and mutations to TREM2 are associated with decreased phagocytosis and an increased pro-inflammatory reactive phenotype. Individuals heterozygous for TREM2 mutations have a high risk of developing AD, however the mutation is rare [18, 19]. Additional AD risk factor genes that have been identified include genes associated with lipid processing, endocytosis, and the immune response, which have recently been covered in excellent reviews [20, 21]. The common unifying feature of these immune-associated mutations is that they are proposed to interfere with microglial function, in particular, the efficiency of phagocytosis [20]. Specifically, mutations to complement receptor 1 (CR1) and cluster of differentiation 33 (CD33) can result in reduced activity of the complement system and reduced phagocytosis [22, 23]. Phosphatidylinositol binding clathrin assembly protein (PICALM) and bridging integrator 1 (BIN1) mutations affect clathrin-mediated endocytosis [24, 25] and SORL1 mutations reduce intracellular trafficking of AβPP [26]. The function of some of these proteins in relation to phagocytosis is discussed later in this review. The identification of such a wide array of risk genes associated with reduced immune cell function now leads us to believe that abnormal functioning of immune cells may play a more important role in the early stages of disease than previously considered.
MICROGLIA
Microglia are the immune cells of the CNS and account for approximately 10% of the CNS cellpopulation, with regional variation in density [27, 28]. During embryonic development, microglia originate from yolk sac progenitor cells that migrate into the developing CNS during early embryogenesis [29,30].Following construction of the blood-brain barrier (BBB), microglia are renewed by local turnover [31]. In the healthy brain, microglia actively support neurons through the release of insulin-like growth factor 1, nerve growth factor, ciliary neurotrophic factor, and brain-derived neurotrophic factor (BDNF) [32–34]. Microglia also provide indirect support to neurons by clearance of debris to maintain the extracellular environment, and phagocytosis of apoptotic cells to facilitate neurogenesis [35, 36]. In the adult brain, microglia coordinate much of their activity with astrocytes and activate in response to similar stimuli [37, 38]. Dysfunctional signaling between microglia and astrocytes often results in chronic inflammation, a characteristic of many neurodegenerative diseases [39, 40].
Historically, it has been thought that microglia ‘rest’ when not responding to inflammatory stimuli or damage [41, 42]. However, this notion is being increasingly recognized as inaccurate [43]. When not involved in active inflammatory signaling, microglia constantly patrol the neuropil by extension and retraction of their finely branched processes [44]. Microglial activation is often broadly classified into two states; pro-inflammatory (M1) or anti-inflammatory (M2) [36, 45], based on similar phenotypes in peripheral macrophages [46]. M1 activated microglia are characterized by increased expression of pro-inflammatory mediators and cytokines, including inducible nitric oxide synthase, tumor necrosis factor-α, and interleukin-1β, often under the control of the transcription factor nuclear factor-κB [45]. Pro-inflammatory microglia rapidly retract their processes and adopt an amoeboid morphology and often migrate closer to the site of injury [47]. Anti-inflammatory M2 activation of microglia, often referred to as alternative activation, represents the other side of microglial behavior. Anti-inflammatory activation is characterized by increased expression of cytokines including arginase 1 and interleukin-10, and is associated with increased ramification of processes [45]. The polarization of microglia into M1 or M2 throughout the brain is well characterized, especially in neurodegenerative diseases [48]. In the AD brain, microglia expressing markers of M1 activation are typically localized to brain regions such as the hippocampus that are most heavily affected in the disease [49]. However, it is important to note that M1 and M2 classifications of microglia may over-simplify microglial phenotypes and may only represent the extremes of microglial activation [50]. It has been more recently proposed that microglia likely occupy a continuum between these phenotypes [39, 51].
Do microglia have multiple roles in AD?
Classical pro-inflammatory activation of microglia has long been associated with AD [39, 49]. Samples taken from late-stage AD brains contain characteristic signs of inflammation, including amoeboid morphology of microglia, high levels of pro-inflammatory cytokines in the cerebrospinal fluid, and evidence of neuronal damage due to chronic exposure to pro-inflammatory cytokines and oxidative stress [52, 53]. The cause of this inflammation may be in response to direct toxicity of Aβ to neurons resulting in activation of nearby microglia and astrocytes [53, 54]. However, Aβ may also induce inflammatory activation of microglia and astrocytes. Activated immune cells are typically present surrounding amyloid plaques [55–57], with such peri-plaque cells exhibiting strong evidence of pro-inflammatory activation [56, 58–60]. The presence of undigested Aβ particles within these activated microglia may suggest that the Aβ peptide itself is a pro-inflammatory signal for microglia [61–64]. In vitro experiments provide supporting evidence for the in vivo studies, with Aβ promoting pro-inflammatory microglial activation [65, 66], and also acting as a potent chemotactic signal [67].
However, it is important to note that although widespread inflammation is characteristic of late-stage AD, it remains unclear what role inflammation could play in early stages of the disease. Some evidence suggests that reducing inflammation through the long-term use of some non-steroidal anti-inflammatory drugs (NSAIDs) can reduce the risk of AD [68]. However, these findings have not yet been verified in clinical trials [69, 70]. Little is understood about how NSAIDs and related compounds affect the delicate balance of pro- versus anti-inflammatory microglial activity within the brain. Although there is considerable evidence to suggest that chronic inflammation may contribute to pathology in the later stages of AD, it is important to note that inflammation normally only represents a small aspect of microglial function. The non-inflammatory functions of microglia may play a more important role in early disease; specifically, microglial functions relating to maintenance of the CNS.
Phagocytosis: A vital role of microglia that may be lost in AD
SYNAPTIC PRUNING: MICROGLIA CAN REGULATE NETWORK ACTIVITY
Recently, a new function has been proposed for microglia. A number of studies have provided evidence that microglia prune synapses throughout life. Microglia are known to remove extraneous synapses during development to ensure that only meaningful connections remain [43]. It was, however, thought that differentiated astrocytes performed the majority of synaptic pruning in the adult brain [91]. The discovery that microglial processes are constantly active within the brain and are often positioned near synapses raised the question of whether microglial synaptic pruning continued throughout life [44, 47, 92–94]. This question was answered in 2014 in a study that demonstrated that microglia do prune synapses into adulthood, and that this activity is important for normal brain function [95]. These findings supported those found a year earlier in a study reporting that ablation of microglia from brain slices increases synapse density and results in abnormal firing of hippocampalneurons [96].
Altered microglial behavior may underlie altered neuronal firing in AD
Altered neuronal activity is an early phenomenon in AD
The cause of DMN hypoactivity in AD is not yet clear; however studies performed in cohorts that are genetically predisposed to AD suggest that DMN hypoactivity is preceded by a period of hyperactivity and increased functional connectivity [123, 136], often manifesting as an absence of normal DMN deactivation during external tasks [137–140]. DMN hyperactivity may interfere with hippocampal memory encoding, leading to the memory deficits that are present in mild cognitive impairment [141, 142]. It has been proposed that hippocampal hyperexcitability in AD may develop as a protective mechanism against increased input from the DMN [142–144]. As AD progresses, the initial hyperexcitability of the DMN and hippocampus may result in hypoactivity due to exhaustion of compensatory mechanisms [123, 136]. Evidence from both transgenic AD mice and longitudinal human studies supports an exhaustion model of hyperactivation leading to later hypoactivation [143, 145–147]. Interestingly, a number of studies report a lower incidence of AD among those who regularly practice meditation which specifically ‘calms’ the DMN [148].
Our understanding of AD as a disease is changing. Historically considered to be primarily a disease of neuronal degeneration, this neurocentric view has widened to encompass non-neuronal cells such as astrocytes into our understanding of the disease process and pathogenesis. A proposed model for microglia in AD is shown in Fig. 2. Microglia perform a wide range of functions in the CNS and although this includes induction of an inflammatory reaction in response to damage, they also have critical roles for maintaining normal function in the brain. Recent evidence shows that microglia regulate neuronal activity through synaptic pruning throughout life as an extension on their normal phagocytosis behavior. The discovery of a large number of AD risk genes associated with reduced immune cell function suggests that perturbed microglial phagocytosis could lead to AD. In our model, altered microglial phagocytosis of synapses results in network dysfunction and onset of AD, occurring downstream of Aβ.
The immune system and microglia represent a novel target for intervention in AD. Importantly, a large number of anti-inflammatory drugs are already in use for other conditions. What is important to know at this stage is exactly how to best target immune cell function. The studies outlined here provide evidence that an indiscriminate dampening down of all microglial activity may result in a worse outcome for individuals by suppressing normal microglial regulatory functions. We currently do not know whether future microglial-based therapies should focus on reducing chronic inflammation or conversely, whether they should be aimed at boosting microglial phagocytosis. It is also likely that future treatment strategies may use a combination of approaches to target Aβ, immune cell phagocytosis and network activity. An increasing view in the AD field is that any drug or therapy needs to be provided very early in the disease process to maximize its beneficial effects. Although we are currently unable to effectively target those at risk of AD at such an early stage, advances in neuroimaging for subtle changes in network activity, or in assays for immune cell function, may provide new avenues for identification of early damage and risk of disease.
REFERENCES
[1]
Selkoe DJ ((2011) ) Alzheimer’s disease. Cold Spring Harb Perspect Biol 3: , pii: a004457.
[2]
Masters CL , Simms G , Weinman NA , Multhaup G , McDonald BL , Beyreuther K ((1985) ) Amyloid plaque core protein in Alzheimer disease and Down syndrome. Proc Natl Acad Sci U S A 82: , 4245–4249.
[3]
Glenner GG , Wong CW ((1984) ) Alzheimer’s disease: Initial report of the purification and characterization of a novel cerebrovascular amyloid protein. Biochem Biophys Res Commun 120: , 885–890.
[4]
Goldgaber D , Lerman MI , McBride OW , Saffiotti U , Gajdusek DC ((1987) ) Characterization and chromosomal localization of a cDNA encoding brain amyloid of Alzheimer’s disease. Science 235: , 877–880.
[5]
Kang J , Lemaire HG , Unterbeck A , Salbaum JM , Masters CL , Grzeschik KH , Multhaup G , Beyreuther K , Muller-Hill B ((1987) ) The precursor of Alzheimer’s disease amyloid A4 protein resembles a cell-surface receptor. Nature 325: , 733–736.
[6]
Robakis NK , Ramakrishna N , Wolfe G , Wisniewski HM ((1987) ) Molecular cloning and characterization of a cDNA encoding the cerebrovascular and the neuritic plaque amyloid peptides. Proc Natl Acad Sci U S A 84: , 4190–4194.
[7]
Levy E , Carman MD , Fernandez-Madrid IJ , Power MD , Lieberburg I , van Duinen SG , Bots GT , Luyendijk W , Frangione B ((1990) ) Mutation of the Alzheimer’s disease amyloid gene in hereditary cerebral hemorrhage, Dutch type. Science 248: , 1124–1126.
[8]
Levy-Lahad E , Wasco W , Poorkaj P , Romano DM , Oshima J , Pettingell WH , Yu CE , Jondro PD , Schmidt SD , Wang K , et al ((1995) ) Candidate gene for the chromosome 1 familial Alzheimer’s disease locus. Science 269: , 973–977.
[9]
Rogaev EI , Sherrington R , Rogaeva EA , Levesque G , Ikeda M , Liang Y , Chi H , Lin C , Holman K , Tsuda T , et al ((1995) ) Familial Alzheimer’s disease in kindreds with missense mutations in a gene on chromosome 1 related to the Alzheimer’s disease type 3 gene. Nature 376: , 775–778.
[10]
Sherrington R , Rogaev EI , Liang Y , Rogaeva EA , Levesque G , Ikeda M , Chi H , Lin C , Li G , Holman K , Tsuda T , Mar L , Foncin JF , Bruni AC , Montesi MP , Sorbi S , Rainero I , Pinessi L , Nee L , Chumakov I , Pollen D , Brookes A , Sanseau P , Polinsky RJ , Wasco W , Da Silva HA , Haines JL , Perkicak-Vance MA , Tanzi RE , Roses AD , Fraser PE , Rommens JM , St George-Hyslop PH ((1995) ) Cloning of a gene bearing missense mutations in early-onset familial Alzheimer’s disease. Nature 375: , 754–760.
Late-Onset Metachromatic Leukodystrophy with Early Onset Dementia Associated with a Novel Missense Mutation in the Arylsulfatase A Gene
A 48-year-old male patient presented with personality changes and progressive memory loss over 2 years with initially suspected Hashimoto’s encephalopathy. Strategy of diagnostic workup of early onset dementia included dementia from neurodegenerative, neuroinflammatory, metabolic/toxic, and psychiatric origin. The patient’s neurological exam was normal. MRI revealed a leukencephalopathy, predominantly in the frontal periventricular white matter, without notable changes over 2 years. On neurophysiological examination, prolonged central conduction times and a sensorimotor polyneuropathy were noted. Neuropsychological impairment included disorientation in place and a reduced short time memory. Behavioral alterations were predominated by sudden mood changes and disinhibition. Cerebrospinal fluid was normal. Despite presence of thyroid autoantibodies, glucocorticosteroid treatment did not improve the dementia. A metachromatic leukodystrophy was diagnosed by decreased arylsulfatase-A activity in leucocytes/fibroblasts and identification of a compound heterozygous mutation in the ARSA gene: c.542T>G (exon 3) and the novel mutation c.1013T>C (exon 6). Pathogenic function was suggested by bioinformatic mutation search. In a patient with early onset dementia, strategic diagnostic workup including genetic assessment revealed an adult-onset metachromatic leukodystrophy with a novel mutation in the arylsulfatase A gene.
Most-Read JAD Articles in March 2016
Microbes and Alzheimer’s Disease – Openly Available Itzhaki, Ruth F. | Lathe, Richard | Balin, Brian J. | Ball, Melvyn J. | Bearer, Elaine L. | Braak, Heiko | Bullido, Maria J. | Carter, Chris | Clerici, Mario | Cosby, S. Louise | Del Tredici, Kelly | Field, Hugh | Fulop, Tamas | Grassi, Claudio | Griffin, W. Sue T. | Haas, Jürgen | Hudson, Alan P. | Kamer, Angela R. | Kell, Douglas B. | Licastro, Federico | Letenneur, Luc | Lövheim, Hugo | Mancuso, Roberta | Miklossy, Judith | Otth, Carola | Palamara, Anna Teresa | Perry, George | Preston, Christopher | Pretorius, Etheresia | Strandberg, Timo | Tabet, Naji | Taylor-Robinson, Simon D. | Whittum-Hudson, Judith A.
Zika virus impairs growth in human neurospheres and brain organoids
Patricia P. Garcez1,2,*, Erick Correia Loiola2,†, Rodrigo Madeiro da Costa2,†,…., Rodrigo Brindeiro3, Amilcar Tanuri3, Stevens K. Rehen2,1,* 1Institute of Biomedical Sciences, Federal University of Rio de Janeiro, Rio de Janeiro, Brazil. 2D’Or Institute for Research and Education (IDOR), Rio de Janeiro, Brazil. 3Institute of Biology, Federal University of Rio de Janeiro, Rio de Janeiro, Brazil.4Institute of Biology, State University of Campinas, Campinas, Brazil. ↵*Corresponding author. Email: ppgarcez@icb.ufrj.br (P.P.G.); srehen@lance-ufrj.org (S.K.R.) Science 10 Apr 2016: http://dx.doi.org:/10.1126/science.aaf6116
Since the emergence of Zika virus (ZIKV), reports of microcephaly have increased significantly in Brazil; however, causality between the viral epidemic and malformations in fetal brains needs further confirmation. Here, we examine the effects of ZIKV infection in human neural stem cells growing as neurospheres and brain organoids. Using immunocytochemistry and electron microscopy, we show that ZIKV targets human brain cells, reducing their viability and growth as neurospheres and brain organoids. These results suggest that ZIKV abrogates neurogenesis during human brain development.
Primary microcephaly is a severe brain malformation characterized by the reduction of the head circumference. Patients display a heterogeneous range of brain impairments, compromising motor, visual, hearing and cognitive functions (1).
Microcephaly is associated with decreased neuronal production as a consequence of proliferative defects and death of cortical progenitor cells (2). During pregnancy, the primary etiology of microcephaly varies from genetic mutations to external insults. The so-called TORCHS factors (Toxoplasmosis, Rubella, Cytomegalovirus, Herpes virus, Syphilis) are the main congenital infections that compromise brain development in utero (3).
The increase in the rate of microcephaly in Brazil has been associated with the recent outbreak of Zika virus (ZIKV) (4, 5), a flavivirus that is transmitted by mosquitoes (6) and sexually (7–9). So far, ZIKV has been described in the placenta and amniotic fluid of microcephalic fetuses (10–13), and in the blood of microcephalic newborns (11, 14). ZIKV had also been detected within the brain of a microcephalic fetus (13, 14), and recently, there is direct evidence that ZIKV is able to infect and cause death of neural stem cells (15).
Here, we used human induced pluripotent stem (iPS) cells cultured as neural stem cells (NSC), neurospheres and brain organoids to explore the consequences of ZIKV infection during neurogenesis and growth with 3D culture models. Human iPS-derived NSCs were exposed to ZIKV (MOI 0.25 to 0.0025). After 24 hours, ZIKV was detected in NSCs (Fig. 1, A to D), when viral envelope protein was shown in 10.10% (MOI 0.025) and 21.7% (MOI 0.25) of cells exposed to ZIKV (Fig. 1E). Viral RNA was also detected in the supernatant of infected NSCs (MOI 0.0025) by qRT-PCR (Fig. 1F), supporting productive infection.
Confocal microscopy images of iPS-derived NSCs double stained for (A) ZIKV in the cytoplasm, and (B) SOX2 in nuclei, one day after virus infection. (C) DAPI staining, (D) merged channels show perinuclear localization of ZIKV. Bar = 100 μm. (E) Percentage of ZIKV infected SOX2 positive cells (MOI 0.25 and 0.025). (F) RT-PCR analysis of ZIKV RNA extracted from supernatants of mock and ZIKV-infected neurospheres (MOI 0.0025) after 3 DIV, showing amplification only in infected cells. RNA was extracted, qPCR performed and virus production normalized to 12h post-infection controls. Data presented as mean ± SEM, n=5, Student’s t test, *p < 0.05, **p < 0.01.
To investigate the effects of ZIKV during neural differentiation, mock- and ZIKV-infected NSCs were cultured as neurospheres. After 3 days in vitro, mock NSCs generated round neurospheres. However, ZIKV-infected NSCs generated neurospheres with morphological abnormalities and cell detachment (Fig. 2B). After 6 days in vitro (DIV), hundreds of neurospheres grew under mock conditions (Fig. 2, C and E). Strikingly, in ZIKV-infected NSCs (MOI 2.5 to 0.025) only a few neurospheres survived (Fig. 2, D and E).
Fig. 2ZIKV alters morphology and halts the growth of human neurospheres.
(A) Control neurosphere displays spherical morphology after 3 DIV. (B) Infected neurosphere showed morphological abnormalities and cell detachment after 3 DIV. (C) Culture well-plate containing hundreds of mock neurospheres after 6 DIV. (D) ZIKV-infected well-plate (MOI 2.5-0.025) containing few neurospheres after 6 DIV. Bar = 250 μm in (A) and (B), and 1 cm in (C) and (D). (E) Quantification of the number of neurospheres in different MOI. Data presented as mean ± SEM, n=3, Student’s t test, ***p < 0.01.
Mock neurospheres presented expected ultrastructural morphology of nucleus and mitochondria (Fig. 3A). ZIKV-infected neurospheres revealed the presence of viral particles, similarly to those observed in murine glial and neuronal cells (16). ZIKV was bound to the membranes and observed in mitochondria and vesicles of cells within infected neurospheres (Fig. 3, B and F, arrows). Apoptotic nuclei, a hallmark of cell death, were observed in all ZIKV-infected neurospheres analyzed (Fig. 3B). Of note, ZIKV-infected cells in neurospheres presented smooth membrane structures (SMS) (Fig. 3, B and F), similarly to those previously described in other cell types infected with dengue virus (17). These results suggest that ZIKV induces cell death in human neural stem cells and thus impairs the formation of neurospheres.
Ultrastructure of mock- and ZIKV-infected neurospheres after 6 days in vitro. (A) Mock-infected neurosphere showing cell processes and organelles, (B) ZIKV-infected neurosphere shows pyknotic nucleus, swollen mitochondria, smooth membrane structures and viral envelopes (arrow). Arrows point viral envelopes on cell surface (C), inside mitochondria (D), endoplasmic reticulum (E) and close to smooth membrane structures (F). Bar = 1 μm in (A) and (B) and 0.2 μm in (C) to (F). m = mitochondria; n = nucleus; sms = smooth membrane structures.
To further investigate the impact of ZIKV infection during neurogenesis, human iPS-derived brain organoids (18) were exposed with ZIKV, and followed for 11 days in vitro (Fig. 4). The growth rate of 12 individual organoids (6 per condition) was measured during this period (Fig. 4, A and D). As a result of ZIKV infection, the average growth area of ZIKV-exposed organoids was reduced by 40% when compared to brain organoids under mock conditions (0.624 mm2 ± 0.064 ZIKV-exposed organoids versus 1.051 mm2 ± 0.1084 mock-infected organoids normalized, Fig. 4E).
Fig. 4ZIKV reduces the growth rate of human brain organoids.
35 days old brain organoids were infected with (A) MOCK and (B) ZIKV for 11 days in vitro. ZIKV-infected brain organoids show reduction in growth compared with MOCK. Arrows point to detached cells. Organoid area was measured before and after 11 days exposure with (C) MOCK and (D) ZIKV in vitro. Plotted quantification represent the growth rate. (E) Quantification of the average of mock- and ZIKV-infected organoid area 11 days after infection in vitro. Data presented as mean ± SEM, n=6, Student’s ttest, *p < 0.05.
In addition to MOCK infection, we used dengue virus 2 (DENV2), a flavivirus with genetic similarities to ZIKV (11, 19), as an additional control group. One day after viral exposure, DENV2 infected human NSCs with a similar rate as ZIKV (fig. S1, A and B). However, after 3 days in vitro, there was no increase in caspase 3/7 mediated cell death induced by DENV2 with the same 0.025 MOI adopted for ZIKV infection (fig. S1, C and D). On the other hand, ZIKV induced caspase 3/7 mediated cell death in NSCs, similarly to the results described by Tang and colleagues (15). After 6 days in vitro, there is a significant difference in cell viability between ZIKV-exposed NSCs compared to DENV2-exposed NSCs (fig. S1, E and F). In addition, neurospheres exposed to DENV2 display a round morphology such as uninfected neurospheres after 6 days in vitro (fig. S1G). Finally, there was no reduction of growth in brain organoids exposed to DENV2 for 11 days compared to MOCK (1.023 mm2 ± 0.1308 DENV2-infected organoids versus 1.011 mm2 ± 0.2471 mock-infected organoids normalized, fig. S1, H and I). These results suggest that the deleterious consequences of ZIKV infection in human NSCs, neurospheres and brain organoids are not a general feature of the flavivirus family. Neurospheres and brain organoids are complementary models to study embryonic brain development in vitro (20, 21). While neurospheres present the very early characteristics of neurogenesis, brain organoids recapitulate the orchestrated cellular and molecular early events comparable to the first trimester fetal neocortex, including gene expression and cortical layering (18, 22). Our results demonstrate that ZIKV induces cell death in human iPS-derived neural stem cells, disrupts the formation of neurospheres and reduces the growth of organoids (fig. S2), indicating that ZIKV infection in models that mimics the first trimester of brain development may result in severe damage. Other studies are necessary to further characterize the consequences of ZIKV infection during different stages of fetal development.
Cell death impairing brain enlargement, calcification and microcephaly is well described in congenital infections with TORCHS (3, 23, 24). Our results, together with recent reports showing brain calcification in microcephalic fetuses and newborns infected with ZIKV (10, 14) reinforce the growing body of evidence connecting congenital ZIKV outbreak to the increased number of reports of brain malformations in Brazil.
C.Zanluca, V. C.Melo, A. L.Mosimann, G. I.Santos, C. N.Santos, K.Luz
, First report of autochthonous transmission of Zika virus in Brazil. Mem. Inst. Oswaldo Cruz 110, 569–572 (2015). doi:10.1590/0074-02760150192pmid:26061233
, Zika virus infection and stillbirths: A case of hydrops fetalis, hydranencephaly and fetal demise. PLOS Negl. Trop. Dis. 10, e0004517 (2016). doi:10.1371/journal.pntd.0004517pmid:26914330
Scientists report that the Zika virus may be associated with an autoimmune disorder that attacks the brain’s myelin similar to multiple sclerosis (MS). The investigators will discuss the results of their research at the upcoming American Academy of Neurology’s 68th Annual Meeting in Vancouver, Canada.
“Though our study is small, it may provide evidence that in this case the virus has different effects on the brain than those identified in current studies,” said study author Maria Lucia Brito Ferreira, M.D., with Restoration Hospital in Recife, Brazil. “Much more research will need to be done to explore whether there is a causal link between Zika and these brain problems.”
For the study, researchers followed people who came to the hospital in Recife from December 2014 to June 2015 with symptoms compatible with arboviruses, the family of viruses that includes Zika, dengue, and chikungunya. Six people then developed neurologic symptoms that were consistent with autoimmune disorders and underwent exams and blood tests. The authors saw 151 cases with neurological manifestations during a period of December 2014 to December 2015.
All of the people came to the hospital with fever followed by a rash. Some also had severe itching, muscle and joint pain, and red eyes. The neurologic symptoms started right away for some people and up to 15 days later for others.
Of the six people who had neurologic problems, two of the people developed acute disseminated encephalomyelitis (ADEM), a swelling of the brain and spinal cord that attacks the myelin. In both cases, brain scans showed signs of damage to the brain’s white matter. Unlike MS, ADEM usually consists of a single attack that most people recover from within 6 months. In some cases, the disease can reoccur. Four of the people developed Guillain-Barré syndrome (GBS), a syndrome that involves myelin of the peripheral nervous system and has a previously reported association with the Zika virus.
When they were discharged from the hospital, five of the six people still had problems with motor functioning. One person had vision problems and one had problems with memory and thinking skills. Tests showed that the participants all had Zika virus. Tests for dengue and chikungunya were negative.
“This doesn’t mean that all people infected with Zika will experience these brain problems. Of those who have nervous system problems, most do not have brain symptoms,” said Dr. Ferreira. “However, our study may shed light on possible lingering effects the virus may be associated with in the brain.”
“At present, it does not seem that ADEM cases are occurring at a similarly high incidence as the GBS cases, but these findings from Brazil suggest that clinicians should be vigilant for the possible occurrence of ADEM and other immune-mediated illnesses of the central nervous system,” noted James Sejvar, M.D., with the Centers for Disease Control and Prevention in Atlanta and a member of the American Academy of Neurology. “Of course, the remaining question is ‘why’—why does Zika virus appear to have this strong association with GBS and potentially other immune/inflammatory diseases of the nervous system? Hopefully, ongoing investigations of Zika virus and immune-mediated neurologic disease will shed additional light on this important question.”
Team at Purdue becomes the first to determine the structure of the Zika virus, which reveals insights critical to the development of effective antiviral treatments and vaccines.
The team also identified regions within the Zika virus structure where it differs from other flaviviruses, the family of viruses to which Zika belongs that includes dengue, West Nile, yellow fever, Japanese encephalitis and tick-borne encephalitic viruses.
Any regions within the virus structure unique to Zika have the potential to explain differences in how a virus is transmitted and how it manifests as a disease, said Richard Kuhn, director of the Purdue Institute for Inflammation, Immunology and Infectious Diseases (PI4D) who led the research team with Michael Rossmann, Purdue’s Hanley Distinguished Professor of Biological Sciences.
“The structure of the virus provides a map that shows potential regions of the virus that could be targeted by a therapeutic treatment, used to create an effective vaccine or to improve our ability to diagnose and distinguish Zika infection from that of other related viruses,” said Kuhn, who also is head of Purdue’s Department of Biological Sciences. “Determining the structure greatly advances our understanding of Zika – a virus about which little is known. It illuminates the most promising areas for further testing and research to combat infection.”
The Zika virus, a mosquito-borne disease, has recently been associated with a birth defect called microcephaly that causes brain damage and an abnormally small head in babies born to mothers infected during pregnancy. It also has been associated with the autoimmune disease Guillain-Barré syndrome, which can lead to temporary paralysis. In the majority of infected individuals symptoms are mild and include fever, skin rashes and flulike illness, according to the World Health Organization.
Zika virus transmission has been reported in 33 countries. Of the countries where Zika virus is circulating 12 have reported an increased incidence of Guillain-Barré syndrome, and Brazil and French Polynesia have reported an increase in microcephaly, according to WHO. In February WHO declared the Zika virus to be “a public health emergency of international concern.”
“This breakthrough illustrates not only the importance of basic research to the betterment of human health, but also its nimbleness in quickly addressing a pressing global concern,” said Purdue President Mitch Daniels. “This talented team of researchers solved a very difficult puzzle in a remarkably short period of time, and have provided those working on developing vaccines and treatments to stop this virus a map to guide their way.”
Rossmann and Kuhn collaborated with Theodore Pierson, chief of the viral pathogenesis section of the Laboratory of Viral Diseases at the National Institutes of Health National Institute of Allergy and Infectious Diseases. Additional research team members include Purdue graduate student Devika Sirohi and postdoctoral research associates Zhenguo Chen, Lei Sun and Thomas Klose.
The team’s paper marks the first published success of the new Purdue Institute for Inflammation, Immunology and Infectious Diseases in Purdue’s Discovery Park.
The university’s recently announced $250 million investment in the life sciences funded the purchase of advanced equipment that allowed the team to do in a couple of months what otherwise would have taken years, Rossmann said.
“We were able to determine through cryo-electron microscopy the virus structure at a resolution that previously would only have been possible through X-ray crystallography,” he said. “Since the 1950s X-ray crystallography has been the standard method for determining the structure of viruses, but it requires a relatively large amount of virus, which isn’t always available; it can be very difficult to do, especially for viruses like Zika that have a lipid membrane and don’t organize accurately in a crystal; and it takes a long time. Now, we can do it through electron microscopy and view the virus in a more native state. This was unthinkable only a few years ago.”
The team studied a strain of Zika virus isolated from a patient infected during the French Polynesia epidemic and determined the structure to 3.8Å. At this near-atomic resolution key features of the virus structure can be seen and groups of atoms that form specific chemical entities, such as those that represent one of 20 naturally occurring amino acids, can be recognized, Rossmann said.
The team found the structure to be very similar to that of other flaviviruses with an RNA genome surrounded by a lipid, or fatty, membrane inside an icosahedral protein shell.
The strong similarity with other flaviviruses was not surprising and is perhaps reassuring in terms of vaccine development already underway, but the subtle structural differences are possibly key, Sirohi said.
“Most viruses don’t invade the nervous system or the developing fetus due to blood-brain and placental barriers, but the association with improper brain development in fetuses suggest Zika does,” Sirohi said. “It is not clear how Zika gains access to these cells and infects them, but these areas of structural difference may be involved. These unique areas may be crucial and warrant further investigation.”
The team found that all of the known flavivirus structures differ in the amino acids that surround a glycosylation site in the virus shell. The shell is made up of 180 copies of two different proteins. These, like all proteins, are long chains of amino acids folded into particular structures to create a protein molecule, Rossmann said.
The glycosylation site where Zika virus differs from other flaviviruses protrudes from the surface of the virus. A carbohydrate molecule consisting of various sugars is attached to the viral protein surface at this site.
In many other viruses it has been shown that as the virus projects a glycosylation site outward, an attachment receptor molecule on the surface of a human cell recognizes the sugars and binds to them, Kuhn said.
The virus is like a menacing stranger luring an unsuspecting victim with the offer of sweet candy. The human cell gladly reaches out for the treat and then is caught by the virus, which, once attached, may initiate infection of that cell.
The glycosylation site and surrounding residues on Zika virus may also be involved in attachment to human cells, and the differences in the amino acids between different flaviviruses could signify differences in the kinds of molecules to which the virus can attach and the different human cells it can infect, Rossmann said.
“If this site functions as it does in dengue and is involved in attachment to human cells, it could be a good spot to target an antiviral compound,” Rossmann said. “If this is the case, perhaps an inhibitor could be designed to block this function and keep the virus from attaching to and infecting human cells.”
The team plans to pursue further testing to evaluate the different regions as targets for treatment and to develop potential therapeutic molecules, Kuhn said.
Kuhn and Rossmann have studied flaviviruses, the family of viruses to which Zika belongs, for more than 14 years. They were the first to map the structure of any flavivirus when they determined the dengue virus structure in 2002. In 2003 they were first to determine the structure of West Nile virus and now they are the first to do so with the Zika virus.
A new blood test that uses the DNA strands of dying cells to detect diabetes, cancer, traumatic brain injury, and neurodegenerative disease has been developed by researchers at Hadassah Medical Organization (HMO) and The Hebrew University.
In a study involving 320 patients, the researchers were able to infer cell death in specific tissues by looking at the unique chemical modifications (called methylation patterns) of circulating DNA that these dying cells release. Previously, it had not been possible to measure cell death in specific human tissues non-invasively.
The findings are reported in the March 14, 2016 online edition of Proceedings of National Academy of Sciences USA, in an article entitled “Identification of tissue specific cell death using methylation patterns of circulating DNA.” Prof. Benjamin Glaser, head of Endocrinology at Hadassah, and Dr. Ruth Shemer and Prof. Yuval Dor from The Hebrew University of Jerusalem led an international team in performing the groundbreaking research.
Cell death is a central feature in health and disease. It can signify the early stages of pathology (e.g. a developing tumor or the beginning of an autoimmune or neurodegenerative disease); it can illuminate whether a disease has progressed and whether a particular treatment, such as chemotherapy, is working; and it can alert physicians to unintended toxic effects of treatment or the early rejection of a transplant.
As the researchers relate: “The approach can be adapted to identify cfDNA (cell-free circulating DNA) derived from any cell type in the body, offering a minimally invasive window for diagnosing and monitoring a broad spectrum of human pathologies as well as providing a better understanding of normal tissue dynamics.”
“In the long run,” notes Prof. Glaser, “we envision a new type of blood test aimed at the sensitive detection of tissue damage, even without a-priori suspicion of disease in a specific organ. We believe that such a tool will have broad utility in diagnostic medicine and in the study of human biology.”
The research was performed by Hebrew University students Roni Lehmann-Werman, Daniel Neiman, Hai Zemmour, Joshua Moss and Judith Magenheim, aided by clinicians and scientists from Hadassah Medical Center, Sheba Medical Center, and from institutions in Germany, Sweden, the USA and Canada, who provided precious blood samples from patients.
Scientists have known for decades that dying cells release fragmented DNA into the blood; however, since the DNA sequence of all cells in the body is identical, it had not been possible to determine the tissue of origin of the circulating DNA. Knowing that the DNA of each cell type carries a unique methylation and that methylation patterns of DNA account for the identity of cells, the researchers were able to use patterns of methylated DNA sequences as biomarkers to detect the origin of the DNA and to identify a specific pathology. For example, they were able to detect evidence of pancreatic beta-cell death in the blood of patients with new-onset type 1 diabetes, oligodendrocyte cell death in patients with relapsing multiple sclerosis, brain cell death in patients after traumatic or ischemic brain damage, and exocrine pancreatic tissue cell death in patients with pancreatic cancer or pancreatitis.
Support for the research came from the Juvenile Diabetes Research Foundation, the Human Islet Research Network of the National Institutes of Health, the Sir Zalman Cowen Universities Fund, the DFG (a Trilateral German-Israel-Palestine program), and the Soyka pancreatic cancer fund.
Identification of tissue-specific cell death using methylation patterns of circulating DNA.
Minimally invasive detection of cell death could prove an invaluable resource in many physiologic and pathologic situations. Cell-free circulating DNA (cfDNA) released from dying cells is emerging as a diagnostic tool for monitoring cancer dynamics and graft failure. However, existing methods rely on differences in DNA sequences in source tissues, so that cell death cannot be identified in tissues with a normal genome. We developed a method of detecting tissue-specific cell death in humans based on tissue-specific methylation patterns in cfDNA. We interrogated tissue-specific methylome databases to identify cell type-specific DNA methylation signatures and developed a method to detect these signatures in mixed DNA samples. We isolated cfDNA from plasma or serum of donors, treated the cfDNA with bisulfite, PCR-amplified the cfDNA, and sequenced it to quantify cfDNA carrying the methylation markers of the cell type of interest. Pancreatic β-cell DNA was identified in the circulation of patients with recently diagnosed type-1 diabetes and islet-graft recipients; oligodendrocyte DNA was identified in patients with relapsing multiple sclerosis; neuronal/glial DNA was identified in patients after traumatic brain injury or cardiac arrest; and exocrine pancreas DNA was identified in patients with pancreatic cancer or pancreatitis. This proof-of-concept study demonstrates that the tissue origins of cfDNA and thus the rate of death of specific cell types can be determined in humans. The approach can be adapted to identify cfDNA derived from any cell type in the body, offering a minimally invasive window for diagnosing and monitoring a broad spectrum of human pathologies as well as providing a better understanding of normal tissue dynamics.
While impressively organ specific, they did not specifically prove that the DNA was from an actual dying cell. For example, you would need to see if Troponin levels were elevated when assuming the DNA is from injured myocardium. Also, for brain, though impractical , you’d want to see a brain biopsy or imaging for the brain related cases. The experiment of spiking with DNA was clever though. Also, what is the turnaround time for this test in practical use?
Larry HB
Very good comment. I was reluctant to put this up, but it was of interest and published in PNAS. Perhaps I can find more information. Troponin levels would be good for 48 hours, longer than CK and comparable to LD. What about Nat peptides?
Glutamine and cancer: cell biology, physiology, and clinical opportunities
Glutamine is an abundant and versatile nutrient that participates in energy formation, redox homeostasis, macromolecular synthesis, and signaling in cancer cells. These characteristics make glutamine metabolism an appealing target for new clinical strategies to detect, monitor, and treat cancer. Here we review the metabolic functions of glutamine as a super nutrient and the surprising roles of glutamine in supporting the biological hallmarks of malignancy. We also review recent efforts in imaging and therapeutics to exploit tumor cell glutamine dependence, discuss some of the challenges in this arena, and suggest a disease-focused paradigm to deploy these emerging approaches.
It has been nearly a century since the discovery that tumors display metabolic activities that distinguish them from differentiated, non-proliferating tissues and presumably contribute to their supraphysiological survival and growth (1). Interest in cancer metabolism was boosted by discoveries that oncogenes and tumor suppressors could regulate nutrient metabolism, and that mutations in some metabolic enzymes participate in the development of malignancy (2, 3). The persistent appeal of cancer metabolism as a line of investigation lies both in its ability to uncover fundamental aspects of malignancy and in the translational potential of exploiting cancer metabolism to improve the way we diagnose, monitor, and treat cancer. Furthermore, an improved understanding of how altered metabolism contributes to cancer has a high potential for synergy with translational efforts. For example, the demonstration that asparagine is a conditionally essential nutrient in rapidly growing cancer cells paved the way for L-asparaginase therapy in leukemia. Additionally, the avidity of some tumors for glucose uptake led to the development of 18fluoro-2-deoxyglucose imaging by PET; this in turn stimulated hundreds of studies on the biological underpinnings of tumor glucose metabolism.
There continue to be large gaps in understanding which metabolic pathways are altered in cancer, whether these alterations benefit the tumor in a substantive way, and how this information could be used in clinical oncology. In this Review, we consider glutamine, a highly versatile nutrient whose metabolism has implications for tumor cell biology, metabolic imaging, and perhaps novel therapeutics.
Glutamine metabolism has been reviewed extensively and is briefly outlined here (4, 5). The importance of glutamine as a nutrient in cancer derives from its abilities to donate its nitrogen and carbon into an array of growth-promoting pathways (Figure 1). At concentrations of 0.6–0.9 mmol/l, glutamine is the most abundant amino acid in plasma (6). Although most tissues can synthesize glutamine, during periods of rapid growth or other stresses, demand outpaces supply, and glutamine becomes conditionally essential (7). This requirement for glutamine is particularly true in cancer cells, many of which display oncogene-dependent addictions to glutamine in culture (8). Glutamine catabolism begins with its conversion to glutamate in reactions that either donate the amide nitrogen to biosynthetic pathways or release it as ammonia. The latter reactions are catalyzed by the glutaminases (GLSs), of which several isozymes are encoded by human genes GLS and GLS2 (9). Classical studies revealed that GLS isozymes, particularly those encoded by GLS, are expressed in experimental tumors in rats and mice, where their enzyme activity correlates with growth rate and malignancy. Silencing GLS expression or inhibiting GLS activity is sufficient to delay tumor growth in a number of models (10–13). The role of GLS2 in cancer appears to be context specific and regulated by factors that are still incompletely characterized. In some tissues, GLS2 is a p53 target gene and seems to function in tumor suppression (14). On the other hand, GLS2 expression is enhanced in some neuroblastomas, where it contributes to cell survival (15). These observations, coupled with the demonstration that c-Myc stimulates GLS expression (12, 16), position at least some of the GLS isozymes as pro-oncogenic.
Figure 1Glutamine metabolism as a target for diagnostic imaging and therapy in cancer. Glutamine is imported via SLC1A5 and other transporters, then enters a complex metabolic network by which its carbon and nitrogen are supplied to pathways that promote cell survival and growth. Enzymes discussed in the text are shown in green, and inhibitors that target various aspects of glutamine metabolism are shown in red. Green arrows denote reductive carboxylation. 18F-labeled analogs of glutamine are also under development as PET probes for localization of tumor tissue. AcCoA, acetyl-CoA; DON, 6-diazo-5-oxo-L-norleucine; GSH, glutathione; NEAA, nonessential amino acids; ME, malic enzyme; OAA, oxaloacetate; TA, transaminase; 968, compound 968; α-KG, α-ketoglutarate.
Glutamate, the product of the GLS reaction, is a precursor of glutathione, the major cellular antioxidant. It is also the source of amino groups for nonessential amino acids like alanine, aspartate, serine, and glycine, all of which are required for macromolecular synthesis. In glutamine-consuming cells, glutamate is also the major source of α-ketoglutarate, a TCA cycle intermediate and substrate for dioxygenases that modify proteins and DNA. These dioxygenases include prolyl hydroxylases, histone demethylases, and 5-methylcytosine hydroxylases. Their requirement for α-ketoglutarate, although likely accounting for only a small fraction of total α-ketoglutarate utilization, makes this metabolite an essential component of cell signaling and epigenetic networks.
Conversion of glutamate to α-ketoglutarate occurs either through oxidative deamination by glutamate dehydrogenase (GDH) in the mitochondrion or by transamination to produce nonessential amino acids in either the cytosol or the mitochondrion. During avid glucose metabolism, the transamination pathway predominates (17). When glucose is scarce, GDH becomes a major pathway to supply glutamine carbon to the TCA cycle, and is required for cell survival (17, 18). Metabolism of glutamine-derived α-ketoglutarate in the TCA cycle serves several purposes: it generates reducing equivalents for the electron transport chain (ETC) and oxidative phosphorylation, becoming a major source of energy (19); and it is an important anaplerotic nutrient, feeding net production of oxaloacetate to offset export of intermediates from the cycle to supply anabolism (20). Glutamine oxidation also supports redox homeostasis by supplying carbon to malic enzyme, some isoforms of which produce NADPH (Figure 1). In KRAS-driven pancreatic adenocarcinoma cells, a pathway involving glutamine-dependent NADPH production is essential for redox balance and growth (21). In these cells, glutamine is used to produce aspartate in the mitochondria. This aspartate is then trafficked to the cytosol, where it is deaminated to produce oxaloacetate and then malate, the substrate for malic enzyme.
Recent work has uncovered an unexpected role for glutamine in cells with reduced mitochondrial function. Despite glutamine’s conventional role as a respiratory substrate, several studies demonstrated a persistence of glutamine dependence in cells with permanent mitochondrial dysfunction from mutations in the ETC or TCA cycle, or transient impairment secondary to hypoxia (22–25). Under these conditions, glutamine-derived α-ketoglutarate is reductively carboxylated by NADPH-dependent isoforms of isocitrate dehydrogenase to produce isocitrate, citrate, and other TCA cycle intermediates (Figure 1). These conditions broaden glutamine’s utility as a carbon source because it becomes not only a major source of oxaloacetate, but also generates acetyl-CoA in what amounts to a striking rewiring of TCA cycle metabolism.
Deregulated energetics. One hallmark of cancer cells is aberrant bioenergetics (26). Glutamine’s involvement in the pathways outlined above contributes to a phenotype conducive to energy formation, survival, and growth. In addition to its role in mitochondrial metabolism, glutamine also suppresses expression of thioredoxin-interacting protein, a negative regulator of glucose uptake (27). Thus, glutamine contributes to both of the energy-forming pathways in cancer cells: oxidative phosphorylation and glycolysis. Glutamine also modulates hallmarks not traditionally thought to be metabolic, as outlined below. These interactions highlight the complex interplay between glutamine metabolism and many aspects of cell biology.
Sustaining proliferative signaling. Pathological cancer cell growth relies on maintenance of proliferative signaling pathways with increased autonomy relative to non-malignant cells. Several lines of evidence argue that glutamine reinforces activity of these pathways. In some cancer cells, excess glutamine is exported in exchange for leucine and other essential amino acids. This exchange facilitates activation of the serine/threonine kinase mTOR, a major positive regulator of cell growth (28). In addition, glutamine-derived nitrogen is a component of amino sugars, known as hexosamines, that are used to glycosylate growth factor receptors and promote their localization to the cell surface. Disruption of hexosamine synthesis reduces the ability to initiate signaling pathways downstream of growth factors (29).
Enabling replicative immortality. Some aspects of glutamine metabolism oppose senescence and promote replicative immortality in cultured cells. In IMR90 lung fibroblasts, silencing either of two NADPH-generating isoforms of malic enzyme (ME1, ME2) rapidly induced senescence, while malic enzyme overexpression suppressed senescence (30). Both malic enzyme isoforms are repressed at the transcriptional level by p53 and contribute to enhanced levels of glutamine consumption and NADPH production in p53-deficient cells. The ability of p53-replete cells to resist senescence required the expression of ME1 and ME2, and silencing either enzyme reduced the growth of TP53+/+ and, to a lesser degree, TP53–/– tumors (30). These observations position malic enzymes as potential therapeutic targets.
Resisting cell death. Although many cancer cells require glutamine for survival, cells with enhanced expression of Myc oncoproteins are particularly sensitive to glutamine deprivation (8, 12, 16). In these cells, glutamine deprivation induces depletion of TCA cycle intermediates, depression of ATP levels, delayed growth, diminished glutathione pools, and apoptosis. Myc drives glutamine uptake and catabolism by activating the expression of genes involved in glutamine metabolism, including GLSand SLC1A5, which encodes the Na+-dependent amino acid transporter ASCT2 (12, 16). SilencingGLS mimicked some of the effects of glutamine deprivation, including growth suppression in Myc-expressing cells and tumors (10, 12). MYCN amplification occurs in 20%–25% of neuroblastomas and is correlated with poor outcome (31). In cells with high N-Myc levels, glutamine deprivation triggered an ATF4-dependent induction of apoptosis that could be prevented by restoring downstream metabolites oxaloacetate and α-ketoglutarate (15). In this model, pharmacological activation of ATF4, inhibition of glutamine metabolic enzymes, or combinations of these treatments mimicked the effects of glutamine deprivation in cells and suppressed growth of MYCN-amplified subcutaneous and transgenic tumors in mice.
The PKC isoform PKC-ζ also regulates glutamine metabolism. Loss of PKC-ζ enhances glutamine utilization and enables cells to survive glucose deprivation (32). This effect requires flux of carbon and nitrogen from glutamine into serine. PKC-ζ reduces the expression of phosphoglycerate dehydrogenase, an enzyme required for glutamine-dependent serine biosynthesis, and also phosphorylates and inactivates this enzyme. Thus, PKC-ζ loss, which promotes intestinal tumorigenesis in mice, enables cells to alter glutamine metabolism in response to nutrient stress.
Invasion and metastasis. Loss of the epithelial cell-cell adhesion molecule E-cadherin is a component of the epithelial-mesenchymal transition, and is sufficient to induce migration, invasion, and tumor progression (33, 34). Addiction to glutamine may oppose this process because glutamine favors stabilization of tight junctions in some cells (35). Furthermore, the selection of breast cancer cells with the ability to grow without glutamine yielded highly adaptable subpopulations with enhanced mesenchymal marker expression and improved capacity for anchorage-independent growth, therapeutic resistance, and metastasis in vivo (36). It is unknown whether this result reflects a primary role for glutamine in suppressing these markers of aggressiveness in breast cancer, or whether prolonged glutamine deprivation selects for cells with enhanced fitness across a number of phenotypes.
As a major player in carbon and nitrogen transport, glutamine metabolism displays complex inter-organ dynamics, with some organs functioning as net producers and others as consumers (Figure 2). Organ-specific glutamine metabolism has frequently been studied in humans and animal models by measuring the arteriovenous difference in plasma glutamine abundance. In healthy subjects, the plasma glutamine pool is largely the result of release from skeletal muscle (37–39). In rats, the lungs are comparable to muscle in terms of glutamine production (40, 41), and human lungs also have the capacity for marked glutamine release, although such release is most prominent in times of stress (42, 43). Stress-induced release from the lung is regulated by an induction of glutamine synthase expression as a consequence of glucocorticoid signaling and other mechanisms (44, 45). Although this results in a small arteriovenous difference, the overall release of glutamine is significant because of the large pulmonary perfusion. In rats and humans, adipose tissue is a minor but potentially important source of glutamine (46, 47). The liver has the capacity to synthesize or catabolize glutamine, with these activities subject both to regional heterogeneity among hepatocytes and regulatory effects of systemic acidosis and hyperammonemia. However, the liver does not appear to be a major contributor to the plasma glutamine pool in healthy rats and humans (39, 48, 49).
Figure 2Model for inter-organ glutamine metabolism in health and cancer. Organs that release glutamine into the bloodstream are shown in green, and those that consume glutamine are in red; the shade denotes magnitude of consumption/release. For some organs (liver, kidneys), evidence from model systems and/or human studies suggests that there is a change in net glutamine flux during tumorigenesis.
Glutamine consumption occurs largely in the gut and kidney. The organs of the gastrointestinal tract drained by the portal vein, particularly the small intestine, are major consumers of plasma glutamine in both rats and humans (37, 38, 49, 50). Enterocytes oxidize more than half of glutamine carbon to CO2, accounting for a third of the respiration of these cells in fasting animals (51). The kidney consumes net quantities of glutamine to maintain acid-base balance (37, 38, 52, 53). During acidosis, the kidneys substantially increase their uptake of glutamine, cleaving it by GLS to produce ammonia, which is excreted along with organic acids to maintain physiologic pH (52, 54). Glutamine is also a major metabolic substrate in lymphocytes and macrophages, at least during mitogenic stimulation of primary cells in culture (55–57).
Importantly, cancer seems to cause major changes in inter-organ glutamine trafficking (Figure 2). Currently, much work in this area is derived from studies in methylcholanthrene-induced fibrosarcoma in the rat, a model of an aggressively growing, glutamine-consuming tumor. In this model, fibrosarcoma induces skeletal muscle expression of glutamine synthetase and greatly increases the release of glutamine into the circulation. As the tumor increases in size, intramuscular glutamine pools are depleted in association with loss of lean muscle mass, mimicking the cachectic phenotype of humans in advanced stages of cancer (52). Simultaneously, both the liver and the kidneys become net glutamine exporters, although the hepatic effect may be diminished as the tumor size becomes very large (48, 49, 52). Glutamine utilization by organs supplied by the portal vein is diminished in cancer (48). In addition to its function as a nutrient for the tumor itself, and possibly for cancer-associated immune cells, glutamine provides additional, indirect metabolic benefits to both the tumor and the host. For example, glutamine was used as a gluconeogenic substrate in cachectic mice with large orthotopic gliomas, providing a significant source of carbon in the plasma glucose pool (58). This glucose was taken up and metabolized by the tumor to produce lactate and to supply the TCA cycle.
It will be valuable to extend work in human inter-organ glutamine trafficking, both in healthy subjects and in cancer patients. Such studies will likely produce a better understanding of the pathophysiology of cancer cachexia, a major source of morbidity and mortality. Research in this area should also aid in the anticipation of organ-specific toxicities of drugs designed to interfere with glutamine metabolism. Alterations of glutamine handling in cancer may induce a different spectrum of toxicities compared with healthy subjects.
One important consideration is that not all cancer cells need an exogenous supply of glutamine. A panel of lung cancer cell lines displayed significant variability in their response to glutamine deprivation, with some cells possessing almost complete independence (59). Breast cancer cells also demonstrate systematic differences in glutamine dependence, with basal-type cells tending to be glutamine dependent and luminal-type cells tending to be glutamine independent (60). Resistance to glutamine deprivation is associated with the ability to synthesize glutamine de novo and/or to engage alternative pathways of anaplerosis (10, 60).
Tumors also display variable levels of glutamine metabolism in vivo. A study of orthotopic gliomas revealed that genetically diverse, human-derived tumors took up glutamine in the mouse brain but did not catabolize it (58). Rather, the tumors synthesized glutamine de novo and used pyruvate carboxylation for anaplerosis. Cells derived from these tumors did not require glutamine to survive or proliferate when cultured ex vivo. Glutamine synthesis from glucose was also a prominent feature of primary gliomas in human subjects infused with 13C-glucose at the time of surgical resection (61). Furthermore, an analysis of glutamine metabolism in lung and liver tumors revealed that both the tissue of origin and the oncogene influence whether the tumor produces or consumes glutamine (62). MET-induced hepatic tumors produced glutamine, whereas Myc-induced liver tumors catabolized it. In the lung, however, Myc expression was associated with glutamine accumulation.
This variability makes it imperative to develop ways to predict which tumors have the highest likelihood of responding to inhibitors of glutamine metabolism. Methods to image or otherwise quantify glutamine metabolism in vivo would be useful in this regard (63). Infusions of pre-surgical subjects with isotopically labeled glutamine, followed by extraction of metabolites from the tumor and analysis of 13C enrichment, can be used to detect both glutamine uptake and catabolism (58, 62). However, this approach requires a specimen of the tumor to be obtained. Approaches for glutamine-based imaging, which avoid this problem, include a number of glutamine analogs compatible with PET. Although glutamine could in principle be imaged using the radioisotopes 11C, 13N, or 18F, the relatively long half-life of the latter increases its appeal. In mice, 18F-(2S, 4R)4-fluoroglutamine is avidly taken up by tumors derived from highly glutaminolytic cells, and by glutamine-consuming organs including the intestine, kidney, liver, and pancreas (64). Labeled analogs of glutamate are also taken up by some tumors (65, 66). One of these, (4S)-4-(3-[18F] fluoropropyl)-L-glutamate (18F-FSPG, also called BAY 94-9392), was evaluated in small clinical trials involving patients with several types of cancer (65, 67). This analog enters the cell through the cystine/glutamate exchange transporter (xC–transport system), which is linked to glutathione biosynthesis (68). The analog was well tolerated, with high tumor detection rates and good tumor-to-background ratios in hepatocellular carcinoma and lung cancer.
PET approaches detect analog uptake and retention but cannot provide information about downstream metabolism. Analysis of hyperpolarized nuclei can provide a real-time view of enzyme-catalyzed reactions. This technique involves redistribution of the populations of energy levels of a nucleus (e.g., 13C, 15N), resulting in a gain in magnetic resonance signal that can temporarily exceed 10,000-fold (69). This gain in signal enables rapid detection of both the labeled molecule and its downstream metabolites. Glutamine has been hyperpolarized on 15N and 13C (70, 71). In the latter case, the conversion of hyperpolarized glutamine to glutamate could be detected in intact hepatoma cells (70). If these analogs are translated to clinical studies, they might provide a dynamic view of the proximal reactions of glutaminolysis in vivo.
Efforts to inhibit glutamine metabolism using amino acid analogs have an extensive history, including evaluation in clinical trials. Acivicin, 6-diazo-5-oxo-L-norleucine, and azaserine, three of the most widely studied analogs (Figure 1), all demonstrated variable degrees of gastrointestinal toxicity, myelosuppression, and neurotoxicity (72). Because these agents non-selectively target glutamine-consuming processes, recent interest has focused on developing methods directed at specific nodes of glutamine metabolism. First, ASCT2, the Na+-dependent neutral amino acid transporter encoded by SLC1A5, is broadly expressed in lung cancer cell lines and accounts for a majority of glutamine transport in those cells (Figure 1). It has been shown that γ-L-glutamyl-p-nitroanilide (GPNA) inhibits this transporter and limits lung cancer cell growth (73). Additional interest in GPNA lies in its ability to enhance the uptake of drugs imported via the monocarboxylate transporter MCT1. Suppressing glutamine uptake with GPNA enhances MCT1 stability and stimulates uptake of the glycolytic inhibitor 3-bromopyruvate (3-BrPyr) (74, 75). Because enforced MCT1 overexpression is sufficient to sensitize tumor xenografts to 3-BrPyr (76), GPNA may have a place in 3-BrPyr–based therapeutic regimens.
Two inhibitors of GLS isoforms have been characterized in recent years (Figure 1). Compound 968, an inhibitor of the GLS-encoded splice isoform GAC, inhibits the transformation of fibroblasts by oncogenic RhoGTPases and delays the growth of GLS-expressing lymphoma xenografts (13). Bis-2-(5-phenylacetamido-1,2,4-thiadiazol-2-yl)ethyl sulfide (BPTES) also potently inhibits GLS isoforms encoded by GLS (77). BPTES impairs ATP levels and growth rates of P493 lymphoma cells under both normoxic and hypoxic conditions and suppresses the growth of P493-derived xenografts (78).
Evidence also supports a role for targeting the flux from glutamate to α-ketoglutarate, although no potent, specific inhibitors yet exist to inhibit these enzymes in intact cells. Aminooxyacetate (AOA) inhibits aminotransferases non-specifically, but milliomolar doses are typically used to achieve this effect in cultured cells (Figure 1). Nevertheless, AOA has demonstrated efficacy in both breast adenocarcinoma xenografts and autochthonous neuroblastomas in mice (15, 79). Epigallocatechin gallate (EGCG), a green tea polyphenol, has numerous pharmacological effects, one of which is to inhibit GDH (80). The effects of EGCG on GDH have been used to kill glutamine-addicted cancer cells during glucose deprivation or glycolytic inhibition (17, 18) and to suppress growth of neuroblastoma xenografts (15).
Recent advances in glutamine-based imaging, coupled with the successful application of glutamine metabolic inhibitors in mouse models of cancer, make it possible to conceive of treatment plans that feature consideration of tumor glutamine utilization. A key challenge will be predicting which tumors are most likely to respond to inhibitors of glutamine metabolism. Neuroblastoma is used here as an example of a tumor in which evidence supports the utility of strategies that would involve both glutamine-based imaging and therapy (Figure 3). Neuroblastoma is the second most common extracranial solid malignancy of childhood. High-risk neuroblastoma is defined by age, stage, and biological features of the tumor, including MYCN amplification, which occurs in some 20%–25% of cases (31). Because MYCN-amplified tumor cells require glutamine catabolism for survival and growth (15), glutamine-based PET at the time of standard diagnostic imaging could help predict which tumors would be likely to respond to inhibitors of glutamine metabolism. Infusion of 13C-glutamine coordinated with the diagnostic biopsy could then enable inspection of 13C enrichment in glutamine-derived metabolites from the tumor, confirming the activity of glutamine catabolic pathways. Following on evidence from mouse models of neuroblastoma, treatment could then include agents directed against glutamine catabolism (15). Of note, some tumors were sensitive to the ATF4 agonist fenretinide (FRT), alone or in combination with EGCG. Importantly, FRT has already been the focus of a Phase I clinical trial in children with solid tumors, including neuroblastoma, and was fairly well tolerated (81).
Figure 3A strategy to integrate glutamine metabolism into the diagnosis, classification, treatment, and monitoring of neuroblastoma. Neuroblastoma commonly presents in children as an abdominal mass. A standard evaluation of a child with suspected neuroblastoma includes measurement of urine catecholamines, a bone scan, and full-body imaging with meta-iodobenzylguanidine (MIBG), all of which contribute to diagnosis and disease staging. In animal models, a subset of these tumors requires glutamine metabolism. This finding implies that approaches to image, quantify, or block glutamine metabolism (highlighted in red) in human neuroblastoma could be incorporated into the diagnosis and management of this disease. In particular, glutamine metabolic studies may help predict which tumors would respond to therapies targeting glutamine metabolism. HVA, homovanillic acid; VMA, vanillylmandelic acid.
Glutamine is a versatile nutrient required for the survival and growth of a potentially large subset of tumors. Work over the next several years should produce a more accurate picture of the molecular determinants of glutamine addiction and the identification of death pathways that execute cells when glutamine catabolism is impaired. Advancement of glutamine-based imaging into clinical practice should soon make it possible to differentiate tumors that take up glutamine from those that do not. Finally, the development of safe, high-potency inhibitors of key metabolic nodes should facilitate therapeutic regimens featuring inhibition of glutamine metabolism.
Therapeutic strategies impacting cancer cell glutamine metabolism
The metabolic adaptations that support oncogenic growth can also render cancer cells dependent on certain nutrients. Along with the Warburg effect, increased utilization of glutamine is one of the metabolic hallmarks of the transformed state. Glutamine catabolism is positively regulated by multiple oncogenic signals, including those transmitted by the Rho family of GTPases and by c-Myc. The recent identification of mechanistically distinct inhibitors of glutaminase, which can selectively block cellular transformation, has revived interest in the possibility of targeting glutamine metabolism in cancer therapy. Here, we outline the regulation and roles of glutamine metabolism within cancer cells and discuss possible strategies for, and the consequences of, impacting these processes therapeutically.
Interest in the metabolic changes characteristic of malignant transformation has undergone a renaissance of sorts in the cancer biology and pharmaceutical communities. However, the recognition that an important connection exists between cellular metabolism and cancer began nearly a century ago with the work of Otto Warburg [1–3]. Warburg found that rapidly proliferating tumor cells exhibit elevated glucose uptake and glycolytic flux, and furthermore that much of the pyruvate generated by glycolysis is reduced to lactate rather than undergoing mitochondrial oxidation via the tricarboxylic acid (TCA) cycle (Figure 1). This phenomenon persists even under aerobic conditions (‘aerobic glycolysis’), and is known as the Warburg effect [4]. Warburg proposed that aerobic glycolysis was caused by defective mitochondria in cancer cells, but it is now known that mitochondrial dysfunction is relatively rare and that most tumors have an unimpaired capacity for oxidative phosphorylation [5]. In fact, the most important selective advantages provided by the Warburg effect are still debated. Although aerobic glycolysis is an inefficient way to produce ATP (2 ATP/glucose vs ~36 ATP/glucose by complete oxidation), a high glycolytic flux can generate ATP rapidly and furthermore can provide a biosynthetic advantage by supplying precursors and reducing equivalents for the synthesis of macromolecules [4]. The mechanisms underlying the Warburg effect are also not yet fully resolved, although it is increasingly clear that a number of oncogenes and tumor suppressors contribute to the phenomenon. The PI3K/Akt/mTORC1 signaling axis, for example, is a key regulator of aerobic glycolysis and biosynthesis, driving the surface expression of nutrient transporters and the upregulation of glycolytic enzymes [6]. The HIF transcription factor also upregulates expression of glucose transporters and glycolytic enzymes in response to hypoxia and growth factors (or loss of the von Hippel–Landau [VHL] tumor suppressor), and the oncogenic transcription factor c-Myc similarly induces expression of proteins important for glycolysis [6].
A second major change in the metabolic program of many cancer cells, and the primary focus of this review, is the alteration of glutamine metabolism. Glutamine is the major carrier of nitrogen between organs, and the most abundant amino acid in plasma [7]. It is also a key nutrient for numerous intracellular processes including oxidative metabolism and ATP generation, biosynthesis of proteins, lipids and nucleic acids, and also redox homeostasis and the regulation of signal transduction pathways [8–10]. Although most mammalian cells are capable of synthesizing glutamine, the demand for this amino acid can become so great during rapid proliferation that an additional extracellular supply is required; hence glutamine is considered conditionally essential [11]. Indeed, many cancer cells are ‘glutamine addicted’, and cannot survive in the absence of an exogenous glutamine supply [12,13].
An important step in the elevation of glutamine catabolism is the activation of the mitochondrial enzyme glutaminase, which catalyzes the hydrolysis of glutamine to generate glutamate and ammonium. The subsequent deamination of glutamate releases a second ammonium to yield the TCA cycle intermediate α-ketoglutarate (α-KG), a reaction catalyzed by glutamate dehydrogenase (GLUD1). This series of reactions is particularly important in rapidly proliferating cells, in which a considerable proportion of the TCA cycle metabolite citrate is exported from mitochondria in order to generate cytosolic acetyl-CoA for lipid biosynthesis [14]. Replenishment of TCA cycle intermediates (anaplerosis) is therefore required, and glutamine often serves as the key anaplerotic substrate through its conversion via glutamate to α-KG (Figure 1).
Mammals express two genes for glutaminase enzymes [15–17]. The GLS gene encodes a protein initially characterized in kidney and thus called kidney-type glutaminase (KGA), although this enzyme and its shorter splice variant glutaminase C (GAC), collectively referred to as GLS, are now known to be widely distributed [18–20]. The KGA and GAC isoforms share identical N-terminal and catalytic domains, encoded by exons 1–14 of the GLS gene, but have distinct C-termini derived from exon 15 in the case of GAC and exons 16–19 in the case of KGA [21]. Upregulation of GLS, in particular the GAC iso-form, is common in cancer cells and the degree of GLS overexpression correlates with both the degree of malignancy and the tumor grade in human breast cancer samples [22,23]. The GLS2 gene encodes a protein originally discovered and characterized in liver, which has thus been referred to as liver-type glutaminase and, more recently, as glutaminase 2 (GLS2) [15].
Both KGA and GAC can be activated by inorganic phosphate (Pi), and this activation correlates closely with a dimer-to-tetramer transition for each enzyme [7, 22]. As the concentration of Pi is raised the apparent catalytic constant, kcatapp, increases and simultaneously the apparent Michaelis constant, Kmapp, decreases; consequently the catalytic efficiency rises dramatically, especially in the case of GAC [22]. x-ray crystal structures of GAC and KGA in different states indicate that the positioning of a key loop within each monomer (Glu312 to Pro329), located between the active site and the dimer–dimer interface, is critical for mediating tetramerization-induced activation [22,24]. Given the ability of Pi to promote tetramerization and activation of GAC and KGA, it has been proposed that the elevated mitochondrial Pi levels found under hypoxic conditions, which are commonly encountered in the tumor microenvironment, could be one trigger for GLS activation [22].
At least two classes of cellular signals regulate glutamine metabolism, influencing both the expression level and the enzymatic activity of GLS. The transcription factor c-Myc can suppress the expression of microRNAs miR-23a and miR-23b and, in doing so, upregulates GLS (specifically GAC) expression [13,25]. Independent of changes in GAC expression, oncogenic diffuse B-cell lymphoma protein (Dbl), a GEF for Rho GTPases and oncogenic variants of downstream Rho GTPases are able to signal to activate GAC in a manner that is dependent on NF-κB [23]. Mitochondria isolated from Dbl- or Rho GTPase-transformed NIH-3T3 fibroblasts demonstrate significantly higher basal glutaminase activity than mitochondria isolated from non-transformed cells [23]. Furthermore, the enzymatic activity of GAC immunoprecipitated from Dbl-transformed cells is elevated relative to GAC from non-transformed cells, indicating the presence of activating post-translational modification(s) [23]. Indeed, when GAC isolated from Dbl-transformed cells is treated with alkaline phosphatase, basal enzymatic activity is dramatically reduced [23]. Collectively, these findings point to phosphorylation events underlying the activation of GAC in transformed cells. Similarly, phosphorylation-dependent regulation of KGA activity downstream of the Raf-Mek-Erk signaling axis occurs in response to EGF stimulation [24].
It is becoming clear that, in addition to c-Myc and Dbl, many other oncogenic signals and environmental conditions can impact cellular glutamine metabolism. Loss of the retinoblastoma tumor suppressor, for example, leads to a marked increase in glutamine uptake and catabolism, and renders mouse embryonic fibroblasts dependent on exogenous glutamine [26]. Cells transformed by KRAS also illustrate increased expression of genes associated with glutamine metabolism and a corresponding increased utilization of glutamine for anabolic synthesis [27]. In fact, KRAS signaling appears to induce glutamine dependence, since the deleterious effects of glutamine withdrawal in KRAS-driven cells can be rescued by expression of a dominant-negative GEF for Ras [28]. Downstream of Ras, the Raf-MEK-ERK signaling pathway has been implicated in the upregulation of glutamine uptake and metabolism [24,29]. A recent study using human pancreatic ductal adenocarcinoma cells identified a novel KRAS-regulated metabolic pathway, through which glutamine supports cell growth [30]. Proliferation of KRAS-mutant pancreatic ductal adenocarcinoma cells depends on GLS-catalyzed production of glutamate, but not on downstream deamination of glutamate to α-KG; instead, transaminase-mediated glutamate metabolism is essential for growth. Glutamine-derived aspartate is subsequently transported into the cytoplasm where it is converted by aspartate transaminase into oxaloacetate, which can be used to generate malate and pyruvate. The series of reactions maintains NADPH levels and thus the cellular redox state [30].
Other recent studies have revealed that another pathway for glutamine metabolism can be essential under hypoxic conditions, and also in cancer cells with mitochondrial defects or loss of the VHL tumor suppressor [31–35]. In these situations, glutamine-derived α-KG undergoes reductive carboxylation by IDH1 or IDH2 to generate citrate, which can be exported from mitochondria to support lipogenesis (Figure 1). Activation of HIF is both necessary and sufficient for driving the reductive carboxylation phenotype in renal cell carcinoma, and suppression of HIF activity can induce a switch from glutamine-mediated lipogenesis back to glucose-mediated lipogenesis [32,35]. Furthermore, loss of VHL and consequent downstream activation of HIF renders renal cell carcinoma cells sensitive to inhibitors of GLS [35]. Evidently, the metabolic routes through which glutamine supports cancer cell proliferation vary with genetic background and with microenvironmental conditions. Nevertheless, it is increasingly clear that diverse oncogenic signals promote glutamine utilization and furthermore that hypoxia, a common condition within poorly vascularized tumors, increases glutamine dependence.
…….
Consistent with the critical role of TCA cycle anaplerosis in cancer cell proliferation, a range of glutamine-dependent cancer cell lines are sensitive to silencing or inhibition of GLS [23,93]. Although loss of GLS suppresses proliferation, in some cases the induction of a compensatory anaplerotic mechanism mediated by pyruvate carboxylase (PC) allows the use of glucose- rather than glutamine-derived carbon for anaplerosis [93]. Low glutamine conditions render glioblastoma cells completely dependent on PC for proliferation; reciprocally, glucose deprivation causes them to become dependent on GLUD1, presumably as a mediator of glutamine-dependent anaplerosis [94]. These studies provide insight into the possibility of inhibiting glutamine-dependent TCA cycle anaplerosis (e.g., with 968 or BPTES) and indicate that high expression of PC could represent a means of resistance to GLS inhibitors.
In c-Myc-induced human Burkitt lymphoma P493 cells, entry of glucose-derived carbon into the TCA cycle is attenuated under hypoxia, whereas glutamine oxidation via the TCA cycle persists [95]. Upon complete withdrawal of glucose, the TCA cycle continues to function and is driven by glutamine. The proportions of viable and proliferating cell populations are almost identical in glucose-replete and -deplete conditions so long as glutamine is present. Inhibition of GLS by BPTES causes a decrease in ATP and glutathione levels, with a simultaneous increase in reactive oxygen species production. Strikingly, whereas BPTES treatment under aerobic conditions suppresses proliferation, under hypoxic conditions it results in cell death, an effect ascribed to glutamine’s critical roles in alleviating oxidative stress in addition to supporting bioenergetics.
In addition to deamidation, glutamine-derived carbon can also reach the TCA cycle through transamination [96], and recent studies indicate that inhibition of this process could be a promising strategy for cancer treatment [30,97,98]. The transaminase inhibitor amino-oxyacetate selectively suppresses proliferation of the aggressive breast cancer cell line MDA-MB-231 relative to normal human mammary epithelial cells, and similar effects were observed with siRNA knockdown of aspartate transaminase [97]. Treatment with amino-oxyacetate killed glutamine-dependent glioblastoma cells, in a manner that could be rescued by α-KG and was dependent on c-Myc expression [13]. Transaminase inhibitors have also been found to suppress both anchorage-dependent and anchorage-independent growth of lung carcinoma cells [98].
Reductive carboxylation
The central metabolic precursor for fatty acid biosynthesis is acetyl-CoA, which can be generated from pyruvate in the mitochondria by pyruvate dehydrogenase. Since acetyl-CoA cannot cross the inner mitochondrial membrane, it is exported to the cytosol via the citrate shuttle following its condensation with oxaloacetate in the TCA cycle (Figure 3). In the cytosol, citrate is converted back to acetyl-CoA and oxaloacetate in a reaction catalyzed by ATP citrate lyase. In addition to its synthesis from glycolytic pyruvate, citrate can also be generated by reductive carboxylation of α-KG [99]. Across a range of cancer cell lines, 10–25% of lipogenic acetyl-CoA is generated from glutamine via this reductive pathway; indeed, reductive metabolism is the primary route for incorporation of glutamine, glutamate and α-KG carbon into lipids [32]. Some of the reductive carboxylation of α-KG is catalyzed by cytosolic IDH1, as well as by mitochondrial IDH2 and/or IDH3.
In A549 lung carcinoma cells, glutamine dependence and reductive carboxylation flux increases under hypoxic conditions [32,34], such that glutamine-derived α-KG accounts for approximately 80% of the carbon used for de novo lipogenesis. Similarly, in melanoma cells, the major source of carbon for acetyl-CoA, citrate and fatty acids switches from glucose under normoxia to glutamine (via reductive carboxylation) under hypoxia [31]. The hypoxic switch to reductive glutamine metabolism is dependent on HIF, and constitutive activation of HIF is sufficient to induce the preferential reductive metabolism of α-KG even under normoxic conditions [32]. Tumor cells with mitochondrial defects, such as electron-transport chain mutations/inhibition, also use glutamine-dependent reductive carboxylation as the major pathway for citrate generation, and loss of electron-transport chain activity is sufficient to induce a switch from glucose to glutamine as the primary source of lipogenic carbon [33].
Together these studies indicate that mitochondrial defects/inhibition, and/or hypoxia, might sensitize cancer cells to inhibition of GLS. The fact that P493 cells are more sensitive to BPTES under hypoxic conditions could in part be explained by an increased reliance on glutamine-dependent reductive carboxylation for lipogenesis [95]. Intriguingly, cancer cells harboring neoenzymatic mutations in IDH1, which results in production of the oncometabolite 2-hydroxyglutarate, are also sensitized to GLS inhibition [100]. 2-hydroxyglutarate is generated primarily from glutamine-derived α-KG [100,101], and therefore tumors expressing mutant IDH might be especially susceptible to alterations in α-KG levels.
……
As with all therapies, the potential side effects of strategies impacting glutamine metabolism must be seriously considered. The widespread use of l-asparaginase to lower plasma asparagine and glutamine concentrations in ALL patients demonstrates the potential for glutamine metabolism to be safely targeted, and also sheds light on potential toxicological consequences. For example, glutamine is known to be essential for the proliferation of lymphocytes, macrophages and neutrophils, and immunosuppression is a known side effect of l-asparaginase treatment, requiring close monitoring [11,105]. Evidence from early trials using glutamine-mimetic anti-metabolites, such as l-DON, indicates that these unselective molecules can cause excessive gastrointestinal toxicity and neurotoxicity. Within the brain, GLS converts glutamine into the neurotransmitter glutamate in neurons; astrocytes then take up synaptically released glutamate and convert it back to glutamine, which is subsequently transported back to neurons [106,107].
……
It has become clear during the past decade that altered metabolism plays a critical, in some cases even causal, role in the development and maintenance of cancers. It is now accepted that virtually all oncogenes and tumor suppressors impact metabolic pathways [5]. Furthermore, mutations in certain metabolic enzymes (e.g., isocitrate dehydrogenase, succinate dehydrogenase and fumarate hydratase) are associated with both familial and sporadic human cancers [113]. With this realization has come a renewed interest in the possibility of selectively targeting the metabolism of cancer cells as a therapeutic strategy. The use of l-asparaginase to treat ALL by depleting plasma asparagine and glutamine levels and the promising outcome of the first use of dichloroacetate (which acts, at least in part, through its inhibition of the metabolic enzyme pyruvate dehydrogenase kinase) in glioblastoma patients [114,115], support the notion that cancer metabolism can be safely and effectively targeted in the clinic. The metabolic adaptations of cancer cells must balance the requirements for modestly increased ATP synthesis, dramatically upregulated macromolecular biosynthesis and maintenance of redox balance. By serving as a carbon source for energy generation, a carbon and nitrogen source for biosynthesis and a precursor of the cellular antioxidant glutathione, glutamine is able to contribute to each of these requirements.
The countless combinations of genetic alterations that are found in human neo-plasias mean that there is not a single rigid metabolic program that is characteristic of all transformed cells. This perhaps explains why some current anti-metabolite chemotherapies (e.g., those targeting nucleotide synthesis) are effective only for certain malignancies. A deeper understanding of the metabolic alterations within specific genetic contexts will allow for better-targeted therapeutic interventions. Furthermore, it seems highly likely that combination therapies based on drug synergisms will be especially important for exploiting therapeutic windows within which cancer cells, but not normal cells, are impacted [37]. Glucose and glutamine metabolic pathways, for example, might be able to compensate for one another under some circumstances. When glucose metabolism is impaired in glioblastoma cells, glutamine catabolism becomes essential for survival [94]; reciprocally, suppression of GLS expression causes cells to become fully dependent on glucose-driven TCA cycle anaplerosis via PC [93]. The implication is that PC inhibition could synergize with GLS inhibition.
A topic warranting further investigation is the role that GLS2 plays in cellular metabolism. GLS, in particular the GAC isoform, is upregulated downstream of oncogenes and downregulated by tumor suppressors, and is essential for growth of many cancer cells. In contrast, GLS2 is activated by the ‘universal’ tumor suppressor p53, and furthermore is significantly downregulated in liver tumors and can block transformed characteristics of some cancer cells when overexpressed [116–118]. Emphasizing the importance of genetic context, it was recently reported that GLS2 is significantly upregulated in neuroblastomas overexpressing N-Myc [119]. There are various possible explanations for the apparently different roles of two enzymes that catalyze the same reaction. Because the regulation of GLS and GLS2 is distinct, they will be called up under different conditions. The two enzymes have different kinetic characteristics, and therefore might influence energy metabolism and antioxidant defense in different manners [20]. There is also evidence that GLS2 may act, directly or indirectly, as a transcription factor [118]. Finally, it is possible that the different interactions of GLS and GLS2 with other proteins are responsible for their apparently different roles.
Mitochondria as biosynthetic factories for cancer proliferation
Unchecked growth and proliferation is a hallmark of cancer, and numerous oncogenic mutations reprogram cellular metabolism to fuel these processes. As a central metabolic organelle, mitochondria execute critical biochemical functions for the synthesis of fundamental cellular components, including fatty acids, amino acids, and nucleotides. Despite the extensive interest in the glycolytic phenotype of many cancer cells, tumors contain fully functional mitochondria that support proliferation and survival. Furthermore, tumor cells commonly increase flux through one or more mitochondrial pathways, and pharmacological inhibition of mitochondrial metabolism is emerging as a potential therapeutic strategy in some cancers. Here, we review the biosynthetic roles of mitochondrial metabolism in tumors and highlight specific cancers where these processes are activated.
………………
Recent characterizations of metabolic enzymes as tumor suppressors and oncogene-driven metabolic reprogramming have reinvigorated interest in cancer metabolism. Although therapies targeting metabolic processes have long been a staple in cancer treatment (e.g. inhibition of folate metabolism via methotrexate), the focused therapeutic potential surrounding these findings have generated a renewed appreciation for Otto Warburg’s work almost a century ago. Warburg observed that tumor cells ferment much of the glucose taken up during growth to lactate, thus using glycolysis as a major means of adenosine triphosphate (ATP) regeneration [1]. However, the observation of decreased respiration in cancer cells and idea that “the respiration of all cancer cells is damaged” belies the critical role of mitochondria in biosynthesis and cell survival [1]. On the contrary, functional mitochondria are present in all proliferative cells within our body (including all tumors), as they are responsible for converting the diverse nutrients available to cells into the fundamental building blocks required for cell growth. These organelles execute numerous functions in cancer cells to promote tumor growth and survival in response to stress. Here, we outline the critical biosynthetic functions served by mitochondria within tumors (Figure 1). Although many of these functions are similarly important in normal, proliferating cells, we have attempted to highlight potential points where mitochondrial metabolism may be therapeutically targeted to slow cancer growth. This review is organized by specific metabolic pathways or processes (i.e., glucose metabolism and lipogenesis, amino acid metabolism, and nucleotide biosynthesis). Tumors or cancer cell types where enzymes in each pathway have been specifically observed to by dysregulated are described within the text and summarized in Table 1.
Figure 1
Biosynthetic nodes within mitochondria. Metabolic pathways within mitochondria that contribute to biosynthesis in cancer and other proliferating cells. TCA metabolism and FOCM enable cells to convert carbohydrates and amino acids to lipids, non-essential amino acids, nucleotides (including purines used for cofactor synthesis), glutathione, heme, and other cellular components. Critical biosynthetic routes are indicated by yellow arrows. Enzymatic reactions that are dependent on redox-sensitive cofactors are depicted in red. https://static-content.springer.com/image/art%3A10.1186%2Fs40170-015-0128-2/MediaObjects/40170_2015_128_Fig1_HTML.gif
Table 1
Overview of mitochondrial biosynthetic enzymes important in cancer
TCA cycle, anaplerosis, and AcCoA metabolism
Cancers in which three or more mitochondrial enzymes have been studied and found to be differentially regulated (or mutated, as indicated) in cancers vs. control groups are included. Dysregulation of each enzyme was demonstrated in clinical tumors samples, animal models, or cell lines at the levels of genes, mRNA, protein, metabolites, and/or flux.
Figure 2
Coordination of carbon and nitrogen metabolism across amino acids. Glutamate and aKG are key substrates in numerous transamination reactions and can also serve as precursors for glutamine, proline, and the TCA cycle. Mitochondrial enzymes catalyzing these reactions are highlighted in blue, and TCA cycle intermediates are highlighted in orange (pyruvate enters the TCA cycle as acetyl-CoA or oxaloacetate). https://static-content.springer.com/image/art%3A10.1186%2Fs40170-015-0128-2/MediaObjects/40170_2015_128_Fig2_HTML.gif
Mitochondria operate as both engine and factory in eukaryotes, coordinating cellular energy production and the availability of fundamental building blocks that are required for cell proliferation. Cancer cells must therefore balance their relative bioenergetic and biosynthetic needs to grow, proliferate, and survive within the physical constraints of energy and mass conservation. In contrast to quiescent cells, which predominantly use oxidative mitochondrial metabolism to produce ATP and uptake glucose at much lower rates than proliferating cells, tumor cells exhibit increased glycolytic rates to provide an elevated flux of substrate for biosynthetic pathways, including those executed within mitochondria. Given these higher rates of nutrient utilization, metabolic flux through mitochondrial pathways and the associated ROS production can often be higher in cancer cells. Not surprisingly, activation of cellular antioxidant response pathways is commonly observed in cancer or subpopulations of cells within tumors [46,78]. Cellular compartmentalization affords a degree of protection from such damaging side products of metabolism, and methods which are able to deconvolute the relative contributions of each cellular compartment (e.g. mitochondria, cytosol, peroxisome, etc.) to cancer metabolism will be crucial to more completely understand the metabolism of cancer cells in the future [74,79]. Ultimately, while mitochondrial dysregulation is widely considered to be a hallmark of cancer, numerous mitochondrial functions remain critical for tumor growth and are emerging as clinical targets.
Following this point, it comes as no surprise that mitochondrial metabolism is highly active in virtually all tumors (i.e., cancer cells, stroma, or both), and investigators have begun targeting these pathways to explore potential efficacy. Indeed, some evidence suggests that biguanides such as metformin or phenformin may limit tumor incidence and burden in humans and animals [80,81]. These effects are presumably due, at least in part, to complex I inhibition of the ETC, which significantly perturbs mitochondrial function [82,83]. However, more insights are needed into the mechanisms of these compounds in patients to determine the therapeutic potential of targeting this and other components of mitochondria. In developing new therapies that target cancer metabolism, researchers will face challenges similar to those that are relevant for many established chemotherapies since deleterious effects on normal proliferating cells that also depend on mitochondrial metabolism (and aerobic glycolysis) are likely to arise.
As we acquire a more detailed picture of how specific genetic modifications in a patient’s tumor correlate with its metabolic profile, opportunities for designing targeted or combinatorial therapies will become increasingly apparent. Cancer therapies that address tumor-specific mitochondrial dysregulation and dysfunction may be particularly effective. For example, some cancer cells harbor mutations in TCA enzymes (e.g., FH, SDH, IDH2) or regulatory proteins that control mitophagy (i.e., LKB1) [84]. Such tumors may be compromised with respect to some aspects of mitochondrial biosynthesis and dependent on alternate pathways for growth and/or survival such that synthetically lethal targets emerge. Ultimately, such strategies will require clinicians and researchers to coordinate metabolic, biochemical, and genetic information in the design of therapeutic strategies.
“Not well versed in Nat peptides so I could not say. I also hesitate with any PNAS paper because those in their academy tend to have a fast track to publication. It has been that way since at least early 2000’s wh n I began research. I don’t doubt their goal and approach (this same group leads the way in methylation-based diagnosis of CNS neoplasms, which is apparently highly accurate). But when I see “dying cells” I know what that means biochemically and look for those hallmarks. Organ specific oligonucleosomes would be a nice cell death surrogate. “
The author and his father have seen several relatives succumb to mental illness.CREDIT PHOTOGRAPH BY DAYANITA SINGH FOR THE NEW YORKER
In the winter of 2012, I travelled from New Delhi, where I grew up, to Calcutta to visit my cousin Moni. My father accompanied me as a guide and companion, but he was a sullen and brooding presence, lost in a private anguish. He is the youngest of five brothers, and Moni is his firstborn nephew—the eldest brother’s son. Since 2004, Moni, now fifty-two, has been confined to an institution for the mentally ill (a “lunatic home,” as my father calls it), with a diagnosis of schizophrenia. He is kept awash in antipsychotics and sedatives, and an attendant watches, bathes, and feeds him through the day.
My father has never accepted Moni’s diagnosis. Over the years, he has waged a lonely campaign against the psychiatrists charged with his nephew’s care, hoping to convince them that their diagnosis was a colossal error, or that Moni’s broken psyche would somehow mend itself. He has visited the institution in Calcutta twice—once without warning, hoping to see a transformed Moni, living a secretly normal life behind the barred gates. But there was more than just avuncular love at stake for him in these visits. Moni is not the only member of the family with mental illness. Two of my father’s four brothers suffered from various unravellings of the mind. Madness has been among the Mukherjees for generations, and at least part of my father’s reluctance to accept Moni’s diagnosis lies in a grim suspicion that something of the illness may be buried, like toxic waste, in himself.
Rajesh, my father’s third-born brother, had once been the most promising of the Mukherjee boys—the nimblest, the most charismatic, the most admired. But in the summer of 1946, at the age of twenty-two, he began to behave oddly, as if a wire had been tripped in his brain. The most obvious change in his personality was a volatility: good news triggered uncontained outbursts of joy; bad news plunged him into inconsolable desolation. By that winter, the sine curve of Rajesh’s psyche had tightened in its frequency and gained in its amplitude. My father recalls an altered brother: fearful at times, reckless at others, descending and ascending steep slopes of mood, irritable one morning and overjoyed the next. When Rajesh received news of a successful performance on his college exams, he vanished, elated, on a two-night excursion, supposedly “exercising” at a wrestling camp. He was feverish and hallucinating when he returned, and died of pneumonia soon afterward. Only years later, in medical school, did I realize that Rajesh was likely in the throes of an acute manic phase. His mental breakdown was the result of a near-textbook case of bipolar disorder.
Jagu, the fourth-born of my father’s siblings, came to live with us in Delhi in 1975, when I was five years old and he was forty-five. His mind, too, was failing. Tall and rail thin, with a slightly feral look in his eyes and a shock of matted, overgrown hair, he resembled a Bengali Jim Morrison. Unlike Rajesh, whose illness had surfaced in his twenties, Jagu had been troubled from his adolescence. Socially awkward, withdrawn from everyone except my grandmother, he was unable to hold a job or live by himself. By 1975, he had visions, phantasms, and voices in his head that told him what to do. He was still capable of extraordinary bursts of tenderness—when I accidentally smashed a beloved Venetian vase at home, he hid me in his bedclothes and informed my mother that he had “mounds of cash” stashed away, enough to buy “a thousand” replacement vases. But this episode was symptomatic: even his love for me extended the fabric of his psychosis and confabulation.
Unlike Rajesh, Jagu was formally diagnosed. In the late nineteen-seventies, a physician in Delhi examined him and determined that he had schizophrenia. But no medicines were prescribed. Instead, Jagu continued to live at home, half hidden away in my grandmother’s room. (As in many families in India, my grandmother lived with us.) For nearly a decade, she and my father maintained a fragile truce, with Jagu living under her care, eating meals in her room and wearing clothes that she stitched for him. At night, when Jagu was consumed by his fears and fantasies, she put him to bed like a child, with her hand on his forehead. She was his nurse, his housekeeper, his only friend, and, more important, his public defender. When my grandmother died, in 1985, Jagu joined a religious sect in Delhi and disappeared, until his death, a dozen years later.
……
at schizophrenia runs in families was evident even to the person who first defined the illness. In 1911, Eugen Bleuler, a Swiss-German psychiatrist, published a book describing a series of cases of men and women, typically in their teens and early twenties, whose thoughts had begun to tangle and degenerate. “In this malady, the associations lose their continuity,” Bleuler wrote. “The threads between thoughts are torn.” Psychotic visions and paranoid thoughts flashed out of nowhere. Some patients “feel themselves weak, their spirit escapes, they will never survive the day. There is a growth in their heads. Their bones have turned liquid; their hearts have turned into stone. . . . The patient’s wife must not use eggs in cooking, otherwise he will grow feathers.” His patients were often trapped between flickering emotional states, unable to choose between two radically opposed visions, Bleuler noted. “You devil, you angel, you devil, you angel,” one woman said to her lover.
Bleuler tried to find an explanation for the mysterious symptoms, but there was only one seemingly common element: schizophrenic patients tended to have first-degree relatives who were also schizophrenic. He had no tools to understand the mechanism behind the heredity. The word “gene” had been coined just two years before Bleuler published his book. The notion that a mental illness could be carried across generations by unitary, indivisible factors—corpuscles of information threading through families—would have struck most of Bleuler’s contemporaries as mad in its own right. Still, Bleuler was astonishingly prescient about the complex nature of inheritance. “If one is looking for ‘theheredity,’ one can nearly always find it,” he wrote. “We will not be able to do anything about it even later on, unless the single factor of heredity can be broken down into many hereditary factors along specific lines.”
In the nineteen-sixties, Bleuler’s hunch was confirmed by twin studies. Psychiatrists determined that if an identical twin was schizophrenic the other twin had a forty-to-fifty-per-cent chance of developing the disease—fiftyfold higher than the risk in the general population. By the early two-thousands, large population studies had revealed a strong genetic link between schizophrenia and bipolar disorder. Some of the families described in these studies had a crisscrossing history that was achingly similar to my own: one sibling affected with schizophrenia, another with bipolar disorder, and a nephew or niece also schizophrenic.
“The twin studies clarified two important features of schizophrenia and bipolar disorder,” Jeffrey Lieberman, a Columbia University psychiatrist who has studied schizophrenia for thirty years, told me. “First, it was clear that there wasn’t a single gene, but dozens of genes involved in causing schizophrenia—each perhaps exerting a small effect. And, second, even if you inherited the entire set of risk genes, as identical twins do, you still might not develop the disease. Obviously, there were other triggers or instigators involved in releasing the illness.” But while these studies established that schizophrenia had a genetic basis, they revealed nothing about the nature of the genes involved. “For doctors, patients, and families in the schizophrenia community, genetics became the ultimate mystery,” Lieberman said. “If we knew the identity of the genes, we would find the causes, and if we found the causes we could find medicines.”
In 2006, an international consortium of psychiatric geneticists launched a genomic survey of schizophrenia, hoping to advance the search for the implicated genes. With 3,322 patients and 3,587 controls, this was one of the largest and most rigorous such studies in the history of the disease. Researchers scanned through the nearly seven thousand genomes to find variations in gene segments that were correlated with schizophrenia. This strategy, termed an “association study,” does not pinpoint a gene, but it provides a general location where a disease-linked gene may be found, like a treasure map with a large “X” scratched in a corner of the genome.
The results, reported in 2009 (and updated in 2014) in the journal Nature, were a dispiriting validation of Bleuler’s hunch about multiple hereditary factors: more than a hundred independent segments of the genome were associated with schizophrenia. “There are lots of small, common genetic effects, scattered across the genome,” one researcher said. “There are many different biological processes involved.” Some of the putative culprits made biological sense—if dimly. There were genes linked to transmitters that relay messages between neurons, and genes for molecular channels that move electrical signals up and down nerve cells. But by far the most surprising association involved a gene segment on chromosome 6. This region of the genome—termed the MHC region—carries hundreds of genes typically associated with the immune system.
“The MHC-segment finding was so strange and striking that you had to sit up and take notice,” Lieberman told me. “Here was the most definitive evidence that something in the immune system might have something to do with schizophrenia. There had been hints about an immunological association before, but this was impossible to argue with. It raised an endlessly fascinating question: what was the link between immune-response genes and schizophrenia?”
In the first years of her career in brain research, Beth Stevens thought of microglia with annoyance if she thought of them at all. When she gazed into a microscope and saw these ubiquitous cells with their spidery tentacles, she did what most neuroscientists had been doing for generations: she looked right past them and focused on the rest of the brain tissue, just as you might look through specks of dirt on a windshield.
“What are they doing there?” she thought. “They’re in the way.’”
Stevens never would have guessed that just a few years later, she would be running a laboratory at Harvard and Boston’s Children’s Hospital devoted to the study of these obscure little clumps. Or that she would be arguing in the world’s top scientific journals that microglia might hold the key to understanding not just normal brain development but also what causes Alzheimer’s, Huntington’s, autism, schizophrenia, and other intractable brain disorders.
Microglia are part of a larger class of cells—known collectively as glia—that carry out an array of functions in the brain, guiding its development and serving as its immune system by gobbling up diseased or damaged cells and carting away debris. Along with her frequent collaborator and mentor, Stanford biologist Ben Barres, and a growing cadre of other scientists, Stevens, 45, is showing that these long-overlooked cells are more than mere support workers for the neurons they surround. Her work has raised a provocative suggestion: that brain disorders could somehow be triggered by our own bodily defenses gone bad.
A type of glial cell known as an oligodendrocyte
In one groundbreaking paper, in January, Stevens and researchers at the Broad Institute of MIT and Harvard showed that aberrant microglia might play a role in schizophrenia—causing or at least contributing to the massive cell loss that can leave people with devastating cognitive defects. Crucially, the researchers pointed to a chemical pathway that might be targeted to slow or stop the disease. Last week, Stevens and other researchers published a similar finding for Alzheimer’s.
This might be just the beginning. Stevens is also exploring the connection between these tiny structures and other neurological diseases—work that earned her a $625,000 MacArthur Foundation “genius” grant last September.
All of this raises intriguing questions. Is it possible that many common brain disorders, despite their wide-ranging symptoms, are caused or at least worsened by the same culprit, a component of the immune system? If so, could many of these disorders be treated in a similar way—by stopping these rogue cells?
Schizophrenia is a heritable brain illness with unknown pathogenic mechanisms. Schizophrenia’s strongest genetic association at a population level involves variation in the major histocompatibility complex (MHC) locus, but the genes and molecular mechanisms accounting for this have been challenging to identify. Here we show that this association arises in part from many structurally diverse alleles of the complement component 4 (C4) genes. We found that these alleles generated widely varying levels of C4A and C4B expression in the brain, with each common C4 allele associating with schizophrenia in proportion to its tendency to generate greater expression of C4A. Human C4 protein localized to neuronal synapses, dendrites, axons, and cell bodies. In mice, C4 mediated synapse elimination during postnatal development. These results implicate excessive complement activity in the development of schizophrenia and may help explain the reduced numbers of synapses in the brains of individuals with schizophrenia.
Science 31 Mar 2016; http://dx.doi.org:/10.1126/science.aad8373Complement and microglia mediate early synapse loss in Alzheimer mouse models. Soyon Hong1, Victoria F. Beja-Glasser1,*, Bianca M. Nfonoyim1,*,…., Ben A. Barres6, Cynthia A. Lemere,2, Dennis J. Selkoe2,7, Beth Stevens1,8,†
Synapse loss in Alzheimer’s disease (AD) correlates with cognitive decline. Involvement of microglia and complement in AD has been attributed to neuroinflammation, prominent late in disease. Here we show in mouse models that complement and microglia mediate synaptic loss early in AD. C1q, the initiating protein of the classical complement cascade, is increased and associated with synapses before overt plaque deposition. Inhibition of C1q, C3 or the microglial complement receptor CR3, reduces the number of phagocytic microglia as well as the extent of early synapse loss. C1q is necessary for the toxic effects of soluble β-amyloid (Aβ) oligomers on synapses and hippocampal long-term potentiation (LTP). Finally, microglia in adult brains engulf synaptic material in a CR3-dependent process when exposed to soluble Aβ oligomers. Together, these findings suggest that the complement-dependent pathway and microglia that prune excess synapses in development are inappropriately activated and mediate synapse loss in AD.
Genome-wide association studies (GWAS) implicate microglia and complement-related pathways in AD (1). Previous research has demonstrated both beneficial and detrimental roles of complement and microglia in plaque-related neuropathology (2, 3); however, their roles in synapse loss, a major pathological correlate of cognitive decline in AD (4), remain to be identified. Emerging research implicates microglia and immune-related mechanisms in brain wiring in the healthy brain (1). During development, C1q and C3 localize to synapses and mediate synapse elimination by phagocytic microglia (5–7). We hypothesized that this normal developmental synaptic pruning pathway is activated early in the AD brain and mediates synapse loss.
Complex machinery
It’s not surprising that scientists for years have ignored microglia and other glial cells in favor of neurons. Neurons that fire together allow us to think, breathe, and move. We see, hear, and feel using neurons, and we form memories and associations when the connections between different neurons strengthen at the junctions between them, known as synapses. Many neuroscientists argue that neurons create our very consciousness.
Glia, on the other hand, have always been considered less important and interesting. They have pedestrian duties such as supplying nutrients and oxygen to neurons, as well as mopping up stray chemicals and carting away the garbage.
Scientists have known about glia for some time. In the 1800s, the pathologist Rudolf Virchow noted the presence of small round cells packing the spaces between neurons and named them “nervenkitt” or “neuroglia,” which can be translated as nerve putty or glue. One variety of these cells, known as astrocytes, was defined in 1893. And then in the 1920s, the Spanish scientist Pio del Río Hortega developed novel ways of staining cells taken from the brain. This led him to identify and name two more types of glial cells, including microglia, which are far smaller than the others and are characterized by their spidery shape and multiple branches. It is only when the brain is damaged in adulthood, he suggested, that microglia spring to life—rushing to the injury, where it was thought they helped clean up the area by eating damaged and dead cells. Astrocytes often appeared on the scene as well; it was thought that they created scar tissue.
This emergency convergence of microglia and astrocytes was dubbed “gliosis,” and by the time Ben Barres entered medical school in the late 1970s, it was well established as a hallmark of neurodegenerative diseases, infection, and a wide array of other medical conditions. But no one seemed to understand why it occurred. That intrigued Barres, then a neurologist in training, who saw it every time he looked under a microscope at neural tissue in distress. “It was just really fascinating,” he says. “The great mystery was: what is the point of this gliosis? Is it good? Is it bad? Is it driving the disease process, or is it trying to repair the injured brain?”
Barres began looking for the answer. He learned how to grow glial cells in a dish and apply a new recording technique to them. He could measure their electrical qualities, which determine the biochemical signaling that all brain cells use to communicate and coördinate activity.
“From the second I started recording the glial cells, I thought ‘Oh, my God!’” Barres recalls. The electrical activity was more dynamic and complex than anyone had thought. These strange electrical properties could be explained only if the glial cells were attuned to the conditions around them, and to the signals released from nearby neurons. Barres’s glial cells, in other words, had all the machinery necessary to engage in a complex dialogue with neurons, and presumably to respond to different kinds of conditions in the brain.
Why would they need this machinery, though, if they were simply involved in cleaning up dead cells? What could they possibly be doing? It turns out that in the absence of chemicals released by glia, the neurons committed the biochemical version of suicide. Barres also showed that the astrocytes appeared to play a crucial role in forming synapses, the microscopic connections between neurons that encode memory. In isolation, neurons were capable of forming the spiny appendages necessary to reach the synapses. But without astrocytes, they were incapable of connecting to one another.
Hardly anyone believed him. When he was a young faculty member at Stanford in the 1990s, one of his grant applications to the National Institutes of Health was rejected seven times. “Reviewers kept saying, ‘Nah, there’s no way glia could be doing this,’” Barres recalls. “And even after we published two papers in Science showing that [astrocytes] had profound, almost all-or-nothing effects in controlling synapses’ formation or synapse activity, I still couldn’t get funded! I think it’s still hard to get people to think about glia as doing anything active in the nervous system.”
Marked for elimination
Beth Stevens came to study glia by accident. After graduating from Northeastern University in 1993, she followed her future husband to Washington, D.C., where he had gotten work in the U.S. Senate. Stevens had been pre-med in college and hoped to work in a lab at the National Institutes of Health. But with no previous research experience, she was soundly rebuffed. So she took a job waiting tables at a Chili’s restaurant in nearby Rockville, Maryland, and showed up at NIH with her résumé every week.
After a few months, Stevens received a call from a researcher named Doug Fields, who needed help in his lab. Fields was studying the intricacies of the process in which neurons become insulated in a coating called myelin. That insulation is essential for the transmission of electrical impulses.
As Stevens spent the following years pursuing a PhD at the University of Maryland, she was intrigued by the role that glial cells played in insulating neurons. Along the way, she became familiar with other insights into glial cells that were beginning to emerge, especially from the lab of Ben Barres. Which is why, soon after completing her PhD in 2003, Stevens found herself a postdoc in Barres’s lab at Stanford, about to make a crucial discovery.
Barres’s group had begun to identify the specific compounds astrocytes secreted that seemed to cause neurons to grow synapses. And eventually, they noticed that these compounds also stimulated production of a protein called C1q.
Conventional wisdom held that C1q was activated only in sick cells—the protein marked them to be eaten up by immune cells—and only outside the brain. But Barres had found it in the brain. And it was in healthy neurons that were arguably at their most robust stage: in early development. What was the C1q protein doing there?
The answer lies in the fact that marking cells for elimination is not something that happens only in diseased brains; it is also essential for development. As brains develop, their neurons form far more synaptic connections than they will eventually need. Only the ones that are used are allowed to remain. This pruning allows for the most efficient flow of neural transmissions in the brain, removing noise that might muddy the signal.
But it was unknown how exactly the process worked. Was it possible that C1q helped signal the brain to prune unused synapses? Stevens focused her postdoctoral research on finding out. “We could have been completely wrong,” she recalls. “But we went for it.”
It paid off. In a 2007 paper, Barres and Stevens showed that C1q indeed plays a role in eliminating unneeded neurons in the developing brain. And they found that the protein is virtually absent in healthy adult neurons.
Now the scientists faced a new puzzle. Does C1q show up in brain diseases because the same mechanism involved in pruning a developing brain later goes awry? Indeed, evidence was already growing that one of the earliest events in neurodegenerative diseases such as Alzheimer’s, Parkinson’s, and Huntington’s was significant loss of synapses.
When Stevens and Barres examined mice bred to develop glaucoma, a neurodegenerative disease that kills neurons in the optic system, they found that C1q appeared long before any other detectable sign that the disease was taking hold. It cropped up even before the cells started dying.
This suggested the immune cells might in fact cause the disease, or at the very least accelerate it. And that offered an intriguing possibility: that something could be made to halt the process. Barres founded a company, Annexon Biosciences, to develop drugs that could block C1q. Last week’s paper published by Barres, Stevens, and other researchers shows that a compound being tested by Annexon appears to be able to prevent the onset of Alzheimer’s in mice bred to develop the disease. Now the company hopes to test it in humans in the next two years.
Paths to treatments
To better understand the process that C1q helps trigger, Stevens and Barres wanted to figure out what actually plays the role of Pac-Man, eating up the synapses marked for death. It was well known that white blood cells known as macrophages gobbled up diseased cells and foreign invaders in the rest of the body. But macrophages are not usually present in the brain. For their theory to work, there had to be some other mechanism. And further research has shown that the cells doing the eating even in healthy brains are those mysterious clusters of material that Beth Stevens, for years, had been gazing right past in the microscope—the microglia that Río Hortega identified almost 100 years ago.
Now Stevens’s lab at Harvard, which she opened in 2008, devotes half its efforts to figuring out what microglia are doing and what causes them to do it. These cells, it turns out, appear in the mouse embryo at day eight, before any other brain cell, which suggests they might help guide the rest of brain development—and could contribute to any number of neurodevelopmental diseases when they go wrong.
Meanwhile, she is also expanding her study of the way different substances determine what happens in the brain. C1q is actually just the first in a series of proteins that accumulate on synapses marked for elimination. Stevens has begun to uncover evidence that there is a wide array of protective “don’t eat me” molecules too. It’s the balance between all these cues that regulates whether microglia are summoned to destroy synapses. Problems in any one could, conceivably, mess up the system.
Evidence is now growing that microglia are involved in several neurodevelopmental and psychiatric problems. The potential link to schizophrenia that was revealed in January emerged after researchers at the Broad Institute, led by Steven McCarroll and a graduate student named Aswin Sekar, followed a trail of genetic clues that led them directly to Stevens’s work. In 2009, three consortia from around the globe had published papers comparing DNA in people with and without schizophrenia. It was Sekar who identified a possible pattern: the more a specific type of protein was present in synapses, the higher the risk of developing the disease. The protein, C4, was closely related to C1q, the one first identified in the brain by Stevens and Barres.
McCarroll knew that schizophrenia strikes in late adolescence and early adulthood, a time when brain circuits in the prefrontal cortex undergo extensive pruning. Others had found that areas of the prefrontal cortex are among those most ravaged by the disease, which leads to massive synapse loss. Could it be that over-pruning by rogue microglia is part of what causes schizophrenia?
To find out, Sekar and McCarroll got in touch with Stevens, and the two labs began to hold joint weekly meetings. They soon demonstrated that C4 also had a role in pruning synapses in the brains of young mice, suggesting that excessive levels of the protein could indeed lead to over-pruning—and to the thinning out of brain tissue that appears to occur as symptoms such as psychotic episodes grow worse.
If the brain damage seen in Parkinson’s and Alzheimer’s stems from over-pruning that might begin early in life, why don’t symptoms of those diseases show up until later? Barres thinks he knows. He notes that the brain can normally compensate for injury by rewiring itself and generating new synapses. It also contains a lot of redundancy. That would explain why patients with Parkinson’s disease don’t show discernible symptoms until they have lost 90 percent of the neurons that produce dopamine.
It also might mean that subtle symptoms could in fact be detected much earlier. Barres points to a study of nuns published in 2000. When researchers analyzed essays the nuns had written upon entering their convents decades before, they found that women who went on to develop Alzheimer’s had shown less “idea density” even in their 20s. “I think the implication of that is they could be lifelong diseases,” Barres says. “The disease process could be going on for decades and the brain is just compensating, rewiring, making new synapses.” At some point, the microglia are triggered to remove too many cells, Barres argues, and the symptoms of the disease begin to manifest fully.
Turning this insight into a treatment is far from straightforward, because much remains unclear. Perhaps an overly aggressive response from microglia is determined by some combination of genetic variants not shared by everyone. Stevens also notes that diseases like schizophrenia are not caused by one mutation; rather, a wide array of mutations with small effects cause problems when they act in concert. The genes that control the production of C4 and other immune-system proteins may be only part of the story. That may explain why not everyone who has a C4 mutation will go on to develop schizophrenia.
Nonetheless, if Barres and Stevens are right that the immune system is a common mechanism behind devastating brain disorders, that in itself is a fundamental breakthrough. Because we have not known the mechanisms that trigger such diseases, medical researchers have been able only to alleviate the symptoms rather than attack the causes. There are no drugs available to halt or even slow neurodegeneration in diseases like Alzheimer’s. Some drugs elevate neurotransmitters in ways that briefly make it easier for individuals with dementia to form new synaptic connections, but they don’t reduce the rate at which existing synapses are destroyed. Similarly, there are no treatments that tackle the causes of autism or schizophrenia. Even slowing the progress of these disorders would be a major advance. We might finally go after diseases that have run unchecked for generations.
“We’re a ways away from a cure,” Stevens says. “But we definitely have a path forward.”
The complement protein C4 is a non-enzymatic component of the C3 and C5 convertases and thus essential for the propagation of the classical complement pathway. The covalent binding of C4 to immunoglobulins and immune complexes (IC) also enhances the solubilization of immune aggregates, and the clearance of IC through complement receptor one (CR1) on erythrocytes. Human C4 is the most polymorphic protein of the complement system. In this review, we summarize the current concepts on the 1-2-3 loci model of C4A and C4B genes in the population, factors affecting the expression levels of C4 transcripts and proteins, and the structural, functional and serological diversities of the C4A and C4B proteins. The diversities and polymorphisms of the mouse homologues Slp and C4 proteins are described and contrasted with their human homologues. The human C4 genes are located in the MHC class III region on chromosome 6. Each human C4 gene consists of 41 exons coding for a 5.4-kb transcript. The long gene is 20.6 kb and the short gene is 14.2 kb. In the Caucasian population 55% of the MHC haplotypes have the 2-locus, C4A-C4B configurations and 45% have an unequal number of C4A and C4B genes. Moreover, three-quarters of C4 genes harbor the 6.4 kb endogenous retrovirus HERV-K(C4) in the intron 9 of the long genes. Duplication of a C4 gene always concurs with its adjacent genes RP, CYP21 and TNX, which together form a genetic unit termed an RCCX module. Monomodular, bimodular and trimodular RCCX structures with 1, 2 and 3 complement C4 genes have frequencies of 17%, 69% and 14%, respectively. Partial deficiencies of C4A and C4B, primarily due to the presence of monomodular haplotypes and homo-expression of C4A proteins from bimodular structures, have a combined frequency of 31.6%. Multiple structural isoforms of each C4A and C4B allotype exist in the circulation because of the imperfect and incomplete proteolytic processing of the precursor protein to form the beta-alpha-gamma structures. Immunofixation experiments of C4A and C4B demonstrate > 41 allotypes in the two classes of proteins. A compilation of polymorphic sites from limited C4 sequences revealed the presence of 24 polymophic residues, mostly clustered C-terminal to the thioester bond within the C4d region of the alpha-chain. The covalent binding affinities of the thioester carbonyl group of C4A and C4B appear to be modulated by four isotypic residues at positions 1101, 1102, 1105 and 1106. Site directed mutagenesis experiments revealed that D1106 is responsible for the effective binding of C4A to form amide bonds with immune aggregates or protein antigens, and H1106 of C4B catalyzes the transacylation of the thioester carbonyl group to form ester bonds with carbohydrate antigens. The expression of C4 is inducible or enhanced by gamma-interferon. The liver is the main organ that synthesizes and secretes C4A and C4B to the circulation but there are many extra-hepatic sites producing moderate quantities of C4 for local defense. The plasma protein levels of C4A and C4B are mainly determined by the corresponding gene dosage. However, C4B proteins encoded by monomodular short genes may have relatively higher concentrations than those from long C4A genes. The 5′ regulatory sequence of a C4 gene contains a Spl site, three E-boxes but no TATA box. The sequences beyond–1524 nt may be completely different as the C4 genes at RCCX module I have RPI-specific sequences, while those at Modules II, III and IV have TNXA-specific sequences. The remarkable genetic diversity of human C4A and C4B probably promotes the exchange of genetic information to create and maintain the quantitative and qualitative variations of C4A and C4B proteins in the population, as driven by the selection pressure against a great variety of microbes. An undesirable accompanying byproduct of this phenomenon is the inherent deleterious recombinations among the RCCX constituents leading to autoimmune and genetic disorders.
C4A isotype is responsible for effective binding to form amide bonds with immune aggregates or protein antigens, while C4B isotype catalyzes the transacylation of the thioester carbonyl group to form ester bonds with carbohydrate antigens.
Derived from proteolytic degradation of complement C4, C4a anaphylatoxin is a mediator of local inflammatory process.
Schizophrenia and the Synapse
Genetic evidence suggests that overactive synaptic pruning drives development of schizophrenia.
Compared to the brains of healthy individuals, those of people with schizophrenia have higher expression of a gene called C4, according to a paper published inNature today (January 27). The gene encodes an immune protein that moonlights in the brain as an eradicator of unwanted neural connections (synapses). The findings, which suggest increased synaptic pruning is a feature of the disease, are a direct extension of genome-wide association studies (GWASs) that pointed to the major histocompatibility (MHC) locus as a key region associated with schizophrenia risk.
“The MHC [locus] is the first and the strongest genetic association for schizophrenia, but many people have said this finding is not useful,” said psychiatric geneticist Patrick Sullivan of the University of North Carolina School of Medicine who was not involved in the study. “The value of [the present study is] to show that not only is it useful, but it opens up new and extremely interesting ideas about the biology and therapeutics of schizophrenia.”
Schizophrenia has a strong genetic component—it runs in families—yet, because of the complex nature of the condition, no specific genes or mutations have been identified. The pathological processes driving the disease remain a mystery.
Researchers have turned to GWASs in the hope of finding specific genetic variations associated with schizophrenia, but even these have not provided clear candidates.
“There are some instances where genome-wide association will literally hit one base [in the DNA],” explained Sullivan. While a 2014 schizophrenia GWAS highlighted the MHC locus on chromosome 6 as a strong risk area, the association spanned hundreds of possible genes and did not reveal specific nucleotide changes. In short, any hope of pinpointing the MHC association was going to be “really challenging,” said geneticist Steve McCarroll of Harvard who led the new study.
Nevertheless, McCarroll and colleagues zeroed in on the particular region of the MHC with the highest GWAS score—the C4 gene—and set about examining how the area’s structural architecture varied in patients and healthy people.
The C4 gene can exist in multiple copies (from one to four) on each copy of chromosome 6, and has four different forms: C4A-short, C4B-short, C4A-long, and C4B-long. The researchers first examined the “structural alleles” of the C4 locus—that is, the combinations and copy numbers of the different C4 forms—in healthy individuals. They then examined how these structural alleles related to expression of both C4Aand C4B messenger RNAs (mRNAs) in postmortem brain tissues.
…………..
Schizophrenia risk from complex variation of complement component 4
Schizophrenia is a heritable brain illness with unknown pathogenic mechanisms. Schizophrenia’s strongest genetic association at a population level involves variation in the major histocompatibility complex (MHC) locus, but the genes and molecular mechanisms accounting for this have been challenging to identify. Here we show that this association arises in part from many structurally diverse alleles of the complement component 4 (C4) genes. We found that these alleles generated widely varying levels of C4A and C4B expression in the brain, with each common C4 allele associating with schizophrenia in proportion to its tendency to generate greater expression of C4A. Human C4 protein localized to neuronal synapses, dendrites, axons, and cell bodies. In mice, C4 mediated synapse elimination during postnatal development. These results implicate excessive complement activity in the development of schizophrenia and may help explain the reduced numbers of synapses in the brains of individuals with schizophrenia.
Cannon, T. D. et al. Cortex mapping reveals regionally specific patterns of genetic and disease-specific gray-matter deficits in twins discordant for schizophrenia. Proc. Natl Acad. Sci. USA99, 3228–3233 (2002)
Cannon, T. D. et al. Progressive reduction in cortical thickness as psychosis develops: a multisite longitudinal neuroimaging study of youth at elevated clinical risk. Biol. Psychiatry77,147–157 (2015)
Garey, L. J. et al. Reduced dendritic spine density on cerebral cortical pyramidal neurons in schizophrenia. J. Neurol. Neurosurg. Psychiatry65, 446–453 (1998)
Glantz, L. A. & Lewis, D. A. Decreased dendritic spine density on prefrontal cortical pyramidal neurons in schizophrenia. Arch. Gen. Psychiatry57, 65–73 (2000)
Schizophrenia Working Group of the Psychiatric Genomics Consortium. Biological insights from 108 schizophrenia-associated genetic loci. Nature511, 421–427 (2014)
International Schizophrenia Consortium et al. Common polygenic variation contributes to risk of schizophrenia and bipolar disorder. Nature460, 748–752 (2009)
Schizophrenia Psychiatric Genome-Wide Association Study Consortium. Genome-wide association study identifies five new schizophrenia loci. Nature Genet . 43, 969–976 (2011)
The strongest genetic association found in schizophrenia is its association to genetic markers across the major histocompatibility complex (MHC) locus, first described in three Nature papers in 2009. …
Schizophrenia: From genetics to physiology at last
Jianxin Shi1, et al. Common variants on chromosome 6p22.1 are associated with schizophrenia. Nature 460, 753-757 (6 August 2009) | doi:10.1038/nature08192; Received 29 May 2009; Accepted 10 June 2009; Published online 1 July 2009; Corrected 6 August 2009
Schizophrenia, a devastating psychiatric disorder, has a prevalence of 0.5–1%, with high heritability (80–85%) and complex transmission1. Recent studies implicate rare, large, high-penetrance copy number variants in some cases2, but the genes or biological mechanisms that underlie susceptibility are not known. Here we show that schizophrenia is significantly associated with single nucleotide polymorphisms (SNPs) in the extended major histocompatibility complex region on chromosome 6. We carried out a genome-wide association study of common SNPs in the Molecular Genetics of Schizophrenia (MGS) case-control sample, and then a meta-analysis of data from the MGS, International Schizophrenia Consortium and SGENE data sets. No MGS finding achieved genome-wide statistical significance. In the meta-analysis of European-ancestry subjects (8,008 cases, 19,077 controls), significant association with schizophrenia was observed in a region of linkage disequilibrium on chromosome 6p22.1 (P = 9.54 × 10⁻⁹). This region includes a histone gene cluster and several immunity-related genes—possibly implicating aetiological mechanisms involving chromatin modification, transcriptional regulation, autoimmunity and/or infection. These results demonstrate that common schizophrenia susceptibility alleles can be detected. The characterization of these signals will suggest important directions for research on susceptibility mechanisms.
Editor’s Summary 6 August 2009
Schizophrenia risk: link to chromosome 6p22.1
A genome-wide association study using the Molecular Genetics of Schizophrenia case-control data set, followed by a meta-analysis that included over 8,000 cases and 19,000 controls, revealed that while common genetic variation that underlies risk to schizophrenia can be identified, there probably are few or no single common loci with large effects. The common variants identified here lie on chromosome 6p22.1 in a region that includes a histone gene cluster and several genes implicated in immunity.
Letter
Hreinn Stefansson1,48, et al. Common variants conferring risk of schizophrenia. Nature460, 744-747 (6 August 2009) | doi:10.1038/nature08186; Received 16 March 2009; Accepted 5 June 2009; Published online 1 July 2009
Schizophrenia is a complex disorder, caused by both genetic and environmental factors and their interactions. Research on pathogenesis has traditionally focused on neurotransmitter systems in the brain, particularly those involving dopamine. Schizophrenia has been considered a separate disease for over a century, but in the absence of clear biological markers, diagnosis has historically been based on signs and symptoms. A fundamental message emerging from genome-wide association studies of copy number variations (CNVs) associated with the disease is that its genetic basis does not necessarily conform to classical nosological disease boundaries. Certain CNVs confer not only high relative risk of schizophrenia but also of other psychiatric disorders1, 2, 3. The structural variations associated with schizophrenia can involve several genes and the phenotypic syndromes, or the ‘genomic disorders’, have not yet been characterized4. Single nucleotide polymorphism (SNP)-based genome-wide association studies with the potential to implicate individual genes in complex diseases may reveal underlying biological pathways. Here we combined SNP data from several large genome-wide scans and followed up the most significant association signals. We found significant association with several markers spanning the major histocompatibility complex (MHC) region on chromosome 6p21.3-22.1, a marker located upstream of the neurogranin gene (NRGN) on 11q24.2 and a marker in intron four of transcription factor 4 (TCF4) on 18q21.2. Our findings implicating the MHC region are consistent with an immune component to schizophrenia risk, whereas the association with NRGN and TCF4 points to perturbation of pathways involved in brain development, memory and cognition.
Letter
The International Schizophrenia Consortium. Common polygenic variation contributes to risk of schizophrenia and bipolar disorder. Nature460, 748-752 (6 August 2009) | doi:10.1038/nature08185; Received 11 February 2009; Accepted 8 June 2009; Published online 1 July 2009; Corrected 6 August 2009
Schizophrenia is a severe mental disorder with a lifetime risk of about 1%, characterized by hallucinations, delusions and cognitive deficits, with heritability estimated at up to 80%1, 2. We performed a genome-wide association study of 3,322 European individuals with schizophrenia and 3,587 controls. Here we show, using two analytic approaches, the extent to which common genetic variation underlies the risk of schizophrenia. First, we implicate the major histocompatibility complex. Second, we provide molecular genetic evidence for a substantial polygenic component to the risk of schizophrenia involving thousands of common alleles of very small effect. We show that this component also contributes to the risk of bipolar disorder, but not to several non-psychiatric diseases.
The Psychiatric GWAS Consortium Steering Committee. A framework for interpreting genome-wide association studies of psychiatric disorders. Molecular Psychiatry (2009) 14, 10–17; doi:10.1038/mp.2008.126; published online 11 November 2008
Genome-wide association studies (GWAS) have yielded a plethora of new findings in the past 3 years. By early 2009, GWAS on 47 samples of subjects with attention-deficit hyperactivity disorder, autism, bipolar disorder, major depressive disorder and schizophrenia will be completed. Taken together, these GWAS constitute the largest biological experiment ever conducted in psychiatry (59 000 independent cases and controls, 7700 family trios and >40 billion genotypes). We know that GWAS can work, and the question now is whether it will work for psychiatric disorders. In this review, we describe these studies, the Psychiatric GWAS Consortium for meta-analyses of these data, and provide a logical framework for interpretation of some of the conceivable outcomes.
The purpose of this article is to consider the ‘big picture’ and to provide a logical framework for the possible outcomes of these studies. This is not a review of GWAS per se as many excellent reviews of this technically and statistically intricate methodological approach are available.7, 8, 9, 10, 11, 12 This is also not a review of the advantages and disadvantages of different study designs and sampling strategies for the dissection of complex psychiatric traits. We would like to consider how the dozens of GWAS papers that will soon be in the literature can be synthesized: what can integrated mega-analyses (meta-analysis is based on summary data (for example, odds ratios) from all available studies whereas ‘mega-analysis’ uses individual-level genotype and phenotype data) of all available GWAS data tell us about the etiology of these psychiatric disorders? This is an exceptional opportunity as positive or negative results will enable us to learn hard facts about these critically important psychiatric disorders. We suggest that it is not a matter of ‘success versus failure’ or ‘optimism versus pessimism’ but rather an opportunity for systematic and logical approaches to empirical data whereby both positive and appropriately qualified negative findings are informative.
The studies that comprise the Psychiatric GWAS Consortium (PGC; http://pgc.unc.edu) are shown in Table 1. GWAS data for ADHD, autism, bipolar disorder, major depressive disorder and schizophrenia from 42 samples of European subjects should be available for mega-analyses by early 2009 (>59 000 independent cases and controls and >7700 family trios). To our knowledge, the PGC will have access to the largest set of GWAS data available.
A major change in human genetics in the past 5 years has been in the growth of controlled-access data repositories, and individual phenotype and genotype data are now available for many of the studies in Table 1. When the PGC mega-analyses are completed, most data will be available to researchers via the NIMH Human Genetics Initiative (http://nimhgenetics.org). Although the ready availability of GWAS data is a benefit to the field by allowing rapid application of a wide range of analytic strategies to GWAS data, there are potential disadvantages. GWAS mega-analysis is complex and requires considerable care and expertise to be done validly. For psychiatric phenotypes, there is the additional challenge of working with disease entities based largely on clinical description, with unknown biological validity and having both substantial clinical variation within diagnostic categories as well as overlaps across categories.13 Given the urgent need to know if there are replicable genotype–phenotype associations, a new type of collaboration was required.
The purpose of the PGC is to conduct rigorous and comprehensive within- and cross-disorder GWAS mega-analyses. The PGC began in early 2007 with the principal investigators of the four GAIN GWAS,14 and within six months had grown to 110 participating scientists from 54 institutions in 11 countries. The PGC has a coordinating committee, five disease-working groups, a cross-disorder group, a statistical analysis and computational group, and a cluster computer for statistical analysis. It is remarkable that almost all investigators approached agreed to participate and that no one has left the PGC. Most effort is donated but we have obtained funding from the NIMH, the Netherlands Scientific Organization, Hersenstichting Nederland and NARSAD.
The PGC has two major specific aims. (1) Within-disorder mega-analyses: conduct separate mega-analyses of all available GWAS data for ADHD, autism, bipolar disorder, major depressive disorder, and schizophrenia to attempt to identify genetic variation convincingly associated with any one of these five disorders. (2) Cross-disorder mega-analyses: the clinically-derived DSM-IV and ICD-10 definitions may not directly reflect the fundamental genetic architecture.15 There are two subaims. (2a) Conduct mega-analysis to identify genetic variation convincingly associated with conventional definitions of two or more disorders. This nosological aim could assist in delineating the boundaries of this set of disorders. (2b) An expert working group will convert epidemiological and genetic epidemiological evidence into explicit hypotheses about overlap among these disorders, and then conduct mega-analyses based on these definitions (for example, to examine the lifetime presence of idiopathic psychotic features without regard to diagnostic context).
The goal of the PGC is to identify convincing genetic variation-disease associations. A convincing association would be extremely unlikely to result from chance, show consistent effect sizes across all or almost all samples and be impervious to vigorous attempts to disprove the finding (for example, by investigating sources of bias, confirmatory genotyping, and so on). Careful attention will be paid to the impact of potential sources of heterogeneity17 with the goal of assessing its impact without minimizing its presence.
Biological plausibility is not an initial requirement for a convincing statistical association, as there are many examples in human genetics of previously unsuspected candidate genes nonetheless showing highly compelling associations. For example, multiple SNPs in intron 1 of the FTO gene were associated with body mass index in 13 cohorts with 38 759 participants18 and yet ‘FTO’ does not appear in an exhaustive 116 page compilation of genetic studies of obesity.19 Some strong associations are in gene deserts: multiple studies have found convincing association between prostate cancer and a region on 8q24 that is ~250 kb from the nearest annotated gene.20 Both of these examples are being intensively investigated and we suspect that a compelling mechanistic ‘story’ will emerge in the near future. The presence of a compelling association without an obvious biological mechanism establishes a priority research area for molecular biology and neuroscience of a psychiatric disorder.
The PGC will use mega-analysis as the main analytic tool as individual-level data will be available from almost all samples. To wield this tool appropriately, a number of preconditions must be met. First, genotype data from different GWAS platforms must be made comparable as the direct overlap between platforms is often modest. This requires meticulous quality control for the inclusion of both SNPs and subjects and attention to the factors that can cause bias (for example, population stratification, cryptic relatedness or genotyping batch effects). Genotype harmonization can be accomplished using imputation (21, 22, for example) so that the same set of ~2 million23, 24 directly or imputed SNP genotypes are available for all subjects. Second, phenotypes need to be harmonized across studies. This is one of the most crucial components of the PGC and we are fortunate to have world experts directing the work. Third, the mega-analyses will assess potential heterogeneity of associations across samples.
A decision-tree schematic of the potential outcomes of the PGC mega-analyses is shown in Figure 1. Note that many of the possibilities in Figure 1 are not mutually exclusive and different disorders may take different paths through this framework. It is possible that there eventually will be dozens or hundreds of sequence variants strictly associated with these disorders with frequencies ranging from very rare to common.
………
GWAS has the potential to yield considerable insights but it is no panacea and may well perform differently for psychiatric disorders. Even if these psychiatric GWAS efforts are successful, the outcomes will be complex. GWAS may help us learn that clinical syndromes are actually many different things—for example, proportions of individuals with schizophrenia might evidence associations with rare CNVs of major effect,5, 6 with more common genetic variation in dozens (perhaps hundreds) of genomic regions, between genetic variation strongly modified by environmental risk factors, and some proportion may be genetically indistinguishable from the general population. Moreover, as fuel to long-standing ‘lumper versus splitter’ debates in psychiatric nosology, empirical data might show that some clinical disorders or identifiable subsets of subjects might overlap considerably.
The critical advantage of GWAS is the search of a ‘closed’ hypothesis space. If the large amount of GWAS data being generated are analyzed within a strict and coherent framework, it should be possible to establish hard facts about the fundamental genetic architecture of a set of important psychiatric disorders—which might include positive evidence of what these disorders are or exclusionary evidence of what they are not. Whatever the results, these historically large efforts should yield hard facts about ADHD, autism, bipolar disorder, major depressive disorder and schizophrenia that may help guide the next era of psychiatric research.
Pe’er I, Yelensky R, Altshuler D, Daly MJ. Estimation of the multiple testing burden for genomewide association studies of nearly all common variants. Genet Epidemiol 2008; 32: 381–385. | Article | PubMed |
Weiss LA, Shen Y, Korn JM, Arking DE, Miller DT, Fossdal R et al. Association between microdeletion and microduplication at 16p11.2 and autism. N Engl J Med 2008; 358: 667–675. | Article | PubMed | ChemPort |
Letter
Hreinn Stefansson1,36, et al. Large recurrent microdeletions associated with schizophrenia. Nature455, 232-236 (11 September 2008) | doi:10.1038/nature07229; Received 17 April 2008; Accepted 8 July 2008; Corrected 11 September 2008
Reduced fecundity, associated with severe mental disorders1, places negative selection pressure on risk alleles and may explain, in part, why common variants have not been found that confer risk of disorders such as autism2, schizophrenia3 and mental retardation4. Thus, rare variants may account for a larger fraction of the overall genetic risk than previously assumed. In contrast to rare single nucleotide mutations, rare copy number variations (CNVs) can be detected using genome-wide single nucleotide polymorphism arrays. This has led to the identification of CNVs associated with mental retardation4, 5 and autism2. In a genome-wide search for CNVs associating with schizophrenia, we used a population-based sample to identify de novoCNVs by analysing 9,878 transmissions from parents to offspring. The 66 de novo CNVs identified were tested for association in a sample of 1,433 schizophrenia cases and 33,250 controls. Three deletions at 1q21.1, 15q11.2 and 15q13.3 showing nominal association with schizophrenia in the first sample (phase I) were followed up in a second sample of 3,285 cases and 7,951 controls (phase II). All three deletions significantly associate with schizophrenia and related psychoses in the combined sample. The identification of these rare, recurrent risk variants, having occurred independently in multiple founders and being subject to negative selection, is important in itself. CNV analysis may also point the way to the identification of additional and more prevalent risk variants in genes and pathways involved in schizophrenia.
The C4 gene can exist in multiple copies (from one to four) on each copy of chromosome 6, and has four different forms: C4A-short, C4B-short, C4A-long, and C4B-long. The researchers first examined the “structural alleles” of the C4 locus—that is, the combinations and copy numbers of the different C4 forms—in healthy individuals. They then examined how these structural alleles related to expression of both C4Aand C4B messenger RNAs (mRNAs) in postmortem brain tissues.
From this the researchers had a clear picture of how the architecture of the C4 locus affected expression ofC4A and C4B. Next, they compared DNA from roughly 30,000 schizophrenia patients with that from 35,000 healthy controls, and a correlation emerged: the alleles most strongly associated with schizophrenia were also those that were associated with the highest C4A expression. Measuring C4A mRNA levels in the brains of 35 schizophrenia patients and 70 controls then revealed that, on average, C4A levels in the patients’ brains were 1.4-fold higher.
C4 is an immune system “complement” factor—a small secreted protein that assists immune cells in the targeting and removal of pathogens. The discovery of C4’s association to schizophrenia, said McCarroll, “would have seemed random and puzzling if it wasn’t for work . . . showing that other complement components regulate brain wiring.” Indeed, complement protein C3 locates at synapses that are going to be eliminated in the brain, explained McCarroll, “and C4 was known to interact with C3 . . . so we thought well, actually, this might make sense.”
McCarroll’s team went on to perform studies in mice that revealed C4 is necessary for C3 to be deposited at synapses. They also showed that the more copies of the C4 gene present in a mouse, the more the animal’s neurons were pruned.
Synaptic pruning is a normal part of development and is thought to reflect the process of learning, where the brain strengthens some connections and eradicates others. Interestingly, the brains of deceased schizophrenia patients exhibit reduced neuron density. The new results, therefore, “make a lot of sense,” said Cardiff University’s Andrew Pocklington who did not participate in the work. They also make sense “in terms of the time period when synaptic pruning is occurring, which sort of overlaps with the period of onset for schizophrenia: around adolescence and early adulthood,” he added.
“[C4] has not been on anybody’s radar for having anything to do with schizophrenia, and now it is and there’s a whole bunch of really neat stuff that could happen,” said Sullivan. For one, he suggested, “this molecule could be something that is amenable to therapeutics.”
UniProtKB
Derived from proteolytic degradation of complement C4, C4a anaphylatoxin is a mediator of local inflammatory process. It induces the contraction of smooth muscle, increases vascular permeability and causes histamine release from mast cells and basophilic leukocytes.
Non-enzymatic component of C3 and C5 convertases and thus essential for the propagation of the classical complement pathway. Covalently binds to immunoglobulins and immune complexes and enhances the solubilization of immune aggregates and the clearance of IC through CR1 on erythrocytes. C4A isotype is responsible for effective binding to form amide bonds with immune aggregates or protein antigens, while C4B isotype catalyzes the transacylation of the thioester carbonyl group to form ester bonds with carbohydrate antigens.
Researchers from Harvard Medical School and Massachusetts General Hospital have completed the first stage of an important collaboration aimed at understanding the intricate variables of neuropsychiatric disease—something that currently eludes clinicians and scientists.
The research team, led by Isaac Kohane at HMS and Roy Perlis at Mass General, has created a neuropsychiatric cellular biobank—one of the largest in the world.
It contains induced pluripotent stem cells, or iPSCs, derived from skin cells taken from 100 people with neuropsychiatric diseases such as schizophrenia, bipolar disorder and major depression, and from 50 people without neuropsychiatric illness.
In addition, a detailed profile of each patient, obtained from hours of in-person assessment as well as from electronic medical records, is matched to each cell sample.
As a result, the scientific community can now for the first time access cells representing a broad swath of neuropsychiatric illness. This enables researchers to correlate molecular data with clinical information in areas such as variability of drug reactions between patients. The ultimate goal is to help treat, with greater precision, conditions that often elude effective management.
The cell collection and generation was led by investigators at Mass General, who in collaboration with Kohane and his team are working to characterize the cell lines at a molecular level. The cell repository, funded by the National Institutes of Health, is housed at Rutgers University.
“This biobank, in its current form, is only the beginning,” said Perlis, director of the MGH Psychiatry Center for Experimental Drugs and Diagnostics and HMS associate professor of psychiatry. “By next year we’ll have cells from a total of four hundred patients, with additional clinical detail and additional cell types that we will share with investigators.”
A current major limitation to understanding brain diseases is the inability to access brain biopsies on living patients. As a result, researchers typically study blood cells from patients or examine post-mortem tissue. This is in stark contrast with diseases such as cancer, for which there are many existing repositories of highly characterized cells from patients.
The new biobank offers a way to push beyond this limitation.
A Big Step Forward
While the biobank is already a boon to the scientific community, researchers at MGH and the HMS Department of Biomedical Informatics will be adding additional layers of molecular data to all of the cell samples. This information will include whole genome sequencing and transcriptomic and epigenetic profiling of brain cells made from the stem cell lines.
Collaborators in the HMS Department of Neurobiology, led by Michael Greenberg, department chair and Nathan Marsh Pusey Professor of Neurobiology, will also work to examine characteristics of other types of neurons derived from these stem cells.
“This can potentially alter the entire way we look at and diagnose many neuropsychiatric conditions,” said Perlis.
One example may be to understand how the cellular responses to medication correspond to the patient’s documented responses, comparing in vitro with in vivo. “This would be a big step forward in bringing precision medicine to psychiatry,” Perlis said.
“It’s important to recall that in the field of genomics, we didn’t find interesting connections to disease until we had large enough samples to really investigate these complex conditions,” said Kohane, chair of the HMS Department of Biomedical Informatics.
“Our hypothesis is that here we will require far fewer patients,” he said. “By measuring the molecular functioning of the cells of each patient rather than only their genetic risk, and combining that all that’s known of these people in terms of treatment response and cognitive function, we will discover a great deal of valuable information about these conditions.”
Added Perlis, “In the early days of genetics, there were frequent false positives because we were studying so few people. We’re hoping to avoid the same problem in making cellular models, by ensuring that we have a sufficient number of cell lines to be confident in reporting differences between patient groups.”
The generation of stem cell lines and characterization of patients and brain cell lines is funded jointly by the the National Institute of Mental Health, the National Human Genome Research Institute and a grant from the Centers of Excellence in Genomic Science program.
On C.T.E. and Athletes, Science Remains in Its Infancy
Alzheimer’s disease is the most common form of dementia, characterized by two pathological hallmarks: amyloid-β plaques and neurofibrillary tangles1. The amyloid hypothesis of Alzheimer’s disease posits that the excessive accumulation of amyloid-β peptide leads to neurofibrillary tangles composed of aggregated hyperphosphorylated tau2, 3. However, to date, no single disease model has serially linked these two pathological events using human neuronal cells. Mouse models with familial Alzheimer’s disease (FAD) mutations exhibit amyloid-β-induced synaptic and memory deficits but they do not fully recapitulate other key pathological events of Alzheimer’s disease, including distinct neurofibrillary tangle pathology4, 5. Human neurons derived from Alzheimer’s disease patients have shown elevated levels of toxic amyloid-β species and phosphorylated tau but did not demonstrate amyloid-β plaques or neurofibrillary tangles6, 7, 8, 9, 10, 11. Here we report that FAD mutations in β-amyloid precursor protein and presenilin 1 are able to induce robust extracellular deposition of amyloid-β, including amyloid-β plaques, in a human neural stem-cell-derived three-dimensional (3D) culture system. More importantly, the 3D-differentiated neuronal cells expressing FAD mutations exhibited high levels of detergent-resistant, silver-positive aggregates of phosphorylated tau in the soma and neurites, as well as filamentous tau, as detected by immunoelectron microscopy. Inhibition of amyloid-β generation with β- or γ-secretase inhibitors not only decreased amyloid-β pathology, but also attenuated tauopathy. We also found that glycogen synthase kinase 3 (GSK3) regulated amyloid-β-mediated tau phosphorylation. We have successfully recapitulated amyloid-β and tau pathology in a single 3D human neural cell culture system. Our unique strategy for recapitulating Alzheimer’s disease pathology in a 3D neural cell culture model should also serve to facilitate the development of more precise human neural cell models of other neurodegenerative disorders.
Figure 2: Robust increases of extracellular amyloid-β deposits in 3D-differentiated hNPCs with FAD mutations.close
a, Thin-layer 3D culture protocol. HC, histochemistry; IF, immunofluorescence; IHC, immunohistochemistry. b, Amyloid-β deposits in 6-week differentiated control and FAD ReN cells in 3D Matrigel (green, GFP; blue, 3D6; scale bar, …
In the March 28th, 2016 issue of the journal Nature Medicine, Mark Tuszynski and his colleagues from the University of California, San Diego, in collaboration with colleagues from Japan and Wisconsin, report that they were able to successfully coax stem cell-derived neurons to regenerate damaged corticospinal tracts in rats. Furthermore, this regeneration produced observable, functional benefits.
What is the “corticospinal tract” you ask? The corticospinal tracts are part of the “pyramidal tracts” that include the corticospinal and corticobulbar tracts. The pyramidal tracts are the main controllers of voluntary movement and connect their nerve fibers eventually to cells that serve voluntary muscles and allow them to contract. We call such nerves “motor nerves,” and the corticospinal nerve tracts are among the most important of the motor nerve tracts.
These neural tracts are collectively called “pyramidal tracts” because they pass through a small area of the brain stem known as the pyramids, which lie on the ventral side of the medulla oblongata. Both pyramidal tracts originate in the forebrain; specifically from the so-called “motor cortex” of the forebrain. The motor cortex lies just in front of the central sulcus of the forebrain. In the motor cortex, lies thousands of “upper motor neurons” that extend their axons down to the brain stem and spinal cord.
In the brain stem, the majority of these corticospinal tracts crossover (or decussate) to the other side of the brain stem and travel down the opposite side of the spinal cord. The corticospinal axons extend all the way down the spinal cord, until they make a connection (synapse) with a “lower motor neuron” that extends its axon to the skeletal muscles that it will direct to contract. The corticobulbar tract contains nerves that conduct nerve impulses from cranial nerves and these help the muscles of the face and neck contract, and are involved in facial expressions, swallowing, chewing, and so on.
Damage to the upper motor neurons as a result of a stroke can rob a person of the ability to move, since the muscles that are attached to the upper motor neurons cannot receive any signals to contract. Likewise, damage to the axonal tracts (also known as nerve fibers) can paralyze a patient and rob them of their ability to move.
“We humans use corticospinal axons for voluntary movement,” said Tuszynski. “In the absence of regeneration of this system in previous studies, I was doubtful that most therapies taken to humans would improve function. Now that we can regenerate the most important motor system for humans, I think that the potential for translation is more promising.”
Novel use of EPR spectroscopy to study in vivo protein structure
α-synuclein is a protein found abundantly throughout the brain. It is present mainly at the neuron ends where it is thought to play a role in ensuring the supply of synaptic vesicles in presynaptic terminals, which are required for the release of neurotransmitters to relay signals between neurons. It is critical for normal brain function.
However, α-synuclein is also the primary protein component of the cerebral amyloid deposits characteristic of Parkinson’s disease and its precursor is found in the amyloid plaques of Alzheimer’s disease. Although α-synuclein is present in all areas of the brain, these disease-state amyloid plaques only arise in distinct areas.
Imaging of isolated samples of α-synuclein in vitro indicate that it does not have the precise 3D folded structure usually associated with proteins. It is therefore classed as an intrinsically disordered protein. However, it was not known whether the protein also lacked a precise structure in vivo.
There have been reports that it can form helical tetramers. Since the 3D structure of a biological protein is usually precisely matched to the specific function it performs, knowing the structure of α-synuclein within a living cell will help elucidate its role and may also improve understanding of the disease states with which it is associated.
If α-synuclein remains disordered in vivo, it may be possible for the protein to achieve different structures, and have different properties, depending on its surroundings.
Techniques for determining protein structure
It has long been known that elucidating the structure of a protein at an atomic level is fundamental for understanding its normal function and behavior. Furthermore, such knowledge can also facilitate the development of targeted drug treatments. Unfortunately, observing the atomic structure of a protein in vivo is not straightforward.
X-ray diffraction is the technique usually adopted for visualizing structures at atomic resolution, but this requires crystals of the molecule to be produced and this cannot be done without separating the molecules of interest from their natural environment. Such processes can modify the protein from its usual state and, particularly with complex structures, such effects are difficult to predict.
The development of nuclear magnetic resonance (NMR) spectroscopy improved the situation by making it possible for molecules to be analyzed under in vivo conditions, i.e. same pH, temperature and ionic concentration.
More recently, increases in the sensitivity of NMR and the use of isotope labelling have enabled determinations of the atomic level structure and dynamics of proteins to be determined within living cells1. NMR has been used to determine the structure of a bacterial protein within living cells2 but it is difficult to achieve sufficient quantities of the required protein within mammalian cells and to keep the cells alive for NMR imaging to be conducted.
Electron paramagnetic resonance (EPR) spectroscopy for determining protein structure
Recently, researchers have managed to overcome these obstacles by using in-cell NMR and electron paramagnetic resonance (EPR) spectroscopy. EPR spectroscopy is a technique that is similar to NMR spectroscopy in that it is based on the measurement and interpretation of the energy differences between excited and relaxed molecular states.
In EPR spectroscopy it is electrons that are excited, whereas in NMR signals are created through the spinning of atomic nuclei. EPR was developed to measure radicals and metal complexes, but has also been utilized to study the dynamic organization of lipids in biological membranes3.
EPR has now been used for the first time in protein structure investigations and has provided atomic-resolution information on the structure of α-synuclein in living mammalians4,5.
Bacterial forms of the α-synuclein protein labelled with 15N isotopes were introduced into five types of mammalian cell using electroporation. Concentrations of α-synuclein close to those found in vivo were achieved and the 15N isotopes allowed the protein to be clearly defined from other cellular components by NMR. The conformation of the protein was then determined using electron paramagnetic resonance (EPR).
The results showed that within living mammalian cells α-synuclein remains as a disordered and highly dynamic monomer. Different intracellular environments did not induce major conformational changes.
Summary
The novel use of EPR spectroscopy has resolved the mystery surrounding the in vivo conformation of α-synuclein. It showed that α-synuclein maintains its disordered monomeric form under physiological cell conditions. It has been demonstrated for the first time that even in crowded intracellular environments α-synuclein does not form oligomers, showing that intrinsic structural disorder can be sustained within mammalian cells.
References
Freedberg DI and Selenko P. Live cell NMR Annu. Rev. Biophys. 2014;43:171–192.
Sakakibara D, et al. Protein structure determination in living cells by in-cell NMR spectroscopy. Nature 2009;458:102–105.
Yashroy RC. Magnetic resonance studies of dynamic organisation of lipids in chloroplast membranes. Journal of Biosciences 1990;15(4):281.
Alderson TA and Bax AD. Parkinson’s Disease. Disorder in the court. Nature 2016; doi:10.1038/nature16871.
Theillet FX, et al. Structural disorder of monomeric α-synuclein persists in mammalian cells. Nature 2016; doi:10.1038/nature16531.
The corticospinal tract (CST) is the most important motor system in humans, yet robust regeneration of this projection after spinal cord injury (SCI) has not been accomplished. In murine models of SCI, we report robust corticospinal axon regeneration, functional synapse formation and improved skilled forelimb function after grafting multipotent neural progenitor cells into sites of SCI. Corticospinal regeneration requires grafts to be driven toward caudalized (spinal cord), rather than rostralized, fates. Fully mature caudalized neural grafts also support corticospinal regeneration. Moreover, corticospinal axons can emerge from neural grafts and regenerate beyond the lesion, a process that is potentially related to the attenuation of the glial scar. Rat corticospinal axons also regenerate into human donor grafts of caudal spinal cord identity. Collectively, these findings indicate that spinal cord ‘replacement’ with homologous neural stem cells enables robust regeneration of the corticospinal projection within and beyond spinal cord lesion sites, achieving a major unmet goal of SCI research and offering new possibilities for clinical translation.


 2012pharmaceutical
 sjwilliamspa