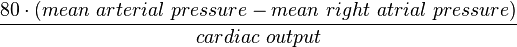Feeds:
Posts
Comments

Archive for the ‘HTN’ Category

Treatment, Prevention and Cost of Cardiovascular Disease: Current & Predicted Cost of Care and the Potential for Improved Individualized Care Using Clinical Decision Support Systems

Author, and Content Consultant to e-SERIES A: Cardiovascular Diseases: Justin Pearlman, MD, PhD, FACC

Author and Curator: Larry H Bernstein, MD, FACP

and

Curator: Aviva Lev-Ari, PhD, RN

This article has the following FIVE parts:

1. Forecasting the Impact of Heart Failure in the United States : A Policy Statement From the American Heart Association

2. A Case Study from the GENETIC CONNECTIONS — In The Family: Heart Disease Seeking Clues to Heart Disease in DNA of an Unlucky Family

3. Arterial Stiffness and Cardiovascular Events : The Framingham Heart Study

4. Arterial Elasticity in Quest for a Drug Stabilizer: Isolated Systolic Hypertension
caused by Arterial Stiffening Ineffectively Treated by Vasodilatation Antihypertensives

5. Clinical Decision Support Systems: Realtime Clinical Expert Support — Biomarkers of Cardiovascular Disease : Molecular Basis and Practical Considerations


1. Forecasting the Impact of Heart Failure in the United States : A Policy Statement From the American Heart Association

PA Heidenreich, NM Albert, LA Allen, DA Bluemke, J Butler, et al. Circulation: Heart Failure 2013;6.
Print ISSN: 1941-3289, Online ISSN: 1941-3297.

Heart failure (HF) poses a major burden on productivity and cost of national healthcare expenditures

  • among older Americans, more are hospitalized for HF than for any other medical condition.

As the population ages, the prevalence of HF is expected to increase.

The purpose of this report is to

  • provide an in-depth look at how the changing demographics in the United States will impact the prevalence and cost of care for HF for different US populations.

 Projections of HF Prevalence

Prevalence estimates for HF were determined from

 Projections of the US Population With HF From 2010 to 2030 for Different Age Groups

Year

All ages

18-44 y

45-64 y

65-79 y

> 80

2012 5 813 262 396 578 1 907 141 2 192 233 1 317 310
2015 6 190 606 402 926 1 949 669 2 483 853 1 354 158
2020 6 859 623 417 600 1 974 585 3 004 002 1 463 436
2025 7 644 674 434 635 1 969 852 3 526 347 1 713 840
2030 8 489 428 450 275 2 000 896 3 857 729 2 180 528

Future Costs of HF

The future costs of HF were estimated by methods developed by the American Heart Association

  • project the prevalence and costs of HF from 2012 to 2030
  • factor out  the costs attributable to comorbid conditions.

The model does this by assuming that

(1) HF prevalence percentages will remain constant by age, sex, and race/ethnicity;

(2) the costs of technological innovation will rise at the current rate.

HF prevalence and costs (direct and indirect) were projected using the following steps:

1. HF prevalence and average cost per person were estimated by age group (18–44, 45–64, 65–79, ≥80 years), gender (male, female), and race/ethnicity (white non-Hispanic, white Hispanic, black, other) [32]. The initial HF cost per person and rate of increase in cost was determined for each demographic group, as a percentage of total healthcare expeditures.

2. Inflation is separately addressed by correcting dollar values from Medical Expenditure Panel Survey (MEPS) to 2010 dollars.

3. Nursing home spending triggered an adjustment. The estimates project the incremental cost of care attributable to heart failure (HF).

4. Total HF population prevalence and costs were projected by multiplying the US Census–projected population of each demographic group by the percentage prevalence and average cost

5. The total work loss and home productivity loss costs were generated by multiplying per capita work days lost attributable to HF by (1) prevalence of HF, (2) the probability of employment given HF (for work loss costs only), (3) mean per capita daily earnings, and (4) US Census population projection counts.

Projections of Indirect Costs

Indirect costs of lost productivity from morbidity and premature mortality were estimated as detailed below.
Morbidity costs represent the value of lost earnings attributable to HF and include loss of work among

  • currently employed individuals and those too sick to work, as well as
  • home productivity loss, which is the value of household services performed by household members who do not receive pay for the services.

Total Costs Attributable to Heart Failure (HF)

Projections of Total Cost of Care ($ Billions) for HF for Different Age Groups of the US Population

Year All 18–44 45–64 65–79 ≥ 80
2012
Medical 20.9 0.33 3.67 8.46 8.42
Indirect: Morbidity 5.42 0.52 1.92 2.05 0.93
Indirect: Mortality 4.35 0.66 2.53 0.98 0.18
Total 30.7 1.51 8.12 11.5 9.53
2020
Medical 31.1 0.43 4.58 14.2 11.8
Indirect: Morbidity 7.09 0.66 2.20 3.11 1.12
Indirect: Mortality 5.39 0.79 2.89 1.49 0.22
Total 43.6 1.88 9.67 18.8 13.2
2030
Medical 53.1 0.59 5.86 23.3 23.4
Indirect: Morbidity 9.80 0.91 2.54 4.48 1.87
Indirect: Mortality 6.84 0.98 3.32 2.16 0.37
Total 69.7 2.48 11.7 29.9 25.6

Excludes HF care costs that have been attributed to comorbid conditions.

Cost of Care

Total medical costs are projected to increase from $20.9 billion in 2012 to $53.1 billion in 2030, a 2.5-fold increase. Assuming continuation of current hospitalization practices, the majority (80%) of the costs stem from

  • hospitalization. Also, the majority of increase is from directs costs. Indirect costs are expected to rise as well, but at a lower rate, from $9.8 billion to $16.6 billion, an increase of 69%.

Direct costs (cost of medical care) are expected to increase at a faster rate than indirect costs because of premature deaths and lost productivity.

The total cost of HF (direct and indirect costs) is expected to increase in 2030 from the current $30.7 billion to at least $69.8 billion. This will amount to $244 for every US adult in 2030.

Thus the burden of HF for the US healthcare system will grow substantially during the next 18 years if current trends continue.

It is estimated that

  • by 2030, the prevalence of HF in the United States will increase by 25%, to 3.0%.
  • >8 million people in the US (1 in every 33) will have HF by 2030.
  • the projected total direct medical costs of HF between 2012 and 2030 (in 2010 dollars) will increase from $21 billion to $53 billion.
  • Total costs, including indirect costs for HF, are estimated to increase from $31 billion in 2012 to $70 billion in 2030.
  • If one assumes all costs of cardiac care for HF patients are attributable to HF
    (no cost attribution to comorbid conditions), the 2030 projected cost estimates of treating patients with HF will be 3-fold higher ($160 billion in direct costs).

Projections can be lowered if action is taken to reduce the health and economic burden of HF. Strategies, plans, and implementation to prevent HF and improve the efficiency of care are needed.

Causes and Stages of HF

If the projections for accelerating HF costs are to be avoided, attention to the different causes of HF and their risk factors is warranted.
HF is a clinical syndrome that results from a variety of cardiac disorders

  1. idiopathic dilated cardiomyopathy
  2. cardiac valvular disease
  3. pericarditis or pericardial effusion
  4. ischemic heart disease
  5. primary or secondary hypertension
  6. renovascular disease
  7. advanced liver disease with decreased venous return
  8. pulmonary hypertension
  9. prolonged hypoalbuminemia with generalized interstitial edema
  10. diabetic nephropathy
  11. heart muscle infiltration disease such as primary or secondary amyloidosis
  12. myocarditis
  13. rhythm disorders
  14. congenital diseases
  15. accidental trauma (war, chest trauma)
  16. toxicities (methamphetamine, cocaine, heavy metals, chemotherapy)

HF generally causes symptoms:

  • shortness of breath
  • fatigue
  • swelling (edema)
  • inability to lay flat (orthopnea, paroxysmal nocturnal dyspnea)
  • possibly cough, wheezing

In the Western world the predominant causes of HF are:

  • coronary artery disease
  • valvular disease
  • hypertension
  • viral, alcohol, methamphetamine or other drug  toxicity cardiomyopathy
  • stress (catechol toxicity, takotsubo “broken heart” cardiomyopathy)
  • atrial fibrillation/rapid heart rates
  • thyroid disease

In 2001, the American College of Cardiology and AHA practice guidelines for chronic HF promoted a classification system that encompasses 4 stages of HF.

  • Stage A: Patients at high risk for developing HF in the future but no functional or structural heart disorder.
  • Stage B: a structural heart disorder but no symptoms.
  • Stage C: previous or current symptoms of heart failure, manageable with medical treatment.
  • Stage D: advanced disease requiring hospital-based support, a heart transplant or palliative care.

Stages A and B are considered precursors to the clinical HF and are meant

  1. to alert healthcare providers to known risk factors for HF and
  2. the available therapies aimed at mitigating disease progression.

Stage A patients have risk factors for HF hypertension, atherosclerotic heart disease, and/or diabetes mellitus.

Patients with stage B are asymptomatic patients who have  developed structural heart disease from a variety of potential insults to the heart muscle such as myocardial infarction or valvular heart disease.

Stages C and D represent the symptomatic phases of HF, with stage C manageable and stage D failing medical management, resulting in marked symptoms at rest or with minimal activity despite optimal medical therapy.

Therapeutic interventions include:

  • dietary salt restriction and diuretics
  • medications known to prolong survival (beta blockers, ACE inhibitors, aldosterone inhibitors)
  • implantable devices such as pacemakers and defibrillators
  • stoppage of tobacco, toxic drugs, excess alcohol

Classic demographic risk factors for the development of HF include

  • older age, male gender, ethnicity, and low socioeconomic status.
  • comorbid disease states contribute to the development of HF
    • Ischemic heart disease
    • Hypertension

Diabetes mellitus, insulin resistance, and obesity are also linked to HF development,

  • with diabetes mellitus increasing the risk of HF by ≈2-fold in men and up to 5-fold in women.

Smoking remains the single largest preventable cause of disease and premature death in the United States.

Translation of Scientific Evidence into Clinical Practice

In multiple studies, failures to apply evidence-based management strategies are blamed for avoidable hospitalizations and/or deaths from HF

Improved implementation of guidelines can delay, mitigate or prevent the onset of HF, and improve survival. Performance improvement programs have facilitated the implementation of evidence-based therapies in both hospital and ambulatory care settings.

Care transition programs by hospitals have become more widespread

  • in an effort to reduce avoidable readmissions.

The interventions used by these programs include

  • initiating discharge planning early in the course of hospital care,
  • actively involving patients and families or caregivers in the plan of care,
  • providing new processes and systems that ensure patient understanding of the plan of care before discharge from the hospital, and
  • improving quality of care by continually monitoring adherence to national evidence-based guidelines with appropriate adaptations for individual differences in needs and responses.

In multiple studies,adherence to the HF plan of care was associated with reduced all-cause mortality as well as HF hospitalization.

It is anticipated that care transition programs may increase appropriate admissions while decreasing inappropriate admissions

This would have a potentially benenficial impact on the 30-day all-cause readmission rate that has become

  • a focus of public reporting in pay for performance.

More than a quarter of Medicare spending occurs in the last year of life, and

  • the costs of care during the last 6 months for a patient with HF have been increasing (11% from 2000 to 2007).

Improving end-of-life care cost effectiveness for patients with stage D HF will require ongoing

  • improved prediction of outcomes
  • integration of multiple aspects of care
  • educated examination of alternatives and priorities
  • improved decision-making
  • unbiased allocation of resources and coverage for this process rather than unbalanced coverage favoring catastrophic care

Palliative care, including formal hospice care, is increasingly advocated for patients with advanced HF.
Offering palliative care to patients with HF may lead to

  • more conservative (and less expensive) treatment
  • consistent with many patients’ goals for care

The use of hospice services is growing among the HF population,

  • HF now the second most common reason for entering hospice
  • but hospice declaration may impose automated restrictions on care that can impose an impediment to election of hospice

A recent study of patients in hospice care found that

  • patients with HF were more likely than patients with cancer to use hospice services longer than 6 months or to be discharged from hospice care alive.

Highlights:

1. Increasing incidence and costs of care for heart failure projected from 2012 to 2030

2. Direct costs rising at greater rate than indirect costs

3. American Heart Association has defined 4 stages of HF, the last 2 of which are advanced

4. Stages C & D are clinically overt and contribute to rehospitalization

5. Stage D accounts for a significant use of end-of-life hospice care

6. There are evidence-based guidelines for the provision of coordinated care that are not widely applied at present

Basic questions raised:

1. If stages A & B are under the radar, then what measures can best trigger the use of evidence-based guidelines for care?
2. Why are evidence-based guidelines commonly not deployed?

  • Flaws in the “evidence” due to bias, design errors, limted ability to extrapolate to the patients it should address
  • Delays in education, convincing of caretakers, and deployment
  • Inadequate resources
  • Financial or other disincentives

The arguments for introducing coordinated care and for evidence-based guidelines is strong.

Arguments AGAINST slavish imposition of evidence based medicine include genetic individuality (what is best on average is not necessarily best for each genetically and behaviorly distinct individual). Strict adherence to evidence-based guidelines also stifles innovative explorations. None-the-less, deviations from evidence-based plans should be cautious, well-documented, and well-informed, not due to mal-aligned incentives, ignorance, carelessness or error.

The question of when and how to intervene most cost effectively is unanswered. If some patients are salt-sensitive as a contribution to the prevalence of hypertension and heart failure, should EVERYONE be salt restricted or should there be a more concerted effort to define who is salt sensitive? What if it proved more cost-effective to restrict salt intake for everyone, even though many might be fine with high sodium intake, and some might even benefit from or require high sodium intake? Is it reasonable to impose costs, hurdles, even possible harm on some as a cheaper way to achieve “greater good”?
These issues are highly relevant to the proposed emphasis on holistic solutions.

2. A Case Study from the GENETIC CONNECTIONS — In The Family: Heart Disease Seeking Clues to Heart Disease in DNA of an Unlucky Family

By GINA KOLATA   2013.05.13  New York Times

Scientists are studying the genetic makeup of the Del Sontro family for

  • telltale mutations or aberrations in the DNA.

Robin Ashwood, one of Mr. Del Sontro’s sisters, found out she had extensive heart disease even though her electrocardiograms was normal. Six of her seven siblings also have heart disease, despite not having any of the traditional risk factors. Then, after a sister, just 47 years old, found out she had advanced heart disease, Mr. Del Sontro, then 43, went to a cardiologist. An X-ray of his arteries revealed the truth. Like his grand-father, his mother, his four brothers and two sisters, he had heart disease.

Now he and his extended family have joined an extraordinary federal research project that is using genetic sequencing to find factors that increase the risk of heart disease beyond the usual suspects — high cholesterol, high blood pressure, smoking and diabetes.“We don’t know yet how many pathways there are to heart disease,” said Dr. Leslie Biesecker, who directs the study Mr. Del Sontro joined. “That’s the power of genetics. To try and dissect that.”

“I had bought the dream: if you just do the right things and eat the right things, you will be O.K.,” said Mr. Del Sontro, whose cholesterol and blood pressure are reassuringly low.

3. Arterial Stiffness and Cardiovascular Events : The Framingham Heart Study

GF Mitchell, Shih-Jen Hwang, RS Vasan, MG Larson.

Circulation. 2010;121:505-511.  http://circ.ahajournals.org/content/121/4/505
http://dx.doi.org/10.1161/CIRCULATIONAHA.109.886655

Various measures of arterial stiffness and wave reflection have been proposed as cardiovascular risk markers.
Prior studies have not assessed relations of a comprehensive panel of stiffness measures to prognosis.
First-onset major cardiovascular disease events in relation to arterial stiffness

  • pulse wave velocity [PWV]
  • wave reflection
    • augmentation index
    • carotid-brachial pressure amplification)
  • central pulse pressure

were analyzed  in 2232 participants (mean age, 63 years; 58% women) in the Framingham Heart Study by a proportional hazards model. During median follow-up of 7.8 (range, 0.2 to 8.9) years,

  • 151 of 2232 participants (6.8%) experienced an event.

In multivariable models adjusted for

  • age
  • sex
  • systolic blood pressure
  • use of antihypertensive therapy
  • total and high-density lipoprotein cholesterol concentrations
  • smoking
  • presence of diabetes mellitus

higher aortic PWV was associated with a 48% increase in cardiovascular disease risk (95% confidence interval, 1.16 to 1.91 per SD; P 0.002).

After PWV was added to a standard risk factor model, integrated discrimination improvement was 0.7% (95% confidence interval, 0.05% to 1.3%; P 0.05).

In contrast,

  • augmentation index,
  • central pulse pressure, and
  • pulse pressure amplification

were not related to cardiovascular disease outcomes in multivariable models.

Higher aortic stiffness assessed by PWV

  • is associated with increased risk for a first cardiovascular event.

Aortic PWV improves risk prediction when added to standard risk factors and may represent

  • a valuable biomarker of cardiovascular disease risk

We shall here visit a recent article by Justin D. Pearlman and Aviva Lev-Ari, PhD, RN, on

Pros and Cons of Drug Stabilizers for Arterial  Elasticity as an Alternative or Adjunct to Diuretics and Vasodilators in the Management of Hypertension, titled

4. Hypertension and Vascular Compliance: 2013 Thought Frontier – An Arterial Elasticity Focus

http://pharmaceuticalintelligence.com/2013/05/11/arterial-elasticity-in-quest-for-a-drug-stabilizer-isolated-systolic-hypertension-caused-by-arterial-stiffening-ineffectively-treated-by-vasodilatation-antihypertensives/

Speaking at the 2013 International Conference on Prehypertension and Cardiometabolic Syndrome, meeting cochair Dr Reuven Zimlichman (Tel Aviv University, Israel) argued that there is a growing number of patients for whom the conventional methods are inappropriate for

  • the definitions of hypertension
  • the risk-factor tables used to guide treatment

Most antihypertensives today work by producing vasodilation or decreasing blood volume which may be

  • ineffective treatments for patients in whom average arterial diameter and circulating volume are not the causes of hypertension and as targets of therapy may promote decompensation

In the future, he predicts, “we will have to start looking for a totally different medication that will aim to

  • improve or at least to stabilize arterial elasticity: medication that might affect factors that determine the stiffness of the arteries, like collagen, like fibroblasts.

Those are not the aim of any group of antihypertensive medications today.”

Zimlichman believes existing databases could be used to develop algorithms that focus on

  • inelasticity as a mechanism of hypertensive disease

He also points out that

  • ambulatory blood-pressure-monitoring devices can measure elasticity

http://www.theheart.org/article/1502067.do

A related article was published on the relationship between arterial stiffening and primary hypertension.

Arterial stiffening provides sufficient explanation for primary hypertension.

KH Pettersen, SM Bugenhagen, J Nauman, DA Beard, SW Omholt.

By use of empirically well-constrained computer models describing the coupled function of the baroreceptor reflex and mechanics of the circulatory system, we demonstrate quantitatively that

  • arterial stiffening seems sufficient to explain age-related emergence of hypertension.

Specifically,

  • the empirically observed chronic changes in pulse pressure with age
  • the capacity of hypertensive individuals to regulate short-term changes in blood pressure becomes impaired

The results suggest that a major target for treating chronic hypertension in the elderly  may include

  • the reestablishment of a proper baroreflex response.

http://arxiv.org/abs/1305.0727v2?goback=%2Egde_4346921_member_240018699

5. Clinical Decision Support Systems: Realtime Clinical Expert Support: Biomarkers of Cardiovascular Disease — Molecular Basis and Practical Considerations

RS Vasan.  Circulation. 2006;113:2335-2362

http://dx.doi.org/10.1161/CIRCULATIONAHA.104.482570

http://circ.ahajournals.org/content/113/19/2335

Substantial data indicate that CVD is a life course disease that begins with the evolution of risk factors that contribute to

  • subclinical atherosclerosis.

Subclinical disease culminates in overt CVD. The onset of CVD itself portends an adverse prognosis with greater

  • risks of recurrent adverse cardiovascular events, morbidity, and mortality.

Clinical assessment alone has limitations. Clinicians have used additional tools to aid clinical assessment and to enhance their ability to identify the “vulnerable” patient at risk for CVD, as suggested by a recent National Institutes of Health (NIH) panel.

Biomarkers are one such tool to better identify high-risk individuals, to diagnose disease conditions promptly for diagnosis, prognosis, and treatment guidance.

Biological marker (biomarker): A laboratory test value that is objectively measured and evaluated as an indicator of

  1. normal biological processes,
  2. pathogenic processes, or
  3. pharmacological responses to a therapeutic intervention.

Type 0 biomarker: A marker of the natural history of a disease

  • Type 0 correlates longitudinally with known clinical indices/predicts outcomes.

Type I biomarker: A marker that captures the effects of a therapeutic intervention

  • Type I assesses an aspect of treatment mechanism of action.

Type 2 biomarker (surrogate end point):  A marker intended to predict outcomes on the basis of

  • epidemiologic
  • therapeutic
  • pathophysiologic or
  • other scientific evidence.

With biomarkers monitoring disease progression or response to therapy, the patient can serve as  his or her own control (follow-up values may be compared to baseline  values).

Costs may be less important for prognostic markers when they are largely restricted to people with disease (total cost=cost per person x number to be tested, plus down-stream costs). Some biomarkers (e.g., an exercise stress test) may be used for both diagnostic and prognostic purposes.

Generally there are cost differences in establishing a prognostic value versus diagnostic value of a biomarker:

  • prognostic utility typically requires a large sample and a prospective design, whereas
  • diagnostic value often can be determined with a smaller sample in a cross-sectional design

Regardless of the intended use, it is important to remember that biomarkers that do not change disease management

  • cannot affect patient outcome and therefore
  • are unlikely to be cost-effective (judged in terms of quality-adjusted life-years gained).

Typically, for a biomarker to change management, it is important to have evidence that risk reduction strategies should vary with biomarker levels, and/or biomarker-guided management achieves advantages over a management scheme that ignores the biomarker levels.

Typically it means that biomarker levels should be modifiable by therapy.

Gil David and Larry Bernstein have developed, in consultation with Prof. Ronald Coifman, in the Yale University Applied Mathematics Program, a software system that is the equivalent of an intelligent Electronic Health Records Dashboard that

  • provides empirical medical reference and
  • suggests quantitative diagnostics options.

The current design of the Electronic Medical Record (EMR) is a
linear presentation of portions of the record

  • by services
  • by diagnostic method, and
  • by date

to cite examples.

This allows perusal through a graphical user interface (GUI) that

  • partitions the information or necessary reports in a workstation entered by keying to icons.
  • presents decision support

Examples of data partitions include:

  • history
  • medications
  • laboratory reports
  • imaging
  • EKGs

The introduction of a DASHBOARD adds presentation of

  • drug reactions
  • allergies
  • primary and secondary diagnoses, and
  • critical information

about any patient the care giver needing access to the record.

A basic issue for such a tool is what information is presented and how it is displayed.

A determinant of the success of this endeavor is if it

  • facilitates workflow
  • facilitates decision-making process
  • reduces medical error.

Continuing work is in progress in extending the capabilities with model datasets, and sufficient data based on the assumption that computer extraction of data from disparate sources will, in the long run, further improve this process.

For instance, there is synergistic value in finding coincidence of:

  • ST shift on EKG
  • elevated cardiac biomarker (troponin)
  • in the absence of substantially reduced renal function.

Similarly, the conversion of hematology based data into useful clinical information requires the establishment of problem-solving constructs based on the measured data.

The most commonly ordered test used for managing patients worldwide is the hemogram that often incorporates

  • morphologic review of a peripheral smear
  • descriptive statistics

While the hemogram has undergone progressive modification of the measured features over time the subsequent expansion of the panel of tests has provided a window into the cellular changes in the

  • production
  • release
  • or suppression

of the formed elements from the blood-forming organ into the circulation. In the hemogram one can view data reflecting the characteristics of a broad spectrum of medical conditions.

Progressive modification of the measured features of the hemogram has delineated characteristics expressed as measurements of

  • size
  • density, and
  • concentration

resulting in many characteristic features of classification. In the diagnosis of hematological disorders

  • proliferation of marrow precursors
  • domination of a cell line
  • suppression of hematopoiesis

Other dimensions are created by considering

  • the maturity and size of the circulating cells.

The application of rules-based, automated problem solving should provide a valid approach to

  • the classification and interpretation of the data used to determine a knowledge-based clinical opinion.

The exponential growth of knowledge since the mapping of the human genome enabled by parallel advances in applied mathematics that have not been a part of traditional clinical problem solving.

As the complexity of statistical models has increased

  • the dependencies have become less clear to the individual.

Contemporary statistical modeling has a primary goal of finding an underlying structure in studied data sets.
The development of an evidence-based inference engine that can substantially interpret the data at hand and

  • convert it in real time to a “knowledge-based opinion”

could improve clinical decision-making by incorporating into the model

  • multiple complex clinical features as well as onset and duration .

An example of a difficult area for clinical problem solving is found in the diagnosis of Systemic Inflammatory Response Syndrome (SIRS) and associated sepsis. SIRS is a costly diagnosis in hospitalized patients.   Failure to diagnose it in a timely manner increases the financial and safety hazard.  The early diagnosis of SIRS/sepsis is made by the application of defined criteria by the clinician.

  • temperature
  • heartrate
  • respiratory rate and
  • WBC count

The application of those clinical criteria, however, defines the condition after it has developed, leaving unanswered the hope for

  • a reliable method for earlier diagnosis of SIRS.

The early diagnosis of SIRS may possibly be enhanced by the measurement of proteomic biomarkers, including

  • transthyretin
  • C-reactive protein
  • procalcitonin
  • mean arterial pressure

Immature granulocyte (IG) measurement has been proposed as a

  • readily available indicator of the presence of granulocyte precursors (left shift).

The use of such markers, obtained by automated systems in conjunction with innovative statistical modeling, provides

  • a promising support to early accurate decision making.

Such a system aims to reduce medical error by utilizing

  • the conjoined syndromic features of disparate data elements .

How we frame our expectations is important. It determines

  • the data we collect to examine the process.

In the absence of data to support an assumed benefit, there is no proof of validity at whatever cost.

Potential arenas of benefit include:

  • hospital operations
  • nonhospital laboratory studies
  • companies in the diagnostic business
  • planners of health systems

The problem stated by LL  WEED in “Idols of the Mind” (Dec 13, 2006):
“ a root cause of a major defect in the health care system is that, while we falsely admire and extol the intellectual powers of highly educated physicians, we do not search for the external aids their minds require.” Hospital information technology (HIT) use has been focused on information retrieval, leaving

  • the unaided mind burdened with information processing.

We deal with problems in the interpretation of data presented to the physician, and how the situation could be improved through better

  • design of the software that presents data .

The computer architecture that the physician uses to view the results is more often than not presented

  • as the designer would prefer, and not as the end-user would like.

In order to optimize the interface for physician, the system could have a “front-to-back” design, with the call up for any patient

  • A dashboard design that presents the crucial information that the physician would likely act on in an easily accessible manner
  • Each item used has to be closely related to a corresponding criterion needed for a decision.

Feature Extraction.

Eugene Rypka contributed greatly to clarifying the extraction of features in a series of articles, which

  • set the groundwork for the methods used today in clinical microbiology.

The method he describes is termed S-clustering, and

  • will have a significant bearing on how we can view laboratory data.

He describes S-clustering as extracting features from endogenous data that

  • amplify or maximize structural information to create distinctive classes.

The method classifies by taking the number of features with sufficient variety to generate maps.

The mapping is done by

  • a truth table NxN of messages and choices
  • each variable is scaled to assign values for each message choice.

For example, the message for an antibody titer would be converted from 0 + ++ +++ to 0 1 2 3.

Even though there may be a large number of measured values, the variety is reduced by this compression, even though it may represent less information.

The main issue is

  • how a combination of variables falls into a table to convey meaningful information.

We are concerned with

  • accurate assignment into uniquely variable groups by information in test relationships.

One determines the effectiveness of each variable by its contribution to information gain in the system. The reference or null set is the class having no information.  Uncertainty in assigning to a classification can be countered by providing sufficient information.

One determines the effectiveness of each variable by its contribution to information gain in the system. The possibility for realizing a good model for approximating the effects of factors supported by data used

  • for inference owes much to the discovery of Kullback-Liebler distance or “information”, and Akaike
  • found a simple relationship between K-L information and Fisher’s maximized log-likelihood function.

In the last 60 years the application of entropy comparable to

  • the entropy of physics, information, noise, and signal processing,
  • developed by Shannon, Kullback, and others
  • integrated with modern statistics,
  • as a result of the seminal work of Akaike, Leo Goodman, Magidson and Vermunt, and work by Coifman

Akaike pioneered recognition that the choice of model influence results in a measurable manner. In particular, a larger number of variables promotes further explanations of variance, such that a model selection criterion is important that penalizes for the number of variables when success is measured by explanation of variance.

Gil David et al. introduced an AUTOMATED processing of the data available to the ordering physician and

  • can anticipate an enormous impact in diagnosis and treatment of perhaps half of the top 20 most common
  • causes of hospital admission that carry a high cost and morbidity.

For example:

  1. anemias (iron deficiency, vitamin B12 and folate deficiency, and hemolytic anemia or myelodysplastic syndrome);
  2. pneumonia; systemic inflammatory response syndrome (SIRS) with or without bacteremia;
  3. multiple organ failure and hemodynamic shock;
  4. electrolyte/acid base balance disorders;
  5. acute and chronic liver disease;
  6. acute and chronic renal disease;
  7. diabetes mellitus;
  8. protein-energy malnutrition;
  9. acute respiratory distress of the newborn;
  10. acute coronary syndrome;
  11. congestive heart failure;
  12. hypertension
  13. disordered bone mineral metabolism;
  14. hemostatic disorders;
  15. leukemia and lymphoma;
  16. malabsorption syndromes; and
  17. cancer(s)[breast, prostate, colorectal, pancreas, stomach, liver, esophagus, thyroid, and parathyroid].
  18. endocrine disorders
  19. prenatal and perinatal diseases

Rudolph RA, Bernstein LH, Babb J: Information-Induction for the diagnosis of
myocardial infarction. Clin Chem 1988;34:2031-2038.

Bernstein LH (Chairman). Prealbumin in Nutritional Care Consensus Group.

Measurement of visceral protein status in assessing protein and energy
malnutrition: standard of care. Nutrition 1995; 11:169-171.

Bernstein LH, Qamar A, McPherson C, Zarich S, Rudolph R. Diagnosis of myocardial infarction:
integration of serum markers and clinical descriptors using information theory.
Yale J Biol Med 1999; 72: 5-13.

Kaplan L.A.; Chapman J.F.; Bock J.L.; Santa Maria E.; Clejan S.; Huddleston D.J.; Reed R.G.;
Bernstein L.H.; Gillen-Goldstein J. Prediction of Respiratory Distress Syndrome using the
Abbott FLM-II amniotic fluid assay. The National Academy of Clinical Biochemistry (NACB)
Fetal Lung Maturity Assessment Project.  Clin Chim Acta 2002; 326(8): 61-68.

Bernstein LH, Qamar A, McPherson C, Zarich S. Evaluating a new graphical ordinal logit method
(GOLDminer) in the diagnosis of myocardial infarction utilizing clinical features and laboratory
data. Yale J Biol Med 1999; 72:259-268.

Bernstein L, Bradley K, Zarich SA. GOLDmineR: Improving models for classifying patients with
chest pain. Yale J Biol Med 2002; 75, pp. 183-198.

Ronald Raphael Coifman and Mladen Victor Wickerhauser. Adapted Waveform Analysis as a Tool for Modeling, Feature Extraction, and Denoising. Optical Engineering, 33(7):2170–2174, July 1994.

R. Coifman and N. Saito. Constructions of local orthonormal bases for classification and regression.
C. R. Acad. Sci. Paris, 319 Série I:191-196, 1994.

Realtime Clinical Expert Support and validation System

We have developed a software system that is the equivalent of an intelligent Electronic Health Records Dashboard that provides empirical medical reference and suggests quantitative diagnostics options. The primary purpose is to gather medical information, generate metrics, analyze them in realtime and provide a differential diagnosis, meeting the highest standard of accuracy. The system builds its unique characterization and provides a list of other patients that share this unique profile, therefore

  • utilizing the vast aggregated knowledge (diagnosis, analysis, treatment, etc.) of the medical community.
  • The main mathematical breakthroughs are provided by accurate patient profiling and inference methodologies
  • in which anomalous subprofiles are extracted and compared to potentially relevant cases.

As the model grows and its knowledge database is extended, the diagnostic and the prognostic become more accurate and precise.
We anticipate that the effect of implementing this diagnostic amplifier would result in

  • higher physician productivity at a time of great human resource limitations,
  • safer prescribing practices,
  • rapid identification of unusual patients,
  • better assignment of patients to observation, inpatient beds,
    intensive care, or referral to clinic,
  • shortened length of patients ICU and bed days.

The main benefit is a

  1. real time assessment as well as
  2. diagnostic options based on comparable cases,
  3. flags for risk and potential problems

as illustrated in the following case acquired on 04/21/10. The patient was diagnosed by our system with severe SIRS at a grade of 0.61 .

Graphical presentation of patient status

The patient was treated for SIRS and the blood tests were repeated during the following week. The full combined record of our system’s assessment of the patient, as derived from the further hematology tests, is illustrated below. The yellow line shows the diagnosis that corresponds to the first blood test (as also shown in the image above). The red line shows the next diagnosis that was performed a week later.

Progression changes in patient ICU stay with SIRS

The MISSIVE(c) system, by Justin Pearlman, is an alternative approach that includes not only automated data retrieval and reformatting of data for decision support, but also an integrated set of tools to speed up analysis, structured for quality and error reduction, couplled to facilitated report generation, incorporation of just-in-time knowledge and group expertise, standards of care, evidence-based planning, and both physician and patient instruction.

See also in Pharmaceutical Intelligence:

The Cost Burden of Disease: U.S. and Michigan.CHRT Brief. January 2010. @www.chrt.org

The National Hospital Bill: The Most Expensive Conditions by Payer, 2006. HCUP Brief #59.

Rudolph RA, Bernstein LH, Babb J: Information-Induction for the diagnosis of myocardial infarction. Clin Chem 1988;34:2031-2038.

Bernstein LH, Qamar A, McPherson C, Zarich S, Rudolph R. Diagnosis of myocardial infarction:
integration of serum markers and clinical descriptors using information theory.
Yale J Biol Med 1999; 72: 5-13.

Kaplan L.A.; Chapman J.F.; Bock J.L.; Santa Maria E.; Clejan S.; Huddleston D.J.; Reed R.G.;
Bernstein L.H.; Gillen-Goldstein J. Prediction of Respiratory Distress Syndrome using the Abbott FLM-II amniotic fluid assay. The National Academy of Clinical Biochemistry (NACB) Fetal Lung Maturity Assessment Project.  Clin Chim Acta 2002; 326(8): 61-68.

Bernstein LH, Qamar A, McPherson C, Zarich S. Evaluating a new graphical ordinal logit method (GOLDminer) in the diagnosis of myocardial infarction utilizing clinical features and laboratory
data. Yale J Biol Med 1999; 72:259-268.

Bernstein L, Bradley K, Zarich SA. GOLDmineR: Improving models for classifying patients with chest pain. Yale J Biol Med 2002; 75, pp. 183-198.

Ronald Raphael Coifman and Mladen Victor Wickerhauser. Adapted Waveform Analysis as a Tool for Modeling, Feature Extraction, and Denoising.
Optical Engineering 1994; 33(7):2170–2174.

R. Coifman and N. Saito. Constructions of local orthonormal bases for classification and regression. C. R. Acad. Sci. Paris, 319 Série I:191-196, 1994.

W Ruts, S De Deyne, E Ameel, W Vanpaemel,T Verbeemen, And G Storms. Dutch norm data for 13 semantic categoriesand 338 exemplars. Behavior Research Methods, Instruments,
& Computers 2004; 36 (3): 506–515.

De Deyne, S Verheyen, E Ameel, W Vanpaemel, MJ Dry, WVoorspoels, and G Storms.  Exemplar by feature applicability matrices and other Dutch normative data for semantic
concepts.
  Behavior Research Methods 2008; 40 (4): 1030-1048

Landauer, T. K., Ross, B. H., & Didner, R. S. (1979). Processing visually presented single words: A reaction time analysis [Technical memorandum].  Murray Hill, NJ: Bell Laboratories.
Lewandowsky , S. (1991).

Weed L. Automation of the problem oriented medical record. NCHSR Research Digest Series DHEW. 1977;(HRA)77-3177.

Naegele TA. Letter to the Editor. Amer J Crit Care 1993;2(5):433.

Sheila Nirenberg/Cornell and Chethan Pandarinath/Stanford, “Retinal prosthetic strategy with the capacity to restore normal vision,” Proceedings of the National Academy of Sciences.

Other related articles published in this Open Access Online Scientific Journal include the following:

http://pharmaceuticalintelligence.com/2012/08/13/the-automated-second-opinion-generator/

http://pharmaceuticalintelligence.com/2012/09/21/the-electronic-health-record-how-far-we-
have-travelled-and-where-is-journeys-end/

http://pharmaceuticalintelligence.com/2013/02/18/the-potential-contribution-of-
informatics-to-healthcare-is-more-than-currently-estimated/

http://pharmaceuticalintelligence.com/2013/05/04/cardiovascular-diseases-decision-support-
systems-for-disease-management-decision-making/?goback=%2Egde_4346921_member_239739196

http://pharmaceuticalintelligence.com/2012/08/13/demonstration-of-a-diagnostic-clinical-
laboratory-neural-network-agent-applied-to-three-laboratory-data-conditioning-problems/

http://pharmaceuticalintelligence.com/2012/12/17/big-data-in-genomic-medicine/

http://pharmaceuticalintelligence.com/2013/02/13/cracking-the-code-of-human-life-
the-birth-of-bioinformatics-and-computational-genomics/

http://pharmaceuticalintelligence.com/2013/04/28/genetics-of-conduction-disease-
atrioventricular-av-conduction-disease-block-gene-mutations-transcription-excitability-
and-energy-homeostasis/

http://pharmaceuticalintelligence.com/2012/12/10/identification-of-biomarkers-that-
are-related–to-the-actin-cytoskeleton/

http://pharmaceuticalintelligence.com/2012/08/14/regression-a-richly-textured-method-
for-comparison-and-classification-of-predictor-variables/

http://pharmaceuticalintelligence.com/2012/08/02/diagnostic-evaluation-of-sirs-by-
immature-granulocytes/

http://pharmaceuticalintelligence.com/2012/08/01/automated-inferential-diagnosis-
of-sirs-sepsis-septic-shock/

http://pharmaceuticalintelligence.com/2012/08/12/1815/

http://pharmaceuticalintelligence.com/2012/08/15/1946/

http://pharmaceuticalintelligence.com/2013/05/13/vinod-khosla-20-doctor-included-speculations-
musings-of-a-technology-optimist-or-technology-will-replace-80-of-what-doctors-do/

http://pharmaceuticalintelligence.com/2013/05/05/bioengineering-of-vascular-and-tissue-models/

The Heart: Vasculature Protection – A Concept-based Pharmacological Therapy including THYMOSIN
Aviva Lev-Ari, PhD, RN 2/28/2013
http://pharmaceuticalintelligence.com/2013/02/28/the-heart-vasculature-protection-a-concept-
based-pharmacological-therapy-including-thymosin/

FDA Pending 510(k) for The Latest Cardiovascular Imaging Technology
Aviva Lev-Ari, PhD, RN 1/28/2013
http://pharmaceuticalintelligence.com/2013/01/28/fda-pending-510k-for-the-latest-
cardiovascular-imaging-technology/

PCI Outcomes, Increased Ischemic Risk associated with Elevated Plasma Fibrinogen not
Platelet Reactivity    Aviva Lev-Ari, PhD, RN 1/10/2013
http://pharmaceuticalintelligence.com/2013/01/10/pci-outcomes-increased-ischemic-risk-
associated-with-elevated-plasma-fibrinogen-not-platelet-reactivity/

The ACUITY-PCI score: Will it Replace Four Established Risk Scores — TIMI, GRACE, SYNTAX,
and Clinical SYNTAX   Aviva Lev-Ari, PhD, RN 1/3/2013
http://pharmaceuticalintelligence.com/2013/01/03/the-acuity-pci-score-will-it-replace-four-
established-risk-scores-timi-grace-syntax-and-clinical-syntax/

Coronary artery disease in symptomatic patients referred for coronary angiography: Predicted by
Serum Protein Profiles    Aviva Lev-Ari, PhD, RN 12/29/2012
http://pharmaceuticalintelligence.com/2012/12/29/coronary-artery-disease-in-symptomatic-
patients-referred-for-coronary-angiography-predicted-by-serum-protein-profiles/

New Definition of MI Unveiled, Fractional Flow Reserve (FFR)CT for Tagging Ischemia
Aviva Lev-Ari, PhD, RN 8/27/2012
http://pharmaceuticalintelligence.com/2012/08/27/new-definition-of-mi-unveiled-
fractional-flow-reserve-ffrct-for-tagging-ischemia/

Herceptin Fab (antibody) - light and heavy chains

Herceptin Fab (antibody) – light and heavy chains (Photo credit: Wikipedia)

Personalized Medicine

Personalized Medicine (Photo credit: Wikipedia)

Diagnostic of pathogenic mutations. A diagnost...

Diagnostic of pathogenic mutations. A diagnostic complex is a dsDNA molecule resembling a short part of the gene of interest, in which one of the strands is intact (diagnostic signal) and the other bears the mutation to be detected (mutation signal). In case of a pathogenic mutation, the transcribed mRNA pairs to the mutation signal and triggers the release of the diagnostic signal (Photo credit: Wikipedia)

Read Full Post »

Pros and Cons of Drug Stabilizers for Arterial  Elasticity as an Alternative or Adjunct to Diuretics and Vasodilators in the Management of Hypertension.

Author, and Content Consultant to e-SERIES A: Cardiovascular Diseases: Justin Pearlman, MD, PhD, FACC

and

Article Curator: Aviva Lev-Ari, PhD, RN

This article presents the 2013 Thought Frontier on Hypertension and Vascular Compliance.

Conceptual development of the subject is presented in the following nine parts:

1.        Physiology of Circulation and Role of Arterial Elasticity

2.      Isolated Systolic Hypertension caused by Arterial Stiffening may be inadequately treated by Diuretics or Vasodilatation Antihypertensive Medications

3.         Physiology of Circulation and Compensatory Mechanism of Arterial Elasticity

4.         Vascular Compliance – The Potential for Novel Therapies

  • Novel Mechanism for Disease Etiology: Modulation of Nuclear and Cytoskeletal Actin Polymerization.
  • Genetic Therapy targeting Vascular Conductivity 
  • Regenerative Medicine for Vasculature Function Protection

5.        In addition to curtailing high pressures, stabilizing BP variability is a potential target for management of hypertension

6.        Mathematical Modeling: Arterial stiffening  explains much of primary hypertension

7.         Classification of Blood Pressure and Hypertensive Treatment Best Practice of Care in the US

8.         Genetic Risk for High Blood Pressure

9.         Is it Hypertension or Physical Inactivity: Cardiovascular Risk and Mortality – New results in 3/2013.

Summary By Justin D. Pearlman MD ME PhD MA FACC

1.       Physiology of Circulation and Role of Arterial Elasticity

  • Simplistically, high blood pressure stems from too much volume (salt water) for the vascular space, or conversely, too little space for the volume. Biological signals, such as endothelin, hypoxia, acidosis, nitric oxide, can modify vascular volume by constricting muscles in blood vessel walls. Less simplistically the physics of circulation are governed by numerous factors, with essentials detailed below.
  • The vascular space has two major circuits: pulmonary (lungs) and systemic (body).
  • Compliance (C)  relates change in volume (ΔV) to change in pressure (ΔP) as a measure of the strength of elasticity, where elasticity summarizes the intrinsic forces that  return to original shape after deformation: C = ΔV/ΔP . Those values can be estimated by ultrasound imaging with Doppler blood velocity estimation, by MRI, or invasively. Related properties can also be measured, such as wave propagation time or fractional flow reserve.
  • The vascular system is dynamic, with frequency components and reactive elements. The fundamental frequency is governed by the heart rate delivering a stroke volume forward into the vasculature; a heart rate of 60/minute corresponds to the frequency of 1 Hertz (1 cycle/second). The pressure rise due to the ejection of stroke volume is called the pulse pressure.
  • Numerous factors affect blood flow, including blood composition (affected by anemia or blood dilution), leakiness of vessels, elasticity, wave propagation, streamlines, viscosity, osmotic pressure (affected by protein deficiency and other factors),
  • In a static system, the driving force relates linearly flow by way of resistance (R  in units of dyn·s·cm−5): V=IR (Ohm’s law).
    • Pulmonary:\frac {80 \cdot (mean\ pulmonary\ arterial\ pressure - mean \ pulmonary \ artery \ wedge \ pressure)} {cardiac\ output}
    • Systemic:\frac {80 \cdot (mean\ arterial\ pressure - mean \ right \ atrial \ pressure)} {cardiac\ output}
  • In a dynamic, reactive system, the relation between the driving potential (pressure gradient), and current (blood flow) is governed by a differential equation. However, use of complex numbers and exponentials recovers simplicity similar to Ohm’s law:
    • Variables take the form Ae^{st}, where t is time, s is a complex parameter, and A is a complex scalar. Complex values simply mean two dimensional, e.g., magnitude (as in resistance) plus phase shift (to account for reactive components).
    • Complex version of Ohm’s law: \boldsymbol{V} = \boldsymbol{I} \cdot \boldsymbol{Z} where V and I are the complex scalars in the voltage and current respectively and Z is the complex impedance.
    • Frequency dependent “resistance” is captured by the term impedance.
  • Breathing in increases the return of blood to the heart, adding to pulse variation.
  • Dynamic elastance  (Eadyn)  relates volume variation (VVS) to pressure variation (PPV): Eadyn=PPV/SVV
    • PPV(%) = 100% × (PPmax − PPmin)/[(PPmax + PPmin)/2)]
      • where PPmax and PPmin are the maximum and minimum pulse pressures determined during a single  respiratory cycle
    • SVV(%) = 100% × [(SVmax − SVmin)/SVmean]
      • where SVmax and SVmin  are the maximum and minimum standard deviation of arterial pressure about the mean arterial pressure during a single respiratory cycle
  • The nervous system provides both stimulants and inhibitors (sympathetic and vagal nerves) to regulate blood vessel wall muscle tone and also heart rate. Many medications, and anesthetic agents in particular, reduce those responses to stimuli, so the vessels dilate, vascular impedance lowers, pressures drop, and autoregulation is impaired.
  • Diuretics aim to decrease volume of circulating fluid, vasodilators aim to increase the vascular space, and elasticity treatments will aim to preserve or improve the ability to accommodate changes in volume of fluid.
    • Vessel dilation near the skin promotes heat loss.
  • Vascular elasticity is impaired by atherosclerosis, menopause, and endothelial dysfunction (impaired nitric oxide signals  response, impaired endothelin response).
  • Elastance in a cyclic pressure system of systole-diastole (contraction-dilation) presents impedance as a pulsatile load on the heart. Inotropy describes the generation of pressure by cardiac contraction, lusiotropy the compliance of the heart to accept filling with minimal back pressure to the lungs. Chronic exposure to elevated vascular impedance leads to impairment of lusiotropy (diastolic failure, stiff heart) and inotropy (systolic failure, weak heart).

2.      Isolated Systolic Hypertension caused by Arterial Stiffening may be inadequately treated by Diuretics or Vasodilatation Antihypertensive Medications

3. Physiology of Circulation and Compensatory Mechanism of Arterial Elasticity

Antihypertensive agents have focused on the following approaches:

  1. The most common prescriptions, a mild diuretic, hydrochlorothiazide (HCTZ), is known to improve blood vessel compliance by reducing cell turgor, which explains why its full onset of benefit as well as its slow offset when stopped can take more than one month.
  2. Chlorthalidone  – Some evidence suggests that chlorthalidone may be superior to hydrochlorothiazide for the treatment of hypertension. However, a recent study concluded: chlorthalidone in older adults was not associated with fewer adverse cardiovascular events or deaths than hydrochlorothiazide. However, it was associated with a greater incidence of electrolyte abnormalities, particularly hypokalemia.
  • Increased vascular space (vasodilation)

    • Alternatively, the pressure can be lowered by increasing the vascular space for a given vascular volume. Examples of mediators for arterial tone (degree of dilation) include nitric oxide, prostacyclin and endothelin.


Class

Description

Hyperpolarization mediated (Calcium channel blocker) Changes in the resting membrane potential of thecell affects the level of intracellular calciumthrough modulation of voltage sensitive calcium channelsin the plasma membrane.
cAMP mediated Adrenergic stimulation results in elevated levelsof cAMP and protein kinase A, which results inincreasing calcium removal from the cytoplasm.
cGMP mediated (Nitrovasodilator) Through stimulation of protein kinase G.Until 2002, the enzyme for this conversion wasdiscovered to be mitochondrial aldehyde dehydrogenase.Proc. Natl. Acad. Sci. USA 102 (34): 12159–12164. doi:10.1073/pnas.0503723102http://www.pnas.org/content/102/34/12159.long

Class

Example

Hyperpolarization mediated (Calcium channel blocker) adenosineamlodipine (Norvasc),diltiazem (Cardizem,Dilacor XR) andnifedipine (Adalat, Procardia).
cAMP mediated prostacyclin
cGMP mediated (Nitrovasodilator) nitric oxide
  • Reduced pulsatile force (beta blockers)

These work by blocking certain nerve and hormonal signals to the heart and blood vessels, thus lowering blood pressure. Frequently prescribed beta blockers include

  • metoprolol (Lopressor, Toprol XL)
  • carvedilol (Coreg)
  • nadolol (Corgard)
  • penbutolol (Levatol).
  • Metabolized nebivolol increases vascular NO production, involves endothelial ß2-adrenergic receptor ligation, with a subsequent rise in endothelial free [Ca2+]i and endothelial NO synthase–dependent NO production
  • Angiotensin-converting enzyme (ACE) inhibitors

These allow blood vessels to widen by preventing the hormone angiotensin from affecting blood vessels. Frequently prescribed ACE inhibitors include captopril (Capoten), lisinopril (Prinivil, Zestril) and ramipril (Altace).

  • Angiotensin II receptor blockers

These help blood vessels relax by blocking the action of angiotensin. Frequently prescribed angiotensin II receptor blockers include losartan (Cozaar), olmesartan (Benicar) and valsartan (Diovan).
Another very commonly prescribed drug class of medication counteracts hardening of arteries.

Atheroma lipids have enzyme systems that explicitly disassemble cholesterol esters and reconstruct them inside blood vessel walls,e.g.,  Anacetrapib, Genetic variants that improve cholesterol levels are stimulating development of additional medications.

We can propose that atheroma build up in arterial blood vessel walls constitutes a maladaptive defense against aneurysm and risk of vessel rupture from hypertension.

Arguably, HMG-CoA reductase inhibitors,  statin therapy is a second example of a medication that helps protect vascular elasticity, both by its lipid effects and its anti-inflammatory effects.

The best-selling statin is atorvastatin, marketed as Lipitor (manufactured by Pfizer) and Torvast. By 2003, atorvastatin became the best-selling pharmaceutical in history,[4] with Pfizer reporting sales of US$12.4 billion in 2008.[5] As of 2010, a number of statinsare on the market: atorvastatin (Lipitor and Torvast), fluvastatin (Lescol), lovastatin (Mevacor, Altocor, Altoprev), pitavastatin(Livalo, Pitava), pravastatin (Pravachol, Selektine, Lipostat), rosuvastatin (Crestor) and simvastatin (Zocor, Lipex).[6] Several combination preparations of a statin and another agent, such as ezetimibe/simvastatin, are also available.

References for Statins from:

http://en.wikipedia.org/wiki/Statin

Clinical Considerations of Statin Therapy’s manifold effects, in

http://pharmaceuticalintelligence.com/2012/10/08/statins-nonlipid-effects-on-vascular-endothelium-through-enos-activation/

Compensatory Effects in the Physiology of Circulation

Before declaring vessel elasticity a new and highly desirable treatment target, consider that it is not firmly established that hardening of arteries (loss of elasticity) is entirely maladaptive.

In parallel with any focus on increasing vascular elasticity or compliance, each of the issues discussed, below merits scrutiny and investigation.

Cardiac Circulation Dynamics

Endothelium morphology, rheological properties of intra vasculature fluid dynamics and blood viscosity provided explanation for shear stress of vessels under arterial pressure

http://pharmaceuticalintelligence.com/2012/11/28/special-considerations-in-blood-lipoproteins-viscosity-assessment-and-treatment/

and

http://pharmaceuticalintelligence.com/2012/11/28/what-is-the-role-of-plasma-viscosity-in-hemostasis-and-vascular-disease-risk/

Aging and Vasculature Diminished Elasticity

While among other reasons for Hypertension increasing prevalence with aging, arterial stiffening is one.

Yet, stiffer vessels are more efficient at transmitting pressure to distal targets. With aging, muscle mass diminishes markedly and the contribution to circulation from skeletal muscle tissue compressions combined with competent venous valves fades.

http://pharmaceuticalintelligence.com/2012/08/27/endothelial-dysfunction-diminished-availability-of-cepcs-increasing-cvd-risk-for-macrovascular-disease-therapeutic-potential-of-cepcs/

and

http://pharmaceuticalintelligence.com/2012/10/19/clinical-trials-results-for-endothelin-system-pathophysiological-role-in-chronic-heart-failure-acute-coronary-syndromes-and-mi-marker-of-disease-severity-or-genetic-determination/

and

http://pharmaceuticalintelligence.com/2012/11/13/peroxisome-proliferator-activated-receptor-ppar-gamma-receptors-activation-pparγ-transrepression-for-angiogenesis-in-cardiovascular-disease-and-pparγ-transactivation-for-treatment-of-dia/

Aging and Myocardial Diminished Contractility and Ejection Fraction

With aging heart contractility diminishes. These issues can cause under perfusion of tissues, inadequate nutrient blood delivery (ischemia), lactic acidosis, tissue dysfunction and multi-organ failure. Hardened arteries may compensate. Thus, pharmacotherapy to increase Arterial Elasticity may be counterindicated for patients with mild to progressive CHF.

http://pharmaceuticalintelligence.com/2013/05/05/bioengineering-of-vascular-and-tissue-models/

and

http://pharmaceuticalintelligence.com/2012/10/20/nitric-oxide-and-sepsis-hemodynamic-collapse-and-the-search-for-therapeutic-options/

and

http://pharmaceuticalintelligence.com/2012/10/17/chronic-heart-failure-personalized-medicine-two-gene-test-predicts-response-to-beta-blocker-bucindolol/
Our biosystems are highly interdependent, and we cannot leap to conclusions without careful thorough evidence. Increasing arterial elastance will lower vascular impedance and change the frequency components of our pulsatile perfusion system.

MOST comprehensive review of the Human Cardiac Conduction System presented to date:

http://pharmaceuticalintelligence.com/2013/04/28/genetics-of-conduction-disease-atrioventricular-av-conduction-disease-block-gene-mutations-transcription-excitability-and-energy-homeostasis/

Diminished contractility will increase the amount of energy needed to maintain circulation. It will change efficiency dramatically – consider the difference between periodically pushing someone sitting on a swing at the resonance frequency if the pendulum versus significantly off resonance.

http://pharmaceuticalintelligence.com/2013/04/14/mitochondrial-metabolism-and-cardiac-function/

and

http://pharmaceuticalintelligence.com/2012/10/28/mitochondrial-damage-and-repair-under-oxidative-stress/

Increased Arterial Elasticity – Potential Risk to Myocardium

The hypothesis that we should focus on cellular therapies to increase vascular compliance may decrease the circulation efficiency and result in worsening of cardiac right ventricular morphology and development of Dilated cardiomyopathy and hypertrophic cardiomyopathy (muscle thickening and diastolic failure), an undesirable outcome resulting from an attempt to treat the hypertension.

4. Vascular Compliance – The Potential of Noval Therapies

  • Novel Mechanism for Disease Etiology for the Cardiac Phenotype: Modulation of Nuclear and Cytoskeletal Actin Polymerization.

Lamin A/C and emerin regulate MKL1–SRF activity by modulating actin dynamics

Chin Yee Ho,

Diana E. Jaalouk,

Maria K. Vartiainen

& Jan Lammerding

Nature (2013) doi:10.1038/nature12105

Published online 05 May 2013

Affiliations

Cornell University, Weill Institute for Cell and Molecular Biology/Department of Biomedical Engineering, Ithaca, New York 14853, USA

Chin Yee Ho &

Jan Lammerding

Brigham and Women’s Hospital/Harvard Medical School, Department of Medicine, Boston 02115, Massachusetts, USA

Chin Yee Ho,

Diana E. Jaalouk &

Jan Lammerding

Institute of Biotechnology, University of Helsinki, 00014 Helsinki, Finland

Maria K. Vartiainen

Present address: American University of Beirut, Department of Biology, Beirut 1107 2020, Lebanon.

Diana E. Jaalouk

Contributions

C.Y.H., D.E.J. and J.L. conceived and designed the overall project, with valuable help from M.K.V. C.Y.H. and D.E.J. performed the experiments. C.Y.H., D.E.J. and J.L. analysed data. C.Y.H. and J.L. wrote the paper.

Corresponding author Jan Lammerding

Laminopathies, caused by mutations in the LMNA gene encoding the nuclear envelope proteins lamins A and C, represent a diverse group of diseases that include Emery–Dreifuss muscular dystrophy (EDMD), dilated cardiomyopathy (DCM), limb-girdle muscular dystrophy, and Hutchison–Gilford progeria syndrome1. Most LMNA mutations affect skeletal and cardiac muscle by mechanisms that remain incompletely understood. Loss of structural function and altered interaction of mutant lamins with (tissue-specific) transcription factors have been proposed to explain the tissue-specific phenotypes1. Here we report in mice that lamin-A/C-deficient (Lmna−/−) and LmnaN195K/N195K mutant cells have impaired nuclear translocation and downstream signalling of the mechanosensitive transcription factor megakaryoblastic leukaemia 1 (MKL1), a myocardin family member that is pivotal in cardiac development and function2. Altered nucleo-cytoplasmic shuttling of MKL1 was caused by altered actin dynamics in Lmna−/− and LmnaN195K/N195K mutant cells. Ectopic expression of the nuclear envelope protein emerin, which is mislocalized in Lmnamutant cells and also linked to EDMD and DCM, restored MKL1 nuclear translocation and rescued actin dynamics in mutant cells. These findings present a novel mechanism that could provide insight into the disease aetiology for the cardiac phenotype in many laminopathies, whereby lamin A/C and emerin regulate gene expression through modulation of nuclear and cytoskeletal actin polymerization.

 http://www.nature.com/nature/journal/vaop/ncurrent/full/nature12105.html

  • Genetic Therapy to Conductivity Disease

http://pharmaceuticalintelligence.com/2012/10/01/ngs-cardiovascular-diagnostics-long-qt-genes-sequenced-a-potential-replacement-for-molecular-pathology/

  • Regenerative Medicine for Vasculature Function Protection

http://pharmaceuticalintelligence.com/2012/08/29/positioning-a-therapeutic-concept-for-endogenous-augmentation-of-cepcs-therapeutic-indications-for-macrovascular-disease-coronary-cerebrovascular-and-peripheral/

and

http://pharmaceuticalintelligence.com/2012/08/28/cardiovascular-outcomes-function-of-circulating-endothelial-progenitor-cells-cepcs-exploring-pharmaco-therapy-targeted-at-endogenous-augmentation-of-cepcs/

and

http://pharmaceuticalintelligence.com/2013/02/28/the-heart-vasculature-protection-a-concept-based-pharmacological-therapy-including-thymosin/

5. Stabilizing BP Variability is the next Big Target in Hypertension Management

Hypertension caused by Arterial Stiffening is Ineffectively Treated by Diuretics and Vasodilatation Antihypertensives

Barcelona, Spain – An aging population grappling with rising rates of hypertension and other cardiometabolic risk factors should prompt an overhaul of how hypertension is diagnosed and monitored and should spur development of drugs with entirely new mechanisms of action, one expert says. Speaking here at the 2013 International Conference on Prehypertension and Cardiometabolic Syndrome, meeting cochair Dr Reuven Zimlichman (Tel Aviv University, Israel) argued that the definitions of hypertension, as well as the risk-factor tables used to guide treatment, are no longer appropriate for a growing number of patients.

Most antihypertensives today work by producing vasodilation or decreasing blood volume and so are ineffective treatments in ISH patients. In the future, he predicts, “we will have to start looking for a totally different medication that will aim to improve or at least to stabilize arterial elasticity: medication that might affect factors that determine the stiffness of the arteries, like collagen, like fibroblasts. Those are not the aim of any group of antihypertensive medications today.”

Zimlichman believes existing databases could be used to develop algorithms that take this progression of disease into account, in order to better guide hypertension management. He also points out that new ambulatory blood-pressure-monitoring devices also measure arterial elasticity. “Unquestionably, these will improve our ability to diagnose both the status of the arteries and the changes of the arteries with time as a result of our treatment. So if we treat the patient and we see no improvement in arterial elasticity, or the patient is worse, something is wrong, something is not working—either the patient is not taking the medication, or our choice of medication is not appropriate, or the dose is insufficient, etc.”

http://www.theheart.org/article/1502067.do

Oslo, Norway – New research that is only just starting to be digested by the hypertension community indicates that visit-to-visit variability in blood-pressure readings will likely become another way of looking for “at-risk” hypertensive patients and in fact is likely to be more reliable as an indicator of cardiovascular risk than the currently used mean BP.

The Goal of Stabilizing BP variability 

June 29, 2010  

Discussing the importance of this issue for guidelines and clinical practice, Dr Tony Heagerty (University of Manchester, UK) told the recent European Society of Hypertension (ESH) European Meeting on Hypertension 2010: “We are poking around in the dark, offering treatment blankly across a large community, and probably treating a lot of people who don’t need to be treated, while not necessarily treating the highest-risk patients. We should stop being reassured by ‘occasional’ normal BPs. The whole game now is, can we improve the identification of our ‘at-risk’ individuals?”

Heagerty was speaking at a special plenary session on late-breaking research discussing BP variability as a risk factor. This issue has emerged following new analyses reported at the ACC meeting and published in a number of papers in the Lancet and Lancet Neurology earlier this year, which showed that variability in blood pressure is a much stronger determinant of both stroke and coronary disease outcome than average blood pressure.

http://www.theheart.org/article/1093553.do

Three years later, 2/1/2013, Zimlichman also argued that definitions of essential and secondary hypertension have changed very little over the past few decades and have typically only been tweaked up or down related to other CV risk factors. Diastolic hypertension has been the primary goal of treatment, and treatment goals have not adequately taken patient age into account (in whom arterial stiffening plays a larger role), and they have typically relied too heavily on threshold cutoffs, rather than the “linear progression” of risk factors and their impact on organ damage.

6. Mathematical Modeling: Arterial stiffening provides sufficient explanation for primary hypertension

Klas H. Pettersen, Scott M. Bugenhagen, Javaid Nauman, Daniel A. Beard, Stig W. Omholt

(Submitted on 3 May 2013 (v1), last revised 6 May 2013 (this version, v2))

Hypertension is one of the most common age-related chronic diseases and by predisposing individuals for heart failure, stroke and kidney disease, it is a major source of morbidity and mortality. Its etiology remains enigmatic despite intense research efforts over many decades. By use of empirically well-constrained computer models describing the coupled function of the baroreceptor reflex and mechanics of the circulatory system, we demonstrate quantitatively that arterial stiffening seems sufficient to explain age-related emergence of hypertension. Specifically, the empirically observed chronic changes in pulse pressure with age, and the impaired capacity of hypertensive individuals to regulate short-term changes in blood pressure, arise as emergent properties of the integrated system. Results are consistent with available experimental data from chemical and surgical manipulation of the cardio-vascular system. In contrast to widely held opinions, the results suggest that primary hypertension can be attributed to a mechanogenic etiology without challenging current conceptions of renal and sympathetic nervous system function. The results support the view that a major target for treating chronic hypertension in the elderly is the reestablishment of a proper baroreflex response.

Klas H. Pettersen1, Scott M. Bugenhagen2, Javaid Nauman3, Daniel A. Beard2 & Stig W. Omholt3

1Department of Mathematical and Technological Sciences, Norwegian University of Life Science, Norway

2Department of Physiology, Medical College of Wisconsin, Milwaukee, Wisconsin, USA

3NTNU Norwegian University of Science and Technology, Department of Circulation and Medical Imaging, Cardiac Exercise Research Group, Trondheim, Norway

Correspondence should be addressed to: KHP (klas.pettersen@gmail.com)

Keywords: hypertension, mechanogenic, baroreceptor signaling, cardiovascular model, arterial stiffening

Author contributions: K.H.P. and S.W.O. designed the study. K.H.P. constructed the

integrated model and performed the numerical experiments with contributions from

D.A.B. and S.M.B.. J.N. extracted and compiled empirical test data from the HUNT2

Survey. S.W.O, K.H.P. and D.A.B. wrote the paper.

http://arxiv.org/abs/1305.0727v2

http://arxiv.org/pdf/1305.0727v2.pdf


7. Classification of Blood Pressure and Hypertensive Treatment:

Best Practice of Care in the US

8. Genetic Risk for High Blood Pressure

Hypertension.2013; 61: 931doi: 10.1161/​HYP.0b013e31829399b2

Blood Pressure Single-Nucleotide Polymorphisms and Coronary Artery Sisease (page 995)

Blood pressure (BP) is considered a major cardiovascular risk factor that is influenced by multiple genetic and environmental factors. However, the precise genetic underpinning influencing interindividual BP variation is not well characterized; and it is unclear whether BP-associated genetic variants also predispose to clinically apparent cardiovascular disease. Such an association of BP-related variants with cardiovascular disease would strengthen the concept of BP as a causal risk factor for cardiovascular disease. In this issue of Hypertension, analyses within the Coronary ARtery DIsease Genome-Wide Replication And Meta-Analysis consortium indicate that common genetic variants associated with BP in the population, indeed, contribute to the susceptibility for coronary artery disease (CAD). Lieb et al tested 30 single-nucleotide polymorphisms—that based on prior studies were known to affect BP—for their association with CAD. In total, data from 22 233 CAD cases and 64 762 controls were analyzed. The vast majority (88%) of BP-related single-nucleotide polymorphisms were also shown to increase the risk of CAD (as defined by an odds ratio for CAD >1; Figure). On average, each of the multiple BP-raising alleles was associated with a 3% (95% confidence interval, 1.8%–4.3%) risk increase for CAD.

Masked Hypertension in Diabetes Mellitus (page 964)

The first important finding in the IDACO study of masked hypertension (MH) in the population with diabetes mellitus and non–diabetes mellitus was that antihypertensive treatment converted some sustained hypertensives into sustained normotensives; this resulted in an increased cardiovascular disease risk in the treated versus untreated normotensive comparator group (Figure). Not surprisingly, normalization of blood pressure (BP) with treatment did not eliminate the lifetime cardiovascular disease burden associated with prior elevated BP nor did it correct other cardiometabolic risk factors that clustered with the hypertensive state.

The second important IDACO finding was that treatment increased the prevalence of MH by decreasing conventional BP versus daytime ambulatory BP (ABP) by a ratio of ≈3 to 2. The clinical implication of increased prevalence of MH with therapy in the population of both diabetes mellitus and non–diabetes mellitus was that these subjects did not receive sufficient antihypertensive therapy to convert MH into normalized ABP (ie, treated, normalized ABP being the gold standard for minimizing cardiovascular disease risk). Indeed, there is a transformation-continuum from sustained hypertension to MH and finally to sustained normotension with increasing antihypertensive therapy. These IDACO findings strongly suggest that many physicians mistakenly have their primary focus on normalizing in-office rather than out-of-office home BP and/or 24-hour ABP values and this results in an increased prevalence of MH. However, what constitutes optimal normalized ABP will remain empirical until established in randomized controlled trials.

Genetic Risk Score for Blood Pressure (page 987)

Elevated blood pressure (BP) is a strong, independent, and modifiable risk factor for stroke and heart disease. BP is a heritable trait, and genome-wide association studies have identified several genetic loci that are associated with systolic BP, diastolic BP, or both. Although the variants have modest effects on BP, typically 0.5 to 1.0 mm Hg, their presence may act over the entire life course and, therefore, lead to substantial increase in risk of cardiovascular disease (CVD). However, the independent impact of these variants on CVD risk has not been established in a prospective setting. Havulinna et al genotyped 32 common single-nucleotide polymorphisms in several Finnish cohorts, with up to 32 669 individuals after exclusion of prevalent CVD cases. The median follow-up was 9.8 years, during which 2295 incident CVD events occurred. Genetic risk scores were created for systolic BP and diastolic BP by multiplying the risk allele count of each single-nucleotide polymorphism by the effect size estimated in published genome-wide association studies on BP traits. The GRSs were strongly associated with baseline systolic BP, diastolic BP, and hypertension (all P<10–62). Hazard ratios for incident CVD increased roughly linearly by quintile of systolic BP or diastolic BP GRS (Figure). GRSs remained significant predictors of CVD risk after adjustment for traditional risk factors, even including BP and use of antihypertensive medication. These findings are consistent with a lifelong effect of these variants on BP and CVD risk.

Related Articles on Genetics and Blood Pressure

Genetic Predisposition to Higher Blood Pressure Increases Coronary Artery Disease Risk

  • Wolfgang Lieb,
  • Henning Jansen,
  • Christina Loley,
  • Michael J. Pencina,
  • Christopher P. Nelson,
  • Christopher Newton-Cheh,
  • Sekar Kathiresan,
  • Muredach P. Reilly,
  • Themistocles L. Assimes,
  • Eric Boerwinkle,
  • Alistair S. Hall,
  • Christian Hengstenberg,
  • Reijo Laaksonen,
  • Ruth McPherson,
  • Unnur Thorsteinsdottir,
  • Andreas Ziegler,
  • Annette Peters,
  • John R. Thompson,
  • Inke R. König,
  • Jeanette Erdmann,
  • Nilesh J. Samani,
  • Ramachandran S. Vasan,
  • andHeribert Schunkert
  • , on behalf of CARDIoGRAM

Hypertension. 2013;61:995-1001, published online before print March 11 2013,doi:10.1161/HYPERTENSIONAHA.111.00275

Masked Hypertension in Diabetes Mellitus: Treatment Implications for Clinical Practice

  • Stanley S. Franklin,
  • Lutgarde Thijs,
  • Yan Li,
  • Tine W. Hansen,
  • José Boggia,
  • Yanping Liu,
  • Kei Asayama,
  • Kristina Björklund-Bodegård,
  • Takayoshi Ohkubo,
  • Jørgen Jeppesen,
  • Christian Torp-Pedersen,
  • Eamon Dolan,
  • Tatiana Kuznetsova,
  • Katarzyna Stolarz-Skrzypek,
  • Valérie Tikhonoff,
  • Sofia Malyutina,
  • Edoardo Casiglia,
  • Yuri Nikitin,
  • Lars Lind,
  • Edgardo Sandoya,
  • Kalina Kawecka-Jaszcz,
  • Jan Filipovský,
  • Yutaka Imai,
  • Jiguang Wang,
  • Hans Ibsen,
  • Eoin O’Brien,
  • and Jan A. Staessen
  • , on behalf of the International Database on Ambulatory blood pressure in relation to Cardiovascular Outcomes (IDACO) Investigators

Hypertension. 2013;61:964-971, published online before print March 11 2013,doi:10.1161/HYPERTENSIONAHA.111.00289

A Blood Pressure Genetic Risk Score Is a Significant Predictor of Incident Cardiovascular Events in 32 669 Individuals

  • Aki S. Havulinna,
  • Johannes Kettunen,
  • Olavi Ukkola,
  • Clive Osmond,
  • Johan G. Eriksson,
  • Y. Antero Kesäniemi,
  • Antti Jula,
  • Leena Peltonen,
  • Kimmo Kontula,
  • Veikko Salomaa,
  • and Christopher Newton-Cheh

Hypertension. 2013;61:987-994, published online before print March 18 2013,doi:10.1161/HYPERTENSIONAHA.111.00649

9. Is it Hypertension or Physical Inactivity: Cardiovascular Risk and Mortality – New results in 3/2013.

Heart doi:10.1136/heartjnl-2012-303461

  • Epidemiology
  • Original article

Estimating the effect of long-term physical activity on cardiovascular disease and mortality: evidence from the Framingham Heart Study

  1. Susan M Shortreed1,2,
  2. Anna Peeters1,3,
  3. Andrew B Forbes1

+Author Affiliations


  1. 1Department of Epidemiology and Preventive Medicine, Monash University, Melbourne, Australia

  2. 2Biostatistics Unit, Group Health Research Institute, Seattle, Washington, USA

  3. 3Obesity and Population Health Unit, Baker IDI Heart and Diabetes Institute, Melbourne, Australia

Correspondence toDr Susan M Shortreed, Biostatistics Unit, Group Health Research Institute, 1730 Minor Avenue, Suite 1600, Seattle, WA 98101, USA; shortreed.s@ghc.org

  • Published Online First 8 March 2013

Abstract

Objective In the majority of studies, the effect of physical activity (PA) on cardiovascular disease (CVD) and mortality is estimated at a single time point. The impact of long-term PA is likely to differ. Our study objective was to estimate the effect of long-term adult-life PA compared with long-term inactivity on the risk of incident CVD, all-cause mortality and CVD-attributable mortality.

Design Observational cohort study.

Setting Framingham, MA, USA.

Patients 4729 Framingham Heart Study participants who were alive and CVD-free in 1956.

Exposures PA was measured at three visits over 30 years along with a variety of risk factors for CVD. Cumulative PA was defined as long-term active versus long-term inactive.

Main outcome measures Incident CVD, all-cause mortality and CVD-attributable mortality.

Results During 40 years of follow-up there were 2594 cases of incident CVD, 1313 CVD-attributable deaths and 3521 deaths. Compared with long-term physical inactivity, the rate ratio of long-term PA was 0.95 (95% CI 0.84 to 1.07) for CVD, 0.81 (0.71 to 0.93) for all-cause mortality and 0.83 (0.72 to 0.97) for CVD-attributable mortality. Assessment of effect modification by sex suggests greater protective effect of long-term PA on CVD incidence (p value for interaction=0.004) in men (0.79 (0.66 to 0.93)) than in women (1.15 (0.97 to 1.37)).

Conclusions

  • Cumulative long-term PA has a protective effect on incidence of all-cause and CVD-attributable mortality compared with long-term physical inactivity.
  • In men, but not women, long-term PA also appears to have a protective effect on incidence of CVD.

Summary – PENDING

REFERENCES
1. Kannel WB, Gordan T (1978) Evaluation of cardiovascular risk in the elderly: the Framingham study. Bull N Y Acad Med 54:573–591.
2. Franklin SS, Khan SA, Wong ND, Larson MG, Levy D (1999) Is pulse pressure useful in predicting risk for coronary heart disease?: The Framingham Heart Study. Circulation 100:354–360.
3. Mitchell GF et al. (2010) Hemodynamic Correlates of Blood Pressure Across the Adult Age Spectrum: Noninvasive Evaluation in the Framingham Heart Study. Circulation 122:1379–1386.
4. Khattar RS, Swales JD, Dore C, Senior R, Lahiri A (2001) Effect of Aging on the Prognostic Significance of Ambulatory Systolic, Diastolic, and Pulse Pressure in Essential Hypertension. Circulation 104:783–789.
5. Franklin SS et al. (1997) Hemodynamic patterns of age-related changes in blood pressure: the Framingham Heart Study. Circulation 96:308.
6. Guyenet PG (2006) The sympathetic control of blood pressure. Nat Rev Neurosci 7:335–346.
7. Monahan KD (2007) Effect of aging on baroreflex function in humans. Am J Physiol Regul Integr Comp Physiol 293:R3–R12.
8. Zieman SJ (2005) Mechanisms, Pathophysiology, and Therapy of Arterial Stiffness. Arterioscler Thromb Vasc Biol 25:932–943.
9. McVeigh GE, Bank AJ, Cohn JN (2007) Arterial compliance. Cardiovasc Med:1811–1831.
10. Guyton AC (1991) Blood pressure control–special role of the kidneys and body fluids. Science 252:1813–1816.
11. Smith BW, Chase JG, Nokes RI, Shaw GM, Wake G (2004) Minimal haemodynamic system model including ventricular interaction and valve dynamics. Med Eng Phys 26:131–139.
12. Smith BW, Geoffrey Chase J, Shaw GM, Nokes RI (2005) Experimentally verified minimal cardiovascular system model for rapid diagnostic assistance. Control Eng Pract 13:1183–1193.13. Bugenhagen SM, Cowley AW, Beard DA (2010) Identifying physiological origins of baroreflex dysfunction in salt-sensitive hypertension in the Dahl SS rat. Physiol Genomics 42:23–41.14. Beard DA et al. (2012) Multiscale Modeling and Data Integration in the Virtual Physiological Rat Project. Ann Biomed Eng.15. King AL (1946) Pressure-Volume Relation for Cylindrical Tubes with Elastomeric Walls: The Human Aorta. J Appl Phys 17:501.16. Dayan P, Abbott LF (2001) Theoretical Neuroscience: Computational and Mathematical Modeling of Neural Systems (Computational Neuroscience) (The MIT Press). 1st Ed.17. Andresen MC, Krauhs JM, Brown AM (1978) Relationship of aortic wall and baroreceptor properties during development in normotensive and spontaneously hypertensive rats. Circ Res 43:728–738.18. Hallock P, Benson IC (1937) Studies on the elastic properties of human isolated aorta. J Clin Invest 16:595–602.19. Coffman TM (2011) Under pressure: the search for the essential mechanisms of hypertension. Nat Med 17:1402–1409.20. Proctor DN et al. (1998) Influence of age and gender on cardiac output-V O 2 relationships during submaximal cycle ergometry. J Appl Physiol 84:599–605.21. Fagard R, Thijs L, AMERY A (1993) Age and the Hemodynamic Response to Posture and Exercise. Am J Geriatr Cardiol 2:23–40.22. Stratton JR, Levy WC, Cerqueira MD, Schwartz RS, Abrass IB (1994) Cardiovascular responses to exercise. Effects of aging and exercise training in healthy men. Circulation 89:1648–1655.23. Holmen J et al. (2003) The Nord-Trøndelag Health Study 1995–97 (HUNT 2): objectives, contents, methods and participation. Norsk epidemiologi 13:19–32.24. Chobanian AV et al. (2003) The Seventh Report of the Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure: the JNC 7 report. JAMA 289:2560–2572.25. Cowley AW, LIARD JF, Guyton AC (1973) Role of the Baroreceptor Reflex in Daily Control of Arterial Blood Pressure and Other Variables in Dogs. Circ Res 32:564–576.26. Schreihofer AM, Sved AF (1992) Nucleus tractus solitarius and control of blood pressure in chronic sinoaortic denervated rats. Am J Physiol 263:R258–66.27. Ito S, Sved AF (1997) Influence of GABA in the nucleus of the solitary tract on blood pressure in baroreceptor-denervated rats. Am J Physiol Regul Integr Comp Physiol 273:R1657–R1662.28. Thrasher TN (2004) Baroreceptors, baroreceptor unloading, and the long-term control of blood pressure. Am J Physiol Regul Integr Comp Physiol 288:R819– R827.29. Monahan KD et al. (2001) Age-associated changes in cardiovagal baroreflex sensitivity are related to central arterial compliance. Am J Physiol Heart Circ Physiol 281:H284–H289.30. Malpas S (2009) Editorial comment: Montani versus Osborn exchange of views. Experimental Physiology 94:381–382.31. Mori T et al. (2008) High Perfusion Pressure Accelerates Renal Injury in Salt-Sensitive Hypertension. Journal of the American Society of Nephrology 19:1472–1482.32. Beard DA, Mescam M (2012) Mechanisms of pressure-diuresis and pressurenatriuresis in Dahl salt-resistant and Dahl salt-sensitive rats. BMC Physiol 12:6.33. Iliescu R, Irwin ED, Georgakopoulos D, Lohmeier TE (2012) Renal Responses to Chronic Suppression of Central Sympathetic Outflow. Hypertension 60:749–756.34. Krum H et al. (2009) Catheter-based renal sympathetic denervation for resistant hypertension: a multicentre safety and proof-of-principle cohort study. Lancet 373:1275–1281.35. Mahfoud F et al. (2012) Renal Hemodynamics and Renal Function After Catheter-Based Renal Sympathetic Denervation in Patients With Resistant Hypertension. Hypertension 60:419–424.36. Vink EE, Blankestijn PJ (2012) Evidence and Consequences of the Central Role of the Kidneys in the Pathophysiology of Sympathetic Hyperactivity. Front Physio 3.37. Cowley A Jr (1992) Long-term control of arterial blood pressure. Physiol Rev 72:231–300.38. Mancia G, Ludbrook J, Ferrari A, Gregorini L, Zanchetti A (1978) Baroreceptor reflexes in human hypertension. Circ Res 43:170–177.39. Kaess BM et al. (2012) Aortic stiffness, blood pressure progression, and incident hypertension. JAMA 308:875–881.

40. Kirkwood TBL (1977) Evolution of ageing. Nature 270:301–304.

41. Nakayama Y et al. (2001) Heart Rate-Independent Vagal Effect on End-Systolic Elastance of the Canine Left Ventricle Under Various Levels of Sympathetic Tone. Circulation 104:2277–2279.

42. Cohen A (1991) A Padé approximant to the inverse Langevin function. Rheologic Acta 30:270–273.

43. Brown AM, Saum WR, Tuley FH (1976) A comparison of aortic baroreceptor discharge in normotensive and spontaneously hypertensive rats. Circ Res 39:488–496.

44. Smith H (2011) in Texts in Applied Mathematics, Texts in Applied Mathematics. (Springer New York, New York, NY), pp 119–130.

Other related articles were published on this Open Access Online Scientific Journal including the following:

Pearlman, JD and A. Lev-Ari 5/24/2013 Imaging Biomarker for Arterial Stiffness: Pathways in Pharmacotherapy for Hypertension and Hypercholesterolemia Management

http://pharmaceuticalintelligence.com/2013/05/24/imaging-biomarker-for-arterial-stiffness-pathways-in-pharmacotherapy-for-hypertension-and-hypercholesterolemia-management/

Lev-Ari, A. 5/17/2013 Synthetic Biology: On Advanced Genome Interpretation for Gene Variants and Pathways: What is the Genetic Base of Atherosclerosis and Loss of Arterial Elasticity with Aging

http://pharmaceuticalintelligence.com/2013/05/17/synthetic-biology-on-advanced-genome-interpretation-for-gene-variants-and-pathways-what-is-the-genetic-base-of-atherosclerosis-and-loss-of-arterial-elasticity-with-aging/

Bernstein, HL and A. Lev-Ari 5/15/2013 Diagnosis of Cardiovascular Disease, Treatment and Prevention: Current & Predicted Cost of Care and the Promise of Individualized Medicine Using Clinical Decision Support Systems

http://pharmaceuticalintelligence.com/2013/05/15/diagnosis-of-cardiovascular-disease-treatment-and-prevention-current-predicted-cost-of-care-and-the-promise-of-individualized-medicine-using-clinical-decision-support-systems-2/

Pearlman, JD and A. Lev-Ari 5/7/2013 On Devices and On Algorithms: Arrhythmia after Cardiac Surgery Prediction and ECG Prediction of Paroxysmal Atrial Fibrillation Onset

http://pharmaceuticalintelligence.com/2013/05/07/on-devices-and-on-algorithms-arrhythmia-after-cardiac-surgery-prediction-and-ecg-prediction-of-paroxysmal-atrial-fibrillation-onset/

Pearlman, JD and A. Lev-Ari 5/4/2013 Cardiovascular Diseases: Decision Support Systems for Disease Management Decision Making

http://pharmaceuticalintelligence.com/2013/05/04/cardiovascular-diseases-decision-support-systems-for-disease-management-decision-making/

Larry H Bernstein, MD, FACP, 12/10/2012

Genomics & Genetics of Cardiovascular DiseaseDiagnoses: A Literature Survey of AHA’s Circulation Cardiovascular Genetics, 3/2010 – 3/2013

Aviva Lev-Ari, PhD, RN and Larry H. Bernstein, MD, FACP, 3/7/2013

Mitochondrial Dysfunction and Cardiac Disorders

Curator: Larry H Bernstein, MD, FACP

Aviva Lev-Ari, PhD, RN, 4/7/2013


Read Full Post »

Drug Eluting Stents: On MIT’s Edelman Lab’s Contributions to Vascular Biology and its Pioneering Research on DES

Drug Eluting Stents: On MIT‘s Edelman Lab’s Contributions to Vascular Biology and its Pioneering Research on DES

Author: Larry H Bernstein, MD, FACP

and 

Curator: Aviva Lev-Ari, PhD, RN
http://PharmaceuticalIntelligence.com/2013/04/25/Contributions
-to-vascular-biology/

This is the first of a three part series on the evolution of vascular biology and the studies of the effects of biomaterials in vascular reconstruction and on drug delivery, which has embraced a collaboration of cardiologists at Harvard Medical School , Affiliated Hospitals, and MIT,
requiring cardiovascular scientists at the PhD and MD level, physicists, and computational biologists working in concert, and
an exploration of the depth of the contributions by a distinguished physician, scientist, and thinker.

The first part – Vascular Biology and Disease – will cover the advances in the research on

  • vascular biology,
  • signaling pathways,
  • drug diffusion across the endothelium and
  • the interactions with the underlying muscularis (media),
  • with additional considerations for type 2 diabetes mellitus.

The second part – Stents and Drug Delivery – will cover the

  • purposes,
  • properties and
  • evolution of stent technology with
  • the acquired knowledge of the pharmacodynamics of drug interactions and drug distribution.

The third part – Problems and Promise of Biomaterials Technology – will cover the shortcomings of the cardiovascular devices, and opportunities for improvement

Vascular Biology and Cardiovascular Disease

Early work on endothelial injury and drug release principles

The insertion of a catheter for the administration of heparin is not an innocuous procedure. Heparin is infused to block coagulation, lowering the risk of a dangerous

  • clot formation and
  • dissemination.

It was shown experimentally that the continuous infusion of heparin

  • suppresses smooth muscle proliferation after endothelial injury. It may lead to
  • hemorrhage as a primary effect.

The anticoagulant property of heparin was removed by chemical modification without loss of the anti-proliferative effect.

In this study, MIT researches placed ethylene-vinyl acetate copolymer matrices containing standard and modified heparin adjacent to rat carotid arteries at the time of balloon deendothelialization.

Matrix delivery of both heparin compounds effectively diminished this proliferation in comparison to controls without producing systemic anticoagulation or side effects.

This mode of therapy appeared more effective than administering the agents by either

  • intravenous pumps or
  • heparin/polymer matrices placed in a subcutaneous site distant from the injured carotid artery

This indicated that the site of placement at the site of injury is a factor in the microenvironment, and is a preference for avoiding restenosis after angioplasty and other interventions.

This raised the question of why the proliferation of vascular muscle occurs in the first place.
 Edelman, Nugent and Karnovsky  (1) showed that the proliferation required first the denudation of vascular surface endothelium. This exposed the underlayer to the effect of basic fibroblast growth factor, which stimulates mitogenesis of the exposed cell, explained by the endothelium as a barrier from circulating bFGF.

To answer this question, they compared the effect of

  • 125I-labelled bFGF intravenously given with perivascular controlled bFGF release.
  • Polymeric controlled release devices delivered bFGF to the extravascular space without transendothelial transport. 
Deposition within the blood vessel wall was rapidly distributed circumferentially and was substantially greater than that observed following intravenous injection.

The amount of bFGF deposited in arteries adjacent to the release devices was 40 times that deposited in similar arteries in animals who received a single intravenous bolus of bFGF.

The presence of intimal hyperplasia increased deposition of perivascularly released bFGF 2.4-fold but decreased the deposition of intravenously injected bFGF by 67%.

  • bFGF was 5- to 30-fold more abundant in solid organs after intravenous injection than it was following perivascular release, and
  • bFGF deposition was greatest in the kidney, liver, and spleen and was substantially lower in the heart and lung.

This result indicated that vascular deposition of bFGF is independent of endothelium, and

  • bFGF delivery is effectively perivascular. (2)

Drug activity studies have to be done in well controlled and representative conditions.
 Edelsman’s Lab researchers studied the

  • dose response of injured arteries to exogenous heparin in vivo by providing steady and predictable arterial levels of drug.
  • Controlled-release devices were fabricated to direct heparin uniformly and at a steady rate to the adventitial surface of balloon-injured rat carotid arteries.

Researchers predicted the distribution of heparin throughout the arterial wall using computational simulations and correlated these concentrations with the biologic response of the tissues.

Researchers determined from this process that an in vivo arterial concentration of 0.3 mg/ml of heparin is required to maximallyinhibit intimal hyperplasia after injury.

This estimation of the required tissue concentration of a drug is

  • independent of the route of administration and
  • applies to all forms of drug release.

In this way the Team was able to

  • evaluate the potential of  widely disparate forms of drug release and, to finally
  • create some rigorous criteria by which to guide the development of particular delivery strategies for local diseases. (3)

Chiefly, the following three effects:

(1) Effect of controlled adventitial heparin delivery on smooth muscle cell proliferation following endothelial injury. ER Edelman, DH Adams, and MJ Karnovsky. PNAS May 1990; 87: 3773-3777.


(2) Perivascular and intravenous administration of basic fibroblast growth factor: Vascular and solid organ deposition. ER Edelman, MA Nugent, and MJ Karnovsky. PNAS Feb 1993; 90: 1513-1517.


(3) Tissue concentration of heparin, not administered dose, correlates with the biological response of injured arteries in vivo. MA Lovich and ER Edelman. PNAS Sep 1999; 96: 11111–11116.

Vascular Injury and Repair

Perlecan is a heparin-sulfate proteoglycan that might be critical for regulation of vascular repair by inhibiting the binding and mitogenic activity of basic fibroblast growth factor-2 (bFGF-2) in vascular smooth muscle cells .

The Team generated

  • Clones of endothelial cells expressing an antisense vector targeting domain III of perlecan. The transfected cells produced significantly less perlecan than parent cells, and they had reduced bFGF in vascular smooth muscle cells.
  • Endothelial cells were seeded onto three-dimensional polymeric matrices and implanted adjacent to porcine carotid arteries subjected to deep injury.
  • The parent endothelial cells prevented thrombosis, but perlecan deficient cells were ineffective.

The ability of endothelial cells to inhibit intimal hyperplasia, however, was only in part suppressed by perlecan. The differential regulation by perlecan of these aspects of vascular repair may clarify why control of clinical clot formation does not lead to full control of intimal hyperplasia.

The use of genetically modified tissue engineered cells provides a new approach for dissecting the role of specific factors within the blood vessel wall.(1) Successful implementation of local arterial drug delivery requires transmural distribution of drug. The physicochemical properties of the applied compound govern its transport and tissue binding.

  • Hydrophilic compounds are cleared rapidly.
  • Hydrophobic drugs bind to fixed tissue elements, potentially prolonging tissue residence and biological effect.

Local vascular drug delivery provides

  • elevated concentrations of drug in the target tissue while
  • minimizing systemic side effects.

To better characterize local pharmacokinetics the Team examined the arterial transport of locally applied dextran and dextran derivatives in vivo.

Using a two-compartment pharmacokinetic model to correct

  • The measured transmural flux of these compounds for systemic
  • Redistribution and elimination as delivered from a photo-polymerizable hydrogel.
  • The diffusivities and the transendothelial permeabilities were strongly dependent on molecular weight and charge
  • For neutral dextrans, the diffusive resistance increased with molecular weightapproximately 4.1-fold between the molecular weights of 10 and 282 kDa.
  • Endothelial resistance increased 28-fold over the same molecular weight range.
  • The effective medial diffusive resistance was unaffected by cationic charge as such molecules moved identically to neutral compounds, but increased approximately 40% when dextrans were negatively charged.

Transendothelial resistance was 20-fold lower for the cationic dextrans, and 11-fold higher for the anionic dextrans, when both were compared to neutral counterparts.

These results suggest that, while

  • low molecular weight drugs will rapidly traverse the arterial wall with the endothelium posing a minimal barrier,
  • the reverse is true for high molecular weight agents.

The deposition and distribution of locally released vascular therapeutic compounds might be predicted based upon chemical properties, such as molecular weight and charge. (2)

Paclitaxel is hydrophobic and has therapeutic potential against proliferative vascular disease.
 The favorable preclinical data with this compound may, in part, result from preferential tissue binding.
 The complexity of Paclitaxel pharmacokinetics required in-depth investigation if this drug is to reach its full clinical potential in proliferative vascular diseases.

Equilibrium distribution of Paclitaxel reveals partitioning above and beyond perfusate concentration and a spatial gradient of drug across the arterial wall.

The effective diffusivity (Deff) was estimated from the Paclitaxel distribution data to

  • facilitate comparison of transport of Paclitaxel through arterial parenchyma with that of other vasoactive agents and to
  • characterize the disparity between endovascular and perivascular application of drug.

This transport parameter described the motion of drug in tissues given an applied concentration gradient and includes, in addition to diffusion,

  • the impact of steric hindrance within the arterial interstitium;
  • nonspecific binding to arterial elements; and, in the preparation used here,
  • convective effects from the applied transmural pressure gradient.

At all times, the effective diffusivity for endovascular delivery exceeded that of perivascular delivery. The arterial transport of Paclitaxel was quantified through application ex vivo and measurement of the subsequent transmural distribution.

  • Arterial Paclitaxel deposition at equilibrium varied across the arterial wall.
  • Permeation into the wall increased with time, from 15 minutes to 4 hours, and
  • varied with the origin of delivery.

In contrast to hydrophilic compounds, the concentration in tissue exceeded the applied concentration and the rate of transport was markedly slower. Furthermore, endovascular and perivascular Paclitaxel application led to differences in deposition across the blood vessel wall.

This leads to a conclusion that Paclitaxel interacts with arterial tissue elements  as it moves under the forces of

  • diffusion and
  • convection and
  • can establish substantial partitioning and spatial gradients across the tissue. (3)

Endovascular drug-eluting stents have changed the practice of  cardiovascular vascularization, and yet it is unclear how they so dramatically reduce restenosis

We don’t know how to distinguish between the different formulations available.
 Researchers are now questioning whether individual properties of different drugs beyond lipid avidity effect arterial transport and distribution.

In bovine internal carotid segments, tissue-loading profiles for

  • Hydrophobic Paclitaxel and Rapamycin are indistinguishable, reaching load steady state after 2 days.
  • Hydrophilic dextran reaches equilibrium in hours.

Paclitaxel and Rapamycin bind to the artery at 30–40 times bulk concentration, and bind to specific tissue elements.

Transmural drug distribution profiles are markedly different for the two compounds.

  • Rapamycin binds specifically to FKBP12 binding protein and it distributes evenly through the artery,
  • Paclitaxel binds specifically to microtubules, and remains primarily in the subintimal space.

The binding of Rapamycin and Paclitaxel to specific intracellular proteins plays an essential role in

  • determining arterial transport and distribution and in
  • distinguishing one compound from another.

These results offer further insight into the

  • mechanism of local drug delivery and the
  • specific use of existing drug-eluting stent formulations. (4)

The Role of Amyloid beta (A) in Creation of Vascular Toxic Plaque

Amyloid beta (A) is a peptide family produced and deposited in neurons and endothelial cells (EC).
It is found at subnanomolar concentrations in the plasma of healthy individuals.
 Simple conformational changes produce a form of A-beta , A-beta 42, which creates toxic plaque in the brains of Alzheimer’s patients.

Oxidative stress induced blood brain barrier degeneration has been proposed as a key factor for A-beta 42 toxicity.

This cannot account for lack of injury from the same peptide in healthy tissues.
Researchers hypothesized that cell state mediates A-beta’s effect.
 They examined the viability in the presence of A-beta secreted from transfected
Chinese hamster ovary cells (CHO) of

  • aortic Endothelial Cells (EC),
  • vascular smooth muscle cells (SMC) and
  • epithelial cells (EPI) in different states

A-beta was more toxic to all cell types when they were subconfluent.
 Subconfluent EC sprouted and SMC and EPI were inhibited by A-beta.
Confluent EC were virtually resistant to A-beta and suppressed A-beta production by A-beta +CHO.

Products of subconfluent EC overcame this resistant state, stimulating the production and toxicity of A-beta 42. Confluent EC overgrew >35% beyond their quiescent state in the presence of A-beta conditioned in media from subconfluent EC.

These findings imply that A-beta 42 may well be even more cytotoxic to cells in injured or growth states and potentially explain the variable and potent effects of this protein.

One may now need to consider tissue and cell state in addition to local concentration of and exposure duration to A-beta.

The specific interactions of A-beta and EC in a state-dependent fashion may help understand further the common and divergent forms of vascular and cerebral toxicity of A-beta and the spectrum of AD. (5)

(1) Perlecan is required to inhibit thrombosis after deep vascular injury and contributes
to endothelial cell-mediated inhibition of intimal hyperplasia. MA Nugent, HM Nugent,
RV Iozzoi, K Sanchack, and ER Edelman. PNAS Jun 2000; 97(12): 6722-6727


(2) Correlation of transarterial transport of various dextrans with their physicochemical properties.
O Elmalak, MA Lovich, E Edelman. Biomaterials 2000; 21: 2263-2272


(3) Arterial Paclitaxel Distribution and Deposition. CJ Creel, MA Lovich, ER Edelman. Circ Res. 2000;86:879-884


(4) Specific binding to intracellular proteins determines arterial transport properties for rapamycin and Paclitaxel.
AD Levin, N Vukmirovic, Chao-Wei Hwang, and ER Edelman. PNAS Jun 2004; 101(25): 9463–9467.
www.pnas.org/cgi/doi/10.1073/pnas.0400918101


(5) Amyloid beta toxicity dependent upon endothelial cell state. M Balcells, JS Wallins, ER Edelman.
Neuroscience Letters 441 (2008) 319–322

Endothelial Damage as an Inflammatory State

Autoimmunity may drive vascular disease through anti-endothelial cell (EC) antibodies. This raises a question about whether an increased morbidity of cardiovascular diseases in concert with systemic illnesses may involve these antibodies.

Matrix-embedded ECs act as powerful regulators of vascular repair accompanied by significant reduction in expected systemic and local inflammation.

The Lab researchers compared the immune response against free and matrix-embedded ECs in naive mice and mice with heightened EC immune reactivity. Mice were presensitized to EC with repeated subcutaneous injections of saline-suspended porcine EC (PAE) (5*10^5 cells).

On day 42, both naive mice (controls) and mice with heightened EC immune reactivity received 5*10^5 matrix-embedded or free PAEs. Circulating PAE-specific antibodies and effector T-cells were analyzed 90 days after implantation for –

  • PAE-specific antibody-titers,
  • frequency of CD4+-effector cells, and
  • xenoreactive splenocytes

These were 2- to 4-fold lower (P<0.0001) when naıve mice were injected with matrix-embedded instead of saline-suspended PAEs.

Though basal levels of circulating antibodies were significantly elevated after serial PAE injections (2210+341 mean fluorescence intensity, day 42) and almost doubled again 90 days after injection of a fourth set of free PAEs, antibody levels declined by half in recipients of matrix-embedded PAEs at day 42 (P<0.0001), as did levels of CD4+-effector cells and xenoreactive splenocytes.

A significant immune response to implantation of free PAE is elicited in naıve mice, that is even more pronounced in mice with pre-developed anti-endothelial immunity.

Matrix-embedding protects xenogeneic ECs against immune reaction in naive mice and in mice with heightened immune reactivity.

Matrix-embedded EC might offer a promising approach for treatment of advanced cardiovascular disease. (1)

Researchers examined the molecular mechanisms through which

mechanical force and hypertension modulate

endothelial cell regulation of vascular homeostasis.

Exposure to mechanical strain increased the paracrine inhibition of vascular smooth muscle cells (VSMCs) by endothelial cells.

Mechanical strain stimulated the production by endothelial cells of perlecan and heparan-sulfate glycosaminoglycans. By inhibiting the expression of perlecan with an antisense vector researchers demonstrated that perlecan was essential to the strain-mediated effects on endothelial cell growth control.

Mechanical regulation of perlecan expression in endothelial cells was

  • governed by a mechano-transduction pathway
  • requiring transforming growth factor (TGF-β) signaling and
  • intracellular signaling through the ERK pathway.

Immunohistochemical staining of the aortae of spontaneously hypertensive rats
demonstrated strong correlations between

  • endothelial TGF-β,
  • phosphorylated signaling intermediates, and
  • arterial thickening.

Studies on ex vivo arteries exposed to varying levels of pressure demonstrated that

ERK and TGF-beta signaling were required for pressure-induced upregulation of endothelial HSPG.

The Team’s findings suggest a novel feedback control mechanism in which

  • net arterial remodeling to hemodynamic forces is controlled by a dynamic interplay between growth stimulatory signals from vSMCs and
  • growth inhibitory signals from endothelial cells. (2)

Heparan-sulfate proteoglycans (HSPGs) are potent regulators of vascular remodeling and repair.
 The major enzyme capable of degrading HSPGs is heparanase, which led us to examine
the role of heparanase in controlling

  • arterial structure,
  • mechanics, and
  • remodeling.

In vitro studies suggested heparanase expression in endothelial cells serves as a negative regulator of endothelial inhibition of vascular smooth muscle cell (vSMC) proliferation.

ECs inhibit vSMC proliferation through the interplay between

  • growth stimulatory signals from vSMCs and
  • growth inhibitory signals from ECs.

This would be expected if ECs had HSPGs that are degraded by heparanase.
Arterial structure and remodeling to injury is modified by heparanase expression.
Transgenic mice overexpressing heparanase had

  • increased arterial thickness,
  • cellular density, and
  • mechanical compliance.

Endovascular stenting studies in Zucker rats demonstrated increased heparanase expression in the neointima of obese, hyperlipidemic rats in comparison to lean rats.

The extent of heparanase expression within the neointima strongly correlated with the neointimal thickness following injury. To test the effects of heparanase overexpression on arterial repair, researchers developed a novel murine model of stent injury using small diameter self-expanding stents.

Using this model, researchers found that increased

  • neointimal formation and
  • macrophage recruitment occurs in transgenic mice overexpressing heparanase.
  • Taken together, these results support a role for heparanase in the regulation of arterial structure, mechanics, and repair. (3)

The first host–donor reaction in transplantation occurs at the blood–tissue interface.
When the primary component of the implant (donor) is the endothelial cells, it incites an immunologic reaction. Injections of free endothelial cell implants elicit a profound major histocompatibility complex (MHC) II dominated immune response.

Endothelial cells embedded within three-dimensional matrices behave like quiescent endothelial cells.

Perivascular implants of such embedded ECs cells are the most potent inhibitor of intimal hyperplasia and thrombosis following controlled vascular injury, but without any immune reactivity.

Allo- and even exenogenic endothelial cells evoke no significant humoral or
cellular immune response in immune-competent hosts when embedded within matrices.
 Moreover,  endothelial implants are immune-modulatory, reducing the extent of the memory response to previous free cell implants.

Attenuated immunogenicity results in muted activation of adaptive and innate immune cells. These findings point toward a pivotal role of matrix–cell-interconnectivity for

  • the cellular immune phenotype and might therefore assist in the design  of
  • extracellular matrix components for successful tissue engineering. (4)

Because changes in subendothelial matrix composition are associated with alterations of the endothelial immune phenotype, researchers sought to understand if

  • cytokine-induced NF-κB activity and
  • downstream effects depend on substrate adherence of endothelial cells (EC).

The team compared the upstream

  • phosphorylation cascade,
  • activation of NF-ĸβ, and
  • expression/secretion

of downstream effects of EC grown on tissue culture polystyrene plates (TCPS) with EC embedded within collagen-based matrices (MEEC).

Adhesion of natural killer (NK) cells was quantified in vitro and in vivo.

  • NF-κβ subunit p65 nuclear levels were significantly lower and
  • p50 significantly higher in cytokine-stimulated MEEC than in EC-TCPS.

Despite similar surface expression of TNF-α receptors, MEEC had significantly decreased secretion and expression of IL-6, IL-8, MCP-1, VCAM-1, and ICAM-1.

Attenuated fractalkine expression and secretion in MEEC (two to threefold lower than in EC-TCPS; p < 0.0002) correlated with 3.7-fold lower NK cell adhesion to EC (6,335 ± 420 vs. 1,735 ± 135 cpm; p < 0.0002).

Furthermore, NK cell infiltration into sites of EC implantation in vivo was significantly reduced when EC were embedded within matrix.

Matrix embedding enables control of EC substratum interaction.

This in turn regulates chemokine and surface molecule expression and secretion, in particular – of those compounds within NF-κβ pathways,

  • chemoattraction of NK cells,
  • local inflammation, and
  • tissue repair. (5)

Monocyte recruitment and interaction with the endothelium is imperative to vascular recovery.

Tie2 plays a key role in endothelial health and vascular remodeling.
Researchers studied monocyte-mediated Tie2/angiopoietin signaling following interaction of primary monocytes with endothelial cells and its role in endothelial cell survival.

The direct interaction of primary monocytes with subconfluent endothelial cells

resulted in transient secretion of angiopoietin-1 from monocytes and

the activation of endothelial Tie2. This effect was abolished by preactivation of monocytes with tumor necrosis factor-α (TNFα).

Although primary monocytes contained high levels of

  • both angiopoietin 1 and 2,
  • endothelial cells contained primarily angiopoietin 2.

Seeding of monocytes on serum-starved endothelial cells reduced caspase-3 activity by 46+5.1%, and 52+5.8% after TNFα treatment, and it decreased single-stranded DNA levels by 41+4.2% and 40+ 3.5%, respectively.

This protective effect of monocytes on endothelial cells was reversed by Tie2 silencing with specific short interfering RNA.

The antiapoptotic effect of monocytes was further supported by the

  • activation of cell survival signaling pathways involving phosphatidylinositol 3-kinase,
  • STAT3, and
  • AKT.

Monocytes and endothelial cells form a unique Tie2/angiopoietin-1 signaling system that affects endothelial cell survival and may play critical a role in vascular remodeling and homeostasis. (6)

(1) Cell–Matrix Contact Prevents Recognition and Damage of Endothelial Cells in States of Heightened Immunity.
H Methe, ER Edelman. Circulation. 2006;114[suppl I]:I-233–I-238.
http://www.circulationaha.org/DOI/10.1161/CIRCULATIONAHA.105.000687

(2) Endothelial Cells Provide Feedback Control for Vascular Remodeling Through a Mechanosensitive Autocrine
TGFβ Signaling Pathway. AB Baker, DS Ettenson, M Jonas, MA Nugent, RV Iozzo, ER Edelman.
Circ. Res. 2008;103;289-297   http://dx.doi.org/10.1161/CIRCRESAHA.108.179465
http://circres.ahajournals.org/cgi/content/full/103/3/289

(3) Heparanase Alters Arterial Structure, Mechanics, and Repair Following Endovascular Stenting in Mice.
AB Baker, A Groothuis, M Jonas, DS Ettenson…ER Edelman.   Circ. Res. 2009;104;380-387;
http://dx.doi.org/10.1161/CIRCRESAHA.108.180695  http://circres.ahajournals.org/cgi/content/full/104/3/380

(4) The effect of three-dimensional matrix-embedding of endothelial cells on the humoral and cellular immune response.
H Methe, S Hess, ER Edelman. Seminars in Immunology 20 (2008) 117–122. http://dx.doi.org/10.1016/j.smim.2007.12.005

(5) NF-kB Activity in Endothelial Cells Is Modulated by Cell Substratum Inter-actions and Influences Chemokine-Mediated
Adhesion of Natural Killer Cells.  S Hess, H Methe, Jong-Oh Kim, ER Edelman.
Cell Transplantation 2009; 18: 261–273


(6) Primary Monocytes Regulate Endothelial Cell Survival Through Secretion of Angiopoietin-1 and Activation of Endothelial Tie2.
SY Schubert, A Benarroch, J Monter-Solans and ER Edelman. Arterioscler Thromb Vasc Biol 2011;31;870-875
http://dx.doi.org/10.1161/ATVBAHA.110.218255

Neointimal Formation, Shear Stress, and Remodelling with Reference to Diabetes

Innate immunity is of major importance in vascular repair. The present study evaluated whether

  • systemic and transient depletion of monocytes and macrophages with
  • liposome-encapsulated bisphosphonates inhibits experimental in-stent neointimal formation.

The Experiment

Rabbits fed on a hypercholesterolemic diet underwent bilateral iliac artery balloon denudation and stent deployment.

Liposomal alendronate (3 or 6 mg/kg) was given concurrently with stenting.

  • Monocyte counts were reduced by 90% 24 to 48 hours aftera single injection of liposomal alendronate, returning to basal levels at 6 days.

This treatment significantly reduced

  • intimal area at 28 days, from 3.88+0.93 to 2.08+0.58 and 2.16 +0.62 mm2.
  • Lumen area was increased from 2.87+0.44 to 3.57­+0.65 and 3.45+0.58 mm2, and
  • arterial stenosis was reduced from 58 11% to 37 8% and 38 7% in controls, in rabbits treated with 3 mg/kg, and with 6 mg/kg, respectively (mean+SD, n=8 rabbits/group, P< 0.01 for all 3 parameters).

No drug-related adverse effects were observed.
Reduction in neointimal formation was associated with

  • reduced arterial macrophage infiltration and proliferation at 6 days and with an
  • equal reduction in intimal macrophage and smooth muscle cell content at 28 days after injury.

Conversely, drug regimens ineffective in reducing monocyte levels did not inhibit neointimal formation.
Researchers have shown that a

  • single liposomal bisphosphonates injection concurrent with injury reduces in-stent neointimal formation and
  • arterial stenosis in hypercholesterolemic rabbits, accompanied by systemic transient depletion of monocytes and macrophages. (1)

Diabetes and insulin resistance are associated with increased disease risk and poor outcomes from cardiovascular interventions.

Even drug-eluting stents exhibit reduced efficacy in patients with diabetes.
Researchers reported the first study of vascular response to stent injury in insulin-resistant and diabetic animal models.

Endovascular stents were expanded in the aortae of

  • obese insulin-resistant and
  • type 2 diabetic Zucker rats,
  • in streptozotocin-induced type 1 diabetic Sprague-Dawley rats, and
  • in matched controls.

Insulin-resistant rats developed thicker neointima (0.46+0.08 versus 0.37+0.06 mm2, P 0.05), with  decreased lumen area (2.95+0.26 versus 3.29+0.15 mm2, P 0.03) 14 days after stenting compared with controls, but without increased vascular inflammation (tissue macrophages).

Insulin-resistant and diabetic rat vessels did exhibit markedly altered signaling pathway activation 1 and 2 weeks after stenting, with up to a 98% increase in p-ERK (anti-phospho ERK) and a 54% reduction in p-Akt (anti-phospho Akt) stained cells. Western blotting confirmed a profound effect of insulin resistance and diabetes on Akt and ERK signaling in stented segments. p-ERK/p-Akt ratio in stented segments uniquely correlated with neointimal response (R2 = 0.888, P< 0.04) , but not in lean controls.

Transfemoral aortic stenting in rats provides insight into vascular responses in insulin resistance and diabetes.

Shifts in ERK and Akt signaling related to insulin resistance may reflect altered tissue repair in diabetes accompanied by a

  • shift in metabolic : proliferative balance.

These findings may help explain the increased vascular morbidity in diabetes and suggest specific therapies for patients with insulin resistance and diabetes. (2)

Researchers investigated the role of Valsartan (V) alone or in combination with Simvastatin (S) on coronary atherosclerosis and vascular remodeling, and tested the hypothesis that V or V/S attenuate the pro-inflammatory effect of low endothelial shear stress (ESS).

Twenty-four diabetic, hyperlipidemic swine were allocated into Early (n = 12) and Late (n=12) groups.
Diabetic swine in each group were treated with Placebo (n=4), V (n = 4) and V/S (n = 4) and  followed for 8 weeks in the Early group and 30 weeks in the Late group.

Blood pressure, serum cholesterol and glucose were similar across the treatment subgroups.
ESS was calculated in plaque-free subsegments of interest (n = 109) in the Late group at week 23.
Coronary arteries of this group were harvested at week 30, and the subsegments of interest were identified, and analyzed histopathologically.

Intravascular geometrically correct 3-dimensional reconstruction of the coronary arteries of 12 swine was performed 23 weeks after initiation of diabetes mellitus and a hyperlipidemic diet. Local endothelial shear stress was calculated

  • in plaque-free subsegments of interest (n=142) with computational fluid dynamics, and
  • the coronary arteries (n=31) were harvested and the same subsegments were identified at 30 weeks.

V alone or with S

  • reduced the severity of inflammation in high-risk plaques.
Both regimens attenuated the severity of enzymatic degradation of the arterial wall, reducing the severity of expansive remodeling.
  • attenuated the pro-inflammatory effect of low ESS.
V alone or with S
  • exerts a beneficial effect of reducing and stabilizing high-risk plaque characteristics independent of a blood pressure- and lipid-lowering effect. (3)

This study tested the hypothesis that low endothelial shear stress  augments the

  • expression of matrix-degrading proteases, promoting the
  • formation of thin-capped atheromata.

Researchers assessed the messenger RNA and protein expression, and elastolytic activity of selected elastases and their endogenous inhibitors.

Subsegments with low endothelial shear stress at week 23 showed

  • reduced endothelial coverage,
  • enhanced lipid accumulation, and
  • intense infiltration of activated inflammatory cells at week 30.

These lesions showed increased expression of messenger RNAs encoding

  • matrix metalloproteinase-2, -9, and -12, and cathepsins K and S
  • relative to their endogenous inhibitors and
  • increased elastolytic activity.

Expression of these enzymes correlated positively with the severity of internal elastic lamina fragmentation.

Thin-capped atheromata in regions with

  • lower preceding endothelial shear stress had
  • reduced endothelial coverage,
  • intense lipid and inflammatory cell accumulation,
  • enhanced messenger RNA expression and
  • elastolytic activity of MMPs and cathepsins with
  • severe internal elastic lamina fragmentation.

Low endothelial shear stress induces endothelial discontinuity and

  • accumulation of activated inflammatory cells, thereby
  • augmenting the expression and activity of elastases in the intima and
  • shifting the balance with their inhibitors toward matrix breakdown.

Team’s results provide new insight into the mechanisms of regional formation of plaques with thin fibrous caps. (4)

Elevated CRP levels predict increased incidence of cardiovascular events and poor outcomes following interventions. There is the suggestion that CRP is also a mediator of vascular injury.

Transgenic mice carrying the human CRP gene (CRPtg) are predisposed to arterial thrombosis post-injury.

Researchers examined whether CRP similarly modulates the proliferative and hyperplastic phases of vascular repair in CRPtg when thrombosis is controlled with daily aspirin and heparin at the time of trans-femoral arterial wire-injury.

Complete thrombotic arterial occlusion at 28 days was comparable for wild-type and CRPtg mice (14 and 19%, respectively). Neointimal area at 28d was 2.5 fold lower in CRPtg (4190±3134 m2, n = 12) compared to wild-types (10,157±8890 m2, n = 11, p < 0.05).

Likewise, neointimal/media area ratio was 1.10±0.87 in wild-types and 0.45±0.24 in CRPtg (p < 0.05).

  • Seven days post-injury, cellular proliferation and apoptotic cell number in the intima were both less pronounced in CRPtg than wild-type.
  • No differences were seen in leukocyte infiltration or endothelial coverage.
CRPtg mice had significantly reduced p38 MAPK signaling pathway activation following injury.

The pro-thrombotic phenotype of CRPtg mice was suppressed by aspirin/heparin, revealing CRP’s influence on neointimal growth after trans-femoral arterial wire-injury.

  • Signaling pathway activation,
  • cellular proliferation, and
  • neointimal formation

were all reduced in CRPtg following vascular injury.
 Increasingly the Team was aware of CRP multipotent effects.
 Once considered only a risk factor, and recently a harmful agent, CRP is a far more complex regulator of vascular biology. (5)

(1) Liposomal Alendronate Inhibits Systemic Innate Immunity and Reduces In-Stent Neointimal
Hyperplasia in Rabbits. HD Danenberg, G Golomb, A Groothuis, J Gao…, ER Edelman.
Circulation. 2003;108:2798-2804


(2) Vascular Neointimal Formation and Signaling Pathway Activation in Response to Stent Injury
in Insulin-Resistant and Diabetic Animals. M Jonas, ER Edelman, A Groothuis, AB Baker, P Seifert, C Rogers.
Circ. Res. 2005;97;725-733.        http://dx.doi.org/10.1161/01.RES.0000183730.52908.C6
http://circres.ahajournals.org/cgi/content/full/97/7/725

(3) Attenuation of inflammation and expansive remodeling by Valsartan alone or in combination with
Simvastatin in high-risk coronary atherosclerotic plaques. YS Chatzizisis, M Jonas, R Beigel, AU Coskun…
ER Edelman, CL Feldman, PH Stone.  Atherosclerosis 203 (2009) 387–394


(4) Augmented Expression and Activity of Extracellular Matrix-Degrading Enzymes in Regions of Low
Endothelial Shear Stress Colocalize With Coronary Atheromata With Thin Fibrous Caps in Pigs.
YS Chatzizisis, AB Baker, GK Sukhova,…P Libby, CL Feldman, ER Edelman, PH Stone
Circulation 2011;123;621-630     http://dx.doi.org/10.1161/CIRCULATIONAHA.110.970038
http://circ.ahajournals.org/cgi/content/full/123/6/621


(5) Neointimal formation is reduced after arterial injury in human crp transgenic mice
HD Danenberg, E Grad, RV Swaminathan, Z Chenc,…ER Edelman
Atherosclerosis 201 (2008) 85–91

A Rattle Bag of Science and the Art of Translation

Science Translational Medicine – A rattle bag of science and the art of translation
E. R. Edelman, G. A. FitzGerald.
Sci.Transl. Med. 3, 104ed3 (2011). http://dx.doi.org/10.1126/scitranslmed.3002131

Elazer R. Edelman is the Thomas D. and Virginia W. Cabot Professor of Health Sciences and Technology at MIT,
Professor of Medicine at Harvard Medical School, a coronary care unit cardiologist at the Brigham and Women’s
Hospital, and Director of the Harvard-MIT Biomedical Engineering Center. E-mail: ere@mit.edu

Garret A. FitzGerald is the McNeil Professor in Translational Medicine and Therapeutics, Chair of the Department of
Pharmacology, and Director of the Institute for Translational Medicine & Therapeutics, University of Pennsylvania.
E-mail: garret@upenn.edu

In 2011, the American Association for the Advancement of Science (AAAS)  founded Science Translational Medicine (STM)
to disseminate interdisciplinary science integrating basic and clinical research that defines and fosters new therapeutics, devices, and diagnostics.

Conceived and nourished under the creative vision of Elias Zerhouni and Katrina Kelner, the journal has attracted widespread attention.
Now, as we assume the mantle of co-chief scientific advisors, we look back on the journal’s early accomplishments, restate our mission, and make clear the kinds of manuscripts we seek and accept for publication.

STM’s mission, as articulated by Elias and Katrina, was to

“promote human health by providing a forum for communication and cross-fertilization among basic, translational, and clinical research practitioners and trainees from all relevant established and emerging disciplines.”

This statement remains relevant and accurate today.
 With this mission on our masthead, STM now receives ~25 manuscripts (full-length research articles) per week and publishes ~10% of them. Roughly half of the submissions are deemed inappropriate for the journal and are returned without review within 8 to 10 days of receipt.

Of those papers that undergo full peer review,

decisions to reject are made within 48 days and

the mean time to acceptance (including the revision period) is 125 days.

There is now an average wait of only 24 days between acceptance and publication.

Defining TRANSLATIONAL Medicine

In accord with the journal’s broad readership, the ideal manuscript meets five criteria: It
(i) reports a discovery of translational relevance with high-impact potential;
(ii) has a conceptual focus with interdisciplinary appeal;
(iii) elucidates a biological mechanism;
(iv) is innovative and novel; and
(v) is presented in clear, broadly accessible language.
 STM seeks to publish research that describes

  • how innovative concepts drive the creative biomedical science
  • that ultimately improves the quality of people’s lives—

This is the broadest of our journal’s criteria but is the one that sets us apart as well.
Translational relevance does not require demonstration of benefit in humans but does require the evident potential to advance clinical medicine, thus impacting the direction of our culture and the welfare of our communities. Conceptual focus and mechanistic emphasis discriminate our papers from those that contain observational descriptions of technical findings for which value is restricted to a specific discipline.

However, innovation and novelty may apply to a fundamental scientific discovery or to the nature of its application and relevance to the translational process. Criteria enable the journal to consider versatile technological advances that apply new and creative thinking but may not necessarily offer fresh insights into biological mechanisms. Finally, while the subsequent additional efforts of the STM editorial staff are not to be discounted, the clarity of writing and coherence of argument presented within a submitted manuscript are likely to facilitate its progress through the challenge of peer review.

On Causes – Hippocrates, Aristotle, Robert Koch, and the Dread Pirate Roberts

Elazer R. Edelman
Circulation 2001;104:2509-2512

The idea of risk factors for vascular disease has evolved

  • from a dichotomous to continuous hazard analysis and
  • from the consideration of a few factors to
  • mechanistic investigation of many interrelated risks.

However, confusion still abounds regarding issues of association and causation. Originally, the simple presence of

  • tobacco abuse, hypertension, and/or hypercholesterolemia were tallied, and
  • the cumulative score was predictive of subsequent coronary artery disease.

Since then, dose responses have been defined for these and other factors and it has been suggested that almost 300 factors place patients at risk; these factors include elevations in plasma homocysteine.
 Recent studies shed interesting light on the mechanism of this potentially causal relationship, which was first noted in 1969.

Aside from putative effects on vessel wall dynamics, there is now direct evidence that homocysteine is atherogenic. Twenty-fold increases in plasma homocysteine achieved by dietary manipulation of apoE–/– mice increased aortic root lesion size 2-fold and produced a prolonged chronic inflammatory mural response accompanied by elevations in vascular cell adhesion molecule-1 (VCAM) and tumor necrosis factor-a (TNF-a).

In long term followup, homocysteine levels elevated by

  • dietary supplementation with methionine or homocysteine
  • promoted lesion size and plaque fibrosis in these
  • atherosclerosis-prone mice early in life, but without influencing ultimate plaque burden as the animals aged.

A number of mechanisms were proposed by which homocysteine achieved this effect, including

  • promotion of inflammation,
  • regulation of lipoprotein metabolism, and
  • modification of critical biochemical pathways and
  • metabolites including nitric oxide (NO).

See p 2569
In the present issue of Circulation,

Stühlinger et al 7 advance these mechanistic insights one critical step further by defining homocysteine’s effects at an enzymatic level.

The group led by Lentz published an association between levels of the

  • endogenous inhibitor of Nirtic Oxide synthase,
  • asymmetric dimethyl arginine (ADMA), and
  • homocysteine in cultured endothelial cells and in the serum of cynomolgus monkeys.

Such an association is interesting because the L-arginine–NO synthase pathway seems to be a critical component in the full range of endothelial cell biology and vascular dysfunction.

Stühlinger et al 7  now show that increased cultured endothelial cell elaboration of ADMA by homocysteine and its precursor L-methionine is associated with a dose-dependent impairment of the activity of endothelial dimethylarginine dimethylaminohydrolase (DDAH), the enzyme that degrades ADMA. Homocysteine directly inhibited DDAH activity in a cell-free system by targeting a critical sulfhydryl group on this enzyme.

Thus, one could envision that the balance of cardiovascular health and disease could well be determined by the ability of an intact Nirtic Oxide synthase system to overcome environmental, dietary, and even genetic factors.

In patients with altered enzymatic defense systems,

  • elevated homocysteine,
  • oxidized lipoproteins,
  • inflammation, and other
  • vasotoxins

may dominate even the most potent defense mechanisms.
These studies raise a number of issues.
Do we need to add to our list of established cardiovascular risk factors to accommodate new findings and associations?
Is there a final common pathway for all risk factors or perhaps even a unified factor theory into which all potential risks can be grouped?
And, as always, should we consider Nirtic Oxide at the core of this universality?
Finally, should we change our focus altogether and speak not of risk factors but of

  • genetic predisposition,
  • extent of biochemical aberration, and
  • degree of physical damage?

Some would view these remarkable success stories and the repeated association of hyperhomocyst(e)inemia with coronary, cerebral, and peripheral vascular disease and simply advocate for increased folic acid intake for all.

Indeed, this intervention of negligible cost and

  • insignificant side effect is already partially in place;
  • many foods are fortified with folate to prevent congenital neural tube defects.

This reader considers the seminal work by Vernon Young and Yves Ingenbleek on the relationship between

  • S8 and regions distant from lava flows in Asia and Indian subcontinents,
  • where they have determined hyperhomocysteinemia and the consequence associated with:
  • veganism (not voluntary)
  • impaired methyl donor reactions and transsulfuration pathways (not corrected by B12, folate)
  • loss of lean body mass due to the constant relationship of S:N (insufficient from plant sources)

What happens, when we fail to continue to pursue causality,

  • the linkage of biological significance or scientific plausibility with
  • epidemiologically or statistically significant association?

In medicine, risk becomes the likelihood that people without a disease will acquire the disease through contact with factors thought to increase disease risk.

All of these risk factors are then, by nature, imprecise and nonspecific.
 They are stochastic measures of what will happen to normal people who fall into particular measures of these parameters.

The daring may be willing to accept these risks, citing friend and foe who live well beyond or for far lesser times than anticipated by risk alone. Such concerns may well become moot if we can simultaneously identify patients at risk

  • by linking phenotype with genotype,
  • gene expression with protein elaboration, and
  • environmental exposures with the biochemical consequences and
  • direct anatomic aberrations they induce.

This kind of characterization may well replace a family history of arterial disease as a rough estimate of

  • genotype,
  • serum cholesterol as an indirect measure of the health of lipoprotein metabolism,
  • serum glucose as a crude determinant of the ravages of diabetes mellitus,
  • blood pressure measurement as a marker of long-standing endogenous exposure to altered flow, and
  • tobacco abuse as a maker of long-standing exposure to exogenous toxins.

Rather than identifying patients on the basis of their serum cholesterol, we will have a direct measure of their

  • LDL receptor number,
  • internalization rate,
  • macrophage content in the blood vessel wall,
  • metalloproteinase activity, etc.
  • insulin receptor metabolism,
  • oxidative state, and
  • glycated burden.
  • Serum glucose will similarly give way to these tests

Evaluating a new way to open clogged arteries: Computational model offers insight into mechanisms of drug-coated balloons.

A new study from MIT analyzes the potential usefulness of a new treatment that combines the benefits of angioplasty balloons and drug-releasing stents, but may pose fewer risks. With this new approach, a balloon is inflated in the artery for only a brief period, during which it releases a drug that prevents cells from accumulating and clogging the arteries over time.
While approved for limited use in Europe, these drug-coated balloons are still in development in the United States and have not received FDA approval. The MIT study, which models the behavior of the balloons, should help scientists optimize their performance and aid regulators in evaluating their effectiveness and safety.
“Until now, people who evaluate such technology could not distinguish hype from promise,” says Elazer Edelman, the Thomas D. and Virginia W. Cabot Professor of Health Sciences and Technology and senior author of the paper describing the study, which appeared online recently in the journal Circulation.
Lead author of the paper is Vijaya Kolachalama, a former MIT postdoc who is now a principal member of the technical staff at the Charles Stark Draper Laboratory.
Edelman’s lab is investigating a possible alternative to the current treatments: drug-coated balloons. “We’re trying to understand how and when this therapy could work and identify the conditions in which it may not,” Kolachalama says. “It has its merits; it has some disadvantages.”

Modeling drug release

The drug-coated balloons are delivered by a catheter and inflated at the narrowed artery for about 30 seconds, sometimes longer. During that time, the balloon coating, containing a drug such as Zotarolimus, is released from the balloon. The properties of the coating allow the drug to be absorbed in the body’s tissues. Once the drug is released, the balloon is removed.
In their new study, Kolachalama, Edelman and colleagues set out to rigorously characterize the properties of the drug-coated balloons. After performing experiments in tissue grown in the lab and in pigs, they developed a computer model that explains the dynamics of drug release and distribution. They found that factors such as the size of the balloon, the duration of delivery time, and the composition of the drug coating all influence how long the drug stays at the injury site and how effectively it clears the arteries.
One significant finding is that when the drug is released, some of it sticks to the lining of the blood vessels. Over time, that drug is slowly released back into the tissue, which explains why the drug’s effects last much longer than the initial 30-second release period.
“This is the first time we can explain the reasons why drug-coated balloons can work,” Kolachalama says. “The study also offers areas where people can consider thinking about optimizing drug transfer and delivery.”

http://circ.ahajournals.org/content/127/20/2047.short  
http://www.mit.edu/people/vbk/Circulation_2013.pdf 
http://www.sciencedaily.com/…13/05/130521121513.ht…    
Circulation, 2013; 127 (20): 2047 – 2055
http://dx.doi.org/10.1161/CIRCULATIONAHA.113.002051;


Conclusion

MIT’s Edelman’s Lab conducted the pioneering work in Vascular biology, animal models of drug eluting stents and was at the forefront of Empirical Molecular Cardiology in its studies in vascular physiology, biology and biomaterials for medical devices.

Related articles

MUC1* Ligand, NM23-H1, Is a Novel Growth Factor That Maintains Human Stem Cells in a More Naïve State (plosone.org)

Mass. General team develops implantable, bioengineered rat kidney (eurekalert.org)

Suppression of JAK2/STAT3 Signaling Reduces End-to-End Arterial Anastomosis Induced Cell Proliferation in Common Carotid Arteries of Rats (plosone.org)

Blood Vessel Function and Breathing Control Adversely Affected by Cutting Back on Sleep (medindia.net)

miRNA Biogenesis Enzyme Drosha Is Required for Vascular Smooth Muscle Cell Survival (plosone.org)

Cell-Permeable Peptide Shows Promise For Controlling Cardiovascular Disease (medicalnewstoday.com)

The Heart Revolution By Kilmer McCully, Martha McCully

HarperCollinsPublishers, 1969

http://books.google.com/books?id=iYLbuZFxEt8C&pg=PR20&dq=New+York+Times+homocysteine+and+Cholesterol&hl=en&sa=X&ei=_0F7UfDRA8zB4APozIHQAQ&ved=0CEMQ6AEwAg


Other Related Articles that were published on this Open Access Online Scientific Journal include the following:

Modeling Targeted Therapy

Larry H Bernstein, MD, FACP 3/2/2013

Quantum Biology And Computational Medicine

Larry H Bernstein, MD, FACP 4/3/2013

Virtual Biopsy – is it possible?

Larry H Bernstein, MD, FACP 3/3/2013

Reprogramming cell fate  3/2/2013

Larry H Bernstein, MD, FACP

How Methionine Imbalance with Sulfur-Insufficiency Leads to Hyperhomocysteinemia

Larry H Bernstein, MD, FACP 4/4/2013

http://pharmaceuticalintelligence.com/2013/04/04/sulfur-deficiency-and-hyperhomocusteinemia/

Amyloidosis with Cardiomyopathy

Larry H Bernstein, MD, FACP 3/31/2013

http://pharmaceuticalintelligence.com/2013/03/31/amyloidosis-with-cardiomyopathy/

Nitric Oxide, Platelets, Endothelium and Hemostasis

Larry H Bernstein, MD, FACP 11/8/2012

http://pharmaceuticalintelligence.com/2012/11/08/nitric-oxide-platelets-endothelium-and-hemostasis/

Mitochondrial Damage and Repair under Oxidative Stress

Larry H Bernstein, MD, FACP 10/28/2012

http://pharmaceuticalintelligence.com/2012/10/28/mitochondrial-damage-and-repair-under-oxidative-stress/

Endothelial Function and Cardiovascular Disease

Larry H Bernstein, MD, FACP 10/25/2012

http://pharmaceuticalintelligence.com/2012/10/25/endothelial-function-and-cardiovascular-disease/

Endothelial Dysfunction, Diminished Availability of cEPCs, Increasing CVD Risk for Macrovascular Disease –Therapeutic Potential of cEPCs

Aviva Lev-Ari, PhD, RN 8/27/2012

Revascularization: PCI, Prior History of PCI vs CABG

Aviva Lev-Ari, PhD, RN 4/25/2013

http://pharmaceuticalintelligence.com/2013/04/25/revascularization-pci-prior-history-of-pci-vs-cabg/

Cholesteryl Ester Transfer Protein (CETP) Inhibitor: Potential of Anacetrapib to treat Atherosclerosis and CAD

Aviva Lev-Ari, PhD, RN 4/7/2013

http://pharmaceuticalintelligence.com/2013/04/07/cholesteryl-ester-transfer-protein-cetp-inhibitor-potential-of-anacetrapib-to-treat-atherosclerosis-and-cad/

Hypertriglyceridemia concurrent Hyperlipidemia: Vertical Density Gradient Ultracentrifugation a Better Test to Prevent Undertreatment of High-Risk Cardiac Patients

Aviva Lev-Ari, PhD, RN 4/4/2013

http://pharmaceuticalintelligence.com/2013/04/04/hypertriglyceridemia-concurrent-hyperlipidemia-vertical-density-gradient-ultracentrifugation-a-better-test-to-prevent-undertreatment-of-high-risk-cardiac-patients/

Fight against Atherosclerotic Cardiovascular Disease: A Biologics not a Small Molecule – Recombinant Human lecithin-cholesterol acyltransferase (rhLCAT) attracted AstraZeneca to acquire AlphaCore

Aviva Lev-Ari, PhD, RN 4/3/2013

http://pharmaceuticalintelligence.com/2013/04/03/fight-against-atherosclerotic-cardiovascular-disease-a-biologics-not-a-small-molecule-recombinant-human-lecithin-cholesterol-acyltransferase-rhlcat-attracted-astrazeneca-to-acquire-alphacore/

High-Density Lipoprotein (HDL): An Independent Predictor of Endothelial Function & Atherosclerosis, A Modulator, An Agonist, A Biomarker for Cardiovascular Risk

Aviva Lev-Ari, PhD, RN 3/31/2013

http://pharmaceuticalintelligence.com/2013/03/31/high-density-lipoprotein-hdl-an-independent-predictor-of-endothelial-function-artherosclerosis-a-modulator-an-agonist-a-biomarker-for-cardiovascular-risk/

Acute Chest Pain/ER Admission: Three Emerging Alternatives to Angiography and PCI

Aviva Lev-Ari, PhD, RN 3/10/2013

http://pharmaceuticalintelligence.com/2013/03/10/acute-chest-painer-admission-three-emerging-alternatives-to-angiography-and-pci/

Genomics & Genetics of Cardiovascular Disease Diagnoses: A Literature Survey of AHA’s Circulation Cardiovascular Genetics, 3/2010 – 3/2013

Lev-Ari, A. and L H Bernstein 3/7/2013

http://pharmaceuticalintelligence.com/2013/03/07/genomics-genetics-of-cardiovascular-disease-diagnoses-a-literature-survey-of-ahas-circulation-cardiovascular-genetics-32010-32013/

The Heart: Vasculature Protection – A Concept-based Pharmacological Therapy including THYMOSIN

Aviva Lev-Ari, PhD, RN 2/28/2013

http://pharmaceuticalintelligence.com/2013/02/28/the-heart-vasculature-protection-a-concept-based-pharmacological-therapy-including-thymosin/

Arteriogenesis and Cardiac Repair: Two Biomaterials – Injectable Thymosin beta4 and Myocardial Matrix Hydrogel

Aviva Lev-Ari, PhD, RN 2/27/2013

http://pharmaceuticalintelligence.com/2013/02/27/arteriogenesis-and-cardiac-repair-two-biomaterials-injectable-thymosin-beta4-and-myocardial-matrix-hydrogel/

Coronary artery disease in symptomatic patients referred for coronary angiography: Predicted by Serum Protein Profiles

Aviva Lev-Ari, PhD, RN 12/29/2012

http://pharmaceuticalintelligence.com/2012/12/29/coronary-artery-disease-in-symptomatic-patients-referred-for-coronary-angiography-predicted-by-serum-protein-profiles/

Special Considerations in Blood Lipoproteins, Viscosity, Assessment and Treatment

Bernstein, HL and Lev-Ari, A. 11/28/2012

http://pharmaceuticalintelligence.com/2012/11/28/special-considerations-in-blood-lipoproteins-viscosity-assessment-and-treatment/

Peroxisome proliferator-activated receptor (PPAR-gamma) Receptors Activation: PPARγ transrepression for Angiogenesis in Cardiovascular Disease and PPARγ transactivation for Treatment of Diabetes

Aviva Lev-Ari, PhD, RN 11/13/2012

http://pharmaceuticalintelligence.com/2012/11/13/peroxisome-proliferator-activated-receptor-ppar-gamma-receptors-activation-pparγ-transrepression-for-angiogenesis-in-cardiovascular-disease-and-pparγ-transactivation-for-treatment-of-dia/

Clinical Trials Results for Endothelin System: Pathophysiological role in Chronic Heart Failure, Acute Coronary Syndromes and MI – Marker of Disease Severity or Genetic Determination?

Aviva Lev-Ari, PhD, RN 10/19/2012

http://pharmaceuticalintelligence.com/2012/10/19/clinical-trials-results-for-endothelin-system-pathophysiological-role-in-chronic-heart-failure-acute-coronary-syndromes-and-mi-marker-of-disease-severity-or-genetic-determination/

Endothelin Receptors in Cardiovascular Diseases: The Role of eNOS Stimulation

Aviva Lev-Ari, PhD, RN 10/4/2012

http://pharmaceuticalintelligence.com/2012/10/04/endothelin-receptors-in-cardiovascular-diseases-the-role-of-enos-stimulation/

Inhibition of ET-1, ETA and ETA-ETB, Induction of NO production, stimulation of eNOS and Treatment Regime with PPAR-gamma agonists (TZD): cEPCs Endogenous Augmentation for Cardiovascular Risk Reduction – A Bibliography

Aviva Lev-Ari, PhD, RN 10/4/2012

http://pharmaceuticalintelligence.com/2012/10/04/inhibition-of-et-1-eta-and-eta-etb-induction-of-no-production-and-stimulation-of-enos-and-treatment-regime-with-ppar-gamma-agonists-tzd-cepcs-endogenous-augmentation-for-cardiovascular-risk-reduc/

Positioning a Therapeutic Concept for Endogenous Augmentation of cEPCs — Therapeutic Indications for Macrovascular Disease: Coronary, Cerebrovascular and Peripheral

Aviva Lev-Ari, PhD, RN 8/29/2012

http://pharmaceuticalintelligence.com/2012/08/29/positioning-a-therapeutic-concept-for-endogenous-augmentation-of-cepcs-therapeutic-indications-for-macrovascular-disease-coronary-cerebrovascular-and-peripheral/

Cardiovascular Outcomes: Function of circulating Endothelial Progenitor Cells (cEPCs): Exploring Pharmaco-therapy targeted at Endogenous Augmentation of cEPCs

Aviva Lev-Ari, PhD, RN 8/28/2012

http://pharmaceuticalintelligence.com/2012/08/28/cardiovascular-outcomes-function-of-circulating-endothelial-progenitor-cells-cepcs-exploring-pharmaco-therapy-targeted-at-endogenous-augmentation-of-cepcs/

Endothelial Dysfunction, Diminished Availability of cEPCs, Increasing CVD Risk for Macrovascular Disease – Therapeutic Potential of cEPCs

Aviva Lev-Ari, PhD, R N 8/27/2012

http://pharmaceuticalintelligence.com/2012/08/27/endothelial-dysfunction-diminished-availability-of-cepcs-increasing-cvd-risk-for-macrovascular-disease-therapeutic-potential-of-cepcs/

Vascular Medicine and Biology: CLASSIFICATION OF FAST ACTING THERAPY FOR PATIENTS AT HIGH RISK FOR MACROVASCULAR EVENTS Macrovascular Disease – Therapeutic Potential of cEPCs

Aviva Lev-Ari, PhD, RN 8/24/2012

http://pharmaceuticalintelligence.com/2012/08/24/vascular-medicine-and-biology-classification-of-fast-acting-therapy-for-patients-at-high-risk-for-macrovascular-events-macrovascular-disease-therapeutic-potential-of-cepcs/

Cardiovascular Disease (CVD) and the Role of agent alternatives in endothelial Nitric Oxide Synthase (eNOS) Activation and Nitric Oxide Production

Aviva Lev-Ari, PhD, RN 7/19/2012

http://pharmaceuticalintelligence.com/2012/07/19/cardiovascular-disease-cvd-and-the-role-of-agent-alternatives-in-endothelial-nitric-oxide-synthase-enos-activation-and-nitric-oxide-production/

Resident-cell-based Therapy in Human Ischaemic Heart Disease: Evolution in the PROMISE of Thymosin beta4 for Cardiac Repair

Aviva Lev-Ari, PhD, RN 4/30/2012

http://pharmaceuticalintelligence.com/2012/04/30/93/

Triple Antihypertensive Combination Therapy Significantly Lowers Blood Pressure in Hard-to-Treat Patients with Hypertension and Diabetes

Aviva Lev-Ari, PhD, RN 5/29/2012

http://pharmaceuticalintelligence.com/2012/05/29/445/

Macrovascular Disease – Therapeutic Potential of cEPCs: Reduction Methods for CV Risk

Aviva Lev-Ari, PhD, RN 7/2/2012

http://pharmaceuticalintelligence.com/2012/07/02/macrovascular-disease-therapeutic-potential-of-cepcs-reduction-methods-for-cv-risk/

Mitochondria Dysfunction and Cardiovascular Disease – Mitochondria: More than just the “powerhouse of the cell”

Aviva Lev-Ari, PhD, RN 7/9/2012

http://pharmaceuticalintelligence.com/2012/07/09/mitochondria-more-than-just-the-powerhouse-of-the-cell/

Bystolic’s generic Nebivolol – positive effect on circulating Endothelial Proginetor Cells endogenous augmentation

Aviva Lev-Ari, PhD, RN 7/16/2012

http://pharmaceuticalintelligence.com/2012/07/16/bystolics-generic-nebivolol-positive-effect-on-circulating-endothilial-progrnetor-cells-endogenous-augmentation/

Arteriogenesis and Cardiac Repair: Two Biomaterials – Injectable Thymosin beta4 and Myocardial Matrix Hydrogel

Aviva Lev-Ari, PhD, RN 2/27/2013

http://pharmaceuticalintelligence.com/2013/02/27/arteriogenesis-and-cardiac-repair-two-biomaterials-injectable-thymosin-beta4-and-myocardial-matrix-hydrogel/

Cardiac Surgery Theatre in China vs. in the US: Cardiac Repair Procedures, Medical Devices in Use, Technology in Hospitals, Surgeons’ Training and Cardiac Disease Severity”

Aviva Lev-Ari, PhD, RN 1/8/2013

http://pharmaceuticalintelligence.com/2013/01/08/cardiac-surgery-theatre-in-china-vs-in-the-us-cardiac-repair-procedures-medical-devices-in-use-technology-in-hospitals-surgeons-training-and-cardiac-disease-severity/

Heart Remodeling by Design – Implantable Synchronized Cardiac Assist Device: Abiomed’s Symphony

Aviva Lev-Ari, PhD, RN 7/23/2012

http://pharmaceuticalintelligence.com/2012/07/23/heart-remodeling-by-design-implantable-synchronized-cardiac-assist-device-abiomeds-symphony/

Acute Chest Pain/ER Admission: Three Emerging Alternatives to Angiography and PCI

Aviva Lev-Ari, PhD, RN 3/10/2013

http://pharmaceuticalintelligence.com/2013/03/10/acute-chest-painer-admission-three-emerging-alternatives-to-angiography-and-pci/

Dilated Cardiomyopathy: Decisions on implantable cardioverter-defibrillators (ICDs) using left ventricular ejection fraction (LVEF) and Midwall Fibrosis: Decisions on Replacement using late gadolinium enhancement cardiovascular MR (LGE-CMR)

Aviva Lev-Ari, PhD, RN 3/10/2013
http://pharmaceuticalintelligence.com/2013/03/10/dilated-cardiomyopathy-decisions-on-implantable-cardioverter-defibrillators-icds-using-left-ventricular-ejection-fraction-lvef-and-midwall-fibrosis-decisions-on-replacement-using-late-gadolinium/

The Heart: Vasculature Protection – A Concept-based Pharmacological Therapy including THYMOSIN

Aviva Lev-Ari, PhD, RN 2/28/2013
http://pharmaceuticalintelligence.com/2013/02/28/the-heart-vasculature-protection-a-concept-based-pharmacological-therapy-including-thymosin/

FDA Pending 510(k) for The Latest Cardiovascular Imaging Technology

Aviva Lev-Ari, PhD, RN 1/28/2013
http://pharmaceuticalintelligence.com/2013/01/28/fda-pending-510k-for-the-latest-cardiovascular-imaging-technology/

PCI Outcomes, Increased Ischemic Risk associated with Elevated Plasma Fibrinogen not Platelet Reactivity

Aviva Lev-Ari, PhD, RN 1/10/2013
http://pharmaceuticalintelligence.com/2013/01/10/pci-outcomes-increased-ischemic-risk-associated-with-elevated-plasma-fibrinogen-not-platelet-reactivity/

The ACUITY-PCI score: Will it Replace Four Established Risk Scores — TIMI, GRACE, SYNTAX, and Clinical SYNTAX

Aviva Lev-Ari, PhD, RN
http://pharmaceuticalintelligence.com/2013/01/03/the-acuity-pci-score-will-it-replace-four-established-risk-scores-timi-grace-syntax-and-clinical-syntax/

Coronary artery disease in symptomatic patients referred for coronary angiography: Predicted by Serum Protein Profiles

Aviva Lev-Ari, PhD, RN
http://pharmaceuticalintelligence.com/2012/12/29/coronary-artery-disease-in-symptomatic-patients-referred-for-coronary-angiography-predicted-by-serum-protein-profiles/

Heart Renewal by pre-existing Cardiomyocytes: Source of New Heart Cell Growth Discovered

Aviva Lev-Ari, PhD, RN 12/23/2012
http://pharmaceuticalintelligence.com/2012/12/23/heart-renewal-by-pre-existing-cardiomyocytes-source-of-new-heart-cell-growth-discovered/

Cardiovascular Risk Inflammatory Marker: Risk Assessment for Coronary Heart Disease and Ischemic Stroke – Atherosclerosis.

Aviva Lev-Ari, PhD, RN 10/30/2012
http://pharmaceuticalintelligence.com/2012/10/30/cardiovascular-risk-inflammatory-marker-risk-assessment-for-coronary-heart-disease-and-ischemic-stroke-atherosclerosis/

To Stent or Not? A Critical Decision

Aviva Lev-Ari, PhD, RN 10/23/2012
http://pharmaceuticalintelligence.com/2012/10/23/to-stent-or-not-a-critical-decision/

New Definition of MI Unveiled, Fractional Flow Reserve (FFR)CT for Tagging Ischemia

Aviva Lev-Ari, PhD, RN 8/27/2012
http://pharmaceuticalintelligence.com/2012/08/27/new-definition-of-mi-unveiled-fractional-flow-reserve-ffrct-for-tagging-ischemia/

Ethical Considerations in Studying Drug Safety — The Institute of Medicine Report

Aviva Lev-Ari, PhD, RN 8/23/2012
http://pharmaceuticalintelligence.com/2012/08/23/ethical-considerations-in-studying-drug-safety-the-institute-of-medicine-report/

New Drug-Eluting Stent Works Well in STEMI

Aviva Lev-Ari, PhD, RN 8/22/2012
http://pharmaceuticalintelligence.com/2012/08/22/new-drug-eluting-stent-works-well-in-stemi/

Expected New Trends in Cardiology and Cardiovascular Medical Devices

Aviva Lev-Ari, PhD, RN 8/17/2012
http://pharmaceuticalintelligence.com/2012/08/17/expected-new-trends-in-cardiology-and-cardiovascular-medical-devices/

Coronary Artery Disease – Medical Devices Solutions: From First-In-Man Stent Implantation, via Medical Ethical Dilemmas to Drug Eluting Stents

Aviva Lev-Ari, PhD, RN 8/13/2012

http://pharmaceuticalintelligence.com/2012/08/13/coronary-artery-disease-medical-devices-solutions-from-first-in-man-stent-implantation-via-medical-ethical-dilemmas-to-drug-eluting-stents/

Percutaneous Endocardial Ablation of Scar-Related Ventricular Tachycardia

Aviva Lev-Ari, PhD, RN 7/18/2012

http://pharmaceuticalintelligence.com/2012/07/18/percutaneous-endocardial-ablation-of-scar-related-ventricular-tachycardia/

Competition in the Ecosystem of Medical Devices in Cardiac and Vascular Repair: Heart Valves, Stents, Catheterization Tools and Kits for Open Heart and Minimally Invasive Surgery (MIS)

Aviva Lev-Ari, PhD, RN 6/22/2012

http://pharmaceuticalintelligence.com/2012/06/22/competition-in-the-ecosystem-of-medical-devices-in-cardiac-and-vascular-repair-heart-valves-stents-catheterization-tools-and-kits-for-open-heart-and-minimally-invasive-surgery-mis/

Global Supplier Strategy for Market Penetration & Partnership Options (Niche Suppliers vs. National Leaders) in the Massachusetts Cardiology & Vascular Surgery Tools and Devices Market for Cardiac Operating Rooms and Angioplasty Suites

Aviva Lev-Ari, PhD, RN 6/22/2012

http://pharmaceuticalintelligence.com/2012/06/22/global-supplier-strategy-for-market-penetration-partnership-options-niche-suppliers-vs-national-leaders-in-the-massachusetts-cardiology-vascular-surgery-tools-and-devices-market-for-car/

Blood_Vessels

Blood_Vessels (Photo credit: shoebappa)

Visceral Myopathy in Statins

Visceral Myopathy in Statins (Photo credit: Snipergirl)

Medical science has advanced significantly sin...

Medical science has advanced significantly since 1507, when Leonardo da Vinci drew this diagram of the internal organs and vascular systems of a woman. (Photo credit: Wikipedia)

English: Lee Hood, MD, PhD, President and Co-f...

English: Lee Hood, MD, PhD, President and Co-found of the Institute for Systems Biology (Photo credit: Wikipedia)

Read Full Post »

Mitochondrial Dysfunction and Cardiac Disorders

Curator: Larry H Bernstein, MD, FACP

This article is the THIRD in a four-article Series covering the topic of the Roles of the Mitochondria in Cardiovascular Diseases. They include the following;

  • Mitochondria and Cardiovascular Disease: A Tribute to Richard Bing, Larry H Bernstein, MD, FACP

http://pharmaceuticalintelligence.com/2013/04/14/chapter-5-mitochondria-and-cardiovascular-disease/

  • Mitochondrial Metabolism and Cardiac Function, Larry H Bernstein, MD, FACP

http://pharmaceuticalintelligence.com/2013/04/14/mitochondrial-metabolism-and-cardiac-function/

  • Mitochondrial Dysfunction and Cardiac Disorders, Larry H Bernstein, MD, FACP

http://pharmaceuticalintelligence.com/2013/04/14/mitochondrial-dysfunction-and-cardiac-disorders/

http://pharmaceuticalintelligence.com/2013/04/14/reversal-of-cardiac-mitochondrial-dysfunction/

Mitochondrial Metabolism in Impaired Cardiac Function

Mitochondrial Dysfunction and the Heart

Chronically elevated plasma free fatty acid levels in heart failure are associated with
  • decreased metabolic efficiency and cellular insulin resistance.
The mitochondrial theory of aging (MTA) and the free-radical theory of aging (FRTA) are closely related.
They were in fact proposed by the same researcher about 20 years apart. MTA adds
  • the mitochondria and its production of free radicals
  • into the concept that free-radicals damage DNA over time.
Tissue hypoxia, resulting from low cardiac output with or independent of endothelial impairment,
This dysfunctional state causes loss of mitochondrial mass. Therapies aimed at protecting mitochondrial function
  • have shown promise in patients and animal models with heart failure that will be the subject of Chapter III.

Myocardial function in hypertension

Genetic variation in vitamin D-dependent signaling
  • is associated with congestive heart failure in human subjects with hypertension.
Functional polymorphisms were selected from five candidate genes:
  1. CYP27B1,
  2. CYP24A1,
  3. VDR,
  4. REN and
  5. ACE.
Using the Marshfield Clinic Personalized Medicine Research Project,
  • 205 subjects with hypertension and congestive heart failure,
  • 206 subjects with hypertension alone and
  • 206 controls (frequency matched by age and gender) were genotyped.
In the context of hypertension, a SNP in CYP27B1 was associated with congestive heart failure
(odds ratio: 2.14 for subjects homozygous for the C allele; 95% CI: 1.05–4.39).
Genetic variation in vitamin D biosynthesis is associated with increased risk of heart failure.
RA Wilke, RU Simpson, BN Mukesh, SV Bhupathi, et al. Genetic variation in CYP27B1 is associated

Heart Failure and Coronary Circulation

There is a decrease in resting and peak stress myocardial function in chronic heart failure patients,
  • with recovery of skeletal muscle phosphocreatine following exercise induced by perhexiline treatment.
This suggested that mitochondrial deficiencies, caused by excessive free fatty acids (FFAs)
  • underlie a common cardiac and skeletal muscle myopathy in heart failure patients.
Tissue hypoxia in chronic heart failure from inadequate circulation in heart failure
  • increases the oxidative stress in lean body mass and in the heart itself.
The heterodimeric transcription factor hypoxia-inducible factor (HIF)-1
  • induces changes in the transcription of genes that encode proteins involved in the adaptation to hypoxia.
HIF-1 activity depends on levels of the HIF-1a subunit, which has a short half-life.
HIF-1a increases in rats with experimentally induced myocardial infarction together with elevated levels of
  • GLUT1 and haemoxygenase-1 in the peri-infarct region of the heart
The cardiac metabolic response to hypoxia is considered to be
  • a return to a pattern of fetal metabolism, in which
  • carbohydrates predominate as substrates for energy metabolism.
The reliance on carbohydrate energy source is thought to be a result of  the downregulation of PPARa with a decreased activity of
The sarcolemmal fatty acid transporter protein (FATP) levels are also decreased with palmitate oxidation,
  • transitioning away from fatty acid metabolism proportional to the degree of cardiac impairment.
The hypoxic changes of heart failure drives a switch toward
  1. glycolysis and glucose oxidation
  2. restriction of myocardial fatty acid uptake.
Nevertheless, late in the progression of heart failure, substrate metabolism is insufficient to support cardiac function, because
  • the hypoxic failing heart is no longer able to oxidize fats and may also be insulin resistant.
The author surmises that mitochondrial dysfunction caused by tissue hypoxia might be mediated by the
  • proapoptotic protein BCL2/adenovirus E1B 19kDa interacting protein (Bnip)3.
It  is strongly upregulated in response to hypoxia. In the isolated, perfused rat heart, Bnip3 expression was
  • induced after 1h of hypoxia, with Bnip3 integrating into the mitochondria of hypoxic ventricular myocytes.
This resulted in mitochondrial defects associated with
  1. opening of the permeability transition pore, leading to
  2. loss of inner membrane integrity and
  3. loss of mitochondrial mass.

Mitochondrial Dysfunction caused by Bnip3 Precedes Cell Death.

Experimentally induced myocardial ischemia had evidence of contractile dysfunction but preserved viability. A progressive
  • decline in circulating levels of endothelial progenitor cells was documented 3 months following instrumentation (P<0.001).
Quantitative polymerase chain reaction analysis revealed that
  • chronic myocardial ischemia produced a biphasic response in both
    • hypoxic-inducible factor 1 and
    • stromal-derived factor 1 mRNA expression.
While initially unregulated, a gradual decline was observed over time (from day 45 to 90), in
  • hypoxic-inducible factor 1 and
  • stromal-derived factor 1 mRNA expression .
On serial assessment, endothelial progenitor cell migration was progressively impaired in response to chemo-attractant gradients of:
  1. vascular endothelial growth factor (10-200 ng/mL)
  2. and stromal cell-derived factor-1 (10-100 ng/mL) .
Decreased circulating levels and migratory dysfunction of bone marrow derived endothelial progenitor cells
  • were documented in a reproducible clinically relevant model of myocardial ischemia.

Nitric Oxide (NO) in Myocardial Ischemia and Infarct

Nitric oxide (NO) is a free radical with an unpaired electron; it is an important physiologic messenger,
  • produced by nitric oxide synthases, which catalyze the reaction l-arginine to citrulline and NO.
The constitutive isoforms exists in neuronal and endothelial cells and is calcium dependent. Calcium binds to calmodulin and
  1. the calcium calmodulin complex activates the constitutive NO synthase that releases NO,
  2. relaxing smooth muscle cells through activation of guanylate cyclase and the production cGMP.
Therefore, the NO produced has a negative inotropic effect on the heart and is instrumental in the autoregulation of the coronary circulation.
The inducible form of NO synthase (iNOS), mostly produced in macrophages, is activated by cytokines and endotoxin. It eliminates intracellular pathogens,
damaging cells by inhibiting
  1. ATP production
  2. oxidative phosphorylation
  3. DNA synthesis.
In infection, lipopolysaccharide released from bacterial walls, stimulates production of iNOS. The large amount of NO produced
  • causes extensive vasodilation and hypotension.
We sought to assess whether oxidation products of
  • nitric oxide (NO), nitrite (NO2−) and nitrate (NO3−), referred to as NOx,
  • are released by the heart of patients after acute myocardial infarction (AMI) and
  • whether NOx can be determined in peripheral blood of these patients.
Previously we reported that in experimental myocardial infarction (rabbits) NOx is released mainly by inflammatory cells
  • (macrophages) in the myocardium 3 days after onset of  ischemia.
NOx is formed in heart muscle from NO; It originates through the activity of the inducible form of nitric oxide synthase (iNOS).
Eight patients with acute anterior MI and an equal number of controls were studied. Coronary venous blood was obtained by
coronary sinus catheterization; NOx concentrations in coronary sinus, in arterial and peripheral venous plasma were measured.
Left ventricular end-diastolic pressure was determined. Measurements were carried out 24, 48 and 72 h after onset of symptoms.
The type and location of coronary arterial lesions were determined by coronary angiography. Plasma NO3− was reduced to NO2−
by nitrate reductase before determination of NO2− concentration by chemiluminescence.
The results provided evidence that in patients with acute anterior MI, the myocardial production of nitrite and nitrate (NOx) was increased,
  • as well as the coronary arterial–venous difference.
Increased NOx production by the infarcted heart accounted for the increase of NOx concentration in arterial and the peripheral venous plasma.
The peak elevation of NOx occurred on days 2 and 3 after onset of the symptoms, suggesting that NOx production was at least in part the result of
  • production of NO by inflammatory cells (macrophages) in the heart.
The appearance of oxidative products of NO (NO2− and NO3−) in peripheral blood of patients with acute MI is
  • the result of their increased release from infarcted heart during the inflammatory phase of myocardial ischemia.
Further studies are needed to define the clinical value of these observations.
K Akiyama,  A Kimura, H Suzuki, Y Takeyama, …. R Bing.  Production of oxidative products of nitric oxide in infarcted human heart.  J Am Coll Cardiol. 1998;32(2):373-379.   http://dx.doi.org/10.1016/S0735-1097(98)00270-8
OPA1 Mutation and Late-Onset Cardiomyopathy
No cardiac disorders have been described in patients with OPA1 or similar mutations
  • involving the fission/fusion genes as seen in inherited maladies like Charcot–Marie–Tooth disease.
Our results indicate that, at least for OPA1, cardiac abnormalities are not completely
  • manifest until the development of blindness.

The OPA1-mutant mice survived more than 1 year and appeared healthy.

In patients with these diseases, reduced cardiac function may go undetected
secondary to reduced physical activity secondary to loss of vision.
It would be expected that patients with such mutations would have impaired cardiac reserve with
  • reduced ability to respond to high-stress disease states such as myocardial infarction and sepsis.
The OPA1-mutant mice have reduced cardiac reserve, as shown by
  • the lack of response to isoproterenol or to ischemia/reperfusion injury,
This suggests that patients with OPA1 and related inherited mitochondrial diseases
  • should be screened for abnormalities of cardiac function.
Le Chen; T Liu; A Tran; Xiyuan Lu; …AA. Knowlton. OPA1 Mutation and Late-Onset Cardiomyopathy:
Mitochondrial Dysfunction and mtDNA Instability.  http://jaha.ahajournals.org/content/1/5/e003012.full

Oxidative Stress and Mitochondria in the Failing Heart

The major problem in tissue hypoxia in the failing heart is oxidative stress. Reactive oxygen species (ROS), including
  • superoxide,
  • hydroxyl radicals and
  • hydrogen peroxide,
are generated by a number of cellular processes, including
  • mitochondrial electron transport,
  • NADPH oxidase and
  • xanthine dehydrogenase/xanthine oxidase.
The low availability of oxygen, the final receptor of mitochondrial electron transport (ET), results in
  • electron accumulation in the ET chain as the complexes become highly reduced.
A number of experimental and clinical studies have suggested that ROS generation is
  • enhanced in heart failure because of electron leak, and complexes I and II
  • are implicated as the primary sites of this loss.
Prolonged oxidative stress in cardiac failure results in damage to mitochondrial DNA.
The continued ROS generation and consequent cellular injury leads to functional decline.
Thus, mitochondria are both the sources and targets of a cycle of ROS-mediated injury in the failing heart.
Mice with a cardiac/skeletal muscle specific deficiency in the scavenger enzyme superoxide dismutase
  • developed progressive congestive heart failure
  • with defects in mitochondrial respiration.
Oxidative stress in these mice also caused specific morphological changes in cardiac mitochondria
  • characterized by decreased ATP levels,
  • impaired contractility,
  • dramatically restricted exercise capacity and
  • decreased survival.
This was in part corrected by treatment with the antioxidant superoxide dismutase mimetic, namely
  • manganese5,10,15,20-tetrakis-(4-benzoic acid)-porphyrin.
EUK-8, a superoxide dismutase and catalase mimetic improved survival and contractile parameters in a mutant mouse model
  • of pressure overload-induced oxidative stress and heart failure and in wild-type mice subjected to pressure overload.
In addition, mitochondria show
  • functional impairment and
  • morphological disorganization
in the left ventricle of Hypertrophic Cardiomyopathy (HCM)  patients without baseline systolic dysfunction.
These mitochondrial changes were associated with impaired myocardial contractile and relaxation reserves.
A strategy to protect the heart against oxidative stress could lie with
  • the modulation of mitochondrial electron transport itself.
Mild mitochondrial uncoupling may offer a potential cardioprotective effect by decreasing ROS production
  • preventing electron accumulation at complex III and
  • the Fe–S centres of complex I, and may therefore

mtDNA, Autophagy, and Heart Failure

Mitochondria are evolutionary endosymbionts derived from bacteria and contain DNA similar to bacterial DNA.
Mitochondria damaged by external haemodynamic stress are degraded by the autophagy/lysosome system in cardiomyocytes.
Mitochondrial DNA (mtDNA) that escapes from autophagy cell-autonomously leads to Toll-like receptor (TLR) 9-mediated
  • inflammatory responses in cardiomyocytes and
  • is capable of inducing myocarditis and dilated cardiomyopathy.
Cardiac-specific deletion of lysosomal deoxyribonuclease (DNase) II showed no cardiac phenotypes under baseline conditions,
but increased mortality and caused severe myocarditis and dilated cardiomyopathy 10 days after treatment with pressure overload.
Early in the pathogenesis, DNase II-deficient hearts showed
  • infiltration of inflammatory cells
  • increased messenger RNA expression of inflammatory cytokines
  • accumulation of mitochondrial DNA deposits in autolysosomes in the myocardium.
Administration of inhibitory oligodeoxynucleotides against TLR9, which is known to be activated by bacterial DNA6, or ablation of Tlr9
  • attenuated the development of cardiomyopathy in DNase II-deficient mice.
Furthermore, Tlr9 ablation
  • improved pressure overload-induced cardiac dysfunction and
  • inflammation even in mice with wild-type Dnase2a alleles.
These data provide new perspectives on the mechanism of genesis of chronic inflammation in failing hearts.
T Oka, S Hikoso, O Yamaguchi, M Taneike, T Takeda, T Tamai, et al.  Mitochondrial DNA that escapes from autophagy causes inflammation and heart failure.

Mitochondrial Dysfunction Increases Expression of Endothelin-1 and Induces Apoptosis

We developed an in vitro model of mitochondrial dysfunction using rotenone, a mitochondrial respiratory chain complex I inhibitor, and studied
  • preproendothelin-1 gene expression and apoptosis.
Rotenone greatly increased the gene expression of preproendothelin-1 in cardiomyocytes.
This result suggests that the gene expression of preproendothelin-1 is induced by the mitochondrial dysfunction.
Furthermore, treatment of cardiomyocytes with rotenone induced an elevation of caspase-3 activity, and caused a marked
  • increase in DNA laddering, an indication of apoptosis.
In conclusion, it is suggested that mitochondrial impairment in primary cultured cardiomyocytes induced by rotenone in vitro,
  • mimics some of the pathophysiological features of heart failure in vivo, and that ET-1 may have a role in myocardial dysfunction
    • with impairment of mitochondria in the failing heart.

Summary

This review focused on the evidence accumulated to the effect that mitochondria are key players in
  • the progression of congestive heart failure (CHF).
Mitochondria are the primary source of energy in the form of adenosine triphosphate that fuels the contractile apparatus,
  • essential for the mechanical activity and the Starling Effect of the heart.
We evaluate changes in mitochondrial morphology and alterations in the main components of mitochondrial energetics, such as
  • substrate utilization and
  • oxidative phosphorylation,
in the context of their contribution to the chronic energy deficit and mechanical dysfunction in HF.
REFERENCES
Zachman AL, Page JM, Prabhakar G, Guelcher SA, and Sung HJ, “Elucidation of adhesion-dependent spontaneous apoptosis in macrophages using phase separated PEG/polyurethane films.”
Acta Biomater. 2012 Nov 2.    http://dx.doi.org/pii: S1742-7061(12)00530-2. 10.1016/j.actbio.2012.10.038.    http://www.ncbi.nlm.nih.gov/pubmed/23128157

Other Related articles published on this Open Access Scientific Journal, include the following:

Perspectives on Nitric Oxide in Disease Mechanisms: The Nitric Oxide Discovery, Function, and Targeted Therapy  Opportunities, 2013, Aviral Vatsa, PhD and Larry H Bernstein, MD, FACP, Editors, Amazon e-Books (forthcoming). http://pharmaceuticalintelligence.com/biomed-e-books/perspectives-on-nitric-oxide-in-disease-mechanisms-v2/

Mitochondria: More than just the “powerhouse of the cell” Ritu Saxena, Ph.D. Consultants: Aviva Lev-Ari, PhD, RN and Pnina G. Abir-Am, PhD 7/9/2012

http://pharmaceuticalintelligence.com/2012/07/09/mitochondria-more-than-just-the-powerhouse-of-the-cell/

Mitochondrial dynamics and cardiovascular diseases, Ritu Saxena, PhD 11/14/2012
http://pharmaceuticalintelligence.com/2012/11/14/mitochondrial-dynamics-and-cardiovascular-diseases/

Mitochondrial Damage and Repair under Oxidative Stress, Larry H Bernstein, MD, FACP 10/28/2012
http://pharmaceuticalintelligence.com/2012/10/28/mitochondrial-damage-and-repair-under-oxidative-stress/

Mitochondria: Origin from oxygen free environment, role in aerobic glycolysis, metabolic adaptation, Larry H Bernstein, MD, FACP 9/26/2012

http://pharmaceuticalintelligence.com/2012/09/26/mitochondria-origin-from-oxygen-free-environment-role-in-aerobic-glycolysis-metabolic-adaptation/

Ca2+ signaling: transcriptional control, Larry H Bernstein, MD, FACP 3/6/2-13
http://pharmaceuticalintelligence.com/2013/03/06/ca2-signaling-transcriptional-control/

MIT Scientists on Proteomics: All the Proteins in the Mitochondrial Matrix identified, Aviva Lev-Ari, PhD, RN 2/3/2013
http://pharmaceuticalintelligence.com/2013/02/03/mit-scientists-on-proteomics-all-the-proteins-in-the-mitochondrial-matrix-identified/

Nitric Oxide has a ubiquitous role in the regulation of glycolysis -with a concomitant influence on mitochondrial function, Larry H Bernstein, MD, FACP 9/16/2012
http://pharmaceuticalintelligence.com/2012/09/16/nitric-oxide-has-a-ubiquitous-role-in-the-regulation-of-glycolysis-with-a-concomitant-influence-on-mitochondrial-function/

Ubiquinin-Proteosome pathway, autophagy, the mitochondrion, proteolysis and cell apoptosis, Larry H Bernstein, MD, FACP 2/14/2013
http://pharmaceuticalintelligence.com/2013/02/14/ubiquinin-proteosome-pathway-autophagy-the-mitochondrion-proteolysis-and-cell-apoptosis-reconsidered/

Low Bioavailability of Nitric Oxide due to Misbalance in Cell Free Hemoglobin in Sickle Cell Disease – A Computational Model   Anamika Sarkar, PhD 11/9/2012
http://pharmaceuticalintelligence.com/2012/11/09/low-bioavailability-of-nitric-oxide-due-to-misbalance-in-cell-free-hemoglobin-in-sickle-cell-disease-a-computational-model/

The rationale and use of inhaled NO in Pulmonary Artery Hypertension and Right Sided Heart Failure, , Larry H Bernstein, MD, FACP 8/20/2012

http://pharmaceuticalintelligence.com/2012/08/20/the-rationale-and-use-of-inhaled-no-in-pulmonary-artery-hypertension-and-right-sided-heart-failure/

Clinical Trials Results for Endothelin System: Pathophysiological role in Chronic Heart Failure, Acute Coronary Syndromes and MI – Marker of Disease Severity or Genetic Determination? Aviva Lev-Ari, PhD, RN 10/19/2012

http://pharmaceuticalintelligence.com/2012/10/19/clinical-trials-results-for-endothelin-system-pathophysiological-role-in-chronic-heart-failure-acute-coronary-syndromes-and-mi-marker-of-disease-severity-or-genetic-determination/

Endothelin Receptors in Cardiovascular Diseases: The Role of eNOS Stimulation, Aviva Lev-Ari, PhD, RN 10/4/2012

http://pharmaceuticalintelligence.com/2012/10/04/endothelin-receptors-in-cardiovascular-diseases-the-role-of-enos-stimulation/

Inhibition of ET-1, ETA and ETA-ETB, Induction of NO production, stimulation of eNOS and Treatment Regime with PPAR-gamma agonists (TZD): cEPCs Endogenous Augmentation for Cardiovascular Risk Reduction – A Bibliography, Aviva Lev-Ari, PhD, RN 10/4/2012

http://pharmaceuticalintelligence.com/2012/10/04/inhibition-of-et-1-eta-and-eta-etb-induction-of-no-production-and-stimulation-of-enos-and-treatment-regime-with-ppar-gamma-agonists-tzd-cepcs-endogenous-augmentation-for-cardiovascular-risk-reduc/

Genomics & Genetics of Cardiovascular Disease Diagnoses: A Literature Survey of AHA’s Circulation Cardiovascular Genetics, 3/2010 – 3/2013, L H Bernstein, MD, FACP and Aviva Lev-Ari,PhD, RN  3/7/2013

http://pharmaceuticalintelligence.com/2013/03/07/genomics-genetics-of-cardiovascular-disease-diagnoses-a-literature-survey-of-ahas-circulation-cardiovascular-genetics-32010-32013/

Cardiovascular Disease (CVD) and the Role of agent alternatives in endothelial Nitric Oxide Synthase (eNOS) Activation and Nitric Oxide Production, Aviva Lev-Ari, PhD, RN 7/19/2012

http://pharmaceuticalintelligence.com/2012/07/19/cardiovascular-disease-cvd-and-the-role-of-agent-alternatives-in-endothelial-nitric-oxide-synthase-enos-activation-and-nitric-oxide-production/

Cardiovascular Risk Inflammatory Marker: Risk Assessment for Coronary Heart Disease and Ischemic Stroke – Atherosclerosis.

Aviva Lev-Ari, PhD, RN 10/30/2012

http://pharmaceuticalintelligence.com/2012/10/30/cardiovascular-risk-inflammatory-marker-risk-assessment-for-coronary-heart-disease-and-ischemic-stroke-atherosclerosis/

Cholesteryl Ester Transfer Protein (CETP) Inhibitor: Potential of Anacetrapib to treat Atherosclerosis and CAD, Aviva Lev-Ari, PhD, RN 4/7/2013

http://pharmaceuticalintelligence.com/2013/04/07/cholesteryl-ester-transfer-protein-cetp-inhibitor-potential-of-anacetrapib-to-treat-atherosclerosis-and-cad/

Hypertriglyceridemia concurrent Hyperlipidemia: Vertical Density Gradient Ultracentrifugation a Better Test to Prevent Undertreatment of High-Risk Cardiac Patients, Aviva Lev-Ari, PhD, RN  4/4/2013

http://pharmaceuticalintelligence.com/2013/04/04/hypertriglyceridemia-concurrent-hyperlipidemia-vertical-density-gradient-ultracentrifugation-a-better-test-to-prevent-undertreatment-of-high-risk-cardiac-patients/

Fight against Atherosclerotic Cardiovascular Disease: A Biologics not a Small Molecule – Recombinant Human lecithin-cholesterol acyltransferase (rhLCAT) attracted AstraZeneca to acquire AlphaCore, Aviva Lev-Ari, PhD, RN 4/3/2013

http://pharmaceuticalintelligence.com/2013/04/03/fight-against-atherosclerotic-cardiovascular-disease-a-biologics-not-a-small-molecule-recombinant-human-lecithin-cholesterol-acyltransferase-rhlcat-attracted-astrazeneca-to-acquire-alphacore/

High-Density Lipoprotein (HDL): An Independent Predictor of Endothelial Function & Atherosclerosis, A Modulator, An Agonist, A Biomarker for Cardiovascular Risk, Aviva Lev-Ari, PhD, RN 3/31/2013

http://pharmaceuticalintelligence.com/2013/03/31/high-density-lipoprotein-hdl-an-independent-predictor-of-endothelial-function-artherosclerosis-a-modulator-an-agonist-a-biomarker-for-cardiovascular-risk/

Peroxisome proliferator-activated receptor (PPAR-gamma) Receptors Activation: PPARγ transrepression for Angiogenesis in Cardiovascular Disease and PPARγ transactivation for Treatment of Diabetes, Aviva Lev-Ari, PhD, RN 11/13/2012

http://pharmaceuticalintelligence.com/2012/11/13/peroxisome-proliferator-activated-receptor-ppar-gamma-receptors-activation-pparγ-transrepression-for-angiogenesis-in-cardiovascular-disease-and-pparγ-transactivation-for-treatment-of-dia/

Sulfur-Deficiciency and Hyperhomocysteinemia, L H Bernstein, MD, FACP

http://pharmaceuticalintelligence.com/2013/04/04/sulfur-deficiency-and-hyperhomocusteinemia/

Mitochondrial metabolism and cardiac function, L H Bernstein, MD, FACP
Cardiotoxicity and Cardiomyopathy Related to Drugs Adverse Effects, L H Bernstein, MD, FACP
Lp(a) Gene Variant Association, L H Bernstein, MD, FACP

Predicting Drug Toxicity for Acute Cardiac Events, L H Bernstein, MD, FACP

Amyloidosis with Cardiomyopathy, L H Bernstein, MD, FACP

Mitochondria and Cardiovascular Disease: A Tribute to Richard Bing, Larry H Bernstein, MD, FACP

http://pharmaceuticalintelligence.com/2013/04/14/chapter-5-mitochondria-and-cardiovascular-disease/

Mitochondrial Metabolism and Cardiac Function, Larry H Bernstein, MD, FACP

http://pharmaceuticalintelligence.com/2013/04/14/mitochondrial-metabolism-and-cardiac-function/

Mitochondrial Dysfunction and Cardiac Disorders, Larry H Bernstein, MD, FACP

http://pharmaceuticalintelligence.com/2013/04/14/mitochondrial-dysfunction-and-cardiac-disorders/

Reversal of Cardiac mitochondrial dysfunction, Larry H Bernstein, MD, FACP

http://pharmaceuticalintelligence.com/2013/04/14/reversal-of-cardiac-mitochondrial-dysfunction/

Related articles

Diagram taken from the paper "Dissection ...

Diagram taken from the paper “Dissection of mitochondrial superhaplogroup H using coding region SNPs” (Photo credit: Asparagirl)

English: Treatment Guidelines for Chronic Hear...

English: Treatment Guidelines for Chronic Heart Failure (Photo credit: Wikipedia)

Nitric Oxide Synthase

Nitric Oxide Synthase (Photo credit: Wikipedia)

Apoptosis Network

Apoptosis Network (Photo credit: sjcockell)

Read Full Post »

Reversal of Cardiac mitochondrial dysfunction

Curator: Larry H Bernstein, MD, FACP

This article is the FOURTH in a four-article Series covering the topic of the Roles of the Mitochondria in Cardiovascular Diseases. They include the following;

  • Mitochondria and Cardiovascular Disease: A Tribute to Richard Bing, Larry H Bernstein, MD, FACP

http://pharmaceuticalintelligence.com/2013/04/14/chapter-5-mitochondria-and-cardiovascular-disease/

  • Mitochondrial Metabolism and Cardiac Function, Larry H Bernstein, MD, FACP

http://pharmaceuticalintelligence.com/2013/04/14/mitochondrial-metabolism-and-cardiac-function/

  • Mitochondrial Dysfunction and Cardiac Disorders, Larry H Bernstein, MD, FACP

http://pharmaceuticalintelligence.com/2013/04/14/mitochondrial-dysfunction-and-cardiac-disorders/

http://pharmaceuticalintelligence.com/2013/04/14/reversal-of-cardiac-mitochondrial-dysfunction/


Mitochondrial metabolism and cardiac function

There is sufficient evidence to suggest that, even with optimal therapy, there is an

  • attenuation or loss of effectiveness of neurohormonal antagonism as heart failure worsens.

The production of oxygen radicals is increased in the failing heart, whereas

  • normal antioxidant enzyme activities are preserved.

Mitochondrial electron transport is an enzymatic source of oxygen radical generation and

  • can be a therapeutic target against oxidant-induced damage in the failing myocardium.

Therefore, future therapeutic targets

  • must address the cellular and molecular mechanisms that contribute to heart failure.

Furthermore, since  fundamental characteristics of the failing heart are 

  • defective mitochondrial energetics and
  • abnormal substrate metabolism

we might expect that substantial benefit may be derived from the development of therapies aimed at

  • preserving cardiac mitochondrial function and
  • optimizing substrate metabolism.

Nutrition and physiological function

Blockade of electron transport in isolated, perfused guinea pig hearts –
before ischaemia with the reversible complex I inhibitor amobarbital
  • decreased superoxide production and
  • preserved oxidative phosphorylation in cardiac mitochondria,
  • decreased myocardial damage.
But when ascorbic acid was administered orally to chronic heart failure patients, there were improvements
  • in endothelial function but
  • no improvement in skeletal muscle energy metabolism.
Angiotensin I-converting enzyme (ACE) inhibitors with trandolapril treatment  in models of heart failure
  • appear to preserve mitochondrial function
  • improving cardiac energy metabolism and
  • function in rats with chronic heart failure.
Similarly perindopril treatment   – in rat skeletal muscle after myocardial infarction -restored :
  • levels of the mitochondrial biogenesis transcription factors PPARg coactivator-1a and
  • nuclear respiratory factor-2a, and
  • prevented mitochondrial dysfunction
Tissue effects of ACE inhibition, such as
might activate intracellular signalling cascades that
  • stimulate mitochondrial biogenesis and
  • improve energy metabolism.
Clearly, the mechanisms of metabolic regulation by
  • existing cardioprotective agents require further investigation.

Substrate metabolism in the failing heart

Increased sympathetic drive in heart failure patients causes adipose tissue lipolysis, thus
  • elevating plasma FFA concentrations.
Myocardial FFA uptake rates are largely determined by circulating FFA concentrations.
In addition to being a major fuel in heart,
  • fatty acids are ligands for the peroxisome proliferator-activated receptors (PPARs),
    •  members of the nuclear hormone receptor (NHR) family.
One PPAR subtype, PPARa, is highly expressed in heart and skeletal muscle. PPARs regulate gene expression by
binding to response elements in the promoter region of target genes that control fatty acid metabolism, including
It has been known for many years that high plasma FFA concentrations are detrimental to the heart,
  • increasing oxygen consumption for any given workload.
Decreased myocardial oxygen efficiency could result, in part,
  • from the inherent stoichiometric inefficiency of fatty acid oxidation,
  • which accounts for the consumption of 12% more oxygen per ATP synthesized than glucose oxidation.

High levels of plasma FFAs have been associated with increased cardiac UCP3 levels in patients undergoing CABG(Fig) and

  • are believed to activate the uncoupling action of UCP3.

http://htmlimg1.scribdassets.com/8o5pfgywg0lyerj/images/4-244729cb6a.jpg

Fig .  Metabolic modulation of the failing heart can be achieved by inhibiting mitochondrial beta-oxidation with trimetazidine, or
  • free fatty acid (FFA) uptake via the carnitine palmitoyltransferase (CPT) system with perhexiline,
    • giving rise to more oxygen-efficient glucose oxidation.
Alternatively, CPT is inhibited by malonyl-coenzyme A (CoA),
  • synthesized from cytosolic acetyl-CoA by acetyl-CoA  carboxylase.
Pharmacological inhibition, or mutation, of
  • malonyl-CoA decarboxylase, which normally converts malonyl-CoA back to acetyl-CoA,
  • elevates malonyl-CoA levels, inhibiting mitochondrial FFA uptake and thus protects the failing heart.

Nutritional Support for the Mitochondria

Human Studies                                       Animal or In Vitro Studies

Alpha lipoic acid                                                    Resveratrol
Co-Enzyme Q10                                                      EgCG
Acetyl-L-Carnitine                                                Curcumin

Lipoic Acid & Acetyl-L-Carnitine

Alpha lipoic acid is known to be a mitochondrial antioxidant that preserves or improves mitochondrial function.

  •  lipoic acid can prevent arterial calcification, and
  • arterial calcification may be related to mitochondrial dysfunction
  • methods are under study to increase lipoic acid synthase production, the enzyme responsible for making lipoic acid in the body.

Co-Enzyme Q10

It is well known that statin drugs taken for high cholesterol severely reduce CoQ10 levels, and causes other negative cardiovascular side effects.
A  study on CAD patients has shown that over 8 weeks of supplementing with 300mg of CoQ10 reversed

  • mitochondrial dysfunction (as measured by a reduced lactate:pyruvate ratio) and
  • improved endothelial function (as measured by increased flow-mediated dilation)

Other Mitochondrial Antioxidants

Other natural compounds that have been shown to have antioxidant effects in the mitochondria include

  • resveratrol, found in wine and grapes,
  • curcumin from turmeric and
  • EGCG, found abundantly in green tea extract.

But no studies have been conducted for these compounds in CVD.

Metabolic syndrome and serum carotenoids: findings of a cross-sectional study
in Queensland, Australia

Metabolic syndrome and serum carotenoids.

T Coyne, TI Ibiebele, PD Baade, CS McClintock and JE Shaw.
Viertel Center for Research in Cancer Control, Cancer Council Queensland, and School of Public Health,
Queensland University of Technology and University of Queensland, Brisbane, Australia
Several components of the metabolic syndrome are known to be oxidative stress-related conditions
  1. diabetes and
  2. cardiovascular disease,
Carotenoids are compounds derived primarily from plants and several have been shown to be potent antioxidant nutrients.
Both diabetes and cardiovascular disease are known to be oxidative stress-related conditions such that
  • antioxidant nutrients may play a protective role in these conditions.
Several cross–sectional surveys have found lower levels of serum carotenoids among those with impaired glucose metabolism or type 2 diabetes.
Carotenoids are compounds derived primarily from plants, several of which are known to be potent antioxidants.
Epidemiological evidence indicates that some serum carotenoids may play a protective role against the development of chronic diseases such as
  1. atherosclerosis,
  2. stroke,
  3. hypertension,
  4. certain cancers,
  5. inflammatory diseases and
  6. diabetic retinopathy.

The primary carotenoids found in human serum are

  1. α-carotene
  2. β-carotene
  3. β-cryptoxanthin
  4. lutein/zeaxanthin
  5. lycopene.
The aim of this study was to examine the associations between metabolic syndrome status and major serum carotenoids in adult Australians.
Data on the presence of the metabolic syndrome, based on International Diabetes Federation 2005 criteria, were collected from 1523 adults
aged 25 years and over in six randomly selected urban centers in Queensland, Australia, using a cross sectional study design.
The following were determined:
  1. Weight
  2. height
  3. BMI
  4. waist circumference
  5. blood pressure
  6. fasting and 2-34 hour blood glucose
  7. lipids
  8. five serum carotenoids.
Criteria used to assess the number of metabolic syndrome components present in a 171 participant using the
2005 International Diabetes Federation definition are as follows:
Components = 0 -none of the metabolic syndrome components (i.e. abdominal obesity, raised triglyceride,
reduced HDL-cholesterol, raised blood pressure, and impaired fasting plasma glucose) are present;
  1. Components = any 1 one of the five metabolic syndrome components is present ;
  2. Components = 2 – any two of the five components are present;
  3. Components = 3 any three of the components are present;
  4. Components = 4 – any four of the components are present;
  5. Components = 5 = all five metabolic syndrome components are present.
This study investigated the relationships between these five primary serum carotenoids and the metabolic syndrome
in a cross-sectional population-based study in Queensland, Australia.  Distributions of serum carotenoids were skewed
and therefore natural logarithmically transformed to better approximate the normal distribution for regression analyses.
Association between log transformed serum carotenoids as dependent variables and metabolic syndrome status were
assessed using multiple linear regression analysis. Results are reported as back transformed geometric means.
Analysis was performed for each serum carotenoid separately, and the sum of the five carotenoids,
adjusting for the following potential confounders:
  1. age
  2. sex
  3. education
  4. BMI
  5. smoking
  6. alcohol intake
  7. physical activity
  8. vitamin use.
Mean serum alpha-carotene, beta-carotene and the sum of the five carotenoid concentrations were significantly lower (p<0.05)
in persons with the metabolic syndrome (after adjusting for age,sex, education, BMI status, alcohol intake, smoking, physical activity
status and vitamin/mineral use) than persons without the syndrome. Alpha, beta and total carotenoids also decreased significantly
(p<0.05) with increased number of components of the metabolic syndrome, after adjusting for these confounders. These differences
were significant among former smokers and non-smokers, but not in current smokers. Low concentrations of serum
  • alpha-carotene,
  • beta carotene and
  • the sum of five carotenoids
appear to be associated with metabolic syndrome status.
The overall prevalence of the syndrome was 24% and was significantly higher among males than females. As would be expected, significant
differences in prevalence of the syndrome were seen with
  • body mass index
  • waist circumference
  • systolic and diastolic blood pressure
  • blood lipids.
Significant differences were also evident by
  • age group, smoking status, educational status and income.
Income was marginally inversely associated. The prevalence increased with age, and was lower in those with post graduate education.
No significant differences were seen by alcohol intake, physical activity levels,  vitamin usage, or fruit intake. There was actually an
  • inverse relationship between vegetable intake (not fruit) and serum carotenoids.
Those who consumed 4 serves or more of vegetable were less likely to have the metabolic syndrome
  • compared to those who consumed 1 serve or less of vegetables.
The mean concentrations of serum alpha-carotene, beta-carotene and the sum of the five carotenoids were significantly lower for participants
  • with the metabolic syndrome present compared with those without the syndrome, after adjusting for potential confounding variables.
Concentrations of alpha-carotene, beta-carotene and the sum of the five carotenoids decreased significantly as
  • the number of components of the metabolic syndrome increased after adjusting for potential confounding variables.
Similarly there was an inverse association between quartiles of
  • individual and total serum carotenoids and metabolic syndrome status and each of its components.
This study was designed to investigate the association between several serum carotenoids and the metabolic syndrome.
The data from the present population study suggest that several serum carotenoids are inversely related to the metabolic syndrome.
The study showed significantly lower concentrations present among those with the metabolic syndrome of
  1. α-carotene,
  2. β-carotene and
  3. the sum of the five carotenoids
 compared to those without.We also found decreasing concentrations of all the carotenoids tested as

  • the number of the metabolic syndrome components increased.
This was significant for
  1. α-carotene,
  2. β-carotene,
  3. β-cryptoxanthin
  4. total carotenoids.
    (not lycopenes)
These findings are consistent with data reported from the third National Health and Nutrition Examination Survey (NHANES III).
In the NHANES III study, significantly lower concentrations of all the carotenoids, except lycopene, were found among persons
with the metabolic syndrome compared with those without, after adjusting for confounding factors similar to those in our study.

Carnitine: A novel health factor-An overview. 

CD Dayanand, N Krishnamurthy, S Ashakiran, KN Shashidhar
Int J Pharm Biomed Res 2011; 2(2): 79-89.  ISSN No: 0976-0350
Carnitine comprises L-carnitine, acetyl –L-carnitine and Propionyl –L-carnitine. Carnitine is
  • obtained in greater amount from animal dietary sources than from plant sources.
The endogenous synthesis of carnitine takes place in animal tissues like
  • liver
  • kidney
  • brain
using precursor amino acids lysine and methionine by a pathway
  • dependent on iron, vitamin C, niacin, pyridoxine .
This is the basis of vegans generally depending on carnitine in larger proportion
  • through in vivo synthesis than omnivorous subjects.
The concentration of tri-methyl lysine residues and the tissue specificity of  butyro-betaine dehydrogenase
  • plays a significant role in regulating the carnitine biosynthesis.
Carnitine transport from the site of synthesis to target tissue occurs via blood.
The measurement of plasma carnitine concentration represents –
  • the balance between the rate of synthesis and rate of excretion
    • through specific transporter proteins.
The cellular functional role of carnitine depends on the uptake into cells through
  1. carnitine transport proteins and
  2. transport into mitochondrial matrix.
The function of carnitine is to traverse Long-chain Fatty Acids across inner mitochondrial membrane
  • for β-oxidation, thereby, generating ATP.
Carnitine deficiency results in muscle disorders.  The deficiency states are primary and secondar.
The primary is of systemic or myopathic, characterized by a defect of high affinity organic cation transporter protein (CTP)
  • present on the plasma membrane of liver and kidney and
  • also due to dysfunction of carnitine reabsorbtion through
    • similar transport proteins in renal tubules.
Secondary carnitine deficiency is associated with
  1. mitochondrial disorders and also
  2. defective β-oxidation such as CPT-II and acyl CoA dehydrogenase.
In recent times, carnitine has been extensively studied in various research activities to explore the therapeutic benefit.
Thus, carnitine justifies as a novel health factor.

Propionyl-L-carnitine Corrects Metabolic and Cardiovascular Alterations in
Diet-Induced Obese Mice and Improves Liver Respiratory Chain Activity

C Mingorance,  L Duluc, M Chalopin, G Simard, et al.
PLC improved the insulin-resistant state and reversed the increased total cholesterol
but not the increase in free fatty acid, triglyceride and HDL/LDL ratio induced by high-fat diet.
Vehicle-HF exhibited a reduced

  • cardiac output/body weight ratio,
  • endothelial dysfunction and
  • tissue decrease of NO production,

all of them being improved by PLC treatment.
The decrease of hepatic mitochondrial activity by high-fat diet was reversed by PLC.

Oral administration of PLC improves the insulin-resistant state developed by obese animals and
decreases the cardiovascular risk associated with the metabolically impaired mitochondrial function.

Omega-3 Fatty Acid and cardioprotection

The Benefits of Flaxseed    

By Elaine Magee, MPH, RD    WebMD Expert Column
Some call it one of the most powerful plant foods on the planet. There’s some evidence it may help reduce your risk of

  • heart disease, cancer, stroke, and diabetes.

That’s quite a tall order for a tiny seed that’s been around for centuries.

Flaxseed was cultivated in Babylon as early as 3000 BC. In the 8th century, King Charlemagne believed so strongly in the
health benefits of flaxseed that he passed laws requiring his subjects to consume it. Now, thirteen centuries later, some
experts say we have preliminary research to back up what Charlemagne suspected.

http://img.webmd.com/dtmcms/live/webmd/consumer_assets/site_images/article_
thumbnails/features/benefits_of_flaxseed_features/375x321_benefits_of_flaxseed_features.jpg

Not only has consumer demand for flaxseed grown, agricultural use has also increased.
Flaxseed is what’s used to feed all those chickens that are laying eggs with higher levels of omega-3 fatty acids.
Although flaxseed contains all sorts of healthy components, it owes its primary healthy reputation to three of them:

  1. Omega-3 essential fatty acids, have been shown to have heart-healthy effects.  1.8 grams of plant omega-3s/tablespoon ground.
  2. Lignans, which have both plant estrogen and antioxidant qualities.  75 to 800 times more lignans than other plant foods.
  3. Fiber. Flaxseed contains both the soluble and insoluble types.

Omega-3 Polyunsaturated Fatty Acids and Cardiovascular Diseases

CJ Lavie, RV Milani, MR Mehra, and HO Ventura.
J. Am. Coll. Cardiol. 2009;54;585-594.   http://dx.doi.org/10.1016/j.jacc.2009.02.084
Fish oil is obtained in the human diet by eating oily fish, such as
  • herring, mackerel, salmon, albacore tuna, and sardines, or
  • by consuming fish oil supplements or cod liver oil.
Fish do not naturally produce these oils, but obtain them through the ocean food chain from the marine microorganisms
  • that are the original source of the omega-3 polyunsaturated fatty acids (ω-3 PUFA) found in fish oils.
Numerous prospective and retrospective trials from many countries, including the U.S., have shown that moderate
  • fish oil consumption decreases the risk of major cardiovascular (CV) events, such as
  1. myocardial infarction (MI),
  2. sudden cardiac death (SCD),
  3. coronary heart disease (CHD),
  4. atrial fibrillation (AF), and most recently,
  5. death in patients with heart failure (HF).
Most of the evidence for benefits of the ω-3 PUFA has been obtained for
  • eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA), the long-chain fatty acids in this family.
There is support for a benefit from alpha-linolenic acid (ALA),
  • the plant-based precursor of EPA.
The American Heart Association (AHA) has currently endorsed the use of ω-3 PUFA in patients with documented CHD

  • at a dose of approximately 1 g/day of combined DHA and EPA, either in the form of fatty fish or fish oil supplements
The health benefits of these long chain fatty acids are numerous and remain an active area of research.
Omega-3 polyunsaturated fatty acid (ω-3 PUFA) therapy continues to show great promise in primary and,
  • particularly in secondary prevention of cardiovascular (CV) diseases.
This portion of discussion summarizes the current scientific data on the effects of the long chain ω-3 PUFA
  • in the primary and secondary prevention of various CV disorders.
The most compelling evidence for CV benefits of ω-3 PUFA comes from 4 controlled trials
  • of nearly 40,000 participants randomized to receive eicosapentaenoic acid (EPA)
  • with or without docosahexaenoic acid (DHA) in studies of patients
    • in primary prevention,
    • after myocardial infarction, and
    • with heart failure (HF).
The evidence from retrospective epidemiologic studies and from large randomized controlled trials
show the benefits of ω-3 PUFA, specifically EPA and DHA, in primary and secondary CV prevention
and provide insight into potential mechanisms of these observed benefits.

Background Epidemiologic Evidence

During the past 3 decades, numerous epidemiologic and observational studies have been published on the CV benefits of ω-3 PUFA.
As early as 1944, Sinclair described the rarity of CHD in Greenland Eskimos, who consumed a diet high in whale, seal, and fish.
More than 30 years ago, Bang and Dyberg reported that despite a diet low in fruit, vegetables, and complex carbohydrates but
high in saturated fat and cholesterol, serum cholesterol and triglycerides were lower in Greenland Inuit than in age-matched residents
of Denmark, and the risk of MI was markedly lower in the Greenland population compared with the Danes. These initial observations raised
speculation on the potential benefits of ω-3 PUFA (particularly EPA and DHA) as the protective “Eskimo factor”.
Potential EPA and DHA Effects   
  1. Antiarrhythmic effects
  2. Improvements in autonomic function
  3. Decreased platelet aggregation
  4. Vasodilation
  5. Decreased blood pressure
  6. Anti-inflammatory effects
  7. Improvements in endothelial function
  8. Plaque stabilization
  9. Reduced atherosclerosis
  10. Reduced free fatty acids and triglycerides
  11. Up-regulated adiponectin synthesis
  12. Reduced collagen deposition
The target EPA + DHA consumption should be at least 500 mg/day for individuals without underlying overt CV disease
  • and at least 800 to 1,000 mg/day for individuals with known coronary heart disease and HF.
Further studies are needed to determine optimal dosing and the relative ratio of DHA and EPA ω-3 PUFA that
  • provides maximal cardioprotection in those at risk of CV disease
  • as well in the treatment of atherosclerotic, arrhythmic, and primary myocardial disorders.
Lavie et al.  Omega-3 PUFA and CV Diseases  J Am Coll Cardiol 2009; 54(7): 585–94

Assessing Appropriateness of Lipid Management Among Patients With Diabetes Mellitus

Moving From Target to Treatment.   AJ Beard, TP Hofer, JR Downs, et al. and Diabetes Clinical Action Measures Workgroup
Performance measures that emphasize only a treat-to-target approach may motivate ove-rtreatment with high-dose statins,
  • potentially leading to adverse events and unnecessary costs.
We developed a clinical action performance measure for lipid management in patients with diabetes mellitus that is designed
  • to encourage appropriate treatment with moderate-dose statins while minimizing over-treatment.
We examined data from July 2010 to June 2011 for 964 818 active Veterans Affairs primary care patients ≥18 years of age with diabetes mellitus.
We defined 3 conditions as successfully meeting the clinical action measure for patients 50 to 75 years old:
  1.  having a low-density lipoprotein (LDL) <100 mg/dL,
  2. taking a moderate-dose statin regardless of LDL level or measurement, or
  3. receiving appropriate clinical action (starting, switching, or intensifying statin therapy) if LDL is ≥100 mg/dL.
We examined possible over-treatment for patients ≥18 years of age by examining the proportion of patients
  • without ischemic heart disease who were on a high-dose statin.
We then examined variability in measure attainment across 881 facilities using 2-level hierarchical multivariable logistic models.
Of 668 209 patients with diabetes mellitus who were 50 to 75 years of age, 84.6% passed the clinical action measure:
  1. 67.2% with LDL <100 mg/dL,
  2. 13.0% with LDL ≥100 mg/dL and either on a moderate-dose statin (7.5%) or with appropriate clinical action (5.5%), and
  3. 4.4% with no index LDL on at least a moderate-dose statin. Of the entire cohort ≥18 years of age, 13.7% were potentially over-treated.
Use of a performance measure that credits appropriate clinical action indicates that almost 85% of diabetic veterans 50 to 75 years of age
  • are receiving appropriate dyslipidemia management.

Exercise training and mitochondria in heart failure

The beneficial effects of exercise in the rehabilitation of patients with heart failure are well established,
with improvements observed in
  • exercise capacity,
  • quality of life,
  • hospitalization rates and
  • morbidity/mortality.
There is no evidence of training-induced
improvements in cardiac energy metabolism or
  • mitochondrial function, and
  • no modification of myocardial oxidative capacity,
  • oxidative enzymes, or
  • energy transfer enzymes
in exercising rats with experimental heart failure, but there is  evidence of
There are also improvements in
  • skeletal muscle oxidative capacity with
  • increased mitochondrial density
following endurance training in heart failure patients associated with alleviation of symptoms such as
  • exercise intolerance and
  • chronic fatigue.
The mechanism underlying improvements in mitochondrial function may perhaps be a result of
  • more effective peripheral oxygen delivery following training,
  • alleviating tissue hypoxia and oxidative stress.

Treating Type 2 diabetes, and lowering cardiovascular disease risk

Treating Diabetes and Obesity with an FGF21-Mimetic Antibody
Activating the βKlotho/FGFR1c Receptor Complex

IN Foltz, S Hu, C King, Xinle Wu, et al.  Amgen and Texas A&M HSC, Houston, TX.
Sci Transl Med  Nov 2012; 4(162), p. 162ra153
http://dx.doi.org/10.1126/scitranslmed.3004690

Fibroblast growth factor 21 (FGF21) is a distinctive member of the FGF family with potent beneficial effects on

  1. lipid
  2. body weight
  3. glucose metabolism

A monoclonal antibody, mimAb1, binds to βKlotho with high affinity and specifically

  • activates signaling from the βKlotho/FGFR1c (FGF receptor 1c) receptor complex.

Injection of mimAb1 into obese cynomolgus monkeys led to FGF21-like metabolic effects:

  1. decreases in body weight,
  2. plasma insulin,
  3. triglycerides, and
  4. glucose during tolerance testing.

Mice with adipose-selective FGFR1 knockout were refractory to FGF21-induced improvements

  • in glucose metabolism and body weight.

mimAb1 depends on βKlotho to activate FGFR1c, but

  • it is not expected to induce side effects caused by activating FGFR1c alone.

The results in obese monkeys (with mimAb1) and in FGFR1 knockout mice (with FGF21) demonstrated

  • the essential role of FGFR1c in FGF21 function and
  • suggest fat as a critical target tissue for the cytokine and antibody.

This antibody activates FGF21-like signaling through cell surface receptors, and  provided

  • preclinical validation for an innovative therapeutic approach to diabetes and obesity.

Influencing Factors on Cardiac Structure and Function Beyond Glycemic Control
in Patients With Type 2 Diabetes Mellitus (T2DM)

R Ichikawa, M Daimon, T Miyazaki, T Kawata, et al.     Cardiovasc Diabetol. 2013;12(38)

We studied 148 asymptomatic patients with T2DM without overt heart disease.
Early (E) and late (A) diastolic mitral flow velocity and early diastolic mitral annular velocity (e’)

  • were measured for assessing left ventricular (LV) diastolic function.

In addition

  • insulin resistance,
  • non-esterified fatty acid,
  • high-sensitive CRP,
  • estimated glomerular filtration rate,
  • waist/hip ratio,
  • abdominal visceral adipose tissue (VAT),
  • subcutaneous adipose tissue (SAT)

In T2DM (compared to controls),

  • E/A and e’ were significantly lower, and
  • E/e’, left atrial volume and LV mass were significantly greater

VAT  and age were independent determinants of

  • left atrial volume (β =0.203, p=0.011),
  • E/A (β =−0.208, p=0.002), e’ (β =−0.354, p<0.001) and
  • E/e’ (β=0.220, p=0.003).

Independent determinants of LV mass were

  • systolic blood pressure,
  • waist-hip ratio (β=0.173, p=0.024)
  • VAT/SAT ratio (β=0.162, p=0.049)

Excessive visceral fat accompanied by adipocyte dysfunction may play a greater role than

  • glycemic control in the development of diastolic dysfunction and LV hypertrophy in T2DM

Inhibition of oxidative stress and mtDNA damage

Novel pharmacological agents are needed that

  • optimize substrate metabolism and
  • maintain mitochondrial integrity,
  • improve oxidative capacity in heart and skeletal muscle, and
  • alleviate many of the clinical symptoms associated with heart failure.

The evidence for the attenuation or loss of effectiveness of neurohormonal antagonism as heart failure worsens

  • indicates future therapeutic targets must address the cellular and molecular mechanisms that contribute to heart failure.

Pharmacological Targets of oxidative stress and mitochondrial damage

Defective mitochondrial energetics and abnormal substrate metabolism are fundamental characteristics of CHF.

A significant benefit may be derived from developing therapies aimed at

  • preserving cardiac mitochondrial function and
  • optimizing substrate metabolism.
Oxidative stress is enhanced in myocardial remodelling and failure. The increased production of oxygen radicals in the failing heart
  • with preserved antioxidant enzyme activities suggests
  • mitochondrial electron transport as a source of oxygen radical generation
  • can be a therapeutic target against oxidant-induced damage in the failing myocardium.
Chronic increases in oxygen radical production in the mitochondria
  • leads to mitochondrial DNA (mtDNA) damage,
  • functional decline,
  • further oxygen radical generation, and
  • cellular injury.
MtDNA defects may thus play an important role in the
  • development and progression of myocardial remodelling and failure.
Reactive oxygen species induce
  1. myocyte hypertrophy,
  2. apoptosis, and
  3. interstitial fibrosis
  4. by activating matrix metallo-proteinases,
  5. promoting the development and
  6. progression of maladaptive myocardial remodelling and failure.
Oxidative stress has direct effects on cellular structure and function and
  • may activate integral signalling molecules in myocardial remodelling and failure (Figure).
ROS result in a phenotype characterized by
  • hypertrophy and apoptosis in isolated cardiac myocytes.
Therefore, oxidative stress and mtDNA damage are good therapeutic targets.
Overexpression of the genes for
  • peroxiredoxin-3 (Prx-3), a mitochondrial antioxidant, or
  • mitochondrial transcription factor A (TFAM),
    • could ameliorate the decline in mtDNA copy number in failing hearts.
Consistent with alterations in mtDNA, the
  • decrease in mitochondrial function was prevented,
  • proving that the activation of Prx-3 or TFAM gene expression
  • could ameliorate the pathophysiological processes seen
  1. in mitochondrial dysfunction and
  2. myocardial remodelling.
Inhibition of oxidative stress and mtDNA damage
  • could be novel and effective treatment strategies for heart failure.
Proposed mechanisms through which overexpression of the
  • mitochondrial transcription factor A (TFAM) gene prevents
  • mitochondrial DNA (mtDNA) damage,
  • oxidative stress, and
  • myocardial remodelling and failure.
In wild-type mice, mitochondrial transcription factor A
  • directly interacts with mitochondrial DNA to form nucleoids.
Stress such as ischaemia causes mitochondrial DNA damage, which
  1. increases the production of reactive oxygen species (ROS)
  2. leading to a catastrophic cycle of mitochondrial electron transport impairment,
  3. further reactive oxygen species generation, and mitochondrial dysfunction.
TFAM overexpression may protect mitochondrial DNA from damage by
  1. directly binding and stabilizing mitochondrial DNA and
  2. increasing the steady-state levels of mitochondrial DNA
ameliorating mitochondrial dysfunction and thus the development and progression of heart failure.

Conclusion

Heart failure is a multifactorial syndrome that is characterized by
  • abnormal energetics and substrate metabolism in heart and skeletal muscle.
Although existing therapies have been beneficial, there is a clear need for new approaches to treatment.
Pharmacological targeting of the cellular stresses underlying mitochondrial dysfunction, such as
  • elevated fatty acid levels,
  • tissue hypoxia and oxidative stress and
  • metabolic modulation of heart and skeletal muscle mitochondria,
    • appears to offer a promising therapeutic strategy for tackling heart failure.
Murray AJ, Anderson RE, Watson GC, et al. Uncoupling proteins in human heart. Lancet 2004; 364:1786.
Delarue J, Magnan C. Free fatty acids and insulin resistance. Curr Opin ClinNutr Metab Care 2007; 10:142
Lee L, Campbell R, Scheuermann-Freestone M, et al. Metabolic modulation with perhexiline in chronic heart failure: a randomized, controlled trialof short-term use of a novel treatment. Circulation 2005; 112:3280
Tsutsui H, Kinugawa S, Matsushima S. Mitochondrial oxidative stress and dysfunction in myocardial remodelling. Cardiovasc Res. 2009;81(3):449-56. http://dxdoi.org/10.1093/cvr/cvn280.
C Maack, M Böhm. Targeting Mitochondrial Oxidative Stress in Heart Failure. J Am Coll Cardiol. 2011;58(1):83-86. http://dx.doi.org/10.1016/j.jacc.2011.01.032

 References

Mitochondrial dynamics and cardiovascular diseases    Ritu Saxena
http://pharmaceuticalintelligence.com/2012/11/14/mitochondrial-dynamics-and-cardiovascular-diseases/

Mitochondrial Damage and Repair under Oxidative Stress   larryhbern
http://pharmaceuticalintelligence.com/2012/10/28/mitochondrial-damage-and-repair-under-oxidative-stress/

Mitochondria: Origin from oxygen free environment, role in aerobic glycolysis, metabolic adaptation   larryhbern
http://pharmaceuticalintelligence.com/2012/09/26/mitochondria-origin-from-oxygen-free-environment-role-in-aerobic-glycolysis-metabolic-adaptation/

Ca2+ signaling: transcriptional control     larryhbern
http://pharmaceuticalintelligence.com/2013/03/06/ca2-signaling-transcriptional-control/

MIT Scientists on Proteomics: All the Proteins in the Mitochondrial Matrix identified  Aviva Lev-Ari
http://pharmaceuticalintelligence.com/2013/02/03/mit-scientists-on-proteomics-all-the-proteins-in-the-mitochondrial-matrix-identified/

Nitric Oxide has a ubiquitous role in the regulation of glycolysis -with a concomitant influence on mitochondrial function    larryhbern
http://pharmaceuticalintelligence.com/2012/09/16/nitric-oxide-has-a-ubiquitous-role-in-the-regulation-of-glycolysis-with-a-concomitant-influence-on-mitochondrial-function/

Ubiquinin-Proteosome pathway, autophagy, the mitochondrion, proteolysis and cell apoptosis  larryhbern
http://pharmaceuticalintelligence.com/2013/02/14/ubiquinin-proteosome-pathway-autophagy-the-mitochondrion-proteolysis-and-cell-apoptosis-reconsidered/

Low Bioavailability of Nitric Oxide due to Misbalance in Cell Free Hemoglobin in Sickle Cell Disease – A Computational Model   Anamika Sarkar
http://pharmaceuticalintelligence.com/2012/11/09/low-bioavailability-of-nitric-oxide-due-to-misbalance-in-cell-free-hemoglobin-in-sickle-cell-disease-a-computational-model/

The rationale and use of inhaled NO in Pulmonary Artery Hypertension and Right Sided Heart Failure    larryhbern
http://pharmaceuticalintelligence.com/2012/08/20/the-rationale-and-use-of-inhaled-no-in-pulmonary-artery-hypertension-and-right-sided-heart-failure/

Mitochondria and Cardiovascular Disease: A Tribute to Richard Bing, Larry H Bernstein, MD, FACP
http://pharmaceuticalintelligence.com/2013/04/14/chapter-5-mitochondria-and-cardiovascular-disease/

Mitochondrial Metabolism and Cardiac Function, Larry H Bernstein, MD, FACP
http://pharmaceuticalintelligence.com/2013/04/14/mitochondrial-metabolism-and-cardiac-function/

Mitochondrial Dysfunction and Cardiac Disorders, Larry H Bernstein, MD, FACP
http://pharmaceuticalintelligence.com/2013/04/14/mitochondrial-dysfunction-and-cardiac-disorders/

Reversal of Cardiac mitochondrial dysfunction, Larry H Bernstein, MD, FACP
http://pharmaceuticalintelligence.com/2013/04/14/reversal-of-cardiac-mitochondrial-dysfunction/

Clinical Trials Results for Endothelin System: Pathophysiological role in Chronic Heart Failure, Acute Coronary Syndromes and MI – Marker of Disease Severity or Genetic Determination? Aviva Lev-Ari, PhD, RN 10/19/2012
http://pharmaceuticalintelligence.com/2012/10/19/clinical-trials-results-for-endothelin-system-pathophysiological-role-in-chronic-heart-failure-acute-coronary-syndromes-and-mi-marker-of-disease-severity-or-genetic-determination/

Endothelin Receptors in Cardiovascular Diseases: The Role of eNOS Stimulation, Aviva Lev-Ari, PhD, RN 10/4/2012
http://pharmaceuticalintelligence.com/2012/10/04/endothelin-receptors-in-cardiovascular-diseases-the-role-of-enos-stimulation/

Inhibition of ET-1, ETA and ETA-ETB, Induction of NO production, stimulation of eNOS and Treatment Regime with PPAR-gamma agonists (TZD): cEPCs Endogenous Augmentation for Cardiovascular Risk Reduction – A Bibliography, Aviva Lev-Ari, PhD, RN 10/4/2012
http://pharmaceuticalintelligence.com/2012/10/04/inhibition-of-et-1-eta-and-eta-etb-induction-of-no-production-and-stimulation-of-enos-and-treatment-regime-with-ppar-gamma-agonists-tzd-cepcs-endogenous-augmentation-for-cardiovascular-risk-reduc/

Genomics & Genetics of Cardiovascular Disease Diagnoses: A Literature Survey of AHA’s Circulation Cardiovascular Genetics, 3/2010 – 3/2013, L H Bernstein, MD, FACP and Aviva Lev-Ari,PhD, RN  3/7/2013
http://pharmaceuticalintelligence.com/2013/03/07/genomics-genetics-of-cardiovascular-disease-diagnoses-a-literature-survey-of-ahas-circulation-cardiovascular-genetics-32010-32013/

Cardiovascular Disease (CVD) and the Role of agent alternatives in endothelial Nitric Oxide Synthase (eNOS) Activation and Nitric Oxide Production, Aviva Lev-Ari, PhD, RN 7/19/2012 http://pharmaceuticalintelligence.com/2012/07/19/cardiovascular-disease-cvd-and-the-role-of-agent-alternatives-in-endothelial-nitric-oxide-synthase-enos-activation-and-nitric-oxide-production/

Cardiovascular Risk Inflammatory Marker: Risk Assessment for Coronary Heart Disease and Ischemic Stroke – Atherosclerosis. Aviva Lev-Ari, PhD, RN 10/30/2012
http://pharmaceuticalintelligence.com/2012/10/30/cardiovascular-risk-inflammatory-marker-risk-assessment-for-coronary-heart-disease-and-ischemic-stroke-atherosclerosis/

Cholesteryl Ester Transfer Protein (CETP) Inhibitor: Potential of Anacetrapib to treat Atherosclerosis and CAD.     Aviva Lev-Ari, PhD, RN 4/7/2013
http://pharmaceuticalintelligence.com/2013/04/07/cholesteryl-ester-transfer-protein-cetp-inhibitor-potential-of-anacetrapib-to-treat-atherosclerosis-and-cad/

Hypertriglyceridemia concurrent Hyperlipidemia: Vertical Density Gradient Ultracentrifugation a Better Test to Prevent Undertreatment of High-Risk Cardiac Patients, Aviva Lev-Ari, PhD, RN  4/4/2013  http://pharmaceuticalintelligence.com/2013/04/04/hypertriglyceridemia-concurrent-hyperlipidemia-vertical-density-gradient-ultracentrifugation-a-better-test-to-prevent-undertreatment-of-high-risk-cardiac-patients/

Fight against Atherosclerotic Cardiovascular Disease: A Biologics not a Small Molecule – Recombinant Human lecithin-cholesterol acyltransferase (rhLCAT) attracted AstraZeneca to acquire AlphaCore.
Aviva Lev-Ari, PhD, RN 4/3/2013
http://pharmaceuticalintelligence.com/2013/04/03/fight-against-atherosclerotic-cardiovascular-disease-a-biologics-not-a-small-molecule-recombinant-human-lecithin-cholesterol-acyltransferase-rhlcat-attracted-astrazeneca-to-acquire-alphacore/

High-Density Lipoprotein (HDL): An Independent Predictor of Endothelial Function & Atherosclerosis, A Modulator, An Agonist, A Biomarker for Cardiovascular Risk.   Aviva Lev-Ari, PhD, RN 3/31/2013
http://pharmaceuticalintelligence.com/2013/03/31/high-density-lipoprotein-hdl-an-independent-predictor-of-endothelial-function-artherosclerosis-a-modulator-an-agonist-a-biomarker-for-cardiovascular-risk/

Peroxisome proliferator-activated receptor (PPAR-gamma) Receptors Activation: PPARγ transrepression for Angiogenesis in Cardiovascular Disease and PPARγ transactivation for Treatment of Diabetes.
Aviva Lev-Ari, PhD, RN 11/13/2012
http://pharmaceuticalintelligence.com/2012/11/13/peroxisome-proliferator-activated-receptor-ppar-gamma-receptors-activation-pparγ-transrepression-for-angiogenesis-in-cardiovascular-disease-and-pparγ-transactivation-for-treatment-of-dia/

Sulfur-Deficiciency and Hyperhomocysteinemia, L H Bernstein, MD, FACP
http://pharmaceuticalintelligence.com/2013/04/04/sulfur-deficiency-and-hyperhomocusteinemia/

Structure of the human mitochondrial genome.

Structure of the human mitochondrial genome. (Photo credit: Wikipedia)

English: Treatment Guidelines for Chronic Hear...

English: Treatment Guidelines for Chronic Heart Failure (Photo credit: Wikipedia)

English: Oxidative stress process Italiano: Pr...

English: Oxidative stress process Italiano: Processo dello stress ossidativo (Photo credit: Wikipedia)

Diagram taken from the paper "Dissection ...

Diagram taken from the paper “Dissection of mitochondrial superhaplogroup H using coding region SNPs” (Photo credit: Asparagirl)

Read Full Post »

Reporter: Aviva Lev-Ari, PhD, RN

Walking Versus Running for Hypertension, Cholesterol, and Diabetes Mellitus Risk Reduction

  1. Paul T. Williams,
  2. Paul D. Thompson


From the Life Sciences Division, Lawrence Berkeley National Laboratory, Berkeley, CA (P.T.W.); and Division of Cardiology, Hartford Hospital, Hartford, CT (P.D.T.).
 

Correspondence to Paul T. Williams, PhD, Life Sciences Division, Lawrence Berkeley National Laboratory, Donner 464, 1 Cycloton Rd, Berkeley, CA 94720. E-mailptwilliams@lbl.gov
Abstract

Objective—To test whether equivalent energy expenditure by moderate-intensity (eg, walking) and vigorous-intensity exercise (eg, running) provides equivalent health benefits.

Approach and Results—We used the National Runners’ (n=33 060) and Walkers’ (n=15 945) Health Study cohorts to examine the effect of differences in exercise mode and thereby exercise intensity on coronary heart disease (CHD) risk factors. Baseline expenditure (metabolic equivant hours per day [METh/d]) was compared with self-reported, physician-diagnosed incident hypertension, hypercholesterolemia, diabetes mellitus, and CHD during 6.2 years follow-up. Running significantly decreased the risks for incident hypertension by 4.2% (P<10−7), hypercholesterolemia by 4.3% (P<10−14), diabetes mellitus by 12.1% (P<10−5), and CHD by 4.5% per METh/d (P=0.05). The corresponding reductions for walking were 7.2% (P<10−7), 7.0% (P<10−8), 12.3% (P<10−4), and 9.3% (P=0.01). Relative to <1.8 METh/d, the risk reductions for 1.8 to 3.6, 3.6 to 5.4, 5.4 to 7.2, and ≥7.2 METh/d were as follows: (1) 10.0%, 17.7%, 25.1%, and 34.9% from running and 14.0%, 23.8%, 21.8%, and 38.3% from walking for hypercholesterolemia; (2) 19.7%, 19.4%, 26.8%, and 39.8% from running and 14.7%, 19.1%, 23.6%, and 13.3% from walking for hypertension; and (3) 43.5%, 44.1%, 47.7%, and 68.2% from running, and 34.1%, 44.2% and 23.6% from walking for diabetes mellitus (walking >5.4 METh/d excluded for too few cases). The risk reductions were not significantly different for running than walking for diabetes mellitus (P=0.94), hypercholesterolemia (P=0.06), or CHD (P=0.26), and only marginally greater for walking than running for hypercholesterolemia (P=0.04).

Conclusions—Equivalent energy expenditures by moderate (walking) and vigorous (running) exercise produced similar risk reductions for hypertension, hypercholesterolemia, diabetes mellitus, and possibly CHD.

http://atvb.ahajournals.org/content/early/2013/04/04/ATVBAHA.112.300878.abstract.html?papetoc

Read Full Post »

Hypertriglyceridemia concurrent Hyperlipidemia: Vertical Density Gradient Ultracentrifugation a Better Test to Prevent Undertreatment of High-Risk Cardiac Patients

Curator: Aviva Lev-Ari, PhD, RN

Equation May Give Wrong LDL Status

By Todd Neale, Senior Staff Writer, MedPage Today

Published: March 28, 2013

Reviewed by Robert Jasmer, MD; Associate Clinical Professor of Medicine, University of California, San Francisco and Dorothy Caputo, MA, BSN, RN, Nurse Planner

  • The widely used Friedewald equation may be underestimating LDL cholesterol levels in many patients, a study found.
  • Note that 14.6% of the patients in the study were placed into different treatment groups by the Friedewald estimates and direct measurements, mainly due to classification in a lower LDL cholesterol treatment group by Friedewald compared with direct LDL cholesterol.

After excluding the patients who had a triglyceride level of 400 mg/dL or greater — in whom there are known limitations of the Friedewald equation — the researchers examined data from 1,310,440 adults (mean age 59) who underwent lipid screening; 14.6% had a Friedewald-estimated LDL cholesterol level of less than 70 mg/dL, the treatment target for high-risk patients.

“Nevertheless, non-HDL cholesterol and apolipoprotein B are alternative approaches, with potential advantages over any measure of LDL cholesterol, and these measures avoid confusion that arises in defining LDL cholesterol …,” they wrote. “Moreover, in clinical trial patients with LDL cholesterol levels in the high-risk range highlighted in our study, non-HDL cholesterol and apolipoprotein B were stronger markers of residual risk than Friedewald LDL cholesterol.”

Martin S, et al “Friedewald estimated versus directly measured low-density lipoprotein cholesterol and treatment implications” J Am Coll Cardiol 2013; DOI: 10.1016/j.jacc.2013.01.079.

VIEW VIDEO: Biomarker Series: Lipoprotein A — WellnessFX

VIEW VIDEO:  BioMarker Series: Apolipoprotein B — WellnessFX

The widely used Friedewald equation may be underestimating LDL cholesterol levels in many patients, researchers found.

The discrepancy between LDL cholesterol values that were estimated by the Friedewald equation and those that were directly measured was greatest when LDL cholesterol levels were low and triglyceride levels were high, according to Seth Martin, MD, of Johns Hopkins Hospital, and colleagues.

Among patients with a Friedewald-estimated value of less than 70 mg/dL, for example, the directly measured level was a median of 9 mg/dL higher when triglycerides were 150 to 199 mg/dL and 18.4 mg/dL higher when triglycerides were 200 to 399 mg/dL, the researchers reported online in the Journal of the American College of Cardiology.

Overall, 14.6% of the patients included in the study were placed into different treatment groups by the Friedewald estimates and direct measurements. This discordance was mainly due to “classification in a lower LDL cholesterol treatment group by Friedewald compared with direct LDL cholesterol,” which occurred in 11.3% of patients, they noted.

The discordance was greatest “when accuracy is most crucial, in patients with LDL cholesterol levels in the high-risk treatment range and concurrent hypertriglyceridemia,” Martin and colleagues wrote, noting that because the Friedewald estimates were generally lower than the directly measured values, using the equation could result in undertreatment of high-risk patients.

“This phenomenon warrants consideration in contemporary patient care and clinical practice guidelines,” the authors wrote.

With the Friedewald equation, LDL cholesterol is estimated by subtracting the HDL cholesterol level and the triglyceride level (divided by 5) from the total cholesterol level. Using the equation avoids the extra time and expense needed to directly measure LDL with ultracentrifugation.

Since the equation was introduced in 1972, however, practice guidelines have introduced lower LDL cholesterol targets, and high triglyceride levels have become more common due to the increasing problems of obesity, insulin resistance, and diabetes.

To assess the accuracy of the equation in a contemporary setting, the researchers compared Friedewald estimates with direct measurements performed with vertical density gradientultracentrifugation by the Vertical Auto Profile (VAP) from 2009 to 2011.

After excluding the patients who had a triglyceride level of 400 mg/dL or greater — in whom there are known limitations of the Friedewald equation — the researchers examined data from 1,310,440 adults (mean age 59) who underwent lipid screening; 14.6% had a Friedewald-estimated LDL cholesterol level of less than 70 mg/dL, the treatment target for high-risk patients.

The median directly measured LDL cholesterol level was 109 mg/dL. Lipid distributions were similar to those seen in the National Health and Nutrition Examination Survey for 2007 to 2008, indicating that the study sample was nationally representative.

In general, the Friedewald estimates were lower than the direct measurements of LDL cholesterol, and the discordance was greatest among patients with low LDL cholesterol levels and high triglyceride levels.

Of the patients with a Friedewald estimate of less than 70 mg/dL, 23% had a direct measurement that was higher than that. That figure rose to 39% when triglycerides were 150 to 199 mg/dL and 59% when triglycerides were 200 to 399 mg/dL.

The findings could have implications for patient care, according to the researchers.

“While we are not suggesting the need for routine clinical measurement of LDL cholesterol by direct assays, it bears mentioning that multiple direct assays beyond the VAP test [used in this study] are available,” they wrote.

“Nevertheless, non-HDL cholesterol and apolipoprotein B are alternative approaches, with potential advantages over any measure of LDL cholesterol, and these measures avoid confusion that arises in defining LDL cholesterol …,” they wrote. “Moreover, in clinical trial patients with LDL cholesterol levels in the high-risk range highlighted in our study, non-HDL cholesterol and apolipoprotein B were stronger markers of residual risk than Friedewald LDL cholesterol.”

They acknowledged some limitations of the analysis, including the possibility that patients who undergo a VAP test may be a special population and the use of one-time LDL cholesterol measurements. In addition, the researchers did not have access to detailed clinical characteristics of the patients or clinical outcomes or information on statin use and fasting status before the lipid test.

http://www.medpagetoday.com/Cardiology/Dyslipidemia/38147?xid=NL_DHE_2013-03-29

REFERENCES

http://my.americanheart.org/professional/General/Secondary-Prevention-Risk-Reduction-for-Cardiac-and-Vascular-Disease_UCM_432926_Article.jsp

Related Statements and Guidelines

Late Breaking Clinical Trials

LBCT.01     Practice Implications for CAD and VTE     Sun., Nov. 4, 2012 / 3:30pm-5:20pm

Aspirin for The Prevention of Recurrent Venous Thromboembolism After a First Unprovoked Event: Results of the ASPIRE Randomized Controlled Trial
ASPIRE: This trial is investigating the efficacy of aspirin in preventing recurrent venous thromboembolism (VTE) in patients with first unprovoked VTE

A Randomized Trial of Bedside Platelet Function Monitoring to Adjust Antiplatelet Therapy Versus Standard of Care in Patients Undergoing Drug Eluting Stent Implantation: The ARCTIC Study
ARCTIC was designed to compare a strategy of monitoring platelet function at the bedside to adjust antiplatelet therapy to standard of care in patients having drug eluting stent implantation.

First Large-Scale Platelet Function Evaluation in an Acute Coronary Syndromes Trial – The TRILOGY ACS Platelet Function Sub-study
TRILOGY ACS is an international, phase 3, randomized trial comparing the platelet inhibitor prasugrel+aspirin with clopidogrel+aspirin in medically managed US/NSTEMI ACS patients.

Results of the Trial to Assess Chelation Therapy
The Trial to Assess Chelation Therapy (TACT) is an NIH-sponsored randomized, double blind clinical trial testing the benefits and risks of 40 infusions of a standard ethylene diamine tetra-acetic (EDTA)-chelation solution compared with placebo in patients with coronary artery disease.

Main Results of the Future REvascularization Evaluation in patients with Diabetes mellitus: Optimal management of Multivessel disease (FREEDOM) Trial
FREEDOM – This trial was designed to determine whether coronary artery bypass grafting (CABG) or percutaneous coronary intervention (PCI) is the superior approach for revascularization of diabetic patients with multivessel coronary artery disease.

LBCT.02     Health Economics and Quality of Life in Contemporary Trials     Sun., Nov. 4, 2012 / 5:30pm-6:43pm

LBCT.03     Treatments for Prevention of Cardiovascular Events: A Population Perspective     Mon., Nov. 5, 2012 /  9:00am-10:28am

LBCT.04     Novel Treatments for Managing Lipid Disorders     Mon., Nov. 5, 2012 / 10:45am-11:55am

LBCT.05     Cell-Based Therapies for Myocardial Regeneration     Tues., Nov. 6, 2012 / 10:45am-12:00pm

LBCT.06     Management of LV Dysfunction: Devices and Drugs     Tues., Nov. 6, 2012 / 3:45pm-5:35pm

Clinical Science: Special Reports

CS.01     Prevention and Treatment of Ischemic Heart Disease: Novel Approaches     Mon., Nov. 5, 2012 / 7:30am-8:46am

Low Dose Colchicine for Secondary Prevention of Cardiovascular Disease [LoDoCo]: A Randomized Controlled Trial
The LoDoCo trial was designed to determine whether colchicine given in addition to standard medical therapy therapy is effective for the prevention of major cardiovascular endpoints in patients with  stable coronary artery disease.

Results of the Responses of Myocardial Ischemia to Escitalopram Treatment Trial
This trial examines the effects of escitalopram, a selective serotonin reuptake inhibitor (SSRI) , on mental stress-induced myocardial ischemia (MSIMI) in coronary heart disease patients.

Safety and Efficacy of Losmapimod in Non-ST-Segment Elevation Acute Myocardial Infarction: Results of the SOLSTICE Phase 2 Randomized Trial
SOLSTICE (Study Of LoSmapimod Treatment on Inflammation and InfarCt SizE) is a randomized, double-blind, placebo-controlled, parallel group, multicenter phase 2a study to evaluate safety and efficacy of 12-week treatment with 2 dose regimens of losmapimod (GW856553), a potent oral p38-MAPK inhibitor, versus placebo (randomized 3:3:2) in patients with non-ST-segment elevation myocardial infarction (NSTEMI) expected to undergo an invasive strategy.

EnligHTN™ I, First-in-man Multi-center Study of a Novel Multi-electrode Renal Denervation Catheter in Patients with Drug-Resistant Hypertension
EnligHTN I: This study was designed to study the efficacy and safety of a new radio frequency ablation catheter in patients withdrug-resistant  resistant hypertension.

CS.02     New Insights into Management of Common Cardiovascular Disorders     Mon., Nov. 5, 2012 / 5:30pm-6:40pm

CS.03     Emerging Therapeutics for Diabetes and Dyslipidemia     Tues., Nov. 6, 2012 / 7:30am-8:25am

CS.04     Valvular Heart Disease, PAD, Atrial Fibrillation: International Perspectives     Wed., Nov. 7, 2012 / 10:45am – 12:15pm

Related articles on this Open Access Online Scientific Journal include the following:

High-Density Lipoprotein (HDL): An Independent Predictor of Endothelial Function & Atherosclerosis, A Modulator, An Agonist, A Biomarker for Cardiovascular Risk 

Aviva Lev-Ari, PhD, RN, 3/31/2013

Artherogenesis: Predictor of CVD – the Smaller and Denser LDL Particles

Aviva Lev-Ari, PhD, RN 11/15/2012

Special Considerations in Blood Lipoproteins, Viscosity, Assessment and Treatment

Larry H. Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN, 11/28/2012

What is the role of plasma viscosity in hemostasis and vascular disease risk?

Larry H. Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN, 11/28/2012

Aviva Lev-Ari, PhD, RN, 3/7/2013

Read Full Post »

Reporter: Aviva Lev-Ari, PhD, RN


Very significant research results are reported below.

I witnessed the Rapid Response Team at MGH, on my night shift in August 2007 on a Cardiac Step-down Floor, performing CPR on a 71 year old female, a Cardiac patient. She was unsalvageable, her Attending Physician arrived to her bedside from home, two dozen professionals gathers in minuted from the Code Blue overhead announcement. The code cart was pushed to her room by myself and another Nurse. As the Physician who managed the Code left the patient room very disappointed, saying, “I have yet to see one successful resuscitation.”

In January 2009, as Supervisor of Kindred Long Term Care Acute Hospital at Waltham Hospital, 5th Floor, I performed CPR for a 69 year old male, a non Cardiac patient in Cardiac Arrest, Dr. Natov contacted the Code Blue, ACLS guidelines were followed and Patient survived.

I am very encouraged to learn the Survival Improvement by CPR achieved after “In-hospital Cardiac Arrest” as I am reporting, below.

In-hospital Cardiac Arrest: No Longer ‘Unsalvageable’

By Jill Gormley
Feb 27, 2013
 - Chest pain

In-hospital cardiac arrest accounts for approximately160,000 deaths in the U.S. every year—similar to deaths from lung cancer—and yet it receives little attention and limited research funding. Those studying this silent epidemic say that decreasing the morbidity and mortality associated with in-hospital cardiac arrest is attainable and should be a focus of every provider’s quality improvement efforts.

One of those researchers, Paul S. Chan, MD, of Saint Luke’s Health System in Kansas City, Mo., feels that paying more attention to preventing and responding appropriately to in-hospital cardiac arrest can make a huge impact. He cites the great leaps made in improving care for heart failure and MI over the past few decades, contending that similar strides can be made in improving survival after in-hospital cardiac arrest.

The American Heart Association has made in-hospital cardiac arrest a focus for quality improvement with its Get With the Guidelines-Resuscitation (GWTG-R) registry, which collects information about resuscitation cases from participating hospitals and offers feedback on resuscitative practices and outcomes. The registry also uses the information collected to develop evidence-based guidelines and best practices. Currently, more than 1,550 hospitals participate in the registry, and studies of outcomes using registry data indicate that attention to the problem is producing results.

Survival Is Improving

ACS-NSQIP = American College of SurgeonsNational Surgical Quality Improvement Program; CPR = cardiopulmonary resuscitation
Source: JAMA Surg 2013;148[1]:14-21

Studying adults who experienced in-hospital cardiac arrest and using acute resuscitation survival (rate of return of spontaneous circulation for at least 20 minutes) and survival to discharge as endpoints, Chan and colleagues found encouraging trends among hospitals participating in GWTG-R (N Engl J Med 2012;367:1912-1920). Survival to discharge improved from 13.7 percent in 2000 to 22.3 percent in 2009. Acute resuscitation survival improved from 42.7 percent to 54.1 percent over the same period, and post-resuscitation survival increased from 32 percent to 42.9 percent.

There are similar trends in the pediatric arena. Between 2 and 6 percent of children admitted to intensive care units experience in-hospital cardiac arrest every year. Survival rates are poor and survivors often are left with neurological impairment. But a study of urban teaching hospitals with pediatric residency or fellowship programs participating in GWTG-R showed improvement among this vulnerable population as well (Circ Cardiovasc Qual Outcomes 2013; 6:42-49). Survival to discharge increased from 14.3 percent in 2000 to 43.4 percent in 2009 and post-resuscitation survival increased from 42.9 percent to 81.2 percent over the same time period. The researchers found no significant change in the percentage of survivors who experienced neurological impairment.

Saket Girotra, MD, an interventional cardiologist at the University of Iowa Hospital and co-author with Chan of the adult and pediatric studies, suggests there are a number of factors supporting increased survival of in-hospital cardiac arrest. Prompt recognition of patient distress, quality of chest compressions, timely defibrillation when necessary, proper administration of optimal medication, the engagement of hospital leadership in organizing better resuscitation team coordination and improved aftercare stand out among them. “All these are likely contributors, but we don’t yet have data to tell us what is driving these improvements. That is the next step for research,” he says.

There is some evidence that length of resuscitation efforts has an impact on survival (Lancet 2012;380:1473-1481). Again working with the GWTG-R registry, researchers analyzed the duration of resuscitation attempts in non-survivors at more than 400 hospitals to determine the mean length of resuscitation attempts before termination of rescue efforts. Overall, the mean length was 12 minutes for survivors and 20 minutes for non-survivors. But the researchers noted substantial variation between hospitals, with the hospitals in the quartile

with the longest duration of resuscitation attempts (mean of 25 minutes) engaging in resuscitative efforts 50 percent longer than hospitals in the quartile with the shortest duration of resuscitation (mean of 16 minutes). They found that patients who had cardiac arrests within hospitals with longer mean resuscitation attempt times were more likely to survive than those whose arrests occurred in hospitals with shorter mean resuscitation times.

Another recent study by a different team of researchers looked at cardiopulmonary resuscitation in surgical patients, and identified a potentially potent weapon against in-hospital arrest and mortality—prevention. This study found that complications, especially pneumonia and sepsis, preceded the large majority of cardiac arrests in surgical patients (JAMA Surg 2013;148[1]:14-21). Survival among these patients was poor—overall mortality at 30 days was 71.6 percent—but the authors concluded that many of these deaths could have been avoided through prevention of complications and expedient diagnosis and treatment of complications when they occurred.

Misperceptions Impede Progress

The opinion that the in-hospital cardiac arrest patient is unsalvageable persists, according to Chan. “There is a perception of futility that these patients are very, very sick, that they are unlikely to survive and that if they do survive, they will be neurologically devastated. Twenty years ago, that may have been true in many cases, but our research is showing it’s not true anymore,” he says.

In-hospital cardiac arrest is now less likely to be a result of MI or to be related to cardiovascular disease than it was in 2000, according to the analyses of GWTG-R data. Patients suffering in-hospital cardiac arrest are younger than they were in 2000 and more likely to have septicemia or other infections, to have been on mechanical ventilation and to have received intravenous vasopressors.

“Also, and very significantly, is that most patients who survive to discharge leave the hospital with no or minor neurological disability,” says Girotra. The study on survival outcomes showed that in 2000 half the patients who survived to discharge left the hospital with severe or clinically significant neurological disability, but by 2009, that percentage had dropped to 38.8 percent.

The study on duration of resuscitation attempts also examined neurologic status among patients who survived to discharge, and showed that those who survived long resuscitation attempts fared no worse neurologically than those whose resuscitations were shorter.

Researchers are currently exploring costs associated with survival of in-hospital cardiac arrest, aftercare, readmission and other variables, compared with the costs of surviving heart failure. “We are trying to paint an accurate picture of these patients to determine the amount of resources it takes to care for them after survival, and whether the outlook for these patients is really as pessimistic as is sometimes thought,” Chan says.

More granular data are necessary to identify the drivers of increased survival of in-hospital cardiac arrest and Chan says there is a need for funding to study cardiac arrest as a disease process. “If we can pinpoint exactly what the high-performing hospitals are doing well, we can establish good guidelines and best practices,” Girotra says. “Then, perhaps, we will see the sort of improvement that we have seen in MI survival extend to these patients, at all hospitals.”

http://www.cardiovascularbusiness.com/topics/prevention/hospital-cardiac-arrest-no-longer-‘unsalvageable’?page=0%2C1


Read Full Post »

Genomics & Genetics of Cardiovascular Disease Diagnoses: A Literature Survey of AHA’s Circulation Cardiovascular Genetics, 3/2010 – 3/2013


Curators: Aviva Lev-Ari, PhD, RN and Larry H. Bernstein, MD, FCAP


348 articles that appeared in AHA’s Circulation Cardiovascular Genetics, 3/2010 – 3/2013 were classified by the curators of this article into the following TEN categories. The first 9, represent DIAGNOSES of cardiovascular diseases, the last, deals with Pharmacogenomics.

The Cardiovascular Diagnoses that were covered in the period of 3/2010 – 3/2013, include the following:

  • Preventative Cardiology
  • MicroRNA in Serum as Bimarker for Cardiovascular Pathologies: acute myocardial infarction, viral myocarditis, diastolic dysfunction, and acute heart failure
  • Genetic Determinants of Potassium Sensitivity and Hypertension
  • Heart and Aging Research in Genomic Epidemiology: 1700 MIs and 2300 coronary heart disease events among about 29 000 eligible patients
  • Genetics of CVD and Hyperlipidemia, Hyper Cholesterolemia, Metabolic Syndrome
  • Genomics and Valvular Disease
  • Pharmacogenomics

Introductions

Larry H. Bernstein, MD, FCAP


The curation of this large amount of material in 10 categories begins with a first chapter on preventative cardiology, which has had much public attention for the last decade.  Much of the concern with preventive cardiology has emphasized diet and exercise.  There is much to be said about this in articles not yet written.  However, there are several decades of research on the amino acid composition of foods, and the essential fatty acids, that indicates an essential balance between proinflammatory and antiinflammatory fatty acids in polyunsaturated fatty acids, and of the harmful effects of saturated fats.  There is also much to be said of essential amino acids, and in particular, those essential for methylation processes, and sulfur metabolism.

The next eight chapters are all concerned with genomics in cardiovascular disease.  This is in no small part a follow up on the completion of the genetic code in 2003, a seminal event.  Let us look at these in clusters.

[1]   microRNA in serum is now considered for a biomarker for cardiovascular disease.  It can be measured at very low levels, but we don’t yet know where it fits.   It might be more revealing once we understand the adaptive mechanism in development of congestive heart failure, renal hypertension, and post-genomic events.

[2]  It appears to me that potassium sensitivity and hypertension approached from the genomic side is more complicate.  Why is that?   The kidney excretes a sodium load and in metabolic acidosis, the serum potassium rises with a metabolic acidemia that can’t be compensated by the respiratory loss of CO2 through the carbonic anhydrase mechanism.

[3]  Heart and aging research is a rich area for work on the long term post-genomic changes, and it involves a large population base.

[4][5]  The genomics of cardiac dysrrhytmias and cardiomyopathies will open new doors into our understanding of the mechanisms of these diseases, and perhaps find therapeutic targets.  There has been a large volume of work on lipid synthesis, the role of the liver in generating apolipoproteins, and this has new answers on the way.  The most important feature, not readily accepted is the measurement of particles, which has now been done by a monoclonal antibody.  Metabolic syndrome brings together adipose tissue metabolism, endocrine and changes in CRP and IL-1.

[6]   Vascular pathologies and coagulation, hyperviscosity has had an enormous increase in intensity of research.  The concept of plaque rupture to account for all AMIs is being modified, and the high sensitivity cardio-specific troponins have become the most widely use test.

[7]  The genomics of valvular disease fits with the increased surgical procedures for valvular disease related to atheroschlerosis and advent of minimally invasive surgical procedures for the reapir and replacement of valves, procedure called TAVR vs. Openhealrt surgery for valve replacement.

[8]  Inherited cardiovascular disease is an older family of disorders, going back to Victor McKusik, and also the “Blue Baby” operation, both at Johns Hopkins.

[9] Pharmacogenomics is a vary active field of investigation and has uncovered inter-individual differences in handling Warfarin as a starter.


Preventative Cardiology


Methods in Genetics and Clinical Interpretation Randomized Trial of Personal Genomics for Preventive Cardiology Design and Challenges

Joshua W. Knowles, MD, PhD, Themistocles L. Assimes, MD, PhD, Michaela Kiernan, PhD, Aleksandra Pavlovic, BS, Benjamin A. Goldstein, PhD, Veronica Yank, MD, Michael V. McConnell, MD, Devin Absher, PhD, Carlos Bustamante, PhD, Euan A. Ashley, MD, DPhil and John P.A. Ioannidis, MD, DSc

Author Affiliations

From the Division of Cardiovascular Medicine (J.W.K., T.L.A., A.P., M.V.M., E.A.A.), Stanford Prevention Research Center (M.K., V.Y., J.P.A.I.), Division of General Medical Disciplines (V.Y.), Department of Genetics (C.B.), Department of Health Research and Policy (J.P.A.I.), Stanford University School of Medicine, Stanford, CA; Quantitative Sciences Unit, Stanford University School of Medicine, Palo Alto, CA (B.A.G.); HudsonAlpha Institute for Biotechnology, Huntsville, AL (D.A.); Department of Statistics, Stanford University School of Humanities and Sciences, Stanford, CA (J.P.A.I.).

Correspondence to Joshua W. Knowles, MD, PhD, Stanford University School of Medicine, Division of Cardiovascular Medicine, Falk CVRC, 300 Pasteur Dr, Stanford, CA 94305. E-mail knowlej@stanford.edu

Background

Genome-wide association studies (GWAS) have identified more than 1500 disease-associated single nucleotide polymorphisms (SNPs), including many related to atherosclerotic cardiovascular disease (CVD). Associations have been found for most traditional risk factors (TRFs), including lipids,1,2 blood pressure/hypertension,3,4 weight/body mass index,5,6 smoking behavior,7 and diabetes.8–13 GWAS have also identified susceptibility variants for coronary heart disease (CHD). The first and, so far, strongest of these signals was found in the 9p21.3 locus, where common variants in this region increase the relative risk of CVD by 15% to 30% per risk allele in most race/ethnic groups.13–20 Subsequent large-scale GWAS meta-analyses and replication studies in largely white/European populations have led to the reliable identification of an additional 26 loci conferring susceptibility to CHD,2,20–23 all with substantially lower effects sizes compared with the 9p21 locus. Many of these CVD susceptibility loci appear to be conferring risk independent of TRFs and thus cannot currently be assessed by surrogate clinical measures (Table 1). Among the 27 independent loci identified in the most recent large meta-analyses of CVD, 21 were reported not to be associated with any of the TRFs.20,21

 SOURCE

Circulation: Cardiovascular Genetics 2012; 5: 368-376

doi: 10.1161/ CIRCGENETICS.112.962746


MicroRNA in Serum as Bimarker for Cardiovascular Pathologies: acute myocardial infarction, viral myocarditis,  diastolic dysfunction, and acute heart failure

Increased MicroRNA-1 and MicroRNA-133a Levels in Serum of Patients With Cardiovascular Disease Indicate Myocardial Damage


Yasuhide Kuwabara, MD, Koh Ono, MD, PhD, Takahiro Horie, MD, PhD, Hitoo Nishi, MD, PhD, Kazuya Nagao, MD, PhD, Minako Kinoshita, MD, PhD, Shin Watanabe, MD, PhD, Osamu Baba, MD, Yoji Kojima, MD, PhD, Satoshi Shizuta, MD, Masao Imai, MD, Toshihiro Tamura, MD, Toru Kita, MD, PhD and Takeshi Kimura, MD, PhD

Author Affiliations

From the Department of Cardiovascular Medicine, Graduate School of Medicine, Kyoto University, Kyoto, Japan (Y. Kuwabara, K.O., T.H., H.N., K.N., M.K., S.W., O.B., Y. Kojima, S.S., M.I., T.T., T. Kimura); and Kobe City Medical Center General Hospital, Kobe, Japan (T. Kita).

Correspondence to Koh Ono, MD, PhD, Department of Cardiovascular Medicine, Graduate School of Medicine, Kyoto University, 54 Shogoin-kawahara-cho, Sakyo-ku, Kyoto, Japan 606-8507. E-mail kohono@kuhp.kyoto-u.ac.jp


Abstract

Background—Recently, elevation of circulating muscle-specific microRNA (miRNA) levels has been reported in patients with acute myocardial infarction. However, it is still unclear from which part of the myocardium or under what conditions miRNAs are released into circulating blood. The purpose of this study was to identify the source of elevated levels of circulating miRNAs and their function in cardiovascular diseases.

Conclusions—These results suggest that elevated levels of circulating miR-133a in patients with cardiovascular diseases originate mainly from the injured myocardium. Circulating miR-133a can be used as a marker for cardiomyocyte death, and it may have functions in cardiovascular diseases.

SOURCE:

Circulation: Cardiovascular Genetics. 2011; 4: 446-454

Published online before print June 2, 2011,

doi: 10.1161/ CIRCGENETICS.110.958975

Selective Articles citing this article

Plasma microRNAs serve as biomarkers of therapeutic efficacy and disease progression in hypertension-induced heart failure 
Eur J Heart Fail. 2013;0:hft018v1-hft018,

AbstractFull TextPDF

Intercellular Transport of MicroRNAs 
Arterioscler. Thromb. Vasc. Bio.. 2013;33:186-192,

AbstractFull TextPDF

MicroRNAs Within the Continuum of Postgenomics Biomarker Discovery 
Arterioscler. Thromb. Vasc. Bio.. 2013;33:206-214,

AbstractFull TextPDF

Reply to “Need for Rigor in Design, Reporting, and Interpretation of Transcriptomic Biomarker Studies” 
J. Clin. Microbiol.. 2012;50:4192-4193,

http://www.ncbi.nlm.nih.gov/pmc/articles/PMC3502969/

Full TextPDF

Circulating microRNAs as diagnostic biomarkers for cardiovascular diseases 
Am. J. Physiol. Heart Circ. Physiol.. 2012;303:H1085-H1095,

AbstractFull TextPDF

Sonic Hedgehog-Modified Human CD34+ Cells Preserve Cardiac Function After Acute Myocardial Infarction 
Circ. Res.. 2012;111:312-321,

AbstractFull TextPDF

Metabolomics, Proteomics, Genomics, and Transcriptomics in Circulation and the Circulation Subspecialty Journals 
Circulation. 2012;125:e507-e519,

AbstractFull TextPDF

Circulating MicroRNAs: Novel Biomarkers and Extracellular Communicators in Cardiovascular Disease? 
Circ. Res.. 2012;110:483-495,

AbstractFull TextPDF

Circulating MicroRNAs in Cardiovascular Disease 
Circulation. 2011;124:1908-1910,

Full TextPDF

Circulating MicroRNAs: Biomarkers or Mediators of Cardiovascular Diseases? 
Arterioscler. Thromb. Vasc. Bio.. 2011;31:2383-2390,

AbstractFull TextPDF


Circulating MicroRNA-208b and MicroRNA-499 Reflect Myocardial Damage in Cardiovascular Disease

Maarten F. Corsten, MD, Robert Dennert, MD, Sylvia Jochems, BSc, Tatiana Kuznetsova, MD, PhD, Yvan Devaux, PhD, Leon Hofstra, MD, PhD, Daniel R. Wagner, MD, PhD, Jan A. Staessen, MD, PhD, Stephane Heymans, MD, PhD and Blanche Schroen, PhD

Author Affiliations

From the Center for Heart Failure Research (M.F.C., R.D., S.J., S.H., B.S.), Cardiovascular Research Institute, Maastricht, The Netherlands; the Division of Hypertension and Cardiovascular Rehabilitation (T.K., J.A.S.), Department of Cardiovascular Diseases, University of Leuven, Leuven, Belgium and Department of Epidemiology, Maastricht University Medical Center, Maastricht, The Netherlands; Centre de Recherche Public–Santé, Luxembourg (Y.D., D.R.W.), Luxembourg; Maastricht University Medical Center (L.H.), Maastricht, The Netherlands; and Centre Hospitalier Luxembourg (D.R.W.), Luxembourg.

Correspondence to Blanche Schroen, PhD, Center for Heart Failure Research, Cardiovascular Research Institute Maastricht, Universiteitssingel 50, 6229 ER Maastricht, The Netherlands. E-mail b.schroen@cardio.unimaas.nl

Drs Heymans and Schroen contributed equally to this work.

Abstract

Background— Small RNA molecules, called microRNAs, freely circulate in human plasma and correlate with varying pathologies. In this study, we explored their diagnostic potential in a selection of prevalent cardiovascular disorders.

Methods and Results— MicroRNAs were isolated from plasmas from well-characterized patients with varying degrees of cardiac damage:

(1) acute myocardial infarction,

(2) viral myocarditis,

(3) diastolic dysfunction, and

(4) acute heart failure.

Plasma levels of selected microRNAs, including heart-associated (miR-1, -133a, -208b, and -499), fibrosis-associated (miR-21 and miR-29b), and leukocyte-associated (miR-146, -155, and -223) candidates, were subsequently assessed using real-time polymerase chain reaction. Strikingly, in plasma from acute myocardial infarction patients, cardiac myocyte–associated miR-208b and -499 were highly elevated, 1600-fold (P<0.005) and 100-fold (P<0.0005), respectively, as compared with control subjects. Receiver operating characteristic curve analysis revealed an area under the curve of 0.94 (P<10−10) for miR-208b and 0.92 (P<10−9) for miR-499. Both microRNAs correlated with plasma troponin T, indicating release of microRNAs from injured cardiomyocytes. In viral myocarditis, we observed a milder but significant elevation of these microRNAs, 30-fold and 6-fold, respectively. Plasma levels of leukocyte-expressed microRNAs were not significantly increased in acute myocardial infarction or viral myocarditis patients, despite elevated white blood cell counts. In patients with acute heart failure, only miR-499 was significantly elevated (2-fold), whereas no significant changes in microRNAs studied could be observed in diastolic dysfunction. Remarkably, plasma microRNA levels were not affected by a wide range of clinical confounders, including age, sex, body mass index, kidney function, systolic blood pressure, and white blood cell count.

Conclusions— Cardiac damage initiates the detectable release of cardiomyocyte-specific microRNAs-208b and -499 into the circulation.

SOURCE:

Circulation: Cardiovascular Genetics. 2010; 3: 499-506

Published online before print October 4, 2010,

doi: 10.1161/ CIRCGENETICS.110.957415


Selective Articles citing this article

Plasma microRNAs serve as biomarkers of therapeutic efficacy and disease progression in hypertension-induced heart failure 
Eur J Heart Fail. 2013;0:hft018v1-hft018,

AbstractFull TextPDF

Aspirin treatment hampers the use of plasma microRNA-126 as a biomarker for the progression of vascular disease 
Eur Heart J. 2013;0:eht007v1-eht007,

AbstractFull TextPDF

MicroRNAs in Myocardial Infarction 
Arterioscler. Thromb. Vasc. Bio.. 2013;33:201-205,

AbstractFull TextPDF

MicroRNAs Within the Continuum of Postgenomics Biomarker Discovery 
Arterioscler. Thromb. Vasc. Bio.. 2013;33:206-214,

AbstractFull TextPDF

MicroRNAs Are Involved in End-Organ Damage During Hypertension 
Hypertension. 2012;60:1088-1093,

AbstractFull TextPDF

Circulating microRNAs as diagnostic biomarkers for cardiovascular diseases 
Am. J. Physiol. Heart Circ. Physiol.. 2012;303:H1085-H1095,

AbstractFull TextPDF

Circulation Editors’ Picks: Most Read Articles in Cardiovascular Genetics 
Circulation. 2012;126:e163-e169,

AbstractFull TextPDF

MicroRNAs in Patients on Chronic Hemodialysis (MINOS Study) 
CJASN. 2012;7:619-623,

AbstractFull TextPDF

Novel techniques and targets in cardiovascular microRNA research 
Cardiovasc Res. 2012;93:545-554,

AbstractFull TextPDF

Microparticles: major transport vehicles for distinct microRNAs in circulation 
Cardiovasc Res. 2012;93:633-644,

AbstractFull TextPDF

Profiling of circulating microRNAs: from single biomarkers to re-wired networks 
Cardiovasc Res. 2012;93:555-562,

AbstractFull TextPDF

Small but smart–microRNAs in the centre of inflammatory processes during cardiovascular diseases, the metabolic syndrome, and ageing 
Cardiovasc Res. 2012;93:605-613,

AbstractFull TextPDF

Circulation: Heart Failure Editors’ Picks: Most Important Papers in Pathophysiology and Genetics 
Circ Heart Fail. 2012;5:e32-e49,

AbstractFull TextPDF

Use of Circulating MicroRNAs to Diagnose Acute Myocardial Infarction 
Clin. Chem.. 2012;58:559-567,

AbstractFull TextPDF

Circulating MicroRNAs: Novel Biomarkers and Extracellular Communicators in Cardiovascular Disease? 
Circ. Res.. 2012;110:483-495,

AbstractFull TextPDF

Serum levels of microRNAs in patients with heart failure 
Eur J Heart Fail. 2012;14:147-154,

AbstractFull TextPDF

Circulating microRNAs to identify human heart failure 
Eur J Heart Fail. 2012;14:118-119,

Full TextPDF

Next Steps in Cardiovascular Disease Genomic Research–Sequencing, Epigenetics, and Transcriptomics 
Clin. Chem.. 2012;58:113-126,

AbstractFull TextPDF

Most Read in Cardiovascular Genetics on Biomarkers, Inherited Cardiomyopathies and Arrhythmias, Metabolomics, and Genomics 
Circ Cardiovasc Genet. 2011;4:e24-e30,

AbstractFull TextPDF

MicroRNA-126 modulates endothelial SDF-1 expression and mobilization of Sca-1+/Lin- progenitor cells in ischaemia 
Cardiovasc Res. 2011;92:449-455,

AbstractFull TextPDF

Circulating MicroRNAs: Biomarkers or Mediators of Cardiovascular Diseases? 
Arterioscler. Thromb. Vasc. Bio.. 2011;31:2383-2390,

AbstractFull TextPDF

Transcoronary Concentration Gradients of Circulating MicroRNAs 
Circulation. 2011;124:1936-1944,

AbstractFull TextPDF

MicroRNAs: New Players in Cardiac Injury and Protection 
Mol. Pharmacol.. 2011;80:558-564,

AbstractFull TextPDF

Circulation Editors’ Picks: Most Read Articles in Cardiovascular Genetics, Part I 
Circulation. 2011;124:e345-e357,

AbstractFull TextPDF

MicroRNAs regulating oxidative stress and inflammation in relation to obesity and atherosclerosis 
FASEB J.. 2011;25:2515-2527,

AbstractFull TextPDF

miR-143 and miR-145: Molecular Keys to Switch the Phenotype of Vascular Smooth Muscle Cells 
Circ Cardiovasc Genet. 2011;4:197-205,

Full TextPDF

Response to Letter Regarding Article, “Circulating MicroRNA-208b and MicroRNA-499 Reflect Myocardial Damage in Cardiovascular Disease” 
Circ Cardiovasc Genet. 2011;4:e8,

Full TextPDF


Genetic Determinants of Potassium Sensitivity and Hypertension


Integrated Computational and Experimental Analysis of the Neuroendocrine Transcriptome in Genetic Hypertension Identifies Novel Control Points for the Cardiometabolic Syndrome

Ryan S. Friese, PhD, Chun Ye, PhD, Caroline M. Nievergelt, PhD, Andrew J. Schork, BS, Nitish R. Mahapatra, PhD, Fangwen Rao, MD, Philip S. Napolitan, BS, Jill Waalen, MD, MPH, Georg B. Ehret, MD, Patricia B. Munroe, PhD, Geert W. Schmid-Schönbein, PhD, Eleazar Eskin, PhD and Daniel T. O’Connor, MD

Author Affiliations

From the Departments of Bioengineering (R.S.F., G.W.S.-S.), Medicine (R.S.F., A.J.S., F.R., P.S.N., D.T.O.), Pharmacology (D.T.O.), and Psychiatry (C.M.N.), the Bioinformatics Program (C.Y.), and the Institute for Genomic Medicine (D.T.O.), University of California at San Diego; the VA San Diego Healthcare System, San Diego, CA (D.T.O.); the Departments of Computer Science & Human Genetics, University of California at Los Angeles (E.E.); the Department of Biotechnology, Indian Institute of Technology Madras, Chennai, India (N.R.M.); Clinical Pharmacology and The Genome Centre, William Harvey Research Institute, Barts and The London School of Medicine and Dentistry, Queen Mary University of London, London, United Kingdom (P.B.M.); Center for Complex Disease Genomics, McKusick-Nathans Institute of Genetic Medicine, Johns Hopkins University School of Medicine, Baltimore, MD (G.B.E.); and Scripps Research Institute, La Jolla, CA (J.W.).

Correspondence to Daniel T. O’Connor, MD, Department of Medicine, University of California at San Diego School of Medicine, VASDHS (0838), Skaggs (SSPPS) Room 4256, 9500 Gilman Drive, La Jolla, CA 92093-0838. E-mail doconnor@ucsd.edu

Abstract

Background—Essential hypertension, a common complex disease, displays substantial genetic influence. Contemporary methods to dissect the genetic basis of complex diseases such as the genomewide association study are powerful, yet a large gap exists betweens the fraction of population trait variance explained by such associations and total disease heritability.

Methods and Results—We developed a novel, integrative method (combining animal models, transcriptomics, bioinformatics, molecular biology, and trait-extreme phenotypes) to identify candidate genes for essential hypertension and the metabolic syndrome. We first undertook transcriptome profiling on adrenal glands from blood pressure extreme mouse strains: the hypertensive BPH (blood pressure high) and hypotensive BPL (blood pressure low). Microarray data clustering revealed a striking pattern of global underexpression of intermediary metabolism transcripts in BPH. The MITRA algorithm identified a conserved motif in the transcriptional regulatory regions of the underexpressed metabolic genes, and we then hypothesized that regulation through this motif contributed to the global underexpression. Luciferase reporter assays demonstrated transcriptional activity of the motif through transcription factors HOXA3, SRY, and YY1. We finally hypothesized that genetic variation at HOXA3, SRY, and YY1 might predict blood pressure and other metabolic syndrome traits in humans. Tagging variants for each locus were associated with blood pressure in a human population blood pressure extreme sample with the most extensive associations for YY1 tagging single nucleotide polymorphism rs11625658 on systolic blood pressure, diastolic blood pressure, body mass index, and fasting glucose. Meta-analysis extended the YY1 results into 2 additional large population samples with significant effects preserved on diastolic blood pressure, body mass index, and fasting glucose.

Conclusions—The results outline an innovative, systematic approach to the genetic pathogenesis of complex cardiovascular disease traits and point to transcription factor YY1 as a potential candidate gene involved in essential hypertension and the cardiometabolic syndrome.

 SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 430-440

Published online before print June 5, 2012,

doi: 10.1161/ CIRCGENETICS.111.962415

Genome-Wide Linkage and Positional Candidate Gene Study of Blood Pressure Response to Dietary Potassium Intervention

The Genetic Epidemiology Network of Salt Sensitivity Study

Tanika N. Kelly, PhD, James E. Hixson, PhD, Dabeeru C. Rao, PhD, Hao Mei, MD, PhD, Treva K. Rice, PhD, Cashell E. Jaquish, PhD, Lawrence C. Shimmin, PhD, Karen Schwander, MS, Chung-Shuian Chen, MS, Depei Liu, PhD, Jichun Chen, MD, Concetta Bormans, PhD, Pramila Shukla, MS, Naveed Farhana, MS, Colin Stuart, BS, Paul K. Whelton, MD, MSc, Jiang He, MD, PhD and Dongfeng Gu, MD, PhD

Author Affiliations

From the Department of Epidemiology (T.N.K., H.M., C.-S.C., J.H.), Tulane University School of Public Health and Tropical Medicine, and Department of Medicine (J.H.), Tulane University School of Medicine, New Orleans, La; Department of Epidemiology (J.E.H., L.C.S., C.B., P.S., N.F., C.S.), University of Texas School of Public Health, Houston, Tex; Division of Biostatistics (D.C.R., T.K.R., K.S.), Washington University School of Medicine, St Louis, Mo; Division of Prevention and Population Sciences (C.E.J.), National Heart, Lung, Blood Institute, Bethesda, Md; National Laboratory of Medical Molecular Biology (D.L.), Institute of Basic Medical Sciences, Chinese Academy of Medical Sciences and Peking Union Medical College, Beijing, China; Cardiovascular Institute and Fuwai Hospital (J.C., D.G.), Chinese Academy of Medical Sciences and Peking Union Medical College and Chinese National Center for Cardiovascular Disease Control and Research, Beijing, China; and Office of the President (P.K.W.), Loyola University Health System and Medical Center, Maywood, Ill.

Correspondence to Dongfeng Gu, MD, PhD, Division of Population Genetics and Prevention, Cardiovascular Institute and Fuwai Hospital, 167 Beilishi Rd, Beijing 100037, China. E-mail gudongfeng@vip.sina.com

Abstract

Background— Genetic determinants of blood pressure (BP) response to potassium, or potassium sensitivity, are largely unknown. We conducted a genome-wide linkage scan and positional candidate gene analysis to identify genetic determinants of potassium sensitivity.

Conclusions— Genetic regions on chromosomes 3 and 11 may harbor important susceptibility loci for potassium sensitivity. Furthermore, the AGTR1 gene was a significant predictor of BP responses to potassium intake.

SOURCE:

Circulation: Cardiovascular Genetics. 2010; 3: 539-547

Published online before print September 22, 2010,

doi: 10.1161/ CIRCGENETICS.110.940635


Genome-Wide Association Study of Cardiac Structure and Systolic Function in African Americans

The Candidate Gene Association Resource (CARe) Study

Ervin R. Fox, MD*, Solomon K. Musani, PhD*, Maja Barbalic, PhD*, Honghuang Lin, PhD, Bing Yu, MS, Kofo O. Ogunyankin, MD, Nicholas L. Smith, PhD, Abdullah Kutlar, MD, Nicole L. Glazer, MD, Wendy S. Post, MD, MS, Dina N. Paltoo, PhD, MPH, Daniel L. Dries, MD, MPH, Deborah N. Farlow, PhD, Christine W. Duarte, PhD, Sharon L. Kardia, PhD, Kristin J. Meyers, PhD, Yan V. Sun, PhD, Donna K. Arnett, PhD, Amit A. Patki, MS, Jin Sha, MS, Xiangqui Cui, PhD, Tandaw E. Samdarshi, MD, MPH, Alan D. Penman, PhD, Kirsten Bibbins-Domingo, MD, PhD, Petra Bůžková, PhD, Emelia J. Benjamin, MD, David A. Bluemke, MD, PhD, Alanna C. Morrison, PhD, Gerardo Heiss, MD, J. Jeffrey Carr, MD, MSc, Russell P. Tracy, PhD, Thomas H. Mosley, PhD, Herman A. Taylor, MD, Bruce M. Psaty, MD, PhD, Susan R. Heckbert, MD, PhD, Thomas P. Cappola, MD, ScM and Ramachandran S. Vasan, MD

Author Affiliations

Guest Editor for this article was Barry London, MD, PhD.

Correspondence to Ervin Fox, MD MPH, FAHA, FACC, Professor of Medicine, Department of Medicine, University of Mississippi Medical Center, 2500 North State St, Jackson, MS 39216. E-mail efox@medicine.umsmed.edu

↵* These authors contributed equally as joint first authors.

Abstract

Background—Using data from 4 community-based cohorts of African Americans, we tested the association between genome-wide markers (single-nucleotide polymorphisms) and cardiac phenotypes in the Candidate-gene Association Resource study.

Methods and Results—Among 6765 African Americans, we related age, sex, height, and weight-adjusted residuals for 9 cardiac phenotypes (assessed by echocardiogram or magnetic resonance imaging) to 2.5 million single-nucleotide polymorphisms genotyped using Genome-wide Affymetrix Human SNP Array 6.0 (Affy6.0) and the remainder imputed. Within the cohort, genome-wide association analysis was conducted, followed by meta-analysis across cohorts using inverse variance weights (genome-wide significance threshold=4.0 ×10−7). Supplementary pathway analysis was performed. We attempted replication in 3 smaller cohorts of African ancestry and tested lookups in 1 consortium of European ancestry (EchoGEN). Across the 9 phenotypes, variants in 4 genetic loci reached genome-wide significance: rs4552931 in UBE2V2 (P=1.43×10⁻⁷) for left ventricular mass, rs7213314 in WIPI1 (P=1.68×10⁻⁷) for left ventricular internal diastolic diameter, rs1571099 in PPAPDC1A (P=2.57×10⁻⁸) for interventricular septal wall thickness, and rs9530176 in KLF5 (P=4.02×10⁻⁷) for ejection fraction. Associated variants were enriched in 3 signaling pathways involved in cardiac remodeling. None of the 4 loci replicated in cohorts of African ancestry was confirmed in lookups in EchoGEN.

Conclusions—In the largest genome-wide association study of cardiac structure and function to date in African Americans, we identified 4 genetic loci related to left ventricular mass, interventricular septal wall thickness, left ventricular internal diastolic diameter, and ejection fraction, which reached genome-wide significance. Replication results suggest that these loci may be unique to individuals of African ancestry. Additional large-scale studies are warranted for these complex phenotypes.

SOURCE:

Circulation: Cardiovascular Genetics. 2013; 6: 37-46

Published online before print December 28, 2012,

doi: 10.1161/ CIRCGENETICS.111.962365


Heart and Aging Research in Genomic Epidemiology: 1700 MIs and 2300 coronary heart disease events among about 29 000 eligible patients


Cohorts for Heart and Aging Research in Genomic Epidemiology (CHARGE) Consortium

Design of Prospective Meta-Analyses of Genome-Wide Association Studies From 5 Cohorts

Bruce M. Psaty, MD, PhD, Christopher J. O’Donnell, MD, MPH, Vilmundur Gudnason, MD, PhD, Kathryn L. Lunetta, PhD, Aaron R. Folsom, MD, Jerome I. Rotter, MD, André G. Uitterlinden, PhD, Tamara B. Harris, MD, Jacqueline C.M. Witteman, PhD, Eric Boerwinkle, PhD and on Behalf of the CHARGE Consortium

Author Affiliations

From the Cardiovascular Health Research Unit, Departments of Medicine, Epidemiology, and Health Services (B.M.P.), University of Wash; Center for Health Studies, Group Health (B.M.P.), Seattle, Wash; the National Heart, Lung and Blood Institute and the Framingham Heart Study (C.J.O.D.), Framingham, Mass; Icelandic Heart Association and the Department of Cardiovascular Genetics (Y.G.), University of Iceland, Reykjavik, Iceland; Department of Biostatistics (K.L.), Boston University School of Public Health, Mass; Division of Epidemiology and Community Health (A.R.F.), University of Minnesota, Minneapolis; Medical Genetics Institute (J.I.R.), Cedars-Sinai Medical Center, Los Angeles, Calif; Departments of Internal Medicine (A.G.U.) and Epidemiology (A.G.U., J.C.M.W.), Erasmus Medical Center, Rotterdam, The Netherlands; Laboratory of Epidemiology, Demography, and Biometry (T.B.H.), Intramural Research Program, National Institute on Aging, Bethesda, Md; and Human Genetics Center and Division of Epidemiology (E.B.), University of Texas, Houston.

Guest editor for this article was Elizabeth R. Hauser, PhD.

Abstract

Background— The primary aim of genome-wide association studies is to identify novel genetic loci associated with interindividual variation in the levels of risk factors, the degree of subclinical disease, or the risk of clinical disease. The requirement for large sample sizes and the importance of replication have served as powerful incentives for scientific collaboration.

Methods— The Cohorts for Heart and Aging Research in Genomic Epidemiology Consortium was formed to facilitate genome-wide association studies meta-analyses and replication opportunities among multiple large population-based cohort studies, which collect data in a standardized fashion and represent the preferred method for estimating disease incidence. The design of the Cohorts for Heart and Aging Research in Genomic Epidemiology Consortium includes 5 prospective cohort studies from the United States and Europe: the Age, Gene/Environment Susceptibility—Reykjavik Study, the Atherosclerosis Risk in Communities Study, the Cardiovascular Health Study, the Framingham Heart Study, and the Rotterdam Study. With genome-wide data on a total of about 38 000 individuals, these cohort studies have a large number of health-related phenotypes measured in similar ways. For each harmonized trait, within-cohort genome-wide association study analyses are combined by meta-analysis. A prospective meta-analysis of data from all 5 cohorts, with a properly selected level of genome-wide statistical significance, is a powerful approach to finding genuine phenotypic associations with novel genetic loci.

Conclusions— The Cohorts for Heart and Aging Research in Genomic Epidemiology Consortium and collaborating non-member studies or consortia provide an excellent framework for the identification of the genetic determinants of risk factors, subclinical-disease measures, and clinical events.

Example of Coronary Heart Disease

The cohort-study methods papers provide detail about many of the phenotypes listed in Table 2. For coronary heart disease, investigators knowledgeable about the phenotype in each study decided to focus on fatal and nonfatal myocardial infarction (MI) as the primary outcome because the MI criteria differed in only trivial ways among the studies. There were some minor differences in the definition of the composite outcome of MI, fatal coronary heart disease, and sudden death, which became the secondary outcome. Only subjects at risk for an incident event were included in the analysis. MI survivors whose DNA was drawn after the event were not eligible. The primary analysis was restricted to Europeans or European Americans. Patients entered the analysis at the time of the DNA blood draw, and were followed until an event, death, loss to follow up, or the last visit. The main recommendations of the Analysis Committee were adopted, and a threshold of 5×10⁻⁸ was selected for genome-wide statistical significance. Analyses in progress include about 1700 MIs and 2300 coronary heart disease events among about 29 000 eligible patients. Each cohort conducted its own analysis, and results were uploaded to a secure share site for the fixed-effects meta-analysis. Even with this number of events (Supplemental Figure 2), power is good for only for relatively high minor allele frequencies (>0.25) and large relative risks (>1.3).

The authors had full access to and take full responsibility for the integrity of the data. All authors have read and agree to the manuscript as written.

Discussion

In thousands of published papers, the 5 CHARGE cohort studies and many of the collaborating studies have already characterized the risk factors for and the incidence and prognosis of a variety of aging-related and cardiovascular conditions. The analysis of the incident MI, for instance, is free from the survival bias typically associated with cross-sectional or case-control studies. The methodologic advantages of the prospective population-based cohort design, the similarity of phenotypes across 5 studies, the availability of genome-wide genotyping data in each cohort, and the need for large sample sizes to provide reliable estimates of genotype-phenotype associations have served as the primary incentives for the formation of the CHARGE consortium, which includes GWAS data on about 38 000 individuals. The consortium effort relies on collaborative methods that are similar to those used by the individual contributing cohorts.

Phenotype experts who know the studies and the data well are responsible for phenotype-standardization across cohorts. The coordinated prospectively planned meta-analyses of CHARGE provide results that are virtually identical to a cohort-adjusted pooled analysis of individual level data. This approach–the within-study analysis followed by a between-study meta-analysis–avoids the human subjects issues associated with individual-level data sharing.

Editors, reviewers, and readers expect replication as the standard in science.6 The finding of a genetic association in one population with evidence for replication in multiple independent populations provides moderate assurance against false-positive reports and helps to establish the validity of the original finding. In a single experiment, the discovery-replication structure is traditionally embodied in a 2-stage design. The CHARGE consortium includes up to 5 independent replicate samples as well as additional collaborating studies for some phenotype working groups, so that it would have been possible to set up analysis plans within CHARGE to mimic the traditional 2-stage design for replication. For instance, the 2 largest cohorts could have served as the discovery set and the others as the replication set. However, attaining the extremely small probability values expected in GWAS requires large sample sizes. For any phenotype, a prospective meta-analysis of all participating cohorts, with a properly selected level of genome-wide statistical significance to minimize the chance of false-positives, is the most powerful approach to finding new genuine associations for genetic loci.25 When findings narrowly miss the prespecified significance threshold, genotyping individuals in other independent populations provides additional evidence about the association. For findings that substantially exceed pre-established significance thresholds, the results of a CHARGE meta-analysis effectively provide evidence of a multistudy replication.

The effort to assemble and manage the CHARGE consortium has provided some interesting and unanticipated challenges. Participating cohorts often had relationships with outside study groups that predated the formation of CHARGE. Timelines for genotyping and imputation have shifted. Purchases of new computer systems for the volume of work were sometimes necessary. Each cohort came to the consortium with their own traditions for methods of analysis, organization, and authorship policies that, while appropriate for their own work, were not always optimal for collaboration with multiple external groups. Within each cohort, the investigators had often formed working groups that divided up the large number of available phenotypes in ways that made sense locally but did not necessarily match the configuration that had been adopted by other cohorts. The Research Steering Committee has attempted to create a set of CHARGE working groups that accommodate the needs and the conventions of the various cohorts. Transparency, disclosure, and professional collaborative behavior by all participating investigators have been essential to the process.

Resource limitations are another challenge. Grant applications that funded the original single-study genome-wide genotyping effort typically imagined a much simpler design. The CHS whole-genome study had as its primary aim, for instance, the analysis of data on 3 endpoints, coronary disease, stroke and heart failure. With a score of active phenotype working groups, the CHARGE collaboration broadened the scope of the short-term work well beyond initial expectations for all the participating cohorts.

One of the premier challenges has been communications among scores of investigators at a dozen sites. CHS and ARIC are themselves multi-site studies. To be successful, the CHARGE collaboration has required effective communications: (1) within each cohort; (2) between cohorts; (3) within the CHARGE working groups; and (4) among the major CHARGE committees. In addition to the traditional methods of conference calls and email, the CHARGE “wiki,” set up by Dr J. Bis (Seattle, Wash), has provided a crucial and highly functional user-driven website for calendars, minutes, guidelines, working group analysis plans, manuscript proposals, and other documents. In the end, there is no substitute for face-to-face meetings, especially at the beginning of the collaboration, and this complex meta-organization has benefited from several CHARGE-wide meetings.

The major emerging opportunity is the collaboration with other studies and consortia. Many working groups have already incorporated nonmember studies into their efforts. Several working groups have coordinated submissions of initial manuscripts with the parallel submission of manuscripts from other studies or consortia. Several working groups have embarked on plans for joint meta-analyses between CHARGE and other consortia. CHARGE has tried to acknowledge and reward the efforts of champions, who assume leadership responsibility for moving these large complex projects forward and who are often hard-working young investigators, the key to the future success of population science.

The CHARGE Consortium represents an innovative model of collaborative research conducted by research teams that know well the strengths, the limitations, and the data from 5 prospective population-based cohort studies. By leveraging the dense genotyping, deep phenotyping and the diverse expertise, prospective meta-analyses are underway to identify and replicate the major common genetic determinants of risk factors, measures of subclinical disease, and clinical events for cardiovascular disease and aging.

SOURCE:

Circulation: Cardiovascular Genetics.2009; 2: 73-80

doi: 10.1161/ CIRCGENETICS.108.829747


Genomics of Ventricular arrhythmias, A-Fib, Right Ventricular Dysplasia, Cardiomyopathy


Comprehensive Desmosome Mutation Analysis in North Americans With Arrhythmogenic Right Ventricular Dysplasia/Cardiomyopathy

A. Dénise den Haan, MD, Boon Yew Tan, MBChB, Michelle N. Zikusoka, MD, Laura Ibañez Lladó, MS, Rahul Jain, MD, Amy Daly, MS, Crystal Tichnell, MGC, Cynthia James, PhD, Nuria Amat-Alarcon, MS, Theodore Abraham, MD, Stuart D. Russell, MD, David A. Bluemke, MD, PhD, Hugh Calkins, MD, Darshan Dalal, MD, PhD and Daniel P. Judge, MD

Author Affiliations

From the Department of Medicine/Cardiology (A.D.d.H., B.Y.T., M.N.Z., L.I.L., R.J., A.D., C.T., C.J., N.A.-A., T.A., S.D.R., H.C., D.D., D.P.J.), Johns Hopkins University School of Medicine, Baltimore, Md; Department of Cardiology, Division of Heart and Lungs (A.D.d.H.), University Medical Center Utrecht, Utrecht, The Netherlands; and National Institutes of Health, Radiology and Imaging Sciences (D.A.B.), Bethesda, Md.

Correspondence to Daniel P. Judge, MD, Johns Hopkins University, Division of Cardiology, Ross 1049; 720 Rutland Avenue, Baltimore, MD 21205. E-mail djudge@jhmi.edu

Abstract

Background— Arrhythmogenic right ventricular dysplasia/cardiomyopathy (ARVD/C) is an inherited disorder typically caused by mutations in components of the cardiac desmosome. The prevalence and significance of desmosome mutations among patients with ARVD/C in North America have not been described previously. We report comprehensive desmosome genetic analysis for 100 North Americans with clinically confirmed or suspected ARVD/C.

Methods and Results— In 82 individuals with ARVD/C and 18 people with suspected ARVD/C, DNA sequence analysis was performed on PKP2, DSG2, DSP, DSC2, and JUP. In those with ARVD/C, 52% harbored a desmosome mutation. A majority of these mutations occurred in PKP2. Notably, 3 of the individuals studied have a mutation in more than 1 gene. Patients with a desmosome mutation were more likely to have experienced ventricular tachycardia (73% versus 44%), and they presented at a younger age (33 versus 41 years) compared with those without a desmosome mutation. Men with ARVD/C were more likely than women to carry a desmosome mutation (63% versus 38%). A mutation was identified in 5 of 18 patients (28%) with suspected ARVD. In this smaller subgroup, there were no significant phenotypic differences identified between individuals with a desmosome mutation compared with those without a mutation.

Conclusions— Our study shows that in 52% of North Americans with ARVD/C a mutation in one of the cardiac desmosome genes can be identified. Compared with those without a desmosome gene mutation, individuals with a desmosome gene mutation had earlier-onset ARVD/C and were more likely to have ventricular tachycardia.

SOURCE:

Circulation: Cardiovascular Genetics.2009; 2: 428-435

Published online before print June 3, 2009,

doi: 10.1161/ CIRCGENETICS.109.858217


Selective Articles citing this article

Genetics of arrhythmogenic right ventricular cardiomyopathy 
J. Med. Genet.. 2013;0:jmedgenet-2013-101523v1-jmedgenet-2013-101523,

AbstractFull Text

Genetic complexity in hypertrophic cardiomyopathy revealed by high-throughput sequencing 
J. Med. Genet.. 2013;0:jmedgenet-2012-101270v1-jmedgenet-2012-101270, 
AbstractFull Text

An Update on Channelopathies: From Mechanisms to Management 
Circulation. 2013;127:126-140,

Full TextPDF

Arrhythmogenic Right Ventricular Cardiomyopathy 
Circ Arrhythm Electrophysiol. 2012;5:1233-1246,

Full TextPDF

Ventricular arrhythmias associated with long-term endurance sports: what is the evidence? 
Br. J. Sports. Med.. 2012;46:i44-i50,

AbstractFull TextPDF

Phospholamban R14del mutation in patients diagnosed with dilated cardiomyopathy or arrhythmogenic right ventricular cardiomyopathy: evidence supporting the concept of arrhythmogenic cardiomyopathy 
Eur J Heart Fail. 2012;14:1199-1207,

AbstractFull TextPDF

Assessing the Significance of Pathogenic Mutations and Autopsy Findings in the Light of 2010 Arrhythmogenic Right Ventricular Cardiomyopathy Diagnostic Criteria: A Clinical Challenge 
Circ Cardiovasc Genet. 2012;5:384-386,

Full TextPDF

Loss of Cadherin-Binding Proteins {beta}-Catenin and Plakoglobin in the Heart Leads to Gap Junction Remodeling and Arrhythmogenesis 
Mol. Cell. Biol.. 2012;32:1056-1067, 
AbstractFull TextPDF

Loss of {alpha}T-catenin alters the hybrid adhering junctions in the heart and leads to dilated cardiomyopathy and ventricular arrhythmia following acute ischemia 
J. Cell Sci.. 2012;125:1058-1067,

AbstractFull TextPDF

General and Disease-Specific Psychosocial Adjustment in Patients With Arrhythmogenic Right Ventricular Dysplasia/Cardiomyopathy With Implantable Cardioverter Defibrillators: A Large Cohort Study 
Circ Cardiovasc Genet. 2012;5:18-24,

AbstractFull TextPDF

Restrictive loss of plakoglobin in cardiomyocytes leads to arrhythmogenic cardiomyopathy 
Hum Mol Genet. 2011;20:4582-4596,

AbstractFull TextPDF

Circulation Editors’ Picks: Most Read Articles in Cardiovascular Genetics, Part I 
Circulation. 2011;124:e345-e357,

AbstractFull TextPDF

Genetic Variation in Titin in Arrhythmogenic Right Ventricular Cardiomyopathy-Overlap Syndromes 
Circulation. 2011;124:876-885,

AbstractFull TextPDF

Circulation: Cardiovascular Genetics Editors’ Picks: A Selection of the Most Important Articles Published 
Circulation. 2011;124:e179-e187,

AbstractFull TextPDF

Sudden Cardiac Arrest Without Overt Heart Disease 
Circulation. 2011;123:2994-3008,

Full TextPDF

Familial Evaluation in Arrhythmogenic Right Ventricular Cardiomyopathy: Impact of Genetics and Revised Task Force Criteria 
Circulation. 2011;123:2701-2709,

AbstractFull TextPDF

Arrhythmogenic Right Ventricular Dysplasia/Cardiomyopathy: Pathogenic Desmosome Mutations in Index-Patients Predict Outcome of Family Screening: Dutch Arrhythmogenic Right Ventricular Dysplasia/Cardiomyopathy Genotype-Phenotype Follow-Up Study 
Circulation. 2011;123:2690-2700,

AbstractFull TextPDF

Arrhythmogenic Right Ventricular Dysplasia/Cardiomyopathy: A Family Affair 
Circulation. 2011;123:2661-2663,

Full TextPDF

Lack of plakoglobin leads to lethal congenital epidermolysis bullosa: a novel clinico-genetic entity 
Hum Mol Genet. 2011;20:1811-1819,

AbstractFull TextPDF

Mechanistic insights into arrhythmogenic right ventricular cardiomyopathy caused by desmocollin-2 mutations 
Cardiovasc Res. 2011;90:77-87,

AbstractFull TextPDF

Cardiac Tissue-Restricted Deletion of Plakoglobin Results in Progressive Cardiomyopathy and Activation of {beta}-Catenin Signaling 
Mol. Cell. Biol.. 2011;31:1134-1144,

AbstractFull TextPDF

Psychological Issues in Genetic Testing for Inherited Cardiovascular Diseases 
Circ Cardiovasc Genet. 2011;4:81-90,

Full TextPDF

De novo desmin-mutation N116S is associated with arrhythmogenic right ventricular cardiomyopathy 
Hum Mol Genet. 2010;19:4595-4607,

AbstractFull TextPDF

Wide spectrum of desmosomal mutations in Danish patients with arrhythmogenic right ventricular cardiomyopathy 
J. Med. Genet.. 2010;47:736-744,

AbstractFull TextPDF

Dilated Cardiomyopathy With Conduction Disease and Arrhythmia 
Circulation. 2010;122:527-534,

Full TextPDF

Lower than expected desmosomal gene mutation prevalence in endurance athletes with complex ventricular arrhythmias of right ventricular origin 
Heart. 2010;96:1268-1274, AbstractFull TextPDF

Desmosomal gene analysis in arrhythmogenic right ventricular dysplasia/cardiomyopathy: spectrum of mutations and clinical impact in practice 
Europace. 2010;12:861-868,

 AbstractFull TextPDF


Large-Scale Candidate Gene Analysis in Whites and African Americans Identifies IL6R Polymorphism in Relation to Atrial Fibrillation

The National Heart, Lung, and Blood Institute’s Candidate Gene Association Resource (CARe) Project

Renate B. Schnabel, MD, MSc*, Kathleen F. Kerr, PhD*, Steven A. Lubitz, MD*, Ermeg L. Alkylbekova, MD*, Gregory M. Marcus, MD, MAS, Moritz F. Sinner, MD, Jared W. Magnani, MD, Philip A. Wolf, MD, Rajat Deo, MD, Donald M. Lloyd-Jones, MD, ScM, Kathryn L. Lunetta, PhD, Reena Mehra, MD, MS, Daniel Levy, MD, Ervin R. Fox, MD, MPH, Dan E. Arking, PhD, Thomas H. Mosley, PhD, Martina Müller-Nurasyid, MSc, PhD, Taylor R. Young, MA, H.-Erich Wichmann, MD, PhD, Sudha Seshadri, MD, Deborah N. Farlow, PhD, Jerome I. Rotter, MD, Elsayed Z. Soliman, MD, MSc, MS, Nicole L. Glazer, PhD, James G. Wilson, MD, Monique M.B. Breteler, MD, Nona Sotoodehnia, MD, MPH, Christopher Newton-Cheh, MD, MPH, Stefan Kääb, MD, PhD, Patrick T. Ellinor, MD, PhD*, Alvaro Alonso, MD*, Emelia J. Benjamin, MD, ScM*, Susan R. Heckbert, MD, PhD* and for the Candidate Gene Association Resource (CARe) Atrial Fibrillation/Electrocardiography Working Group

Correspondence to Susan R. Heckbert, MD, PhD, Cardiovascular Health Research Unit, University of Washington, 1730 Minor Ave, Suite 1360, Seattle, WA 98101. E-mail heckbert@u.washington.edu; Emelia J. Benjamin, MD, ScM, Medicine and Epidemiology, Boston University Schools of Medicine and Public Health, The Framingham Heart Study, 73 Mount Wayte Ave, Framingham, MA 01702–5827. E-mail emelia@bu.edu; Renate B. Schnabel, MD, MSc, Department of Medicine 2, Cardiology, Johannes Gutenberg University, Langenbeckstr 1, 55131 Mainz, Germany. E-mail schnabelr@gmx.de

↵* These authors contributed equally to the manuscript.

Abstract

Background—The genetic background of atrial fibrillation (AF) in whites and African Americans is largely unknown. Genes in cardiovascular pathways have not been systematically investigated.

Methods and Results—We examined a panel of approximately 50 000 common single-nucleotide polymorphisms (SNPs) in 2095 cardiovascular candidate genes and AF in 3 cohorts with participants of European (n=18 524; 2260 cases) or African American descent (n=3662; 263 cases) in the National Heart, Lung, and Blood Institute’s Candidate Gene Association Resource. Results in whites were followed up in the German Competence Network for AF (n=906, 468 cases). The top result was assessed in relation to incident ischemic stroke in the Cohorts for Heart and Aging Research in Genomic Epidemiology Stroke Consortium (n=19 602 whites, 1544 incident strokes). SNP rs4845625 in the IL6R gene was associated with AF (relative risk [RR] C allele, 0.90; 95% confidence interval [CI], 0.85–0.95; P=0.0005) in whites but did not reach statistical significance in African Americans (RR, 0.86; 95% CI, 0.72–1.03; P=0.09). The results were comparable in the German AF Network replication, (RR, 0.71; 95% CI, 0.57–0.89; P=0.003). No association between rs4845625 and stroke was observed in whites. The known chromosome 4 locus near PITX2 in whites also was associated with AF in African Americans (rs4611994; hazard ratio, 1.40; 95% CI, 1.16–1.69; P=0.0005).

Conclusions—In a community-based cohort meta-analysis, we identified genetic association in IL6R with AF in whites. Additionally, we demonstrated that the chromosome 4 locus known from recent genome-wide association studies in whites is associated with AF in African Americans.

 SOURCE:

Circulation: Cardiovascular Genetics.2011; 4: 557-564

Published online before print August 16, 2011,

doi: 10.1161/ CIRCGENETICS.110.959197

PITX2c Is Expressed in the Adult Left Atrium, and Reducing Pitx2c Expression Promotes Atrial Fibrillation Inducibility and Complex Changes in Gene Expression

Paulus Kirchhof, MD*, Peter C. Kahr*, Sven Kaese, Ilaria Piccini, PhD, Ismail Vokshi, BSc, Hans-Heinrich Scheld, MD, Heinrich Rotering, MD, Lisa Fortmueller, MD (vet), Sandra Laakmann, MD (vet), Sander Verheule, PhD, Ulrich Schotten, MD, PhD, Larissa Fabritz, MD and Nigel A. Brown, PhD

Author Affiliations

From the Department of Cardiology and Angiology (P.K., P.C.K., S.K., I.P., L.F., S.L., L.F.) and the Department of Thoracic and Cardiovascular Surgery (H.-H.S., H.R.), University Hospital Muenster, Germany; Division of Biomedical Sciences (P.C.K., I.V., N.A.B.), St. George’s, University of London, United Kingdom; and the Department of Physiology (S.V., U.S.), Maastricht University, The Netherlands.

Correspondence to Nigel A. Brown, PhD, Division of Biomedical Sciences, St George’s, University of London, Cranmer Terrace, London, SW17 0RE, UK. E-mail nbrown@sgul.ac.uk

↵* Drs Kirchhof and Kahr contributed equally to this work.

Abstract

Background— Intergenic variations on chromosome 4q25, close to the PITX2 transcription factor gene, are associated with atrial fibrillation (AF). We therefore tested whether adult hearts express PITX2 and whether variation in expression affects cardiac function.

Methods and Results— mRNA for PITX2 isoform c was expressed in left atria of human and mouse, with levels in right atrium and left and right ventricles being 100-fold lower. In mice heterozygous for Pitx2c (Pitx2c+/−), left atrial Pitx2c expression was 60% of wild-type and cardiac morphology and function were not altered, except for slightly elevated pulmonary flow velocity. Isolated Pitx2c+/− hearts were susceptible to AF during programmed stimulation. At short paced cycle lengths, atrial action potential durations were shorter in Pitx2c+/− than in wild-type. Perfusion with the β-receptor agonist orciprenaline abolished inducibility of AF and reduced the effect on action potential duration. Spontaneous heart rates, atrial conduction velocities, and activation patterns were not affected in Pitx2c+/− hearts, suggesting that action potential duration shortening caused wave length reduction and inducibility of AF. Expression array analyses comparing Pitx2c+/− with wild-type, for left atrial and right atrial tissue separately, identified genes related to calcium ion binding, gap and tight junctions, ion channels, and melanogenesis as being affected by the reduced expression of Pitx2c.

Conclusions— These findings demonstrate a physiological role for PITX2 in the adult heart and support the hypothesis that dysregulation of PITX2 expression can be responsible for susceptibility to AF.

 SOURCE:

Circulation: Cardiovascular Genetics.2011; 4: 123-133

Published online before print January 31, 2011,

doi: 10.1161/ CIRCGENETICS.110.958058


Genetics of CVD and Hyperlipidemia, Hyper Cholesterolemia, Metabolic Syndrome


Genetic Loci Associated With Plasma Concentration of Low-Density Lipoprotein Cholesterol, High-Density Lipoprotein Cholesterol, Triglycerides, Apolipoprotein A1, and Apolipoprotein B Among 6382 White Women in Genome-Wide Analysis With Replication

Daniel I. Chasman, PhD*, Guillaume Paré, MD, MS*, Robert Y.L. Zee, PhD, MPH, Alex N. Parker, PhD, Nancy R. Cook, ScD, Julie E. Buring, ScD, David J. Kwiatkowski, MD, PhD, Lynda M. Rose, MS, Joshua D. Smith, BS, Paul T. Williams, PhD, Mark J. Rieder, PhD, Jerome I. Rotter, MD, Deborah A. Nickerson, PhD, Ronald M. Krauss, MD, Joseph P. Miletich, MD and Paul M Ridker, MD, MPH

Author Affiliations

From the Center for Cardiovascular Disease Prevention (D.I.C., G.P., R.Y.L.Z., N.R.C., J.E.B., L.M.R., P.M.R.) and Donald W. Reynolds Center for Cardiovascular Research (D.I.C., G.P., R.Y.L.Z., N.R.C., D.J.K., P.M.R.), Brigham and Women’s Hospital, Harvard Medical School, Boston, Mass; Amgen, Inc, Cambridge, Mass (A.N.P., J.M.P.); Department of Genome Sciences, University of Washington, Seattle, Wash (J.D.S., M.J.R., D.A.N.); Life Science Division, Lawrence Berkeley National Laboratory, Berkeley, Calif (P.T.W., R.M.K.); Medical Genetics Institute, Cedars-Sinai Medical Center, Los Angeles, Calif (J.I.R.); and Children’s Hospital Oakland Research Institute, Oakland, Calif (R.M.K.).

Correspondence to Daniel I. Chasman, Center for Cardiovascular Disease Prevention, Brigham and Women’s Hospital, 900 Commonwealth Ave E, Boston, MA 02215. E-mail dchasman@rics.bwh.harvard.edu

Abstract

Background— Genome-wide genetic association analysis represents an opportunity for a comprehensive survey of the genes governing lipid metabolism, potentially revealing new insights or even therapeutic strategies for cardiovascular disease and related metabolic disorders.

Methods and Results— We have performed large-scale, genome-wide genetic analysis among 6382 white women with replication in 2 cohorts of 970 additional white men and women for associations between common single-nucleotide polymorphisms and low-density lipoprotein cholesterol, high-density lipoprotein cholesterol, triglycerides, apolipoprotein (Apo) A1, and ApoB. Genome-wide associations (P<5×10⁻⁸) were found at the PCSK9 gene, the APOB gene, the LPL gene, the APOA1-APOA5 locus, the LIPC gene, the CETP gene, the LDLR gene, and the APOE locus. In addition, genome-wide associations with triglycerides at the GCKR gene confirm and extend emerging links between glucose and lipid metabolism. Still other genome-wide associations at the 1p13.3 locus are consistent with emerging biological properties for a region of the genome, possibly related to the SORT1 gene. Below genome-wide significance, our study provides confirmatory evidence for associations at 5 novel loci with low-density lipoprotein cholesterol, high-density lipoprotein cholesterol, or triglycerides reported recently in separate genome-wide association studies. The total proportion of variance explained by common variation at the genome-wide candidate loci ranges from 4.3% for triglycerides to 12.6% for ApoB.

Conclusion— Genome-wide associations at the GCKR gene and near the SORT1 gene, as well as confirmatory associations at 5 additional novel loci, suggest emerging biological pathways for lipid metabolism among white women.

 SOURCE:

Circulation: Cardiovascular Genetics.2008; 1: 21-30

doi: 10.1161/ CIRCGENETICS.108.773168


Integrated Computational and Experimental Analysis of the Neuroendocrine Transcriptome in Genetic Hypertension Identifies Novel Control Points for the Cardiometabolic Syndrome

Ryan S. Friese, PhD, Chun Ye, PhD, Caroline M. Nievergelt, PhD, Andrew J. Schork, BS, Nitish R. Mahapatra, PhD, Fangwen Rao, MD, Philip S. Napolitan, BS, Jill Waalen, MD, MPH, Georg B. Ehret, MD, Patricia B. Munroe, PhD, Geert W. Schmid-Schönbein, PhD, Eleazar Eskin, PhD and Daniel T. O’Connor, MD

Author Affiliations

From the Departments of Bioengineering (R.S.F., G.W.S.-S.), Medicine (R.S.F., A.J.S., F.R., P.S.N., D.T.O.), Pharmacology (D.T.O.), and Psychiatry (C.M.N.), the Bioinformatics Program (C.Y.), and the Institute for Genomic Medicine (D.T.O.), University of California at San Diego; the VA San Diego Healthcare System, San Diego, CA (D.T.O.); the Departments of Computer Science & Human Genetics, University of California at Los Angeles (E.E.); the Department of Biotechnology, Indian Institute of Technology Madras, Chennai, India (N.R.M.); Clinical Pharmacology and The Genome Centre, William Harvey Research Institute, Barts and The London School of Medicine and Dentistry, Queen Mary University of London, London, United Kingdom (P.B.M.); Center for Complex Disease Genomics, McKusick-Nathans Institute of Genetic Medicine, Johns Hopkins University School of Medicine, Baltimore, MD (G.B.E.); and Scripps Research Institute, La Jolla, CA (J.W.).

Correspondence to Daniel T. O’Connor, MD, Department of Medicine, University of California at San Diego School of Medicine, VASDHS (0838), Skaggs (SSPPS) Room 4256, 9500 Gilman Drive, La Jolla, CA 92093-0838. E-mail doconnor@ucsd.edu

Abstract

Background—Essential hypertension, a common complex disease, displays substantial genetic influence. Contemporary methods to dissect the genetic basis of complex diseases such as the genomewide association study are powerful, yet a large gap exists betweens the fraction of population trait variance explained by such associations and total disease heritability.

Methods and Results—We developed a novel, integrative method (combining animal models, transcriptomics, bioinformatics, molecular biology, and trait-extreme phenotypes) to identify candidate genes for essential hypertension and the metabolic syndrome. We first undertook transcriptome profiling on adrenal glands from blood pressure extreme mouse strains: the hypertensive BPH (blood pressure high) and hypotensive BPL (blood pressure low). Microarray data clustering revealed a striking pattern of global underexpression of intermediary metabolism transcripts in BPH. The MITRA algorithm identified a conserved motif in the transcriptional regulatory regions of the underexpressed metabolic genes, and we then hypothesized that regulation through this motif contributed to the global underexpression. Luciferase reporter assays demonstrated transcriptional activity of the motif through transcription factors HOXA3, SRY, and YY1. We finally hypothesized that genetic variation at HOXA3, SRY, and YY1 might predict blood pressure and other metabolic syndrome traits in humans. Tagging variants for each locus were associated with blood pressure in a human population blood pressure extreme sample with the most extensive associations for YY1 tagging single nucleotide polymorphism rs11625658 on systolic blood pressure, diastolic blood pressure, body mass index, and fasting glucose. Meta-analysis extended the YY1 results into 2 additional large population samples with significant effects preserved on diastolic blood pressure, body mass index, and fasting glucose.

Conclusions—The results outline an innovative, systematic approach to the genetic pathogenesis of complex cardiovascular disease traits and point to transcription factor YY1 as a potential candidate gene involved in essential hypertension and the cardiometabolic syndrome.

 SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 430-440

Published online before print June 5, 2012,

doi: 10.1161/ CIRCGENETICS.111.962415


Associations Between Incident Ischemic Stroke Events and Stroke and Cardiovascular Disease-Related Genome-Wide Association Studies Single Nucleotide Polymorphisms in the Population Architecture Using Genomics and Epidemiology Study

Cara L. Carty, PhD, Petra Bůžková, PhD, Myriam Fornage, PhD, Nora Franceschini, MD, Shelley Cole, PhD, Gerardo Heiss, MD, PhD, Lucia A. Hindorff, PhD, MPH, Barbara V. Howard, PhD, Sue Mann, MPH, Lisa W. Martin, MD, Ying Zhang, PhD, Tara C. Matise, PhD, Ross Prentice, PhD, Alexander P. Reiner, MD, MS and Charles Kooperberg, PhD

Author Affiliations

From the Public Health Sciences, Fred Hutchinson Cancer Research Center (C.L.C., S.M., R.P., C.K.); Department of Biostatistics, University of Washington, Seattle, WA (P.B.); Institute of Molecular Medicine, University of Texas Health Sciences Center at Houston, Houston, TX (M.F.); Division of Epidemiology, School of Public Health, University of Texas Health Sciences Center, Houston, TX (M.F.); Department of Epidemiology, University of North Carolina, Chapel Hill, NC (N.F., G.H.); Department of Genetics, Texas Biomedical Research Institute, San Antonio, TX (S.C.); Office of Population Genomics, National Human Genome Research Institute, Bethesda, MD (L.A.H.); Medstar Health Research Institute, Washington, DC (B.V.H.); George Washington University School of Medicine, Washington, DC (B.V.H., L.W.M.); University of Oklahoma Health Sciences Center, Oklahoma City, OK (Y.Z.); Department of Genetics, Rutgers University, Piscataway, NJ (T.C.M.); Department of Epidemiology, University of Washington, Seattle, WA (A.P.R.).

Correspondence to Dr Cara L. Carty, Fred Hutchinson Cancer Research Center, 1100 Fairview Ave N./M3-A410, Seattle, WA 98109. E-mail ccarty@fhcrc.org

Abstract

Background—Genome-wide association studies (GWAS) have identified loci associated with ischemic stroke (IS) and cardiovascular disease (CVD) in European-descent individuals, but their replication in different populations has been largely unexplored.

Methods and Results—Nine single nucleotide polymorphisms (SNPs) selected from GWAS and meta-analyses of stroke, and 86 SNPs previously associated with myocardial infarction and CVD risk factors, including blood lipids (high density lipoprotein [HDL], low density lipoprotein [LDL], and triglycerides), type 2 diabetes, and body mass index (BMI), were investigated for associations with incident IS in European Americans (EA) N=26 276, African-Americans (AA) N=8970, and American Indians (AI) N=3570 from the Population Architecture using Genomics and Epidemiology Study. Ancestry-specific fixed effects meta-analysis with inverse variance weighting was used to combine study-specific log hazard ratios from Cox proportional hazards models. Two of 9 stroke SNPs (rs783396 and rs1804689) were associated with increased IS hazard in AA; none were significant in this large EA cohort. Of 73 CVD risk factor SNPs tested in EA, 2 (HDL and triglycerides SNPs) were associated with IS. In AA, SNPs associated with LDL, HDL, and BMI were significantly associated with IS (3 of 86 SNPs tested). Out of 58 SNPs tested in AI, 1 LDL SNP was significantly associated with IS.

Conclusions—Our analyses showing lack of replication in spite of reasonable power for many stroke SNPs and differing results by ancestry highlight the need to follow up on GWAS findings and conduct genetic association studies in diverse populations. We found modest IS associations with BMI and lipids SNPs, though these findings require confirmation.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 210-216

Published online before print March 8, 2012,

doi: 10.1161/ CIRCGENETICS.111.962191


Common Variation in Fatty Acid Genes and Resuscitation From Sudden Cardiac Arrest

Catherine O. Johnson, PhD, MPH, Rozenn N. Lemaitre, PhD, MPH, Carol E. Fahrenbruch, MSPH, Stephanie Hesselson, PhD, Nona Sotoodehnia, MD, MPH, Barbara McKnight, PhD, Kenneth M. Rice, PhD, Pui-Yan Kwok, MD, PhD, David S. Siscovick, MD, MPH and Thomas D. Rea, MD, MPH

Author Affiliations

From the Departments of Medicine (C.O.J., R.N.L., N.S., D.S.S., T.D.R.), Biostatistics (B.M., K.M.R.), and Epidemiology (D.S.S), University of Washington, Seattle; King County Emergency Medical Services, Seattle, WA (C.E.F.); and Institute of Human Genetics, University of California San Francisco (S.H., P.-Y.K.).

Correspondence to Catherine O. Johnson, PhD, MPH, Department of Medicine, University of Washington, CHRU 1730 Minor Ave, Suite 1360, Seattle, WA 98101. E-mail johnsoco@uw.edu

Abstract

Background—Fatty acids provide energy and structural substrates for the heart and brain and may influence resuscitation from sudden cardiac arrest (SCA). We investigated whether genetic variation in fatty acid metabolism pathways was associated with SCA survival.

Methods and Results—Subjects (mean age, 67 years; 80% male, white) were out-of-hospital SCA patients found in ventricular fibrillation in King County, WA. We compared subjects who survived to hospital admission (n=664) with those who did not (n=689), and subjects who survived to hospital discharge (n=334) with those who did not (n=1019). Associations between survival and genetic variants were assessed using logistic regression adjusting for age, sex, location, time to arrival of paramedics, whether the event was witnessed, and receipt of bystander cardiopulmonary resuscitation. Within-gene permutation tests were used to correct for multiple comparisons. Variants in 5 genes were significantly associated with SCA survival. After correction for multiple comparisons, single-nucleotide polymorphisms in ACSL1 and ACSL3 were significantly associated with survival to hospital admission. Single-nucleotide polymorphisms in ACSL3, AGPAT3, MLYCD, and SLC27A6 were significantly associated with survival to hospital discharge.

Conclusions—Our findings indicate that variants in genes important in fatty acid metabolism are associated with SCA survival in this population.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 422-429

Published online before print June 1, 2012,

doi: 10.1161/ CIRCGENETICS.111.961912


Genome-Wide Association Study Pinpoints a New Functional Apolipoprotein B Variant Influencing Oxidized Low-Density Lipoprotein Levels But Not Cardiovascular Events

AtheroRemo Consortium

Kari-Matti Mäkelä, BM, BSc, Ilkka Seppälä, MSc, Jussi A. Hernesniemi, MD, PhD, Leo-Pekka Lyytikäinen, MD, Niku Oksala, MD, PhD, DSc, Marcus E. Kleber, PhD, Hubert Scharnagl, PhD, Tanja B. Grammer, MD, Jens Baumert, PhD, Barbara Thorand, PhD, Antti Jula, MD, PhD, Nina Hutri-Kähönen, MD, PhD, Markus Juonala, MD, PhD, Tomi Laitinen, MD, PhD, Reijo Laaksonen, MD, PhD, Pekka J. Karhunen, MD, PhD, Kjell C. Nikus, MD, PhD, Tuomo Nieminen, MD, PhD, MSc, Jari Laurikka, MD, PhD, Pekka Kuukasjärvi, MD, PhD, Matti Tarkka, MD, PhD, Jari Viik, PhD, Norman Klopp, PhD, Thomas Illig, PhD, Johannes Kettunen, PhD, Markku Ahotupa, PhD, Jorma S.A. Viikari, MD, PhD, Mika Kähönen, MD, PhD, Olli T. Raitakari, MD, PhD, Mahir Karakas, MD, Wolfgang Koenig, MD, PhD, Bernhard O. Boehm, MD, Bernhard R. Winkelmann, MD, Winfried März, MD and Terho Lehtimäki, MD, PhD

Correspondence to Kari-Matti Mäkelä, Department of Clinical Chemistry, Finn-Medi 2, PO Box 2000, FI-33521 Tampere, Finland. E-mail kari-matti.makela@uta.fi

Abstract

Background—Oxidized low-density lipoprotein may be a key factor in the development of atherosclerosis. We performed a genome-wide association study on oxidized low-density lipoprotein and tested the impact of associated single-nucleotide polymorphisms (SNPs) on the risk factors of atherosclerosis and cardiovascular events.

Methods and Results—A discovery genome-wide association study was performed on a population of young healthy white individuals (N=2080), and the SNPs associated with a P<5×10⁻⁸ were replicated in 2 independent samples (A: N=2912; B: N=1326). Associations with cardiovascular endpoints were also assessed with 2 additional clinical cohorts (C: N=1118; and D: N=808). We found 328 SNPs associated with oxidized low-density lipoprotein. The genetic variant rs676210 (Pro2739Leu) in apolipoprotein B was the proxy SNP behind all associations (P=4.3×10–136, effect size=13.2 U/L per allele). This association was replicated in the 2 independent samples (A and B, P=2.5×10–47 and 1.1×10⁻¹¹, effect sizes=10.3 U/L and 7.8 U/L, respectively). In the meta-analyses of cohorts A, C, and D (excluding cohort B without angiographic data), the top SNP did not associate significantly with the age of onset of angiographically verified coronary artery disease (hazard ratio=1.00 [0.94–1.06] per allele), 3-vessel coronary artery disease (hazard ratio=1.03 [0.94–1.13]), or myocardial infarction (hazard ratio=1.04 [0.96–1.12]).

Conclusions—This novel genetic marker is an important factor regulating oxidized low-density lipoprotein levels but not a major genetic factor for the studied cardiovascular endpoints.

 SOURCE:

Circulation: Cardiovascular Genetics.2013; 6: 73-81

Published online before print December 17, 2012,

doi: 10.1161/ CIRCGENETICS.112.964965

Genome-Wide Screen for Metabolic Syndrome Susceptibility Loci Reveals Strong Lipid Gene Contribution But No Evidence for Common Genetic Basis for Clustering of Metabolic Syndrome Traits

Kati Kristiansson, PhD, Markus Perola, MD, PhD, Emmi Tikkanen, MSc, Johannes Kettunen, PhD, Ida Surakka, MSc, Aki S. Havulinna, DSc (Tech.), Alena Stančáková, MD, PhD, Chris Barnes, PhD, Elisabeth Widen, MD, PhD, Eero Kajantie, MD, PhD, Johan G. Eriksson, MD, DMSc, Jorma Viikari, MD, PhD, Mika Kähönen, MD, PhD, Terho Lehtimäki, MD, PhD, Olli T. Raitakari, MD, PhD, Anna-Liisa Hartikainen, MD, PhD, Aimo Ruokonen, MD, PhD, Anneli Pouta, MD, PhD, Antti Jula, MD, PhD, Antti J. Kangas, MSc, Pasi Soininen, PhD, Mika Ala-Korpela, PhD, Satu Männistö, PhD, Pekka Jousilahti, MD, PhD, Lori L. Bonnycastle, PhD, Marjo-Riitta Järvelin, MD, PhD, Johanna Kuusisto, MD, PhD, Francis S. Collins, MD, PhD, Markku Laakso, MD, PhD, Matthew E. Hurles, PhD, Aarno Palotie, MD, PhD, Leena Peltonen, MD, PhD*, Samuli Ripatti, PhD and Veikko Salomaa, MD, PhD

Correspondence to Dr Kati Kristiansson, National Institute for Health and Welfare, University of Helsinki, Biomedicum, PL 104, FI-00251 Helsinki, Finland. E-mail kati.kristiansson@thl.fi

Abstract

Background—Genome-wide association (GWA) studies have identified several susceptibility loci for metabolic syndrome (MetS) component traits, but have had variable success in identifying susceptibility loci to the syndrome as an entity. We conducted a GWA study on MetS and its component traits in 4 Finnish cohorts consisting of 2637 MetS cases and 7927 controls, both free of diabetes, and followed the top loci in an independent sample with transcriptome and nuclear magnetic resonance-based metabonomics data. Furthermore, we tested for loci associated with multiple MetS component traits using factor analysis, and built a genetic risk score for MetS.

Methods and Results—A previously known lipid locus, APOA1/C3/A4/A5 gene cluster region (SNP rs964184), was associated with MetS in all 4 study samples (P=7.23×10⁻⁹ in meta-analysis). The association was further supported by serum metabolite analysis, where rs964184 was associated with various very low density lipoprotein, triglyceride, and high-density lipoprotein metabolites (P=0.024–1.88×10⁻⁵). Twenty-two previously identified susceptibility loci for individual MetS component traits were replicated in our GWA and factor analysis. Most of these were associated with lipid phenotypes, and none with 2 or more uncorrelated MetS components. A genetic risk score, calculated as the number of risk alleles in loci associated with individual MetS traits, was strongly associated with MetS status.

Conclusions—Our findings suggest that genes from lipid metabolism pathways have the key role in the genetic background of MetS. We found little evidence for pleiotropy linking dyslipidemia and obesity to the other MetS component traits, such as hypertension and glucose intolerance.

 SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 242-249

Published online before print March 7, 2012,

doi: 10.1161/ CIRCGENETICS.111.961482


Genetics and Vascular Pathologies and Platelet Aggregation, Cardiac Troponin T in Serum


TGFβRIIb Mutations Trigger Aortic Aneurysm Pathogenesis by Altering Transforming Growth Factor β2 Signal Transduction

Katharine J. Bee, PhD, David C. Wilkes, PhD, Richard B. Devereux, MD, Craig T. Basson, MD, PhD and Cathy J. Hatcher, PhD

Author Affiliations

From the Center for Molecular Cardiology, Greenberg Division of Cardiology, Weill Cornell Medical College, New York, NY.

Correspondence to Cathy J. Hatcher, PhD, Greenberg Division of Cardiology, Weill Cornell Medical College, 525 E. 68th St, New York, NY 10065. E-mail cjhatche@med.cornell.edu

Abstract

Background—Thoracic aortic aneurysm (TAA) is a common progressive disorder involving gradual dilation of the ascending and/or descending thoracic aorta that eventually leads to dissection or rupture. Nonsydromic TAA can occur as a genetically triggered, familial disorder that is usually transmitted in a monogenic autosomal dominant fashion and is known as familial TAA. Genetic analyses of families affected with TAA have identified several chromosomal loci, and further mapping of familial TAA genes has highlighted disease-causing mutations in at least 4 genes: myosin heavy chain 11 (MYH11), α-smooth muscle actin (ACTA2), and transforming growth factor β receptors I and II (TGFβRI and TGFβRII).

Methods and Results—We evaluated 100 probands to determine the mutation frequency in MYH11, ACTA2, TGFβRI, and TGFβRII in an unbiased population of individuals with genetically mediated TAA. In this study, 9% of patients had a mutation in one of the genes analyzed, 3% of patients had mutations in ACTA2, 3% in MYH11, 1% in TGFβRII, and no mutations were found in TGFβRI. Additionally, we identified mutations in a 75 base pair alternatively spliced TGFβRII exon, exon 1a that produces the TGFβRIIb isoform and accounted for 2% of patients with mutations. Our in vitro analyses indicate that the TGFβRIIb activating mutations alter receptor function on TGFβ2 signaling.

Conclusions—We propose that TGFβRIIb expression is a regulatory mechanism for TGFβ2 signal transduction. Dysregulation of the TGFβ2 signaling pathway, as a consequence of TGFβRIIb mutations, results in aortic aneurysm pathogenesis.

SOURCE: 

Circulation: Cardiovascular Genetics.2012; 5: 621-629

Published online before print October 24, 2012,doi: 10.1161/​CIRCGENETICS.112.964064

Matrix Metalloproteinase-9 Genotype as a Potential Genetic Marker for Abdominal Aortic Aneurysm

Tyler Duellman, BS, Christopher L. Warren, PhD, Peggy Peissig, PhD, Martha Wynn, MD and Jay Yang, MD, PhD

Author Affiliations

From the Molecular and Cellular Pharmacology Graduate Program (T.D., J.Y.) and Department of Anesthesiology (M.W., J.Y.), University of Wisconsin School of Medicine and Public Health, Madison; Illumavista Biosciences LLC, Madison, WI (C.L.W.); and Biomedical Informatics Research Center, Marshfield Clinics Research Foundation, Marshfield, WI (P.P.).

Correspondence to Jay Yang, MD, PhD, Department of Anesthesiology, University of Wisconsin SMPH, SMI 301, 1300 University Ave, Madison, WI 53706. E-mail Jyang75@wisc.edu

Abstract

Background—Degradation of extracellular matrix support in the large abdominal arteries contribute to abnormal dilation of aorta, leading to abdominal aortic aneurysms, and matrix metalloproteinase-9 (MMP-9) is the predominant enzyme targeting elastin and collagen present in the walls of the abdominal aorta. Previous studies have suggested a potential association between MMP-9 genotype and abdominal aortic aneurysm, but these studies have been limited only to the p-1562 and (CA) dinucleotide repeat microsatellite polymorphisms in the promoter region of the MMP-9 gene. We determined the functional alterations caused by 15 MMP-9 single-nucleotide polymorphisms (SNPs) reported to be relatively abundant in the human genome through Western blots, gelatinase, and promoter–reporter assays and incorporated this information to perform a logistic-regression analysis of MMP-9 SNPs in 336 human abdominal aortic aneurysm cases and controls.

Methods and Results—Significant functional alterations were observed for 6 exon SNPs and 4 promoter SNPs. Genotype analysis of frequency-matched (age, sex, history of hypertension, hypercholesterolemia, and smoking) cases and controls revealed significant genetic heterogeneity exceeding 20% observed for 6 SNPs in our population of mostly white subjects from Northern Wisconsin. A step-wise logistic-regression analysis with 6 functional SNPs, where weakly contributing confounds were eliminated using Akaike information criteria, gave a final 2 SNP (D165N and p-2502) model with an overall odds ratio of 2.45 (95% confidence interval, 1.06–5.70).

Conclusions—The combined approach of direct experimental confirmation of the functional alterations of MMP-9 SNPs and logistic-regression analysis revealed significant association between MMP-9 genotype and abdominal aortic aneurysm.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 529-537

Published online before print August 31, 2012,

doi: 10.1161/ CIRCGENETICS.112.963082

Common Genetic Variation in the 3′–BCL11B Gene Desert Is Associated With Carotid-Femoral Pulse Wave Velocity and Excess Cardiovascular Disease Risk

The AortaGen Consortium

Gary F. Mitchell, MD*, Germaine C. Verwoert, MSc*, Kirill V. Tarasov, MD, PhD*, Aaron Isaacs, PhD, Albert V. Smith, PhD, Yasmin, BSc, MA, PhD, Ernst R. Rietzschel, MD, PhD, Toshiko Tanaka, PhD, Yongmei Liu, MD, PhD, Afshin Parsa, MD, MPH, Samer S. Najjar, MD, Kevin M. O’Shaughnessy, MA, BM, DPhil, FRCP, Sigurdur Sigurdsson, MSc, Marc L. De Buyzere, MSc, Martin G. Larson, ScD, Mark P.S. Sie, MD, PhD, Jeanette S. Andrews, MS, Wendy S. Post, MD, MS, Francesco U.S. Mattace-Raso, MD, PhD, Carmel M. McEniery, BSc, PhD, Gudny Eiriksdottir, MSc, Patrick Segers, PhD, Ramachandran S. Vasan, MD, Marie Josee E. van Rijn, MD, PhD, Timothy D. Howard, PhD, Patrick F. McArdle, PhD, Abbas Dehghan, MD, PhD, Elizabeth S. Jewell, MS, Stephen J. Newhouse, MSc, PhD, Sofie Bekaert, PhD, Naomi M. Hamburg, MD, Anne B. Newman, MD, MPH, Albert Hofman, MD, PhD, Angelo Scuteri, MD, PhD, Dirk De Bacquer, PhD, Mohammad Arfan Ikram, MD, PhD†, Bruce M. Psaty, MD, PhD†, Christian Fuchsberger, PhD‡, Matthias Olden, PhD‡, Louise V. Wain, PhD§, Paul Elliott, MB, PhD§, Nicholas L. Smith, PhD‖, Janine F. Felix, MD, PhD‖, Jeanette Erdmann, PhD¶, Joseph A. Vita, MD, Kim Sutton-Tyrrell, PhD, Eric J.G. Sijbrands, MD, PhD, Serena Sanna, PhD, Lenore J. Launer, MS, PhD, Tim De Meyer, PhD, Andrew D. Johnson, MD, Anna F.C. Schut, MD, PhD, David M. Herrington, MD, MHS, Fernando Rivadeneira, MD, PhD, Manuela Uda, PhD, Ian B. Wilkinson, MA, BM, FRCP, Thor Aspelund, PhD, Thierry C. Gillebert, MD, PhD, Luc Van Bortel, MD, PhD, Emelia J. Benjamin, MD, MSc, Ben A. Oostra, PhD, Jingzhong Ding, MD, PhD, Quince Gibson, MBA, André G. Uitterlinden, PhD, Gonçalo R. Abecasis, PhD, John R. Cockcroft, BSc, MB, ChB, FRCP, Vilmundur Gudnason, MD, PhD, Guy G. De Backer, MD, PhD, Luigi Ferrucci, MD, Tamara B. Harris, MD, MS, Alan R. Shuldiner, MD, Cornelia M. van Duijn, PhD, Daniel Levy, MD*, Edward G. Lakatta, MD* and Jacqueline C.M. Witteman, PhD*

Correspondence to Gary F. Mitchell, MD, Cardiovascular Engineering, Inc, 1 Edgewater Dr, Suite 201A, Norwood, MA 02062. E-mail GaryFMitchell@mindspring.com

↵* These authors contributed equally.

Abstract

Background—Carotid-femoral pulse wave velocity (CFPWV) is a heritable measure of aortic stiffness that is strongly associated with increased risk for major cardiovascular disease events.

Methods and Results—We conducted a meta-analysis of genome-wide association data in 9 community-based European ancestry cohorts consisting of 20 634 participants. Results were replicated in 2 additional European ancestry cohorts involving 5306 participants. Based on a preliminary analysis of 6 cohorts, we identified a locus on chromosome 14 in the 3′-BCL11B gene desert that is associated with CFPWV (rs7152623, minor allele frequency=0.42, β=−0.075±0.012 SD/allele, P=2.8×10⁻¹⁰; replication β=−0.086±0.020 SD/allele, P=1.4×10⁻⁶). Combined results for rs7152623 from 11 cohorts gave β=−0.076±0.010 SD/allele, P=3.1×10⁻¹⁵. The association persisted when adjusted for mean arterial pressure (β=−0.060±0.009 SD/allele, P=1.0×10⁻¹¹). Results were consistent in younger (<55 years, 6 cohorts, n=13 914, β=−0.081±0.014 SD/allele, P=2.3×10⁻⁹) and older (9 cohorts, n=12 026, β=−0.061±0.014 SD/allele, P=9.4×10⁻⁶) participants. In separate meta-analyses, the locus was associated with increased risk for coronary artery disease (hazard ratio=1.05; confidence interval=1.02–1.08; P=0.0013) and heart failure (hazard ratio=1.10, CI=1.03–1.16, P=0.004).

Conclusions—Common genetic variation in a locus in the BCL11B gene desert that is thought to harbor 1 or more gene enhancers is associated with higher CFPWV and increased risk for cardiovascular disease. Elucidation of the role this novel locus plays in aortic stiffness may facilitate development of therapeutic interventions that limit aortic stiffening and related cardiovascular disease events.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 81-90

Published online before print November 8, 2011,

doi: 10.1161/ CIRCGENETICS.111.959817

Genetic Variation in PEAR1 is Associated with Platelet Aggregation and Cardiovascular Outcomes

Joshua P. Lewis1, Kathleen Ryan1, Jeffrey R. O’Connell1, Richard B. Horenstein1, Coleen M. Damcott1, Quince Gibson1, Toni I. Pollin1, Braxton D. Mitchell1, Amber L. Beitelshees1, Ruth Pakzy1, Keith Tanner1, Afshin Parsa1, Udaya S. Tantry2, Kevin P. Bliden2, Wendy S. Post3, Nauder Faraday3, William Herzog4, Yan Gong5, Carl J. Pepine6, Julie A. Johnson5, Paul A. Gurbel2 and Alan R. Shuldiner7*

Author Affiliations

1University of Maryland School of Medicine, Baltimore, MD

2Sinai Hospital of Baltimore, Baltimore, MD

3Johns Hopkins University School of Medicine, Baltimore, MD

4Sinai Hospital of Baltimore & Johns Hopkins University School of Medicine, Baltimore, MD

5University of Florida College of Pharmacy, Gainesville, FL

6University of Florida College of Medicine, Gainesville, FL

7University of Maryland School of Medicine & Veterans Administration Medical Center, Baltimore, MD

↵* University of Maryland School of Medicine & Veterans Administration Medical Center, Baltimore, MD ashuldin@medicine.umaryland.edu

Abstract

Background-Aspirin or dual antiplatelet therapy (DAPT) with aspirin and clopidogrel is standard therapy for patients at increased risk for cardiovascular events. However, the genetic determinants of variable response to aspirin (alone and in combination with clopidogrel) are not known.

Methods and Results-We measured ex-vivo platelet aggregation before and after DAPT in individuals (n=565) from the Pharmacogenomics of Antiplatelet Intervention (PAPI) Study and conducted a genome-wide association study (GWAS) of drug response. Significant findings were extended by examining genotype and cardiovascular outcomes in two independent aspirin-treated cohorts: 227 percutaneous coronary intervention (PCI) patients, and 1,000 patients of the International VErapamil SR/trandolapril Study (INVEST) GENEtic Substudy (INVEST-GENES). GWAS revealed a strong association between single nucleotide polymorphisms on chromosome 1q23 and post-DAPT platelet aggregation. Further genotyping revealed rs12041331 in the platelet endothelial aggregation receptor-1 (PEAR1) gene to be most strongly associated with DAPT response (P=7.66×10⁻⁹). In Caucasian and African American patients undergoing PCI, A-allele carriers of rs12041331 were more likely to experience a cardiovascular event or death compared to GG homozygotes (hazard ratio = 2.62, 95%CI 0.96-7.10, P=0.059 and hazard ratio = 3.97, 95%CI 1.10-14.31, P=0.035 respectively). In aspirin-treated INVEST-GENES patients, rs12041331 A-allele carriers had significantly increased risk of myocardial infarction compared to GG homozygotes (OR=2.03, 95%CI 1.01-4.09, P=0.048).

Conclusions-Common genetic variation in PEAR1 may be a determinant of platelet response and cardiovascular events in patients on aspirin, alone and in combination with clopidogrel.

Clinical Trial Registration Information-clinicaltrials.gov; Identifiers: NCT00799396 and NCT00370045

SOURCE:

CIRCGENETICS.112.964627

Published online before print February 7, 2013,

doi: 10.1161/ CIRCGENETICS.111.964627

Association of Genome-Wide Variation With Highly Sensitive Cardiac Troponin-T Levels in European Americans and Blacks

A Meta-Analysis From Atherosclerosis Risk in Communities and Cardiovascular Health Studies

Bing Yu, MD, MSc, Maja Barbalic, PhD, Ariel Brautbar, MD, Vijay Nambi, MD, Ron C. Hoogeveen, PhD, Weihong Tang, PhD, Thomas H. Mosley, PhD, Jerome I. Rotter, MD, Christopher R. deFilippi, MD, Christopher J. O’Donnell, MD, Sekar Kathiresan, MD, Ken Rice, PhD, Susan R. Heckbert, MD, PhD, Christie M. Ballantyne, MD, Bruce M. Psaty, MD, PhD and Eric Boerwinkle, PhD on behalf of the CARDIoGRAM Consortium

Author Affiliations

From the Human Genetic Center, University of Texas Health Science Center at Houston, Houston, TX (B.Y., M.B., E.B.); Deptartment of Medicine (A.B., V.N., R.C.H., C.M.B.), and Human Genome Sequencing Center (E.B.), Baylor College of Medicine, Houston, TX; Department of Epidemiology, University of Minnesota, Minneapolis, MN (W.T.); Division of Geriatrics, University of Mississippi Medical Center, Jackson, MS (T.H.M.); Medical Genetics Institute, Cedars-Sinai Medical Center, Los Angeles, CA (J.I.R.); School of Medicine, University of Maryland, Baltimore, MD (C.R.D.); National Heart, Lung, and Blood Institute and Framingham Heart Study, National Institutes of Health, Bethesda, MD (C.J.O.D.); Center for Human Genetic Research & Cardiovascular Research Center, Massachusetts General Hospital and Department of Medicine, Harvard Medical School, Boston, MA (S.K.); Department of Biostatistics (K.R.), and Cardiovascular Health Research Unit & Department of Epidemiology (S.R.H.), University of Washington, Seattle, WA; and Cardiovascular Health Research Unit, Departments of Medicine, Epidemiology, and Health Services, University of Washington & Group Health Research Institute, Group Health Cooperative, Seattle, WA (B.M.P.).

Correspondence to Eric Boerwinkle, PhD, Human Genetic Center, University of Texas School of Public Health, 1200 Herman Pressler E-447, Houston, TX 77030. E-mail Eric.Boerwinkle@uth.tmc.edu

Abstract

Background—High levels of cardiac troponin T, measured by a highly sensitive assay (hs-cTnT), are strongly associated with incident coronary heart disease and heart failure. To date, no large-scale genome-wide association study of hs-cTnT has been reported. We sought to identify novel genetic variants that are associated with hs-cTnT levels.

Methods and Results—We performed a genome-wide association in 9491 European Americans and 2053 blacks free of coronary heart disease and heart failure from 2 prospective cohorts: the Atherosclerosis Risk in Communities Study and the Cardiovascular Health Study. Genome-wide association studies were conducted in each study and race stratum. Fixed-effect meta-analyses combined the results of linear regression from 2 cohorts within each race stratum and then across race strata to produce overall estimates and probability values. The meta-analysis identified a significant association at chromosome 8q13 (rs10091374; P=9.06×10⁻⁹) near the nuclear receptor coactivator 2 (NCOA2) gene. Overexpression of NCOA2 can be detected in myoblasts. An additional analysis using logistic regression and the clinically motivated 99th percentile cut point detected a significant association at 1q32 (rs12564445; P=4.73×10⁻⁸) in the gene TNNT2, which encodes the cardiac troponin T protein itself. The hs-cTnT-associated single-nucleotide polymorphisms were not associated with coronary heart disease in a large case-control study, but rs12564445 was significantly associated with incident heart failure in Atherosclerosis Risk in Communities Study European Americans (hazard ratio=1.16; P=0.004).

Conclusions—We identified 2 loci, near NCOA2 and in the TNNT2 gene, at which variation was significantly associated with hs-cTnT levels. Further use of the new assay should enable replication of these results.

 SOURCE:

Circulation: Cardiovascular Genetics.2013; 6: 82-88

Published online before print December 16, 2012,

doi: 10.1161/ CIRCGENETICS.112.963058


Genomics and Valvular Disease


Supravalvular Aortic Stenosis Elastin Arteriopathy


Giuseppe Merla, PhD, Nicola Brunetti-Pierri, MD, Pasquale Piccolo, PhD, Lucia Micale, PhD and Maria Nicla Loviglio, PhD, MSc

Author Affiliations

From the Medical Genetics Unit, IRCCS Casa Sollievo Della Sofferenza Hospital, San Giovanni Rotondo, Italy (G.M., L.M., M.N.L.); Telethon Institute of Genetics and Medicine, Napoli, Italy (N.B-P., P.P.); Department of Pediatrics, Federico II University of Naples, Naples, Italy (N.B-P.); and CIG Center for Integrative Genomics, University of Lausanne, Lausanne, Switzerland (M.N.L.).

Correspondence to Giuseppe Merla, PhD, Medical Genetics Unit, IRCCS Casa Sollievo della Sofferenza, viale Cappuccini, 71013 San Giovanni Rotondo, Italy. E-mail g.merla@operapadrepio.it

Abstract

Supravalvular aortic stenosis is a systemic elastin (ELN) arteriopathy that disproportionately affects the supravalvular aorta. ELN arteriopathy may be present in a nonsyndromic condition or in syndromic conditions such as Williams–Beuren syndrome. The anatomic findings include congenital narrowing of the lumen of the aorta and other arteries, such as branches of pulmonary or coronary arteries. Given the systemic nature of the disease, accurate evaluation is recommended to establish the degree and extent of vascular involvement and to plan appropriate interventions, which are indicated whenever hemodynamically significant stenoses occur. ELN arteriopathy is genetically heterogeneous and occurs as a consequence of haploinsufficiency of the ELN gene on chromosome 7q11.23, owing to either microdeletion of the entire chromosomal region or ELN point mutations. Interestingly, there is a prevalence of premature termination mutations resulting in null alleles among ELN point mutations. The identification of the genetic defect in patients with supravalvular aortic stenosis is essential for a definitive diagnosis, prognosis, and genetic counseling.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 692-696

doi: 10.1161/ CIRCGENETICS.112.962860

Genetic Loci for Coronary Calcification and Serum Lipids Relate to Aortic and Carotid Calcification

Daniel Bos, MD, M. Arfan Ikram, MD, PhD, Aaron Isaacs, PhD, Benjamin F.J. Verhaaren, MD, Albert Hofman, MD, PhD, Cornelia M. van Duijn, PhD, Jacqueline C.M. Witteman, PhD, Aad van der Lugt, MD, PhD and Meike W. Vernooij, MD, PhD

Author Affiliations

From the Departments of Radiology (D.B., M.A.I., B.F.J.V., A.v.d.L., M.W.V), Epidemiology (D.B., M.A.I., A.I., B.F.J.V., A.H., C.M.v.D., J.C.M.W., M.W.V.), and Genetic Epidemiology Unit (A.I., C.M.v.D.), Erasmus MC, Rotterdam, the Netherlands.

Correspondence to Meike W. Vernooij, MD, PhD, Department of Radiology, Erasmus MC, Gravendijkwal 230, PO Box 2040, 3000CA Rotterdam, the Netherlands. E-mail m.vernooij@erasmusmc.nl

Abstract

Background—Atherosclerosis in different vessel beds shares lifestyle and environmental risk factors. It is unclear whether this holds for genetic risk factors. Hence, for the current study genetic loci for coronary artery calcification and serum lipid levels, one of the strongest risk factors for atherosclerosis, were used to assess their relation with atherosclerosis in different vessel beds.

Methods and Results—From 1987 persons of the population-based Rotterdam Study, 3 single-nucleotide polymorphisms (SNPs) for coronary artery calcification and 132 SNPs for total cholesterol, low-density lipoprotein cholesterol, high-density lipoprotein cholesterol or triglycerides were used. To quantify atherosclerotic calcification as a marker of atherosclerosis, all participants underwent nonenhanced computed tomography of the aortic arch and carotid arteries. Associations between genetic risk scores of the joint effect of the SNPs and of all calcification were investigated. The joint effect of coronary artery calcification–SNPs was associated with larger calcification volumes in all vessel beds (difference in calcification volume per SD increase in genetic risk score: 0.15 [95% confidence interval, 0.11–0.20] in aorta, 0.14 [95% confidence interval, 0.10–0.18] in extracranial carotids, and 0.11 [95% confidence interval, 0.07–0.16] in intracranial carotids). The joint effect of total cholesterol SNPs, low-density lipoprotein SNPs, and of all lipid SNPs together was associated with larger calcification volumes in both the aortic arch and the carotid arteries but attenuated after adjusting for the lipid fraction and lipid-lowering medication.

Conclusions—The genetic basis for aortic arch and carotid artery calcification overlaps with the most important loci of coronary artery calcification. Furthermore, serum lipids share a genetic predisposition with both calcification in the aortic arch and the carotid arteries, providing novel insights into the cause of atherosclerosis.

 SOURCE:

Circulation: Cardiovascular Genetics.2013; 6: 47-53

Published online before print December 16, 2012,

doi: 10.1161/ CIRCGENETICS.112.963934


Joint Associations of 61 Genetic Variants in the Nicotinic Acetylcholine Receptor Genes with Subclinical Atherosclerosis in American Indians

A Gene-Family Analysis

Jingyun Yang, PhD*, Yun Zhu, MS*, Elisa T. Lee, PhD, Ying Zhang, PhD, Shelley A. Cole, PhD, Karin Haack, PhD, Lyle G. Best, BS MD, Richard B. Devereux, MD, Mary J. Roman, MD, Barbara V. Howard, PhD and Jinying Zhao, MD, PhD

Author Affiliations

From the Tulane University School of Public Health and Tropical Medicine, New Orleans, LA (J.Y., Y. Zhu, J.Z.); Center for American Indian Health Research, University of Oklahoma Health Sciences Center, Oklahoma City, OK (E.T.L., Y. Zhang); Texas Biomedical Research Institute, San Antonio, TX (S.A.C., K.H.); Missouri Breaks Industries Research Inc, Timber Lake, SD (L.G.B.); The New York Hospital-Cornell Medical Center, New York, NY (R.B.D., M.J.R.); MedStar Health Research Institute, Hyattsville, MD (B.V.H.); and Georgetown and Howard Universities Centers for Translational Sciences, Washington, DC (B.V.H.).

Correspondence to Jinying Zhao, MD, PhD, Department of Epidemiology, School of Public Health and Tropical Medicine, Tulane University, 1440 Canal St, SL18, New Orleans, LA 70112. E-mail jzhao5@tulane.edu

↵* These authors contributed equally to this work.

Abstract

Background—Atherosclerosis is the underlying cause of cardiovascular disease, the leading cause of morbidity and mortality in all American populations, including American Indians. Genetic factors play an important role in the pathogenesis of atherosclerosis. Although a single-nucleotide polymorphism (SNP) may explain only a small portion of variability in disease, the joint effect of multiple variants in a pathway on disease susceptibility could be large.

Methods and Results—Using a gene-family analysis, we investigated the joint associations of 61 tag SNPs in 7 nicotinic acetylcholine receptor genes with subclinical atherosclerosis, as measured by carotid intima-media thickness and plaque score, in 3665 American Indians from 94 families recruited by the Strong Heart Family Study (SHFS). Although multiple SNPs showed marginal association with intima-media thickness and plaque score individually, only a few survived adjustments for multiple testing. However, simultaneously modeling of the joint effect of all 61 SNPs in 7 nicotinic acetylcholine receptor genes revealed significant association of the nicotinic acetylcholine receptor gene family with both intima-media thickness and plaque score independent of known coronary risk factors.

Conclusions—Genetic variants in the nicotinic acetylcholine receptor gene family jointly contribute to subclinical atherosclerosis in American Indians who participated in the SHFS. These variants may influence the susceptibility of atherosclerosis through pathways other than cigarette smoking per se.

SOURCE:

Circulation: Cardiovascular Genetics.2013; 6: 89-96

Published online before print December 22, 2012,

doi: 10.1161/ CIRCGENETICS.112.963967


Heredity of Cardiovascular Disorders Inheritance


A Clinical Approach to Common Cardiovascular Disorders When There Is a Family History

The Implications of Inheritance for Clinical Management

Srijita Sen-Chowdhry, MBBS, MD, FESC, Daniel Jacoby, MD and William J. McKenna, MD, DSc, FESC

Author Affiliations

From the Institute of Cardiovascular Science, University College London, London, United Kingdom (S.S-C., W.J.M.); Department of Epidemiology, Imperial College, London, London, United Kingdom (S.S-C.); Division of Cardiology, Yale School of Medicine, New Haven, CT (D.J., W.J.M.).

Correspondence to Professor William J. McKenna, MD, DSc, FESC, Institute of Cardiovascular Science, University College London, The Heart Hospital, 16-18 Westmoreland Street, London, E-mail william.mckenna@uclh.nhs.uk

Introduction

Since the advent of genotyping, recognition of heritable disease has been perceived as an opportunity for genetic diagnosis or new gene identification studies to advance understanding of pathogenesis. Until recently, however, clinical application of DNA-based testing was confined largely to Mendelian disorders. Even within this remit, predictive testing of relatives is cost-effective only in diseases in which the majority of families harbor mutations in known causal genes, such as adult polycystic kidney disease and hypertrophic cardiomyopathy, but not dilated cardiomyopathy. Confirmatory genetic testing of index cases with borderline clinical features may be economic in the still smaller subset of diseases with limited locus heterogeneity, such as Marfan syndrome. Furthermore, Mendelian diseases account for ≈5% of total disease burden.1 Genome-wide association studies have made headway in elucidating the genetic contribution to the more common, complex diseases, and high throughput techniques promise to facilitate integration of genetic analysis into clinical practice. Nevertheless, many genes remain to be identified and implementation of genomic profiling as a population screening tool would not be cost-effective at present. The implications of heredity, however, extend beyond serving as a platform for genetic analysis, influencing diagnosis, prognostication, and treatment of both index cases and relatives, and enabling rational targeting of genotyping resources. This review covers acquisition of a family history, evaluation of heritability and inheritance patterns, and the impact of inheritance on subsequent components of the clinical pathway.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 467-476

doi: 10.1161/ CIRCGENETICS.110.959361

Clinical Considerations of Heritable Factors in Common Heart Failure

Thomas P. Cappola, MD, ScM and Gerald W. Dorn II, MD

Author Affiliations

From the Department of Medicine, University of Pennsylvania, Philadelphia, PA (T.P.C.), and Center for Pharmacogenomics, Washington University School of Medicine, St Louis, MO (G.W.D.II.).

Correspondence to Gerald W. Dorn II, MD, Center for Pharmacogenomics, Washington University, 660 S Euclid Ave, Campus Box 8220, St Louis, MO 63110. E-mail gdorn@dom.wustl.edu


Introduction

Heart failure is a common condition responsible for at least 290 000 deaths each year in the United States alone.1 A small minority of heart failure cases are attributed to Mendelian or familial cardiomyopathies. The majority of systolic heart failure cases are not familial but represent the end result of 1 or many conditions that primarily injure the myocardium sufficiently to diminish cardiac output in the absence of compensatory mechanisms. Paradoxically, because they also injure the myocardium, it is the chronic actions of the compensatory mechanisms that in many instances contribute to the progression from simple cardiac injury to dilated cardiomyopathy and overt heart failure. Thus, the epidemiology of common heart failure appears to be just as sporadic as its major antecedent conditions (atherosclerosis, diabetes, hypertension, and viral myocarditis).

Familial trends in preclinical cardiac remodeling2 and risk of developing heart failure3 reveal an important role for genetic modifiers in addition to clinical and environmental factors. Candidate gene studies performed over the past 10 years have identified a few polymorphic gene variants that modify risk or progression of common heart failure.4 Whole-genome sequencing will lead to the discovery of other genetic modifiers that were not candidates.5 The imminent availability of individual whole-genome sequences at a cost competitive with available genetic tests for familial cardiomyopathy will no doubt further expand the list of putative genetic heart failure modifiers. Heart failure risk alleles along with traditional clinical factors will need to be considered by clinical cardiologists in their design of optimal disease surveillance and prevention programs and in individually tailoring heart failure management.

The use of individual genetic make-up is likely to have the earliest and greatest impact on managing patients with heart failure by tailoring available pharmacotherapeutics to optimize patient response and minimize adverse effects (ie, the area of pharmacogenetics). Modern heart failure management has been derived and directed by the results of large, randomized, multicenter clinical trials. When standard therapies are applied according to the selection criteria used in these trials, they prolong average survival across affected populations or decrease the incidence of heart failure in populations at risk.6 For this reason, standardized treatment guidelines prescribe heart failure therapies according to trial designs, aiming for the same target doses and general treatment approaches,7 and largely ignore individual characteristics. In this article, we review established and emerging knowledge of genetic influence on common heart failure and try to anticipate how these genetic factors may be best used to eschew the cookie-cutter approach to heart failure management and move toward implementing a personalized medicine approach for the treatment and prevention of this important and prevalent disease.

The Concept of Genotype-Directed Personal Medical Management in Heart Failure

Variation in clinical heart failure progression and therapeutic response (either benefits or side effects) supports the need for a more individualized approach to disease management. On the basis of clinical stratification (eg, by etiology of heart failure as ischemic versus nonischemic, functional status, comorbid disease), physicians try to match each patient’s specific heart failure syndrome with a therapeutic regime devised to provide the most benefit. Standard heart failure pharmacotherapy currently comprises a minimum of 3 medications (angiotensin-converting enzyme [ACE] inhibitors, β-blockers, and aldosterone antagonists), with consideration of additional medications (hydralazine/isosorbide, angiotensin receptor blockers) and diuretics. The recommended target dosages for these agents, derived from their respective clinical trials, is rarely achieved,8 partly because of untoward clinical side effects such as low blood pressure or renal dysfunction. Accordingly, the published guidelines most often are applied in each individual patient using ad hoc approaches derived from personal experience and the “art of medicine.”

Technological advances in human genomics promise a different approach and are bringing cardiology into an era of clinically applied pharmacogenetics9 (whether we want to or not). As sequencing costs decline, it is not hard to envision that patients will present having had their entire genome already sequenced. The imperative to apply genome information in clinical settings will increase, as demonstrated by recent proof-of-concept studies.10 Our field seems poorly prepared for this type of evolution in care; Roden et al9 identified 3 major barriers: First is the absence of rapidly available genotype information in the clinical workflow. This barrier is being overcome with whole-genome sequencing, which (with proper analysis) promises a permanent and largely immutable genetic roadmap for individual disease risk and drug response at a cost comparable to many other clinical tests.11 Second, we must have the knowledge to properly apply information on genetic variants for the diseases we are managing and the drugs we are using. As we describe, this knowledge is accumulating for heart failure and for other cardiac conditions, and the rate at which we are gaining additional information and developing further expertise appears to be accelerating.

The third and perhaps most formidable barrier is the lack of clinical evidence showing how real-time application of genetic information can best benefit patients. As has been broadly communicated to the medical community and lay public, common functional gene variants in CYP2C19 can impair the transformation of clopidogrel into its active metabolite, leading to increased risk of stent thrombosis after percutaneous coronary intervention.12 The relevant question thus becomes the following: If physicians have this information at the time of clinical care and reacted by adjusting clopidogrel dose or substituting prasugrel, which is unaffected by CYP2C19 genotype,13 would there be any improvement in clinical outcome? It is also important to consider whether any observed benefits justify the additional costs of genetic testing and for the alternate drug. Studies are currently examining these questions, and similar clinical trials will prospectively examine whether a genotype-guided strategy of warfarin dosing will be superior to the standard genotype-blinded approach in reaching target anticoagulation goals. At this time, there are no similar prospective, randomized, blinded trials of genotype-guided care for common heart failure.

Emerging Variants

The variants described here are established, but new ones are emerging. Although findings in heart failure genome-wide association studies have been limited, we can expect additional common heart failure variants to emerge as sample sizes increase.65 The CHARGE (Cohorts for Heart and Aging Research in Genomic Epidemiology) consortium published a genome-wide association study of incident heart failure that tested for associations between >2.4 million HapMap-imputed polymorphisms in >20 000 subjects.7 They identified 2 loci associated with heart failure, rs10519210 (15q22, containing USP3 encoding a ubiquitin-specific protease) in subjects of European ancestry and rs11172782 (12q14, containing LRIG3 encoding a leucine-rich, immunoglobulin-like domain-containing protein of uncertain function) in subjects of African ancestry.66 In a companion study using the same population and genotyping results, mortality analysis of the subgroup of individuals who developed heart failure implicated an intronic SNP in CMTM7 (CKLF-like MARVEL transmembrane domain-containing 7).67 These genetic associations require independent replication and further study to identify the underlying biological mechanisms.

A recently published genome-wide association study by a European consortium on dilated cardiomyopathy identified common variants in BAG3 (BCL2-associated athanogene 3) associated with heart failure57 and identified rare BAG3 missense and truncation mutations that segregate with familial cardiomyopathy. These findings were consistent with an earlier exome-sequencing study that identified BAG3 as a familial dilated cardiomyopathy gene and showed recapitulation of cardiomyopathy with BAG3 morpholino knockdown in zebra fish.68 Together, these studies convincingly support variation in BAG3 as a genetic risk factor of cardiomyopathy and heart failure. It is noteworthy that both common and rare functional variations were identified at this locus. A unifying hypothesis for these findings, which needs to be formally tested, is that common variants in BAG3 serve as proxies for rare functional BAG3 mutations with large effects. In this situation, the underlying genetic lesion is a rare variant with a large functional effect. This has recently been described for common variants in MYH6 that correlated with rare functional MYH6 variants to cause sick sinus syndrome.69 It is premature to speculate on the clinical applications of these newer findings.

Moving Knowledge to Practice

A small number of genomic variants have been identified that modify heart failure by affecting well-understood physiological systems. The principal barrier preventing their adoption in practice may be lack of evidence showing how application of this information can best be used for clinical benefit. Trials testing genotype targeting of antiplatelet therapy and anticoagulation will be completed in the coming years. The findings from these studies will likely determine the level of enthusiasm for conducting genotype-guided trials of β-blockers and RAAS antagonists in heart failure. Given that the lifetime risk of heart failure in the United States is estimated at 1 in 5, even a small favorable effect on heart failure prevention or outcome through use of genome-guided therapy has the potential for a large public health impact. We therefore believe that a near-term goal should be to conduct pharmacogenomic trials in heart failure based on our current understanding of heart failure variants.

Looking ahead, unbiased approaches will continue to reveal a large number heart failure-modifying variants (both common and rare). Based on experience in other complex phenotypes, such has height70 and plasma lipid levels,71 the underlying genetic mechanisms for many new heart failure variants will be completely unknown, and their sheer number will preclude detailed experimentation using murine models to figure them out. Leveraging these variants for clinical application is a challenge that we will be forced to confront.

As our ability to identify rare, disease-causing variants improves through personal genome sequencing, we will be faced with the additional problem of how best to estimate the disease risk conferred by a sequence variant for which there has been no biological validation. In probabilistic terms, because there are 3 billion nucleotides in the human genome and over twice that many humans on the planet, it is likely that a nucleotide substitution for every position is represented in someone. Obviously, it will be impossible to recombinantly express and functionally characterize every DNA variant that is going to be implicated in heart failure. Bioinformatics filters have been used to try and separate functionally significant from insignificant variants based on the likelihood of changing transcript expression or protein function. These tools are limited but will improve if we tailor their results to the known characteristics of each gene product. For example, current approaches to categorize amino acid substitutions as conservative or nonconservative based only on charge or side chains can be improved by molecular modeling that incorporates protein-specific structure-function information. This approach has been used to estimate the pathogenicity of myosin heavy chain (MHC) mutations in an effort to determine which mutations are likely to cause familial cardiomyopathy when linkage analysis is not feasible.72 In concept, this approach can be applied to any protein for which structure-function activities have been finely mapped to distinct domains.

A promising extension of this approach may be to use evolutionary genetics to infer disease causality. Again, using the MHC genes as examples, human genome data show a greater prevalence of nonsynonymous gene variants in MYH6, which encodes the minor cardiac α-MHC isoform, compared with the adjacent MYH7, which encodes the major β-MHC isoform. This disparity suggests a greater tolerance for protein changes in the α-MHC isoform and negative selection against these in β-MHC. We can infer, therefore, that amino acid changes are more likely to have adverse impacts in MYH7-encoded β-MHC. If this paradigm survives prospective testing, then the forthcoming explosion of individual genetic data not only will present a massive problem in interpretation, but also will provide the genetic information by which analyses of rare sequence variants across large unaffected populations can help to differentiate the tolerable variants from those that are more likely to alter disease risk.

Each Reference above is found in:

http://circgenetics.ahajournals.org/content/4/6/701.full

SOURCE: 

Circulation: Cardiovascular Genetics.2011; 4: 701-709

doi: 10.1161/ CIRCGENETICS.110.959379


Pharmacogenomics


Hypertension Susceptibility Loci and Blood Pressure Response to Antihypertensives

Results From the Pharmacogenomic Evaluation of Antihypertensive Responses Study

Yan Gong, PhD, Caitrin W. McDonough, PhD, Zhiying Wang, MS, Wei Hou, PhD, Rhonda M. Cooper-DeHoff, PharmD, MS, Taimour Y. Langaee, PhD, Amber L. Beitelshees, PharmD, MPH, Arlene B. Chapman, MD, John G. Gums, PharmD, Kent R. Bailey, PhD, Eric Boerwinkle, PhD, Stephen T. Turner, MD and Julie A. Johnson, PharmD

Author Affiliations

From the Department of Pharmacotherapy and Translational Research (Y.G., C.W.M., R.M.C.-D., T.Y.L., J.G.G., J.A.J.), Department of Biostatistics, College of Medicine (W.H.), Division of Cardiovascular Medicine, College of Medicine (R.M.C.-D., J.A.J.), and Department of Community Health and Family Medicine (J.G.G.), University of Florida, Gainesville, FL; Division of Epidemiology, University of Texas at Houston, Houston, TX (Z.W., E.B.); Division of Endocrinology, Diabetes and Nutrition, University of Maryland, Baltimore, MD (A.L.B.); Renal Division, Emory University, Atlanta, GA (A.B.C.); and Division of Nephrology and Hypertension, Mayo Clinic, Rochester, MN (S.T.T.).

Correspondence to Yan Gong, PhD, Department of Pharmacotherapy and Translational Research, University of Florida, PO Box 100486, 1600 SW Archer Rd, Gainesville, FL 32610. E-mail gong@cop.ufl.edu.

Abstract

Background—To date, 39 single nucleotide polymorphisms (SNPs) have been associated with blood pressure (BP) or hypertension in genome-wide association studies in whites. Our hypothesis is that the loci/SNPs associated with BP/hypertension are also associated with BP response to antihypertensive drugs.

Methods and Results—We assessed the association of these loci with BP response to atenolol or hydrochlorothiazide monotherapy in 768 hypertensive participants in the Pharmacogenomics Responses of Antihypertensive Responses study. Linear regression analysis was performed on whites for each SNP in an additive model adjusting for baseline BP, age, sex, and principal components for ancestry. Genetic scores were constructed to include SNPs with nominal associations, and empirical P values were determined by permutation test. Genotypes of 37 loci were obtained from Illumina 50K cardiovascular or Omni1M genome-wide association study chips. In whites, no SNPs reached Bonferroni-corrected α of 0.0014, 6 reached nominal significance (P<0.05), and 3 were associated with atenolol BP response at P<0.01. The genetic score of the atenolol BP-lowering alleles was associated with response to atenolol (P=3.3×10⁻⁶ for systolic BP; P=1.6×10⁻⁶ for diastolic BP). The genetic score of the hydrochlorothiazide BP-lowering alleles was associated with response to hydrochlorothiazide (P=0.0006 for systolic BP; P=0.0003 for diastolic BP). Both risk score P values were <0.01 based on the empirical distribution from the permutation test.

Conclusions—These findings suggest that selected signals from hypertension genome-wide association studies may predict BP response to atenolol and hydrochlorothiazide when assessed through risk scoring.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 686-691

Published online before print October 19, 2012,

doi: 10.1161/ CIRCGENETICS.112.964080


Genetic Determinants of Statin-Induced Low-Density Lipoprotein Cholesterol Reduction

The Justification for the Use of Statins in Prevention: An Intervention Trial Evaluating Rosuvastatin (JUPITER) Trial

Daniel I. Chasman, PhD, Franco Giulianini, PhD, Jean MacFadyen, BA, Bryan J. Barratt, PhD, Fredrik Nyberg, MD, PhD, MPH and Paul M Ridker, MD, MPH

Author Affiliations

From the Center for Cardiovascular Disease Prevention (D.I.C., F.G., J.M., P.M.R.), JUPITER Trial Coordinating Center (D.I.C., F.G., J.M., P.M.R.), Brigham and Women’s Hospital and Harvard Medical School (D.I.C., P.M.R.), Boston, MA; Personalised Healthcare and Biomarkers, AstraZeneca Research and Development, Alderley Park, United Kingdom (B.J.B.); AstraZeneca Research and Development, Mölndal, Sweden (F.N.); and Unit of Occupational and Environmental Medicine, Department of Public Health and Community Medicine, Sahlgrenska Academy, University of Gothenburg, Gothenburg, Sweden (F.N.).

Correspondence to Daniel I. Chasman, PhD, Center for Cardiovascular Disease Prevention, Brigham and Women’s Hospital, 900 Commonwealth Ave E, Boston, MA 02215. E-mail dchasman@rics.bwh.harvard.edu

Abstract

Background—In statin trials, each 20 mg/dL reduction in cholesterol results in a 10–15% reduction of annual incidence rates for vascular events. However, interindividual variation in low-density lipoprotein cholesterol (LDL-C) response to statins is wide and may partially be determined on a genetic basis.

Methods and Results—A genome-wide association study of LDL-C response was performed among a total of 6989 men and women of European ancestry who were randomly allocated to either rosuvastatin 20 mg daily or placebo. Single nucleotide polymorphisms (SNPs) for genome-wide association (P<5×10⁻⁸) with LDL-C reduction on rosuvastatin were identified at ABCG2, LPA, and APOE, and a further association at PCSK9 was genome-wide significant for baseline LDL-C and locus-wide significant for LDL-C reduction. Median LDL-C reductions on rosuvastatin were 40, 48, 51, 55, 60, and 64 mg/dL, respectively, among those inheriting increasing numbers of LDL-lowering alleles for SNPs at these 4 loci (P trend=6.2×10⁻²⁰), such that each allele approximately doubled the odds of percent LDL-C reduction greater than the trial median (odds ratio, 1.9; 95% confidence interval, 1.8–2.1; P=5.0×10−41). An intriguing additional association with sub–genome-wide significance (P<1×10⁻⁶) was identified for statin related LDL-C reduction at IDOL, which mediates posttranscriptional regulation of the LDL receptor in response to intracellular cholesterol levels. In candidate analysis, SNPs in SLCO1B1 and LDLR were confirmed as associated with LDL-C lowering, and a significant interaction was observed between SNPs in PCSK9 and LDLR.

Conclusions—Inherited polymorphisms that predominantly relate to statin pharmacokinetics and endocytosis of LDL particles by the LDL receptor are common in the general population and influence individual patient response to statin therapy.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 257-264

Published online before print February 13, 2012,

doi: 10.1161/ CIRCGENETICS.111.961144

Genetic Variation in the β2 Subunit of the Voltage-Gated Calcium Channel and Pharmacogenetic Association With Adverse Cardiovascular Outcomes in the INternational VErapamil SR-Trandolapril STudy GENEtic Substudy (INVEST-GENES)

Yuxin Niu, PhD*, Yan Gong, PhD*, Taimour Y. Langaee, PhD, Heather M. Davis, PharmD, Hazem Elewa, PhD, Amber L. Beitelshees, PharmD, MPH, James I. Moss, PhD, Rhonda M. Cooper-DeHoff, PharmD, Carl J. Pepine, MD and Julie A. Johnson, PharmD

Author Affiliations

From the Department of Pharmacotherapy and Translational Research and Center for Pharmacogenomics (Y.N., Y.G., T.Y.L., H.M.D., H.E., J.I.M., R.M.C.-D., J.A.J.), College of Pharmacy, University of Florida, Gainesville, Fla; Division of Endocrinology, Diabetes and Nutrition (A.L.B.), University of Maryland School of Medicine, Baltimore, Md; and Division of Cardiovascular Medicine (R.M.C.-D., C.J.P., J.A.J.), University of Florida College of Medicine, Gainesville, Fla.

Correspondence to Julie A. Johnson, PharmD, Department of Pharmacotherapy and Translational Research, College of Pharmacy, University of Florida, PO Box 100486, Gainesville, FL 32610. E-mail Johnson@cop.ufl.edu

↵* Drs Niu and Gong contributed equally to this work.

Abstract

Background— Single-nucleotide polymorphisms (SNPs) within the regulatory β2 subunit of the voltage-gated calcium channel (CACNB2) may contribute to variable treatment response to antihypertensive drugs and adverse cardiovascular outcomes.

Methods and Results— SNPs in CACNB2 from 60 ethnically diverse individuals were identified and characterized. Three common SNPs (rs2357928, rs7069292, and rs61839258) and a genome-wide association study-identified intronic SNP (rs11014166) were genotyped for a clinical association study in 5598 hypertensive patients with coronary artery disease randomized to a β-blocker (BB) or a calcium channel blocker (CCB) treatment strategy in the INternational VErapamil SR-Trandolapril STudy GENEtic Substudy (INVEST-GENES). Reporter gene assays were conducted on the promoter SNP, showing association with clinical outcomes. Twenty-one novel SNPs were identified. A promoter A>G SNP (rs2357928) was found to have significant interaction with treatment strategy for adverse cardiovascular outcomes (P for interaction, 0.002). In whites, rs2357928 GG patients randomized to CCB were more likely to experience an adverse outcome than those randomized to BB treatment strategy, with adjusted hazard ratio (HR) (CCB versus BB) of 2.35 (95% CI, 1.19 to 4.66; P=0.014). There was no evidence for such treatment difference in AG (HR, 1.16; 95% CI, 0.75 to 1.79; P=0.69) and AA (HR, 0.63; 95% CI, 0.36 to 1.11; P=0.11) patients. This finding was consistent in Hispanics and blacks. CACNB2 rs11014166 showed similar pharmacogenetic effect in Hispanics, but not in whites or blacks. Reporter assay analysis of rs2357928 showed a significant increase in promoter activity for the G allele compared to the A allele.

Conclusions— These data suggest that genetic variation within CACNB2 may influence treatment-related outcomes in high-risk patients with hypertension.

Clinical Trial Registration— URL: http://www.clinicaltrials.gov. Unique identifier: NCT00133692.

SOURCE:

Circulation: Cardiovascular Genetics.2010; 3: 548-555

doi: 10.1161/ CIRCGENETICS.110.957654


Hepatic Metabolism and Transporter Gene Variants Enhance Response to Rosuvastatin in Patients With Acute Myocardial Infarction

The GEOSTAT-1 Study

Kristian M. Bailey, MBChB, Simon P.R. Romaine, BSc, Beryl M. Jackson, RGN, Amanda J. Farrin, MSc, Maria Efthymiou, MSc, Julian H. Barth, MD, Joanne Copeland, BSc, Terry McCormack, MBBS, Andrew Whitehead, MSc, Marcus D. Flather, MBBS, Nilesh J. Samani, MD, FMedSci, Jane Nixon, PhD, Alistair S. Hall, MD, PhD, Anthony J. Balmforth, PhD and on behalf of the SPACE ROCKET Trial Group

Author Affiliations

From the Division of Cardiovascular and Diabetes Research (K.M.B., S.P.R.R., B.M.J., A.J.B.), and Division of Cardiovascular and Neuronal Remodelling (A.S.H.), Multidisciplinary Cardiovascular Research Centre, Leeds Institute of Genetics, Health and Therapeutics, University of Leeds, Leeds, United Kingdom; Clinical Trials Research Unit (A.J.F., M.E., J.C., J.N.), University of Leeds, Leeds, United Kingdom; Clinical Biochemistry (J.H.B.), Leeds General Infirmary, Leeds, United Kingdom; Whitby Group Practice (T.M.), Spring Vale Medical Centre, Whitby, North Yorkshire, United Kingdom; Pharmacy Department (A.W.), Leeds General Infirmary, Leeds, United Kingdom; Clinical Trials and Evaluation Unit (M.D.F.), Royal Brompton and Harefield NHS Trust and Imperial College, London, United Kingdom; and Department of Cardiovascular Sciences (N.J.S.), University of Leicester, Leicester, United Kingdom.

Correspondence to Alistair S. Hall, Clinical Cardiology, Multidisciplinary Cardiovascular Research Centre (MCRC), G Floor, Jubilee Building, Leeds General Infirmary, Leeds, LS1 3EX, United Kingdom. E-mail A.S.Hall@leeds.ac.uk

* Dr Bailey, Mr Romaine, Dr Hall, and Dr Balmforth contributed equally to this study.

Abstract

Background— Pharmacogenetics aims to maximize benefits and minimize risks of drug treatment. Our objectives were to examine the influence of common variants of hepatic metabolism and transporter genes on the lipid-lowering response to statin therapy.

Methods and Results— The Genetic Effects On STATins (GEOSTAT-1) Study was a genetic substudy of Secondary Prevention of Acute Coronary Events—Reduction of Cholesterol to Key European Targets (SPACE ROCKET) (a randomized, controlled trial comparing 40 mg of simvastatin and 10 mg of rosuvastatin) that recruited 601 patients after myocardial infarction. We genotyped the following functional single nucleotide polymorphisms in the genes coding for the cytochrome P450 (CYP) metabolic enzymes, CYP2C9*2 (430C>T), CYP2C9*3 (1075A>C), CYP2C19*2 (681G>A), CYP3A5*1 (6986A>G), and hepatic influx and efflux transporters SLCO1B1 (521T>C) and breast cancer resistance protein (BCRP; 421C>A). We assessed 3-month LDL cholesterol levels and the proportion of patients reaching the current LDL cholesterol target of <70 mg/dL (<1.81 mmol/L). An enhanced response to rosuvastatin was seen for patients with variant genotypes of either CYP3A5 (P=0.006) or BCRP (P=0.010). Furthermore, multivariate logistic-regression analysis revealed that patients with at least 1 variant CYP3A5 and/or BCRP allele (n=186) were more likely to achieve the LDL cholesterol target (odds ratio: 2.289; 95% CI: 1.157, 4.527; P=0.017; rosuvastatin 54.0% to target vs simvastatin 33.7%). There were no differences for patients with variants of CYP2C9, CYP2C19, or SLCO1B1 in comparison with their respective wild types, nor were differential effects on statin response seen for patients with the most common genotypes for CYP3A5 and BCRP (n=415; odds ratio: 1.207; 95% CI: 0.768, 1.899; P=0.415).

Conclusion— The LDL cholesterol target was achieved more frequently for the 1 in 3 patients with CYP3A5 and/or BCRP variant genotypes when prescribed rosuvastatin 10 mg, compared with simvastatin 40 mg.

Clinical Trial Registration— URL: http://isrctn.org. Unique identifier: ISRCTN 89508434.

SOURCE:

Circulation: Cardiovascular Genetics.2010; 3: 276-285

Published online before print March 5, 2010,

doi: 10.1161/ CIRCGENETICS.109.898502


Comprehensive Whole-Genome and Candidate Gene Analysis for Response to Statin Therapy in the Treating to New Targets (TNT) Cohort

John F. Thompson, PhD, Craig L. Hyde, PhD, Linda S. Wood, MS, Sara A. Paciga, MA, David A. Hinds, PhD, David R. Cox, MD, PhD, G. Kees Hovingh, MD, PhD and John J.P. Kastelein, MD, PhD

Author Affiliations

From the Helicos BioSciences (J.F.T.), Cambridge, Mass; Molecular Medicine (J.F.T., L.S.W., S.A.P.) and Statistical Applications (C.L.H.), Pfizer Global Research and Development, Groton, Conn; Perlegen Sciences (D.A.H., D.R.C.), Mountain View, Calif; and Department of Vascular Medicine (G.K.H., J.J.P.K.), Academic Medical Center, Amsterdam, The Netherlands.

Correspondence to John J.P. Kastelein, MD, PhD, Department of Vascular Medicine, Academic Medical Center, Meibergdreef 9, Room F4-159.2, 1105 AZ Amsterdam, The Netherlands. E-mail j.j.kastelein@amc.uva.nl or j.s.jansen@amc.uva.nl

Abstract

Background— Statins are effective at lowering low-density lipoprotein cholesterol and reducing risk of cardiovascular disease, but variability in response is not well understood. To address this, 5745 individuals from the Treating to New Targets (TNT) trial were genotyped in a combination of a whole-genome and candidate gene approach to identify associations with response to atorvastatin treatment.

Methods and Results— A total of 291 988 single-nucleotide polymorphisms (SNPs) from 1984 individuals were analyzed for association with statin response, followed by genotyping top hits in 3761 additional individuals. None was significant at the whole-genome level in either the initial or follow-up test sets for association with low-density lipoprotein cholesterol, high-density lipoprotein cholesterol, or triglyceride response. In addition to the whole-genome platform, 23 candidate genes previously associated with statin response were analyzed in these 5745 individuals. Three SNPs in apoE were most highly associated with low-density lipoprotein cholesterol response, followed by 1 in PCSK9 with a similar effect size. At the candidate gene level, SNPs in HMGCR were also significant though the effect was less than with those in apoE and PCSK9. rs7412/apoE had the most significant association (P=6×10⁻³⁰), and its high significance in the whole-genome study (P=4×10⁻⁹) confirmed the suitability of this population for detecting effects. Age and gender were found to influence low-density lipoprotein cholesterol response to a similar extent as the most pronounced genetic effects.

Conclusions— Among SNPs tested with an allele frequency of at least 5%, only SNPs in apoE are found to influence statin response significantly. Less frequent variants in PCSK9 and smaller effect sizes in SNPs in HMGCR were also revealed.

SOURCE:

Circulation: Cardiovascular Genetics.2009; 2: 173-181

Published online before print February 12, 2009,

doi: 10.1161/ CIRCGENETICS.108.818062

Summary

Larry H. Bernstein, MD, FCAP

This review has examined a compendium of well regarded documents drawn from 248 articles in Circulation Cardiovascular Genetics from March 2010 to March 2013. The large amount of evidence obtained from large population studies identifying Genome Wide Analysis Studies (GWAS) examines a host of cardiac and vascular diseases in which there is association between specific single nucleotide peptides (SNPs), and gene loci, that may play or have no significant role in developing heart disease. It certainly is evidence of the role that the American Heart Association has is in supporting the leading research today for tomorrow’s patients.   It is too early to sort them out, but it speaks to a large volume of discovery in this area.

It raises another issue that we have been confronted with mostly since the second half of the 20th century.  What is that issue?  The issue, it appears to me, is the vast improvements in analytical technology so that “imprecision” is far less likely to be a confounder in biological measurements and this lends access to far better accuracy?  But from that question arises another! Accuracy only refers to what is measured, but does it give us better ability to explain a complex and dynamic process?  In other words, what is what we are looking at representative of in manageable events?   I think that this is the most important idea that should come out of the recent criticism of the trajectory that molecular genetics been on in the last 5 years.

It was still in an era that “BIG’ science was not the normal.  One could spend an enormous effort at stepwise purification of a protein or enzyme, or other biomolecule starting with a slurry made from 100 lbs of “chicken heart”, for example.  These separations were based on negative charges on the molecules and positive charges on the column, and the molecules of no interest were eluted by gradient elution.  Much was learned about large scale preparation from small scale trials.  But this work was not undertaken without the intent to carry out a number of investigations to understand the “functionality” of a link in a metabolic pathway.  The studies that followed the purification required kinetic investigation with a coenzyme, or with a synthetically modified coenzyme, amino acid sequencing, NMR studies, etc.  You could not put together a “mechanism” without having the minimum amount of necessary information for a reliable account.  It is probably this requirement that led to today’s “BIG” science, that is founded upon multiple methods, now large data bases, and teams of investigators across institutions and continents.  The acquisition of knowledge has been astounding, but the integration of knowledge has not caught up.

However, let’s see if we can sort out the most meaningful signals from what I too am beginning to call the “noisy channel”.  As often happens, important areas of research are opened up that are followed by significant discovery and, in the long run, many other dead end publications that have no lasting significance.  In order to do justice to the work, I’ll pick through documents I find interesting, keeping in mind there is a hidden layer of complexity of which only sufficient information leads to a better understanding.  As much literature calls attention to, much of what ails us has nothing to do with classical Mendelian genetics, and has a postgenomic component.

The most fascinating aspect of this is the withering “dark matter” of the genome. While that component may be silent or expressed, the understanding comes at a higher observed order.  The dark became light! The expression became subtle, like weak bond interactions. The underlying organization is a component of the adaptive ability of an organism or individual in an environment with plants and animals in a changing climate, at particular altitudes, with given water supplies, with disease vectors, and with endogenous sources of essential nutrients.  This brings into focus the regulatory role of the genome as just as important a factor as transmission of the genetic code, especially in somatic cell populations.

The remainder of this discussion deals specifically with my observations on cardiovascular genomics. The following conclusion is appropriate, if incomplete, at this time on circulating miRNAs, particularly miR-133a:

  • elevated levels of circulating miR-133a in patients with cardiovascular diseases originate mainly from the injured myocardium.
  • Circulating miR-133a can be used as a marker for cardiomyocyte death, and

A number of articles that cite this article suggest that it may be useful for following disease progression:
Plasma microRNAs serve as biomarkers of therapeutic efficacy and disease progression in hypertension-induced heart failure  Eur J Heart Fail  2013

MicroRNAs Within the Continuum of Postgenomics Biomarker Discovery Arterio. Thromb. Vasc. Bio. 2013;33:206-214

“Need for Rigor in Design, Reporting, and Interpretation of Transcriptomic Biomarker Studies”  J. Clin. Microbiol.. 2012;50:4192-4193

Circulating microRNAs as diagnostic biomarkers for cardiovascular diseases. Am. J. Physiol. Heart Circ. Physiol.. 2012;303:H1085-H1095,

Circulating MicroRNAs: Novel Biomarkers and Extracellular Communicators in Cardiovascular Disease? Circ. Res.. 2012;110:483-495

Circulating MicroRNAs: Biomarkers or Mediators of Cardiovascular Diseases?  Arterioscler. Thromb. Vasc. Bio. 2011;31:2383-2390,

Circulating MicroRNA-208b and MicroRNA-499 Reflect Myocardial Damage in Cardiovascular Disease MF Corsten, R Dennert, S Jochem, T Kuznetsova,  et al.

The finding refers to an association that is related to the appearance of a miRNA in the circulation of patients with acute cardiac ischemia, and particular released into the circulation of patients from injured myocardium.  This finding has to be distinguished from a finding of another miRNA released with acute injury.  In the case of miR499 (and miR208b), there is a comparison with plasma cTnT, and an ROC curve is produced.

The List of this follows:

Circulation: Cardiovascular Genetics 2010; 3: 499-506

Strikingly, in plasma from

  • acute myocardial infarction patients, cardiac myocyte–associated miR-208b and -499 were highly elevated, 1600-fold (P<0.005) and 100-fold (P<0.0005), respectively, as compared with control subjects. Receiver operating characteristic curve analysis revealed an area under the curve of 0.94 (P<10−10) for miR-208b and 0.92 (P<10−9) for miR-499. Both microRNAs correlated with plasma troponin T, indicating release of microRNAs from injured cardiomyocytes.
  • In patients with acute heart failure, only miR-499 was significantly elevated (2-fold), whereas
  • no significant changes in microRNAs studied could be observed in diastolic dysfunction.

Remarkably, plasma microRNA levels were not affected by a wide range of clinical confounders, including

  • age,
  • sex,
  • body mass index,
  • kidney function,
  • systolic blood pressure, and
  • white blood cell count.

This is miRNA with a different twist.  It appears that there are 3 types found in AMI (133a, 208b, 409).  But type 499 alone is increased with acute heart failure (no mention of chronic cardiomyopathy and no effect of estimated GFR, or of age).

If the problem was just of AMI, then we have to know what this brings to the table.  As it is the hs-troponins have yet to be shown to effectively not only increase the high sensitivity of the tests, but to decrease the confusion generated by the elevation.  The enormous improvement of a test that may be superior to the hs-ctn’s is for the patient with very indeterminiate shortness of breath, a nondefinitive ECG, and in a prodromal phase of AMI.  This happened in the past, and it may happen now, and it may account for many cases of silent MI that were found at autopsy.

Cited by
Plasma microRNAs serve as biomarkers of therapeutic efficacy and disease progression in hypertension-induced heart failure Eur J Heart Fail. 2013;0:hft018v1-hft018,
Circulating microRNAs as diagnostic biomarkers for cardiovascular diseases Am. J. Physiol. Heart Circ. Physiol.. 2012;303:H1085-H1095,

Circulation Editors’ Picks: Most Read Articles in Cardiovascular Genetics Circulation. 2012;126:e163-e169,
MicroRNAs in Patients on Chronic Hemodialysis (MINOS Study) CJASN. 2012;7:619-623,

Novel techniques and targets in cardiovascular microRNA research Cardiovasc Res. 2012;93:545-554,

Microparticles: major transport vehicles for distinct microRNAs in circulation Cardiovasc Res. 2012;93:633-644,

Profiling of circulating microRNAs: from single biomarkers to re-wired networks Cardiovasc Res. 2012;93:555-562,

Small but smart–microRNAs in the centre of inflammatory processes during cardiovascular diseases, the metabolic syndrome, and ageing   Cardiovasc Res. 2012;93:605-613,

Circulation: Heart Failure Editors’ Picks: Most Important Papers in Pathophysiology and Genetics Circ Heart Fail. 2012;5:e32-e49

Use of Circulating MicroRNAs to Diagnose Acute Myocardial Infarction   Clin. Chem. 2012;58:559-567,

Circulating microRNAs to identify human heart failure   Eur J Heart Fail. 2012;14:118-119,

Next Steps in Cardiovascular Disease Genomic Research–Sequencing, Epigenetics, and Transcriptomics  Clin. Chem. 2012;58:113-126,

Most Read in Cardiovascular Genetics on Biomarkers, Inherited Cardiomyopathies and Arrhythmias, Metabolomics, and Genomics Circ Cardiovasc Genet. 2011;4:e24-e30,

MicroRNA-126 modulates endothelial SDF-1 expression and mobilization of Sca-1+/Lin- progenitor cells in ischaemia  Cardiovasc Res. 2011;92:449-455,

The use of genomics for treatment is another matter, and has several factors, e.g., age, residual function after AMI, comorbidities

This is a lot of interesting work that opens as many questions as it answers. The observations are real, and they lead to questions relating to the heart and the circulation.  Maybe it will generate answers to very tough issues concerning hypertension, renal disease and the heart.  It is far too early to tell.  It appears that we are about to hear a cacophony of miR’s in a symphony on cardiac and circulatory diseases not be be pieced together soon. But we have many more tools at our disposal than we did when Karmen discovered and made a distinction between

  • Aspartate and Alanine aminotransferases in the late 1950s, followed in the 1960s by
  • Creatine phosphokinase, the
  • MB-isoenzyme of CK by Sobel, Shell and Kjeckshus,
  • isoenzyme-1 of lactate dehydrogenase, and later the
  • Troponins,

leading to the programs to “reduce the extent of infarct damage”.  Then came the

  • a- and b-type natriuretic peptides,

which are still not fully understood in their role in congestive heart failure and in renal disease.

One item strikes the imagination as a fruitful area of further study.   Genetic Determinants of Potassium Sensitivity and Hypertension.    Integrated Computational and Experimental Analysis of the Neuroendocrine Transcriptome in Genetic Hypertension Identifies Novel Control Points for the Cardiometabolic Syndrome

Essential hypertension, a common complex disease, displays substantial genetic influence. Contemporary methods to dissect the genetic basis of complex diseases such as the genomewide association study are powerful, yet a large gap exists betweens the fraction of population trait variance explained by such associations and total disease heritability.

The researchers

  • developed a novel, integrative method (combining animal models, transcriptomics, bioinformatics, molecular biology, and trait-extreme phenotypes)
  • to identify candidate genes for essential hypertension and the metabolic syndrome.

Method  …  transcriptome profiling on adrenal glands from blood pressure extreme mouse strains:

  1. the hypertensive BPH (blood pressure high) and
  2. hypotensive BPL (blood pressure low).

Results….   Microarray data clustering revealed

  • underexpression of intermediary metabolism transcripts in HIGH BLOOD PRESSURE.
  • The MITRA algorithm identified a conserved motif in the transcriptional regulatory regions of the underexpressed metabolic genes,
  • They decide that regulation through this motif contributed to the global underexpression.
  • Luciferase reporter assays demonstrated transcriptional activity of the motif through transcription factors
    • HOXA3,
    • SRY, and
    •  YY1.

They finally hypothesized that genetic variation at HOXA3, SRY, and YY1 might predict blood pressure and other metabolic syndrome traits in humans. Tagging variants for each locus were associated with

  • blood pressure in a human population blood pressure extreme sample with
  • the most extensive associations for YY1 tagging single nucleotide polymorphism rs11625658 on
  1. systolic blood pressure,
  2. diastolic blood pressure,
  3. body mass index, and
  4. fasting glucose.

Meta-analysis extended the YY1 results into 2 additional large population samples with significant effects preserved on diastolic blood pressure, body mass index, and fasting glucose.

It will take much more of this beautiful integrative work to open up our imagination as to what physiological processes are occurring.

Read Full Post »

Heart Vasculature – Regeneration and Protection of Coronary Artery Endothelium and Smooth Muscle: A Concept-based Pharmacological Therapy of a Combination Three Drug Regimen including THYMOSIN 

Author & Curator: Aviva Lev-Ari, PhD, RN


ABSTRACT

A concept-based original pharmacological therapy was developed for the research results presented in Cell by Wu, Fujiwara, Cibulsky et al. (2006), Moretti, Caron, Nakano, et al. (2006) and for the research results in Nature by Smart, Risebro, Melville, et al. (2007). We propose the following concept-based original pharmacological therapy design for Preoperative and Postoperative management of cardiac injury to heart tissue, smooth muscle, to aorta and coronary artery disease. This is a treatment for Coronary Vasculogenesis, Anti-hypertention (short-acting), Vascular Anti-inflammation (vasculitis), Neovascularization of ischemic tissue and release of adult epicardium from a quiescent state while restoring its pluripotency.

VIEW VIDEO

What are Induced Pluripotent Stem Cells? (iPS Cells)

 http://www.youtube.com/watch?v=i-QSurQWZo0

Lasker Lecture: Dr. Shinya Yamanaka, 2 of 3:

Induced Pluripotent Stem Cells? (iPS Cells)

http://www.youtube.com/watch?v=DQNoyDwCPzM

Multipotent Embryonic Isl1^+ Progenitor Cells Lead to Cardiac, Smooth Muscle, and Endothelial Cell Diversification

Alessandra A Moretti, Leslie L Caron, Atsushi A Nakano, Jason T JT Lam, Alexandra A Bernshausen,Yinhong Y Chen, Yibing Y Qyang, Lei L Bu, Mika M Sasaki, Silvia S Martin-Puig, Yunfu Y Sun, Sylvia M SM Evans, Karl-Ludwig KL Laugwitz, Kenneth R KR Chien
Cell 127(6):15 (2006), PMID 17123592

Cardiogenesis requires the generation of endothelial, cardiac, and smooth muscle cells, thought to arise from distinct embryonic precursors. We use genetic fate-mapping studies to document that isl1^+ precursors from the second heart field can generate each of these diverse cardiovascular cell types in vivo. Utilizing embryonic stem (ES) cells, we clonally amplified a cellular hierarchy of isl1^+ cardiovascular progenitors, which resemble the developmental precursors in the embryonic heart. The transcriptional signature of isl1^+/Nkx2.5^+/flk1^+ defines a multipotent cardiovascular progenitor, which can give rise to cells of all three lineages. These studies document a developmental paradigm for cardiogenesis, where muscle and endothelial lineage diversification arises from a single cell-level decision of a multipotent isl1^+ cardiovascular progenitor cell (MICP). The discovery of ES cell-derived MICPs suggests a strategy for cardiovascular tissue regeneration via their isolation, renewal, and directed differentiation into specific mature cardiac, pacemaker, smooth muscle, and endothelial cell types.

http://pubget.com/paper/17123592/Multipotent_Embryonic_Isl1___Progenitor_Cells_Lead_to_Cardiac__Smooth_Muscle__and_Endothelial_Cell_Diversification


Thymosin beta 4 (Tβ4)

is a highly conserved, 43-amino acid acidic peptide (pI 4.6) that was first isolated from bovine thymus tissue over 25 years ago. It is present in most tissues and cell lines and is found in high concentrations in blood platelets, neutrophils, macrophages, and other lymphoid tissues. Tβ4 has numerous physiological functions, the most prominent of which being the regulation of actin polymerization in mammalian nucleated cells and with subsequent effects on actin cytoskeletal organization, necessary for cell motility, organogenesis, and other important cellular events.

Recently,

  • Tβ4 was shown to be expressed in the developing heart and found to stimulate migration of cardiomyocytes and endothelial cells, promote survival of cardiomyocytes (Nature, 2004), and most recently
  • to play an essential role in all key stages of cardiac vessel development: vasculogenesis, angiogenesis, and arteriogenesis (Nature 2006).
  • These results suggest that Tβ4 may have significant therapeutic potential in humans to protect myocardium and promote cardiomyocyte survival in the acute stages of ischemic heart disease.

RegeneRx Biopharmaceuticals, Inc. is developing Tβ4 for the treatment of patients with acute myocardial infarction (AMI). Such efforts presented will include the formulation, development, and manufacture of a suitable drug product for use in the clinic, the performance of nonclinical pharmacology and toxicology studies, and the implementation of a phase 1 clinical protocol to assess the safety, tolerability, and the pharmacokinetics of Tβ4 in healthy volunteers.

http://onlinelibrary.wiley.com/doi/10.1196/annals.1415.051/abstract;jsessionid=BB7CC897572B7DDB60370EA64A81FC3F.d01t03?deniedAccessCustomisedMessage=&userIsAuthenticated=false

EXPLORATIONS with THYMOSIN beta4 for INDUCING ADULT EPICARDIAL PROGENETOR MOBILIZATION AND NEOVASCULARIZATION is presented in

Resident-cell-based Therapy in Human Ischaemic Heart Disease: Evolution in the PROMISE of Thymosin beta4 for Cardiac Repair

http://pharmaceuticalintelligence.com/2012/04/30/93/

EXPLORATIONS with THYMOSIN beta4 for INDUCTION of ARTERIOGENESIS, Prevention and repair of damaged cardiac tissue post MI and other CVD related research projects are presented in

Arteriogenesis and Cardiac Repair: Two Biomaterials – Injectable Thymosin beta4 and Myocardial Matrix Hydrogel

http://pharmaceuticalintelligence.com/2013/02/27/arteriogenesis-and-cardiac-repair-two-biomaterials-injectable-thymosin-beta4-and-myocardial-matrix-hydrogel/

Recent research results with THYMOSIN beta4 in use for Cardiovascular Disease

appeared in 2010:

Annals of the New York Academy of Sciences, May 2010 Volume 1194 Pages ix–xi, 1–230

http://onlinelibrary.wiley.com/doi/10.1111/nyas.2010.1194.issue-1/issuetoc

appeared in 2012:

  • Thymosins in Health and Disease II: 3rd International Symposium on The Emerging Clinical Applications of Tymosin beta 4 in Cardiovascular Disease

Annals of the New York Academy of Sciences, October 2012 Volume 1270 Pages vii-ix, 1–121.

http://onlinelibrary.wiley.com/doi/10.1111/nyas.2012.1270.issue-1/issuetoc

Allan L. Goldstein, Enrico Garaci, Editors, Thymosins in Cardiovascular Disease, November 2012, Wiley-Blackwell (paperback)

http://www.wiley.com/WileyCDA/WileyTitle/productCd-1573319104.html?cid=RSS_WILEY2_LIFEMED

Selected for this article are the abstracts of the following research projects, all were presented at the 2nd International Symposium, May 2010:

Thymosin β4: structure, function, and biological properties supporting current and future clinical applications

Published studies have described a number of physiological properties and cellular functions of thymosin β4 (Tβ4), the major G-actin-sequestering molecule in mammalian cells. Those activities include the promotion of cell migration, blood vessel formation, cell survival, stem cell differentiation, the modulation of cytokines, chemokines, and specific proteases, the upregulation of matrix molecules and gene expression, and the downregulation of a major nuclear transcription factor. Such properties have provided the scientific rationale for a number of ongoing and planned dermal, corneal, cardiac clinical trials evaluating the tissue protective, regenerative and repair potential of Tβ4, and direction for future clinical applications in the treatment of diseases of the central nervous system, lung inflammatory disease, and sepsis. A special emphasis is placed on the development of Tβ4 in the treatment of patients with ST elevation myocardial infarction in combination with percutaneous coronary intervention, pp.179-189, May 2010.


Thymosin β4 and cardiac repair

Hypoxic heart disease is a predominant cause of disability and death worldwide. As adult mammals are incapable of cardiac repair after infarction, the discovery of effective methods to achieve myocardial and vascular regeneration is crucial. Efforts to use stem cells to repopulate damaged tissue are currently limited by technical considerations and restricted cell potential. We discovered that the small, secreted peptide thymosin β4 (Tβ4) could be sufficiently used to inhibit myocardial cell death, stimulate vessel growth, and activate endogenous cardiac progenitors by reminding the adult heart on its embryonic program in vivo. The initiation of epicardial thickening accompanied by increase of myocardial and epicardial progenitors with or without infarction indicate that the reactivation process is independent of injury. Our results demonstrate Tβ4 to be the first known molecule able to initiate simultaneous myocardial and vascular regeneration after systemic administration in vivo. Given our findings, the utility of Tβ4 to heal cardiac injury may hold promise and warrant further investigation, pp. 87-96, May 2010.


Thymosin β4 facilitates epicardial neovascularization of the injured adult heart

Ischemic heart disease complicated by coronary artery occlusion causes myocardial infarction (MI), which is the major cause of morbidity and mortality in humans

http://www.who.int/cardiovascular_diseases/resources/atlas/en/index.html

After MI the human heart has an impaired capacity to regenerate and, despite the high prevalence of cardiovascular disease worldwide, there is currently only limited insight into how to stimulate repair of the injured adult heart from its component parts. Efficient cardiac regeneration requires the replacement of lost cardiomyocytes, formation of new coronary blood vessels, and appropriate modulation of inflammation to prevent maladaptive remodeling, fibrosis/scarring, and consequent cardiac dysfunction. Here we show that thymosin β4 (Tβ4) promotes new vasculature in both the intact and injured mammalian heart. We demonstrate that limited EPDC-derived endothelial-restricted neovascularization constitutes suboptimal “endogenous repair,” following injury, which is significantly augmented by Tβ4 to increase and stabilize the vascular plexus via collateral vessel growth. As such, we identify Tβ4 as a facilitator of cardiac neovascularization and highlight adult EPDCs as resident progenitors which, when instructed by Tβ4, have the capacity to sustain the myocardium after ischemic damage, pp. 97-104, May 2010.


Thymosin β4: a key factor for protective effects of eEPCs in acute and chronic ischemia

Acute myocardial infarction is still one of the leading causes of death in the industrial nations. Even after successful revascularization, myocardial ischemia results in a loss of cardiomyocytes and scar formation. Embryonic EPCs (eEPCs), retroinfused into the ischemic region of the pig heart, provided rapid paracrine benefit to acute and chronic ischemia in a PI-3K/Akt-dependent manner. In a model of acute myocardial ischemia, infarct size and loss of regional myocardial function decreased after eEPC application, unless cell pre-treatment with thymosin β4 shRNA was performed. Thymosin ß4 peptide retroinfusion mimicked the eEPC-derived improvement of infarct size and myocardial function. In chronic ischemia (rabbit model), eEPCs retroinfused into the ischemic hindlimb enhanced capillary density, collateral growth, and perfusion. Therapeutic neovascularization was absent when thymosin ß4 shRNA was introduced into eEPCs before application. In conclusion, eEPCs are capable of acute and chronic ischemia protection in a thymosin ß4 dependent manner, pp. 105-111, May 2010.

Clinical Study Data of Thymosin beta 4 Presented

Published on October 3, 2009 at 5:10 AM

REGENERX BIOPHARMACEUTICALS, INC. (NYSE Amex:RGN) today reported on several clinical studies with Thymosin beta 4 (Tβ4) presented the Second International Symposium on Thymosins in Health and Disease, in Catania, Italy. The following are synopses of the presentations:

Myocardial Development of RGN-352 (Injectable Tβ4 Peptide)

David Crockford, RegeneRx’s vice president for clinical and regulatory affairs presented an overview of the biological properties that support Tβ4’s near term and long term clinical applications. Mr. Crockford noted that special emphasis is being placed on the development of RGN-352 for the systemic (injectable) treatment of patients with ST-elevation myocardial infarction (STEMI) in combination with percutaneous coronary intervention, the current standard of care in most western countries for this common type of heart attack. The goal with RGN-352 is to prevent or repair continued damage to cardiac tissue post-heart attack, when such tissue around the damaged site remains at risk.

Dr. Dennis Ruff, vice president and medical director of ICON, and principal investigator, presented the most current results on the Phase I safety study with RGN-352 entitled, “A Randomized, Double-blind, Placebo-controlled, Dose-response Phase I Study of the Safety and Tolerability of the Intravenous Administration of Thymosin Beta 4 and its Pharmacokinetics After Single and Multiple Doses in Healthy Volunteers.” Dr. Ruff discussed key aspects of the study and concluded with, “There were no dose limiting or serious adverse events throughout the dosing period. Synthetic Tβ4 administered intravenously up to 1260 mg, and for up to 14 days, appears to be well tolerated with low incidence of adverse events and no evidence of serious adverse events.”

http://www.news-medical.net/news/20091003/Clinical-study-data-of-Thymosin-beta-4-presented.aspx

RegeneRx Receives Notice of Allowance from Chinese Patent Office for Treatment and Prevention of Heart Disease

RegeneRx Receives Notice of Allowance from Chinese Patent Office for Treatment and Prevention of Heart Disease

February 7, 2013 — Rockville, MD

RegeneRx Biopharmaceuticals, Inc. (OTC Bulletin Board: RGRX) (“the Company” or “RegeneRx”) today announced that it has received a Notice of Allowance of a Chinese patent application for uses of Thymosin beta 4 (TB4) for treating, preventing, inhibiting or reducing heart tissue deterioration, injury or damage in a subject with heart failure disease. Claims also include uses for restoring heart tissue in those subjects. The patent will expire July 26, 2026 http://www.regenerx.com/wt/page/pr_1360265259

Theoretical treatment protocol differential between the Preoperative which may be between 3 to 6 month, and the Postoperative which may prolong to one year.

Proposal for Preoperative Treatment – Three drug combination involves

  • Drug # 1: Thymosin fraction 5 (a sublingual composition)
  • Drug # 2: Indomethacin (Nonsteroidal anti-inflammatory drugs (NSAID))
  • Drug # 3: Clevidipine (blood pressure lowering drug, (no effect on heart rate))


Proposal for Postoperative Treatment – Three drug combination consists of

  • Drug # 1: Thymosin fraction 5 (a sublingual composition)
  • Drug # 4: ACEI (Captopril (50mg))
  • Drug # 5: Beta Blocker and Diuretic (Metoprolol and hydrochlorothiazide (50 mg/25 mg)) Lopressor HCT

Unprecedented novel paradigm development in the scientific understanding of the origin of

  • (a) myocardial cells
  • (b) smooth muscle cells
  • (c) endothelial cells
  • (d) pace maker cells and
  • (e) heart vasculature: aorta, pulmonary artery and coronary arteries, occurred in 2006.

In a seminal article in Cell, “Developmental Origin of a Bipotential Myocardial and Smooth Muscle Cell Precursor in the Mammalian Heart” Wu, et al., (2006), described their discovery as follows:

“Despite recent advances in delineating the mechanisms involved in cardiogenesis, cellular lineage specification remains incompletely understood.” To explore the relationship between developmental fate and potential.” They “isolated a cardiac-specific Nkx2.5+ cell population from the developing mouse embryo. The majority of these cells differentiated into cardiomyocytes and conduction system cells. Some, surprisingly, adopted a smooth muscle fate. To address the clonal origin of these lineages, we isolated Nkx2.5+ cells from in vitro differentiated murine embryonic stem cells and found ~28% of these cells expressed c-kit. These c-kit+ cells possessed the capacity for long-term in vitro expansion and differentiation into both cardiomyocytes and smooth muscle cells from a single cell.” They “confirmed these findings by isolating c-kit+Nkx2.5+ cells from mouse embryos and demonstrated their capacity for bipotential differentiation in vivo. Taken together, these results support the existence of a common precursor for cardiovascular lineages in the mammalian heart.”

Another breakthrough article in Cell, “Multipotent Embryonic Isl1+ Progenitor Cells Lead to Cardiac, Smooth Muscle, and Endothelial Cell Diversification” Moretti, et al., (2006) described their discovery as follows:

“Cardiogenesis requires the generation of endothelial, cardiac, and smooth muscle cells, thought to arise from distinct embryonic precursors.” They “use genetic fate-mapping studies to document that isl1+ precursors from the second heart field can generate each of these diverse cardiovascular cell types in vivo. Utilizing embryonic stem (ES) cells”, they “clonally amplified a cellular hierarchy of isl1+ cardiovascular progenitors, which resemble the developmental precursors in the embryonic heart. The transcriptional signature of isl1+/Nkx2.5+/flk1+ defines a multipotent cardiovascular progenitor, which can give rise to cells of all three lineages. These studies document a developmental paradigm for cardiogenesis, where muscle and endothelial lineage diversification arises from a single cell-level decision of a multipotent isl1+ cardiovascular progenitor cell (MICP). The discovery of ES cell-derived MICPs suggests a strategy for cardiovascular tissue regeneration via their isolation, renewal, and directed differentiation into specific mature cardiac, pacemaker, smooth muscle, and endothelial cell types.” (Moretti, et al., 2006).

Third scientific breakthrough was reported in Nature on the roles that Thymosin beta4 play in

  • (a) coronary vessel development
  • (b) induction of adult epicardial cell migration
  • (c) cardiomyocyte survival by vascularization which is dependent on Thymosin beta4 and
  • (d) identification of the pro-angiogenic tetrapeptide AcSDKP which is produced by endoproteinase activity of Thymosin beta4 (Smart, et al., 2007).

That new level of understanding has the potential to generate new pharmaco therapies to upregulate biological processes that underlie the function of the various compartments of the cardiovascular system, as new scientific explanations became available in 2006.

We have developed a methodology for discovery of concept-based original pharmacological therapy designs for combination of several drug regimens. We carry out two types of research strategy. Methodology Strategy Type One: we develop an original pharmacological therapy design specialized in addressing medical problems identified in targeted follow up studies on mortality and morbidity of cardiovascular patients. Methodology Strategy Type One is implemented in Lev-Ari & Abourjaily (2006a, 2006b, 2006c). We designed a specialized pharmaco therapy for the research results presented in NEJM, on “Circulating Endothelial Progenitor Cells and Cardiovascular Outcomes” (Werner, Kosiol, Schiegl, et al., 2005a) and the editorial interpretation of these research results by Rosenzweig  (2005). We proposed the following concept-based original pharmacological therapy design for Endogenous Augmentation of circulating Endothelial Progenitor Cells for Reduction of Risk for Macrovascular Cardiac Events.


Proposal of Treatment – Three drug combination

  • Inhibition of ET-1, ETA and ETA-ETB (Bosentan)
  • Induction of NO production and stimulation of eNOS (Nebivolol)
  • Stimulation of PPAR-gamma (substitute to Rosiglitazone)

Our Methodology Strategy Type Two involves discovery of concept-based original pharmacological therapy design for combination of several drug regimens for underlying biological processes discovered in the pursuit of basic researchers conducted in wet lab experiments by vascular biologists and molecular cardiologists. Here, we developed a concept-based original pharmacological therapy for the research results presented in Cell by Wu, Fujiwara, Cibulsky et al. (2006), Moretti, Caron, Nakano, et al. (2006) and for the research results in Nature by Smart, Risebro, Melville, et al. (2007). We propose the following concept-based original pharmacological therapy design for Preoperative and Postoperative management of cardiac injury to heart tissue, smooth muscle and to aorta and coronary artery disease. This is a treatment for Coronary Vasculogenesis, Anti-hypertention (short-acting), Vascular Anti-inflammation (vasculitis), Neovascularization of ischemic tissue and release of adult epicardium from a quiescent state and restoring its pluripotency.


Proposal for Preoperative Treatment – Three drug combination

  • Drug # 1:

Thymosin fraction 5 (a sublingual composition)

  • Drug # 2:

Indomethacin (Nonsteroidal anti-inflammatory drugs (NSAID))

  • Drug # 3:

Clevidipine (blood pressure lowering drug, no effect on heart rate)

Proposal for Postoperative Treatment – Three drugs combination

  • Drug # 1:

Thymosin fraction 5 (a sublingual composition)

  • Drug # 4:

ACEI (Captopril (50mg))

  • Drug # 5:

HCTBeta Blocker and Diuretic (Metoprolol and hydrochlorothiazide (50 mg/25 mg)) Lopressor


Thymosin beta4 Induces Adult Epicardial Progenitor Mobilization and Neovascularization


Smart et al. (2007) implicate Thymosine beta4 (Tb4) with the following functions: (a) Tb4 in regulating all three key stages of cardiac vessel development: coronary vasculogenesis, angiogenesis and arteriogenesis – collateral growth; (b) identify the adult epicardium as a potential source of vascular progenitors which, when stimulated by Tb4, migrate and differentiate into smooth muscle and endothelial cells; (c) the ability of Tb4 to promote coronary vascularization both during development and in the adult, enhances cardiomyocyte survival and contributes significantly towards Tb4-induced cardioprotection.

The reaction in the scientific community to these investigative results was most favorable.

“These results are very exciting because most humans suffering from ischemic cardiac events, either acutely or chronically, do not develop the collateral vessel growth necessary to preserve and restore heart tissue. If, in humans, we see the same effects as seen in mice, TB4 would be the first drug to prevent loss of (heart) muscle cells and restore blood flow in this manner and provide a new and much needed treatment modality for these patients,”

commented Deepak Srivastava, M.D., Professor and Director, Gladstone Institute of Cardiovascular Disease, University of California San Francisco, CA. Dr. Srivastava and his colleagues published the first paper on TB4’s effects on myocardial infarction in Nature in November 2004.

http://phx.corporate-ir.net/phoenix.zhtml?c=144396&p=irol-newsArticle&ID=932573&highlight=

VIEW VIDEO

http://www.youtube.com/watch?v=Vjj7LSuSMAo


Review of the Chemistry and the Mechanism of action supporting the process by which, N-acetyl-seryl-aspartyl-lysyl- proline (Ac-SDKP) stimulates endothelial cell differentiation from adult epicardium, is presented in

Resident-cell-based Therapy in Human Ischaemic Heart Disease: Evolution in the PROMISE of Thymosin beta4 for Cardiac Repair

http://pharmaceuticalintelligence.com/2012/04/30/93/

A Concept-based Pharmacologic Therapy of a Combined Three Drug Regimen for Regeneration and Protection of Coronary Artery Endothelium and Smooth Muscle.

This is a treatment for Coronary Vasculogenesis, Anti-hypertention (short-acting), Vascular Anti-inflammation (vasculitis), Neovascularization of ischemic tissue and release of adult epicardium from a quiescent state and restoring its pluripotency.


Preoperative Treatment – Three drugs

  • Drug # 1:
  • Thymosin fraction 5 (a sublingual composition)
  • Drug # 2:
  • Indomethacin (Nonsteroidal anti-inflammatory drugs (NSAID)) (25 mg PO bid)
  • Drug # 3:
  • Clevidipine (Blood pressure lowering drug, no effect on heart rate)


Postoperative Treatment – Three drugs

  • Drug # 1:
  • Thymosin fraction 5 (a sublingual composition)
  • Drug # 4:
  • ACEI (Captopril (50mg))
  • Drug # 5:
  • Beta Blocker and diuretic (Metoprolol and hydrochlorothiazide (50 mg/25 mg)) Lopressor HCT

Original Drug Therapy Combination Proposed

Drug # 1: Thymosin fraction 5

Drug # 2: Indomethacin

Drug # 3: Clevidipine

Drug # 1:

Sublingual compositions comprising Thymosin fraction 5

United States Patent:  6,733,791

http://www.pharmcast.com/Patents100/Yr2004/May2004/051104/6733791_Sublingual051104.htm

http://www.google.com/patents/US6733791

The compositions comprise a room temperature stable peptide or complex of peptides that may be administered in a dosage of between 0.0001 mg/ml or gm and 600 mg/ml or gm.

Thymosin beta4 is released from human blood platelets and attached by factor XIIIa (transglutaminase) to fibrin and collagen (Huff et al. 2002). They suggest that Thymosin beta4 cross-linking is mediated by factor XIIIa, a transglutaminase that is co-released from stimulated platelets. This provides a mechanism to increase the local concentration of Thymosin beta4 near sites of clots and tissue damage, where it may contribute to wound healing, angiogenesis and inflammatory responses (Al-Nedawi, et al., 2004). The beta-Thymosins constitute a family of highly conserved and extremely water-soluble 5 kDa polypeptides. Thymosin beta4 is the most abundant member; it is expressed in most cell types and is regarded as the main intracellular G-actin sequestering peptide. There is increasing evidence for extracellular functions of Thymosin beta4. For example, Thymosin beta4 increases the rate of attachment and spreading of endothelial cells on matrix components and stimulates the migration of human umbilical vein endothelial cells. They show that Thymosin beta4 can be cross-linked to proteins such as fibrin and collagen by tissue transglutaminase. Thymosin beta4 is not cross-linked to many other proteins and its cross-linking to fibrin is competed by another family member, Thymosin beta10 (Huff et al. 2002).

Rationale for selection of Sublingual compositions comprising Thymosin fraction 5

The actin binding motif of Thymosin beta4 is an essential site for its angiogenic activity (Philip, et al. (2003). Thymosin beta4 is presented in Smart, et al. (2007) in the Nature article as a single factor that can potentially couple myocardial and coronary vascular regeneration in failing mouse hearts. They have shown that cells in the heart’s outer layer can migrate deeper into a failing organ to carry out essential repairs. The migration of progenitor cells is controlled by the protein Thymosin beta 4, already known to help reduce muscle cell loss after a heart attack.

http://news.bbc.co.uk/2/hi/health/6143286.stm

The discovery opens up the possibility of using the protein to develop more effective treatments for heart disease. Previously it was thought that cells within the adult heart are in a state of permanent rest and that any progenitor cells that can contribute to heart tissue repair travel into the heart from the bone marrow. See 150 references on that perspective on cEPCs origin and roles, which was the scientific frontier on this topic, prior to the publication of Smart et al., (2007), in Lev-Ari & Abourjaily (2006a, 2006b, 2006c).

However, researchers at University College London have demonstrated that beneficial cells actually reside in the heart itself (Smart et al. (2007). This approach would bypass the risk of immune system rejection, a major problem with the use of stem cell transplants from another source. Allogenic rejection was the main reason for the selection of an endogenous augmentation method for cEPCs using drug therapy by Lev-Ari & Abourjaily  (2006a, 2006b, 2006c). Closer examination revealed that without the Thymosin beta 4 protein, the progenitor cells failed to move deeper into the heart and change the cells needed to build healthy blood vessels and sustain muscle tissue.

http://www.irishhealth.com/clin/cholesterol/newsstory.php?id=10581

Drug # 2:

Indomethacin

Nonsteroidal anti-inflammatory drugs (NSAIDs) are widely used for their anti-inflammatory effects and have been shown to have chemopreventive effects as well. NSAIDs inhibit cyclooxygenase (COX) activity to exert their anti-inflammatory effects, but it is not clear whether their antitumorigenic ability is through COX inhibition. Using subtractive hybridization, Jain et al. (2004) identified a novel member of the transforming growth factor- superfamily that has antitumorigenic activity from Indomethacin-treated HCT-116 human colorectal cancer cells. On further investigation of this library, they now report the identification of a new cDNA corresponding to the Thymosin beta-4 gene. Thymosin beta-4 is a small peptide that is known for its actin-sequestering function, and it is associated with the induction of angiogenesis, accelerated wound healing, and metastatic potential of tumor cells. However, only selective NSAIDs induce Thymosin beta-4 expression in a time- and concentration-dependent manner. For example,

Indomethacin and SC-560 [5-(4-chlorophenyl)-1-(4-methoxyphenyl)-3-(trifluoromethyl)-1H-pyrazole] induce Thymosin beta-4 expression whereas sulindac sulfide does not.

They show that selective NSAIDs induce actin cytoskeletal reorganization, a precursory step to many dynamic processes regulating growth and motility including tumorigenesis. This is the first report to link Thymosin beta-4 induction with NSAIDs. These data suggest that NSAIDs alter the expression of a diverse number of genes and provide new insights into the chemopreventive and biological activity of these drugs (Jain et al. 2004).

Rationale for Indomethacin selection


Inhibitor of prostaglandin synthesis. Inhibits cyclooxygenase (COX) 1 selective.

Suggested dosage: 25 mg PO bid.

Jain et al. (2004) report a link between Thymosin beta-4 induction with NSAIDs. We selected both drugs (drug classes) and anticipate strong synergistic therapeutic effects.

Drug # 3:

Clevidipine

Clevidipine is the first third-generation calcium channel blocker, Dr. Papadakos said. It has what he called an “ultrashort” clinically relevant half-life of about one minute and then is rapidly metabolized. The effect on blood pressure is seen within one to two minutes.

http://www.medpagetoday.com/MeetingCoverage/SCCM/tb/5091

Clevidipine is an investigational agent undergoing late-stage clinical development to evaluate its potential as an innovative, targeted, fast acting intravenous product under investigation for lowering blood pressure before, during and after surgery.

http://www.themedicinescompany.com/products_Clevidipine.shtml

The Medicines Company entered into agreements with AstraZeneca PLC in March of 2002 for the development, licensing and commercialization of Clevidipine. If approved, the product could be an excellent fit with The Medicines Company’s emerging acute cardiovascular care franchise, which is led by Angiomax® (bivalirudin), an anticoagulant approved in the U.S. and other countries for use during coronary angioplasty procedures. If Clevidipine passes further clinical hurdles — phase III trials are under way — the drug may form a useful addition to the medications available to physicians in the perioperative setting

Mechanism of Action

Clevidipine belongs to a well-known class of drugs called dihydropyridine calcium channel antagonists. In vitro studies demonstrated that Clevidipine acts by selectively relaxing the smooth muscle cells that line small arteries, resulting in widening of the artery opening and reducing blood pressure within the artery (Levy, Huraux, Nordlander, 1997, 345-358).

Phase III Clinical Trials

The Medicines Company is currently sponsoring a Phase III clinical program of five studies to evaluate safety and efficacy of Clevidipine:

Early Development

The Medicines Company’s development program for Clevidipine follows upon the data sets generated by AstraZeneca, which completed clinical pharmacology, dose-finding and efficacy studies in almost 300 patients or volunteers. In clinical studies, Clevidipine has shown to provide the desired blood pressure lowering effect without causing an increase in heart rate (Kotrly, et al. 1984). Further studies demonstrate that reductions in blood pressure are dose-dependent, are not associated with an increase in heart rate and cease rapidly after stopping Clevidipine infusions (Ericsson, et al., 2000), (Schwieler, et al., 1999). In clinical studies Clevidipine was rapidly metabolized independent of the liver and the kidneys, allowing rapid clearance of the drug from the bloodstream (Ericsson, et al., 1999a), (Ericsson, et al., 1999b). Therefore, the effects of Clevidipine are short-lived, which translates into a rapid cessation of its effect on reducing blood pressure.

The two efficacy studies are known as ESCAPE-1 and ESCAPE-2. The primary objective of these studies is to determine the efficacy of Clevidipine injection versus placebo in treating pre-operative (ESCAPE-1) and post-operative (ESCAPE-2) high blood pressure. Three safety studies are collectively known as ECLIPSE. The primary objective is to establish the safety of Clevidipine in the treatment of perioperative high blood pressure, as measured by a comparison of the incidences of death, stroke, myocardial infarction and renal dysfunction between the Clevidipine and comparative treatment groups. The comparative treatments are nitroglycerin, sodium nitroprusside and nicardipine.  The ECLIPSE trial randomized 589 patients at 40 centers in the U.S. to get either sodium nitroprusside or Clevidipine. Sodium nitroprusside was administered according to institutional practice; Clevidipine was begun at 2 mg/kg and doubled every 90 seconds until blood pressure was lowered. The primary endpoint was the difference in major clinical events — death, myocardial infarction, stroke, and renal dysfunction 30 days after surgery. The secondary endpoint was blood pressure control during the first 24 hours after surgery.

The study showed no significant differences in the elements of the primary endpoint, except for mortality, Dr. Papadakos said, where 1.7% of Clevidipine patients died, compared with 4.7 of those getting sodium nitroprusside.  The difference was statistically significant at P<0.05, but Dr. Papadakos characterized the improvement as “slight.” On the other hand, the drug did show an important difference in blood pressure control over the first 24 hours, he said:

  • Patients on Clevidipine spent an average of 4.37 minutes per hour outside the desired blood pressure range.
  • Sodium nitroprusside patients spent, on average, 10.5 minutes per hour outside the desired range.
  • The difference was statistically significant at P<0.003.

Dr. Papadakos concluded that Clevidipine is a new drug that is effective, safe, and easy to use. On 2/20/2007, Dr. Deutschman, who moderated the late-breaking session at which Dr. Papadakos spoke, said that a better comparison, would be intravenous nicardipine (Cardene IV), a second-generation calcium channel blocker that is also in wide use and is considered the standard of care. “We don’t know yet if this drug is going to be better than nicardipine,” he said.

http://www.medpagetoday.com/MeetingCoverage/SCCM/tb/5091

Rationale for Clevidipine selection

Clevidipine is an acute care product. Blood pressure management is a major component of care during the 13.4 million inpatient surgeries conducted in the U.S. each year. Blood pressure control, which is managed by an anesthesiologist, is often important in patients with both normal and high blood pressure undergoing surgery or other interventional procedures. Some of these patients require rapid, precise control of blood pressure to avoid compromising key organ function such as the heart, brain and kidney.

CONCLUSION 

This is the first study to design a novel combination drug treatment for Coronary Vasculogenesis, Anti-hypertention (short-acting), Vascular Anti-inflammation (vasculitis), Neovascularization of ischemic tissue and release of adult epicardium from a quiescent state and restoring its pluripotency. This treatment is based on the new three paradigms that were presented in Cell (2006) and Nature (2007). This combination drug therapy of three drugs, one in current use (Indomethacin), and two in clinical trials (Thymosin beta4 & Clevidipine), has not been proposed before. It represents an original concept drug combination design by Lev-Ari & Abourjaily (2007). This combination represents the cutting edge conceptualization of the field of treatment of cardiac injury based on a protein produced in the heart cells, Thymosin beta4, which function as a tissue and artery healer. Its upregulation by drug therapy will revolutionize cardiology and treatment for cardiovascular disease. The combination drug therapy consists of the following drugs:

  • Drug # 1:

Thymosin fraction 5 (a sublingual composition)

  • Drug # 2:

Indomethacin (Nonsteroidal anti-inflammatory drugs (NSAID)) (25 mg PO bid)

  • Drug # 3:

Clevidipine (Blood pressure lowering drug, (no effect on heart rate))


REFERENCES

Al-Nedawi, K.N.I., Malgorzata, C., Bednarek, R., Szemraj, J., Swiatkowska, M., Cierniewska-Cieslak, A., Wyczolkowska, J., Cierniewski, C.S. (2004, February) “Thymosin 4 induces the synthesis of plasminogen activator inhibitor 1 in cultured endothelial cells and increases its extracellular expression.” Blood, 103, (4), 1319-1324.

Ericsson, H., Fakt. C., Hoglund. L., et al. (1999a). “Pharmacokinetics and pharmacodynamics of Clevidipine in healthy volunteers after intravenous infusion.” Eur J Clin Pharm., 55 (1), 61-67.

Ericsson, H., Fakt, C., Jolin-Mellgard A., et al. (1999b). “Clinical and pharmacokinetic results with a new ultrashort-acting calcium antagonist, Clevidipine, following gradually increasing intravenous doses to healthy volunteers.” Br J Clin Pharm., 47 (5), 531-538.

Ericsson, H., Bredberg, U., Eriksson, U., et al. (2000). “Pharmacokinetics and arteriovenous differences in Clevidipine concentration following a short and a long-term intravenous infusion in healthy volunteers.” Anesthesiology, 92 (4), 993-1001.

Fleming, I. (2006). “Signaling by the Angiotensin-Converting Enzyme” Circulation Research, 98, 887.

Heart can carry out own repairs, 16.11.2006

Retrieved on 3/1/2007

http://www.medicalprogress.org/benefits/heartdis/news.cfm?news_id=478

Retrieved on 3/1/2007

http://news.bbc.co.uk/2/hi/health/6143286.stm

Heart may be able to repair itself

Retrieved on 3/1/2007

http://www.irishhealth.com/clin/cholesterol/newsstory.php?id=10581

Huff, T., Otto, A., Muller, C.S.G., Meier, M., Hannappel, E. (2002). “Thymosin ß4 is released from human blood platelets and attached by factor XIIIa (transglutaminase) to fibrin and collagen.”The FASEB Journal, 16, 691-696.

Jain, A.K., Moore, S.M., Yamaguchi, K., Eling, T.E., Baek, S.J. (2004, August). “Selective Nonsteroidal Anti-Inflammatory Drugs Induce Thymosin beta-4 and Alter Actin Cytoskeletal Organization in Human Colorectal Cancer Cells.” Journal of Pharmacology and Experimental Therapeutics, 311 (3) 885-891.

Kotrly, K. J., Ebert, T. J., Vucins, E. et al. (1984). “Baroreceptor reflex control of heart rate during isoflurane anesthesia in humans.” Anesthesiology,  60, 173-179.

Lev-Ari, A. & Abourjaily, P. (2006a) “An Investigation of the Potential of circulating Endothelial Progenitor Cells (cEPC) as a Therapeutic Target for Pharmacologic Therapy Design for Cardiovascular Risk Reduction.” Part I: Macrovascular Disease – Therapeutic Potential of cEPCs – Reduction methods for CV risk. Unpublished manuscript.

Lev-Ari, A. & Abourjaily, P. (2006b) “An Investigation of the Potential of circulating Endothelial Progenitor Cells (cEPC) as a Therapeutic Target for Pharmacologic Therapy Design for Cardiovascular Risk Reduction.” Part II: Therapeutic Strategy for cEPCs Endogenous Augmentation: A Concept-based Treatment Protocol for a Combined Three Drug Regimen. Unpublished manuscript.

Lev-Ari, A. & Abourjaily, P. (2006c) “An Investigation of the Potential of circulating Endothelial Progenitor Cells (cEPC) as a Therapeutic Target for Pharmacological Therapy Design for Cardiovascular Risk Reduction.” Part III: Biomarker for Therapeutic Targets of Cardiovascular Risk Reduction by cEPCs Endogenous Augmentation using New Combination Drug Therapy of Three Drug Classes and Several Drug Indications. A Theoretical Design for Quantification of the Endogenous EPCs Augmentation for Differential Level of CV Risk Reduction and Diagnostic Device Design for Drug Delivery. Unpublished manuscript.

Lev-Ari, A. & Abourjaily, P. (2007). Heart Vasculature – Regeneration and Protection of Coronary Artery Endothelium and Smooth Muscle: A Concept-based Pharmacological Therapy of a Combined Three Drug Regimen. Unpublished manuscript.

Levy, J. H., Huraux, C., Nordlander, M. (1997). “Treatment of perioperative hypertension.” In: Epstein M, Ed. Chapter in Calcium Antagonists in Clinical Medicine. Philadelphiea: Hanely & Belfus, pp. 345-358.

Liu, J-M, Lawrence, F., Kovacevic, M., Bignon, J., Papadimitriou, E., Lallemand, J-Y., Katsoris, P., Potier, P., Fromes, Y., Wdzieczak-Bakala, J. (2003, April) “The tetrapeptide AcSDKP, an inhibitor of primitive hematopoietic cell proliferation, induces angiogenesis in vitro and in vivo.” Blood, 101 (8), 3014-3020

Moretti, A., Caron, L., Nakano, A., Lam, J.T., Bernshausen, A., Chen, Y., Qyang, Y., Bu, L., Sasaki, M., Martin-Puig, S., Sun, Y., Evans, S.M., Laugwitz, K-L, Chien, K.R. (2006, December) “Multipotent Embryonic Isl1+ Progenitor Cells Lead to Cardiac, Smooth Muscle, and Endothelial Cell Diversification.” Cell, 127, 1151-1165.

Protein Discovered That Can Tell Human Heart to Heal Itself

Retrieved 3/1/2007

http://www.cathlabdigest.com/displaynews.cfm?newsid=1122065

Philp D, Huff T, Gho YS, Hannappel E, Kleinman HK. (2003). “The actin binding site on Thymosin beta4 promotes angiogenesis.” FASEB Journal, published on line 9/18/2003.

Retrieved 3/1/2007

http://www.fasebj.org/cgi/reprint/03-0121fjev1.pdf

Putting the art in heart research, 15 February 2007

Retrieved on 3/1/2007

http://www.ich.ucl.ac.uk/pressoffice/pressrelease_00498

Rosenzweig A., (2005). Circulating Endothelial Progenitors – Cells as Biomarkers. NEJM, 353 (10), 1055-1057.

Schwieler, J.H., Ericsson, H., Lofdahl, P., et al. (1999). “Circulatory effects and pharmacology of Clevidipine, a novel ultra short acting and vascular selective calcium antagonist, in hypertensive humans.” J Cardiovasc Pharmacology, 34 (2), 268-274.

Smart, N., Risebro, C.A., Melville, A.D., Moses, K., Schwartz, R.J., Chien, K.R., Riley, P.R. (2007, January) “Thymosin Beta4 induces adult epicardial progenitor mobilization and neovascularization.” Nature, 445, 177-182.


Sublingual compositions comprising Thymosin fraction 5 and methods for administration

Retrieved 3/1/2007

http://www.pharmcast.com/Patents100/Yr2004/May2004/051104/6733791_Sublingual051104.htm


TMSB4X  Thymosin, beta 4, X-linked

Retrieved on 3/1/2007

http://www.ihop-net.org/UniPub/iHOP/gs/92756.html

Waeckel, L., Jérôme Bignon, J., Jian-Miao Liu, J-M., Markovits, D., Ebrahimian, T.G., Vilar, J., Mees, B., Blanc-Brude, O., Barateau, V., Sophie Le ricousse-Roussanne. S., Duriez, M. Tobelem, G.,  Wdzieczak-Bakala, J., Bernard I Lévy, B.I., Silvestre, J-S. (2006) “Tetrapeptide AcSDKP Induces Postischemic Neovascularization Through Monocyte Chemoattractant Protein-1 Signaling.” Arteriosclerosis, Thrombosis, and Vascular Biology, 26, 773

Wang, D., Oscar A. Carretero, O.A.,Yang, X-Y., Rhaleb, N-E., Liu, Y-H., Liao, T-D., Yang, X-P. (2004). “N-acetyl-seryl-aspartyl-lysyl-proline stimulates angiogenesis in vitro and in vivo.” Am J Physiol Heart Circ Physiol., 287, H2099-H2105.

Werner N, Junk S, Laufs L, Link A, Walenta K, Bohm M, Nickenig G., (2003).  Intravenous transfusion of endothelial progenitor cells reduces neointima formation after vascular injury. Circ Res., 93, e17– e24.

Werner N, Kosiol S, Schiegl T, Ahlers P, Walenta K, Link A, Böhm M, Nickenig G. (2005a). Circulating Endothelial Progenitor Cells and Cardiovascular Outcomes, NEJM, 353, 999-1007

Werner, N. & Nickenig, G. (2005b). Authors Reply to Correspondence to the Editor on Circulating Endothelial Progenitor Cells. NEJM, 353 (24), 2613-2616

Wu, S.M., Fujiwara, Y., Cibulsky, S.M., Clapham, D.E., Lien, C., Schultheiss, T.M., Orkin, S.H. (2006, December). “Developmental Origin of a Bipotential Myocardial and Smooth Muscle Cell Precursor in the Mammalian Heart.” Cell, 127, 1137-1150.

Other related articles on this Open Access Online Scientific Journal, include the following:

Saha, S. (2012b) Innovations in Bio instrumentation for Measurement of Circulating Progenetor Endothelial Cells in Human Blood.
http://pharmaceuticalintelligence.com/2012/07/08/innovations-in-bio-instrumentation-for-measurement-of-circulating-progenitor-endothelial-cells-in-human-blood/


Saha, S. (2012c) Endothelial Differentiation and Morphogenesis of Cardiac Precursor
http://pharmaceuticalintelligence.com/2012/07/17/endothelial-differentiation-and-morphogenesis-of-cardiac-precursors/

Saha, S. (2012e). Human Embryonic-Derived Cardiac Progenitor Cells for Myocardial Repair

http://pharmaceuticalintelligence.com/2012/08/01/human-embryonic-derived-cardiac-progenitor-cells-for-myocardial-repair/

Lev-Ari, A. 12/29/2012. Coronary artery disease in symptomatic patients referred for coronary angiography: Predicted by Serum Protein Profiles

http://pharmaceuticalintelligence.com/2012/12/29/coronary-artery-disease-in-symptomatic-patients-referred-for-coronary-angiography-predicted-by-serum-protein-profiles/


Bernstein, HL and Lev-Ari, A. 11/28/2012. Special Considerations in Blood Lipoproteins, Viscosity, Assessment and Treatment

http://pharmaceuticalintelligence.com/2012/11/28/special-considerations-in-blood-lipoproteins-viscosity-assessment-and-treatment/


Lev-Ari, A. 11/13/2012 Peroxisome proliferator-activated receptor (PPAR-gamma) Receptors Activation: PPARγ transrepression for Angiogenesis in Cardiovascular Disease and PPARγ transactivation for Treatment of Diabetes

http://pharmaceuticalintelligence.com/2012/11/13/peroxisome-proliferator-activated-receptor-ppar-gamma-receptors-activation-pparγ-transrepression-for-angiogenesis-in-cardiovascular-disease-and-pparγ-transactivation-for-treatment-of-dia/


Lev-Ari, A. 10/19/2012 Clinical Trials Results for Endothelin System: Pathophysiological role in Chronic Heart Failure, Acute Coronary Syndromes and MI – Marker of Disease Severity or Genetic Determination?

http://pharmaceuticalintelligence.com/2012/10/19/clinical-trials-results-for-endothelin-system-pathophysiological-role-in-chronic-heart-failure-acute-coronary-syndromes-and-mi-marker-of-disease-severity-or-genetic-determination/


Lev-Ari, A. 10/4/2012 Endothelin Receptors in Cardiovascular Diseases: The Role of eNOS Stimulation

http://pharmaceuticalintelligence.com/2012/10/04/endothelin-receptors-in-cardiovascular-diseases-the-role-of-enos-stimulation/


Lev-Ari, A. 10/4/2012 Inhibition of ET-1, ETA and ETA-ETB, Induction of NO production, stimulation of eNOS and Treatment Regime with PPAR-gamma agonists (TZD): cEPCs Endogenous Augmentation for Cardiovascular Risk Reduction – A Bibliography

http://pharmaceuticalintelligence.com/2012/10/04/inhibition-of-et-1-eta-and-eta-etb-induction-of-no-production-and-stimulation-of-enos-and-treatment-regime-with-ppar-gamma-agonists-tzd-cepcs-endogenous-augmentation-for-cardiovascular-risk-reduc/


Lev-Ari, A. 8/28/2012 Cardiovascular Outcomes: Function of circulating Endothelial Progenitor Cells (cEPCs): Exploring Pharmaco-therapy targeted at Endogenous Augmentation of cEPCs

http://pharmaceuticalintelligence.com/2012/08/28/cardiovascular-outcomes-function-of-circulating-endothelial-progenitor-cells-cepcs-exploring-pharmaco-therapy-targeted-at-endogenous-augmentation-of-cepcs/


Lev-Ari, A. 8/27/2012 Endothelial Dysfunction, Diminished Availability of cEPCs, Increasing CVD Risk for Macrovascular Disease – Therapeutic Potential of cEPCs

http://pharmaceuticalintelligence.com/2012/08/27/endothelial-dysfunction-diminished-availability-of-cepcs-increasing-cvd-risk-for-macrovascular-disease-therapeutic-potential-of-cepcs/


Lev-Ari, A. 8/24/2012 Vascular Medicine and Biology: CLASSIFICATION OF FAST ACTING THERAPY FOR PATIENTS AT HIGH RISK FOR MACROVASCULAR EVENTS Macrovascular Disease – Therapeutic Potential of cEPCs

http://pharmaceuticalintelligence.com/2012/08/24/vascular-medicine-and-biology-classification-of-fast-acting-therapy-for-patients-at-high-risk-for-macrovascular-events-macrovascular-disease-therapeutic-potential-of-cepcs/


Lev-Ari, A. 7/30/2012 Biosimilars: Intellectual Property Creation and Protection by Pioneer and by Biosimilar Manufacturers

http://pharmaceuticalintelligence.com/2012/07/30/biosimilars-intellectual-property-creation-and-protection-by-pioneer-and-by-biosimilar-manufacturers/


Lev-Ari, A. 7/29/2012 Biosimilars: Financials 2012 vs. 2008

http://pharmaceuticalintelligence.com/2012/07/30/biosimilars-financials-2012-vs-2008/


Lev-Ari, A. 7/29/2012 Biosimilars: CMC Issues and Regulatory Requirements

http://pharmaceuticalintelligence.com/2012/07/29/biosimilars-cmc-issues-and-regulatory-requirements/


Lev-Ari, A. 7/19/2012 Cardiovascular Disease (CVD) and the Role of agent alternatives in endothelial Nitric Oxide Synthase (eNOS) Activation and Nitric Oxide Production

http://pharmaceuticalintelligence.com/2012/07/19/cardiovascular-disease-cvd-and-the-role-of-agent-alternatives-in-endothelial-nitric-oxide-synthase-enos-activation-and-nitric-oxide-production/


Lev-Ari, A. 4/30/2012 Resident-cell-based Therapy in Human Ischaemic Heart Disease: Evolution in the PROMISE of Thymosin beta4 for Cardiac Repair

http://pharmaceuticalintelligence.com/2012/04/30/93/

Lev-Ari, A. 5/29/2012 Triple Antihypertensive Combination Therapy Significantly Lowers Blood Pressure in Hard-to-Treat Patients with Hypertension and Diabetes

http://pharmaceuticalintelligence.com/2012/05/29/445/


Lev-Ari, A. 7/2/2012 Macrovascular Disease – Therapeutic Potential of cEPCs: Reduction Methods for CV Risk

http://pharmaceuticalintelligence.com/2012/07/02/macrovascular-disease-therapeutic-potential-of-cepcs-reduction-methods-for-cv-risk/


Lev-Ari, A. 7/9/2012 Mitochondria Dysfunction and Cardiovascular Disease – Mitochondria: More than just the “powerhouse of the cell”

http://pharmaceuticalintelligence.com/2012/07/09/mitochondria-more-than-just-the-powerhouse-of-the-cell/


Lev-Ari, A. 7/16/2012 Bystolic’s generic Nebivolol – positive effect on circulating Endothelial Proginetor Cells endogenous augmentation

http://pharmaceuticalintelligence.com/2012/07/16/bystolics-generic-nebivolol-positive-effect-on-circulating-endothilial-progrnetor-cells-endogenous-augmentation/

Read Full Post »

« Newer Posts - Older Posts »