Feeds:
Posts
Comments

Posts Tagged ‘nitric oxide’

Curator/Reporter Aviral Vatsa PhD, MBBS

Based on: A review by (Wink et al., 2011)

This post is in continuation to Part 1 by the same title.

In part one I covered the basics of role of redox chemistry in immune reactions, the phagosome cauldron, and how bacteria bacteria, virus and parasites trigger the complex pathway of NO production and its downstream effects. While we move further in this post, the previous post can be accessed here.

REDOX REGULATION OF IMMUNE FUNCTION

Regulation of the redox immunomodulators—NO/RNS and ROS

In addition to eradicating pathogens, NO/RNS and ROS and their chemical interactions act as effective immunomodulators that regulate many cellular metabolic pathways and tissue repair and proinflammatory pathways. Figure 3 shows these pathways.

Figure 3. Schematic overview of interactive connections between NO and ROS-mediated metabolic pathways. Credit: (Wink et al., 2011)

Regulation of iNOS enzyme activity is critical to NO production. Factors such as the availability of arginine, BH4, NADPH, and superoxide affect iNOS activity and thus NO production. In the absence of arginine and BH4 iNOS becomes a O2_/H2O2 generator (Vásquez-Vivar et al., 1999). Hence metabolic pathways that control arginine and BH4 play a role in determining the NO/superoxide balance. Arginine levels in cells depend on various factors such as type of uptake mechanisms that determine its spatial presence in various compartments and enzymatic systems. As shown in Fig3 Arginine is the sole substrate for iNOS and arginase. Arginase is another key enzyme in immunemodulation. AG is also regulated by NOS and NOX activities. NOHA, a product of NOS, inhibits AG, and O2–increases AG activity. Importantly, high AG activity is associated with elevated ROS and low NO fluxes. NO antagonises NOX2 assembly that in turn leads to reduction in O2_ production. NO also inhibits COX2 activity thus reducing ROS production. Thus, as NO levels decline, oxidative mechanisms increase. Oxidative and nitrosative stress can also decrease intracellular GSH (reduced form) levels, resulting in a reduced antioxidant capability of the cell.

Immune-associated redox pathways regulate other important metabolic cell functions that have the potential for widespread impact on cells, organs, and organisms. These pathways, such as mediated via methionine and polyamines, are critical for DNA stabilization, cell proliferation, and membrane channel activity, all of which are also involved in immune-mediated repair processes.

NO levels dictate the immune signaling pathway

NO/RNS and ROS actively control innate and adaptive immune signaling by participating in induction, maintenance, and/or termination of proinflammatory and anti-inflammatory signaling. As in pathogen eradication, the temporal and spatial concentration profiles of NO are key factors in determining immune-mediated processes.

Brune and coworkers (Messmer et al., 1994) first demonstrated that p53 expression was associated with the concentrations of NO that led to apoptosis in macrophages. Subsequent studies linked NO concentration profiles with expression of other key signaling proteins such as HIF-1α and Akt-P (Ridnour et al., 2008; Thomas et al., 2008). Various levels of NO concentrations trigger different pathways and expectedly this concentration-dependent profile varies with distance from the NO source.NO is highly diffucible and this characteristic can result in 1000 fold reduction in concentration within one cell length distance travelled from the source of production. Time course studies have also shown alteration in effects of same levels of NO over time e.g. NO-mediated ERK-P levels initially increased rapidly on exposure to NO donors and then decreased with continued NO exposure (Thomas et al., 2004), however HIF-1α levels remained high as long as NO levels were elevated. Thus some of the important factors that play critical role in NO effects are: distance from source, NO concentrations, duration of exposure, bioavailability of NO, and production/absence of other redox molecules.

Figure and legend credits: (Wink et al., 2011)

Fig 4: The effect of steady-state flux of NO on signal transduction mechanisms.

This diagram represents the level of sustained NO that is required to activate specific pathways in tumor cells. Similar effects have been seen on endothelial cells. These data were generated by treating tumor or endothelial cells with the NO donor DETANO (NOC-18) for 24 h and then measuring the appropriate outcome measures (for example, p53 activation). Various concentrations of DETANO that correspond to cellular levels of NO are: 40–60 μM DETANO = 50 nM NO; 80–120 μM DETANO = 100 nM NO; 500 μM DETANO = 400 nM NO; and 1 mM DETANO = 1 μM NO. The diagram represents the effect of diffusion of NO with distance from the point source (an activated murine macrophage producing iNOS) in vitro (Petri dish) generating 1 μM NO or more. Thus, reactants or cells located at a specific distance from the point source (i.e., iNOS, represented by star) would be exposed to a level of NO that governs a specific subset of physiological or pathophysiological reactions. The x-axis represents the different zone of NO-mediated events that is experienced at a specific distance from a source iNOS producing >1 μM. Note: Akt activation is regulated by NO at two different sites and by two different concentration levels of NO.

Species-specific NO production

The relationship of NO and immunoregulation has been established on the basis of studies on tumor cell lines or rodent macrophages, which are readily available sources of NO. However in humans the levels of protein expression for NOS enzymes and the immune induction required for such levels of expression are quite different than in rodents (Weinberg, 1998). This difference is most likely due to the human iNOS promotor rather than the activity of iNOS itself. There is a significant mismatch between the promoters of humans and rodents and that is likely to account for the notable differences in the regulation of gene induction between them. The combined data on rodent versus human NO and O2– production strongly suggest that in general, ROS production is a predominant feature of activated human macrophages, neutrophils, and monocytes, and the equivalent murine immune cells generate a combination of O2– and NO and in some cases, favor NO production. These differences may be crucial to understanding how immune responses are regulated in a species-specific manner. This is particularly useful, as pathogen challenges change constantly.

The next post in this series will cover the following topics:

The impact of NO signaling on an innate immune response—classical activation

NO and proinflammatory genes

NO and regulation of anti-inflammatory pathways

NO impact on adaptive immunity—immunosuppression and tissue-restoration response

NO and revascularization

Acute versus chronic inflammatory disease

Bibliography

1. Wink, D. A. et al. Nitric oxide and redox mechanisms in the immune response. J Leukoc Biol 89, 873–891 (2011).

2. Vásquez-Vivar, J. et al. Tetrahydrobiopterin-dependent inhibition of superoxide generation from neuronal nitric oxide synthase. J. Biol. Chem. 274, 26736–26742 (1999).

3. Messmer, U. K., Ankarcrona, M., Nicotera, P. & Brüne, B. p53 expression in nitric oxide-induced apoptosis. FEBS Lett. 355, 23–26 (1994).

4. Ridnour, L. A. et al. Molecular mechanisms for discrete nitric oxide levels in cancer. Nitric Oxide 19, 73–76 (2008).

5. Thomas, D. D. et al. The chemical biology of nitric oxide: implications in cellular signaling. Free Radic. Biol. Med. 45, 18–31 (2008).

6. Thomas, D. D. et al. Hypoxic inducible factor 1alpha, extracellular signal-regulated kinase, and p53 are regulated by distinct threshold concentrations of nitric oxide. Proc. Natl. Acad. Sci. U.S.A. 101, 8894–8899 (2004).

7. Weinberg, J. B. Nitric oxide production and nitric oxide synthase type 2 expression by human mononuclear phagocytes: a review. Mol. Med. 4, 557–591 (1998).

Further reading on NO:

Nitric Oxide in bone metabolism July 16, 2012

Author: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/07/16/nitric-oxide-in-bone-metabolism/?goback=%2Egde_4346921_member_134751669

Nitric Oxide production in Systemic sclerosis July 25, 2012

Curator: Aviral Vatsa, PhD, MBBS

http://pharmaceuticalintelligence.com/2012/07/25/nitric-oxide-production-in-systemic-sclerosis/?goback=%2Egde_4346921_member_138370383

Nitric Oxide Signalling Pathways August 22, 2012 by

Curator/ Author: Aviral Vatsa, PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/22/nitric-oxide-signalling-pathways/?goback=%2Egde_4346921_member_151245569

Nitric Oxide: a short historic perspective August 5, 2012

Author/Curator: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/05/nitric-oxide-a-short-historic-perspective-7/

Nitric Oxide: Chemistry and function August 10, 2012

Curator/Author: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/10/nitric-oxide-chemistry-and-function/?goback=%2Egde_4346921_member_145137865

Nitric Oxide and Platelet Aggregation August 16, 2012 by

Author: Dr. Venkat S. Karra, Ph.D.

http://pharmaceuticalintelligence.com/2012/08/16/no-and-platelet-aggregation/?goback=%2Egde_4346921_member_147475405

The rationale and use of inhaled NO in Pulmonary Artery Hypertension and Right Sided Heart Failure August 20, 2012

Author: Larry Bernstein, MD

http://pharmaceuticalintelligence.com/2012/08/20/the-rationale-and-use-of-inhaled-no-in-pulmonary-artery-hypertension-and-right-sided-heart-failure/

Nitric Oxide: The Nobel Prize in Physiology or Medicine 1998 Robert F. Furchgott, Louis J. Ignarro, Ferid Murad August 16, 2012

Reporter: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/08/16/nitric-oxide-the-nobel-prize-in-physiology-or-medicine-1998-robert-f-furchgott-louis-j-ignarro-ferid-murad/

Coronary Artery Disease – Medical Devices Solutions: From First-In-Man Stent Implantation, via Medical Ethical Dilemmas to Drug Eluting Stents August 13, 2012

Author: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/08/13/coronary-artery-disease-medical-devices-solutions-from-first-in-man-stent-implantation-via-medical-ethical-dilemmas-to-drug-eluting-stents/

Nano-particles as Synthetic Platelets to Stop Internal Bleeding Resulting from Trauma

August 22, 2012

Reported by: Dr. V. S. Karra, Ph.D.

http://pharmaceuticalintelligence.com/2012/08/22/nano-particles-as-synthetic-platelets-to-stop-internal-bleeding-resulting-from-trauma/

Cardiovascular Disease (CVD) and the Role of agent alternatives in endothelial Nitric Oxide Synthase (eNOS) Activation and Nitric Oxide Production July 19, 2012

Curator and Research Study Originator: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/07/19/cardiovascular-disease-cvd-and-the-role-of-agent-alternatives-in-endothelial-nitric-oxide-synthase-enos-activation-and-nitric-oxide-production/

Macrovascular Disease – Therapeutic Potential of cEPCs: Reduction Methods for CV Risk

July 2, 2012

An Investigation of the Potential of circulating Endothelial Progenitor Cells (cEPCs) as a Therapeutic Target for Pharmacological Therapy Design for Cardiovascular Risk Reduction: A New Multimarker Biomarker Discovery

Curator: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/07/02/macrovascular-disease-therapeutic-potential-of-cepcs-reduction-methods-for-cv-risk/

Bone remodelling in a nutshell June 22, 2012

Author: Aviral Vatsa, Ph.D., MBBS

http://pharmaceuticalintelligence.com/2012/06/22/bone-remodelling-in-a-nutshell/

Targeted delivery of therapeutics to bone and connective tissues: current status and challenges- Part, September  

Author: Aviral Vatsa, PhD, September 23, 2012

http://pharmaceuticalintelligence.com/2012/09/23/targeted-delivery-of-therapeutics-to-bone-and-connective-tissues-current-status-and-challenges-part-i/

Calcium dependent NOS induction by sex hormones: Estrogen

Curator: S. Saha, PhD, October 3, 2012

http://pharmaceuticalintelligence.com/2012/10/03/calcium-dependent-nos-induction-by-sex-hormones/

Nitric Oxide and Platelet Aggregation,

Author V. Karra, PhD, August 16, 2012

http://pharmaceuticalintelligence.com/2012/08/16/no-and-platelet-aggregation/

Bystolic’s generic Nebivolol – positive effect on circulating Endothelial Progenitor Cells endogenous augmentation

Curator: Aviva Lev-Ari, PhD, July 16, 2012

http://pharmaceuticalintelligence.com/?s=Nebivolol

Endothelin Receptors in Cardiovascular Diseases: The Role of eNOS Stimulation

Author: Aviva Lev-Ari, PhD, 10/4/2012

http://pharmaceuticalintelligence.com/2012/10/04/endothelin-receptors-in-cardiovascular-diseases-the-role-of-enos-stimulation/

Inhibition of ET-1, ETA and ETA-ETB, Induction of NO production, stimulation of eNOS and Treatment Regime with PPAR-gamma agonists (TZD): cEPCs Endogenous Augmentation for Cardiovascular Risk Reduction – A Bibliography

Curator: Aviva Lev-Ari, 10/4/2012.

http://pharmaceuticalintelligence.com/2012/10/04/inhibition-of-et-1-eta-and-eta-etb-induction-of-no-production-and-stimulation-of-enos-and-treatment-regime-with-ppar-gamma-agonists-tzd-cepcs-endogenous-augmentation-for-cardiovascular-risk-reduc/

Nitric Oxide Nutritional remedies for hypertension and atherosclerosis. It’s 12 am: do you know where your electrons are?

Author and Reporter: Meg Baker, 10/7/2012.

http://pharmaceuticalintelligence.com/2012/10/07/no-nutritional-remedies-for-hypertension-and-atherosclerosis-its-12-am-do-you-know-where-your-electrons-are/

Read Full Post »

Endothelial Function and Cardiovascular Disease

Pathologist and Author: Larry H Bernstein, MD, FCAP 


This discussion is a continuation of a series on Nitric Oxide, vascular relaxation, vascular integrity, and systemic organ dysfunctions related to inflammatory and circulatory disorders. In some of these, the relationships are more clear than others, and in other cases the vascular disorders are aligned with serious metabolic disturbances. This article, in particular centers on the regulation of NO production, NO synthase, and elaborates more on the assymetrical dimethylarginine (ADMA) inhibition brought up in a previous comment, and cardiovascular disease, including:

Recall, though, that in SIRS leading to septic shock, that there is a difference between the pulmonary circulation, the systemic circulation and the portal circulation in these events. The comment calls attention to:
Böger RH. Asymmetric dimethylarginine, an endogenous inhibitor of nitric oxide synthase, explains the ‘L-arginine paradox’ and acts as a novel cardiovascular risk factor. J Nutr 2004; 134: 2842S–7S.

This observer points out that ADMA inhibits vascular NO production at concentrations found in pathophysiological conditions (i.e., 3–15 μmol/l); ADMA also causes local vasoconstriction when it is infused intra-arterially. ADMA is increased in the plasma of humans with hypercholesterolemia, atherosclerosis, hypertension, chronic renal failure, and chronic heart failure.

Increased ADMA levels are associated with reduced NO synthesis as assessed by impaired endothelium-dependent vasodilation. We’ll go into that more with respect to therapeutic targets – including exercise, sauna, and possibly diet, as well as medical drugs.

It is remarkable how far we have come since the epic discovery of 17th century physician, William Harvey, by observing the action of the heart in small animals and fishes, proved that heart receives and expels blood during each cycle, and argued for the circulation in man. This was a huge lead into renaissance medicine. What would he think now?

Key Words: eNOS, NO, endothelin, ROS, oxidative stress, blood flow, vascular resistance, cardiovascular disease, chronic renal disease, hypertension, diabetes, atherosclerosis, MI, exercise, nutrition, traditional chinese medicine, statistical modeling for targeted therapy.

Endothelial Function
The endothelium plays a crucial role in the maintenance of vascular tone and structure by means of eNOS, producing the endothelium-derived vasoactive mediator nitric oxide (NO), an endogenous messenger molecule formed in healthy vascular endothelium from the amino acid precursor L-arginine. Nitric oxide synthases (NOS) are the enzymes responsible for nitric oxide (NO) generation. The generation and actions of NO under physiological and pathophysiological conditions are exquisitely regulated and extend to almost every cell type and function within the circulation. While the molecule mediates many physiological functions, an excessive presence of NO is toxic to cells.

The enzyme NOS, constitutively or inductively, catalyses the production of NO in several biological systems. NO is derived not only from NOS isoforms but also from NOS-independent sources. In mammals, to date, three distinct NOS isoforms have been identified:

  1. neuronal NOS (nNOS),
  2. inducible NOS (iNOS), and
  3. endothelial NOS (eNOS).

The molecular structure, enzymology and pharmacology of these enzymes have been well defined, and reveal critical roles for the NOS system in a variety of important physiological processes. The role of NO and NOS in regulating vascular physiology, through neuro-hormonal, renal and other non-vascular pathways, as well as direct effects on arterial smooth muscle, appear to be more intricate than was originally thought.

Vallance et al. described the presence of asymmetric dimethylarginine (ADMA) as an endogenous inhibitor of eNOS in 1992. Since then, the role of this molecule in the regulation of eNOS has attracted increasing attention.
Endothelins are 21-amino acid peptides, which are active in almost all tissues in the body. They are potent vasoconstrictors, mediators of cardiac, renal, endocrine and immune functions and play a role in bronchoconstriction, neurotransmitter regulation, activation of inflammatory cells, cell proliferation and differentiation.

Endothelins were first characterised by Yanagisawa et al. (1988). The three known endothelins ET-1, -2 and -3 are structurally similar to sarafotoxins from snake venoms. ET-1 is the major isoform generated in blood vessels and appears to be the isoform of most importance in the cardiovascular system with a major role in the maintenance of vascular tone.

The systemic vascular response to hypoxia is vasodilation. However, reports suggest that the potent vasoconstrictor endothelin-1 (ET-1) is released from the vasculature during hypoxia. ET-1 is reported to augment superoxide anion generation and may counteract nitric oxide (NO) vasodilation. Moreover, ET-1 was proposed to contribute to increased vascular resistance in heart failure by increasing the production of asymmetric dimethylarginine (ADMA).

A study investigated the role of ET-1, the NO pathway, the potassium channels and radical oxygen species in hypoxia-induced vasodilation of large coronary arteries and found NO contributes to hypoxic vasodilation, probably through K channel opening, which is reversed by addition of ET-1 and enhanced by endothelin receptor antagonism. These latter findings suggest that endothelin receptor activation counteracts hypoxic vasodilation.

Endothelial dysfunction
Patients with Raynaud’s Phemonenon had abnormal vasoconstrictor responses to cold pressor tests (CPT) that were similar in primary and secondary RP. There were no differences in median flow-mediated and nitroglycerin mediated dilation or CPT of the brachial artery in the 2 populations. Patients with secondary RP were characterized by abnormalities in microvascular responses to reactive hyperemia, with a reduction in area under the curve adjusted for baseline perfusion, but not in time to peak response or peak perfusion ratio.

Plasma ET-1, ADMA, VCAM-1, and MCP-1 levels were significantly elevated in secondary RP compared with primary RP. There was a significant negative correlation between ET-1 and ADMA values and measures of microvascular perfusion but not macrovascular endothelial function. Secondary RP is characterized by elevations in plasma ET-1 and ADMA levels that may contribute to alterations in cutaneous microvascular function.

ADMA inhibits vascular NO production within the concentration range found in patients with vascular disease. ADMA also causes local vasoconstriction when infused intra-arterially, and increases systemic vascular resistance and impairs renal function when infused systemically. Several recent studies have supplied evidence to support a pathophysiological role of ADMA in the pathogenesis of vascular dysfunction and cardiovascular disease. High ADMA levels were found to be associated with carotid artery intima-media-thickness in a study with 116 clinically healthy human subjects. Taking this observation further, another study performed with hemodialysis patients reported that ADMA prospectively predicted the progression of intimal thickening during one year of follow-up.

In a nested, case-control study involving 150 middle-aged, non-smoking men, high ADMA levels were associated with a 3.9-fold elevated risk for acute coronary events. Clinical and experimental evidence suggests elevation of ADMA can cause a relative L-arginine deficiency, even in the presence of “normal” L-arginine levels. As ADMA is a competitive inhibitor of eNOS, its inhibitory action can be overcome by increasing the concentration of the substrate, L-arginine. Elevated ADMA concentration is one possible explanation for endothelial dysfunction and decreased NO production in these diseases.
Metabolic Regulation of L-arginine and NO Synthesis 
Methylation of arginine residues within proteins or polypeptides occurs through N-methyltransferases, which utilize S-adenosylmethionine as a methyl donor. After proteolysis of these proteins or polypeptides, free ADMA is present in the cytoplasm. ADMA can also be detected in circulating blood plasma. ADMA acts as an inhibitor of eNOS by competing with the substrate of this enzyme, L-arginine. The ensuing reduction in nitric oxide synthesis causes vascular endothelial dysfunction and, subsequently, atherosclerosis. ADMA is eliminated from the body via urinary excretion and via metabolism by the enzyme DDAH to citrulline and dimethylamine.
Supplementation with L-arginine in animals with experimentally-induced vascular dysfunction atherosclerosis improves endothelium-dependent vasodilation. Moreover, L-arginine supplementation results in enhanced endothelium-dependent inhibition of platelet aggregation, inhibition of monocyte adhesion, and reduced vascular smooth muscle proliferation. One mechanism that explains the occurrence of endothelial dysfunction is the presence of elevated blood levels of asymmetric dimethylarginine (ADMA) – an L-arginine analogue that inhibits NO formation and thereby can impair vascular function. Supplementation with L-arginine has been shown to restore vascular function and to improve the clinical symptoms of various diseases associated with vascular dysfunction.

Beneficial Effects of L-Arginine

  • Angina
  • Congestive Heart Failure
  • Hypertension
  • Erectile dysfunction
  • Sickle Cell Disease and Pulmonary Hypertension

The ratio of L-arginine to ADMA is considered to be the most accurate measure of eNOS substrate availability. This ratio will increase during L-arginine supplementation, regardless of initial ADMA concentration. Due to the pharmacokinetics of oral L-arginine and the positive results from preliminary studies, it appears supplementation with a sustained-release L-arginine preparation will achieve positive therapeutic results at lower dosing levels.

Many prospective clinical trials have shown that the association between elevated ADMA levels and major cardiovascular events and total mortality is robust and extends to diverse patient populations. However, we need to define more clearly in the future who will profit from ADMA determination, in order to use this novel risk marker as a more specific diagnostic tool.
Elimination of ADMA by way of DDAH
Asymmetric dimethylarginine (ADMA) and monomethyl arginine (L-NMMA) are endogenously produced amino acids that inhibit all three isoforms of nitric oxide synthase (NOS). ADMA accumulates in various disease states, including renal failure, diabetes and pulmonary hypertension, and its concentration in plasma is strongly predictive of premature cardiovascular disease and death. Both LNMMA and ADMA are eliminated largely through active metabolism by dimethylarginine dimethylaminohydrolase (DDAH) and thus DDAH dysfunction may be a crucial unifying feature of increased cardiovascular risk. These investigators ask whether ADMA is the underlying issue related to the pathogenesis of the vascular disorder.
They identified the structure of human DDAH-1 and probed the function of DDAH-1 both by deleting the Ddah1 gene in mice and by using DDAH-specific inhibitors that is shown by crystallography, bind to the active site of human DDAH-1. The loss of DDAH-1 activity leads to accumulation of ADMA and reduction in NO signaling. This in turn causes vascular pathophysiology, including endothelial dysfunction, increased systemic vascular resistance and elevated systemic and pulmonary blood pressure. The results suggest that DDAH inhibition could be harnessed therapeutically to reduce the vascular collapse associated with sepsis.
Methylarginines are formed when arginine residues in proteins are methylated by the action of protein arginine methyltransferases (PRMTs), and free methylarginines are liberated following proteolysis. Clear demonstration of an effect of endogenous ADMA and L-NMMA on cardiovascular physiology would be of importance, not only because of the implications for disease, but also because it would expose a link between post-translational modification of proteins and signaling through a proteolytic product of these modified proteins.
Which is it? ADMA or DDHA: Intrusion of a Genetic alteration.
The study showed that loss of DDAH expression or activity causes endothelial dysfunction, we believe that DDAH inhibition could potentially be used therapeutically to limit excessive NO production, which can have pathological effects. They then showed treated cultured isolated blood vessels with lipopolysaccharide (LPS) induced expression of the inducible isoform of NO synthase (iNOS) and generated high levels of NO, which were blocked by the iNOS-selective inhibitor 1400W and by DDAH inhibitors. Treatment of isolated blood vessels with DDAH inhibitors significantly increased ADMA accumulation in the culture medium. Treatment of isolated blood vessels with bacterial LPS led to the expected hyporeactivity to the contractile effects of phenylephrine, which was reversed by treatment with a DDAH inhibitor. The effect of the DDAH inhibitor was large and stereospecific, and was reversed by the addition of L-arginine.
In conclusion, genetic and chemical-biology approaches provide compelling evidence that loss of DDAH-1 function results in increased ADMA concentrations and thereby disrupts vascular NO signaling. A broader implication of this study is that post-translational methylation of arginine residues in proteins may have downstream effects by affecting NO signaling upon hydrolysis and release of the free methylated amino acid. This signaling pathway seems to have been highly conserved through evolution.

The crucial role of nitric oxide (NO) for normal endothelial function is well known. In many conditions associated with increased risk of cardiovascular diseases such as hypercholesterolemia, hypertension, abdominal obesity, diabetes and smoking, NO biosynthesis is dysregulated, leading to endothelial dysfunction. The growing evidence from animal and human studies indicates that endogenous inhibitors of endothelial NO synthase such as asymmetric dimethylarginine (ADMA) and NG-monomethyl-L-arginine (L-NMMA) are associated with the endothelial dysfunction and potentially regulate NO synthase.

Nitric Oxide Synthase

Asymmetric dimethylarginine (ADMA) is one of three known endogenously produced circulating methylarginines (i.e. ADMA, NG-monomethyl-L-arginine (L-NMMA) and symmetrically methylated NG, NG-dimethyl-L-arginine). ADMA is formed by the action of protein arginine methyltransferases that methylate arginine residues in proteins and after which free ADMA is released. ADMA and L-NMMA can competitively inhibit NO elaboration by displacing L-arginine from NO synthase (NOS). The amount of methylarginines is related to overall metabolic activity and the protein turnover rate of cells. Although methylarginines are excreted partly by the kidneys, the major route of elimination of ADMA in humans is metabolism by the dimethylarginine dimethylaminohydrolase enzymes[ dimethylarginine dimethylaminohydrolase-1 and -2 (DDAH)] enzymes. Inhibition of DDAH leads to the accumulation of ADMA and consequently to inhibition of NO-mediated endothelium dependent relaxation of blood vessels.
The potential role of ADMA in angina pectoris has been evaluated by Piatti and co-workers, who reported ADMA levels to be higher in patients with cardiac syndrome X (angina pectoris with normal coronary arteriograms) than in controls. According to preliminary results from the CARDIAC (Coronary Artery Risk Determination investigating the influence of ADMA Concentration) study, patients with coronary heart disease (n 816) had a higher median ADMA plasma concentration than age and sex matched controls (median 0.91 vs. 0.70 mol/l; p 0.0001). Further, in a prospective Chinese study, a high plasma ADMA level independently predicted subsequent cardiovascular adverse events (cardiovascular death, myocardial infarction, and repeated revascularization of a target vessel).

Protein detoxification pathway.

Protein detoxification pathway. (Photo credit: Wikipedia)

There are only few published findings concerning variations in human DDAH. However, polymorphisms in other genes potentially related to risk factors for endothelial dysfunction and cardiovascular events have been studied. Reduced NO synthesis has been implicated in the development of atherosclerosis. For example, there are some functionally important variants of the NOS that could affect individual vulnerability to atherosclerosis by changing the amount of NO generated by the endothelium.
There are probably several functional variations in genes coding DDAH enzymes in different populations. Some of them could confer protection against the harmful effects of elevated ADMA and others impair enzyme function causing accumulation of ADMA in cytosol and/or blood.
In a study of 16 men with either low or high plasma ADMA concentrations were screened to identify DDAH polymorphisms that could potentially be associated with increased susceptibility to cardiovascular diseases. In that study a novel functional mutation of DDAH-1 was identified; the mutation carriers had a significantly elevated risk for cardiovascular disease and a tendency to develop hypertension. These results confirmed the clinical role of DDAH enzymes in ADMA metabolism. Furthermore, it is possible that more common variants of DDAH genes contribute more widely to increased cardiovascular risk.
We found a rare variation in the DDAH-1 gene, which is associated with elevated plasma concentrations of ADMA in heterozygous mutation carriers. There was also an increased prevalence of CHD and a tendency to hypertension among individuals with this DDAH-1 mutation. These observations highlight the importance of ADMA as a possible risk factor and emphasize the essential role of DDAH in regulating ADMA levels.

ADMA Elevation and Coronary Artery Disease
Endothelial dysfunction may be considered as a systemic disorder and involves different vascular beds. Coronary endothelial dysfunction (CED) precedes the development of coronary. Endothelial dysfunction is characterized by a reduction in endogenous nitric oxide (NO) activity, which may be accompanied by elevated plasma asymmetric dimethylarginine (ADMA) levels. ADMA is a novel endogenous competitive inhibitor of NO synthase (NOS), an independent marker for cardiovascular risk.
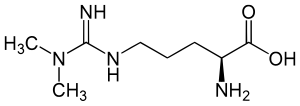
English: Structure of asymmetric dimethylargin...

English: Structure of asymmetric dimethylarginine; ADMA; N,N-Dimethylarginine Deutsch: Asymmetrisches Dimethylarginin; N,N-Dimethyl-L-arginin; Guanidin-N,N-dimethylarginin (Photo credit: Wikipedia)

In a small study fifty-six men without obstructive coronary artery disease (CAD) who underwent coronary endothelial function testing were studied. Men with CED had significant impairment of erectile function (P ¼ 0.008) and significantly higher ADMA levels (0.50+0.06 vs. 0.45+0.07 ng/mL, P ¼ 0.017) compared with men with normal endothelial function. Erectile function positively correlated with coronary endothelial function. This correlation was independent of age, body mass index, high-density lipoprotein, C-reactive protein, homeostasis model assessment of insulin resistance index, and smoking status, suggesting that CED is independently associated with ED and plasma ADMA concentration in men with early coronary atherosclerosis.

ADMA and Chronic Renal Failure in Hepatorenal Syndrome
The concentration of SDMA was significantly higher in the patients with HRS compared to the patients without HRS and it was also higher than the values obtained from the healthy participants (1.76 ± 0.3 μmol/L; 1.01 ± 0.32 and 0.520 ± 0.18 μmol/L, respectively; p < 0.01). The concentrations of ADMA were higher in the cirrhotic patients with HRS than in those without this serious complication of cirrhosis. The concentration of ADMA in all the examined cirrhotic patients was higher than those obtained from healthy volunteers (1.35 ± 0.27 μmol/L, 1.05 ± 0.35 μmol/L and 0.76 ± 0.21 μmol/L, respectively). In the patients with terminal alcoholic liver cirrhosis, the concentrations
of ADMA and SDMA correlated with the progress of cirrhosis as well as with the development of cirrhosis complications. In the patients with HRS there was a positive correlation between creatinine and SDMA in plasma (r2 = 0.0756, p < 0.001) which was not found between creatinine and ADMA. The results demonstrate that the increase in SDMA concentration is proportionate to the progression of chronic damage of the liver and kidneys. Increased ADMA concentration can be a causative agent of renal insufficiency in patients with cirrhosis.

In patients with cirrhosis, ADMA, as well as SDMA could be markers for kidney insufficiency development. Accumulation of ADMA in plasma causes kidney
vasoconstriction and thereby retention of SDMA. Considering that ADMA has several damaging effects, it can be concluded that modulation of the activity of enzyme which participates in ADMA catabolism may represent a new therapeutic goal which is intended to reduce the progress of liver and kidney damage and thus the development of HRS.

ADMA Therapeutic Targets
Elevated plasma concentrations of the endogenous nitric oxide synthase
inhibitor asymmetric dimethylarginine (ADMA) are found in various clinical settings, including

  • renal failure,
  • coronary heart disease,
  • hypertension,
  • diabetes and
  • preeclampsia.

In healthy people acute infusion of ADMA promotes vascular dysfunction,
and in mice chronic infusion of ADMA promotes progression of atherosclerosis.
Thus, ADMA may not only be a marker but also an active player in cardiovascular disease, which makes it a potential target for therapeutic interventions.

This review provides a summary and critical discussion of the presently available data concerning the effects on plasma ADMA levels of cardiovascular drugs, hypoglycemic agents, hormone replacement therapy, antioxidants, and vitamin supplementation.
We assess the evidence that the beneficial effects of drug therapies on vascular function can be attributed to modification of ADMA levels. To develop more specific ADMA-lowering therapies, mechanisms leading to elevation of plasma ADMA concentrations in cardiovascular disease need to be better understood.

ADMA is formed endogenously by degradation of proteins containing arginine residues that have been methylated by S-adenosylmethionine-dependent methyltransferases (PRMTs). There are two major routes of elimination: renal excretion and enzymatic degradation by the dimethylarginine dimethylaminohydrolases (DDAH-1 and -2).

Oxidative stress causing upregulation of PRMT expression and/or attenuation of DDAH activity has been suggested as a mechanism and possible drug target in clinical conditions associated with elevation of ADMA. As impairment of DDAH activity or capacity is associated with substantial increases in plasma ADMA concentrations, DDAH is likely to emerge as a prime target for specific therapeutic interventions.

Cardiovascular diseases (CVD) in diabetic patients have endothelial dysfunction as a key pathogenetic event. Asymmetric dimethylarginine (ADMA), an endogenous inhibitor of nitric oxide synthase (NOS), plays a pivotal role in endothelial dysfunction. Different natural polyphenols have been shown to preserve endothelial function and prevent CVD. Another study assessed the effect of silibinin, a widely used flavonolignan from milk thistle, on ADMA levels and endothelial dysfunction in db/db mice.

Plasma and aorta ADMA levels were higher in db/db than in control lean mice. Silibinin administration markedly decreased plasma ADMA; consistently, aorta ADMA was reduced in silibinin-treated animals. Plasma and aorta ADMA levels exhibited a positive correlation, whereas liver ADMA was inversely correlated with both plasma and aorta ADMA concentrations. Endothelium-(NO)-dependent vasodilatation to ACh was impaired in db/db mice and was restored in the silibinin group, in accordance with the observed reduction of plasma and vascular levels of ADMA. Endothelium-independent vasodilatation to SNP was not modified by silibinin administration.

Endothelin Inhibitors
Endothelins are potent vasoconstrictors and pressor peptides and are important mediators of cardiac, renal andendocrine functions. Increased ET-1 levels in disease states such as congestive heart failure, pulmonary hypertension, acute myocardial infarction, and renal failure suggest the endothelin system as an attractive target for pharmacotherapy. A non-peptidic, selective, competitive endothelin receptor antagonist with an affinity for the ETA receptor in the subnanomolar range was administered by continuous intravenous infusion to beagle dogs, rats, and Goettingen minipigs. It caused mild arteriopathy characterised by segmental degeneration in the media of mid- to large-size coronary arteries in the heart of dog, but not rat or minipig.

The lesions only occurred in the atrium and ventricle. Frequency and severity of the vascular lesions was not sex or dose related. No effects were noted in blood vessels in other organs or tissue. Plasma concentrations at steady state, and overall exposure in terms of AUC(0–24h) were higher in minipig and rat than the dog but did not cause cardiac arteriopathy. These findings concur with those caused by other endothelin anatagonists, vasodilators and positive inotropic: vasodilating drugs such as potassium channel openers, phosphodiesterase inhibitors and peripheral vasodilators.

Results by echocardiography indicate treatment-related local vasodilatation in the coronary arteries. These data suggest that the coronary arteriopathy may be the result of exaggerated pharmacology. Sustained vasodilatation in the coronary vascular bed may alter flow dynamics and lead to increased shear stress and tension on the coronary wall with subsequent microscopic trauma. In our experience with a number of endothelin receptor antagonists, the cardiac arteriopathy was only noted in studies with multiple daily or continuous intravenous infusion inviting speculation that sustained high plasma levels are needed for development of the lesions.

Up-regulation of vascular endothelin type B (ETB) receptors is implicated in the
pathogenesis of cardiovascular disease. Culture of intact arteries has been shown to induce similar receptor alterations and has therefore been suggested as a suitable method for, ex vivo, in detail delineation of the regulation of endothelin receptors. We hypothesize that mitogen-activated kinases (MAPK) and protein kinase C (PKC) are involved in the regulation of endothelin ETB receptors in human internal mammary arteries.

The endothelin-1-induced contraction (after endothelin ETB receptor desensitization) and the endothelin ETA receptor mRNA expression levels were not altered by culture. The sarafotoxin 6c contraction, endothelin ETB receptor protein and mRNA expression levels were increased. This increase was antagonized by;

PKC inhibitors (10 μM bisindolylmaleimide I and 10 μM Ro-32-0432), and
inhibitors of the p38, extracellular signal related kinases 1 and 2 (ERK1/2) and C-jun terminal kinase (JNK) MAPK pathways
Endothelin Receptor Antagonist Tezosentan
The effects of changes in the mean (Sm) and pulsatile (Sp) components of arterial wall shear stress on arterial dilatation of the iliac artery of the anaesthetized dog were examined in the absence and presence of the endothelin receptor antagonist tezosentan (10 mg kg_1 I.V.; Ro 61-0612; [5-isopropylpyridine-2-sulphonic acid 6-(2-hydroxy-ethoxy)-5-(2-methoxy-phenoxy)-2-(2-1H-tetrazol-5-ylpyridin-4-yl)-pyrimidin-4-ylamide]).

Changes in shear stress were brought about by varying local peripheral resistance and stroke volume using a distal infusion of acetylcholine and stimulation of the left ansa subclavia. An increase in Sm from 1.81 ± 0.3 to 7.29 ± 0.7 N m_2 (means ± S.E.M.) before tezosentan caused an endothelium-dependent arterial dilatation which was unaffected by administration of tezosentan for a similar increase in Sm from 1.34 ± 0.6 to 5.76 ± 1.4 N m_2 (means ± S.E.M.).

In contrast, increasing the Sp from 7.1 ± 0.8 to a maximum of 11.5 ± 1.1 N m_2 (means ± S.E.M.) before tezosentan reduced arterial diameter significantly. Importantly, after administration of tezosentan subsequent increases in Sp caused arterial dilatation for the same increase in Sp achieved prior to tezosentan, increasing from a baseline of 4.23 ± 0.4 to a maximum of 9.03 ± 0.9 N m_2 (means ± S.E.M.; P < 0.001). The results of this study provide the first in vivo evidence that pulsatile shear stress is a stimulus for the release of endothelin from the vascular endothelium.

Exercise and Diet
Vascular endotheliumis affected by plasma asymmetric dimethylarginine (ADMA), and it is induced by inflammatory cytokines of tumour necrosis factor (TNF)-a in vitro. Would a tight glycemic control restore endothelial function in patients with type-2 diabetes mellitus (DM) with modulation of TNF-a and/or reduction of ADMA level? In 24 patients with type-2 DM, the flow-mediated, endothelium-dependent dilation (FMD: %) of brachial arteries during reactive hyperaemia was determined by a high-resolution ultrasound method. Blood samples for glucose, cholesterol, TNF-a, and ADMA analyses were also collected from these patients after fasting. No significant glycemic or FMD changes were observed in 10 patients receiving the conventional therapy.

In 14 patients who were hospitalized and intensively treated, there was a significant decrease in glucose level after the treatment [from 190+55 to 117+21 (mean+SD) mg/dL, P , 0.01]. After the intensive control of glucose level, FMD increased significantly (from 2.5+0.9 to 7.2+3.0%), accompanied by a significant (P , 0.01) decrease in TNF-a (from 29+16 to 11+9 pg/dL) and ADMA (from 4.8+1.5 to 3.5+1.1 mM/L) levels. The changes in FMD after treatment correlated inversely with those in TNF-a (R ¼ 20.711, P , 0.01) and ADMA (R ¼ 20.717, P , 0.01) levels.
The exaggerated blood pressure response to exercise (EBPR) is an independent predictor of hypertension. Asymmetric dimethylarginine (ADMA) is an endogenous nitric oxide inhibitor and higher plasma levels of ADMA are related to increased cardiovascular risk. The aim of this study is to identify the relationship between ADMA and EBPR.

A total of 66 patients (36 with EBPR and 30 as controls) were enrolled in the study. EBPR is defined as blood pressure (BP) measurements ≥200/100 mmHg during the treadmill test. All the subjects underwent 24-h ambulatory BP monitoring. L-arginine and ADMA levels were measured using a high performance lipid chromatography technique.

The serum ADMA levels were increased in the EBPR group compared to the healthy controls (4.0±1.4 vs 2.6±1.1 μmol/L respectively, P=0.001), but L-arginine levels were similar in the 2 groups (P=0.19). The serum ADMA levels were detected as an independent predictor of EBPR (odds ratio 2.28; 95% confidence interval 1.22–4.24; P=0.002). Serum ADMA levels might play a role in EBPR to exercise.

Endothelial dysfunction occurs early in atherosclerosis in response to cardiovascular risk factors. The occurrence of endothelial dysfunction is primarily the result of reduced nitric oxide (NO) bioavailabilty. It represents an independent predictor of cardiovascular events and predicts the prognosis of the patient. Therefore, endothelial function has been identified as a target for therapeutic intervention. Regular exercise training is a nonpharmacological option to improve endothelial dysfunction in patients with cardiovascular disease by increasing NO bioavailability.

Peripheral Arterial Disease (PAD) is a cause of significant morbidity and mortality in the Western world. risk factor modification and endovascular and surgical revascularisation are the main treatment options at present. However, a significant number of patients still require major amputation. There is evidence that nitric oxide (NO) and its endogenous inhibitor asymmetric dimethylarginine (ADMA) play significant roles in the pathophysiology of PAD.

This paper reviews experimental work implicating the ADMA-DDAH-NO pathway in PAD, focusing on both the vascular dysfunction and both the vascular dysfunction and effects within the ischaemic muscle, and examines the potential of manipulating this pathway as a novel adjunct therapy in PAD.

In patients with CHF, the peripheral vascular resistance is increased via activation of the neurohormonal system, namely by autonomous sympathetic nervous system, rennin -angiotensin- aldosterone system (RAAS), and endothelin system. The vascular endothelial function in patients with CHF, mainly represented by the endothelium-dependent vasodilation, is altered.

Such alteration leads to increased vascular tone and remodeling of the blood vessels, reducing the peripheral blood flow. Hence, the amount of oxygen for the skeletal muscles is compromised, with progressive exercise intolerance. The vascular endothelial dysfunction in the CHF is mainly due to the decrease of the nitric oxide production induced by the reduced gene expression of eNOS and increased oxidative stress.

The endothelium-dependent vasodilation alteration has been virtually reported in all cardiovascular diseases. Using sauna bath as therapeutic option for CHF is not very recent, since in the 1950’s the first studies with CHF patients were conducted and the potential beneficial effect of sauna was suggested. However, some time later the studies emphasized especially its risks and recommended caution in its use for cardiac patients.

Frequently, sports medicine physicians are invited to evaluate the impact of the sauna on diseases and on health in general. Sauna can be beneficial or dangerous depending on its use. In the past few years the sauna is considered beneficial for the cardiovascular diseases’ patients, as the heart failure and lifestyle-related diseases, mainly by improving the peripheral endothelial function through the increase in cardiac output and peripheral vasodilation.

It is widely known that the vasodilators, such as angiotensin converting enzyme inhibitors, improve the CHF and increase the peripheral perfusion. Since the endothelial function is altered in CHF, the endothelium is considered as a new therapeutic target in heart failure. Hence, the angiotensin converting enzyme inhibitors and physical training improve the endothelial function in CHF patients. One of the proposed mechanisms for the alteration of the endothelium-dependent vasodilation would be through the decrease of the NO production in the peripheral vessels in CHF patients. The decrease of peripheral perfusion would decrease the shear stress. The shear stress is an important stimulus for NO production and eNOS expression. On the other hand, the heat increases the cardiac output and improves the peripheral perfusion in CHF patients. Consequently, with the cardiac output improvement in CHF patients, an increase of the shear stress, NO production and eNOS expression are expected.

Sauna bath
The sauna bath represents a heat load of 300-600 W/m2 of body surface area. The skin temperature rapidly increases to ± 40o-41oC and the thermoregulatory mechanisms are triggered. Evaporative heat transfer by sweating is the only effective body heat loss channel in dry sauna. The sweating begins rapidly and reaches its maximum level in ± 15 min. The total sweat secretion represents a heat loss of about 200 W/m2 of the body surface area. The body cannot compensate for the heat load and causing elevation of internal temperature. The skin circulation increases substantially. The skin blood flow, in the thermo-neutral condition (± 20oC) and in rest corresponding to ± 5-10% of the cardiac output, can reach ± 50-70% of the cardiac output.

Thermal therapy in 60oC produced systemic arterial, pulmonary arterial and venous vasodilation, reduced the preload and afterload and improved the cardiac output and the peripheral perfusion, clinical symptoms, life quality, and cardiac arrhythmias in CHF patients. In infants with severe CHF secondary to ventricular septal defect, the sauna therapy decreased the systemic vascular resistance and increased the cardiac output. The sauna benefits in CHF patients are possibly caused by the improvement of the vascular endothelial function and normalization of the neurohormonal system .

Ikeda et al. discovered that the observed improvements in the sauna therapy are due to the eNOS expression increase in the arterial endothelium. They later showed that the thermal therapy with sauna improves the survival of the TO-2 cardiomyopathic hamsters with CHF and, more recently, showed that the repetitive therapy with sauna increases the eNOS expression and the nitric oxide production in artery endothelium of TO-2 cardiomyopathic hamsters with CHF.
Whether n-3 polyunsaturated fatty acid (PUFA) supplementation and/or diet intervention might have beneficial influence on endothelial function was assessed using plasma levels of ADMA and L-arginine. A male population (n = 563, age 70 ± 6 yrs) with long-standing hyperlipidemia, characterized as high risk individuals in 1970–72, was included, randomly allocated to receive placebo n-3 PUFA capsules (corn oil) and no dietary advice (control group), dietary advice (Mediterranean type), n-3 PUFA capsules, or dietary advice and n-3 PUFA combined and followed for 3 years. Fasting blood samples were drawn at baseline and the end of the study.

Compliance with both intervention regimens were demonstrated by changes in serum fatty acids and by recordings from a food frequency questionnaire. No influence of either regimens on ADMA levels were obtained. However, n-3 PUFA supplementation was accompanied by a significant increase in L-arginine levels, different from the decrease observed in the placebo group (p < 0.05). In individuals with low body mass index (<26 kg/m2), the decrease in L-arginine on placebo was strengthened (p = 0.01), and the L-arginine/ADMA ratio was also significantly reduced (p = 0.04). In this rather large randomized intervention study, ADMA levels were not influenced by n-3 PUFA supplementation or dietary counselling. n-3 PUFA did, however, counteract the age related reduction in L-arginine seen on placebo, especially in lean individuals, which might be considered as an improvement of endothelial function.

Traditional Chinese Medicine

Traditional Chinese Medicine (TCM) involves a broad range of empirical testing and refinement and plays an important role in the health maintenance for people all over the world. However, due to the complexity of Chinese herbs, a full understanding of TCM’s action mechanisms is still unavailable despite plenty of successful applications of TCM in the treatment of various diseases, including especially cardiovascular diseases (CVD), one of the leading causes of death.

An integrated system of TCM has been constructed to uncover the underlying action mechanisms of TCM by incorporating the chemical predictors, target predictors and network construction approaches from three representative Chinese herbs, i.e., Ligusticum chuanxiong Hort., Dalbergia odorifera T. Chen and Corydalis yanhusuo WT Wang widely used in CVD treatment, by combined use of drug absorption, distribution, metabolism and excretion (ADME) screening and network pharmacology techniques. These studies have generated 64 bioactive ingredients and identified 54 protein targets closely associated with CVD, to clarify some of the common conceptions in TCM, and provide clues to modernize such specific herbal medicines.

Ligusticum chuanxiong Hort., Dalbergia odorifera T. Chen and Corydalis yanhusuo WT Wang
Twenty-two of 194 ingredients in Ligusticum chuanxiong demonstrate good bioavailability (60%) after oral administration. Interestingly, as the most abundant bioactive compound of Chuanxiong, Ligustilide (M120) only has an adequate OB of 50.10%, although it significantly inhibits the vasoconstrictions induced by norepinephrine bitartrate (NE) and calcium chloride (CaCl2). Indeed, this compound can be metabolized to butylidenephthalide, senkyunolide I (M156), and senkyunolide H (M155) in vivo.

The three natural ingredients produce various pharmacological activities in cerebral blood vessels, the general circulatory system and immune system including spasmolysis contraction effects, inhibitory effects of platelet aggregation and anti-proliferative activity, and thus improve the therapeutic effect on patients. Cnidilide (M93, OB = 77.55%) and spathulenol (M169, OB = 82.37%) also closely correlate with the smooth muscle relaxant action, and thereby have the strongest spasmolytic activity. Carotol (M8) and Ferulic acid (M105) with an OB of 149.03% and 86.56%, respectively, demonstrate better bioavailability compared with cnidilide and spathulenol, which show strong antifungal, antioxidant and anti-inflammatory activity.

The pharmacological activity of ferulic acid results in the improvement of blood fluidity and the inhibition of platelet aggregation, which may offer beneficial effects against cancer, CVD, diabetes and Alzheimer’s disease. As for 3-n-butylphthalide (M85, OB = 71.28%), this compound is not only able to inhibit platelet aggregation, but also decreases the brain infarct volume and enhances microcirculation, thus benefiting patients with ischemic stroke. Platelet aggregation represents a multistep adhesion process involving distinct receptors and adhesive ligands, with the contribution of individual receptor-ligand interactions to the aggregation process depending on the prevailing blood flow conditions, implying that the rheological (blood flow) conditions are an important impact factor for platelet aggregation. Moreover, thrombosis, the pathological formation of platelet aggregates and one of the biggest risk factors for CVD, occludes blood flow causing stroke and heart attack. This explains why the traditional Chinese herb Ligusticum chuanxiong that inhibits platelet aggregates forming and promotes blood circulation can be used in treatment of CVD.

Twenty-six percent (24 of 93) of the ingredients in Dalbergia odorifera meet the OB > 60% criterion irrespective of the pharmacological activity. Relatively high bioavailability values were predicted for the mainly basic compounds odoriflavene (M275, OB = 84.49%), dalbergin (M247, OB = 78.57%), sativanone (M281, OB = 73.01%), liquiritigenin (M262, OB = 67.19%), isoliquiritigenin (M259, OB = 61.38%) and butein (M241, OB = 78.38%). Interestingly, all of the six ingredients show obvious anti-inflammatory property. Butein, liquiritigenin and isoliquiritigenin inhibit cell inflammatory responses by suppressing the NF-κB activation induced by various inflammatory agents and carcinogens, and by decreasing the NF-κB reporter activity. Inflammation occurs with CVD, and Dalbergia odorifera, one of the most potent anti-cardiovascular and anti-cerebrovascular agents, exerts great anti-inflammatory activity.

Corydalis yanhusuo has gained ever-increasing popularity in today’s world because of its therapeutic effects for the treatment of cardiac arrhythmia disease, gastric and duodenal ulcer and menorrhalgia. In our work, 21% (15 of 73) of chemicals in this Chinese herb display good OB (60% or even high), and the four main effective ingredients are natural alkaloid agents.

Dehydrocorydaline blocks the release of noradrenaline from the adrenergic nerve terminals in both the Taenia caecum and pulmonary artery, and thereby inhibits the relaxation or contraction of adrenergic neurons. As for dehydrocavidine with an OB of 47.59%, this alkaloid exhibits a significant spasmolytic effect, which acts via relaxing smooth muscle.

In recent years, CVD has been at the top list of the most serious health problems. Many different types of therapeutic targets have already been identified for the management and prevention of CVD, such as endothelin and others. The key question asked is

  • what the interactions of the active ingredients of the Chinese herbs are with their protein targets in a systematic manner and
  • how do the corresponding targets change under differential perturbation of the chemicals?

The study used an unbiased approach to probe the proteins that bind to the small molecules of interest in CVD on the basis of the Random Forest (RF) and Support Vector Machine (SVM) methods combining the chemical, genomic and pharmacological information for drug targeting and discovery on a large scale. Applied to 64 ingredients derived from the three traditional Chinese medicines Dalbergia odorifera, Ligusticum chuanxiong and Corydalis yanhusuo, which show good OB, 261 ligand-target interactions have been constructed, 221 of which are enzymes, receptors, and ion channels. This indicates that chemicals with multiple relative targets are responsible for the high interconnectedness of the ligand-target interactions. The promiscuity of drugs has restrained the advance in recent TCM, because they were thought to be undesirable in favor of more target-specific drugs.

Target Identification and Validation
To validate the reliability of these target proteins, the researchers performed a docking analysis to select the ligand-protein interactions with a binding free energies of ≤−5.0 kcal/mol, which leads to the sharp reduction of the interaction number from 5982 to 760. These drug target candidates were subsequently subject to PharmGkb (available online: http://www.pharmgkb.org; accessed on 1 December 2011), a comprehensive disease-target database, to investigate whether they were related to CVD or not, and finally, 54 proteins were collected and retained.

Fourty-two proteins (76%) were identified as the targets of Ligusticum chuanxiong, such as dihydrofolate reductase (P150), an androgen receptor (P210) and angiotensin-converting enzyme (P209) that were involved in the development of CVD. Of the proteins, seven and two were recognized as those of Dalbergia odorifera and Corydalis yanhusuo, respectively. For Dalbergia odorifera, this Chinese herb has 48 potential protein targets, 13 of which have at least one link to other drugs.

The three herbs share 29 common targets, accounting for 52.7% of the total number. Indeed, as one of the most important doctrines of TCM
abstracted from direct experience and perception, “multiple herbal drugs for one disease” has played an undeniable role. These studies explored the targets of the three Chinese herbs, indicating that these drugs target the same targets simultaneously and exhibit similar pharmacological effects on CVD. This is consistent with the theory of “multiple herbal drugs for one disease”.

The three Chinese herbs possess specific targets. The therapeutic efficacy of a TCM depends on multiple components, targets and pathways. The complexity becomes a huge obstacle for the development and innovation of TCM. For example, the Chinese herb Ligusticum chuanxiong identifies the protein caspase-3 (P184), a cysteinyl aspartate-specific protease, as one of its specific targets, and exhibits inhibitory effects on the activity of this protease. In fact, connective tissue growth factor enables the activation of caspase-3 to induce apoptosis in human aortic vascular smooth muscle cells.

Thus, modulation of the activity of caspase-3 with Ligusticum chuanxiong suggests an efficient therapeutic approach to CVD. The Chinese herb Dalbergia odorifera has the α-2A adrenergic receptor (P216) as its specific target and probably blocks the release of this receptor, and thus influences its action. As for Corydalisyanhusuo, the protein tyrosine-protein kinase JAK2 (P9) is the only specific target of this Chinese herb. The results indicate different specific targets possessed by the three Chinese herbs.

Ligand-Candidate Target and Ligand-Potential Target Networks
Previous studies have already reported the relationships of the small molecules with CVD, which indicates the reliability of our results [45,46]. Regarding the candidate targets, we have found that prostaglandin G/H synthase 2 (P46) and prostaglandin G/H synthase 1 (P47) possess the largest number of connected ingredients. Following are nitric-oxide synthase, endothelial (P66) and tyrosine-protein phosphatase non-receptor type 1 (P8), which have 62 and 61 linked chemicals, respectively.
The 29 targets shared by the three traditional Chinese herbs exhibit a high degree of correlations with CVD, which further verifies their effectiveness for the treatment of CVD. These results provide a clear view of the relationships of the target proteins with CVD and other related diseases, which actually link the Chinese herbs and the diseases via the protein targets. This result further explains the theory of “multiple herbal drugs for one disease” based on molecular pharmacology.

Target-Pathway Network
Cells communicate with each other using a “language” of chemical signals. The cell grows, divides,or dies according to the signals it receives. Signals are generally transferred from the outside of the cell. Specialized proteins are used to pass the signal—a process known as signal transduction. Cells have a number of overlapping pathways to transmit signals to multiple targets. Ligand binding in many of the signaling proteins in the pathway can change the cellular communication and finally affect cell growth and proliferation. The authors extracted nine signal pathways closely associated with CVD in PharmGkb (available online: http://www.pharmgkb.org; accessed on 1 December 2011).

As the main components in the VEGF system, proto-oncogene tyrosine-protein kinase Src, eNOS, and hsp90-α is also recognized as common targets of Dalbergia odorifera, Ligusticum chuanxiong and Corydalis yanhusuo, which are efficient for the treatment of CVD. This implies that the candidate drugs can target different target proteins involved in the same or different signal pathways, and thereby have potential effects on the whole signal system.

Target Prediction
In search of the candidate targets, the model that efficiently integrates the chemical, genomic and pharmacological information for drug targeting and discovery on a large scale is based on the two powerful methods Random Forest (RF) and Support Vector Machine (SVM). The model is supported by a large pharmacological database of 6511 drugs and 3999 targets extracted from the DrugBank database (available online: http://drugbank.ca/; accessed on 1 June 2011), and shows an impressive performance of prediction for drug-target interaction, with a concordance of 85.83%, a sensitivity of 79.62% and a specificity of 92.76%. the candidate targets were selected according to the criteria that the possibility of interacting with potential candidate targets was higher than 0.6 for the RF model and 0.7 for the SVM model. The obtained candidate targets were finally reserved and were further predicted for their targets.

Target Validation
Molecular docking analysis was carried out using the AutoDock software (available online: http://autodock.scripps.edu/; accessed on 1 February 2012). This approach performs the docking of the small, flexible ligand to a set of grids describing the target protein. During the docking process, the protein was considered as rigid and the molecules as flexible. The crystal structures of the candidate targets were downloaded from the RCSB Protein Data Bank (available online: http://www.pdb.org/; accessed on 1 December 2011), and the proteins without crystal structures were performed based on homology modeling using the Swiss-Model Automated Protein Modelling Server (available online: http://swissmodel.expasy.org/; accessed on 1 February 2012).

TCM is a heritage that is thousands of years old and is still used by millions of people all over the world—even after the development of modern scientific medicine. Chinese herbal combinations generally include one or more plants and even animal products.

The study identified 54 protein targets, which are closely associated with CVD for the three Chinese herbs, of which 29 are common targets (52.7%), which clarifies the mechanism of efficiency of the herbs for the treatment of CVD.

Activation of NFkB

Extracellular stimuli for NFkB activation and NFkB regulated genes
Extracellular stimuli                       Regulated genes
TNFa                                         Growth factors (G/M-CSF)
Interleukin 1                            G/M CSF, M CSF, G CSF
ROS                                              Cell adhesion molecules
UV light                            ICAM-1, VCAM, E-Selectin, P-selectin
Ischaemia                                   Cytokines
Lipopolysaccharide               TNFa, IL-1, IL-2, IL-6, interferon
Bacteria                                        Transcription regulators
Viruses                                         P53, IkB, c-rel, c-myc
Amyloid                                      Antiapoptotic proteins
Glutamate                              TRAF-1, TRAF-2, c-IAP1, c-IAP2
Pathophysiology
Reactive oxygen species (ROS) are toxic and in conditions of a dysbalance between their overproduction and the diminished activity of various antioxidant enzymes and other molecules induce cellular injury termed oxidative stress. ROS are often related to a number of diseases like atherosclerosis. However, the mechanism is not clear at all. Latest years of research have brought the idea of connection between ROS and NFkB. And indeed, in vitro studies showed a rapid activation of NFkB after exposure of certain cell types to ROS. Today, no specific receptor for ROS has been found, thus, the details of the ROS induced activation of NFkB are missing.

Natural occurring agents which actions are still a matter of debate in the theory and nouvelle small molecular derivates activate or inhibit the transcriptional factor. Synthetic oligo and polypeptide inhibitors of NFkB can penetrate the cell membrane and directly act on the Rel proteins. The most sophisticated approaches towards inhibiting the activation and translocation of NFkB into the nucleus represent gene deliveries, using plasmids or adenoviruses containing genes for various super repressors—modified IkB proteins, or so called NFkB decoys, which interact with activated NFkB and thus, inhibit the interaction between the transcription factor and nuclear DNA enhancers.

A simplified scheme of the activation of NFkB by the degradation of IkB. IkB is phosphorylated by IKK and ubiquinatated by the ubiquitine ligase system (ULS). IkB is further degradated by the 26S proteasome (26S).Activated NFkB can pass the nuclear membrane and interact with kB binding sequences in enhancers of NFkB regulated genes. LPS, lipopolysaccharide; ROS, reactive oxygen species; FasL, Fas ligand; TRAF, TNFa receptor associated factor; NIK, NFkB inducing kinase; MEKK, mitogen activated protein kinase/extracellular signal regulated kinases kinases.

The medicine of this century is a medicine of molecules, the diagnostic procedure and the therapy moves further from the “clinical picture” to the use of achievements in molecular biology and genetics. However, sober scepticism and awareness are indicated. Especially the role of NFkB in multiple signal transducing pathways and the tissue dependent variability of responses to alternations in NFkB pathway may be the reasons for unwanted side effects of the therapy that are after in vitro or in vivo experiments hardly to expect in the clinical use.

Therapeutic Targets
Modern drug discovery is primarily based on the search and subsequent testing of drug candidates acting on a preselected therapeutic target. Progress in genomics, protein structure, proteomics, and disease mechanisms has led to a growing interest in an effort for finding new targets and more effective exploration of existing targets. The number of reported targets of marketed and investigational drugs has significantly increased in the past 8 years. There are 1535 targets collected in the therapeutic target database.
Knowledge of these targets is helpful for molecular dissection of the mechanism of action of drugs and for predicting features that guide new drug design and the
search for new targets. This article summarizes the progress of target exploration and investigates the characteristics of the currently explored targets to analyze their sequence, structure, family representation, pathway association, tissue distribution, and genome location features for finding clues useful for searching for new targets. Possible “rules” to guide the search for druggable proteins and the feasibility of using a statistical learning method for predicting druggable proteins directly from their sequences are discussed.

Current Trends in Exploration of Therapeutic Targets
There are 395 identifiable targets described in 1606 patents. Of these targets, 264 have been found in more than one patent and 50 appear in more than 10 patents. The number of patents associated with a target can be considered to partly correlate with the level of effort and intensity of interest currently being directed to it. Approximately one third of the patents with an identifiable target were approved in the past year. This suggests that the effort for the exploration of these targets is ongoing, and there has been steady progress in the discovery of new investigational agents directed to these targets.

Various degrees of progress have been made toward discovery and testing of agents directed at these targets. However, for some of these targets, many difficulties remain to be resolved before viable drugs can be derived. The appearance of a high number of patents associated with these targets partly reflects the intensity of efforts for finding effective drug candidates against these targets.

There are 62 targets being explored for the design of subtype-specific drugs, which represents 15.7% of the 395 identifiable targets in U.S. patents approved in 2000 through 2004. Compared with the 11 targets of FDA approved subtype-specific drugs during the same period, a significantly larger number of targets are being explored for the design of subtype-specific drugs.

What Constitutes a Therapeutic Target?
The majority of clinical drugs achieve their effect by binding to a cavity and regulating the activity, of its protein target. Specific structural and physicochemical properties, such as the “rule of five” (Lipinski et al., 2001), are required for these drugs to have sufficient levels of efficacy, bioavailability, and safety, which define target sites to which drug-like molecules can bind. In most cases, these sites exist out of functional necessity, and their structural architectures accommodate target-specific drugs that minimally interact with other functionally important but structurally similar sites.
These constraints limit the types of proteins that can be bound by drug-like molecules, leading to the introduction of the concept of druggable proteins (Hopkins and Groom, 2002; Hardy and Peet, 2004). Druggable proteins do not necessarily become therapeutic targets (Hopkins and Groom, 2002); only those that play key roles in diseases can be explored as potential targets.

 Prediction of Druggable Proteins by a Statistical Learning Method

Currently, the support vector machine (SVM) method seems to be the most accurate statistical learning method for protein predictions. SVM is based on the structural risk minimization principle from statistical learning theory. Known proteins are divided into druggable and nondruggable classes; each of these proteins is represented by their sequence-derived physicochemical features.

These features are then used by the SVM to construct a hyperplane in a higher dimensional hyperspace that maximally separates druggable proteins and nondruggable ones. By projecting the sequence of a new protein onto this hyperspace, it can be determined whether this protein is druggable from its location with respect to the hyperplane. It is a druggable protein if it is located on the side of druggable class.
References

Böger RH. Asymmetric dimethylarginine, an endogenous inhibitor of nitric oxide synthase, explains the ‘L-arginine paradox’ and acts as a novel cardiovascular risk factor. J Nutr 2004; 134: 2842S–7S.
B Dobutovi, K Smiljani, S Soski, HD Düngen and ER Isenovi. Nitric Oxide and its Role in Cardiovascular Diseases. The Open Nitric Oxide Journal, 2011; 3: 65-71. 1875-0427/11.
Vallance P, Leone A, Calver A, Collier J, Moncada S. Accumulation of an endogenous inhibitor of nitric oxide synthesis in chronic renal failure. Lancet 1992; 339(8793): 572−5.

ER Hedegaard, E Stankevicius, U Simonsen and O Fröbert. Non-endothelial endothelin counteracts hypoxic vasodilation in porcine large coronary arteries. BMC Physiology 2011; 11:8-20. http://www.biomedcentral.com/1472-6793/11/8

S Rajagopalan, D Pfenninger, C Kehrer, A Chakrabarti. Increased Asymmetric Dimethylarginine and Endothelin 1 Levels in Secondary Raynaud’s Phenomenon. Arthritis & Rheumatism 2003; 48(7): 1992–2000. DOI: 10.1002/art.11060
Boger RH. The emerging role of asymmetric dimethylarginine as a novel cardiovascular risk factor. Cardiovasc Res 2003;59:824-833.

Böger RH, Ron ES. L-Arginine Improves Vascular Function by Overcoming the Deleterious Effects of ADMA, a Novel Cardiovascular Risk Factor. Altern Med Rev 2005;10(1):14-23.

Böger RH. Asymmetric dimethylarginine (ADMA) and cardiovascular disease: insights from prospective clinical trials. Vascular Medicine 2005; 10(2): S19-S25. DOI: 10.1191/ 1358863x 05vm602oa.

J Leiper, M Nandi, B Torondel, J Murray-Rust, et al. Disruption of methylarginine metabolism impairs vascular homeostasis.

Murray-Rust, J. et al. Structural insights into the hydrolysis of cellular nitric oxide synthase inhibitors by dimethylarginine dimethylaminohydrolase. Nat. Struct. Biol. 2001; 8:679–683.

D Nilsson, LGustafsson, A Wackenfors, B Gesslein, et al. Up-regulation of endothelin type B receptors in the human internal mammary artery in culture is dependent on protein kinase C and mitogen-activated kinase signaling pathways. MC Cardiovascular Disorders 2008; 8:21-31. doi:10.1186/1471-2261-8-21. http://www.biomedcentral.com/1471-2261/8/21

GL Volti, S Salomone, V Sorrenti, A Mangiameli, et al. Effect of silibinin on endothelial dysfunction and ADMA levels in obese diabetic mice. Cardiovascular Diabetology 2011, 10:62. http://www.cardiab.com/content/10/1/62

Leiper, J., Murray-Rust, J., McDonald, N. & Vallance, P. S-nitrosylation of dimethylarginine dimethylaminohydrolase regulates enzyme activity: further interactions between nitric oxide synthase and DDAH. Proc. Natl. Acad. Sci. USA 2002; 99: 13527–13532.

R Maas. Pharmacotherapies and their influence on asymmetric dimethylargine (ADMA). Vascular Medicine 2005; 10(2): S49-S57. DOI : 10.1191/ 1358863x05vm605oa

Veli-Pekka Valkonen, Tomi-Pekka Tuomainen, R Laaksonen. DDAH gene and cardiovascular risk. Vascular Medicine 2005; 10: S45–48.

AA Elesber, H Solomon, RJ Lennon, V Mathew, et al. Coronary endothelial dysfunction is associated with erectile dysfunction and elevated asymmetric dimethylarginine in patients with early atherosclerosis. European Heart Journal 2006; 27: 824–831. doi:10.1093/eurheartj/ehi749.

S Yasuda, S Miyazaki, M Kanda, Y Goto, et al. Intensive treatment of risk factors in patients with type-2 diabetes mellitus is associated with improvement of endothelial function coupled with a reduction in the levels of plasma asymmetric dimethylarginine an endogenous inhibitor of nitric oxide synthase. European Heart Journal 2006; 27: 1159–1165. doi:10.1093/ eurheartj/ehi876.

F Markos, BA Hennessy, M Fitzpatrick, J O’Sullivan and HM Snow. The effect of tezosentan, a non-selective endothelin receptor antagonist, on shear stress-induced changes in arterial diameter of the anaesthetized dog. Journal of Physiology 2002; 544(3): 913–918. DOI: 10.1113/jphysiol.2002.030478. http://www.jphysiol.org

M Kayrak; A Bacaksiz; MA Vatankulu, SS Ayhan, et al. Association Between Exaggerated Blood Pressure Response to Exercise and Serum Asymmetric Dimethylarginine Levels. Hypertension and Circulatory Control. Circ J 2010; 74: 1135 – 1141.

C Walther, S Gielen, and R Hambrecht. The effect of exercise training on endothelial function in cardiovascular disease in humans. Exerc Sport Sci Rev 2004; 32(4): 129–134 .

D Abraham, S Selvakumar, DM Baker, and JCS Tsui. Nitric Oxide Manipulation: A Therapeutic Target for Peripheral Arterial Disease? Williams, Xu Shi-Wen, Hindawi Publishing Corporation, Cardiology Research and Practice 2012; Article ID 656247, 7 pages doi:10.1155/2012/656247G . Sidney G. Shaw, Ed.

M Stephan-Gueldner, A Inomata. Coronary arterial lesions induced by endothelin antagonists. Toxicology Letters 2000; 112–113: 531–535.

V Ničković, J Nikolić, N Djindjić, М Ilić, et al. Diagnostic significance of dimethylarginine in the development of hepatorenal syndrome in patients with alcoholic liver cirrhosis. Vojnosanit Pregl 2012; 1-6 .UDC: 616.89-008.441.3-06:[616.36-004-07:616.61-008.6-07DOI: 10.2298/ VSP110728009N.

HMA Eid, H Arnesen, EM Hjerkinn, T Lyberg, et al. Effect of diet and omega-3 fatty acid intervention on asymmetric dimethylarginine. Nutrition & Metabolism 2006; 3:4-14. doi:10.1186/1743-7075-3-4.

B Li, X Xu, X Wang, H Yu, X Li, et al. A Systems Biology Approach to Understanding the Mechanisms of Action of Chinese Herbs for Treatment of Cardiovascular Disease. Int. J. Mol. Sci. 2012; 13: 13501-13520; doi:10.3390/ ijms131013501. ISSN 1422-0067. http://www.mdpi.com/journal/ijms

P Celec. Nuclear factor kappa B—molecular biomedicine: the next generation. Biomedicine & Pharmacotherapy 2004; 58:365–371. http://www.elsevier.com/locate/biopha

C. J. ZHENG, L. Y. HAN, C. W. YAP, Z. L. JI, et al. Therapeutic Targets: Progress of Their Exploration and Investigation of Their Characteristics. Pharmacol Rev 2006; 58:259–279. 0031-6997/06/5802-259–279. http://pharmrev.aspetjournals.org/content/suppl/2006/05/26/58.2.259.D

Lev-Ari, A. Stem cells create new heart cells in baby mice, but not in adults, study shows

http://pharmaceuticalintelligence.com/2012/08/03/stem-cells-create-new-heart-cells-in-baby-mice-but-not-in-adults-study-shows/

Lev-Ari, A. Cardiovascular Disease (CVD) and the Role of agent alternatives in endothelial Nitric Oxide Synthase (eNOS) Activation and Nitric Oxide Production

http://pharmaceuticalintelligence.com/2012/07/19/cardiovascular-disease-cvd-and-the-role-of-agent-alternatives-in-endothelial-nitric-oxide-synthase-enos-activation-and-nitric-oxide-production/

Lev-Ari, A. Bystolic’s generic Nebivolol – positive effect on circulating Endothelial Progenitor Cells endogenous augmentation

http://pharmaceuticalintelligence.com/2012/07/16/bystolics-generic-nebivolol-positive-effect-on-circulating-endothilial-progrnetor-cells-endogenous-augmentation/

Lev-Ari, A. Macrovascular Disease – Therapeutic Potential of cEPCs: Reduction Methods for CV Risk

http://pharmaceuticalintelligence.com/2012/07/02/macrovascular-disease-therapeutic-potential-of-cepcs-reduction-methods-for-cv-risk/

Lev-Ari, A. Heart patients’ skin cells turned into healthy heart muscle cells

http://pharmaceuticalintelligence.com/2012/06/04/heart-patients-skin-cells-turned-into-healthy-heart-muscle-cells/

Lev-Ari, A. Resident-cell-based Therapy in Human Ischaemic Heart Disease: Evolution in the PROMISE of Thymosin beta4 for Cardiac Repair

http://pharmaceuticalintelligence.com/2012/04/30/93/

 Nitric Oxide and Sepsis, Hemodynamic Collapse, and the Search for Therapeutic Options

Congestive Heart Failure & Personalized Medicine: Two-gene Test predicts response to Beta Blocker Bucindolol

Mediterranean Diet is BEST for patients with established Heart Disorders

NO Nutritional remedies for hypertension and atherosclerosis. It’s 12 am: do you know where your electrons are?

Endothelin Receptors in Cardiovascular Diseases: The Role of eNOS Stimulation
Inhibition of ET-1, ETA and ETA-ETB, Induction of NO production, stimulation of eNOS and Treatment Regime with PPAR-gamma agonists (TZD): cEPCs

Endogenous Augmentation for Cardiovascular Risk Reduction – A Bibliography

Reveals from ENCODE project will invite high synergistic collaborations to discover specific targets

Read Full Post »

dimethyl arginineNitric Oxide and Sepsis

Nitric Oxide and Sepsis, Hemodynamic Collapse, and the Search for Therapeutic Options

Curator, Reporter, EAW: Larry H Bernstein, MD, FCAP

This document explores the current understanding of sepsis as a cascade of events that involves the microcirculation unevenly because of a differential effect on the large and contiguous intestinal epithelium, secondary effects on cardiopulmonary blood flows and cardiac output, and the role of Nitric Oxide in the emergence of beneficial and potentially deleterious effects. This leads to a substantial body of work on therapeutic targets, either aimed at total inhibition or selective inhibition of NO synthase, and the special role of iNOS. This is another of a series of discussions on the metabolic and regulatory role of NO in health and disease.

Introduction

Antioxidants are essential, and are involved in several important biological processes such as immunity, protection against tissue damage, reproduction, growth and development. Antioxidants preserve adequate function of cells against homeostatic disturbances such as those caused by septic shock, aging and, in general, processes involving oxidative stress. This review focuses on the involvement of reactive oxygen and nitrogen species.
The presence of free radicals in biological materials was discovered about 50 years ago. Today, there is a large body of evidence indicating that patients in hospital intensive care units (ICUs) are exposed to excessive free radicals from drugs and other substances that alter cellular reduction -oxidation (redox) balance, and disrupt normal biological functions. However, low levels of free radicals are also vital for many cell signaling events and are essential for proper cell function.
Excess free radicals can result from a variety of conditions such as tissue damage and hypoxia (limiting oxygen levels), overexposure to environmental factors (tobacco smoke, ultraviolet radiation, and pollutants), a lack of antioxidants, or destruction of free radical scavengers. When the production of damaging free radicals exceeds the capacity of the body’s antioxidant defenses to detoxify them, a condition known as oxidative stress occurs.

Free Radicals and Antioxidants: an Overview

A free radical can be described as any atom or a group of atoms or molecules in which there is at least one unpaired electron in the outermost shell . These free radicals are very reactive with adjacent molecules such as lipids, proteins, and carbohydrates and can cause cellular damage. Paradoxically, free radicals can also be produced by many cells as a protective mechanism, for example neutrophils produce free radicals to attack and destroy pathogens, while the liver uses free radicals for detoxification. However, the presence of free radicals within the body can also have a significant role in the development and progression of many disease processes for example heart disease, hypertension, cerebrovascular accidents, and diabetic complications. Any free radical involving O2 is referred to as a reactive oxygen species (ROS).
Normal cellular metabolism involves the production of ROS, and in humans, superoxide (O2 -) is the most commonly produced free radical. Phagocytic cells such as macrophages and neutrophils are prominent sources of O2 -. During an inflammatory response, these cells generate free radicals that attack invading pathogens such as bacteria and, because of this, the production of O2- by activated phagocytic cells in response to inflammation is one of the most studied free radical producing systems. The majority of the H2O2 is broken down to O2 and water by the antioxidant enzyme catalase. In addition to catalase, glutathione peroxidase can also break down H2O2 and also any peroxides that form on lipids within the body. When O2 – reacts with nitric oxide (NO), the toxic product peroxynitrite (ONOO-) is formed.
Cellular ROS originate from O2- generated as a by-product of oxidative phosphorylation (mitochondrial respiration), they differ in their mechanism of production, necessary cofactors, diffusion range, hydrophobicity, biological targets, detoxification pathways and breakdown products. O-2 damaging reactions largely involve disassembly of iron-sulphur clusters in proteins. H2O2 or O-2 alone lacked reactivity toward iron regulatory protein-1 (IRP-1), but a combined action of the two species induced reversible inactivation of IRP-1. Such an effect was attributed to direct interactions of O-2 and H2O2 with a preformed pool of IRP-1, resulting in reversible modifications of -SH residues; in fact, its action would be limited to removing only iron atoms, an effect sufficient to abolish enzyme activity.
The hydroxyl radical (.OH) is the most reactive of the free radical molecules. OH- damages cell membranes and lipoproteins by a process termed lipid peroxidation. In fact, lipid peroxidation can be defined as the process whereby free radicals “steal” electrons from the lipids in our cell membranes, resulting in cell damage and increased production of ROS. This process takes place in 3 stages:

  1. Initiation: In a peroxide-free lipid system, the initiation of a peroxidation sequence refers to the attack of an ROS (with sufficient reactivity) able to abstract a hydrogen (H) atom from a methylene group (- CH2-).
  2. Propagation: A peroxyl radical is able to abstract H from another lipid molecule (adjacent fatty acid), especially in the presence of metals such as copper or iron, thus causing an autocatalytic chain reaction. The peroxyl radical combines with H to give a lipid hydroperoxide (or peroxide).
  3. Termination: formation of a hydroperoxide. Lipid peroxidative damage to lipids in low-density lipoprotein (LDL) plays an important role in atherosclerosis [9]. To protect against oxidative damage, organisms have developed a variety of antioxidant defenses that include proteins, compounds such as vitamins, and specialized antioxidant enzymes.

Lipid-soluble antioxidants are located in the cellular membranes and lipoproteins, whereas the water-soluble antioxidants are present in the aqueous environments, such as fluids inside cells and in the blood. Preventative antioxidant enzymes inside the cell are an important defense against free radicals.
In humans, the highest levels of SOD are found in the liver, adrenal gland, kidney, and spleen. Catalase and glutathione peroxidase both work to detoxify O2-reactive radicals by catalyzing the formation of H2O2 derived from O2 -. The liver, kidney, and red blood cells possess high levels of catalase, which helps to detoxify chemicals in the body. The water-soluble tripeptide-thiol glutathione also plays an important role in a variety of detoxification processes. Glutathione is found in millimolar concentrations in the cell cytosol and other aqueous phases, and readily interacts with free radicals, especially the hydroxyl radical, by donating a hydrogen atom.

Sepsis and Signaling Pathways

Serious infections trigger systemic inflammatory response and can result in sepsis. It is believed that sepsis and therefore septic shock are due to the inappropriate increase in the innate immune response via circulating and tissue inflammatory cells, such as monocytes/macrophages and neutrophils. These cells normally exist in a nonactivated state but are rapidly activated in response to bacteria. Sepsis induces a dysfunction in immune cells that contributes to the development of injuries by producing mediators such as cytokines and ROS.

Lipopolysaccharide (Lps) Signaling

LPS of Gram-negative organisms induces macrophages to secrete cytokines, which in turn activate T, and B cells to upregulate the adaptive immune responses. Toll-like receptor 4 (TLR4) is the LPS receptor and its stimulation induces nuclear factor kB (NF-kB) activation. The activation of NF-kB involves phosphorylation and degradation of IkB, an inhibitor of NF-kB. The NF-kB/IkB system exerts transcriptional regulation on proinflammatory genes encoded for various adhesion molecules and cytokines. Activation of NF-kB leads to the induction of NF-kB binding elements in their promoter regions and also leads to the induction of NF-kB dependent effector genes, which produce modifications in blood flow, and aggregation of neutrophils, and platelets. This results in damaged endothelium and also coagulation abnormalities often seen in patients with sepsis and septic shock. Therefore, NF-kB is reported to be an O2 sensor in LPS-induced endotoxemia.

Free Radicals and Antioxidants In Sepsis

The sources of ROS during sepsis are:

  1. the mitochondrial respiratory chain.
  2. the metabolic cascade of arachidonic acid.
  3. the protease-mediated enzyme xanthine oxidase.
  4. granulocytes and other phagocytes activated by complement, bacteria, endotoxin, lysosomal enzymes, etc.
  5. Other oxidases mainly NADPH oxidase.

Under normal physiological conditions, the majority of ROS are formed during cellular respiration and by activated phagocytic cells, including neutrophils, involved in the inflammatory response. ROS have physiologically essential roles in mitochondrial respiration, prostaglandin production pathways and host defense . The electron reduction of O2 occurs in the mitochondrial electron transport system of all aerobically respiring cells. The enzyme catalyzing this transition metals iron and copper in its active site. These ions can be paramagnetic and contain stable unpaired electrons. By using the unpaired electrons in these transition metals to control the O2 reactions, mitochondria prevent the unwanted release of ROS.
In sepsis, there are several potential sources of ROS, including the mitochondrial respiratory electron transport chain, xanthine oxidase activation as a result of ischemia and reperfusion, the respiratory burst associated with immune cell activation, arachidonic acid metabolism and NADPH oxidase.

  • In fact, activated immune cells produce O2 – as a cytotoxic agent as part of the respiratory burst via the action of membrane-bound NADPH oxidase on O2.
  • The increase of ROS after LPS challenge has been demonstrated in different models of septic shock in peritoneal macrophages and lymphocytes.

This disturbance in the balance between pro-oxidants (ROS) and antioxidants in favor of the former is characteristic of oxidative stress in immune cells in response to endotoxin. In this context,

  • a typical behavior of these cells under an oxidative stress situation implies changes in different immune functions such as an increase in adherence and phagocytosis and a decrease in chemotaxis.
  • Neutrophils play a crucial role in the primary immune defense against infectious agents,which includes phagocytosis and the production of ROS.

Antioxidant Defenses

Antioxidants are central to the redox balance in the human body. They do not act in isolation, but synergistically with other classes of molecules. Primary antioxidants prevent oxygen radical formation, by either removing free radical precursors or by inhibiting catalysis, e.g. the enzymes glutathione peroxidase and catalase. Secondary antioxidants react with ROS which have already been formed, either to remove or inhibit them, e.g. vitamins C and E. Endogenous antioxidant defenses exist in a number of locations, namely intracellularly, on the cell membrane and extracellularly. The immune system is highly reliant on accurate cell-cell communication for optimal function, and any damage to the signaling systems involved will result in an impaired immune responsiveness.

  • Oxidant-mediated tissue injury is a particular hazard to the immune system, since phagocyte cells produce ROS as part of the defense against infection.
  • Therefore, adequate amounts of neutralizing antioxidants are required to prevent damage to the immune cells themselves.

The SOD enzymes are a family of metalloenzymes which rapidly promote the conversion of O2- to H2O2. Three forms of SOD are recognized to be important: copper-zinc SOD (cytoplasmic-located), manganese SOD (mitochondrial-located) and extracellular SOD (extracellular matrix-located). Catalase and glutathione peroxidase, a selenium containig enzyme which requires the presence of reduced GSH for its action, both catalyze the conversion of H2O2 to H 2O. GSH also has direct antioxidant activity, through donation of hydrogen ions, to repair damaged DNA. Oxidative stress and modulation on GSH/GSSG (GSSG=oxidized GSH) levels also up-regulate gene expression of several other antioxidant proteins, such as manganese SOD, glutathione peroxidase, thioredoxin (Trx) and metallothionein.

Effects of Nitric Oxide

NO is synthesized from L-arginine by different isoenzymes of (NOS), and is implicated in a wide range of disease processes, exerting both detrimental and beneficial effects at the cellular and vascular levels. To date, three main isoforms of NOS are known:

  • neuronal NOS (NOS-1 or nNOS),
  • inducible NOS (NOS-2 or iNOS), and
  • endothelial NOS (NOS-3 or eNOS).

NO has been shown to play a key role in the pathogenesis of septic shock

Hyperproduction of NO induces

  • excessive vasodilation,
  • changes in vascular permeability, and
  • inhibition of noradrenergic nerve transmission,

all characteristics of human septic shock.
The recogniton of NO production by activated macrophages as part of the inflammatory process was an important milestone for assesing both the biological production of NO and the phenomenon of induction of NOS activity. The observation has been extended to neutrophils, lymphocytes, and other cell types. The role of NO in the pathophysiology of endotoxic shock was advanced by Thiemermann and Vane, who observed that administration of the specific NOS inhibitor N-methyl-L-arginine (L-NMMA) decreased the severe hypotension produced by administration of LPS. Other groups simultaneously reported similar results indicating that endotoxin increases NO production and prompted the idea that pharmacological inhibition of NOS may be useful in the treatment of inflammation and septic shock. However, clinical trials using L-NMMA failed to show a beneficial effect in septic shock patient. The major limitation for the use of NOS inhibitors in clinical studies is the development of pulmonary hypertension as a side effect of NOS blockade, which can be alleviated by the use of inhaled NO.
However, several compounds which modulate NO synthesis have been patented in recent years, such as various inflammatory mediators that have been implicated in the induction and activation of iNOS, particularly IFNg, TNFa, IL-1b, and platelet-activating factor (PAF) alone or synergistically. In addition to the activation of iNOS, cytokines and endotoxin may increase NO release by increasing arginine availability through the opening of the specific y+ channels and the expression of the cationic amino acid transporter (CAT), or by increasing tetrahydrobiopterin levels, a key cofactor in NO synthesis. Several experimental studies have demonstrated a decrease in NOS activity resulting in an impairment in endothelial-dependent relaxation during endotoxemia and experimental sepsis, possibly as the result of a cytokine-or hypoxia-induced shortened half-life of NOS mRNA, or of altered calcium mobilization.
NO exerts in vitro toxic effects including nuclear damage, protein and membrane phospholipid alterations, and the inhibition of mitochondrial respiration in several cell types. Mitochondrial impairment could also be considered as an adaptive phenomenon, decreasing cellular metabolism when the energy supply is limited. The toxicity of NO itself may be enhanced by the formation of ONOO- from the reaction of NO with O-2. Therefore, the multiple organ failure syndrome (MOFS) that often accompanies severe sepsis may be related to the cellular effects of excess NO or ONOO-.

Involvement of Nitrogen Species

NO reacts rapidly with ferrous iron, and at physiological concentrations, NO also binds to soluble guanylate cyclase and to another hemoprotein, cytochrome c oxidase (Complex IV), the terminal enzyme of the mitochondrial respiratory chain. NO can therefore control cellular functions via the reversible inhibition of respiration. There are a number of reactive NO species, such as

  • N2O3 and
  • ONOO-

that can also alter critical cellular components.

During the first hours after injury, iNOS-mediated NO production is upregulated, producing a burst of NO that far exceeds basal levels. This overabundance of NO produces significant cellular injury via several mechanisms.
NO may

  • directly promote overwhelming peripheral vasodilation, resulting in vascular decomposition;
  •  NO may upregulate the transcription NF-kB initiating an inflammatory signaling pathway that, in turn,
  • triggers numerous inflammatory cytokines.

NO also interacts with the O-2 to yield ONOO-, a highly reactive compound that exacerbates the injury produced by either O-2 alone or NO alone.
The ONOO- generation which occurs during fluid resuscitation in the injured subject produces cellular death by enhancing DNA single strand breakage, activates the nuclear enzyme polyADP ribose synthetase (PARS), leading to cellular energy depletion and cellular necrosis. The detrimental effects of ONOO- in shock and resuscitation have been attributed to oxidation of sulfhydryl groups, the nitration of tyrosine, tryptophane, and guanine, as well as inhibition of the membrane sodium-potassium adenosine triphosphatase. PARS activation depletes NAD and thus alters electron transport, ATP synthesis, and glycolysis; and leads to DNA fragmentation and cellular apoptosis.
The activation of monocytes, macrophages and endothelial cells by LPS results in the expression of iNOS, and consequently increases the transformation of L-arginine to NO, which can combine with O2- to form ONOO-, causing tissue injury during shock, inflammation and ischemia reperfusion. NO stimulates H2O2 and O-2 production by mitochondria, increasing leakage of electrons from the respiratory chain. H2O2, in turn, participates in the upregulation of iNOS expression via NFkB activation. ONOO- has been shown to stimulate H2O2 production by isolated mitochondria. On the other hand, NO can decrease ROS-produced damage that occurs at physiological levels of NO. The high reactivity of NO with radicals might be beneficial in vivo by scavenging peroxyl radicals and inhibiting peroxidation. ONOO- may also be a signal transmitter and can mediate vasorelaxation, similarly to NO.
Local generation of RNS contributes to tissue injury. Recent studies have demonstrated that activation of the nuclear enzyme poly(ADP-ribose) polymerase-1 by RNS-mediated DNA damage is an important pathway of tissue injury in conditions associated with oxidative stress. Increased formation of RNS in response to endotoxin challenge is organ specific.
In sepsis, NO may exert direct and indirect effects on cardiac function. Sustained generation of NO occurs in systemic inflammatory reactions, such as septic shock with involvement in circulatory failure. In fact, myocardial iNOS activity has been reported in response to endotoxin and cytokines and inversely correlated with myocardial performance. Low-to-moderate doses of iNOS inhibitors restore myocardial contractility in hearts exposed to proinflammatory cytokines, whereas at higher doses, the effects are reversed. This finding may indicate that small amounts of NO produced by iNOS may be necessary to maintain contractility and can be cardio-protective in experimental sepsis.

Nitric oxide in Septic Shock

A list of effects of NO in sepsis is as follows.

  • Inhibition of nitric oxide synthesis causes myocardial ischemia in endotoxemic rats
  • Nitric oxide causes dysfunction of coronary autoregulation in endotoxemic rats
  • Prolonged inhibition of nitric oxide synthesis in severe septic shock
  • Effect of L-NAME, an inhibitor of nitric oxide synthesis, on cardiopulmonary function in human septic shock
  • Pulmonary hypertension and reduced cardiac output during inhibition of nitric oxide synthesis in human septic shock
  • Effect of L-NAME, an inhibitor of nitric oxide synthesis, on plasma levels of IL-6, IL-8, TNF-u and nitrite/nitrate in human septic shock
  • Endothelin-1 and blood pressure after inhibition of nitric oxide synthesis in human septic shock
  • Distribution and metabolism of NO-nitro-L-arginine methyl ester in patients with septic shock

The possible involvement of the L-arginine-NO pathway in both the vascular and cellular processes seen in sepsis has been supported by numerous in vitro and in vivo studies. iNOS appears to be expressed in a wide array of cell types during sepsis, including immune cells (such as macrophages, neutrophils, T lymphocytes), as well as cells outside the classical immune system (for example, hepatocytes, Kuppfer cells, vascular smooth muscle cells, endothelial cells, and fibroblasts). Expression of iNOS is regulated, both positively and negatively, by a number of mediators present during infection and inflammation. The main stimuli for iNOS induction indude lipopolysaccharide (LPS), interferon-y, interleukin (IL)-10, and tumor necrosis factor (TNF)-a; inhibitory cytokines, such as transforming growth factor-5, IL-4 and IL-10, as well as glucocorticoids, can prevent this induction. The expression of iNOS in response to these agents differs among cell types, but a maximal inducing effect is generally obtained by the combination of microbial products and cytokines acting synergistically.

iNOS activity is also regulated by substrate and cofactor availability. Tetrahydrobiopterin (BH4), an essential cofactor for the enzyme, is coinduced with iNOS in cytokine-stimulated vascular smooth muscle cells.
NO is a simple molecule, but its widespread production in sepsis, coupled with its effects on a variety of intracellular and extracellular target molecules, results in a complex array of biologic roles. Interaction of NO with the metalloproteins in a number of key enzymes can modulate their activity. Many of the signaling actions of ‘NO are mediated by soluble guanylate cyclase. By binding the iron on the heme component of soluble guanylate cyclase, NO is able to activate the enzyme leading to cyclic guanosine monophosphate (cGMP) formation.

Increased cGMP levels account for several of the important cellular actions of NO, including

  • smooth muscle relaxation,
  • platelet aggregation and adherence, as well as
  • neutrophil chemotaxis.

However, *NO can adversely affect cellular metabolism through its disruption of iron-sulfur clusters in essential energy-generating enzymes involved in mitochondrial electron transport, glycolysis, and the Krebs cycle. Further, high concentrations of induced macrophage produced NO can directly interfere with DNA in target cells, resulting in fragmentation.
Another critical reaction that ‘NO undergoes during inflammation is with the superoxide anion radical (02j, yielding peroxynitrite (OONO-). OONO- is a potent oxidant that can decay under acidic conditions to produce a powerful hydoxyl-like free radical. This reaction between *NO and O2 can have a protective or damaging consequence, depending on the individual sites and rates of production of the free radicals, and the redox status of both the generating cells as well as the target cells. OONO- formation can initiate adverse effects such as lipid peroxidation of membranes, and modification of structural proteins through nitration of tyrosine residues (14). Indeed, increased levels of 3-nitrotyrosine have been detected in the lungs of patients with sepsis and animals with acute lung injury. However, OONO- can also S-nitrosylate glutathione and other thiol-containing substances to form S-nitrosothiols, which have marked cardioprotective and cytoprotective effects.
The damaging effect of NOS inhibition may be, in part, mediated by oxygen radicals and platelet deposition, suggesting a cytoprotective role of NO in preventing microvascular thrombosis and as a free radical scavenger. In addition, ‘NO has a protective role in hepatic microcirculatory dysfunction during sepsis through its effect on leukocyte adherence to sinusoidal walls. ‘NO may also protect against circulatory vasoconstrictors during inflammation, as enhanced ‘NO synthesis counteracted phenylephrine-induced increases in intrahepatic resistance in endotoxin-treated rats. Finally, we have recently demonstrated that different types of NOS inhibitors resulted in detectable apoptosis in the liver following LPS injection. This increase in apoptosis was present even with L-N-iminoethyl-lysine (L-NIL), a rather specific inhibitor of iNOS, revealing another important protective role of NO as an antiapoptotic agent in sepsis.
Even though overproduction of *NO in the vasculature contributes to the vasodilatation seen in septic shock, iNOS expression during inflammation also represents a beneficial, adaptive response in some organ systems. Moreover, different tissues can react dissimilarly to the effects of ‘NO cytotoxicity. In this setting, global nonselective inhibition of NOS, including the potentially undesirable consequences of eNOS inhibition, would be harmful. If confirmed, this would suggest that use of isoform-specific inhibitors of NOS within the vascular bed would be more appropriate.

Pulmonary Hypertension and Reduced Cardiac Output

Pulmonary hypertension and reduced cardiac output can be major side effects of continuous NO synthase inhibition. Pulmonary vasoconstriction is undesirable because it may compromise pulmonary gas exchange and because it increases the workload on the right ventricle. In cases where strain already exists on the right ventricle (e.g. sepsis or PEEP ventilation) or in cases where right sided cardiac reserve is minimal, such increase in workload may lead to right ventricular failure, reduced cardiac output and compromised tissue perfusion.
Blood pressure and systemic vascular resistance increased during infusion of the NO synthase inhibitor L-NAME, and the dosage of catecholamines was reduced. The vasoconstrictive response to L-NAME most likely was the result of blocking the NO system . In addition to the systemic effects of L-NAME, severe pulmonary vasoconstriction was observed with L-NAME. Analogous to these findings, in patients with Adult Respiratory Distress Syndrome (ARDS), inhalation of NO is reported to be beneficial by causing local vasodilation in bronchial and pulmonary circulation which results in reduced pulmonary vascular resistance and improved oxygenation. This suggests that the pulmonary circulation is sensitive to the vasodilating effects of both endogenous and exogenous NO. Pulmonary vasoconstriction is not, therefore, unexpected with systemic inhibition of NO synthesis. With a continuous infusion of L-NAME, pulmonary vascular resistance increased five-fold, whereas systemic vascular resistance “only” doubled. pulmonary hypertension was reversible after stopping L-NAME infusion. In prior experiments with a lower dose of LNAME, pulmonary vasoconstriction was less pronounced and did not result in pulmonary hypertension.’ Thus, pulmonary hypertension is a dose-related effect of L-NAME that can probably be attributed to overdosing of the drug. Reduced cardiac output may have directly resulted from the extreme increase in pulmonary vascular resistance compromising venous return and left ventricular preload and/or a reflex reduction in heart rate by the increase in vascular resistance and blood pressure.
S-methyl-isothiourea, a relatively selective inhibitor of iNOS activity, decreased pulmonary leak and improved survival in endotoxemia. However, because of the tissue-protective and antiapoptotic effects of NO, even selective iNOS inhibitors may be detrimental in certain tissues during sepsis.Combining the salutary effects of site-specific local donors that exploit the cytoprotective actions of ‘NO with specific agents that combat the deleterious hypotensive and tissue-damaging effects of ‘NO overproduction may be needed to treat septic shock. In this regard, inhaled ‘NO gas has shown promise as a selective pulmonary vasodilator.

Role of Nitric Oxide in Inflammation and Tissue Injury

Since the discovery that nitric oxide (‘NO) accounts for the biologic activity of endothelial-derived relaxing factor, a torrent of research over the last decade has focused on its role, protective or detrimental, in myriad pathophysiologic conditions. Recently, increasing attention has focused on ‘NO as a possible mediator of the severe hypotension and impaired vasoreactivity characteristic of circulatory failure. Experimental and clinical studies have suggested NOS inhibition might have therapeutic potential in circulatory shock, and other studies have demonstrated the beneficial nature of iNOS expression in modulating tissue perfusion and mediating cytotoxicity. However, inhibition of ‘NO synthesis in experimental and clinical studies of shock has yielded mixed, sometimes contradictory, results. Overproduction of ‘NO in the vasculature may result in systemic vasodilatation, but still ‘NO synthesis has a beneficial role in regulating organ perfusion and mediating cytotoxicity.

Diminished *NO Production Occurs with Hemorrhage

These findings are consistent with those in trauma patients, where nitrite and nitrate levels were reduced for prolonged periods after injury. This impairment of ‘NO production in victims of hemorrhagic hypotension may be due to impairment of eNOS, and indeed, several investigators have demonstrated decreased vasodilatory activity in vascular rings taken from hemorrhaged animals in response to agonists that stimulate endothelial ‘NO production. In studies of hemorrhagic shock no iNOS expression could be detected until the very late irreversible phase of HS. The hemodynamic instability associated with decompensation occurred well before NOS induction.
Using either the selective inhibitor L-NIL or iNOS knockout mice, iNOS inhibition or deficiency not only prevented the upregulation of the inflammatory cytokines IL-6 and granulocyte colony-stimulating factor following resuscitation from HS but also produced a marked reduction in lung and liver injury. Furthermore, the activation of the proinflammatory transcriptional factors nuclear factor kappa B and signal transducer and activator of transcription 3 was also reduced, suggesting iNOS upregulation has a key role in proinflammatory signaling and the subsequent activation of inflammatory cascades. Recent studies have implicated a possible redox-sensitive mechanism. ‘NO activates the critical signaling enzyme p21ras through S-nitrosylation.
Vascular quenching of ‘NO using scavengers may again provide an alternative to NOS inhibition as a means to achieve the goal of reducing ‘NO levels. Use of ‘NO scavengers after HS and resuscitation may serve to supplement a possibly depleted antioxidant defense system and limit the harmful effects of free radicals such as OONO- and hydoxyl radicals. Removal of ‘NO by this method is complicated by the extreme rapidity of the reaction between ‘NO and 02’- .
iNOS upregulation also has a beneficial protective role in several organ systems. In conditions where excess NO production results in maladaptive damaging consequences with disruption of homeostasis, the therapeutic strategy should be to remove this surplus ‘NO without adversely affecting the cytoprotective actions of *NO. Interfering with the physiologic and microcirculatory role of eNOS through nonselective, global inhibition of NOS is undesirable in shock.

Effects of nitric oxide in endotoxemia and hemorrhagic shock and proposed therapeutic strategies for manipulation of nitric oxide production.

Endotoxemia Hemorrhagic shock
Effects of NO                         Beneficial                            Beneficial
by eNOS                      -maintains perfusion;    -maintains perfusion;
cytoprotective               cytoprotective
iNOS                             Beneficial and toxic-         Beneficial and toxic-

depending on site can induce tissue damage and  of production and promote inflammation with microenvironment sustained shock

Therapeutic strategy

Inhibition of eNOS                Avoid                                     Avoid
Inhibition of iNOS         Possibly desirable-       Probably desirable-
to reduce                          to limit exaggerated inflammatory
cytotoxicity and           response and development of
combat hypotension       MODS

NO scavengers   Probably desirable-quench    Probably desirable-quench
extracellular NO without        extracellular NO without
inhibition of eNOS or iNOS;    inhibition of eNOS or iNOS;
supplement antioxidant defenses       supplement antioxidant defenses
NO donors          Possibly desirable-site-            Possibly desirable-site-
specific donors without adverse     specific donors without adverse
systemic  side effects;                      systemic side effects;
limited availability                             limited availability

Therapeutic Outlook

LINCS: L-NAME (a NO synthase inhibitor)
Patients were randomized to supportive care alone (n=15, control group) or to supportive care in addition to L-NAME (1 mg/Kg bolus and 1 mg/Kg/h continuous IV drip for 5 h n=15). Death at one month was 27% in the L-NAME group vs. 67% in the control group (p=0.008). Time on IABP and time on mechanical ventilation were significantly shorter in the L-NAME group. The results of this study indicate that NO synthase inhibitors are beneficial in the treatment of patients with refractory cardiogenic shock.
Inducible Nitric Oxide Synthase Inhibitors
Inducible nitric oxide synthase (iNOS)-dependent production of nitric oxide (NO) plays an important role in inflammation. The effects of various naturally occurring furanocoumarins on NO production in lipopolysaccharide (LPS)-activated RAW 264.7 macrophage cells were evaluated in vitro. The results showed that angelicin, pimpinellin, sphondin, byakangelicol, oxypeucedanin, oxypeucedanin hydrate, xanthotoxin, and cnidilin are potential NO production inhibitors, and their IC50 values for inhibition of nitrite production were 19.5, 15.6, 9.8, 16.9, 16.8, 15.8, 16.6, and 17.7 mg/mL, respectively.

Distinct structure activity relationships were also revealed for the NO production inhibitory activities of these furanocoumarins. Activities of the angelicin type such as pimpinellin and sphondin were more potent than those of the psoralen type. Presence of a methoxy at the C6 position in the angelicin type seemed to be essential to augment the activity. Western blot analysis demonstrated that only sphondin dose-dependently inhibited the expression of the iNOS protein at 2.5±20 mg/mL. However, iNOS enzyme activity was stimulated with LPS for 12 h and sphondin was administered (20 mg/mL) for 24 h, which did not reasonably inhibit iNOS enzyme activity. l-NAME (100 mM), a known specific inhibitor of iNOS, was employed as a positive control with the same protocol and showed more than 50% inhibition activity. The results demonstrate that the NO production inhibitory activity of sphondin is due to the effect of iNOS expression, but not by direct inhibition of iNOS enzyme activity. Thus, sphondin may act as a potent inhibitor of NO production under tissue-damaging inflammatory conditions.
S-Methylisothiourea Sulfate, A Potent And Selective Inhibitor Of Inducible Nitric Oxide Synthase
Non-isoform-selective inhibition of NO formation, however, may lead to side effects by inhibiting the constitutive isoform of NOS and, thus, the various physiological actions of NO. S-Methylisothiourea sulfate (SMT) is at least 10- to 30-fold more potent as an inhibitor of inducible NOS (iNOS) in immuno-stimulated cultured macrophages (EC50, 6 ,AM) and vascular smooth muscle cells (EC50, 2 ,uM) than NG-methyl-L-arginine (MeArg) or any other NOS inhibitor yet known. The effect of SMT on iNOS activity can be reversed by excess L-arginine in a concentration-dependent manner.

Enhanced formation of NO following the induction of iNOS contributes importantly to the circulatory failure (hypotension and vascular hyporeactivity to vasoconstrictor agents) in circulatory shock of various etiologies.
SMT dose-dependently reverses (0.01-3 mg/kg) the hypotension and the vascular hyporeactivity to vasoconstrictor agents caused by endotoxin [bacterial lipopolysaccharide]
SMT, a potent and selective inhibitor of iNOS, may have considerable value in the therapy of circulatory shock of various etiologies and other pathophysiological conditions associated with induction of iNOS.
SMT, or other iNOS-selective inhibitors, are likely to have fewer side effects which are related to the inhibition of eNOS, such as excessive vasoconstriction and organ ischemia), increased platelet and neutrophil adhesion and accumulation, and microvascular leakage.

Iron Chelates Bind Nitric Oxide

Nitric oxide (NO), a short-lived potent vasodilator, was first described as the endothelium-derived relaxation factor (EDRF). The formation of NO from the guanidine nitrogen group of L-arginine is catalyzed by a group of enzymes termed constitutive (cNOs) and inducible (iNOs) NO synthases. The inducible form is not present constitutively in mammalian cells but is induced by proinflammatory stimuli such as bacterial lipopolysaccharide (LPS), Corynebacterium parvum, and the cytokines tumor necrosis factor-a, interleukin-1, or interferon-y, individually or in combination. Excess production of NO is reported to be associated with the development of hypotension associated with endotoxemia and sepsis.

Electrochemical studies show that FeIII-(DTPA)2- binds NO stoichiometrically upon reduction to iron(II) at biologically relevant potentials to form a stable NO adduct. In contrast, FeI”I(HDFB)+ is a stable and efficient electrocatalyst for the reduction of NO to N20 at biologically relevant potentials. These results suggest that the mechanism of protection against death by septic shock involves NO scavenging and that particularly effective drugs that operate a low dosages may be designed based on the principle of redox catalysis. These complexes constitute a new family of drugs that rely on the special ability of transition metals to activate small molecules.

Iron complexes could act as general NO scavengers and provide protection against septic shock. Iron complexes are capable of forming relatively stable NO adducts. Metal complexes, and in particular iron chelators, could act as “molecular sponges,” mopping up the excess NO produced during septic shock. Iron chelators can sequester and (as for 2) catalyze conversion of NO to benign products. Demonstration of mechanistic aspects of septic shock protection in vivo, including interaction with other free radicals, may be hampered by the detection limits of current analytical techniques. To detect the NO Fe-DETC complex formation in livers of LPS-treated mice by the electron paramagnetic resonance.

After screening a library of metal chelators and chelates [Fe(III)(H2DTPA)] and [Fe(III)(HDFB)]+ offered the highest mortality decrease in an experimental model of septic shock. The Fe(II) form of both complexes can bind NO, which appears to be related to their biological function.
Survival was greatly enhanced by the administration of 4 or 2 either 2 h before and at the time of or 30 min after LPS. In contrast, the Fe3+-free ligands of these compounds, 3 and 1, were less protective when administered before and at the time of LPS and virtually ineffective when administered after LPS. The clear advantage of 4 over 2 when administered after LPS was observed over a large number of experiments [76% survival with 4 (n = 102 mice) and 38% survival with 2 (n =64 mice)].

The hydroxamic acid siderophore ferrioxamine B [Fe”‘(HDFB)+] and the iron complex of diethylene-triamine-pentaacetic acid [FeI”(DTPA)2i] protected mice against death by septic shock induced by Corynebacterium parvum + lipopolysaccharide. Although Fem(DTPA)2- was somewhat more effective than FeI”(HDFB)+, the iron-free ligand H4DFB+ was significantly more effective than DTPA. The hydroxamic acid chelator has a much higher iron affinity than the amine carboxylate, allowing for more efficient formation of the FeI”(HDFB)+ complex upon administration of the iron-free ligand.

Efficacy of Treatment With the Iron (III) Complex of Diethylenetriamine Pentaacetic Acid

Bacteremia and septic shock also are associated with overproduction of free radicals such as hydroxyl, superoxide, and carbon- and oxygen-centered radicals. In addition, nitric oxide (NO) overproduction is at least partly responsible for the vasodilation that causes a reduction in mean systemic arterial pressure (MSAP) and organ perfusion pressure during septic shock. This overproduction of NO likely results from early activation of the endothelial constitutive form of NO synthase followed by induction of the inducible form of NO synthase via TNF and IL-1.
The simultaneous increase and further reaction of NO with superoxide, which yields the oxidant peroxynitrite anion, occurs in cellular systems in response to inflammatory mediators. In addition, in sepsis-associated adult respiratory distress syndrome (ARDS), the presence of nitrotyrosine residues (formed by reaction of peroxynitrite and the tyrosine residues of proteins) are apparent throughout the lung.

Administration of the iron (III) complex of diethylenetriamine pentaacetic acid (DTPA iron (III), prevented death in Corynebacterium parvum 1 LPS-treated mice. Using electrochemistry, the binding of NO to DTPA iron (II) is confirmed. The DTPA iron (II) form can be easily formed by common biological reductants, because the potential for the iron (III/II) couple is E = 0.22.
Treatment with DTPA iron (III) resulted in a significant decrease in mortality compared to the untreated controls. The efficacy of DTPA iron (III) increased when given to mice 2 h or more after infection. The best results were observed when DTPA iron (III) was given 5 h after infection.

The iron (III) complex of diethylenetriamine pentaacetic acid (DTPA iron [III]) protected mice and baboons from the lethal effects of an infusion with live LD 100 Escherichia coli. In mice, optimal results were obtained when DTPA iron (III) was administered two or more hours after infection. Prevention of death occurred in spite of the fact that the adverse effects of TNFa were well underway in the mouse model.
In septic baboons, survival was observed after administration of two doses of DTPA iron (III) at 2.125 mg/kg, the first one given before, or as late as 2 h after, severe hypotension. Administration of DTPA iron (III) did not alter mean systemic arterial pressure, but did protect baboons in the presence of high levels of TNFa and free radical overproduction. Furthermore, exaggerated production of nitric oxide was attenuated. Because of its ability to interact in vitro with free radicals, its poor cell permeability, and its short half-life, we postulate that DTPA iron (III) and/or its reduced form may have protected the mice and baboons by sequestration and subsequent elimination of free radicals (including nitric oxide) from their systems. (J. Clin. Invest.1996. 98:192–198.)
Inhibitor of Poly(Adenosine 5′-Diphosphate-Ribose) Synthetase
Poly(adenosine 5′-diphosphate [ADP]-ribose) synthetase (PARS) is a nuclear enzyme which, when activated by DNA singlestrand breaks, initiates an energy-consuming, inefficient metabolic cycle by transferring ADP-ribose units to nuclear proteins. The result of this process is a rapid depletion of intracellular oxidized nicotinamide adenine dinucleotide and adenosine 5′-triphosphate energetic pools, which slows the rate of glycolysis and mitochondrial respiration, leading to cellular dysfunction and death.
Reactive oxygen-centered radicals (superoxide, hydroxyl radicals, singlet oxygen, and hydrogen peroxide) and peroxynitrite (a reactive oxidant produced from the reaction of superoxide and nitric oxide) are powerful triggers of DNA single strand breakage, and they induce activation of a cell suicide cycle governed by PARS in various cell types in vitro.

Multiple reports implicated a role of PARS activation in the pathophysiology of endotoxic shock, hemorrhagic shock, and various forms of ischemia-reperfusion injury.
Twenty pigs were chronically instrumented with intracardiac transducers to measure left ventricular pressure, sonomicrometer crystals in the left ventricle to measure short axis diameter, an ultrasonic flow meter to measure cardiac output, and catheters in the pulmonary artery and aorta to measure blood pressures and collect samples. By using a randomized study design, either the novel potent PARS inhibitor PJ34 (10 mg/kg for 1 hr, 2 mg·kg 1·hr 1 for 96 hrs) or placebo to pigs immediately before intraperitoneal implantation of Escherichia coli 0111.B4 (2.3 0.1 1010 colony-forming units/kg)-laden fibrin clots to produce peritonitis and bacteremia.
PJ34 treatment significantly attenuated this cytokine response. The formation of peroxynitrite and the activation of PARS were confirmed in hearts and lungs of the septic pigs by the immunohistochemical detection of nitrotyrosine and poly(ADP-ribose), respectively. Inhibition of PARS with PJ34 abolished poly(ADP-ribose) formation in septic animals.

Cardiac inotropicity was evaluated by analysis of percentage of short axis diameter shortening (one-dimensional ejection fraction). Bacteremia induced a rapid and progressive loss of inotropy until death in vehicle-treated pigs. A similar decline was observed in the first 6 hrs in PJ34 pigs. This decline was reversed on all subsequent days. Control pigs exhibited rapid and significant increases in systemic vascular (SVR) and pulmonary vascular (PVR) resistances.
This experimental model mimics many aspects of the human sepsis syndrome. Therefore, the positive survival benefit of PARS inhibition suggests a potential utility of PARS inhibitors in human sepsis management. PARS activation is triggered by DNA single-strand breakage.

The current work, demonstrating increased poly(ADP-ribose) staining in the heart of septic pigs, may point toward the importance of a myocardial, PARS dependent cardiodepressive mechanism in the current model of shock. This hypothesis is supported by the following findings:

  • free radicals cause myocardial dysfunction and injury in a PARS dependent fashion in vitro;
  • in the current study, pharmacologic inhibition of PARS with PJ34 markedly improved myocardial function; and

in prior studies, pharmacologic inhibition of PARS markedly improved myocardial contractile function in hypoxic-reoxygenated hearts as well as in a porcine model of hemorrhagic shock.
Treatment with a potent PARS inhibitor improved survival and cardiovascular status and attenuated an important mediator component of the inflammatory response in a lethal porcine model of sepsis. (Crit Care Med 2002; 30:974 –980).

Decrease of the inflammatory response and induction of the Akt/protein kinase B pathway by poly-(ADP-ribose) polymerase 1 inhibitor

The lack of efficacy of anti-inflammatory drugs, anti-coagulants, anti-oxidants, etc. in critically ill patients has shifted interest towards developing alternative treatments. Since inhibitors of the nuclear enzyme poly-(ADP-ribose) polymerase (PARP) were found to be beneficial in many pathophysiological conditions associated with oxidative stress and PARP-1 knock-out mice proved to be resistant to bacterial lipopolysaccharide (LPS)-induced septic shock, PARP. The mechanism of the protective effect of a potent PARP-1 inhibitor, PJ34 was studied in LPS-induced (20 mg/kg, i.p.) septic shock in mice.

We demonstrated a significant inflammatory response by magnetic resonance imaging in the dorsal subcutaneous region, in the abdominal regions around the kidneys and in the inter-intestinal cavities. We have found necrotic and apoptotic histological changes as well as obstructed blood vessels in the liver and small intestine. Additionally, we have detected elevated tumor necrosis factor-a levels in the serum and nuclear factor kappa B activation in liver of LPS-treated mice.

Pre-treating the animals with PJ34 (10 mg/kg, i.p.), before the LPS challenge, besides rescuing the animals from LPS-induced death, attenuated all these changes presumably by activating the phosphatidylinositol 3-kinase–Akt/protein kinase B cytoprotective pathway.

PJ34, a novel, potent PARP-1 inhibitor was found to protect against LPS induced tissue damage. PARP inhibitors protected Langendorff-perfused hearts against ischemia-reperfusion induced damages by activating the PI3-kinase–Akt pathway. The importance of the PI3-kinase–Akt pathway in LPS induced inflammatory mechanisms has gained support, raising the question whether this pathway was involved in the effect of PJ34 on LPS-induced septic shock.
Among all the observed LPS-induced inflammatory responses, we found the most characteristic and most pronounced increases in the gastro-intestinal tract, but no signal increase could be observed inside the kidneys and in skeletal muscle, in the paravertebral or in the femoral muscle. All increases in signal intensities were significantly attenuated in mice treated with PJ34.

Effect of PJ34 on survival of LPS-treated mice

  • PARP-1 inhibitor significantly protected the animals against LPS-induced death, with 86 and 43% surviving mice, respectively.
  • PJ34 treatment itself did not induce death or any obvious damage.

Effect of PJ34 on LPS-induced NF-kB activation

LPS treatment in the lung caused a significant increase in NF-kB activation that was slightly but not statistically significantly attenuated by PJ34 pre-treatment.
in contrast to the lung, NF-kB activation in the liver was prevented by PJ34 pre-treatment
The other tissue with observable LPS-induced pathological changes was the small intestine. Atrophy of villi may reflect the diarrhea observed in the LPS-treated animals and is in agreement with the results of Abreu et al. who found a Fas-mediated apoptosis in intestinal epithelial cells that was sensitised by inhibitors of PI3-kinase and opposed by expressing constitutively active Akt.
Pre-treatment of the animals with a novel, potent PARP-1 inhibitor, PJ34, diminished the thoracic and abdominal inflammatory responses as revealed by T2 imaging, and abolished the above mentioned pathological changes.
The protective role of PARP inhibitors in septic shock is likely to be more complex than merely the regulation of NF-kB/Rel-dependent gene expression.
Activation of the PI3-kinase–Akt/protein kinase B cytoprotective pathway is likely to contribute to the protective effects of PARP inhibitors in shock and inflammation.

Carboxy-PTIO On Hemodynamic And Blood Gas Changes

Infusion of LPS caused a marked decrease in mean arterial pressure (MAP), metabolic acidosis, and hypoxia. These effects were reversed by co-administration of carboxy-PTIO, without affecting other hemodynamic parameters. In control animals, neither hemodynamic nor blood gas parameters changed with or without carboxy-PTIO.
These results indicate that carboxy-PTIO attenuates

  • LPS-induced hypotension,
  • metabolic acidosis, and
  • hypoxia

by scavenging excess NO from the circulation without affecting NO synthase (NOS) activity. An NO scavenger, carboxy-PTIO, may be preferable to non-selective NOS inhibitors for the treatment of human septic shock.

Asymmetrical Dimethyl Arginine Levels

Overwhelming infection with resultant multiple organ failure, which has been termed the ‘sepsis syndrome’ , is a devastating illness with an incidence of 3 per 1,000 population per annum. It has been characterised as a dysregulation of inflammation in response to infection attributable to a combination of

  • excessive inflammation,
  • disseminated coagulopathy and
  • disruption of the integrity of microvascular endothelium.

Asymmetrical dimethyl arginine (ADMA) is an endogenous non-selective inhibitor of nitric oxide synthase that may influence the severity of organ failure and the occurrence of shock secondary to an infectious insult. Levels may be genetically determined by a promoter polymorphism in a regulatory gene encoding dimethylarginine dimethylaminohydrolase II (DDAH II).

A prospective observational study was designed, and 47 intensive care unit (ICU) patients with severe sepsis and 10 healthy controls were enrolled. Serum ADMA and IL-6 were assayed on admission to the ICU and seven days later. Allelic variation for a polymorphism at position -449 in the DDAH II gene was assessed in each patient.
ADMA levels and Sequential Organ Failure Assessment scores were directly associated on day one (p = 0.0001) and day seven (p = 0.002). The degree of acidaemia and lactaemia was directly correlated with ADMA levels at both time points (p < 0.01). On day seven, IL-6 was directly correlated with ADMA levels (p = 0.006). The variant allele with G at position -449 in the DDAH II gene was associated with increased ADMA concentrations at both time points (p < 0.05).
Severity of organ failure, inflammation and presence of early shock in severe sepsis are associated with increased ADMA levels. ADMA concentrations may be influenced by a polymorphism in the DDAH II gene.

Several studies have added to the confusion surrounding the role of NO by demonstrating no effect of NO or NOS inhibition on the myocardium or on b-adrenergic responsiveness. Nevertheless, in most studies,

  • low-to-moderate doses of iNOS inhibitors restore myocardial contractility in hearts exposed to proinflammatory cytokines, whereas
  • at higher doses, the effects are reversed.

This finding may indicate that small amounts of NO produced by iNOS may be necessary to maintain contractility and can be cardio-protective in experimental sepsis.

English: Major cellular sources of ROS in livi...

Major cellular sources of ROS in living cells. Novo and Parola Fibrogenesis & Tissue Repair 2008 1:5 doi:10.1186/1755-1536-1-5 (Photo credit: Wikipedia)

References

  1. VM Victor, K J McCreath and M Rochaa. Recent Progress in Pharmacological Research of Antioxidants in Pathological Conditions: Cardiovascular Health. Recent Patents on Anti-Infective Drug Discovery, 2006, 1, 17-31 17.
  2. G Cottera, E Kaluskia, O Miloa, A Blatta, et al. LINCS: L-NAME (a NO synthase inhibitor) In the treatment of refractory Cardiogenic Shock. A prospective randomized study. The European Society of Cardiology. 2012. doi:10.1016/S0195-668X(03)00193-3 http://eurheartj.oxfordjournals.org/
  3. Ve Laubach, Eg Shesely, O Smithies, Pa Sherman. Mice lacking inducible nitric oxide synthase are not resistant to lipopolysaccharide-induced death. Proc. Natl. Acad. Sci. USA 1995; 92:10688-10692, Genetics
  4. NS Shah and TR Billiar. Role of Nitric Oxide in Inflammation and Tissue Injury during Endotoxemia and Hemorrhagic Shock. Environ Health Perspect 106(Suppl 5):1139-1143 (1998). http://ehpnetl.niehs.nih.gov/docs/1998/Suppl-5/1139-1 143shah/abstract.html
  5. CC Wang, JE Lai, LG Chen, KY Yen, et al. Inducible Nitric Oxide Synthase Inhibitors of Chinese Herbs. Part 2: Naturally Occurring Furanocoumarins’. Bioorganic & Medicinal Chemistry 2000; 8:2701-2707.
  6. MJ O’Dwyer, F Dempsey, V Crowley, DP Kelleher, R McManus, T Ryan. Septic shock is correlated with asymmetrical dimethyl arginine levels, which may be influenced by a polymorphism in the dimethylarginine dimethylaminohydrolase II gene: a prospective observational study. Critical Care 2006; 10:R139 (doi:10.1186/cc5053) http://ccforum.com/content/10/5/R139
  7. C Szab, Gj Southan, And C Thiemermann. Beneficial effects and improved survival in rodent models of septic shock with S-methylisothiourea sulfate, a potent and selective inhibitor of inducible nitric oxide synthase. Proc. Natl. Acad. Sci. USA 1994; 91:12472-12476. Pharmacology
  8. Wm Kazmierski, G Wolberg, Jgwilson, et al. Iron chelates bind nitric oxide and decrease mortality in an experimental model of septic shock. Proc. Natl. Acad. Sci. USA 1996;93:9138-9141.
  9. L Molina, S Studenberg, G Wolberg, W Kazmierski, et al. Efficacy of Treatment With the Iron (III) Complex of Diethylenetriamine Pentaacetic Acid in Mice and Primates Inoculated With Live Lethal Dose 100 Escherichia coli. J. Clin. Invest 1996; 98(1): 192-198. 0021-9738/96/07/192/07
  10. N Kayhan, B Funke, LO Conzelmann, H Winkler, et al. The adenosine deaminase inhibitor erythro-9-[2-hydroxyl-3-nonyl]-adenine decreases intestinal permeability and protects against experimental sepsis: a prospective, randomised laboratory investigation. Critical Care 2008, 12:R125 (doi:10.1186/cc7033) http://ccforum.com/content/12/5/R125
  11. RD Goldfarb, A Marton, É Szabó, L Virág, et al.. Protective effect of a novel, potent inhibitor of poly(adenosine 5′-diphosphate-ribose) synthetase in a porcine model of severe bacterial sepsis. Crit Care Med 2002; 30:974 –980.
  12. B Veres, F Gallyas Jr, G Varbiro, Z Berente, et al. Decrease of the inflammatory response and induction of the Akt/protein kinase B pathway by poly-(ADP-ribose) polymerase 1 inhibitor in endotoxin-induced septic shock. Biochemical Pharmacology 2003; 65: 1373–1382.
  13. C Martinez, C Abad, M Delgado, A Arranz, et al. Anti-inflammatory role in septic shock of pituitary adenylate cyclase-activating polypeptide receptor. PNAS 2002; 99(2):1053–1058. doi 10.1073 pnas.012367999
  • endogenously produced VIP and PACAP are participants of the natural anti-inflammatory machinery.
  • VIP and PACAP are two attractive candidates for the development of therapies against acute and chronic inflammatory diseases, septic shock, and autoimmune diseases

Read Full Post »

Curator and Reporter: Aviral Vatsa PhD, MBBS

Based on: A review by Wink et al., 2011

This is the first part of a two part post

Nitric oxide (NO), reactive nitrogen species (RNS) and reactive oxygen species (ROS) perform dual roles as immunotoxins and immunomodulators. An incoming immune signal initiates NO and ROS production both for tackling the pathogens and modulating the downstream immune response via complex signaling pathways. The complexity of these interactions is a reflection of involvement of redox chemistry in biological setting (fig. 1)

Fig 1. Image credit: (Wink et al., 2011)

Previous studies have highlighted the role of NO in immunity. It was shown that macrophages released a substance that had antitumor and antipathogen activity and required arginine for its production (Hibbs et al., 1987, 1988). Hibbs and coworkers further strengthened the connection between immunity and NO by demonstrating that IL2 mediated immune activation increased NO levels in patients and promoted tumor eradication in mice (Hibbs et al., 1992; Yim et al., 1995).

In 1980s a number of authors showed the direct evidence that macrophages made nitrite, nitrates and nitrosamines. It was also shown that NO generated by macrophages could kill leukemia cells (Stuehr and Nathan, 1989). Collectively these studies along with others demonstrated the important role NO plays in immunity and lay the path for further research in understanding the role of redox molecules in immunity.

NO is produced by different forms of nitric oxide synthase (NOS) enzymes such as eNOS (endothelial), iNOS (inducible) and nNOS (neuronal). The constitutive forms of eNOS generally produce NO in short bursts and in calcium dependent manner. The inducible form produces NO for longer durations and is calcium independent. In immunity, iNOS plays a vital role. NO production by iNOS can occur over a wide range of concentrations from as little as nM to as much as µM. This wide range of NO concentrations provide iNOS with a unique flexibility to be functionally effective in various conditions and micro-environements and thus provide different temporal and concentration profiles of NO, that can be highly efficient in dealing with immune challenges.

Redox reactions in immune responses

NO/RNS and ROS are two categories of molecules that bring about immune regulation and ‘killing’ of pathogens. These molecules can perform independently or in combination with each other. NO reacts directly with transition metals in heme or cobalamine, with non-heme iron, or with reactive radicals (Wink and Mitchell, 1998). The last reactivity also imparts it a powerful antioxidant capability. NO can thus act directly as a powerful antioxidant and prevent injury initiated by ROS (Wink et al., 1999). On the other hand, NO does not react directly with thiols or other nucleophiles but requires activation with superoxide to generate RNS. The RNS species then cause nitrosative and oxidative stress (Wink and Mitchell, 1998).

The variety of functions achieved by NO can be understood if one looks at certain chemical concepts. NO and NO2 are lipophilic and thus can migrate through cells, thus widening potential target profiles. ONOO-, a RNS, reacts rapidly with CO2 that shortens its half life to <10 ms. The anionic form and short half life limits its mobility across membranes. When NO levels are higher than superoxide levels, the CO2-OONO–intermediate is converted to NO2 and N2O3 and changes the redox profile from an oxidative to a nitrosative microenvironment. The interaction of NO and ROS determines the bioavailability of NO and proximity of RNS generation to superoxide source, thus defining a reaction profile. The ROS also consumes NO to generate NO2 and N2O3 as well as nitrite in certain locations. The combination of these reactions in different micro-environments provides a vast repertoire of reaction profiles for NO/RNS and ROS entities.

The Phagosome ‘cauldron’

The phagosome provides an ‘isolated’ environment for the cell to carry out foreign body ‘destruction’. ROS, NO and RNS interact to bring about redox reactions. The concentration of NO in a phagosome can depend on the kind of NOS in the vicinity and its activity and other localised cellular factors. NO and is metabolites such as nitrites and nitrates along with ROS combine forces to kill pathogens in the acidic environment of the phagosome as depicted in the figure 2 below.

Fig 2. The NO chemistry of the phagosome. (image credit: (Wink et al., 2011)

This diagram depicts the different nitrogen oxide and ROS chemistry that can occur within the phagosome to fight pathogens. The presence of NOX2 in the phagosomes serves two purposes: one is to focus the nitrite accumulation through scavenging mechanisms, and the second provides peroxide as a source of ROS or FA generation. The nitrite (NO2−) formed in the acidic environment provides nitrosative stress with NO/NO2/N2O3. The combined acidic nature and the ability to form multiple RNS and ROS within the acidic environment of the phagosome provide the immune response with multiple chemical options with which it can combat bacteria.

Bacteria

There are various ways in which NO combines forces with other molecules to bring about bacterial killing. Here are few examples

E.coli: It appears to be resistant to individual action of NO/RNS and H2O2 /ROS. However, when combined together, H2O2 plus NO mediate a dramatic, three-log increase in cytotoxicity, as opposed to 50% killing by NO alone or H2O2 alone. This indicates that these bacteria are highly susceptible to their synergistic action.

Staphylococcus: The combined presence of NO and peroxide in staphylococcal infections imparts protective effect. However, when these bacteria are first exposed to peroxide and then to NO there is increased toxicity. Hence a sequential exposure to superoxide/ROS and then NO is a potent tool in eradicating staphylococcal bacteria.

Mycobacterium tuberculosis: These bacterium are sensitive to NO and RNS, but in this case, NO2 is the toxic species. A phagosome microenvironment consisting of ROS combined with acidic nitrite generates NO2/N2O3/NO, which is essential for pathogen eradication by the alveolar macrophage. Overall, NO has a dual function; it participates directly in killing an organism, and/or it disarms a pathway used by that organism to elude other immune responses.

Parasites

Many human parasites have demonstrated the initiation of the immune response via the induction of iNOS, that then leads to expulsion of the parasite. The parasites include Plasmodia(malaria), Leishmania(leishmaniasis), and Toxoplasma(toxoplasmosis). Severe cases of malaria have been related with increased production of NO. High levels of NO production are however protective in these cases as NO was shown to kill the parasites (Rockett et al., 1991; Gyan et al., 1994). Leishmania is an intracellualr parasite that resides in the mamalian macrophages. NO upregulation via iNOS induction is the primary pathway involved in containing its infestation. A critical aspect of NO metabolism is that NOHA inhibits AG activity, thereby limiting the growth of parasites and bacteria including Leishmania, Trypanosoma, Schistosoma, Helicobacter, Mycobacterium, and Salmonella, and is distinct from the effects of RNS. Toxoplasma gondii is also an intracellular parasite that elicits NO mediated response. INOS knockout mice have shown more severe inflammatory lesions in the CNS that their wild type counterparts, in response to toxoplasma exposure. This indicates the CNS preventative role of iNOS in toxoplasmosis (Silva et al., 2009).

Virus

Viral replication can be checked by increased production of NO by induction of iNOS (HIV-1, coxsackievirus, influenza A and B, rhino virus, CMV, vaccinia virus, ectromelia virus, human herpesvirus-1, and human parainfluenza virus type 3) (Xu et al., 2006). NO can reduce viral load, reduce latency and reduce viral replication. One of the main mechanisms as to how NO participates in viral eradication involves the nitrosation of critical cysteines within key proteins required for viral infection, transcription, and maturation stages. For example, viral proteases or even the host caspases that contain cysteines in their active site are involved in the maturation of the virus. The nitrosative stress environment produced by iNOS may serve to protect against some viruses by inhibiting viral infectivity, replication, and maturation.

To be continued in part 2 …

Bibliography

Gyan, B., Troye-Blomberg, M., Perlmann, P., Björkman, A., 1994. Human monocytes cultured with and without interferon-gamma inhibit Plasmodium falciparum parasite growth in vitro via secretion of reactive nitrogen intermediates. Parasite Immunol. 16, 371–3

Hibbs, J.B., Jr, Taintor, R.R., Vavrin, Z., 1987. Macrophage cytotoxicity: role for L-arginine deiminase and imino nitrogen oxidation to nitrite. Science 235, 473–476.

Hibbs, J.B., Jr, Taintor, R.R., Vavrin, Z., Rachlin, E.M., 1988. Nitric oxide: a cytotoxic activated macrophage effector molecule. Biochem. Biophys. Res. Commun. 157, 87–94.

Hibbs, J.B., Jr, Westenfelder, C., Taintor, R., Vavrin, Z., Kablitz, C., Baranowski, R.L., Ward, J.H., Menlove, R.L., McMurry, M.P., Kushner, J.P., 1992. Evidence for cytokine-inducible nitric oxide synthesis from L-arginine in patients receiving interleu

Rockett, K.A., Awburn, M.M., Cowden, W.B., Clark, I.A., 1991. Killing of Plasmodium falciparum in vitro by nitric oxide derivatives. Infect Immun 59, 3280–3283.

Stuehr, D.J., Nathan, C.F., 1989. Nitric oxide. A macrophage product responsible for cytostasis and respiratory inhibition in tumor target cells. J. Exp. Med. 169, 1543–1555.

Wink, D.A., Hines, H.B., Cheng, R.Y.S., Switzer, C.H., Flores-Santana, W., Vitek, M.P., Ridnour, L.A., Colton, C.A., 2011. Nitric oxide and redox mechanisms in the immune response. J Leukoc Biol 89, 873–891.

Wink, D.A., Mitchell, J.B., 1998. Chemical biology of nitric oxide: Insights into regulatory, cytotoxic, and cytoprotective mechanisms of nitric oxide. Free Radic. Biol. Med. 25, 434–456.

Wink, D.A., Vodovotz, Y., Grisham, M.B., DeGraff, W., Cook, J.C., Pacelli, R., Krishna, M., Mitchell, J.B., 1999. Antioxidant effects of nitric oxide. Meth. Enzymol. 301, 413–424.

Xu, W., Zheng, S., Dweik, R.A., Erzurum, S.C., 2006. Role of epithelial nitric oxide in airway viral infection. Free Radic. Biol. Med. 41, 19–28.

Yim, C.Y., McGregor, J.R., Kwon, O.D., Bastian, N.R., Rees, M., Mori, M., Hibbs, J.B., Jr, Samlowski, W.E., 1995. Nitric oxide synthesis contributes to IL-2-induced antitumor responses against intraperitoneal Meth A tumor. J. Immunol. 155, 4382–4390.

Further reading on NO:

Nitric Oxide in bone metabolism July 16, 2012

Author: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/07/16/nitric-oxide-in-bone-metabolism/?goback=%2Egde_4346921_member_134751669

Nitric Oxide production in Systemic sclerosis July 25, 2012

Curator: Aviral Vatsa, PhD, MBBS

http://pharmaceuticalintelligence.com/2012/07/25/nitric-oxide-production-in-systemic-sclerosis/?goback=%2Egde_4346921_member_138370383

Nitric Oxide Signalling Pathways August 22, 2012 by

Curator/ Author: Aviral Vatsa, PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/22/nitric-oxide-signalling-pathways/?goback=%2Egde_4346921_member_151245569

Nitric Oxide: a short historic perspective August 5, 2012

Author/Curator: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/05/nitric-oxide-a-short-historic-perspective-7/

Nitric Oxide: Chemistry and function August 10, 2012

Curator/Author: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/10/nitric-oxide-chemistry-and-function/?goback=%2Egde_4346921_member_145137865

Nitric Oxide and Platelet Aggregation August 16, 2012 by

Author: Dr. Venkat S. Karra, Ph.D.

http://pharmaceuticalintelligence.com/2012/08/16/no-and-platelet-aggregation/?goback=%2Egde_4346921_member_147475405

The rationale and use of inhaled NO in Pulmonary Artery Hypertension and Right Sided Heart Failure August 20, 2012

Author: Larry Bernstein, MD

http://pharmaceuticalintelligence.com/2012/08/20/the-rationale-and-use-of-inhaled-no-in-pulmonary-artery-hypertension-and-right-sided-heart-failure/

Nitric Oxide: The Nobel Prize in Physiology or Medicine 1998 Robert F. Furchgott, Louis J. Ignarro, Ferid Murad August 16, 2012

Reporter: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/08/16/nitric-oxide-the-nobel-prize-in-physiology-or-medicine-1998-robert-f-furchgott-louis-j-ignarro-ferid-murad/

Coronary Artery Disease – Medical Devices Solutions: From First-In-Man Stent Implantation, via Medical Ethical Dilemmas to Drug Eluting Stents August 13, 2012

Author: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/08/13/coronary-artery-disease-medical-devices-solutions-from-first-in-man-stent-implantation-via-medical-ethical-dilemmas-to-drug-eluting-stents/

Nano-particles as Synthetic Platelets to Stop Internal Bleeding Resulting from Trauma

August 22, 2012

Reported by: Dr. V. S. Karra, Ph.D.

http://pharmaceuticalintelligence.com/2012/08/22/nano-particles-as-synthetic-platelets-to-stop-internal-bleeding-resulting-from-trauma/

Cardiovascular Disease (CVD) and the Role of agent alternatives in endothelial Nitric Oxide Synthase (eNOS) Activation and Nitric Oxide Production July 19, 2012

Curator and Research Study Originator: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/07/19/cardiovascular-disease-cvd-and-the-role-of-agent-alternatives-in-endothelial-nitric-oxide-synthase-enos-activation-and-nitric-oxide-production/

Macrovascular Disease – Therapeutic Potential of cEPCs: Reduction Methods for CV Risk

July 2, 2012

An Investigation of the Potential of circulating Endothelial Progenitor Cells (cEPCs) as a Therapeutic Target for Pharmacological Therapy Design for Cardiovascular Risk Reduction: A New Multimarker Biomarker Discovery

Curator: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/07/02/macrovascular-disease-therapeutic-potential-of-cepcs-reduction-methods-for-cv-risk/

Bone remodelling in a nutshell June 22, 2012

Author: Aviral Vatsa, Ph.D., MBBS

http://pharmaceuticalintelligence.com/2012/06/22/bone-remodelling-in-a-nutshell/

Targeted delivery of therapeutics to bone and connective tissues: current status and challenges- Part, September  

Author: Aviral Vatsa, PhD, September 23, 2012

http://pharmaceuticalintelligence.com/2012/09/23/targeted-delivery-of-therapeutics-to-bone-and-connective-tissues-current-status-and-challenges-part-i/

Calcium dependent NOS induction by sex hormones: Estrogen

Curator: S. Saha, PhD, October 3, 2012

http://pharmaceuticalintelligence.com/2012/10/03/calcium-dependent-nos-induction-by-sex-hormones/

Nitric Oxide and Platelet Aggregation,

Author V. Karra, PhD, August 16, 2012

http://pharmaceuticalintelligence.com/2012/08/16/no-and-platelet-aggregation/

Bystolic’s generic Nebivolol – positive effect on circulating Endothelial Progenitor Cells endogenous augmentation

Curator: Aviva Lev-Ari, PhD, July 16, 2012

http://pharmaceuticalintelligence.com/?s=Nebivolol

Endothelin Receptors in Cardiovascular Diseases: The Role of eNOS Stimulation

Author: Aviva Lev-Ari, PhD, 10/4/2012

http://pharmaceuticalintelligence.com/2012/10/04/endothelin-receptors-in-cardiovascular-diseases-the-role-of-enos-stimulation/

Inhibition of ET-1, ETA and ETA-ETB, Induction of NO production, stimulation of eNOS and Treatment Regime with PPAR-gamma agonists (TZD): cEPCs Endogenous Augmentation for Cardiovascular Risk Reduction – A Bibliography

Curator: Aviva Lev-Ari, 10/4/2012.

http://pharmaceuticalintelligence.com/2012/10/04/inhibition-of-et-1-eta-and-eta-etb-induction-of-no-production-and-stimulation-of-enos-and-treatment-regime-with-ppar-gamma-agonists-tzd-cepcs-endogenous-augmentation-for-cardiovascular-risk-reduc/

Nitric Oxide Nutritional remedies for hypertension and atherosclerosis. It’s 12 am: do you know where your electrons are?

Author and Reporter: Meg Baker, 10/7/2012.

http://pharmaceuticalintelligence.com/2012/10/07/no-nutritional-remedies-for-hypertension-and-atherosclerosis-its-12-am-do-you-know-where-your-electrons-are/


Read Full Post »

Author and Curator: Ritu Saxena, Ph.D.

Screen Shot 2021-07-19 at 7.09.49 PM

Word Cloud By Danielle Smolyar

Introduction

Nitric oxide (NO) is a lipophilic, highly diffusible and short-lived molecule that acts as a physiological messenger and has been known to regulate a variety of important physiological responses including vasodilation, respiration, cell migration, immune response and apoptosis. Jordi Muntané et al

NO is synthesized by the Nitric Oxide synthase (NOS) enzyme and the enzyme is encoded in three different forms in mammals: neuronal NOS (nNOS or NOS-1), inducible NOS (iNOS or NOS-2), and endothelial NOS (eNOS or NOS-3). The three isoforms, although similar in structure and catalytic function, differ in the way their activity and synthesis in controlled inside a cell. NOS-2, for example is induced in response to inflammatory stimuli, while NOS-1 and NOS-3 are constitutively expressed.

Regulation by Nitric oxide

NO is a versatile signaling molecule and the net effect of NO on gene regulation is variable and ranges from activation to inhibition of transcription.

The intracellular localization is relevant for the activity of NOS. Infact, NOSs are subject to specific targeting to subcellular compartments (plasma membrane, Golgi, cytosol, nucleus and mitochondria) and that this trafficking is crucial for NO production and specific post-translational modifications of target proteins.

Role of Nitric oxide in Cancer

One in four cases of cancer worldwide are a result of chronic inflammation. An inflammatory response causes high levels of activated macrophages. Macrophage activation, in turn, leads to the induction of iNOS gene that results in the generation of large amount of NO. The expression of iNOS induced by inflammatory stimuli coupled with the constitutive expression of nNOS and eNOS may contribute to increased cancer risk. NO can have varied roles in the tumor environment influencing DNA repair, cell cycle, and apoptosis. It can result in antagonistic actions including DNA damage and protection from cytotoxicity, inhibiting and stimulation cell proliferation, and being both anti-apoptotic and pro-apoptotic. Genotoxicity due to high levels of NO could be through direct modification of DNA (nitrosative deamination of nucleic acid bases, transition and/or transversion of nucleic acids, alkylation and DNA strand breakage) and inhibition of DNA repair enzymes (such as alkyltransferase and DNA ligase) through direct or indirect mechanisms. The Multiple actions of NO are probably the result of its chemical (post-translational modifications) and biological heterogeneity (cellular production, consumption and responses). Post-translational modifications of proteins by nitration, nitrosation, phosphorylation, acetylation or polyADP-ribosylation could lead to an increase in the cancer risk. This process can drive carcinogenesis by altering targets and pathways that are crucial for cancer progression much faster than would otherwise occur in healthy tissue.

NO can have several effects even within the tumor microenvironment where it could originate from several cell types including cancer cells, host cells, tumor endothelial cells. Tumor-derived NO could have several functional roles. It can affect cancer progression by augmenting cancer cell proliferation and invasiveness. Infact, it has been proposed that NO promotes tumor growth by regulating blood flow and maintaining the vasodilated tumor microenvironment. NO can stimulate angiogenesis and can also promote metastasis by increasing vascular permeability and upregulating matrix metalloproteinases (MMPs). MMPs have been associated with several functions including cell proliferation, migration, adhesion, differentiation, angiogenesis and so on. Recently, it was reported that metastatic tumor-released NO might impair the immune system, which enables them to escape the immunosurveillance mechanism of cells. Molecular regulation of tumour angiogenesis by nitric oxide.

S-nitrosylation and Cancer

The most prominent and recognized NO reaction with thiols groups of cysteine residues is called S-nitrosylation or S-nitrosation, which leads to the formation of more stable nitrosothiols. High concentrations of intracellular NO can result in high concentrations of S-nitrosylated proteins and dysregulated S-nitrosylation has been implicated in cancer. Oxidative and nitrosative stress is sensed and closely associated with transcriptional regulation of multiple target genes.

Following are a few proteins that are modified via NO and modification of these proteins, in turn, has been known to play direct or indirect roles in cancer.

NO mediated aberrant proteins in Cancer

Bcl2

Bcl-2 is an important anti-apoptotic protein. It works by inhibiting mitochondrial Cytochrome C that is released in response to apoptotic stimuli. In a variety of tumors, Bcl-2 has been shown to be upregulated, and it has additionally been implicated with cancer chemo-resistance through dysregulation of apoptosis. NO exposure causes S-nitrosylation at the two cysteine residues – Cys158 and Cys229 that prevents ubiquitin-proteasomal pathway mediated degradation of the protein. Once prevented from degradation, the protein attenuates its anti-apoptotic effects in cancer progression. The S-nitrosylation based modification of Bcl-2 has been observed to be relevant in drug treatment studies (for eg. Cisplatin). Thus, the impairment of S-nitrosylated Bcl-2 proteins might serve as an effective therapeutic target to decrease cancer-drug resistance.

p53

p53 has been well documented as a tumor suppressor protein and acts as a major player in response to DNA damage and other genomic alterations within the cell. The activation of p53 can lead to cell cycle arrest and DNA repair, however, in case of irrepairable DNA damage, p53 can lead to apoptosis. Nuclear p53 accumulation has been related to NO-mediated anti-tumoral properties. High concentration of NO has been found to cause conformational changes in p53 resulting in biological dysfunction.. In RAW264.7, a murine macrophage cell line, NO donors induce p53 accumulation and apoptosis through JNK-1/2.

HIF-1a

Hypoxia-inducible factor 1 (HIF1) is a heterodimeric transcription factor that is predominantly active under hypoxic conditions because the HIF-1a subunit is rapidly degraded in normoxic conditions by proteasomal degradation. It regulates the transciption of several genes including those involved in angiogenesis, cell cycle, cell metabolism, and apoptosis. Hypoxic conditions within the tumor can lead to overexpression of HIF-1a. Similar to hypoxia-mediated stress, nitrosative stress can stabilize HIF-1a. NO derivatives have also been shown to participate in hypoxia signaling. Resistance to radiotherapy has been traced back to NO-mediated HIF-1a in solid tumors in some cases.

PTEN

Phosphatase and tensin homolog deleted on chromosome ten (PTEN), is again a tumor suppressor protein. It is a phosphatase and has been implicated in many human cancers. PTEN is a crucial negative regulator of PI3K/Akt signaling pathway. Over-activation of PI3K/Akt mediated signaling pathway is known to play a major role in tumorigenesis and angiogenesis. S-nitrosylation of PTEN, that could be a result of NO stress, inhibits PTEN. Inhibition of PTEN phosphatase activity, in turn, leads to promotion of angiogenesis.

C-Src

C-src belongs to the Src family of protein tyrosine kinases and has been implicated in the promotion of cancer cell invasion and metastasis. It was demonstrated that S-nitrosylation of c-Src at cysteine 498 enhanced its kinase activity, thus, resulting in the enhancement of cancer cell invasion and metastasis.

Reference:

Muntané J and la Mata MD. Nitric oxide and cancer. World J Hepatol. 2010 Sep 27;2(9):337-44. http://www.ncbi.nlm.nih.gov/pubmed/21161018

Wang Z. Protein S-nitrosylation and cancer. Cancer Lett. 2012 Jul 28;320(2):123-9. http://www.ncbi.nlm.nih.gov/pubmed/22425962

Ziche M and Morbidelli L. Molecular regulation of tumour angiogenesis by nitric oxide. Eur Cytokine Netw. 2009 Dec;20(4):164-70.http://www.ncbi.nlm.nih.gov/pubmed/20167555

Jaiswal M, et al. Nitric oxide in gastrointestinal epithelial cell carcinogenesis: linking inflammation to oncogenesis. Am J Physiol Gastrointest Liver Physiol. 2001 Sep;281(3):G626-34. http://www.ncbi.nlm.nih.gov/pubmed/11518674

Read Full Post »

Author and Reporter: Meg Baker, Ph.D., Registered Patent Agent

The 1998 Noble Prize for medicine was for the discovery that nitric oxide (NO) was the chemical messenger responsible for relaxing vascular tissue and thereby increasing blood flow and reducing blood pressure. Alfred Noble himself had been prescribed nitro-glycerin for heart problems over 100 years before, a compound which is metabolized to NO.

NO, a gas at room temperature, has an exceedingly short half-life in the body. Normally, NO is produced from an amino acid, L-arginine (L-Arg), a normal component of the dietary protein, and molecular oxygen (O2) by the one of the several Nitric Oxide Synthases (EC 1.14.13.39): endothelial (eNOS, NOS III), inducible (iNOS, NOS II), and neural (nNOS, NOS I). In human studies, supplementation with l-arginine improved endothelium-dependent vasodilation.

The reaction of iNOS with L-Arg to produce NO leaves another amino acid, citrulline. Excess L-Arg can also be degraded by arginase (enzyme having two isoforms, I and II) which may be coinduced with iNOS in some cell types.

Citrulline formed as a by-product of the NOS reaction can be recycled to arginine by argininosuccinate synthetase (AS) and argininosuccinate lyase (AL).

Mori (2007)  http:// www.ncbi.nlm.nih.gov/ pubmed/ 17513437 found that AS and sometimes AL are coinduced with inducible NOS (iNOS) in various cells. In these cells, NO was synthesized from citrulline (via arginine) as well as from arginine, indicating operation of the citrulline-NO cycle.

Whereas, low concentrations of NO protect cells from apoptosis, excessive NO causes apoptosis. NO causes endoplasmic reticulum (ER) stress, induces a transcription factor, CAAT/enhancer binding protein (C/EBP) homologous protein (CHOP), and leads to apoptosis.

The active site of NOS is formed by a heme-containing substrate-binding cavity, where L-arginine (Arg) and O2 are converted to L-citrulline and NO. The electrons required for reductive O2 activation are transferred from NADPH via the NOS-bound flavins (riboflavin, Vitamin B2) FMN and FAD. All NOS isoforms are only active as homodimers.

Generation of NO occurs in two discrete O2-requiring steps, with intermediate formation of N-hydroxy-L-arginine (NHA or NOHLA). NHA formation consumes one molecule of O2 and two electrons. Conversion of NHA to L-citrulline and NO requires another molecule of O2 and one more electron (http://en.wikipedia.org/wiki/Nitric_oxide_synthase).  The overall stoichiometry, reflecting the three electrons derived from NADPH, that pass through the flavin co-factors and are transferred one by one via the heme iron,  is then:

L-arginine + 3/2 NADPH + H+ + 2 O2 = citrulline + nitric oxide + 3/2 NADP+

Another factor affecting NOS activity is the availability of essential co-factors such as tetrahydrobiopterin (BH4) (Boeger et al. Cardiovasc Res (2003) 59 (4): 824-833 http://cardiovascres.oxfordjournals.org/content/59/4/824.full, Vasquez-Vivar J., et al . Superoxide generation by endothelial nitric oxide synthase: the influence of cofactors. Proc. Natl. Acad. Sci. USA 1998;95:9220-9225 http://www.pnas.org/content/95/16/9220.full). H4-biopterin binds in the immediate vicinity of the heme at the dimer interface, interacting with residues from both subunits. When BH4 availability is limiting, electron transfer from NOS flavins becomes “uncoupled” from l-arginine oxidation and the ferrous-dioxygen complex formed as an intermediate in the reaction sequence, dissociates and superoxide(O2−·) is produced.

See Figure 1 in Werner et al.  2003 Exp Biol  Med 228: 1291-1302.

RADICALS

The conversion of Arg to NHA and of NHA to L-citrulline and NO both depend on the presence of H4-biopterin. In the absence of substrate or pterin, NADPH oxidation by NOS is accompanied by formation of O2− and peroxide (H2O2). Uncoupled eNOS is assumed to produce superoxide (O2−·) in addition to or instead of NO (·NO) which will react with itself, with NO, or with -hydroxyl, -sulfhydryl, or or side groups of proteins, lipids, or glycans. Reaction of ·NO produced by eNOS, with O2−· produced by eNOS or by other enzymes, such as NADPH and xanthine oxidases, decreases the amount of ·NO available to stimulate vascular relaxation. At the very low BH4 concentration of 100 nmol/L, recombinant human eNOS activity is fully developed. However, biopterin is formed from the pterin heterocycle also present in folic acid (Vitamin B9,
pteroyl-L-glutamate)
and which is synthesized from GTP. Human GTP cyclohydrolase I (GTPCH), is the rate-limiting enzyme in BH4 synthesis (Crabtree et al. JBC 2008, http://www.jbc.org/content/284/2/1136.full).

In addition to the NOS reaction, which generates a H3-biopterin radical cation, a neutral H3-biopterin radical is formed when H4-biopterin reacts with various radicals and which can be reduced back to H4-biopterin by ascorbate (Vitamin C). Folate species are also required to synthesize pyrimidines and purines (for DNA synthesis and repair and NADH and NADPH).

Enhancing NO Synthesis

The normal way to increase vascular nitric oxide is through vascular stress, such as exercise. As oxygen demand increases, cardiac output increases and the endothelial lining of the arteries releases nitric oxide into the blood, which, in turn, relaxes and widens the vessel wall, allowing for enhanced blood flow.

Enhancing the presence of L-Arg or the one or more of the NOS enzymes are obviously essential for NO production. However, NOS enzymes are co-valently bound to heme (heme, iron), and flavin co-factors (Vit B2), and require soluble co-factors NADPH (a dinucleotide phosphate, containing niacin, Vitamin B3), and BH4 (from Vit B9).

Foods high in Arginine and Citrulline include melons and cucumber, peanuts, salmon, and soy. Arginine is found in varying degrees (3-15% by weight) in all animal proteins. Blue-fin tuna has 1.8 g of arginine per 100 g so 2 oz. of tuna will provide about 1 g of arginine. Other sources of 1 g of L-Arg: 2.7 oz. of chicken thighs, about 4 oz. of chicken breast, 2 oz. of 75 percent lean hamburger or about 2.5 oz. of pork.

Foods rich in antioxidants and polyphenols will provide protection against free radical assault on proteins and, in particular, act to protect the NOS enzyme and cofactors. Almost all fruit and vegetables such as blueberries, cranberries, carrots, grapefruit, soybeans, apples, and spinach contain high levels of antioxidants. In addition, nuts, tea, seeds, dark chocolate, red wine, and seafood generally contain antioxidants such as resveratrol, ascorbate, and other phytochemicals. Other free radical scavengers, tocopherols (alpha-tocopherol, Vit E) work predominantly in the lipid environment such as in cell membranes, while the sulfur-containing soluble molecule, glutathione (GSH) protects the cytosolic milieu.

Supplements

Both L-Arg or L-citrulline can be purchased over the counter. Dietary L-arginine will be taken up by the intestine and transported directly to the liver by the hepatic artery as are most of the products of digestion. Much of this L-Arg will be used in metabolic steps related to the urea cycle which is co-ordinated with the kidney to rid the body of excess nitrogen and prevent ammonia concentration from building. A small amount will enter the blood stream and be used for NO synthesis.

Proargi-9 Plus® is one product being sold containing mutltigram doses of L-Arg plus L-Citrulline in combination with anti-oxidants and folate. Proargi-9 Plus® is a registered trademark and copyright of Nature’s Sunshine Products, Inc. L-arginine Plus™ is formulation with similar ingredients and stated amounts of L-Arg and L-Citrulline and is not affiliated with the makers of Proargi-9-Plus. Niteworks® is a registered trademark and copyright of Herbalife International, Inc. and is not affiliated with or a sponsor of L-arginine Plus™.

Dr. Joe Prendergast is an endocrinologist using L-Arg therapy who, over 19 years, never had to admit any of his 7200 diabetes patients to the hospital for peripheral artery disease, recommends supplemental L-Arg formulations to his patients. The combination of L-Arg with L-citrulline a longer acting NO forming product. http://www.livingwithoutdisease.com/?route=references/prendergast

Supplements of L-Arg and, in particular, in combination with L-citrulline other B-vitamins and antioxidents may be an effective way to boost vascular NO synthesis for anyone not exercising or eating a balanced diet, having a deficiency in any of the L-Arg recycling enzymes, NOS enzymes, co-factor recycling or synthetic enzymes, or other risk factor. Specific risk factors, such as inherently elevated levels of the natural NOS inhibitor ADMA (asymmetric-dimethyl-L-arginine) are beginning to be uncovered and will be the subject of another post.

 Additional References

Nitric Oxide: Biology and Pathobiology,  LJ Ignarro Editor, Sep 13, 2000 http://books.google.com/books?id=h5FugARr4bgC&dq=pterin+ring&source=gbs_navlinks_s

Mori, M. Regulation of nitric oxide synthesis and apoptosis by arginase and arginine recycling.  J Nutr. 2007 Jun;137(6 Suppl 2):1616S-1620S.   http://www.ncbi.nlm.nih.gov/pubmed/17513437

Werner, et al.  Tetrahydrobiopterin and Nitric Oxide: Mechanistic and Pharmacological Aspects Exp Biol Med December 2003 vol. 228 no. 11 1291-1302  Werner et al. Exp Biol Med 2003

Davel AP, Wenceslau CF, Akamine EH, Xavier FE, Couto GK, Oliveira HT, Rossoni LV. Endothelial dysfunction in cardiovascular and endocrine-metabolic diseases: an update.  Braz J Med Biol Res. 2011 Sep;44(9):920-32. Epub 2011 Aug 19. Davel et al. Braz J Med Biol Res 2011

Rainer H Boeger. Pharmacokinetic and pharmacodynamic properties of oral L-citrulline and L-arginine: impact on nitric oxide metabolism   Schwedhelm E, et al. Br J Clin Pharmacol. 2008_65_51-9

Louise Ignarro, UCLA, Nobel Prize Recipient, Author “NO More Heart Disease”

John Cook, Peripheral artery disease study, Author “Cardiovascular Cure”

Other aspects of Nitric Oxide involvement in biological systems in humans are covered in the following posts on this site:

Nitric Oxide in bone metabolism July 16, 2012

Author: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/07/16/nitric-oxide-in-bone-metabolism/?goback=%2Egde_4346921_member_134751669


Nitric Oxide production in Systemic sclerosis July 25, 2012

Curator: Aviral Vatsa, PhD, MBBS

http://pharmaceuticalintelligence.com/2012/07/25/nitric-oxide-production-in-systemic-sclerosis/?goback=%2Egde_4346921_member_138370383


Nitric Oxide Signalling Pathways August 22, 2012 by

Curator/ Author: Aviral Vatsa, PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/22/nitric-oxide-signalling-pathways/?goback=%2Egde_4346921_member_151245569


Nitric Oxide: a short historic perspective August 5, 2012

Author/Curator: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/05/nitric-oxide-a-short-historic-perspective-7/


Nitric Oxide: Chemistry and function August 10, 2012

Curator/Author: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/10/nitric-oxide-chemistry-and-function/?goback=%2Egde_4346921_member_145137865


Nitric Oxide and Platelet Aggregation August 16, 2012 by

Author: Dr. Venkat S. Karra, Ph.D.

http://pharmaceuticalintelligence.com/2012/08/16/no-and-platelet-aggregation/?goback=%2Egde_4346921_member_147475405


The rationale and use of inhaled NO in Pulmonary Artery Hypertension and Right Sided Heart Failure August 20, 2012

Author: Larry Bernstein, MD

http://pharmaceuticalintelligence.com/2012/08/20/the-rationale-and-use-of-inhaled-no-in-pulmonary-artery-hypertension-and-right-sided-heart-failure/

Nitric Oxide: The Nobel Prize in Physiology or Medicine 1998 Robert F. Furchgott, Louis J. Ignarro, Ferid Murad August 16, 2012

Reporter: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/08/16/nitric-oxide-the-nobel-prize-in-physiology-or-medicine-1998-robert-f-furchgott-louis-j-ignarro-ferid-murad/


Coronary Artery Disease – Medical Devices Solutions: From First-In-Man Stent Implantation, via Medical Ethical Dilemmas to Drug Eluting Stents August 13, 2012

Author: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/08/13/coronary-artery-disease-medical-devices-solutions-from-first-in-man-stent-implantation-via-medical-ethical-dilemmas-to-drug-eluting-stents/


Nano-particles as Synthetic Platelets to Stop Internal Bleeding Resulting from Trauma

August 22, 2012

Reported by: Dr. V. S. Karra, Ph.D.

http://pharmaceuticalintelligence.com/2012/08/22/nano-particles-as-synthetic-platelets-to-stop-internal-bleeding-resulting-from-trauma/

Cardiovascular Disease (CVD) and the Role of agent alternatives in endothelial Nitric Oxide Synthase (eNOS) Activation and Nitric Oxide Production July 19, 2012

Curator and Research Study Originator: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/07/19/cardiovascular-disease-cvd-and-the-role-of-agent-alternatives-in-endothelial-nitric-oxide-synthase-enos-activation-and-nitric-oxide-production/

Macrovascular Disease – Therapeutic Potential of cEPCs: Reduction Methods for CV Risk

July 2, 2012

An Investigation of the Potential of circulating Endothelial Progenitor Cells (cEPCs) as a Therapeutic Target for Pharmacological Therapy Design for Cardiovascular Risk Reduction: A New Multimarker Biomarker Discovery

Curator: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/07/02/macrovascular-disease-therapeutic-potential-of-cepcs-reduction-methods-for-cv-risk/


Bone remodelling in a nutshell June 22, 2012

Author: Aviral Vatsa, Ph.D., MBBS

http://pharmaceuticalintelligence.com/2012/06/22/bone-remodelling-in-a-nutshell/

Targeted delivery of therapeutics to bone and connective tissues: current status and challenges- Part, September  

AuthorL Aviral Vatsa, PhD, September 23, 2012

http://pharmaceuticalintelligence.com/2012/09/23/targeted-delivery-of-therapeutics-to-bone-and-connective-tissues-current-status-and-challenges-part-i/

Calcium dependent NOS induction by sex hormones: Estrogen

Curator: S. Saha, PhD, October 3, 2012

http://pharmaceuticalintelligence.com/2012/10/03/calcium-dependent-nos-induction-by-sex-hormones/


Nitric Oxide and Platelet Aggregation,

Author V. Karra, PhD, August 16, 2012

http://pharmaceuticalintelligence.com/2012/08/16/no-and-platelet-aggregation/

Bystolic’s generic Nebivolol – positive effect on circulating Endothelial Progenitor Cells endogenous augmentation

Curator: Aviva Lev-Ari, PhD, July 16, 2012

http://pharmaceuticalintelligence.com/?s=Nebivolol


Endothelin Receptors in Cardiovascular Diseases: The Role of eNOS Stimulation

Author: Aviva Lev-Ari, PhD, 10/4/2012

http://pharmaceuticalintelligence.com/2012/10/04/endothelin-receptors-in-cardiovascular-diseases-the-role-of-enos-stimulation/


Inhibition of ET-1, ETA and ETA-ETB, Induction of NO production, stimulation of eNOS and Treatment Regime with PPAR-gamma agonists (TZD): cEPCs Endogenous Augmentation for Cardiovascular Risk Reduction – A Bibliography

Curator: Aviva Lev-Ari, 10/4/2012.

http://pharmaceuticalintelligence.com/2012/10/04/inhibition-of-et-1-eta-and-eta-etb-induction-of-no-production-and-stimulation-of-enos-and-treatment-regime-with-ppar-gamma-agonists-tzd-cepcs-endogenous-augmentation-for-cardiovascular-risk-reduc/


Read Full Post »

Endothelin Receptors in Cardiovascular Diseases: The Role of eNOS Stimulation 

Author and Curator of an Investigator Initiated Study: Aviva Lev-Ari, PhD, RN

A Three Component Method for Endogenous Augmentation of cEPCs

Macrovascular Disease: The  Therapeutic Potential of cEPCs

Observations on Intellectual Property Development For an Unrecognized Future Fast Acting Therapy for Patients at High Risk for Macrovascular events

ElectEagle represents a discovery of a novel “multimarker biomarker” for cardiovascular disease that innovates on four counts.

First, it proposes new therapeutic indications for acceptable drugs.

Second, it defines a specific combination of therapeutic agents, thus, it put forth a proprietary drug combination.

Third, it targets receptor systems that have not been addressed in the context of cEPCs augmentation methods. Chiefly, modulation of the following three-targeted receptor systems: (a) inhibition of ET-1, ETA and ETA-ETB receptors by antagonists (b) induction of eNOS, by agonists and NO stimulation and (c) upregulation of PPAReceptor-gamma by agonists (TZD). While (b) and (c) are implicated as having favorable effects of cEPCs count, each exerting its effect by a different pathway, it is suggested in this project that (a) might be identify to be the more powerful of the three markers. Our method, ElectEagle is the FIRST to postulate the following: (1) time concentration dependence on eNOS reuptake (2) dose concentration dependence on NO production (3) time and dose concentration dependence for ET-1, ETA and ETA-ETB inhibition, and (4) dose concentration dependence on PPAReceptor-gamma. Points First, Second and Third are covered in Part II where a special focus is placed on ET-1, ETA and ETA-ETB receptors.

Fourth, ElectEagle proposes a platform with triple modes of delivery and use of the test, as described in Part III. The triple modes are as follows: (A) an automated platform from a centralized lab with integration to Lab’s information management system. (B) a point-of-care testing device with appropriate display of test results (small benchtop analyzers in PCP office). (C) a device used for home monitoring of analytes (the hand-held device facilitates rapid read of scores and their translation to drug concentration of each of the three therapeutic agents, with computation of the three drug concentrations done by the device. Thus, it offers quicker optimization of treatment.  ElectEagle is the FIRST to propose a CVD patient kit, hand-held device, which calculates on demand an adjustable therapeutic regimen as a function of cEPCs count biomarker. In this regard, a similarity to the pump, in management of blood sugar in DM patients, exists. Since there is a high co-morbidity between DM and CVD, our methods, ElectEagle may eventually become a targeted therapy for the DM Type 2 population.

Postulates of Multiple Indications for the Method Presented: Positioning of a Therapeutic Concept for Endogenous Augmentation of cEPCs

Potential Therapeutic Indications for ElectEagle

ElectEagle can become the drug therapy of choice for the following indications:

  •       CAD patients
  •       Endothelial Dysfunction in DM patients with or without Erectile   Dysfunction
  •       Atherosclerosis patients: Arteries and or veins
  •       pre-stenting treatment phase
  •       post-stenting treatment phase
  •       if stent is a Bare Metal stent (BMS)
  •       if stent is Drug Eluting stent (DES)
  •       if stent is EPC antibody coated (the ElectEagle method increase cEPCs generation in vitro) so availability of cEPCs is increased
  •       post CABG patients (the ElectEagle enhances healing by endogenous augmentation of cEPCs)
  •       target sub segments of CVD patients on blood thinner drugs (the ElectEagle does not require treatment with antiplatelet agents, it is suitable for all patients on Coumadin. This population have a counter indication for antiplatelet agents which is a follow up treatment after stent implantation for 30 days, with stent-eluting long term regimen of antiplatelet agents, 6 months and in some cases indefinitely (Tung, 2006).
  •       ElectEagle is based on systemic therapeutics (versus the localized stent solution requiring multiple and even overlapping stents)
  •       ElectEagle will be having potential in two contexts

1.  Coronary disease

2.  Periphery vascular disease

Comparative analysis of endogenous and exogenous cEPCs augmentation methods:

A. endogenous augmentation method properties:

  •    temporal – while drug therapy in use – drug action is interruptible
  •    time concentration on eNOS reuptake
  •    dose concentration on NO production
  •    time and dose concentration manner for ETB inhibition
  •    dose concentration on PPAR-gamma

B.  cell-based and other exogenous methods

  • permanent colonization till apoptosis if no repeated attempts of re-transfer, re-implantation as the protocol usually has several stages

ElectEagle will be resulting in potential delay of stenting implantation. Patients that are target for stenting may benefit form ElectEagle that will facilitate and accelerate healing after the stent is in place. EPC antibody coated stents will work if and only if the patient has more that just low cEPCs, most patient undergoing stenting tend to have low level of cEPC. The ElectEagle method can be coupled with that type of new stents, called Genous, now in clinical trials (HEALING II, III). These stents enhance the body ability in mobilization of cEPCs, only. However, if the initial population of cEPCs is low, an endogenous fast acting cell augmentation method is needed for pretreatment before the PCI procedure with Genous is scheduled.

Mechanism of action (MOA) for ElectEagle‘s component 1

Inhibition of ET-1, ETA and ETA-ETB

Source for vasodilators substances in the endothelium are PGI2 and NO. A potent vasoconstrictor peptide is the endothelin family, first isolated in the aortic endothelial cells.

Endothelins: Biosynthesis, Structure & Clearance

Three isoforms of endothelin (ET) have been identified. ET-1, ET-2 and ET-3. Each isoform is the product of a different gene and is synthesized as a prepro form that is processed to a propeptide and then to the mature peptide. Endothelin-converting enzyme (ECE) converts a prepro into a mature peptide. Each ET is a 21-amino-acid peptide containing two disulfide bridges. ETs are widely distributed in the body. ET-1 is the predominant ET secreted by the vascular endothelium. It is also produced by neurons and astrocytes in CNS and in endometrial, renal mesangial, sertoli, breast epithelial and other cells. ETs are present in the blood in low concentrations, they act locally in a paracrine or autocrine fashion rather than as circulating hormones.

Expression of ET-1 gene is increased by Growth Factors and cytokines, transforming factor-beta (TGF-beta) and interleukin 1 (IL-1), vasoactive substances including angiotensin II and vasopressing and mechanical stress. Expression is inhibited by NO, prostacyclin and ANP (source for vasodilators substances in the endothelium are PGI2 and NO.) Clearance of ETs from the circulation is rapid and involves enzymatic degradation by NEP 24.11 and clearance by the ETB receptor.

Endothelins: Action

ET exerts many actions on the body. In particular dose-dependent vasoconstriction in most vascular beds. Intravenous administration of ET-1 causes a rapid decease in BP followed by a prolonged increase. The depressor response results PGI2 and NO release from the vascular endothelium. The pressor response is due to direct constriction of vascular smooth muscle. ETs exert direct positive inotropic and chronotropic actions on the heart and are potent coronary vasoconstrictors. ETs actions on other organ is described in (Reid, 2004). ETs interact with several endocrine systems, increase secretion of renin, aldosterone, vasopressin and Atrial natriuretic peptide (ANP.) Action exerted on CNS and PNS, GI system, liver, GU, reproductive system, eye, skeletal and skin. ET-1 is a potent mitogen for vascular smooth muscle cells, cardiac myocytes and glomerular mesangial cells.

ET receptors are present in many tissues and organs, blood vessel wall, cardiac muscle, CNS, lung, kidney, adrenal, spleen, and GI. The signal transduction mechanism triggered by binding of ET-1 to its receptors, ETA & ETB includes effects of stimulation of phospholipase C, formation of inositol triphosphate and release of calcium from the ER which results in vasoconstriction. Stimulation of PGI2 and NO synthesis result in decreased intracellular calcium concentration and vasodilation.

Two receptor subtypes, ETA & ETB have been cloned and sequenced. ETA receptors have a high affinity for ET-1 and a low affinity for ET-3 and are located on smooth muscle cells, where they mediate vasoconstriction. ETB receptors have an equal affinity for ET-1 and ET-3 and are located on vascular ECs, where they mediate release of PGI2 and NO. Both receptor types belong to the G protein-coupled seven-transmembrane domain family of receptors.

Inhibitors of Endothelin Synthesis & Action

ETs can be blocked with receptor antagonists and with drugs that block the Endothelin-converting enzyme (ECE), Endothelin-converting enzyme inhibitors (ECEI). Two receptor subtypes, ETA & ETB can be blocked selectively, or both can be blocked with nonselective ETA – ETB antagonists. Bosentan is a nonselective antagonist, available both intravenously and orally. It blocks the initial transient depressor (ETB ) and the prolonged pressor (ETA) responses to intravenous ET. Oral ET antagonists are available for research purposes. The formation of Endothelin-converting enzyme (ECE) can be blocked with Phosphoramidon. The therapeutic potential of ECEI is similar to that of the ET receptor antagonist, Bosentan, an active competitive inhibitor of ET [it has teratogenic and hepatotexic effects].

Physiologic & Pathologic Roles of Endothelin Antagonists

Systemic administration of ET receptor antagonists or ECEI causes vasodilation and decreases arterial pressure in human and in experimental animals. Intra-arterial administration of the drugs also causes slow-onset forearm vasodilation in humans. This is an evidence that the endothelin system participates in the regulation of vascular tone, even under resting conditions (Reid, 2004).

There is evidence that ETs participate in CVD, including hypertension, cardiac hypertrophy, CHF, atherosclerosis, CAD, MI. ETs have been implicated in pulmonary diseases, PA HTN, asthma, renal diseases. Increased ET levels was found in the blood, increased expression of ET mRNA in endothelial or vascular smooth muscle cells and the responses to administration of ET antagonists. ET antagonists have potential for treatment of these diseases. In clinical trials, Bosentanand other nonselective antagonists as well as ETA selective antagonists produce beneficial effects on hemodynamics and symptoms of CHF, PA HTN and essential HTN (Sütsch et al., 1998), (Haynes, 1996), (Lahav et al., 1999). Currently, it is approved for use in pulmonary hypertension (Benowitz, 2004).

ElectEagle Project Drug combination Therapy has selected Bosentan or other nonselective ET antagonists as well as ETA selective antagonists to enhance the effects an eNOS agonist and a PPAR-gamma agonist will have on CVD patient’s propensity to achieve beneficial effects for endogenous augmentation of cEPCs. The impact the ETs have on the body is of a very wide range and of a most important from a physiological point of view, respectively, we did not leave Big ET-1 out of the therapeutic treatment design.

Proposed integration plan for ElectEagle’s Version I with CVD patients current medication regimen for selective medical diagnoses

Blood Pressure Medicine:

Beta blockers, Verapamil (Calan), Reserpine (Hydropes), Clonidine (Catapres), Methyldopa (Aldomet)

Diuretics:

Thiazides, Spironolactone (Aldactone), Hydralazine

Antidepressants:

Prozac, Lithium, MOA’s, Tricyclics

Stomach Medicine:

Tagamet and Zantac, plus other compounds containing Cimetidine and Ranitidine or associated compounds in Anticholesterol Drugs

Antipsychotics:

Chlorpromazine (Thorazine), Pimozide (Orap), Thiothixine (Navane), Thiordazine (Mellaril), Sulpiride, Haloperidol (haldol), Fluphenazine (Modecate, Prolixin)

Heart Medicine:

Clofibrate (Atromid), Gemfibrozil, Diagoxin

Hormones:

Estrogen, Progesterone, Proscar, Casodex, Eulexin, Corticosteroids Gonadotropin releasing antagonists: Zoladex and Lupron

Cytotoxic agents:

Cyclophosphamide, Methotrexate, Roferon Non-steroidal anti-inflammatories

Others

Alprazolam, Amoxapine, Chlordiazepoxide, Sertraline, Paroxetine, Clomipramine, Fluvoxamine, Fluoxetine, Imipramine, Doxepine, Desipramine, Clorprothixine, Bethanidine, Naproxen, Nortriptyline, Thioridazine, Tranylcypromine, Venlafaxine, Citalopram.

INTERACTIONS for Nebivolol

Calcium Antagonists:

Caution should be exercised when administering beta-blockers with calcium antagonists of the verapamil or diltiazem type because of their negative effect on contractility and atrio-ventricular conduction. Exaggeration of these effects can occur particularly in patients with impaired ventricular function and/or SA or AV conduction abnormalities. Neither medicine should therefore be administered intravenously within 48 hours of discontinuing the other.

Anti-arrhythmics:

Caution should be exercised when administering beta-blockers with Class I anti-arrhythmic drugs and amiodarone as their effect on atrial conduction time and their negative inotropic effect may be potentiated. Such interactions can have life threatening consequences.

Clonidine:

Beta-blockers increase the risk of rebound hypertension after sudden withdrawal of chronic clonidine treatment.

Digitalis:

Digitalis glycosides associated with beta-blockers may increase atrio-ventricular conduction times. Nebivolol does not influence the kinetics of digoxin & clinical trials have not shown any evidence of an interaction.

Special note: Digitalisation of patients receiving long term beta-blocker therapy may be necessary if congestive cardiac failure is likely to develop. The combination can be considered despite the potentiation of the negative chronotropic effect of the two medicines. Careful control of dosages and of individual patient’s response (notably pulse rate) is essential in this situation.

Insulin & Oral Antidiabetic drugs:

Glucose levels are unaffected, however symptoms of hypoglycemia may be masked.

Anaesthetics:

Concomitant use of beta-blockers & anaesthetics e.g. ether, cyclopropane & trichloroethylene may attenuate reflex tachycardia & increase the risk of hypotension

Testing ElectEagle’s a-priori postulates presented in Part I

a-priori postulates presented in Part I for Component 1:ET-1, ETA and ETA-ETB inhibition

  • time and dose concentration dependence for ETA and ETA-ETB inhibition

 In the literature we found evidence for dose concentration dependence manner (Reid, 2004).


ETA and ETA-ETB inhibitor time concentration dependence manner dose concentration dependencemanner time and dose dose 
Bosentan   (Reid, 2004)   62.5, 125 mg tablets

a-priori postulates presented in Part I for Component 2: NO, eNOS induction and stimulation

  • time concentration dependence on eNOS reuptake
  • dose concentration dependence on NO production

In the literature we found evidence for dose concentration dependence manner

Ach, Histamine, Genistein, ACEI, Fenofibrates, NEBIVOLOL, Calcium channel blocker, Enzyme S-nitrosylation

In the literature we found evidence for time concentration dependence manner:

Ach, BRL37344, a 3-adrenoceptor agonist

In the literature we found evidence for time and dose concentration dependence manner:

Histamine

NO, eNOS AgonistsStimulate phosphorylation of eNOS at serine 1177, 1179, 116 Conversion of L-arginine toL-citrulline time concentration dependence manner dose concentration dependencemanner time and dose dose (nmol·mg

of protein-1)

Grovers et al., (2002)

A23187       (5µM)
Acetylcholine Xu et al., (2002) Sanchez et al., (2006)   (1µM)
5-Hydroxytryptamine       (1µM)
VEGF (       (20ng/ml)
Bradykinin       (1µM)
Histamine   McDuffie et al., (1999) McDuffie et al., (2000) (10µM)
genistein   Liu et al., (2004)   (1µM)
ACEI   Skidgel et al., (2006)    
Fenofibrates   Asai et al., (2006)    
BRL37344, a 3-adrenoceptor agonist Pott et al., (2005)      
NEBIVOLOLß1-selective adrenergic receptor antagonist with nitric oxide (NO)–mediation for vasodilation


  Ritter et al., (2006)    
Calcium channel blocker   Church and Fulton, (2006),    
Enzyme S-nitrosylation   Erwin et al., (2006)    


a-priori postulates presented in Part I for Component 3: PPAR-gamma

  • dose concentration dependence on PPAReceptor-gamma – confirmed by a study for Rosiglitazone and a study for Ciglitazone
PPAReceptor-gamma agonists time concentration dependence manner dose concentration dependencemanner time and dose dose 
Rosiglitazone   Polikandriotis et al., (2005)   maximum recommended daily dose of 8 mg to 2,000 mg.
Ciglitazone Polikandriotis et al., (2005)    


Development of an Experimental Treatment Protocol for

ElectEagle Version I

Therapeutic Strategy for cEPCs Endogenous Augmentation for measuring the number of circulating Endothelial Progenitor Cells (cEPCs) before and after a newly design treatment with Pharmacological agents

Component 1: Inhibition of ET-1, ETA and ETA-ETB

Bosentan (Tracleer) Oral: 62.5, 125 mg tablets


Component 2: Induction of NO production and stimulation of eNOS

Nebivolol – ß1-selective adrenergic receptor antagonist with nitric oxide (NO)– mediation for vasodilation

A single daily dose of 5 mg was appropriate, with no evident advantage at 10 mg (Van Nueten et al.,1997)

Component 3: Treatment Regime with PPAR-gamma agonists (TZD)

A Substitute for Rosiglitazone, 2-8 mg once daily

The combination drug therapy for endogenous augmentation of cEPCs in CVD patients for achievement of reduction in risk for macrovascular events is recommended to be applied for Clinical Trial Phase One in the following regimen:

Use the following combination of drugs for the following Stages

Bosentan (Tracleer), Oral: 62.5 mg tablets

Nebivolol, Oral: 5mg once daily

A substitute for Rosiglitazone, 8 mg once daily


Stage 1: ET-1 Antagonist Effect on eEPC

1.0 Measurement of the Baseline of number of cEPC

1.1 Administer ET-1 antagonist for 10 days

1.2 Measurement of number of cEPC after 10 days of treatment with ET-1 antagonist

Stage 2: Nitric Oxide Effect on cEPC

2.0 Measurement of number of cEPC obtained in 1.2

2.1 Administer Nitric Oxide Agonist for 10 days

2.2 Measurement of number of cEPC after 10 days of

treatment with Nitric Oxide Agonist

Stage 3: Comparison of ET-1 and NO Effects on cEPC Proliferation

3.0 Comparison of number of cEPC in 1.2 to 2.2

¨     IF number of cEPC in 1.2 > number of cEPC in 2.2

-> continue 1.1 only

[ET-1 antagonist more effective for proliferation of cEPC than NO Agonist]

3.1.1      Measurement of number of cEPC every 10 days

¨     IF number of cEPC in 1.2 < number of cEPC in 2.2

-> continue 2.1 only

[ET-1 antagonist less effective for proliferation of cEPC than NO Agonist]

3.2.1      Measurement of number of cEPC every 10 days

¨     IF number of cEPC in 1.2 = number of cEPC in 2.2

-> continue 1.1 AND 2.1

[ET-1 antagonist equal NO Agonist in effectiveness for proliferation of cEPC]

-> Administer a Combination therapy of ET-1 antagonist and NO Agonist for 10 days

3.3.1      Measurement of number of cEPC every 10 days

Stage 4: ET-1 and/or NO Effect on Cardiovascular (CV) Events

q      After 12 months Comparison of CV events in patient population in

Stage 3.1, 3.2, 3.3

  • Cardiovascular events in patients in 3.1
  • Cardiovascular events in patients in 3.2
  • Cardiovascular events in patients in 3.3

Conclusions

  •       Most favorable and unexpected to us was finding in the literature new indications for TDZs as stimulators of eNOS, in addition to the new indication for atherosclerosis besides the classic indication in pharmacology books, being in the reduction of insulin resistance. Reassuring our selection of a substitute for Rosiglitazone.
  •       Most favorable and unexpected to us was finding in the literature new indications for beta blockers as NO stimulant, nebivolol, a case in point, thus, fulfilling two indications in one drug along the direction of the study to identify eNOS agonists.
  •       The following combination of drugs was selected for ElectEagle Version I

Bosentan (Tracleer), Oral: 62.5 mg tablets

Nebivolol, Oral: 5mg once daily

A Substitute for Rosiglitazone, 8 mg once daily

  •       We confirmed time and dose concentrations postulating apriori in most cases. Additional literature searches will benefit the project for the three drugs selected
  •       We have identified Inhibition of ET-1, ETA and ETA-ETB as one of the agent in the drug combination. The entire literature on cEPCs does not implicate Endothelin with impact on eEPCs while it is known that mechanical stress increase its secretion, this type of stress is implicated with hypertension. To leave out ET-1 from the cEPCs function in CVD risk equates to leaving out Thrombin from the coagulation cascade. ElectEagle Version I corrects that ommission. 

REFERENCES

Benowitz, NL., (2004). Antihypertensive Agents. Chapter 11 in Katzung, BG., Basic & Clinical Pharmacology. McGraw-Hill, 9th Edition, pp. 160-183.

Haynes WG, Ferro CJ, O’Kane KP, Somerville D, Lomax CC, Webb DJ, (1996). Systemic endothelin receptor blockade decreases peripheral vascular resistance and blood pressure in humans. Circulation, 15;93(10):1860-70. 

N S Kirkby, P W F Hadoke, A J Bagnall, and D J Webb (2008)

The endothelin system as a therapeutic target in cardiovascular disease: great expectations or bleak house? Br J Pharmacol. 2008 March; 153(6): 1105–1119.

Ohkita Mamoru, Masashi Tawa, Kento Kitada and Yasuo Matsumura (2012). Pathophysiological Roles of Endothelin Receptors in Cardiovascular Diseases,  J Pharmacol Sci 119, 302 – 313 (2012)

Reid, Ian A., (2004). Vasoactive Peptides. Chapter 17 in Katzung, BG., Basic & Clinical Pharmacology. McGraw-Hill, 9th Edition, pp. 281 – 297, in particular, Endothelins, pp. 290-293.

  For a comprehensive Bibliography on the Three Therapeutic Componenets and the pathophysiology of Cardiovascular Disease, follow this link:

Inhibition of ET-1, ETA and ETA-ETB, Induction of NO production, stimulation of eNOS and Treatment Regime with PPAR-gamma agonists (TZD): cEPCs Endogenous Augmentation for Cardiovascular Risk Reduction – A Bibliography

http://pharmaceuticalintelligence.com/2012/10/04/inhibition-of-et-1-eta-and-eta-etb-induction-of-no-production-and-stimulation-of-enos-and-treatment-regime-with-ppar-gamma-agonists-tzd-cepcs-endogenous-augmentation-for-cardiovascular-risk-reduc/

 Other aspects of Nitric Oxide involvement in biological systems in humans are covered in the following posts on this site:

Nitric Oxide in bone metabolism July 16, 2012

Author: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/07/16/nitric-oxide-in-bone-metabolism/?goback=%2Egde_4346921_member_134751669


Nitric Oxide production in Systemic sclerosis July 25, 2012

Curator: Aviral Vatsa, PhD, MBBS

http://pharmaceuticalintelligence.com/2012/07/25/nitric-oxide-production-in-systemic-sclerosis/?goback=%2Egde_4346921_member_138370383


Nitric Oxide Signalling Pathways August 22, 2012 by

Curator/ Author: Aviral Vatsa, PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/22/nitric-oxide-signalling-pathways/?goback=%2Egde_4346921_member_151245569


Nitric Oxide: a short historic perspective August 5, 2012

Author/Curator: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/05/nitric-oxide-a-short-historic-perspective-7/


Nitric Oxide: Chemistry and function August 10, 2012

Curator/Author: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/10/nitric-oxide-chemistry-and-function/?goback=%2Egde_4346921_member_145137865


Nitric Oxide and Platelet Aggregation August 16, 2012 by

Author: Dr. Venkat S. Karra, Ph.D.

http://pharmaceuticalintelligence.com/2012/08/16/no-and-platelet-aggregation/?goback=%2Egde_4346921_member_147475405


The rationale and use of inhaled NO in Pulmonary Artery Hypertension and Right Sided Heart Failure August 20, 2012

Author: Larry Bernstein, MD

http://pharmaceuticalintelligence.com/2012/08/20/the-rationale-and-use-of-inhaled-no-in-pulmonary-artery-hypertension-and-right-sided-heart-failure/

Nitric Oxide: The Nobel Prize in Physiology or Medicine 1998 Robert F. Furchgott, Louis J. Ignarro, Ferid Murad August 16, 2012

Reporter: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/08/16/nitric-oxide-the-nobel-prize-in-physiology-or-medicine-1998-robert-f-furchgott-louis-j-ignarro-ferid-murad/


Coronary Artery Disease – Medical Devices Solutions: From First-In-Man Stent Implantation, via Medical Ethical Dilemmas to Drug Eluting Stents August 13, 2012

Author: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/08/13/coronary-artery-disease-medical-devices-solutions-from-first-in-man-stent-implantation-via-medical-ethical-dilemmas-to-drug-eluting-stents/


Nano-particles as Synthetic Platelets to Stop Internal Bleeding Resulting from Trauma

August 22, 2012

Reported by: Dr. V. S. Karra, Ph.D.

http://pharmaceuticalintelligence.com/2012/08/22/nano-particles-as-synthetic-platelets-to-stop-internal-bleeding-resulting-from-trauma/

Cardiovascular Disease (CVD) and the Role of agent alternatives in endothelial Nitric Oxide Synthase (eNOS) Activation and Nitric Oxide Production July 19, 2012

Curator and Research Study Originator: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/07/19/cardiovascular-disease-cvd-and-the-role-of-agent-alternatives-in-endothelial-nitric-oxide-synthase-enos-activation-and-nitric-oxide-production/

Macrovascular Disease – Therapeutic Potential of cEPCs: Reduction Methods for CV Risk

July 2, 2012

An Investigation of the Potential of circulating Endothelial Progenitor Cells (cEPCs) as a Therapeutic Target for Pharmacological Therapy Design for Cardiovascular Risk Reduction: A New Multimarker Biomarker Discovery

Curator: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/07/02/macrovascular-disease-therapeutic-potential-of-cepcs-reduction-methods-for-cv-risk/


Bone remodelling in a nutshell June 22, 2012

Author: Aviral Vatsa, Ph.D., MBBS

http://pharmaceuticalintelligence.com/2012/06/22/bone-remodelling-in-a-nutshell/

Targeted delivery of therapeutics to bone and connective tissues: current status and challenges- Part, September  

AuthorL Aviral Vatsa, PhD, September 23, 2012

http://pharmaceuticalintelligence.com/2012/09/23/targeted-delivery-of-therapeutics-to-bone-and-connective-tissues-current-status-and-challenges-part-i/

Calcium dependent NOS induction by sex hormones: Estrogen

Curator: S. Saha, PhD, October 3, 2012

http://pharmaceuticalintelligence.com/2012/10/03/calcium-dependent-nos-induction-by-sex-hormones/


Nitric Oxide and Platelet Aggregation,

Author V. Karra, PhD, August 16, 2012

http://pharmaceuticalintelligence.com/2012/08/16/no-and-platelet-aggregation/

Bystolic’s generic Nebivolol – positive effect on circulating Endothelial Progenitor Cells endogenous augmentation

Curator: Aviva Lev-Ari, PhD, July 16, 2012

http://pharmaceuticalintelligence.com/?s=Nebivolol


Endothelin Receptors in Cardiovascular Diseases: The Role of eNOS Stimulation

Author: Aviva Lev-Ari, PhD, 10/4/2012

http://pharmaceuticalintelligence.com/2012/10/04/endothelin-receptors-in-cardiovascular-diseases-the-role-of-enos-stimulation/


Inhibition of ET-1, ETA and ETA-ETB, Induction of NO production, stimulation of eNOS and Treatment Regime with PPAR-gamma agonists (TZD): cEPCs Endogenous Augmentation for Cardiovascular Risk Reduction – A Bibliography

Curator: Aviva Lev-Ari, 10/4/2012.

http://pharmaceuticalintelligence.com/2012/10/04/inhibition-of-et-1-eta-and-eta-etb-induction-of-no-production-and-stimulation-of-enos-and-treatment-regime-with-ppar-gamma-agonists-tzd-cepcs-endogenous-augmentation-for-cardiovascular-risk-reduc/


Nitric Oxide Nutritional remedies for hypertension and atherosclerosis. It’s 12 am: do you know where your electrons are?

Author and Reporter: Meg Baker, 10/7/2012.

http://pharmaceuticalintelligence.com/2012/10/07/no-nutritional-remedies-for-hypertension-and-atherosclerosis-its-12-am-do-you-know-where-your-electrons-are/

Drug Information

Component 1: Inhibition of ET-1, ETA and ETA-ETB

Bosentan (Tracleer)

BACKGROUND: Although local inhibition of the generation or actions of endothelin-1 has been shown to cause forearm vasodilatation, the systemic effects of endothelin receptor blockade in healthy humans are unknown. We therefore investigated the cardiovascular effects of a potent peptide endothelin ETA/B receptor antagonist, TAK-044, in healthy men. METHODS AND RESULTS: Two randomized, placebo-controlled, crossover studies were performed. In nine subjects, TAK-044 (10 to 1000 mg IV over a 15-minute period) caused sustained dose-dependent peripheral vasodilatation and hypotension. Four hours after infusion of the highest dose (1000 mg), there were decreases in mean arterial pressure of 18 mm Hg and total peripheral resistance of 665 AU and increases in heart rate of 8 bpm and cardiac index of 0.9 L x min(-1) x m(-2) compared with placebo. TAK-044 caused a rapid, dose-dependent increase in plasma immunoreactive endothelin (from 3.3 to 35.7 pg/mL within 30 minutes after 1000 mg). In a second study in eight subjects, intravenous administration of TAK-044 at doses of 30, 250, and 750 mg also caused peripheral vasodilatation, and all three doses abolished local forearm vasoconstriction to brachial artery infusion of endothelin-1. Brachial artery infusion of TAK-044 caused local forearm vasodilation. CONCLUSIONS: The endothelin ETA/B receptor antagonist TAK-044 decreases peripheral vascular resistance and, to a lesser extent, blood pressure; increases circulating endothelin concentrations; and blocks forearm vasoconstriction to exogenous endothelin-1. These results suggest that endogenous generation of endothelin-1 plays a fundamental physiological role in maintenance of peripheral vascular tone and blood pressure. The vasodilator properties of endothelin receptor antagonists may prove valuable therapeutically (Haynes et al., 1996).

http://www.tracleer-pph.com/

http://www.medicinenet.com/script/main/art.asp?articlekey=44221&pf=3&page=1

GENERIC NAME: BOSENTAN – ORAL (boh-SEN-tan)

BRAND NAME(S): Tracleer

WARNING: This medication may cause serious liver problems. Your doctor should monitor your liver function closely to decrease your risk of liver-related side effects. Tell your doctor immediately if you notice any of these symptoms of liver problems: nausea, vomiting, stomach pain, unusual tiredness, and yellowing eyes or skin. These effects, if they occur, may go away over time (are reversible). This medication must not be used during pregnancy because it can cause fetal harm (e.g., birth defects). See the pregnancy warning information below (in Precautions section).

USES: Bosentan is used to treat a condition of high blood pressure in the lungs (pulmonary arterial hypertension). It works by causing the blood vessels (arteries) in the lungs to relax and expand, thus decreasing the pressure.

HOW TO USE: Before using, review the bosentan Medication Guide for information on the safe use of this medicine. Take this medication by mouth usually twice daily in the morning and evening with or without food; or as directed by your doctor. The dosage is based on your medical condition and response to therapy. Your doctor may recommend to gradually increase your dose over time so your body may better adjust to the effects of this drug. Do not stop taking this medication without consulting your doctor. Some conditions may become worse when the drug is abruptly stopped. Your dose may need to be gradually decreased.

SIDE EFFECTS: Headache, nose/throat irritation, itching, flushing, or stomach upset may occur. If any of these effects persist or worsen, notify your doctor or pharmacist promptly. Tell your doctor immediately if any of these unlikely but serious side effects occur: irregular heartbeat, unusual tiredness and weakness, swelling of the feet or ankles, trouble breathing, dizziness or lightheadedness. If you notice any of the following very serious side effects of liver problems, stop taking bosentan and consult your doctor immediately: vomiting, stomach pain, yellowing eyes or skin. A serious allergic reaction to this drug is unlikely, but seek immediate medical attention if it occurs. Symptoms of a serious allergic reaction include: rash, itching, swelling, dizziness, severe trouble breathing. If you notice other effects not listed above, contact your doctor or pharmacist.

PRECAUTIONS: Tell your doctor your medical history, especially of: liver problems, blood disorders (e.g., anemia), any allergies. Caution is advised when using this drug in the elderly because they may be more sensitive to the effects of the drug. This medication must not be used during pregnancy because it may cause fetal harm. If you are pregnant or think you may be pregnant, do not take this medication and consult your doctor immediately. It is recommended that you use two reliable forms of birth control while taking this medicine. It is also recommended to have a pregnancy test done before treatment and every month during treatment with this drug. It is not known whether this drug passes into breast milk. Because of the potential risk to the infant, breast-feeding while using this drug is not recommended.

DRUG INTERACTIONS: This drug is not recommended for use with: cyclosporine, glyburide. Ask your doctor or pharmacist for more details. Tell your doctor of all prescription and nonprescription medication you may use, especially: azole antifungals (e.g., itraconazole, ketoconazole), statins for high cholesterol (e.g., lovastatin, simvastatin), HIV protease inhibitors (e.g., indinavir, ritonavir), tacrolimus. This medication may decrease the effectiveness of combination-type birth control pills. This can result in pregnancy. You may need to use an additional form of reliable birth control while using this medication. Consult your doctor or pharmacist for details. Do not start or stop any medicine without doctor or pharmacist approval.

OVERDOSE: If overdose is suspected, contact your local poison control center or emergency room immediately. US residents can call the US national poison hotline at 1-800-222-1222. Canadian residents should call their local poison control center directly.

NOTES: Do not share this medication with others. Laboratory and/or medical tests (e.g., liver function tests- LFT’s, blood tests) will be performed to monitor your progress and for side effects.

MISSED DOSE: If you miss a dose, use it as soon as you remember. If it is near the time of the next dose, skip the missed dose and resume your usual dosing schedule. Do not double the dose to catch up.

STORAGE: Store at room temperature between 68 and 77 degrees F (20 and 25 degrees C) away from light and moisture. Brief storage between 59 and 86 degrees F (15 and 30 degrees C) is permitted.

MEDICAL ALERT: Your condition can cause complications in a medical emergency. For enrollment information call MedicAlert at 1-800-854-1166 (USA), or 1-800-668-1507

Read Full Post »

Curator of an Investigator Initiated Study: Aviva Lev-Ari, PhD, RN

Inhibition of ET-1, ETA and ETA-ETB, Induction of NO production,  stimulation of eNOS and Treatment Regime with PPAR-gamma agonists (TZD): cEPCs Endogenous Augmentation for Cardiovascular Risk Reduction – A Bibliography

Alonso D, Radomski MW, (2003). Nitric oxide, platelet function, myocardial infarction and reperfusion therapies. Heart Fail Rev., 8:47–54.

Anthony MS, Clarkson TB, Williams JK, (1998). Effects of soy isoflavones on atherosclerosis: potential mechanisms. Am J Clin Nutr., 68(6 Suppl):1390S–1393S.

Benowitz, NL., (2004). Antihypertensive Agents. Chapter 11 in Katzung, BG., Basic & Clinical Pharmacology. McGraw-Hill, 9th Edition, pp. 160-183.

Bisoendial RJ, et al. (2003). Restoration of endothelial function by increasing high-density lipoprotein in subjects with isolated low high-density lipoprotein. Circulation, 107:2944–2948.

Blair A, Shaul PW, Yuhanna IS, Conrad PA, Smart EJ., (1999). Oxidized low density lipoprotein displaces endothelial nitric-oxide synthase (eNOS) from plasmalemmal caveolae and impairs eNOS activation. J. Biol. Chem., 274:32512–32519.

Brixius K, Song Q, Malick A, Boelck B, Addicks K, Bloch W, Mehlhorn U, Schwinger R, (2006). eNOS is not activated by nebivolol in human failing myocardium. Life Sci., 2006 Apr 25

Broeders MAW, Doevendans PA, Bekkers BCAM, Bronsaer R, van Gorsel E, Heemskerk JWM. oude Egbrink MGA, van Breda E, Reneman RS, van der Zee R, (2000). Nebivolol: A Third-Generation ß-Blocker That Augments Vascular Nitric Oxide Release, Endothelial ß2-Adrenergic Receptor–Mediated Nitric Oxide Production.Circulation,102:677.

Brown BG, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N. Engl. J. Med., 345:1583–1592.

Brugada P, Brugada J, Brugada R, (2001). Dealing with biological variation in the Brugada syndrome. Eur. Heart J., 22(24): 2231 – 2232.

Caulin-Glaser T, Garcia-Cardena G, Sarrel P, Sessa WC, Bender JR., (1997). 17 beta-estradiol regulation of human endothelial cell basal nitric oxide release, independent of cytosolic Ca2+ mobilization. Circ. Res., 81:885–892.

Cheng Y, Wang M, Yu Y, Lawson J, Funk CD, and Fitzgerald GA., (2006). Cyclooxygenases, microsomal prostaglandin E synthase-1, and cardiovascular function. J. Clin. Invest., 116:1391-1399

Church JE, Fulton D., (2006). Differences in eNOS activity because of subcellular localization are dictated by phosphorylation state rather than the local calcium environment. J Biol Chem., 2006 Jan 20;281(3):1477-88. Epub 2005 Oct 28.

Dessy C, Saliez J, Ghisdal P, Daneau G, Lobysheva II, Frerart F, Belge C, Jnaoui K, Noirhomme P, Feron O, Balligand JL, (2005). Endothelial {beta}3-Adrenoreceptors Mediate Nitric Oxide-Dependent Vasorelaxation of Coronary Microvessels in Response to the Third-Generation {beta}-Blocker Nebivolol. Circulation, 112(8): 1198 – 1205.

Dimmeler S, Aicher A, Vasa M, Mildner-Rihm C, Adler K, Tiemann M, Rutten H, Fichtlscherer S, Martin H, Zeiher AM, (2001). HMG-CoA reductase inhibitors (statins) increase endothelial progenitor cells via the PI3-kinase/Akt pathway. J Clin Invest., 108:391–397.

Dobrydneva Y, Williams RL, Morris GZ, Blackmore PF, (2002). Dietary phytoestrogens and their synthetic structural analogues as calcium channel blockers in human platelets. J Cardiovasc Pharmacol, 40:399–410.

Duarte J, Ocete MA, Perez-Vizcaino F, Zarzuelo A, Tamargo J, (1997). Effect of tyrosine kinase and tyrosine phosphatase inhibitors on aortic contraction and induction of nitric oxide synthase. Eur J Pharmacol, 338:25–33.

Erwin PA, Mitchell DA, Sartoretto J, Marletta MA, Michel T., (2006). Subcellular Targeting and Differential S-Nitrosylation of Endothelial Nitric-oxide Synthase. J. Biol. Chem., 281:1, 151-157.

George T. and P. Ramwell, (2004). Nitric Oxide, Donors, & Inhibitors. Chapter 19 in Katzung, BG., Basic & Clinical Pharmacology. McGraw-Hill, 9th Edition, pp. 313 – 318.

Gong M, et al., (2003). HDL-associated estradiol stimulates endothelial NO synthase and vasodilation in an SR-BI-dependent manner. J. Clin. Invest., 111:1579–1587.

Gonzalez E, Kou R, Lin AJ, Golan DE, Michel T., (2002). Subcellular Targeting and Agonist-induced Site-specific Phosphorylation of Endothelial Nitric-oxide Synthase. J. Biol. Chem., 277;42:39554-39560.

Goon, P.K.Y. Lip G.Y.H, Boos, CJ, Stonelake, PS, Blann, AD. (2006). Circulating Endothelial Cells, Endothelial Progenitor Cells, and Endothelial Microparticles in Cancer, Neoplasia, 8:79-88.

Gottstein N, Ewins BA, Eccleston C, Hubbard GP, Kavanagh IC, Minihane AM, Weinberg PD, Rimbach G, (2003). Effect of genistein and daidzein on platelet aggregation and monocyte and endothelial function. Br J Nutr, 89:607–616

Grovers R, Bevers L, De Bree P, Rabelink TJ, (2002). Endothelial nitric oxide synthase activity is linked to its presence at cell–cell contacts. Biochem. J., 361 (193–201) (Printed in Great Britain)

Haynes WG, Ferro CJ, O’Kane KP, Somerville D, Lomax CC, Webb DJ, (1996). Systemic endothelin receptor blockade decreases peripheral vascular resistance and blood pressure in humans. Circulation, 15;93(10):1860-70. 

Iaccarino G, Cipolletta E, Fiorillo A, AnnecchiaricoM, Ciccarelli M, Cimini V, Koch WJ, B. Trimarco B, (2002). {beta}2-Adrenergic Receptor Gene Delivery to the Endothelium Corrects Impaired Adrenergic Vasorelaxation in Hypertension. Circulation, 106(3): 349 – 355.

Jordan J, Tank J, Stoffels, Franke MG, Christensen NJ, Luft CF, Boschmann M, (2001). Interaction between {beta}-Adrenergic Receptor Stimulation and Nitric Oxide Release on Tissue Perfusion and Metabolism.J. Clin. Endocrinol. Metab., 86(6): 2803 – 2810.

Kalinowski L, Dobrucki LW, Szczepanska-Konkel M, Jankowski M, Martyniec L, Angielski S, Malinski, T, (2003). Third-Generation {beta}-Blockers Stimulate Nitric Oxide Release From Endothelial Cells Through ATP Efflux: A Novel Mechanism for Antihypertensive Action. Circulation, 107(21): 2747 – 2752. 

N S Kirkby, P W F Hadoke, A J Bagnall, and D J Webb (2008). The endothelin system as a therapeutic target in cardiovascular disease: great expectations or bleak house? Br J Pharmacol. 2008 March; 153(6): 1105–1119.

Kleinman, ME, Blei, F, Gurtner, GC, (2005). Circulating Endothelial Progenitor Cells and Vascular Anomalies, Lymphatic Research and Biology, 3;4: 234-239.

Koshimizu T-A, Nasa Y, Tanoue A, Oikawa R, Kawahara Y, Kiyono Y, Adachi T, Tanaka T, Kuwaki T, Mori T, Takeo S, Okamura H, Tsujimoto G., (2006). V1a vasopressin receptors maintain normal blood pressure by regulating circulating blood volume and baroreflex sensitivity. PNAS, 103;20: 7807-7812.

Kotamraju S, Hogg N, Joseph J, Keefer LK, Kalyanaraman B, (2001). Inhibition of oxidized low-density lipoprotein-induced apoptosis in endothelial cells by nitric oxide. Peroxyl radical scavenging as an antiapoptotic mechanism. J Biol Chem, 276:17316–17323.

Kuvin JT, et al., (2002). A novel mechanism for the beneficial vascular effects of high-density lipoprotein cholesterol: enhanced vasorelaxation and increased endothelial nitric oxide synthase expression. Am. Heart J., 144:165–172.

Lahav R, Heffner G, Patterson PH., (1999). An endothelin receptor B antagonist inhibits growth and induces cell death in human melanoma cells in vitro and in vivo. PNAS, 96;20: 11496-11500.

Lantin-Hermoso RL, et al., (1997). Estrogen acutely stimulates nitric oxide synthase activity in fetal pulmonary artery endothelium. Am. J. Physiol., 273:L119–L126.

Laszlo, F, Whittle BJR, Moncada S., (1994). Time dependent enhancement or inhibition of endotoxin-induced vascular injury in rat intestine by nitric oxide synthase inhibitors. Br. J. Pharmacol., 111, 1309–1315.

Laufs U, Werner N, Link A, Endres M, Wassmann S, Jurgens K, Miche E, Bohm M, Nickenig G, (2003). Physical training increases endothelial progenitor cells, inhibits neointima formation, and enhances angiogenesis. Circulation, 109:220 –226.

Li AC, Binder, CJ, Gutierrez, A, Brown, KK, Plotkin, CR, Pattison, JW, Valledor, AF, Davis, RA, Willson, TM, Witztum, JL, Palinski, W, Glass, CK. (2004). Differential inhibition of macrophage foam-cell formation and atherosclerosis in mice by PPAR-alpha, Beta/delta, and gamma. J. Clin. Invest., 114:1564-1576.

Li XP, et al., (2000). Protective effect of high density lipoprotein on endothelium-dependent vasodilatation. Int. J. Cardiol., 73:231–236.

Liu D, Homan LL, Joseph, Dillon JS., (2004). Genistein Acutely Stimulates Nitric Oxide Synthesis in Vascular Endothelial Cells by a Cyclic Adenosine 5′-Monophosphate-Dependent Mechanism, Endocrinology, 145:12, 5532-5539.

Llevadot J, Murasawa S, Kureishi Y, Uchida S, Masuda H, Kawamoto A, Walsh K, Isner JM, Asahara T, (2001). HMG-CoA reductase inhibitor mobilizes bone marrow-derived endothelial progenitor cells. J Clin Invest., 108:399–405.

McDuffie JE, Coaxum SD, Maleque MA, (1999) 5-Hydroxytryptamine evokes endothelial nitric oxide synthase activation in bovine aortic endothelial cell cultures. Proceedings of the Society for Experimental Biology and Medicine, 221, 386-390.

McDuffie JE, Motley ED, Limbird LE, Maleque, MA, (2000). 5-Hydroxytryptamine Stimulates Phosphorylation of p44/p42 Mitogen-Activated Protein Kinase Activation in Bovine Aortic Endothelial Cell Cultures. Journal of Cardiovascular Pharmacology, 35(3):398-402.

McEniery CM, Schmitt M, Qasem A, Webb DJ, Avolio AP, Wilkinson IB, Cockcroft JR, (2004). Nebivolol Increases Arterial Distensibility In Vivo. Hypertension, 44(3): 305 – 310.

Mason RP, Kalinowski L, Jacob RF, Jacoby AM, Malinski BT, (2005). Nebivolol Reduces Nitroxidative Stress and Restores Nitric Oxide Bioavailability in Endothelium of Black Americans. Circulation, 112(24): 3795 – 3801.

McDuffie JE, Motley ED, Limbird LE, Maleque, MA, (2000). 5-Hydroxytryptamine Stimulates Phosphorylation of p44/p42 Mitogen-Activated Protein Kinase Activation in Bovine Aortic Endothelial Cell Cultures. Journal of Cardiovascular Pharmacology, 35(3):398-402.

Mineo C, Yuhanna IS, Quon MJ, Shaul PW., (2003). HDL-induced eNOS activation is mediated by Akt and MAP kinases. J. Biol. Chem., 278:9142–9149.

Mollnau H, Schulz E, Daiber A, Baldus S, Oelze M, August M, Wendt M, Walter U, Geiger C, Agrawal R, Kleschyov AL, Meinertz T. Munzel T, (2003). Nebivolol Prevents Vascular NOS III Uncoupling in Experimental Hyperlipidemia and Inhibits NADPH Oxidase Activity in Inflammatory Cells. Arterioscler. Thromb. Vasc. Biol., 23(4): 615 – 621.

Moncada S., (2006). Adventures in vascular biology: a tale of two mediators. Phil. Trans. R. Soc. B 29 May 2006 vol. 361 no. 1469 735-759

Moncada S, and Higgs EA, (2006). The discovery of nitric oxide and its role in vascular biology. British Journal of Pharmacology, 147, S193–S201

Mukherjee S, Baksi S, Dart RA, Gollub S, Lazar J, Nair C, Schroeder D, Woolf SH, (2003). {beta}-Blockers With Vasodilatory Actions. Chest, 124(4): 1621 – 1621.

Murakami H, Murakami R, Kambe F, Cao X, Takahashi R, Asai T, Hirai T, Numaguchi Y, Okumura K, Seo H, Murohara T., (2006). Fenofibrate activates AMPK and increases eNOS phosphorylation in HUVEC. Biochem Biophys Res Commun., 341(4):973-8. Epub 2006 Jan 24.

Nebivolol is a long-acting, cardioselective beta-blocker currently licensed for the treatment of hypertension.

Nebivolol

http://www.intekom.com/pharm/adcock/nebilet.html – retrieved on 6/20/2006

Nestel PJ, Yamashita T, Sasahara T, Pomeroy S, Dart A, Komesaroff P, Owen A, Abbey M, (1997). Soy isoflavones improve systemic arterial compliance but not plasma lipids in menopausal and perimenopausal women. Arterioscler Thromb Vasc Biol 17:3392–3398.

Nofer J-R, et al., (2004). HDL induces NO-dependent vasorelaxation via the lysophospholipid receptor S1P3. J. Clin. Invest.,113:569–581.

Nolte MS and JH Karam, (2004). Pancreatic Hormones & Antidiabetic Drugs. Chapter 41 in Katzung, BG., Basic & Clinical Pharmacology. McGraw-Hill, 9th Edition, pp.693-715, in particular, Thiazolidinediones, pp.709-710, 713.

Ohkita Mamoru, Masashi Tawa, Kento Kitada and Yasuo Matsumura (2012). Pathophysiological Roles of Endothelin Receptors in Cardiovascular Diseases,          J Pharmacol Sci 119, 302 – 313 (2012)

Polikandriotis JA, Mazzella LJ, Rupnow HL, Hart CM, (2005). Peroxisome proliferator-activated receptor gamma ligands stimulate endothelial nitric oxide production through distinct peroxisome proliferator-activated receptor gamma-dependent mechanisms. Arterioscler Thromb Vasc Biol., 25(9):1810-6. Epub 2005 Jul 14.

Pott C, Steinritz D, Bölck B, Mehlhorn U, Brixius K, Schwinger RHG, BlochW., (2006). eNOS translocation but not eNOS phosphorylation is dependent on intracellular Ca2+ in human atrial myocardium. Am J Physiol Cell Physiol 290: C1437-C1445.

Ramet ME, et al., (2003). High-density lipoprotein increases the abundance of eNOS protein in human vascular endothelial cells by increasing its half-life. J. Am. Coll. Cardiol., 41:2288–2297.

Reid, Ian A., (2004). Vasoactive Peptides. Chapter 17 in Katzung, BG., Basic & Clinical Pharmacology. McGraw-Hill, 9th Edition, pp. 281 – 297, in particular, Endothelins, pp. 290-293.

Richardson SM, Maleque MA, Motley ED., (2003). 3-Morpholinosyndnonimine inhibits 5-hydroxytryptamine-induced phosphorylation of nitric oxide synthase in endothelial cells.Cell Mol Biol.,49(8):1385-1389.

Ritter JM, Ferro A, Chowienczyk PJ., (2006). Relation between beta-adrenoceptor stimulation and nitric oxide synthesis in vascular control. Eur J Clin Pharmacol., 62 (Supplement 13):109-113.

Rosenzweig A., (2005). Circulating Endothelial Progenitors – Cells as Biomarkers. NEJM., 353;10: 1055-1057.

Rubins et al., (1999). Gemfibrozil for the secondary prevention of coronary heart disease in men with low levels of high-density lipoprotein cholesterol. Veterans Affairs High-Density Lipoprotein Cholesterol Intervention Trial Study Group. N. Engl. J. Med., 341:410–418. 

Sanchez FA, Savalia NB, Duran RG, Lal BK, Boric MP, Duran WN., (2006). Functional significance of differential eNOS translocation. Am J Physiol Heart Circ Physiol., May 5; [Epub ahead of print]

Satake N, Shibata S, (1999). The potentiating effect of genistein on the relaxation induced by isoproterenol in rat aortic rings. Gen Pharmacol, 33:221–227. Shaul PW., (2002). Regulation of endothelial nitric oxide synthase: location, location, location. Annu. Rev. Physiol., 64:749–774.

Shaul, PW and Mineo, C, (2004). HDL action on the vascular wall: is the answer NO? J Clin Invest., 15; 113(4): 509–513.

Shin WS, Hong YH, Peng HB, De Caterina R, Libby P, Liao JK, (1996). Nitric oxide attenuates vascular smooth muscle cell activation by interferon. The role of constitutive NF-B activity. J Biol Chem, 271:11317–11324.

Skidgel RA, Stanislavjevic S, Erdos EG., (2006). Kinin- and angiotensin-converting enzyme (ACE) inhibitor-mediated nitric oxide production in endothelial cells. Biol Chem., 387(2):159-65.

Spieker et al., (2002). High-density lipoprotein restores endothelial function in hypercholesterolemic men. Circulation, 105:1399–1402.

Spyridopoulos I, Haendeler J, Urbich C, Brummendorf TH, Oh H, Schneider MD, Zeiher AM, Dimmeler S, (2004). Statins enhance migratory capacity by upregulation of the telomere repeat-binding factor TRF2 in endothelial progenitor cells. Circulation, 110:3136 –3142.

Squadrito F, Altavilla D, Crisafulli A, Saitta A, Cucinotta D, Morabito N, D’Anna R, Corrado F, Ruggeri P, Frisina N, Squadrito G, (2003). Effect of genistein on endothelial function in postmenopausal women: a randomized, double-blind, controlled study. Am J Med, 114:470–476.

Sütsch G, Kiowski W, Yan X-W, Hunziker P, Christen S, Strobel W, Kim J-H, Rickenbacher P, Bertel O., (1998). Short-Term Oral Endothelin-Receptor Antagonist Therapy in Conventionally Treated Patients With Symptomatic Severe Chronic Heart Failure. Circulation, 98:2262-2268

Uittenbogaard A, Shaul PW, Yuhanna IS, Blair A, Smart EJ., (2000). High density lipoprotein prevents oxidized low density lipoprotein-induced inhibition of endothelial nitric-oxide synthase localization and activation in caveolae. J. Biol. Chem., 275:11278–11283.

van der Schouw YT, de Kleijn MJ, Peeters PH, Grobbee DE, (2000). Phyto-oestrogens and cardiovascular disease risk. Nutr Metab Cardiovasc Dis., 10:154–167.

Van Nueten L, Dupont AG, Vertommen C, Goyvaerts H, Robertson JI., (1997). A dose-response trial of nebivolol in essential hypertension. J Hum Hypertens.,11(2):139-44.

Vasa M, Fichtlscherer S, Adler K, Aicher A, Martin H, Zeiher AM, Dimmeler S. (2001a). Increase in circulating endothelial progenitor cells by statin therapy in patients with stable coronary artery disease. Circulation, 103:2885–2890.

Verma S, Szmitko, PE, (2006). The vascular biology of peroxisome proliferator-activated receptors: Modulation of atherosclerosis. Can J Cardiol, 22 (Suppl B):12B-17B.

Walker HA, Dean TS, Sanders TA, Jackson G, Ritter JM, Chowienczyk PJ, (2001). The phytoestrogen genistein produces acute nitric oxide-dependent dilation of human forearm vasculature with similar potency to 17ß-estradiol. Circulation, 103:258–262.

Walter DH, Rittig K, Bahlmann FH, Kirchmair R, Silver M, Murayama T, Nishimura H, Losordo DW, Asahara T, Isner JM, (2002). Statin therapy accelerates reendothelialization: a novel effect involving mobilization and incorporation of bone marrow-derived endothelial progenitor cells. Circulation, 105:3017–3024.

Wang C-H, Ciliberti N, Li S-H, Szmitko PE, Weisel RD, Fedak PWM, Al-Omran M, Cherng W-J, Li R-K, Stanford WL, Verma S., (2004). Rosiglitazone facilitates angiogenic progenitor cell differentiation toward endothelial lineage: a new paradigm in glitazone pleiotropy. Circulation, 109:1392-1400.

Werner N, Junk S, Laufs L, Link A, Walenta K, Bohm M, Nickenig G., (2003). Intravenous transfusion of endothelial progenitor cells reduces neointima formation after vascular injury. Circ Res., 93:e17– e24.

Wilson PW, Abbott RD, Castelli WP, (1988). High density lipoprotein cholesterol and mortality. The Framingham Heart Study.Arteriosclerosis, 8:737–741.

Xu H-L, Feinstein DL, Santizo RA, Koenig HM, Pelligrino DA., (2002).Agonist-specific differences in mechanisms mediating eNOS-dependent pial arteriolar dilation in rats. Am J Physiol Heart Circ Physiol., 282:H237-H243 

Yu J, Rudic RD, Sessa WC, (2002). Nitric oxide-releasing aspirin decreases vascular injury by reducing inflammation and promoting apoptosis. Lab Invest, 82:825–832.

Yuhanna IS, et al., (2001). High-density lipoprotein binding to scavenger receptor-BI activates endothelial nitric oxide synthase. Nat. Med., 7:853–857.

Zeiher AM, Schachlinger V, Hohnloser SH, Saurbier B, Just H., (1994). Coronary atherosclerotic wall thickening and vascular reactivity in humans. Elevated high-density lipoprotein levels ameliorate abnormal vasoconstriction in early atherosclerosis. Circulation, 89:2525–2532.

Read Full Post »

Calcium Dependent NOS Induction by Sex Hormones: Estrogen

Reporter and Curator:  Sudipta Saha, Ph.D.

Nitric oxide (NO) synthases (NOSs) constitute a family of isozymes that catalyze the oxidation of L-arginine to NO and citrulline. First identified in the vascular endothelium, NO synthesis has subsequently been shown to play important roles in:

  • the regulation of vascular and gastrointestinal tone,
  • in cell-mediated cytotoxicity against bacteria and tumors, and
  • in a variety of central and peripheral nervous system activities.

NOSs can be divided into three functional classes based on their sensitivity to calcium.

  • The cytokine- or bacterial product-inducible isoenzyme iNOS binds calmodulin tightly at resting intracellular calcium concentrations.
  • The constitutive forms, isozymes eNOS (originally described in endothelial cells) and
  • nNOS (originally described in neuronal tissue), bind calmodulin in a reversible and calcium-dependent fashion.

The mechanisms by which their synthesis is controlled are unknown. The cDNA species encoding the rat, mouse, and human nNOS, the human and bovine eNOS, and iNOS from several species and cell types have been cloned and sequenced. The three human isozymes characterized to date are distinct, with their deduced protein sequences showing only 50-60%o amino acid identity. nNOS, which in rats and humans localizes to neurons in the central and peripheral nervous system and colocalizes with NADPHdiaphorase activity, has also been shown to be widely distributed in several non-neuronal tissues including human skeletal muscle.

It had been thought that both nNOS and eNOS were purely constitutive enzymes, although studies suggest eNOS may be induced by shear stress. Studies demonstrate that these NOSs can be induced in several tissues during pregnancy and in nonpregnant female and male animals by estradiol and that in skeletal muscle it is accompanied by an increase in NOS-specific mRNA.

Evidences emerging from various laboratories showed that there is an increase in the release of NO from the vasculature during pregnancy. Furthermore, treatment of pregnant animals at the end of gestation with tamoxifen reduced NOS activity in the cerebellum, an organ where tamoxifen acts as a pure estrogen-receptor antagonist. Thus, the increase in calcium-dependent NOS activity during pregnancy is mediated by estrogen. This conclusion is supported by the fact that treatment of nonpregnant females and male animals with estradiol also increased calcium-dependent NOS activity in all tissues studied.

Interestingly, testosterone treatment also increased cerebellar NOS activity without affecting other tissues. However, testosterone may increase brain NOS by directly binding estrogen receptors as has been reported. Furthermore, the cerebellum was the only tissue in the male to respond to a 5-day course of estradiol, suggesting that it may have a larger number and/or a greater availability of estrogen receptors than other tissues. In addition, the brain is rich in aromatase, which converts testosterone into estradiol. This, together with the observation that progesterone does not induce NOS, indicates that the induction of both nNOS and eNOS is specific for estrogen and not a characteristic of all sex steroids. These experiments do not exclude the possibility that the addition of progesterone might modify the estradiol effect.

The increases in NOS activity are the result of augmented enzyme synthesis (enzyme induction) since they are accompanied by increases in the specific mRNAs for both eNOS and nNOS. It is not, however, possible to tell whether the increases in mRNA are caused by an upregulation of mRNA synthesis (transcriptional induction) or decreased mRNA breakdown.

Although calcium-dependent NOS activity was increased by estradiol in tissues obtained from both female and male guinea pigs, a longer duration of treatment was necessary in the male. The most likely explanation for this observation is that the number or availability of estrogen receptors is initially too low in most tissues of the male and requires a period of estrogen priming. Although other factors may play a role, the duration of exposure may well explain the observation that the effect of pregnancy on NOS-specific mRNA is greater than estradiol alone.

The observation that estradiol induces calcium-dependent NOSs has several important implications:

  • An increase in release of NO from the endothelium would decrease vascular tone and contractility, events that are characteristic in pregnancy.
  • Heterogeneity among tissue endothelium regarding the effects of estrogen on basal NO release could explain the selective redistribution of maternal cardiac output to organs important for a successful pregnancy.
  • Consistent with this possibility is the observation that the effect of pregnancy on endothelium-derived NO is greatest in the uterine artery, followed by the mesenteric artery and then renal arteries.
  • An alternative hypothesis to explain the adaptation of smooth muscle to pregnancy is that it is caused by prostacyclin. Prostacyclin is increased during pregnancy and contributes to the observed reduced contractility of the ovine uterine artery to angiotensin II.

However, estradiol does not increase the synthesis of prostacyclin by the endothelium, nor does inhibition of prostacyclin synthesis prevent the effects of pregnancy on smooth muscle. In addition, both the incidence of esophageal reflux and the gastrointestinal transit time are increased during pregnancy. Although this phenomenon has previously been attributed to a direct effect of progesterone, NO is a powerful dilator of the gastrointestinal smooth muscle. If the increase in NOS activity observed in the esophagus applies to the bowel, enhanced NO might be the mechanism underlying both increased esophageal reflux and transit time.

The biological signifcance of an estradiol-dependent increase in the NOS in the central nervous system is of great interest and deserves further investigation. Furthermore, an estradiol-mediated increase in NOS in the vasculature could be the mechanism whereby premenopausal women are protected from coronary artery disease since increased NOS may slow the development of atherosclerosis and reduce the contractile response to acute thrombosis. Finally, the induction of calcium-dependent NOS enzymes by estradiol suggests that the present classification of this family of enzymes into constitutive and inducible types needs to be revised, since eNOS and nNOS enzymes at least are both constitutive and inducible.

Source References:

http://www.ncbi.nlm.nih.gov/pubmed?term=Calcium%20dependent%20NOS%20induction%20by%20sex%20hormones

Other research published on Nitric Oxide on this Scientific Web Site include the following:

Nitric Oxide in bone metabolism July 16, 2012

Author: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/07/16/nitric-oxide-in-bone-metabolism/?goback=%2Egde_4346921_member_134751669


Nitric Oxide production in Systemic sclerosis July 25, 2012

Curator: Aviral Vatsa, PhD, MBBS

http://pharmaceuticalintelligence.com/2012/07/25/nitric-oxide-production-in-systemic-sclerosis/?goback=%2Egde_4346921_member_138370383

Nitric Oxide Signalling Pathways August 22, 2012 by

Curator/ Author: Aviral Vatsa, PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/22/nitric-oxide-signalling-pathways/?goback=%2Egde_4346921_member_151245569

Nitric Oxide: a short historic perspective August 5, 2012

Author/Curator: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/05/nitric-oxide-a-short-historic-perspective-7/


Nitric Oxide: Chemistry and function August 10, 2012

Curator/Author: Aviral Vatsa PhD, MBBS

http://pharmaceuticalintelligence.com/2012/08/10/nitric-oxide-chemistry-and-function/?goback=%2Egde_4346921_member_145137865

Nitric Oxide and Platelet Aggregation August 16, 2012 by

Author: Dr. Venkat S. Karra, Ph.D.

http://pharmaceuticalintelligence.com/2012/08/16/no-and-platelet-aggregation/?goback=%2Egde_4346921_member_147475405


The rationale and use of inhaled NO in Pulmonary Artery Hypertension and Right Sided Heart Failure August 20, 2012

Author: Larry Bernstein, MD

http://pharmaceuticalintelligence.com/2012/08/20/the-rationale-and-use-of-inhaled-no-in-pulmonary-artery-hypertension-and-right-sided-heart-failure/

Nitric Oxide: The Nobel Prize in Physiology or Medicine 1998 Robert F. Furchgott, Louis J. Ignarro, Ferid Murad August 16, 2012

Reporter: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/08/16/nitric-oxide-the-nobel-prize-in-physiology-or-medicine-1998-robert-f-furchgott-louis-j-ignarro-ferid-murad/


Coronary Artery Disease – Medical Devices Solutions: From First-In-Man Stent Implantation, via Medical Ethical Dilemmas to Drug Eluting Stents August 13, 2012

Author: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/08/13/coronary-artery-disease-medical-devices-solutions-from-first-in-man-stent-implantation-via-medical-ethical-dilemmas-to-drug-eluting-stents/

Cardiovascular Disease (CVD) and the Role of agent alternatives in endothelial Nitric Oxide Synthase (eNOS) Activation and Nitric Oxide Production July 19, 2012

Curator and Research Study Originator: Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2012/07/19/cardiovascular-disease-cvd-and-the-role-of-agent-alternatives-in-endothelial-nitric-oxide-synthase-enos-activation-and-nitric-oxide-production/

Macrovascular Disease – Therapeutic Potential of cEPCs: Reduction Methods for CV Risk

An Investigation of the Potential of circulating Endothelial Progenitor Cells (cEPCs) as a Therapeutic Target for Pharmacological Therapy Design for Cardiovascular Risk Reduction: A New Multimarker Biomarker Discovery

Curator: Aviva Lev-Ari, PhD, RN, July 12, 2012

http://pharmaceuticalintelligence.com/2012/07/02/macrovascular-disease-therapeutic-potential-of-cepcs-reduction-methods-for-cv-risk/


Bone remodelling in a nutshell June 22, 2012

Author: Aviral Vatsa, Ph.D., MBBS

http://pharmaceuticalintelligence.com/2012/06/22/bone-remodelling-in-a-nutshell/

Targeted delivery of therapeutics to bone and connective tissues: current status and challenges – Part 1

AuthorL Aviral Vatsa, PhD, September 23, 2012

http://pharmaceuticalintelligence.com/2012/09/23/targeted-delivery-of-therapeutics-to-bone-and-connective-tissues-current-status-and-challenges-part-i/

Calcium dependent NOS induction by sex hormones: Estrogen

Curator: S. Saha, PhD, October 3, 2012

http://pharmaceuticalintelligence.com/2012/10/03/calcium-dependent-nos-induction-by-sex-hormones/


Nitric Oxide and Platelet Aggregation

Author V. Karra, PhD, August 16, 2012

http://pharmaceuticalintelligence.com/2012/08/16/no-and-platelet-aggregation/

Bystolic’s generic Nebivolol – positive effect on circulating Endothelial Progenitor Cells endogenous augmentation

Curator: Aviva Lev-Ari, PhD, July 16, 2012

http://pharmaceuticalintelligence.com/?s=Nebivolol


Read Full Post »

Author: Stephen J. Williams, PhD

     The finding that a substance, derived from vascular endothelium, that could control vascular tone and induce smooth muscle relaxation, led to the discovery of nitric oxide (NO) as a major physiological mediator (1) in many cell types and processes.  Other investigators, working with platelets, determined that nitric oxide is a potent inhibitor, via an autocrine pathway, of platelet aggregation and adhesion to the vessel wall (2).  Nitric oxide is also an important regulator of neurotransmission in the nonadrenergic-noncholinergic system in gastric tissue (3,4).   In addition nitric oxide is involved in macrophage-mediated cytotoxicity, (5)based on the observation the cytotoxic action of macrophages required external arginine, which summarily was converted to citrulline, releasing  the nitric oxide involved in the cell-killing process.  The above physiological responses represent highly regulated, short-term responses that, as seen with classical receptor-based agonists such as epinephrine, terminate once the agonist (NO) is removed.   Given the short half-life of nitric oxide and these rapid physiologic responses, nitric oxide has been given the role of a second messenger within the cell.

However nitric oxide also produces some physiologically, pharmacologically, and pathologically relevant changes, lasting longer time periods, which is the main focus of this article.  For example, nitric oxide is important in the development of long term potentiation (a model of learning and memory), neural plasticity, and neurite outgrowth, revealing nitric oxide can induce more permanent changes in cellular and tissue reorganization (6-9).  Other pathologic and toxicological responses to nitric oxide include cell death from excitotoxic amino acids (glutamate, kainite), oxidative stress, DNA and protein damage, and disease progression in Alzheimer’s disease, epilepsy, aging, apoptosis and Huntington’s chorea (10-12).  These effects persist over longer time frames than the effects which most second messenger systems occur.  These cellular changes can be described by biochemical changes on protein and nucleic acid modification, metabolism (13-15), DNA synthesis and replication, and molecular and organelle reorganization.  The pharmacological and toxicological implications of such cellular changes are inherent in the persistent effects of nitric oxide on biological systems.  The mechanism of nitric oxide-induced physiology and toxicology had been assumed to involve the stimulation of soluble guanylate cyclase, raising intracellular cGMP levels.  As discussed further, this mechanism of action does not account for all the actions of nitric oxide, especially in nitric oxide-induced pathologies.  Other mechanisms of action include post-translational modifications of proteins such as S-nitrosylations, ADP-ribosylations, and a unique nonenzymatic covalent attachment of NAD+ to the regulatory site of glyceraldehyde 3-phosphate dehydrogenase (GAPDH), a reaction specific to this dehydrogenase.  GAPDH is a true multifunctional protein involved in diverse cellular functions such as glycolysis, endocytosis, RNA processing and stability, DNA replication and repair, and involved in apoptosis.  GAPDH has been implicated in trinucleotide repeat neurodegenerative disorders such as Huntington’s disease, spinocerebellar ataxia, via binding to the polyglutamated forms of huntingtin and ataxin, protein modifications only seen in these respective diseases. GAPDH has also been implicated in Alzheimer’s disease as well, in genetic linkage studies as well as a β-amyloid precursor protein binding partner (for reviews see (16-20)).

Next to phosphorylation, ADP ribosylation and NAD+ modifications are the second most  common enzymatic  protein modifications in nature and regulates many cellular processes in nervous tissue, tumoral cell growth, cytoskeletal function, cell death and apoptosis, immune function, and bacterial cytotoxicity(21,22). These include poly ADP-ribosylations such as histones in the apoptotic process, and ADP-ribosylation of G-proteins by pertussis and cholera toxin. Interestingly, nitric oxide and other oxidants promote nonenzymatic ribosylation of proteins such as GAPDH.  Unlike the enzymatic reactions, this modification is covalent and generally considered irreversible and either involves nitrosylation of critical reactive cysteine residues or nitric oxide-mediated attachment of the whole NAD+ moiety, a reaction akin to aging of enzymes by reactive oxygen species.  There have been multiple intracellular targets of nitric oxide, with the result of inhibiting activity and/or protein interactions.  These include mitochondrial enzymes such as aconitase (23) and cytochrome oxidase (24), cytosolic enzymes such as cyclooxygenase and affect heme-containing proteins hemoglobin and myoglobin.  Such nitric oxide mediated effects on these systems were cGMP-independent, therefore independent of nitric oxide synthase.  The inhibition of GAPDH glycolytic activity by nitric oxide and NO-mediated NAD+ modification has been widely studied (21,25) and widely accepting to be important in nitric oxide mediated pathology (16,26-33).

So can this NO-NAD+ modification of GAPDH be useful as a therapeutic target for diseases such as Huntington’s, Alzheimer’s or other nitric oxide associated pathologies?   This is as much an intriguing idea as one fraught with caveats and technical issues.   First there is ample evidence that alterations of GAPDH structure/function exist in these neurodegenerative diseases and evidence that this type of modification may be important in the etiology of such diseases(34-41).

Second, as mentioned before, this modification is unique for GAPDH and would offer a disease-specific target(42).  Third, and most interesting, is the multifunctionality of GAPDH, therefore such modification has the possibility for affecting many processes involved in the disease progression.    However there is the big caveat and problem.  Such NO-NAD+ modifications are a covalent reaction, thought to be irreversible.  Studies on purified GAPDH reveal such modification is released by chemicals that can reduce the cysteine covalent bond such as HgCl2 or NaOH treatment(17).  However such treatment would be impractical for in-vivo use.  The ideal situation would be the discovery of an enzyme activity comparable to phosphatases which could enzymatically release the NO-NAD+ modification from GAPDH. A proof of concept experiment could involve creation of a genetically engineered enzyme capable of this reaction.  Therapeutic use of such an enzyme would depend of course on bioavailability.  Interestingly there has been evidence of cellular NO reductase activities, capable of removing the S-nitrosylation on reactive thiols.  Enzymes with denitrosylation activities include the thioredoxin system, superoxide dismutase, and xanthine oxidoreductase (34-40).  Possible therapeutic strategies may include regulation of these intracellular reductase activities.

1.            Furchgott, R. F., and Vanhoutte, P. M. (1989) FASEB journal : official publication of the Federation of American Societies for Experimental Biology 3, 2007-2018

2.            Radomski, M. W., Zakar, T., and Salas, E. (1996) Methods in enzymology 269, 88-107

3.            Barbier, A. J., and Lefebvre, R. A. (1993) The Journal of pharmacology and experimental therapeutics 266, 172-178

4.            Dick, J. M., and Lefebvre, R. A. (1997) Naunyn-Schmiedeberg’s archives of pharmacology 356, 488-494

5.            Hibbs, J. B., Jr., Taintor, R. R., Vavrin, Z., and Rachlin, E. M. (1988) Biochemical and biophysical research communications 157, 87-94

6.            Sunico, C. R., Portillo, F., Gonzalez-Forero, D., and Moreno-Lopez, B. (2005) The Journal of neuroscience : the official journal of the Society for Neuroscience 25, 1448-1458

7.            Koriyama, Y., Takagi, Y., Chiba, K., Yamazaki, M., Arai, K., Matsukawa, T., Suzuki, H., Sugitani, K., Kagechika, H., and Kato, S. (2011) Journal of neurochemistry 119, 1232-1242

8.            Sen, N., and Snyder, S. H. (2011) Proceedings of the National Academy of Sciences of the United States of America 108, 20178-20183

9.            Zoubovsky, S. P., Pogorelov, V. M., Taniguchi, Y., Kim, S. H., Yoon, P., Nwulia, E., Sawa, A., Pletnikov, M. V., and Kamiya, A. (2011) Biochemical and biophysical research communications 408, 707-712

10.          Brune, B., and Lapetina, E. G. (1995) Genetic engineering 17, 149-164

11.          Brune, B., and Mohr, S. (2001) Current protein & peptide science 2, 61-72

12.          Brune, B., Mohr, S., and Messmer, U. K. (1996) Reviews of physiology, biochemistry and pharmacology 127, 1-30

13.          Galli, F., Rossi, R., Di Simplicio, P., Floridi, A., and Canestrari, F. (2002) Nitric oxide : biology and chemistry / official journal of the Nitric Oxide Society 6, 186-199

14.          Rudkouskaya, A., Sim, V., Shah, A. A., Feustel, P. J., Jourd’heuil, D., and Mongin, A. A. (2010) Free radical biology & medicine 49, 757-769

15.          Borderie, D., Le Marechal, H., Ekindjian, O. G., and Hernvann, A. (2000) Cell biology international 24, 285-289

16.          Mazzola, J. L., and Sirover, M. A. (2002) Neurotoxicology 23, 603-609

17.          Williams, S. J., and Sirover, M. A. (1999) Mechanism of Nitric Oxide-Protein Interactions: Species Specific NO-NAD+ Modification and Kinetic Alteration of the Glycolytic Protein Glyceraldehyde 3-Phosphate Dehydrogenase. Temple University, Temple University Press

18.          Sirover, M. A. (2005) Journal of cellular biochemistry 95, 45-52

19.          Sirover, M. A. (2011) Biochimica et biophysica acta 1810, 741-751

20.          Sirover, M. A. (2012) Journal of cellular biochemistry 113, 2193-2200

21.          McDonald, L. J., and Moss, J. (1993) Proceedings of the National Academy of Sciences of the United States of America 90, 6238-6241

22.          McDonald, L. J., and Moss, J. (1994) Molecular and cellular biochemistry 138, 201-206

23.          Drapier, J. C., and Hibbs, J. B., Jr. (1996) Methods in enzymology 269, 26-36

24.          Torres, J., Cooper, C. E., and Wilson, M. T. (1998) The Journal of biological chemistry 273, 8756-8766

25.          Dimmeler, S., and Brune, B. (1993) FEBS letters 315, 21-24

26.          Mazzola, J. L., and Sirover, M. A. (2001) Journal of neurochemistry 76, 442-449

27.          Mazzola, J. L., and Sirover, M. A. (2002) Brain research. Molecular brain research 100, 95-101

28.          Mazzola, J. L., and Sirover, M. A. (2003) Biochimica et biophysica acta 1622, 50-56

29.          Mazzola, J. L., and Sirover, M. A. (2003) Journal of neuroscience research 71, 279-285

30.          Mazzola, J. L., and Sirover, M. A. (2004) Journal of neuroscience methods 137, 241-246

31.          Mazzola, J. L., and Sirover, M. A. (2005) Biochimica et biophysica acta 1722, 168-174

32.          Nakaizumi, A., Horie, T., Kida, T., Kurimoto, T., Sugiyama, T., Ikeda, T., and Oku, H. (2012) Cellular and molecular neurobiology 32, 95-106

33.          Nakamura, T., and Lipton, S. A. (2009) Neuron 63, 3-6

34.          Beigi, F., Gonzalez, D. R., Minhas, K. M., Sun, Q. A., Foster, M. W., Khan, S. A., Treuer, A. V., Dulce, R. A., Harrison, R. W., Saraiva, R. M., Premer, C., Schulman, I. H., Stamler, J. S., and Hare, J. M. (2012) Proceedings of the National Academy of Sciences of the United States of America 109, 4314-4319

35.          Benhar, M., Forrester, M. T., Hess, D. T., and Stamler, J. S. (2008) Science 320, 1050-1054

36.          Benhar, M., Forrester, M. T., and Stamler, J. S. (2009) Nature reviews. Molecular cell biology 10, 721-732

37.         Duan, S., and Chen, C. (2007) Cellular & molecular immunology 4, 353-358

38.          Straub, A. C., Billaud, M., Johnstone, S. R., Best, A. K., Yemen, S., Dwyer, S. T., Looft-Wilson, R., Lysiak, J. J., Gaston, B., Palmer, L., and Isakson, B. E. (2011) Arteriosclerosis, thrombosis, and vascular biology 31, 399-407

39.          Wu, C., Parrott, A. M., Fu, C., Liu, T., Marino, S. M., Gladyshev, V. N., Jain, M. R., Baykal, A. T., Li, Q., Oka, S., Sadoshima, J., Beuve, A., Simmons, W. J., and Li, H. (2011) Antioxidants & redox signaling 15, 2565-2604

40.          Zheng, W., Liu, Y., Pan, S., Yuan, W., Dai, Y., and Wei, J. (2011) Applied microbiology and biotechnology 90, 1763-1772

41.          Knott, A. B., and Bossy-Wetzel, E. (2009) Antioxidants & redox signaling 11, 541-554

42.          Hara, M. R., Thomas, B., Cascio, M. B., Bae, B. I., Hester, L. D., Dawson, V. L., Dawson, T. M., Sawa, A., and Snyder, S. H. (2006) Proceedings of the National Academy of Sciences of the United States of America 103, 3887-3889

Other research paper on Nitric Oxide were published on this Scientific Web site as follows:

Discovery of nitric oxide and its role in vascular biology

Nitric Oxide and Platelet Aggregation

Inhaled NO in Pulmonary Artery Hypertension and Right Sided Heart Failure

Cardiovascular Disease (CVD) and the Role of agent alternatives in endothelial Nitric Oxide Synthase (eNOS) Activation and Nitric Oxide Production

Nitric Oxide in bone metabolism

Nitric oxide and signalling pathways

Rationale of NO use in hypertension and heart failure

Interaction of Nitric Oxide and Prostacyclin in Vascular Endothelium

Nitric Oxide has a ubiquitous role in the regulation of glycolysis -with a concomitant influence on mitochondrial function

Read Full Post »

« Newer Posts - Older Posts »