Feeds:
Posts
Comments

Posts Tagged ‘Larry H. Bernstein’

Genomic Model of Organogenesis: Computer Modeling of the Gene Regulatory Networks

Curator: Larry H Bernstein, MD, FACP


Caltech biologists created the first predictive computational model of gene networks that control the development of sea-urchin embryos. This model outlines the paths cells take in forming different body parts—muscles, bones, heart. In the process the organ development follows a genetic blueprint, which consists of complex webs of interacting genes called gene regulatory networks.

This model, the scientists say, does a remarkably good job of calculating what these networks do to control the fates of different cells in the early stages of sea-urchin development—confirming that the interactions among a few dozen genes suffice to tell an embryo how to start the development of different body parts in their respective spatial locations. The model is also a powerful tool for understanding gene regulatory networks in a way not previously possible, allowing scientists to better study the genetic bases of both development and evolution.

“We have never had the opportunity to explore the significance of these networks before,” says Eric Davidson, the Norman Chandler Professor of Cell Biology at Caltech. “The results are amazing to us.”

The researchers described their computer model in a paper in the Proceedings of the National Academy of Sciences that appeared as an advance online publication on August 27.

The model encompasses the gene regulatory network that controls the first 30 hours of the development of endomesoderm cells, which eventually form the embryo’s gut, skeleton, muscles, and immune system. This network—so far the most extensively analyzed developmental gene regulatory network of any animal organism—consists of about 50 regulatory genes that turn one another on and off.

To create the model, the researchers distilled everything they knew about the network into a series of logical statements that a computer could understand. “We translated all of our biological knowledge into very simple Boolean statements,” explains Isabelle Peter, a senior research fellow and the first author of the paper. In other words, the researchers represented the network as a series of if-then statements that determine whether certain genes in different cells are on or off (i.e., if gene A is on, then genes B and C will turn off).

By computing the results of each sequence hour by hour, the model determines when and where in the embryo each gene is on and off. Comparing the computed results with experiments, the researchers found that the model reproduced the data almost exactly. “It works surprisingly well,” Peter says.

Some details about the network may still be uncovered, the researchers say, but the fact that the model mirrors a real embryo so well shows that biologists have indeed identified almost all of the genes that are necessary to control these particular developmental processes. The model is accurate enough that the researchers can tweak specific parts—for example, suppress a particular gene—and get computed results that match those of previous experiments.

Allowing biologists to do these kinds of virtual experiments is precisely how computer models can be powerful tools, Peter says. Gene regulatory networks are so complex that it is almost impossible for a person to fully understand the role of each gene without the help of a computational model, which can reveal how the networks function in unprecedented detail.

Studying gene regulatory networks with models may also offer new insights into the evolutionary origins of species. By comparing the gene regulatory networks of different species, biologists can probe how they branched off from common ancestors at the genetic level.

So far, the researchers have only modeled one gene regulatory network, but their goal is to model the networks responsible for every part of a sea-urchin embryo, to build a model that covers not just the first 30 hours of a sea urchin’s life but its entire embryonic development. Now that this modeling approach has been proven effective, Davidson says, creating a complete model is just a matter of time, effort, and resources. 

The title of the PNAS paper is “Predictive computation of genomic logic processing functions in embryonic development.”

http://www.pnas.org/content/109/41/16434.abstract

In addition to Peter and Davidson, the other author on the PNAS paper is Emmanuel Faure, a former Caltech postdoctoral scholar who is now at the École Polytechnique in France. This work was supported by the National Institute of Child Health and Human Development and the National Institute of General Medical Sciences.

A small part of the network is shown here. Image: Caltech/Davidson Lab
After a decade detailing how these gene networks control development in sea-urchin embryos, they   constructed a computational model of sea-urchin embryonic development.
VIEW VIDEO Courtesy of genenetwork

Introduction to Gene Network

GeneNetwork is a group of linked data sets and tools used to study complex networks of genes, molecules, and higher order gene function and phenotypes. GeneNetwork combines more than 25 years of legacy data generated by hundreds of scientists together with sequence data (SNPs) and massive transcriptome data sets (expression genetic or eQTL data sets). The quantitative trait locus (QTL) mapping module that is built into GN is optimized for fast on-line analysis of traits that are controlled by combinations of gene variants and environmental factors.

Historic Highlights of Organ Development

Otto Warburg. Improved manometric techniques of Van Slyke and Haldane in 1920’s and used tissue slices of 100-150 layers of cells, allowing measurement of energy reactions using oxygen without damaging cells.  He demonstrated the rate of oxygen utilization and the respiration of sea urchin egg can increase up to sixfold after fertilization.

Otto Warburg. Hans Krebs.  Clarendon Press. 1981.
Thomas Hunt Morgan.  Explored the mechanism of heredity in accounting for the transmission of variations from 1910 -1928, and claimed that while Mendelian theory could predict breeding results, it could not describe the true processes of heredity.
N William Ingalls (1918)
Carnegie Institution No. 23 – Contributions to Embryology
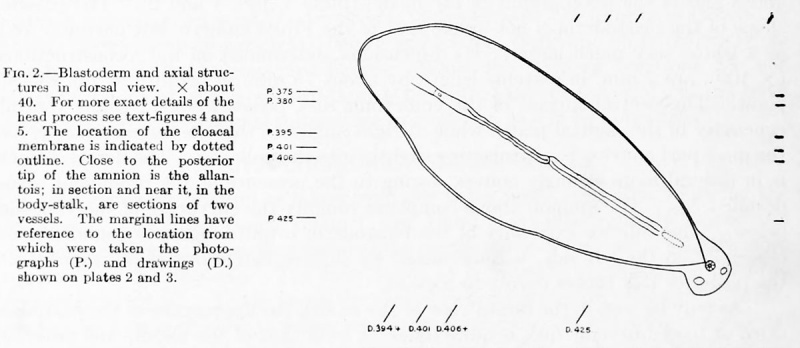
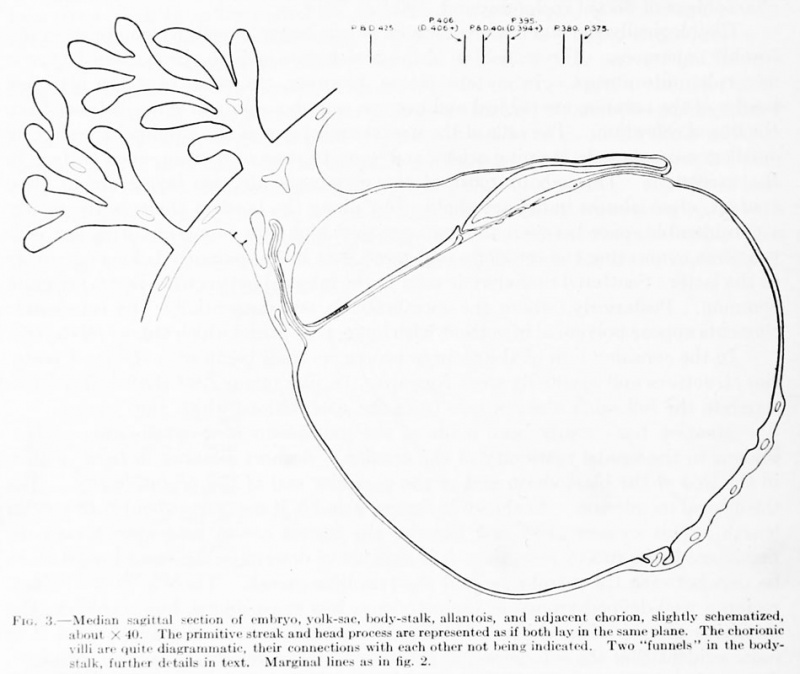
The conditions found here in the cloacal membrane are such as would be expected from the gradual and not entirely regular transformation of the streak into the membrane. All that is required is an arrest of mesoderm formation and the subsequent separation of the upper and middle germ-layers. The entoderm below is a perfectly distinct layer the cells of which have nuclei larger and paler than those of the other layers.
The embryo which we have just described represents an extremely interesting and instructive stage in the ontogenesis of man. In it are found as many important features of early development as could well be expected in one and the same specimen.  Any discussion of the findings in this embryo naturally revolves around the question of gastrulation and the formation of the germ-layers. One should not conclude too much from a single stage, either as to antecedent or later conditions; but every stage must be in harmony with those which precede or follow.
 Hans Spemann (1869 – 1941). Awarded a Nobel Prize in Physiology or Medicine in 1935 for his discovery of the effect now known as embryonic induction. Spemann found that one half of two blastomeres could form a whole embryo, but observed that the plane of division was crucial. This gave support to the concept of a morphogenetic field, a concept of which Spemann learned from Paul Alfred Weiss.  He and colleagues described an area in the embryo, the portions of which, upon transplantation into a second embryo, organized or “induced” secondary embryonic primordia regardless of location.
NOBEL PRIZE FOR GENETICS OF DEVELOPMENT  By Sean Henahan, Access Excellence
Three biologists have been awarded the 1995 Nobel Prize in Medicine for their pioneering work on the genetic control of embryonic development. The researchers work with the Drosophila melanogaster fruit fly provided key information on factors influencing human embryology and birth defects. The recipients of this year’s prize are Drs. Edward Lewis, of the California Institute of Technology; Christiane Nuesslein-Volhard, of Germany’s Max-Planck Institute; and Eric Wieschaus, at Princeton. Each of the three were involved in the early research to find the genes controlling development.
The genes were arranged in the same order on the chromosomes as the body segments they controlled. The first genes in a complex of developmental genes controlled the head region, genes in the middle controlled abdominal segments while the last genes controlled the posterior (“tail”) region.  The fertilized egg is spherical. It divides rapidly to form 2, 4 , 8 cells and so on. Up until the 16-cell stage the early embryo is symmetrical and all cells are equal. Beyond this point, cells begin to specialize and the embryo becomes asymmetrical. Within a week it becomes clear what will form the head and tail regions and what will become the ventral and dorsal sides of the embryo. Somewhat later in development the body of the embryo forms segments and the position of the vertebral column is fixed.
The results of Nuesslein-Volhard and Wieschaus, first published in the English scientific journal Nature during the fall of 1980, established that genes controlling development could be systematically identified. The number of genes involved was limited and they could be classified into specific functional groups.
In 1978 Lewis summarized his results in a review article and formulated theories about how homeotic genes interact, how the gene order corresponded to the segment order along the body axis, and how the individual genes were expressed. This induced other scientists to examine families of analogous genes in higher organisms. In mammalians, the gene clusters first found in Drosophila have been duplicated into four complexes known as the HOX genes. Human genes in these complexes are sufficiently similar to their Drosophila analogues they can restore some of the normal functions of mutant Drosophila genes.
The individual genes within the four HOX gene families in vertebrates occur in the same order as they do in Drosophila, and they exert their influence along the body axis in agreement with the colinearity principle first discovered by Lewis in Drosophila. It is likely that mutations in such important genes are responsible for some of the early, spontaneous abortions that occur in man, and for some of the about 40% of the congenital malformations that develop due to unknown reasons.
Lewis, E.B. (1978) A Gene Complex Controlling Segmentation in Drosophila. Nature 276, 565-570 Nuesslein-Volhard, C., Wieschaus, E. (1980). Mutations Affecting Segment Number and Polarity in Drosophila. Nature 287, 795-801
 Sir John B Gurdon and Shinya Yamanaka. 2012 Nobel Prize for Physiology and Medicine.
the specialisation of cells is reversible,and mature, specialized cells can be reprogrammed.

Work by the Stanford Group on Gene Networks Computational Model

Protein-folding Simulation: Stanford’s Framework for Testing and Predicting Evolutionary Outcomes in Living Organisms – Work by Marcus Feldman

Other Notable and Related Research.
LASAGNA-Search: An integrated web tool for transcription factor binding site search and visualization.  C Lee and Chun-Hsi Huang.
Length-Aware Site Alignment Guided by Nucleotide Association (LASAGNA)
1. unaligned variable-length TF binding sites
2. used for high throughput techniques, such as ChIP-seq
3. a collection of 1726 models
4. automatic promoter sequence retrieval
5. visualization
Biotechniques Rapid Dispatches   http://dx.doi.org/10.2144/000113999

Gene Splicing by Overlap Extension: Tailor-Made Genes Using PCR

RM Horton, Z Cai, SN Ho, LR Pease.  Biotechniques Nov 1990; 8(5):528-535.
Gene splicing by Overlap Extension or “geneSOEing” is a PCR-based recombining DNA sequences without reliance on restriction sites and of directly generated DNA fragments in vitro.  Method relies on modifying the sequences incorporated into the 5′-ends of the primers. Strands from two different fragments can hybridize together forming and overlap.

Democritixing Flow Cytometry.

Reported by M O’Neill. Geneg News Mar 15, 2013; 33(6): p12
Due to advances on many fronts
1. microfluidics
2. software
Flow cytometry is being simplified so that it can be used by a broader range of scientist and clinicians.
Eight Hox genes of D. melanogaster (fruitfly).

Eight Hox genes of D. melanogaster (fruitfly). (Photo credit: Wikipedia)

Read Full Post »

Genomics & Genetics of Cardiovascular Disease Diagnoses: A Literature Survey of AHA’s Circulation Cardiovascular Genetics, 3/2010 – 3/2013


Curators: Aviva Lev-Ari, PhD, RN and Larry H. Bernstein, MD, FCAP


348 articles that appeared in AHA’s Circulation Cardiovascular Genetics, 3/2010 – 3/2013 were classified by the curators of this article into the following TEN categories. The first 9, represent DIAGNOSES of cardiovascular diseases, the last, deals with Pharmacogenomics.

The Cardiovascular Diagnoses that were covered in the period of 3/2010 – 3/2013, include the following:

  • Preventative Cardiology
  • MicroRNA in Serum as Bimarker for Cardiovascular Pathologies: acute myocardial infarction, viral myocarditis, diastolic dysfunction, and acute heart failure
  • Genetic Determinants of Potassium Sensitivity and Hypertension
  • Heart and Aging Research in Genomic Epidemiology: 1700 MIs and 2300 coronary heart disease events among about 29 000 eligible patients
  • Genetics of CVD and Hyperlipidemia, Hyper Cholesterolemia, Metabolic Syndrome
  • Genomics and Valvular Disease
  • Pharmacogenomics

Introductions

Larry H. Bernstein, MD, FCAP


The curation of this large amount of material in 10 categories begins with a first chapter on preventative cardiology, which has had much public attention for the last decade.  Much of the concern with preventive cardiology has emphasized diet and exercise.  There is much to be said about this in articles not yet written.  However, there are several decades of research on the amino acid composition of foods, and the essential fatty acids, that indicates an essential balance between proinflammatory and antiinflammatory fatty acids in polyunsaturated fatty acids, and of the harmful effects of saturated fats.  There is also much to be said of essential amino acids, and in particular, those essential for methylation processes, and sulfur metabolism.

The next eight chapters are all concerned with genomics in cardiovascular disease.  This is in no small part a follow up on the completion of the genetic code in 2003, a seminal event.  Let us look at these in clusters.

[1]   microRNA in serum is now considered for a biomarker for cardiovascular disease.  It can be measured at very low levels, but we don’t yet know where it fits.   It might be more revealing once we understand the adaptive mechanism in development of congestive heart failure, renal hypertension, and post-genomic events.

[2]  It appears to me that potassium sensitivity and hypertension approached from the genomic side is more complicate.  Why is that?   The kidney excretes a sodium load and in metabolic acidosis, the serum potassium rises with a metabolic acidemia that can’t be compensated by the respiratory loss of CO2 through the carbonic anhydrase mechanism.

[3]  Heart and aging research is a rich area for work on the long term post-genomic changes, and it involves a large population base.

[4][5]  The genomics of cardiac dysrrhytmias and cardiomyopathies will open new doors into our understanding of the mechanisms of these diseases, and perhaps find therapeutic targets.  There has been a large volume of work on lipid synthesis, the role of the liver in generating apolipoproteins, and this has new answers on the way.  The most important feature, not readily accepted is the measurement of particles, which has now been done by a monoclonal antibody.  Metabolic syndrome brings together adipose tissue metabolism, endocrine and changes in CRP and IL-1.

[6]   Vascular pathologies and coagulation, hyperviscosity has had an enormous increase in intensity of research.  The concept of plaque rupture to account for all AMIs is being modified, and the high sensitivity cardio-specific troponins have become the most widely use test.

[7]  The genomics of valvular disease fits with the increased surgical procedures for valvular disease related to atheroschlerosis and advent of minimally invasive surgical procedures for the reapir and replacement of valves, procedure called TAVR vs. Openhealrt surgery for valve replacement.

[8]  Inherited cardiovascular disease is an older family of disorders, going back to Victor McKusik, and also the “Blue Baby” operation, both at Johns Hopkins.

[9] Pharmacogenomics is a vary active field of investigation and has uncovered inter-individual differences in handling Warfarin as a starter.


Preventative Cardiology


Methods in Genetics and Clinical Interpretation Randomized Trial of Personal Genomics for Preventive Cardiology Design and Challenges

Joshua W. Knowles, MD, PhD, Themistocles L. Assimes, MD, PhD, Michaela Kiernan, PhD, Aleksandra Pavlovic, BS, Benjamin A. Goldstein, PhD, Veronica Yank, MD, Michael V. McConnell, MD, Devin Absher, PhD, Carlos Bustamante, PhD, Euan A. Ashley, MD, DPhil and John P.A. Ioannidis, MD, DSc

Author Affiliations

From the Division of Cardiovascular Medicine (J.W.K., T.L.A., A.P., M.V.M., E.A.A.), Stanford Prevention Research Center (M.K., V.Y., J.P.A.I.), Division of General Medical Disciplines (V.Y.), Department of Genetics (C.B.), Department of Health Research and Policy (J.P.A.I.), Stanford University School of Medicine, Stanford, CA; Quantitative Sciences Unit, Stanford University School of Medicine, Palo Alto, CA (B.A.G.); HudsonAlpha Institute for Biotechnology, Huntsville, AL (D.A.); Department of Statistics, Stanford University School of Humanities and Sciences, Stanford, CA (J.P.A.I.).

Correspondence to Joshua W. Knowles, MD, PhD, Stanford University School of Medicine, Division of Cardiovascular Medicine, Falk CVRC, 300 Pasteur Dr, Stanford, CA 94305. E-mail knowlej@stanford.edu

Background

Genome-wide association studies (GWAS) have identified more than 1500 disease-associated single nucleotide polymorphisms (SNPs), including many related to atherosclerotic cardiovascular disease (CVD). Associations have been found for most traditional risk factors (TRFs), including lipids,1,2 blood pressure/hypertension,3,4 weight/body mass index,5,6 smoking behavior,7 and diabetes.8–13 GWAS have also identified susceptibility variants for coronary heart disease (CHD). The first and, so far, strongest of these signals was found in the 9p21.3 locus, where common variants in this region increase the relative risk of CVD by 15% to 30% per risk allele in most race/ethnic groups.13–20 Subsequent large-scale GWAS meta-analyses and replication studies in largely white/European populations have led to the reliable identification of an additional 26 loci conferring susceptibility to CHD,2,20–23 all with substantially lower effects sizes compared with the 9p21 locus. Many of these CVD susceptibility loci appear to be conferring risk independent of TRFs and thus cannot currently be assessed by surrogate clinical measures (Table 1). Among the 27 independent loci identified in the most recent large meta-analyses of CVD, 21 were reported not to be associated with any of the TRFs.20,21

 SOURCE

Circulation: Cardiovascular Genetics 2012; 5: 368-376

doi: 10.1161/ CIRCGENETICS.112.962746


MicroRNA in Serum as Bimarker for Cardiovascular Pathologies: acute myocardial infarction, viral myocarditis,  diastolic dysfunction, and acute heart failure

Increased MicroRNA-1 and MicroRNA-133a Levels in Serum of Patients With Cardiovascular Disease Indicate Myocardial Damage


Yasuhide Kuwabara, MD, Koh Ono, MD, PhD, Takahiro Horie, MD, PhD, Hitoo Nishi, MD, PhD, Kazuya Nagao, MD, PhD, Minako Kinoshita, MD, PhD, Shin Watanabe, MD, PhD, Osamu Baba, MD, Yoji Kojima, MD, PhD, Satoshi Shizuta, MD, Masao Imai, MD, Toshihiro Tamura, MD, Toru Kita, MD, PhD and Takeshi Kimura, MD, PhD

Author Affiliations

From the Department of Cardiovascular Medicine, Graduate School of Medicine, Kyoto University, Kyoto, Japan (Y. Kuwabara, K.O., T.H., H.N., K.N., M.K., S.W., O.B., Y. Kojima, S.S., M.I., T.T., T. Kimura); and Kobe City Medical Center General Hospital, Kobe, Japan (T. Kita).

Correspondence to Koh Ono, MD, PhD, Department of Cardiovascular Medicine, Graduate School of Medicine, Kyoto University, 54 Shogoin-kawahara-cho, Sakyo-ku, Kyoto, Japan 606-8507. E-mail kohono@kuhp.kyoto-u.ac.jp


Abstract

Background—Recently, elevation of circulating muscle-specific microRNA (miRNA) levels has been reported in patients with acute myocardial infarction. However, it is still unclear from which part of the myocardium or under what conditions miRNAs are released into circulating blood. The purpose of this study was to identify the source of elevated levels of circulating miRNAs and their function in cardiovascular diseases.

Conclusions—These results suggest that elevated levels of circulating miR-133a in patients with cardiovascular diseases originate mainly from the injured myocardium. Circulating miR-133a can be used as a marker for cardiomyocyte death, and it may have functions in cardiovascular diseases.

SOURCE:

Circulation: Cardiovascular Genetics. 2011; 4: 446-454

Published online before print June 2, 2011,

doi: 10.1161/ CIRCGENETICS.110.958975

Selective Articles citing this article

Plasma microRNAs serve as biomarkers of therapeutic efficacy and disease progression in hypertension-induced heart failure 
Eur J Heart Fail. 2013;0:hft018v1-hft018,

AbstractFull TextPDF

Intercellular Transport of MicroRNAs 
Arterioscler. Thromb. Vasc. Bio.. 2013;33:186-192,

AbstractFull TextPDF

MicroRNAs Within the Continuum of Postgenomics Biomarker Discovery 
Arterioscler. Thromb. Vasc. Bio.. 2013;33:206-214,

AbstractFull TextPDF

Reply to “Need for Rigor in Design, Reporting, and Interpretation of Transcriptomic Biomarker Studies” 
J. Clin. Microbiol.. 2012;50:4192-4193,

http://www.ncbi.nlm.nih.gov/pmc/articles/PMC3502969/

Full TextPDF

Circulating microRNAs as diagnostic biomarkers for cardiovascular diseases 
Am. J. Physiol. Heart Circ. Physiol.. 2012;303:H1085-H1095,

AbstractFull TextPDF

Sonic Hedgehog-Modified Human CD34+ Cells Preserve Cardiac Function After Acute Myocardial Infarction 
Circ. Res.. 2012;111:312-321,

AbstractFull TextPDF

Metabolomics, Proteomics, Genomics, and Transcriptomics in Circulation and the Circulation Subspecialty Journals 
Circulation. 2012;125:e507-e519,

AbstractFull TextPDF

Circulating MicroRNAs: Novel Biomarkers and Extracellular Communicators in Cardiovascular Disease? 
Circ. Res.. 2012;110:483-495,

AbstractFull TextPDF

Circulating MicroRNAs in Cardiovascular Disease 
Circulation. 2011;124:1908-1910,

Full TextPDF

Circulating MicroRNAs: Biomarkers or Mediators of Cardiovascular Diseases? 
Arterioscler. Thromb. Vasc. Bio.. 2011;31:2383-2390,

AbstractFull TextPDF


Circulating MicroRNA-208b and MicroRNA-499 Reflect Myocardial Damage in Cardiovascular Disease

Maarten F. Corsten, MD, Robert Dennert, MD, Sylvia Jochems, BSc, Tatiana Kuznetsova, MD, PhD, Yvan Devaux, PhD, Leon Hofstra, MD, PhD, Daniel R. Wagner, MD, PhD, Jan A. Staessen, MD, PhD, Stephane Heymans, MD, PhD and Blanche Schroen, PhD

Author Affiliations

From the Center for Heart Failure Research (M.F.C., R.D., S.J., S.H., B.S.), Cardiovascular Research Institute, Maastricht, The Netherlands; the Division of Hypertension and Cardiovascular Rehabilitation (T.K., J.A.S.), Department of Cardiovascular Diseases, University of Leuven, Leuven, Belgium and Department of Epidemiology, Maastricht University Medical Center, Maastricht, The Netherlands; Centre de Recherche Public–Santé, Luxembourg (Y.D., D.R.W.), Luxembourg; Maastricht University Medical Center (L.H.), Maastricht, The Netherlands; and Centre Hospitalier Luxembourg (D.R.W.), Luxembourg.

Correspondence to Blanche Schroen, PhD, Center for Heart Failure Research, Cardiovascular Research Institute Maastricht, Universiteitssingel 50, 6229 ER Maastricht, The Netherlands. E-mail b.schroen@cardio.unimaas.nl

Drs Heymans and Schroen contributed equally to this work.

Abstract

Background— Small RNA molecules, called microRNAs, freely circulate in human plasma and correlate with varying pathologies. In this study, we explored their diagnostic potential in a selection of prevalent cardiovascular disorders.

Methods and Results— MicroRNAs were isolated from plasmas from well-characterized patients with varying degrees of cardiac damage:

(1) acute myocardial infarction,

(2) viral myocarditis,

(3) diastolic dysfunction, and

(4) acute heart failure.

Plasma levels of selected microRNAs, including heart-associated (miR-1, -133a, -208b, and -499), fibrosis-associated (miR-21 and miR-29b), and leukocyte-associated (miR-146, -155, and -223) candidates, were subsequently assessed using real-time polymerase chain reaction. Strikingly, in plasma from acute myocardial infarction patients, cardiac myocyte–associated miR-208b and -499 were highly elevated, 1600-fold (P<0.005) and 100-fold (P<0.0005), respectively, as compared with control subjects. Receiver operating characteristic curve analysis revealed an area under the curve of 0.94 (P<10−10) for miR-208b and 0.92 (P<10−9) for miR-499. Both microRNAs correlated with plasma troponin T, indicating release of microRNAs from injured cardiomyocytes. In viral myocarditis, we observed a milder but significant elevation of these microRNAs, 30-fold and 6-fold, respectively. Plasma levels of leukocyte-expressed microRNAs were not significantly increased in acute myocardial infarction or viral myocarditis patients, despite elevated white blood cell counts. In patients with acute heart failure, only miR-499 was significantly elevated (2-fold), whereas no significant changes in microRNAs studied could be observed in diastolic dysfunction. Remarkably, plasma microRNA levels were not affected by a wide range of clinical confounders, including age, sex, body mass index, kidney function, systolic blood pressure, and white blood cell count.

Conclusions— Cardiac damage initiates the detectable release of cardiomyocyte-specific microRNAs-208b and -499 into the circulation.

SOURCE:

Circulation: Cardiovascular Genetics. 2010; 3: 499-506

Published online before print October 4, 2010,

doi: 10.1161/ CIRCGENETICS.110.957415


Selective Articles citing this article

Plasma microRNAs serve as biomarkers of therapeutic efficacy and disease progression in hypertension-induced heart failure 
Eur J Heart Fail. 2013;0:hft018v1-hft018,

AbstractFull TextPDF

Aspirin treatment hampers the use of plasma microRNA-126 as a biomarker for the progression of vascular disease 
Eur Heart J. 2013;0:eht007v1-eht007,

AbstractFull TextPDF

MicroRNAs in Myocardial Infarction 
Arterioscler. Thromb. Vasc. Bio.. 2013;33:201-205,

AbstractFull TextPDF

MicroRNAs Within the Continuum of Postgenomics Biomarker Discovery 
Arterioscler. Thromb. Vasc. Bio.. 2013;33:206-214,

AbstractFull TextPDF

MicroRNAs Are Involved in End-Organ Damage During Hypertension 
Hypertension. 2012;60:1088-1093,

AbstractFull TextPDF

Circulating microRNAs as diagnostic biomarkers for cardiovascular diseases 
Am. J. Physiol. Heart Circ. Physiol.. 2012;303:H1085-H1095,

AbstractFull TextPDF

Circulation Editors’ Picks: Most Read Articles in Cardiovascular Genetics 
Circulation. 2012;126:e163-e169,

AbstractFull TextPDF

MicroRNAs in Patients on Chronic Hemodialysis (MINOS Study) 
CJASN. 2012;7:619-623,

AbstractFull TextPDF

Novel techniques and targets in cardiovascular microRNA research 
Cardiovasc Res. 2012;93:545-554,

AbstractFull TextPDF

Microparticles: major transport vehicles for distinct microRNAs in circulation 
Cardiovasc Res. 2012;93:633-644,

AbstractFull TextPDF

Profiling of circulating microRNAs: from single biomarkers to re-wired networks 
Cardiovasc Res. 2012;93:555-562,

AbstractFull TextPDF

Small but smart–microRNAs in the centre of inflammatory processes during cardiovascular diseases, the metabolic syndrome, and ageing 
Cardiovasc Res. 2012;93:605-613,

AbstractFull TextPDF

Circulation: Heart Failure Editors’ Picks: Most Important Papers in Pathophysiology and Genetics 
Circ Heart Fail. 2012;5:e32-e49,

AbstractFull TextPDF

Use of Circulating MicroRNAs to Diagnose Acute Myocardial Infarction 
Clin. Chem.. 2012;58:559-567,

AbstractFull TextPDF

Circulating MicroRNAs: Novel Biomarkers and Extracellular Communicators in Cardiovascular Disease? 
Circ. Res.. 2012;110:483-495,

AbstractFull TextPDF

Serum levels of microRNAs in patients with heart failure 
Eur J Heart Fail. 2012;14:147-154,

AbstractFull TextPDF

Circulating microRNAs to identify human heart failure 
Eur J Heart Fail. 2012;14:118-119,

Full TextPDF

Next Steps in Cardiovascular Disease Genomic Research–Sequencing, Epigenetics, and Transcriptomics 
Clin. Chem.. 2012;58:113-126,

AbstractFull TextPDF

Most Read in Cardiovascular Genetics on Biomarkers, Inherited Cardiomyopathies and Arrhythmias, Metabolomics, and Genomics 
Circ Cardiovasc Genet. 2011;4:e24-e30,

AbstractFull TextPDF

MicroRNA-126 modulates endothelial SDF-1 expression and mobilization of Sca-1+/Lin- progenitor cells in ischaemia 
Cardiovasc Res. 2011;92:449-455,

AbstractFull TextPDF

Circulating MicroRNAs: Biomarkers or Mediators of Cardiovascular Diseases? 
Arterioscler. Thromb. Vasc. Bio.. 2011;31:2383-2390,

AbstractFull TextPDF

Transcoronary Concentration Gradients of Circulating MicroRNAs 
Circulation. 2011;124:1936-1944,

AbstractFull TextPDF

MicroRNAs: New Players in Cardiac Injury and Protection 
Mol. Pharmacol.. 2011;80:558-564,

AbstractFull TextPDF

Circulation Editors’ Picks: Most Read Articles in Cardiovascular Genetics, Part I 
Circulation. 2011;124:e345-e357,

AbstractFull TextPDF

MicroRNAs regulating oxidative stress and inflammation in relation to obesity and atherosclerosis 
FASEB J.. 2011;25:2515-2527,

AbstractFull TextPDF

miR-143 and miR-145: Molecular Keys to Switch the Phenotype of Vascular Smooth Muscle Cells 
Circ Cardiovasc Genet. 2011;4:197-205,

Full TextPDF

Response to Letter Regarding Article, “Circulating MicroRNA-208b and MicroRNA-499 Reflect Myocardial Damage in Cardiovascular Disease” 
Circ Cardiovasc Genet. 2011;4:e8,

Full TextPDF


Genetic Determinants of Potassium Sensitivity and Hypertension


Integrated Computational and Experimental Analysis of the Neuroendocrine Transcriptome in Genetic Hypertension Identifies Novel Control Points for the Cardiometabolic Syndrome

Ryan S. Friese, PhD, Chun Ye, PhD, Caroline M. Nievergelt, PhD, Andrew J. Schork, BS, Nitish R. Mahapatra, PhD, Fangwen Rao, MD, Philip S. Napolitan, BS, Jill Waalen, MD, MPH, Georg B. Ehret, MD, Patricia B. Munroe, PhD, Geert W. Schmid-Schönbein, PhD, Eleazar Eskin, PhD and Daniel T. O’Connor, MD

Author Affiliations

From the Departments of Bioengineering (R.S.F., G.W.S.-S.), Medicine (R.S.F., A.J.S., F.R., P.S.N., D.T.O.), Pharmacology (D.T.O.), and Psychiatry (C.M.N.), the Bioinformatics Program (C.Y.), and the Institute for Genomic Medicine (D.T.O.), University of California at San Diego; the VA San Diego Healthcare System, San Diego, CA (D.T.O.); the Departments of Computer Science & Human Genetics, University of California at Los Angeles (E.E.); the Department of Biotechnology, Indian Institute of Technology Madras, Chennai, India (N.R.M.); Clinical Pharmacology and The Genome Centre, William Harvey Research Institute, Barts and The London School of Medicine and Dentistry, Queen Mary University of London, London, United Kingdom (P.B.M.); Center for Complex Disease Genomics, McKusick-Nathans Institute of Genetic Medicine, Johns Hopkins University School of Medicine, Baltimore, MD (G.B.E.); and Scripps Research Institute, La Jolla, CA (J.W.).

Correspondence to Daniel T. O’Connor, MD, Department of Medicine, University of California at San Diego School of Medicine, VASDHS (0838), Skaggs (SSPPS) Room 4256, 9500 Gilman Drive, La Jolla, CA 92093-0838. E-mail doconnor@ucsd.edu

Abstract

Background—Essential hypertension, a common complex disease, displays substantial genetic influence. Contemporary methods to dissect the genetic basis of complex diseases such as the genomewide association study are powerful, yet a large gap exists betweens the fraction of population trait variance explained by such associations and total disease heritability.

Methods and Results—We developed a novel, integrative method (combining animal models, transcriptomics, bioinformatics, molecular biology, and trait-extreme phenotypes) to identify candidate genes for essential hypertension and the metabolic syndrome. We first undertook transcriptome profiling on adrenal glands from blood pressure extreme mouse strains: the hypertensive BPH (blood pressure high) and hypotensive BPL (blood pressure low). Microarray data clustering revealed a striking pattern of global underexpression of intermediary metabolism transcripts in BPH. The MITRA algorithm identified a conserved motif in the transcriptional regulatory regions of the underexpressed metabolic genes, and we then hypothesized that regulation through this motif contributed to the global underexpression. Luciferase reporter assays demonstrated transcriptional activity of the motif through transcription factors HOXA3, SRY, and YY1. We finally hypothesized that genetic variation at HOXA3, SRY, and YY1 might predict blood pressure and other metabolic syndrome traits in humans. Tagging variants for each locus were associated with blood pressure in a human population blood pressure extreme sample with the most extensive associations for YY1 tagging single nucleotide polymorphism rs11625658 on systolic blood pressure, diastolic blood pressure, body mass index, and fasting glucose. Meta-analysis extended the YY1 results into 2 additional large population samples with significant effects preserved on diastolic blood pressure, body mass index, and fasting glucose.

Conclusions—The results outline an innovative, systematic approach to the genetic pathogenesis of complex cardiovascular disease traits and point to transcription factor YY1 as a potential candidate gene involved in essential hypertension and the cardiometabolic syndrome.

 SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 430-440

Published online before print June 5, 2012,

doi: 10.1161/ CIRCGENETICS.111.962415

Genome-Wide Linkage and Positional Candidate Gene Study of Blood Pressure Response to Dietary Potassium Intervention

The Genetic Epidemiology Network of Salt Sensitivity Study

Tanika N. Kelly, PhD, James E. Hixson, PhD, Dabeeru C. Rao, PhD, Hao Mei, MD, PhD, Treva K. Rice, PhD, Cashell E. Jaquish, PhD, Lawrence C. Shimmin, PhD, Karen Schwander, MS, Chung-Shuian Chen, MS, Depei Liu, PhD, Jichun Chen, MD, Concetta Bormans, PhD, Pramila Shukla, MS, Naveed Farhana, MS, Colin Stuart, BS, Paul K. Whelton, MD, MSc, Jiang He, MD, PhD and Dongfeng Gu, MD, PhD

Author Affiliations

From the Department of Epidemiology (T.N.K., H.M., C.-S.C., J.H.), Tulane University School of Public Health and Tropical Medicine, and Department of Medicine (J.H.), Tulane University School of Medicine, New Orleans, La; Department of Epidemiology (J.E.H., L.C.S., C.B., P.S., N.F., C.S.), University of Texas School of Public Health, Houston, Tex; Division of Biostatistics (D.C.R., T.K.R., K.S.), Washington University School of Medicine, St Louis, Mo; Division of Prevention and Population Sciences (C.E.J.), National Heart, Lung, Blood Institute, Bethesda, Md; National Laboratory of Medical Molecular Biology (D.L.), Institute of Basic Medical Sciences, Chinese Academy of Medical Sciences and Peking Union Medical College, Beijing, China; Cardiovascular Institute and Fuwai Hospital (J.C., D.G.), Chinese Academy of Medical Sciences and Peking Union Medical College and Chinese National Center for Cardiovascular Disease Control and Research, Beijing, China; and Office of the President (P.K.W.), Loyola University Health System and Medical Center, Maywood, Ill.

Correspondence to Dongfeng Gu, MD, PhD, Division of Population Genetics and Prevention, Cardiovascular Institute and Fuwai Hospital, 167 Beilishi Rd, Beijing 100037, China. E-mail gudongfeng@vip.sina.com

Abstract

Background— Genetic determinants of blood pressure (BP) response to potassium, or potassium sensitivity, are largely unknown. We conducted a genome-wide linkage scan and positional candidate gene analysis to identify genetic determinants of potassium sensitivity.

Conclusions— Genetic regions on chromosomes 3 and 11 may harbor important susceptibility loci for potassium sensitivity. Furthermore, the AGTR1 gene was a significant predictor of BP responses to potassium intake.

SOURCE:

Circulation: Cardiovascular Genetics. 2010; 3: 539-547

Published online before print September 22, 2010,

doi: 10.1161/ CIRCGENETICS.110.940635


Genome-Wide Association Study of Cardiac Structure and Systolic Function in African Americans

The Candidate Gene Association Resource (CARe) Study

Ervin R. Fox, MD*, Solomon K. Musani, PhD*, Maja Barbalic, PhD*, Honghuang Lin, PhD, Bing Yu, MS, Kofo O. Ogunyankin, MD, Nicholas L. Smith, PhD, Abdullah Kutlar, MD, Nicole L. Glazer, MD, Wendy S. Post, MD, MS, Dina N. Paltoo, PhD, MPH, Daniel L. Dries, MD, MPH, Deborah N. Farlow, PhD, Christine W. Duarte, PhD, Sharon L. Kardia, PhD, Kristin J. Meyers, PhD, Yan V. Sun, PhD, Donna K. Arnett, PhD, Amit A. Patki, MS, Jin Sha, MS, Xiangqui Cui, PhD, Tandaw E. Samdarshi, MD, MPH, Alan D. Penman, PhD, Kirsten Bibbins-Domingo, MD, PhD, Petra Bůžková, PhD, Emelia J. Benjamin, MD, David A. Bluemke, MD, PhD, Alanna C. Morrison, PhD, Gerardo Heiss, MD, J. Jeffrey Carr, MD, MSc, Russell P. Tracy, PhD, Thomas H. Mosley, PhD, Herman A. Taylor, MD, Bruce M. Psaty, MD, PhD, Susan R. Heckbert, MD, PhD, Thomas P. Cappola, MD, ScM and Ramachandran S. Vasan, MD

Author Affiliations

Guest Editor for this article was Barry London, MD, PhD.

Correspondence to Ervin Fox, MD MPH, FAHA, FACC, Professor of Medicine, Department of Medicine, University of Mississippi Medical Center, 2500 North State St, Jackson, MS 39216. E-mail efox@medicine.umsmed.edu

↵* These authors contributed equally as joint first authors.

Abstract

Background—Using data from 4 community-based cohorts of African Americans, we tested the association between genome-wide markers (single-nucleotide polymorphisms) and cardiac phenotypes in the Candidate-gene Association Resource study.

Methods and Results—Among 6765 African Americans, we related age, sex, height, and weight-adjusted residuals for 9 cardiac phenotypes (assessed by echocardiogram or magnetic resonance imaging) to 2.5 million single-nucleotide polymorphisms genotyped using Genome-wide Affymetrix Human SNP Array 6.0 (Affy6.0) and the remainder imputed. Within the cohort, genome-wide association analysis was conducted, followed by meta-analysis across cohorts using inverse variance weights (genome-wide significance threshold=4.0 ×10−7). Supplementary pathway analysis was performed. We attempted replication in 3 smaller cohorts of African ancestry and tested lookups in 1 consortium of European ancestry (EchoGEN). Across the 9 phenotypes, variants in 4 genetic loci reached genome-wide significance: rs4552931 in UBE2V2 (P=1.43×10⁻⁷) for left ventricular mass, rs7213314 in WIPI1 (P=1.68×10⁻⁷) for left ventricular internal diastolic diameter, rs1571099 in PPAPDC1A (P=2.57×10⁻⁸) for interventricular septal wall thickness, and rs9530176 in KLF5 (P=4.02×10⁻⁷) for ejection fraction. Associated variants were enriched in 3 signaling pathways involved in cardiac remodeling. None of the 4 loci replicated in cohorts of African ancestry was confirmed in lookups in EchoGEN.

Conclusions—In the largest genome-wide association study of cardiac structure and function to date in African Americans, we identified 4 genetic loci related to left ventricular mass, interventricular septal wall thickness, left ventricular internal diastolic diameter, and ejection fraction, which reached genome-wide significance. Replication results suggest that these loci may be unique to individuals of African ancestry. Additional large-scale studies are warranted for these complex phenotypes.

SOURCE:

Circulation: Cardiovascular Genetics. 2013; 6: 37-46

Published online before print December 28, 2012,

doi: 10.1161/ CIRCGENETICS.111.962365


Heart and Aging Research in Genomic Epidemiology: 1700 MIs and 2300 coronary heart disease events among about 29 000 eligible patients


Cohorts for Heart and Aging Research in Genomic Epidemiology (CHARGE) Consortium

Design of Prospective Meta-Analyses of Genome-Wide Association Studies From 5 Cohorts

Bruce M. Psaty, MD, PhD, Christopher J. O’Donnell, MD, MPH, Vilmundur Gudnason, MD, PhD, Kathryn L. Lunetta, PhD, Aaron R. Folsom, MD, Jerome I. Rotter, MD, André G. Uitterlinden, PhD, Tamara B. Harris, MD, Jacqueline C.M. Witteman, PhD, Eric Boerwinkle, PhD and on Behalf of the CHARGE Consortium

Author Affiliations

From the Cardiovascular Health Research Unit, Departments of Medicine, Epidemiology, and Health Services (B.M.P.), University of Wash; Center for Health Studies, Group Health (B.M.P.), Seattle, Wash; the National Heart, Lung and Blood Institute and the Framingham Heart Study (C.J.O.D.), Framingham, Mass; Icelandic Heart Association and the Department of Cardiovascular Genetics (Y.G.), University of Iceland, Reykjavik, Iceland; Department of Biostatistics (K.L.), Boston University School of Public Health, Mass; Division of Epidemiology and Community Health (A.R.F.), University of Minnesota, Minneapolis; Medical Genetics Institute (J.I.R.), Cedars-Sinai Medical Center, Los Angeles, Calif; Departments of Internal Medicine (A.G.U.) and Epidemiology (A.G.U., J.C.M.W.), Erasmus Medical Center, Rotterdam, The Netherlands; Laboratory of Epidemiology, Demography, and Biometry (T.B.H.), Intramural Research Program, National Institute on Aging, Bethesda, Md; and Human Genetics Center and Division of Epidemiology (E.B.), University of Texas, Houston.

Guest editor for this article was Elizabeth R. Hauser, PhD.

Abstract

Background— The primary aim of genome-wide association studies is to identify novel genetic loci associated with interindividual variation in the levels of risk factors, the degree of subclinical disease, or the risk of clinical disease. The requirement for large sample sizes and the importance of replication have served as powerful incentives for scientific collaboration.

Methods— The Cohorts for Heart and Aging Research in Genomic Epidemiology Consortium was formed to facilitate genome-wide association studies meta-analyses and replication opportunities among multiple large population-based cohort studies, which collect data in a standardized fashion and represent the preferred method for estimating disease incidence. The design of the Cohorts for Heart and Aging Research in Genomic Epidemiology Consortium includes 5 prospective cohort studies from the United States and Europe: the Age, Gene/Environment Susceptibility—Reykjavik Study, the Atherosclerosis Risk in Communities Study, the Cardiovascular Health Study, the Framingham Heart Study, and the Rotterdam Study. With genome-wide data on a total of about 38 000 individuals, these cohort studies have a large number of health-related phenotypes measured in similar ways. For each harmonized trait, within-cohort genome-wide association study analyses are combined by meta-analysis. A prospective meta-analysis of data from all 5 cohorts, with a properly selected level of genome-wide statistical significance, is a powerful approach to finding genuine phenotypic associations with novel genetic loci.

Conclusions— The Cohorts for Heart and Aging Research in Genomic Epidemiology Consortium and collaborating non-member studies or consortia provide an excellent framework for the identification of the genetic determinants of risk factors, subclinical-disease measures, and clinical events.

Example of Coronary Heart Disease

The cohort-study methods papers provide detail about many of the phenotypes listed in Table 2. For coronary heart disease, investigators knowledgeable about the phenotype in each study decided to focus on fatal and nonfatal myocardial infarction (MI) as the primary outcome because the MI criteria differed in only trivial ways among the studies. There were some minor differences in the definition of the composite outcome of MI, fatal coronary heart disease, and sudden death, which became the secondary outcome. Only subjects at risk for an incident event were included in the analysis. MI survivors whose DNA was drawn after the event were not eligible. The primary analysis was restricted to Europeans or European Americans. Patients entered the analysis at the time of the DNA blood draw, and were followed until an event, death, loss to follow up, or the last visit. The main recommendations of the Analysis Committee were adopted, and a threshold of 5×10⁻⁸ was selected for genome-wide statistical significance. Analyses in progress include about 1700 MIs and 2300 coronary heart disease events among about 29 000 eligible patients. Each cohort conducted its own analysis, and results were uploaded to a secure share site for the fixed-effects meta-analysis. Even with this number of events (Supplemental Figure 2), power is good for only for relatively high minor allele frequencies (>0.25) and large relative risks (>1.3).

The authors had full access to and take full responsibility for the integrity of the data. All authors have read and agree to the manuscript as written.

Discussion

In thousands of published papers, the 5 CHARGE cohort studies and many of the collaborating studies have already characterized the risk factors for and the incidence and prognosis of a variety of aging-related and cardiovascular conditions. The analysis of the incident MI, for instance, is free from the survival bias typically associated with cross-sectional or case-control studies. The methodologic advantages of the prospective population-based cohort design, the similarity of phenotypes across 5 studies, the availability of genome-wide genotyping data in each cohort, and the need for large sample sizes to provide reliable estimates of genotype-phenotype associations have served as the primary incentives for the formation of the CHARGE consortium, which includes GWAS data on about 38 000 individuals. The consortium effort relies on collaborative methods that are similar to those used by the individual contributing cohorts.

Phenotype experts who know the studies and the data well are responsible for phenotype-standardization across cohorts. The coordinated prospectively planned meta-analyses of CHARGE provide results that are virtually identical to a cohort-adjusted pooled analysis of individual level data. This approach–the within-study analysis followed by a between-study meta-analysis–avoids the human subjects issues associated with individual-level data sharing.

Editors, reviewers, and readers expect replication as the standard in science.6 The finding of a genetic association in one population with evidence for replication in multiple independent populations provides moderate assurance against false-positive reports and helps to establish the validity of the original finding. In a single experiment, the discovery-replication structure is traditionally embodied in a 2-stage design. The CHARGE consortium includes up to 5 independent replicate samples as well as additional collaborating studies for some phenotype working groups, so that it would have been possible to set up analysis plans within CHARGE to mimic the traditional 2-stage design for replication. For instance, the 2 largest cohorts could have served as the discovery set and the others as the replication set. However, attaining the extremely small probability values expected in GWAS requires large sample sizes. For any phenotype, a prospective meta-analysis of all participating cohorts, with a properly selected level of genome-wide statistical significance to minimize the chance of false-positives, is the most powerful approach to finding new genuine associations for genetic loci.25 When findings narrowly miss the prespecified significance threshold, genotyping individuals in other independent populations provides additional evidence about the association. For findings that substantially exceed pre-established significance thresholds, the results of a CHARGE meta-analysis effectively provide evidence of a multistudy replication.

The effort to assemble and manage the CHARGE consortium has provided some interesting and unanticipated challenges. Participating cohorts often had relationships with outside study groups that predated the formation of CHARGE. Timelines for genotyping and imputation have shifted. Purchases of new computer systems for the volume of work were sometimes necessary. Each cohort came to the consortium with their own traditions for methods of analysis, organization, and authorship policies that, while appropriate for their own work, were not always optimal for collaboration with multiple external groups. Within each cohort, the investigators had often formed working groups that divided up the large number of available phenotypes in ways that made sense locally but did not necessarily match the configuration that had been adopted by other cohorts. The Research Steering Committee has attempted to create a set of CHARGE working groups that accommodate the needs and the conventions of the various cohorts. Transparency, disclosure, and professional collaborative behavior by all participating investigators have been essential to the process.

Resource limitations are another challenge. Grant applications that funded the original single-study genome-wide genotyping effort typically imagined a much simpler design. The CHS whole-genome study had as its primary aim, for instance, the analysis of data on 3 endpoints, coronary disease, stroke and heart failure. With a score of active phenotype working groups, the CHARGE collaboration broadened the scope of the short-term work well beyond initial expectations for all the participating cohorts.

One of the premier challenges has been communications among scores of investigators at a dozen sites. CHS and ARIC are themselves multi-site studies. To be successful, the CHARGE collaboration has required effective communications: (1) within each cohort; (2) between cohorts; (3) within the CHARGE working groups; and (4) among the major CHARGE committees. In addition to the traditional methods of conference calls and email, the CHARGE “wiki,” set up by Dr J. Bis (Seattle, Wash), has provided a crucial and highly functional user-driven website for calendars, minutes, guidelines, working group analysis plans, manuscript proposals, and other documents. In the end, there is no substitute for face-to-face meetings, especially at the beginning of the collaboration, and this complex meta-organization has benefited from several CHARGE-wide meetings.

The major emerging opportunity is the collaboration with other studies and consortia. Many working groups have already incorporated nonmember studies into their efforts. Several working groups have coordinated submissions of initial manuscripts with the parallel submission of manuscripts from other studies or consortia. Several working groups have embarked on plans for joint meta-analyses between CHARGE and other consortia. CHARGE has tried to acknowledge and reward the efforts of champions, who assume leadership responsibility for moving these large complex projects forward and who are often hard-working young investigators, the key to the future success of population science.

The CHARGE Consortium represents an innovative model of collaborative research conducted by research teams that know well the strengths, the limitations, and the data from 5 prospective population-based cohort studies. By leveraging the dense genotyping, deep phenotyping and the diverse expertise, prospective meta-analyses are underway to identify and replicate the major common genetic determinants of risk factors, measures of subclinical disease, and clinical events for cardiovascular disease and aging.

SOURCE:

Circulation: Cardiovascular Genetics.2009; 2: 73-80

doi: 10.1161/ CIRCGENETICS.108.829747


Genomics of Ventricular arrhythmias, A-Fib, Right Ventricular Dysplasia, Cardiomyopathy


Comprehensive Desmosome Mutation Analysis in North Americans With Arrhythmogenic Right Ventricular Dysplasia/Cardiomyopathy

A. Dénise den Haan, MD, Boon Yew Tan, MBChB, Michelle N. Zikusoka, MD, Laura Ibañez Lladó, MS, Rahul Jain, MD, Amy Daly, MS, Crystal Tichnell, MGC, Cynthia James, PhD, Nuria Amat-Alarcon, MS, Theodore Abraham, MD, Stuart D. Russell, MD, David A. Bluemke, MD, PhD, Hugh Calkins, MD, Darshan Dalal, MD, PhD and Daniel P. Judge, MD

Author Affiliations

From the Department of Medicine/Cardiology (A.D.d.H., B.Y.T., M.N.Z., L.I.L., R.J., A.D., C.T., C.J., N.A.-A., T.A., S.D.R., H.C., D.D., D.P.J.), Johns Hopkins University School of Medicine, Baltimore, Md; Department of Cardiology, Division of Heart and Lungs (A.D.d.H.), University Medical Center Utrecht, Utrecht, The Netherlands; and National Institutes of Health, Radiology and Imaging Sciences (D.A.B.), Bethesda, Md.

Correspondence to Daniel P. Judge, MD, Johns Hopkins University, Division of Cardiology, Ross 1049; 720 Rutland Avenue, Baltimore, MD 21205. E-mail djudge@jhmi.edu

Abstract

Background— Arrhythmogenic right ventricular dysplasia/cardiomyopathy (ARVD/C) is an inherited disorder typically caused by mutations in components of the cardiac desmosome. The prevalence and significance of desmosome mutations among patients with ARVD/C in North America have not been described previously. We report comprehensive desmosome genetic analysis for 100 North Americans with clinically confirmed or suspected ARVD/C.

Methods and Results— In 82 individuals with ARVD/C and 18 people with suspected ARVD/C, DNA sequence analysis was performed on PKP2, DSG2, DSP, DSC2, and JUP. In those with ARVD/C, 52% harbored a desmosome mutation. A majority of these mutations occurred in PKP2. Notably, 3 of the individuals studied have a mutation in more than 1 gene. Patients with a desmosome mutation were more likely to have experienced ventricular tachycardia (73% versus 44%), and they presented at a younger age (33 versus 41 years) compared with those without a desmosome mutation. Men with ARVD/C were more likely than women to carry a desmosome mutation (63% versus 38%). A mutation was identified in 5 of 18 patients (28%) with suspected ARVD. In this smaller subgroup, there were no significant phenotypic differences identified between individuals with a desmosome mutation compared with those without a mutation.

Conclusions— Our study shows that in 52% of North Americans with ARVD/C a mutation in one of the cardiac desmosome genes can be identified. Compared with those without a desmosome gene mutation, individuals with a desmosome gene mutation had earlier-onset ARVD/C and were more likely to have ventricular tachycardia.

SOURCE:

Circulation: Cardiovascular Genetics.2009; 2: 428-435

Published online before print June 3, 2009,

doi: 10.1161/ CIRCGENETICS.109.858217


Selective Articles citing this article

Genetics of arrhythmogenic right ventricular cardiomyopathy 
J. Med. Genet.. 2013;0:jmedgenet-2013-101523v1-jmedgenet-2013-101523,

AbstractFull Text

Genetic complexity in hypertrophic cardiomyopathy revealed by high-throughput sequencing 
J. Med. Genet.. 2013;0:jmedgenet-2012-101270v1-jmedgenet-2012-101270, 
AbstractFull Text

An Update on Channelopathies: From Mechanisms to Management 
Circulation. 2013;127:126-140,

Full TextPDF

Arrhythmogenic Right Ventricular Cardiomyopathy 
Circ Arrhythm Electrophysiol. 2012;5:1233-1246,

Full TextPDF

Ventricular arrhythmias associated with long-term endurance sports: what is the evidence? 
Br. J. Sports. Med.. 2012;46:i44-i50,

AbstractFull TextPDF

Phospholamban R14del mutation in patients diagnosed with dilated cardiomyopathy or arrhythmogenic right ventricular cardiomyopathy: evidence supporting the concept of arrhythmogenic cardiomyopathy 
Eur J Heart Fail. 2012;14:1199-1207,

AbstractFull TextPDF

Assessing the Significance of Pathogenic Mutations and Autopsy Findings in the Light of 2010 Arrhythmogenic Right Ventricular Cardiomyopathy Diagnostic Criteria: A Clinical Challenge 
Circ Cardiovasc Genet. 2012;5:384-386,

Full TextPDF

Loss of Cadherin-Binding Proteins {beta}-Catenin and Plakoglobin in the Heart Leads to Gap Junction Remodeling and Arrhythmogenesis 
Mol. Cell. Biol.. 2012;32:1056-1067, 
AbstractFull TextPDF

Loss of {alpha}T-catenin alters the hybrid adhering junctions in the heart and leads to dilated cardiomyopathy and ventricular arrhythmia following acute ischemia 
J. Cell Sci.. 2012;125:1058-1067,

AbstractFull TextPDF

General and Disease-Specific Psychosocial Adjustment in Patients With Arrhythmogenic Right Ventricular Dysplasia/Cardiomyopathy With Implantable Cardioverter Defibrillators: A Large Cohort Study 
Circ Cardiovasc Genet. 2012;5:18-24,

AbstractFull TextPDF

Restrictive loss of plakoglobin in cardiomyocytes leads to arrhythmogenic cardiomyopathy 
Hum Mol Genet. 2011;20:4582-4596,

AbstractFull TextPDF

Circulation Editors’ Picks: Most Read Articles in Cardiovascular Genetics, Part I 
Circulation. 2011;124:e345-e357,

AbstractFull TextPDF

Genetic Variation in Titin in Arrhythmogenic Right Ventricular Cardiomyopathy-Overlap Syndromes 
Circulation. 2011;124:876-885,

AbstractFull TextPDF

Circulation: Cardiovascular Genetics Editors’ Picks: A Selection of the Most Important Articles Published 
Circulation. 2011;124:e179-e187,

AbstractFull TextPDF

Sudden Cardiac Arrest Without Overt Heart Disease 
Circulation. 2011;123:2994-3008,

Full TextPDF

Familial Evaluation in Arrhythmogenic Right Ventricular Cardiomyopathy: Impact of Genetics and Revised Task Force Criteria 
Circulation. 2011;123:2701-2709,

AbstractFull TextPDF

Arrhythmogenic Right Ventricular Dysplasia/Cardiomyopathy: Pathogenic Desmosome Mutations in Index-Patients Predict Outcome of Family Screening: Dutch Arrhythmogenic Right Ventricular Dysplasia/Cardiomyopathy Genotype-Phenotype Follow-Up Study 
Circulation. 2011;123:2690-2700,

AbstractFull TextPDF

Arrhythmogenic Right Ventricular Dysplasia/Cardiomyopathy: A Family Affair 
Circulation. 2011;123:2661-2663,

Full TextPDF

Lack of plakoglobin leads to lethal congenital epidermolysis bullosa: a novel clinico-genetic entity 
Hum Mol Genet. 2011;20:1811-1819,

AbstractFull TextPDF

Mechanistic insights into arrhythmogenic right ventricular cardiomyopathy caused by desmocollin-2 mutations 
Cardiovasc Res. 2011;90:77-87,

AbstractFull TextPDF

Cardiac Tissue-Restricted Deletion of Plakoglobin Results in Progressive Cardiomyopathy and Activation of {beta}-Catenin Signaling 
Mol. Cell. Biol.. 2011;31:1134-1144,

AbstractFull TextPDF

Psychological Issues in Genetic Testing for Inherited Cardiovascular Diseases 
Circ Cardiovasc Genet. 2011;4:81-90,

Full TextPDF

De novo desmin-mutation N116S is associated with arrhythmogenic right ventricular cardiomyopathy 
Hum Mol Genet. 2010;19:4595-4607,

AbstractFull TextPDF

Wide spectrum of desmosomal mutations in Danish patients with arrhythmogenic right ventricular cardiomyopathy 
J. Med. Genet.. 2010;47:736-744,

AbstractFull TextPDF

Dilated Cardiomyopathy With Conduction Disease and Arrhythmia 
Circulation. 2010;122:527-534,

Full TextPDF

Lower than expected desmosomal gene mutation prevalence in endurance athletes with complex ventricular arrhythmias of right ventricular origin 
Heart. 2010;96:1268-1274, AbstractFull TextPDF

Desmosomal gene analysis in arrhythmogenic right ventricular dysplasia/cardiomyopathy: spectrum of mutations and clinical impact in practice 
Europace. 2010;12:861-868,

 AbstractFull TextPDF


Large-Scale Candidate Gene Analysis in Whites and African Americans Identifies IL6R Polymorphism in Relation to Atrial Fibrillation

The National Heart, Lung, and Blood Institute’s Candidate Gene Association Resource (CARe) Project

Renate B. Schnabel, MD, MSc*, Kathleen F. Kerr, PhD*, Steven A. Lubitz, MD*, Ermeg L. Alkylbekova, MD*, Gregory M. Marcus, MD, MAS, Moritz F. Sinner, MD, Jared W. Magnani, MD, Philip A. Wolf, MD, Rajat Deo, MD, Donald M. Lloyd-Jones, MD, ScM, Kathryn L. Lunetta, PhD, Reena Mehra, MD, MS, Daniel Levy, MD, Ervin R. Fox, MD, MPH, Dan E. Arking, PhD, Thomas H. Mosley, PhD, Martina Müller-Nurasyid, MSc, PhD, Taylor R. Young, MA, H.-Erich Wichmann, MD, PhD, Sudha Seshadri, MD, Deborah N. Farlow, PhD, Jerome I. Rotter, MD, Elsayed Z. Soliman, MD, MSc, MS, Nicole L. Glazer, PhD, James G. Wilson, MD, Monique M.B. Breteler, MD, Nona Sotoodehnia, MD, MPH, Christopher Newton-Cheh, MD, MPH, Stefan Kääb, MD, PhD, Patrick T. Ellinor, MD, PhD*, Alvaro Alonso, MD*, Emelia J. Benjamin, MD, ScM*, Susan R. Heckbert, MD, PhD* and for the Candidate Gene Association Resource (CARe) Atrial Fibrillation/Electrocardiography Working Group

Correspondence to Susan R. Heckbert, MD, PhD, Cardiovascular Health Research Unit, University of Washington, 1730 Minor Ave, Suite 1360, Seattle, WA 98101. E-mail heckbert@u.washington.edu; Emelia J. Benjamin, MD, ScM, Medicine and Epidemiology, Boston University Schools of Medicine and Public Health, The Framingham Heart Study, 73 Mount Wayte Ave, Framingham, MA 01702–5827. E-mail emelia@bu.edu; Renate B. Schnabel, MD, MSc, Department of Medicine 2, Cardiology, Johannes Gutenberg University, Langenbeckstr 1, 55131 Mainz, Germany. E-mail schnabelr@gmx.de

↵* These authors contributed equally to the manuscript.

Abstract

Background—The genetic background of atrial fibrillation (AF) in whites and African Americans is largely unknown. Genes in cardiovascular pathways have not been systematically investigated.

Methods and Results—We examined a panel of approximately 50 000 common single-nucleotide polymorphisms (SNPs) in 2095 cardiovascular candidate genes and AF in 3 cohorts with participants of European (n=18 524; 2260 cases) or African American descent (n=3662; 263 cases) in the National Heart, Lung, and Blood Institute’s Candidate Gene Association Resource. Results in whites were followed up in the German Competence Network for AF (n=906, 468 cases). The top result was assessed in relation to incident ischemic stroke in the Cohorts for Heart and Aging Research in Genomic Epidemiology Stroke Consortium (n=19 602 whites, 1544 incident strokes). SNP rs4845625 in the IL6R gene was associated with AF (relative risk [RR] C allele, 0.90; 95% confidence interval [CI], 0.85–0.95; P=0.0005) in whites but did not reach statistical significance in African Americans (RR, 0.86; 95% CI, 0.72–1.03; P=0.09). The results were comparable in the German AF Network replication, (RR, 0.71; 95% CI, 0.57–0.89; P=0.003). No association between rs4845625 and stroke was observed in whites. The known chromosome 4 locus near PITX2 in whites also was associated with AF in African Americans (rs4611994; hazard ratio, 1.40; 95% CI, 1.16–1.69; P=0.0005).

Conclusions—In a community-based cohort meta-analysis, we identified genetic association in IL6R with AF in whites. Additionally, we demonstrated that the chromosome 4 locus known from recent genome-wide association studies in whites is associated with AF in African Americans.

 SOURCE:

Circulation: Cardiovascular Genetics.2011; 4: 557-564

Published online before print August 16, 2011,

doi: 10.1161/ CIRCGENETICS.110.959197

PITX2c Is Expressed in the Adult Left Atrium, and Reducing Pitx2c Expression Promotes Atrial Fibrillation Inducibility and Complex Changes in Gene Expression

Paulus Kirchhof, MD*, Peter C. Kahr*, Sven Kaese, Ilaria Piccini, PhD, Ismail Vokshi, BSc, Hans-Heinrich Scheld, MD, Heinrich Rotering, MD, Lisa Fortmueller, MD (vet), Sandra Laakmann, MD (vet), Sander Verheule, PhD, Ulrich Schotten, MD, PhD, Larissa Fabritz, MD and Nigel A. Brown, PhD

Author Affiliations

From the Department of Cardiology and Angiology (P.K., P.C.K., S.K., I.P., L.F., S.L., L.F.) and the Department of Thoracic and Cardiovascular Surgery (H.-H.S., H.R.), University Hospital Muenster, Germany; Division of Biomedical Sciences (P.C.K., I.V., N.A.B.), St. George’s, University of London, United Kingdom; and the Department of Physiology (S.V., U.S.), Maastricht University, The Netherlands.

Correspondence to Nigel A. Brown, PhD, Division of Biomedical Sciences, St George’s, University of London, Cranmer Terrace, London, SW17 0RE, UK. E-mail nbrown@sgul.ac.uk

↵* Drs Kirchhof and Kahr contributed equally to this work.

Abstract

Background— Intergenic variations on chromosome 4q25, close to the PITX2 transcription factor gene, are associated with atrial fibrillation (AF). We therefore tested whether adult hearts express PITX2 and whether variation in expression affects cardiac function.

Methods and Results— mRNA for PITX2 isoform c was expressed in left atria of human and mouse, with levels in right atrium and left and right ventricles being 100-fold lower. In mice heterozygous for Pitx2c (Pitx2c+/−), left atrial Pitx2c expression was 60% of wild-type and cardiac morphology and function were not altered, except for slightly elevated pulmonary flow velocity. Isolated Pitx2c+/− hearts were susceptible to AF during programmed stimulation. At short paced cycle lengths, atrial action potential durations were shorter in Pitx2c+/− than in wild-type. Perfusion with the β-receptor agonist orciprenaline abolished inducibility of AF and reduced the effect on action potential duration. Spontaneous heart rates, atrial conduction velocities, and activation patterns were not affected in Pitx2c+/− hearts, suggesting that action potential duration shortening caused wave length reduction and inducibility of AF. Expression array analyses comparing Pitx2c+/− with wild-type, for left atrial and right atrial tissue separately, identified genes related to calcium ion binding, gap and tight junctions, ion channels, and melanogenesis as being affected by the reduced expression of Pitx2c.

Conclusions— These findings demonstrate a physiological role for PITX2 in the adult heart and support the hypothesis that dysregulation of PITX2 expression can be responsible for susceptibility to AF.

 SOURCE:

Circulation: Cardiovascular Genetics.2011; 4: 123-133

Published online before print January 31, 2011,

doi: 10.1161/ CIRCGENETICS.110.958058


Genetics of CVD and Hyperlipidemia, Hyper Cholesterolemia, Metabolic Syndrome


Genetic Loci Associated With Plasma Concentration of Low-Density Lipoprotein Cholesterol, High-Density Lipoprotein Cholesterol, Triglycerides, Apolipoprotein A1, and Apolipoprotein B Among 6382 White Women in Genome-Wide Analysis With Replication

Daniel I. Chasman, PhD*, Guillaume Paré, MD, MS*, Robert Y.L. Zee, PhD, MPH, Alex N. Parker, PhD, Nancy R. Cook, ScD, Julie E. Buring, ScD, David J. Kwiatkowski, MD, PhD, Lynda M. Rose, MS, Joshua D. Smith, BS, Paul T. Williams, PhD, Mark J. Rieder, PhD, Jerome I. Rotter, MD, Deborah A. Nickerson, PhD, Ronald M. Krauss, MD, Joseph P. Miletich, MD and Paul M Ridker, MD, MPH

Author Affiliations

From the Center for Cardiovascular Disease Prevention (D.I.C., G.P., R.Y.L.Z., N.R.C., J.E.B., L.M.R., P.M.R.) and Donald W. Reynolds Center for Cardiovascular Research (D.I.C., G.P., R.Y.L.Z., N.R.C., D.J.K., P.M.R.), Brigham and Women’s Hospital, Harvard Medical School, Boston, Mass; Amgen, Inc, Cambridge, Mass (A.N.P., J.M.P.); Department of Genome Sciences, University of Washington, Seattle, Wash (J.D.S., M.J.R., D.A.N.); Life Science Division, Lawrence Berkeley National Laboratory, Berkeley, Calif (P.T.W., R.M.K.); Medical Genetics Institute, Cedars-Sinai Medical Center, Los Angeles, Calif (J.I.R.); and Children’s Hospital Oakland Research Institute, Oakland, Calif (R.M.K.).

Correspondence to Daniel I. Chasman, Center for Cardiovascular Disease Prevention, Brigham and Women’s Hospital, 900 Commonwealth Ave E, Boston, MA 02215. E-mail dchasman@rics.bwh.harvard.edu

Abstract

Background— Genome-wide genetic association analysis represents an opportunity for a comprehensive survey of the genes governing lipid metabolism, potentially revealing new insights or even therapeutic strategies for cardiovascular disease and related metabolic disorders.

Methods and Results— We have performed large-scale, genome-wide genetic analysis among 6382 white women with replication in 2 cohorts of 970 additional white men and women for associations between common single-nucleotide polymorphisms and low-density lipoprotein cholesterol, high-density lipoprotein cholesterol, triglycerides, apolipoprotein (Apo) A1, and ApoB. Genome-wide associations (P<5×10⁻⁸) were found at the PCSK9 gene, the APOB gene, the LPL gene, the APOA1-APOA5 locus, the LIPC gene, the CETP gene, the LDLR gene, and the APOE locus. In addition, genome-wide associations with triglycerides at the GCKR gene confirm and extend emerging links between glucose and lipid metabolism. Still other genome-wide associations at the 1p13.3 locus are consistent with emerging biological properties for a region of the genome, possibly related to the SORT1 gene. Below genome-wide significance, our study provides confirmatory evidence for associations at 5 novel loci with low-density lipoprotein cholesterol, high-density lipoprotein cholesterol, or triglycerides reported recently in separate genome-wide association studies. The total proportion of variance explained by common variation at the genome-wide candidate loci ranges from 4.3% for triglycerides to 12.6% for ApoB.

Conclusion— Genome-wide associations at the GCKR gene and near the SORT1 gene, as well as confirmatory associations at 5 additional novel loci, suggest emerging biological pathways for lipid metabolism among white women.

 SOURCE:

Circulation: Cardiovascular Genetics.2008; 1: 21-30

doi: 10.1161/ CIRCGENETICS.108.773168


Integrated Computational and Experimental Analysis of the Neuroendocrine Transcriptome in Genetic Hypertension Identifies Novel Control Points for the Cardiometabolic Syndrome

Ryan S. Friese, PhD, Chun Ye, PhD, Caroline M. Nievergelt, PhD, Andrew J. Schork, BS, Nitish R. Mahapatra, PhD, Fangwen Rao, MD, Philip S. Napolitan, BS, Jill Waalen, MD, MPH, Georg B. Ehret, MD, Patricia B. Munroe, PhD, Geert W. Schmid-Schönbein, PhD, Eleazar Eskin, PhD and Daniel T. O’Connor, MD

Author Affiliations

From the Departments of Bioengineering (R.S.F., G.W.S.-S.), Medicine (R.S.F., A.J.S., F.R., P.S.N., D.T.O.), Pharmacology (D.T.O.), and Psychiatry (C.M.N.), the Bioinformatics Program (C.Y.), and the Institute for Genomic Medicine (D.T.O.), University of California at San Diego; the VA San Diego Healthcare System, San Diego, CA (D.T.O.); the Departments of Computer Science & Human Genetics, University of California at Los Angeles (E.E.); the Department of Biotechnology, Indian Institute of Technology Madras, Chennai, India (N.R.M.); Clinical Pharmacology and The Genome Centre, William Harvey Research Institute, Barts and The London School of Medicine and Dentistry, Queen Mary University of London, London, United Kingdom (P.B.M.); Center for Complex Disease Genomics, McKusick-Nathans Institute of Genetic Medicine, Johns Hopkins University School of Medicine, Baltimore, MD (G.B.E.); and Scripps Research Institute, La Jolla, CA (J.W.).

Correspondence to Daniel T. O’Connor, MD, Department of Medicine, University of California at San Diego School of Medicine, VASDHS (0838), Skaggs (SSPPS) Room 4256, 9500 Gilman Drive, La Jolla, CA 92093-0838. E-mail doconnor@ucsd.edu

Abstract

Background—Essential hypertension, a common complex disease, displays substantial genetic influence. Contemporary methods to dissect the genetic basis of complex diseases such as the genomewide association study are powerful, yet a large gap exists betweens the fraction of population trait variance explained by such associations and total disease heritability.

Methods and Results—We developed a novel, integrative method (combining animal models, transcriptomics, bioinformatics, molecular biology, and trait-extreme phenotypes) to identify candidate genes for essential hypertension and the metabolic syndrome. We first undertook transcriptome profiling on adrenal glands from blood pressure extreme mouse strains: the hypertensive BPH (blood pressure high) and hypotensive BPL (blood pressure low). Microarray data clustering revealed a striking pattern of global underexpression of intermediary metabolism transcripts in BPH. The MITRA algorithm identified a conserved motif in the transcriptional regulatory regions of the underexpressed metabolic genes, and we then hypothesized that regulation through this motif contributed to the global underexpression. Luciferase reporter assays demonstrated transcriptional activity of the motif through transcription factors HOXA3, SRY, and YY1. We finally hypothesized that genetic variation at HOXA3, SRY, and YY1 might predict blood pressure and other metabolic syndrome traits in humans. Tagging variants for each locus were associated with blood pressure in a human population blood pressure extreme sample with the most extensive associations for YY1 tagging single nucleotide polymorphism rs11625658 on systolic blood pressure, diastolic blood pressure, body mass index, and fasting glucose. Meta-analysis extended the YY1 results into 2 additional large population samples with significant effects preserved on diastolic blood pressure, body mass index, and fasting glucose.

Conclusions—The results outline an innovative, systematic approach to the genetic pathogenesis of complex cardiovascular disease traits and point to transcription factor YY1 as a potential candidate gene involved in essential hypertension and the cardiometabolic syndrome.

 SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 430-440

Published online before print June 5, 2012,

doi: 10.1161/ CIRCGENETICS.111.962415


Associations Between Incident Ischemic Stroke Events and Stroke and Cardiovascular Disease-Related Genome-Wide Association Studies Single Nucleotide Polymorphisms in the Population Architecture Using Genomics and Epidemiology Study

Cara L. Carty, PhD, Petra Bůžková, PhD, Myriam Fornage, PhD, Nora Franceschini, MD, Shelley Cole, PhD, Gerardo Heiss, MD, PhD, Lucia A. Hindorff, PhD, MPH, Barbara V. Howard, PhD, Sue Mann, MPH, Lisa W. Martin, MD, Ying Zhang, PhD, Tara C. Matise, PhD, Ross Prentice, PhD, Alexander P. Reiner, MD, MS and Charles Kooperberg, PhD

Author Affiliations

From the Public Health Sciences, Fred Hutchinson Cancer Research Center (C.L.C., S.M., R.P., C.K.); Department of Biostatistics, University of Washington, Seattle, WA (P.B.); Institute of Molecular Medicine, University of Texas Health Sciences Center at Houston, Houston, TX (M.F.); Division of Epidemiology, School of Public Health, University of Texas Health Sciences Center, Houston, TX (M.F.); Department of Epidemiology, University of North Carolina, Chapel Hill, NC (N.F., G.H.); Department of Genetics, Texas Biomedical Research Institute, San Antonio, TX (S.C.); Office of Population Genomics, National Human Genome Research Institute, Bethesda, MD (L.A.H.); Medstar Health Research Institute, Washington, DC (B.V.H.); George Washington University School of Medicine, Washington, DC (B.V.H., L.W.M.); University of Oklahoma Health Sciences Center, Oklahoma City, OK (Y.Z.); Department of Genetics, Rutgers University, Piscataway, NJ (T.C.M.); Department of Epidemiology, University of Washington, Seattle, WA (A.P.R.).

Correspondence to Dr Cara L. Carty, Fred Hutchinson Cancer Research Center, 1100 Fairview Ave N./M3-A410, Seattle, WA 98109. E-mail ccarty@fhcrc.org

Abstract

Background—Genome-wide association studies (GWAS) have identified loci associated with ischemic stroke (IS) and cardiovascular disease (CVD) in European-descent individuals, but their replication in different populations has been largely unexplored.

Methods and Results—Nine single nucleotide polymorphisms (SNPs) selected from GWAS and meta-analyses of stroke, and 86 SNPs previously associated with myocardial infarction and CVD risk factors, including blood lipids (high density lipoprotein [HDL], low density lipoprotein [LDL], and triglycerides), type 2 diabetes, and body mass index (BMI), were investigated for associations with incident IS in European Americans (EA) N=26 276, African-Americans (AA) N=8970, and American Indians (AI) N=3570 from the Population Architecture using Genomics and Epidemiology Study. Ancestry-specific fixed effects meta-analysis with inverse variance weighting was used to combine study-specific log hazard ratios from Cox proportional hazards models. Two of 9 stroke SNPs (rs783396 and rs1804689) were associated with increased IS hazard in AA; none were significant in this large EA cohort. Of 73 CVD risk factor SNPs tested in EA, 2 (HDL and triglycerides SNPs) were associated with IS. In AA, SNPs associated with LDL, HDL, and BMI were significantly associated with IS (3 of 86 SNPs tested). Out of 58 SNPs tested in AI, 1 LDL SNP was significantly associated with IS.

Conclusions—Our analyses showing lack of replication in spite of reasonable power for many stroke SNPs and differing results by ancestry highlight the need to follow up on GWAS findings and conduct genetic association studies in diverse populations. We found modest IS associations with BMI and lipids SNPs, though these findings require confirmation.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 210-216

Published online before print March 8, 2012,

doi: 10.1161/ CIRCGENETICS.111.962191


Common Variation in Fatty Acid Genes and Resuscitation From Sudden Cardiac Arrest

Catherine O. Johnson, PhD, MPH, Rozenn N. Lemaitre, PhD, MPH, Carol E. Fahrenbruch, MSPH, Stephanie Hesselson, PhD, Nona Sotoodehnia, MD, MPH, Barbara McKnight, PhD, Kenneth M. Rice, PhD, Pui-Yan Kwok, MD, PhD, David S. Siscovick, MD, MPH and Thomas D. Rea, MD, MPH

Author Affiliations

From the Departments of Medicine (C.O.J., R.N.L., N.S., D.S.S., T.D.R.), Biostatistics (B.M., K.M.R.), and Epidemiology (D.S.S), University of Washington, Seattle; King County Emergency Medical Services, Seattle, WA (C.E.F.); and Institute of Human Genetics, University of California San Francisco (S.H., P.-Y.K.).

Correspondence to Catherine O. Johnson, PhD, MPH, Department of Medicine, University of Washington, CHRU 1730 Minor Ave, Suite 1360, Seattle, WA 98101. E-mail johnsoco@uw.edu

Abstract

Background—Fatty acids provide energy and structural substrates for the heart and brain and may influence resuscitation from sudden cardiac arrest (SCA). We investigated whether genetic variation in fatty acid metabolism pathways was associated with SCA survival.

Methods and Results—Subjects (mean age, 67 years; 80% male, white) were out-of-hospital SCA patients found in ventricular fibrillation in King County, WA. We compared subjects who survived to hospital admission (n=664) with those who did not (n=689), and subjects who survived to hospital discharge (n=334) with those who did not (n=1019). Associations between survival and genetic variants were assessed using logistic regression adjusting for age, sex, location, time to arrival of paramedics, whether the event was witnessed, and receipt of bystander cardiopulmonary resuscitation. Within-gene permutation tests were used to correct for multiple comparisons. Variants in 5 genes were significantly associated with SCA survival. After correction for multiple comparisons, single-nucleotide polymorphisms in ACSL1 and ACSL3 were significantly associated with survival to hospital admission. Single-nucleotide polymorphisms in ACSL3, AGPAT3, MLYCD, and SLC27A6 were significantly associated with survival to hospital discharge.

Conclusions—Our findings indicate that variants in genes important in fatty acid metabolism are associated with SCA survival in this population.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 422-429

Published online before print June 1, 2012,

doi: 10.1161/ CIRCGENETICS.111.961912


Genome-Wide Association Study Pinpoints a New Functional Apolipoprotein B Variant Influencing Oxidized Low-Density Lipoprotein Levels But Not Cardiovascular Events

AtheroRemo Consortium

Kari-Matti Mäkelä, BM, BSc, Ilkka Seppälä, MSc, Jussi A. Hernesniemi, MD, PhD, Leo-Pekka Lyytikäinen, MD, Niku Oksala, MD, PhD, DSc, Marcus E. Kleber, PhD, Hubert Scharnagl, PhD, Tanja B. Grammer, MD, Jens Baumert, PhD, Barbara Thorand, PhD, Antti Jula, MD, PhD, Nina Hutri-Kähönen, MD, PhD, Markus Juonala, MD, PhD, Tomi Laitinen, MD, PhD, Reijo Laaksonen, MD, PhD, Pekka J. Karhunen, MD, PhD, Kjell C. Nikus, MD, PhD, Tuomo Nieminen, MD, PhD, MSc, Jari Laurikka, MD, PhD, Pekka Kuukasjärvi, MD, PhD, Matti Tarkka, MD, PhD, Jari Viik, PhD, Norman Klopp, PhD, Thomas Illig, PhD, Johannes Kettunen, PhD, Markku Ahotupa, PhD, Jorma S.A. Viikari, MD, PhD, Mika Kähönen, MD, PhD, Olli T. Raitakari, MD, PhD, Mahir Karakas, MD, Wolfgang Koenig, MD, PhD, Bernhard O. Boehm, MD, Bernhard R. Winkelmann, MD, Winfried März, MD and Terho Lehtimäki, MD, PhD

Correspondence to Kari-Matti Mäkelä, Department of Clinical Chemistry, Finn-Medi 2, PO Box 2000, FI-33521 Tampere, Finland. E-mail kari-matti.makela@uta.fi

Abstract

Background—Oxidized low-density lipoprotein may be a key factor in the development of atherosclerosis. We performed a genome-wide association study on oxidized low-density lipoprotein and tested the impact of associated single-nucleotide polymorphisms (SNPs) on the risk factors of atherosclerosis and cardiovascular events.

Methods and Results—A discovery genome-wide association study was performed on a population of young healthy white individuals (N=2080), and the SNPs associated with a P<5×10⁻⁸ were replicated in 2 independent samples (A: N=2912; B: N=1326). Associations with cardiovascular endpoints were also assessed with 2 additional clinical cohorts (C: N=1118; and D: N=808). We found 328 SNPs associated with oxidized low-density lipoprotein. The genetic variant rs676210 (Pro2739Leu) in apolipoprotein B was the proxy SNP behind all associations (P=4.3×10–136, effect size=13.2 U/L per allele). This association was replicated in the 2 independent samples (A and B, P=2.5×10–47 and 1.1×10⁻¹¹, effect sizes=10.3 U/L and 7.8 U/L, respectively). In the meta-analyses of cohorts A, C, and D (excluding cohort B without angiographic data), the top SNP did not associate significantly with the age of onset of angiographically verified coronary artery disease (hazard ratio=1.00 [0.94–1.06] per allele), 3-vessel coronary artery disease (hazard ratio=1.03 [0.94–1.13]), or myocardial infarction (hazard ratio=1.04 [0.96–1.12]).

Conclusions—This novel genetic marker is an important factor regulating oxidized low-density lipoprotein levels but not a major genetic factor for the studied cardiovascular endpoints.

 SOURCE:

Circulation: Cardiovascular Genetics.2013; 6: 73-81

Published online before print December 17, 2012,

doi: 10.1161/ CIRCGENETICS.112.964965

Genome-Wide Screen for Metabolic Syndrome Susceptibility Loci Reveals Strong Lipid Gene Contribution But No Evidence for Common Genetic Basis for Clustering of Metabolic Syndrome Traits

Kati Kristiansson, PhD, Markus Perola, MD, PhD, Emmi Tikkanen, MSc, Johannes Kettunen, PhD, Ida Surakka, MSc, Aki S. Havulinna, DSc (Tech.), Alena Stančáková, MD, PhD, Chris Barnes, PhD, Elisabeth Widen, MD, PhD, Eero Kajantie, MD, PhD, Johan G. Eriksson, MD, DMSc, Jorma Viikari, MD, PhD, Mika Kähönen, MD, PhD, Terho Lehtimäki, MD, PhD, Olli T. Raitakari, MD, PhD, Anna-Liisa Hartikainen, MD, PhD, Aimo Ruokonen, MD, PhD, Anneli Pouta, MD, PhD, Antti Jula, MD, PhD, Antti J. Kangas, MSc, Pasi Soininen, PhD, Mika Ala-Korpela, PhD, Satu Männistö, PhD, Pekka Jousilahti, MD, PhD, Lori L. Bonnycastle, PhD, Marjo-Riitta Järvelin, MD, PhD, Johanna Kuusisto, MD, PhD, Francis S. Collins, MD, PhD, Markku Laakso, MD, PhD, Matthew E. Hurles, PhD, Aarno Palotie, MD, PhD, Leena Peltonen, MD, PhD*, Samuli Ripatti, PhD and Veikko Salomaa, MD, PhD

Correspondence to Dr Kati Kristiansson, National Institute for Health and Welfare, University of Helsinki, Biomedicum, PL 104, FI-00251 Helsinki, Finland. E-mail kati.kristiansson@thl.fi

Abstract

Background—Genome-wide association (GWA) studies have identified several susceptibility loci for metabolic syndrome (MetS) component traits, but have had variable success in identifying susceptibility loci to the syndrome as an entity. We conducted a GWA study on MetS and its component traits in 4 Finnish cohorts consisting of 2637 MetS cases and 7927 controls, both free of diabetes, and followed the top loci in an independent sample with transcriptome and nuclear magnetic resonance-based metabonomics data. Furthermore, we tested for loci associated with multiple MetS component traits using factor analysis, and built a genetic risk score for MetS.

Methods and Results—A previously known lipid locus, APOA1/C3/A4/A5 gene cluster region (SNP rs964184), was associated with MetS in all 4 study samples (P=7.23×10⁻⁹ in meta-analysis). The association was further supported by serum metabolite analysis, where rs964184 was associated with various very low density lipoprotein, triglyceride, and high-density lipoprotein metabolites (P=0.024–1.88×10⁻⁵). Twenty-two previously identified susceptibility loci for individual MetS component traits were replicated in our GWA and factor analysis. Most of these were associated with lipid phenotypes, and none with 2 or more uncorrelated MetS components. A genetic risk score, calculated as the number of risk alleles in loci associated with individual MetS traits, was strongly associated with MetS status.

Conclusions—Our findings suggest that genes from lipid metabolism pathways have the key role in the genetic background of MetS. We found little evidence for pleiotropy linking dyslipidemia and obesity to the other MetS component traits, such as hypertension and glucose intolerance.

 SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 242-249

Published online before print March 7, 2012,

doi: 10.1161/ CIRCGENETICS.111.961482


Genetics and Vascular Pathologies and Platelet Aggregation, Cardiac Troponin T in Serum


TGFβRIIb Mutations Trigger Aortic Aneurysm Pathogenesis by Altering Transforming Growth Factor β2 Signal Transduction

Katharine J. Bee, PhD, David C. Wilkes, PhD, Richard B. Devereux, MD, Craig T. Basson, MD, PhD and Cathy J. Hatcher, PhD

Author Affiliations

From the Center for Molecular Cardiology, Greenberg Division of Cardiology, Weill Cornell Medical College, New York, NY.

Correspondence to Cathy J. Hatcher, PhD, Greenberg Division of Cardiology, Weill Cornell Medical College, 525 E. 68th St, New York, NY 10065. E-mail cjhatche@med.cornell.edu

Abstract

Background—Thoracic aortic aneurysm (TAA) is a common progressive disorder involving gradual dilation of the ascending and/or descending thoracic aorta that eventually leads to dissection or rupture. Nonsydromic TAA can occur as a genetically triggered, familial disorder that is usually transmitted in a monogenic autosomal dominant fashion and is known as familial TAA. Genetic analyses of families affected with TAA have identified several chromosomal loci, and further mapping of familial TAA genes has highlighted disease-causing mutations in at least 4 genes: myosin heavy chain 11 (MYH11), α-smooth muscle actin (ACTA2), and transforming growth factor β receptors I and II (TGFβRI and TGFβRII).

Methods and Results—We evaluated 100 probands to determine the mutation frequency in MYH11, ACTA2, TGFβRI, and TGFβRII in an unbiased population of individuals with genetically mediated TAA. In this study, 9% of patients had a mutation in one of the genes analyzed, 3% of patients had mutations in ACTA2, 3% in MYH11, 1% in TGFβRII, and no mutations were found in TGFβRI. Additionally, we identified mutations in a 75 base pair alternatively spliced TGFβRII exon, exon 1a that produces the TGFβRIIb isoform and accounted for 2% of patients with mutations. Our in vitro analyses indicate that the TGFβRIIb activating mutations alter receptor function on TGFβ2 signaling.

Conclusions—We propose that TGFβRIIb expression is a regulatory mechanism for TGFβ2 signal transduction. Dysregulation of the TGFβ2 signaling pathway, as a consequence of TGFβRIIb mutations, results in aortic aneurysm pathogenesis.

SOURCE: 

Circulation: Cardiovascular Genetics.2012; 5: 621-629

Published online before print October 24, 2012,doi: 10.1161/​CIRCGENETICS.112.964064

Matrix Metalloproteinase-9 Genotype as a Potential Genetic Marker for Abdominal Aortic Aneurysm

Tyler Duellman, BS, Christopher L. Warren, PhD, Peggy Peissig, PhD, Martha Wynn, MD and Jay Yang, MD, PhD

Author Affiliations

From the Molecular and Cellular Pharmacology Graduate Program (T.D., J.Y.) and Department of Anesthesiology (M.W., J.Y.), University of Wisconsin School of Medicine and Public Health, Madison; Illumavista Biosciences LLC, Madison, WI (C.L.W.); and Biomedical Informatics Research Center, Marshfield Clinics Research Foundation, Marshfield, WI (P.P.).

Correspondence to Jay Yang, MD, PhD, Department of Anesthesiology, University of Wisconsin SMPH, SMI 301, 1300 University Ave, Madison, WI 53706. E-mail Jyang75@wisc.edu

Abstract

Background—Degradation of extracellular matrix support in the large abdominal arteries contribute to abnormal dilation of aorta, leading to abdominal aortic aneurysms, and matrix metalloproteinase-9 (MMP-9) is the predominant enzyme targeting elastin and collagen present in the walls of the abdominal aorta. Previous studies have suggested a potential association between MMP-9 genotype and abdominal aortic aneurysm, but these studies have been limited only to the p-1562 and (CA) dinucleotide repeat microsatellite polymorphisms in the promoter region of the MMP-9 gene. We determined the functional alterations caused by 15 MMP-9 single-nucleotide polymorphisms (SNPs) reported to be relatively abundant in the human genome through Western blots, gelatinase, and promoter–reporter assays and incorporated this information to perform a logistic-regression analysis of MMP-9 SNPs in 336 human abdominal aortic aneurysm cases and controls.

Methods and Results—Significant functional alterations were observed for 6 exon SNPs and 4 promoter SNPs. Genotype analysis of frequency-matched (age, sex, history of hypertension, hypercholesterolemia, and smoking) cases and controls revealed significant genetic heterogeneity exceeding 20% observed for 6 SNPs in our population of mostly white subjects from Northern Wisconsin. A step-wise logistic-regression analysis with 6 functional SNPs, where weakly contributing confounds were eliminated using Akaike information criteria, gave a final 2 SNP (D165N and p-2502) model with an overall odds ratio of 2.45 (95% confidence interval, 1.06–5.70).

Conclusions—The combined approach of direct experimental confirmation of the functional alterations of MMP-9 SNPs and logistic-regression analysis revealed significant association between MMP-9 genotype and abdominal aortic aneurysm.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 529-537

Published online before print August 31, 2012,

doi: 10.1161/ CIRCGENETICS.112.963082

Common Genetic Variation in the 3′–BCL11B Gene Desert Is Associated With Carotid-Femoral Pulse Wave Velocity and Excess Cardiovascular Disease Risk

The AortaGen Consortium

Gary F. Mitchell, MD*, Germaine C. Verwoert, MSc*, Kirill V. Tarasov, MD, PhD*, Aaron Isaacs, PhD, Albert V. Smith, PhD, Yasmin, BSc, MA, PhD, Ernst R. Rietzschel, MD, PhD, Toshiko Tanaka, PhD, Yongmei Liu, MD, PhD, Afshin Parsa, MD, MPH, Samer S. Najjar, MD, Kevin M. O’Shaughnessy, MA, BM, DPhil, FRCP, Sigurdur Sigurdsson, MSc, Marc L. De Buyzere, MSc, Martin G. Larson, ScD, Mark P.S. Sie, MD, PhD, Jeanette S. Andrews, MS, Wendy S. Post, MD, MS, Francesco U.S. Mattace-Raso, MD, PhD, Carmel M. McEniery, BSc, PhD, Gudny Eiriksdottir, MSc, Patrick Segers, PhD, Ramachandran S. Vasan, MD, Marie Josee E. van Rijn, MD, PhD, Timothy D. Howard, PhD, Patrick F. McArdle, PhD, Abbas Dehghan, MD, PhD, Elizabeth S. Jewell, MS, Stephen J. Newhouse, MSc, PhD, Sofie Bekaert, PhD, Naomi M. Hamburg, MD, Anne B. Newman, MD, MPH, Albert Hofman, MD, PhD, Angelo Scuteri, MD, PhD, Dirk De Bacquer, PhD, Mohammad Arfan Ikram, MD, PhD†, Bruce M. Psaty, MD, PhD†, Christian Fuchsberger, PhD‡, Matthias Olden, PhD‡, Louise V. Wain, PhD§, Paul Elliott, MB, PhD§, Nicholas L. Smith, PhD‖, Janine F. Felix, MD, PhD‖, Jeanette Erdmann, PhD¶, Joseph A. Vita, MD, Kim Sutton-Tyrrell, PhD, Eric J.G. Sijbrands, MD, PhD, Serena Sanna, PhD, Lenore J. Launer, MS, PhD, Tim De Meyer, PhD, Andrew D. Johnson, MD, Anna F.C. Schut, MD, PhD, David M. Herrington, MD, MHS, Fernando Rivadeneira, MD, PhD, Manuela Uda, PhD, Ian B. Wilkinson, MA, BM, FRCP, Thor Aspelund, PhD, Thierry C. Gillebert, MD, PhD, Luc Van Bortel, MD, PhD, Emelia J. Benjamin, MD, MSc, Ben A. Oostra, PhD, Jingzhong Ding, MD, PhD, Quince Gibson, MBA, André G. Uitterlinden, PhD, Gonçalo R. Abecasis, PhD, John R. Cockcroft, BSc, MB, ChB, FRCP, Vilmundur Gudnason, MD, PhD, Guy G. De Backer, MD, PhD, Luigi Ferrucci, MD, Tamara B. Harris, MD, MS, Alan R. Shuldiner, MD, Cornelia M. van Duijn, PhD, Daniel Levy, MD*, Edward G. Lakatta, MD* and Jacqueline C.M. Witteman, PhD*

Correspondence to Gary F. Mitchell, MD, Cardiovascular Engineering, Inc, 1 Edgewater Dr, Suite 201A, Norwood, MA 02062. E-mail GaryFMitchell@mindspring.com

↵* These authors contributed equally.

Abstract

Background—Carotid-femoral pulse wave velocity (CFPWV) is a heritable measure of aortic stiffness that is strongly associated with increased risk for major cardiovascular disease events.

Methods and Results—We conducted a meta-analysis of genome-wide association data in 9 community-based European ancestry cohorts consisting of 20 634 participants. Results were replicated in 2 additional European ancestry cohorts involving 5306 participants. Based on a preliminary analysis of 6 cohorts, we identified a locus on chromosome 14 in the 3′-BCL11B gene desert that is associated with CFPWV (rs7152623, minor allele frequency=0.42, β=−0.075±0.012 SD/allele, P=2.8×10⁻¹⁰; replication β=−0.086±0.020 SD/allele, P=1.4×10⁻⁶). Combined results for rs7152623 from 11 cohorts gave β=−0.076±0.010 SD/allele, P=3.1×10⁻¹⁵. The association persisted when adjusted for mean arterial pressure (β=−0.060±0.009 SD/allele, P=1.0×10⁻¹¹). Results were consistent in younger (<55 years, 6 cohorts, n=13 914, β=−0.081±0.014 SD/allele, P=2.3×10⁻⁹) and older (9 cohorts, n=12 026, β=−0.061±0.014 SD/allele, P=9.4×10⁻⁶) participants. In separate meta-analyses, the locus was associated with increased risk for coronary artery disease (hazard ratio=1.05; confidence interval=1.02–1.08; P=0.0013) and heart failure (hazard ratio=1.10, CI=1.03–1.16, P=0.004).

Conclusions—Common genetic variation in a locus in the BCL11B gene desert that is thought to harbor 1 or more gene enhancers is associated with higher CFPWV and increased risk for cardiovascular disease. Elucidation of the role this novel locus plays in aortic stiffness may facilitate development of therapeutic interventions that limit aortic stiffening and related cardiovascular disease events.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 81-90

Published online before print November 8, 2011,

doi: 10.1161/ CIRCGENETICS.111.959817

Genetic Variation in PEAR1 is Associated with Platelet Aggregation and Cardiovascular Outcomes

Joshua P. Lewis1, Kathleen Ryan1, Jeffrey R. O’Connell1, Richard B. Horenstein1, Coleen M. Damcott1, Quince Gibson1, Toni I. Pollin1, Braxton D. Mitchell1, Amber L. Beitelshees1, Ruth Pakzy1, Keith Tanner1, Afshin Parsa1, Udaya S. Tantry2, Kevin P. Bliden2, Wendy S. Post3, Nauder Faraday3, William Herzog4, Yan Gong5, Carl J. Pepine6, Julie A. Johnson5, Paul A. Gurbel2 and Alan R. Shuldiner7*

Author Affiliations

1University of Maryland School of Medicine, Baltimore, MD

2Sinai Hospital of Baltimore, Baltimore, MD

3Johns Hopkins University School of Medicine, Baltimore, MD

4Sinai Hospital of Baltimore & Johns Hopkins University School of Medicine, Baltimore, MD

5University of Florida College of Pharmacy, Gainesville, FL

6University of Florida College of Medicine, Gainesville, FL

7University of Maryland School of Medicine & Veterans Administration Medical Center, Baltimore, MD

↵* University of Maryland School of Medicine & Veterans Administration Medical Center, Baltimore, MD ashuldin@medicine.umaryland.edu

Abstract

Background-Aspirin or dual antiplatelet therapy (DAPT) with aspirin and clopidogrel is standard therapy for patients at increased risk for cardiovascular events. However, the genetic determinants of variable response to aspirin (alone and in combination with clopidogrel) are not known.

Methods and Results-We measured ex-vivo platelet aggregation before and after DAPT in individuals (n=565) from the Pharmacogenomics of Antiplatelet Intervention (PAPI) Study and conducted a genome-wide association study (GWAS) of drug response. Significant findings were extended by examining genotype and cardiovascular outcomes in two independent aspirin-treated cohorts: 227 percutaneous coronary intervention (PCI) patients, and 1,000 patients of the International VErapamil SR/trandolapril Study (INVEST) GENEtic Substudy (INVEST-GENES). GWAS revealed a strong association between single nucleotide polymorphisms on chromosome 1q23 and post-DAPT platelet aggregation. Further genotyping revealed rs12041331 in the platelet endothelial aggregation receptor-1 (PEAR1) gene to be most strongly associated with DAPT response (P=7.66×10⁻⁹). In Caucasian and African American patients undergoing PCI, A-allele carriers of rs12041331 were more likely to experience a cardiovascular event or death compared to GG homozygotes (hazard ratio = 2.62, 95%CI 0.96-7.10, P=0.059 and hazard ratio = 3.97, 95%CI 1.10-14.31, P=0.035 respectively). In aspirin-treated INVEST-GENES patients, rs12041331 A-allele carriers had significantly increased risk of myocardial infarction compared to GG homozygotes (OR=2.03, 95%CI 1.01-4.09, P=0.048).

Conclusions-Common genetic variation in PEAR1 may be a determinant of platelet response and cardiovascular events in patients on aspirin, alone and in combination with clopidogrel.

Clinical Trial Registration Information-clinicaltrials.gov; Identifiers: NCT00799396 and NCT00370045

SOURCE:

CIRCGENETICS.112.964627

Published online before print February 7, 2013,

doi: 10.1161/ CIRCGENETICS.111.964627

Association of Genome-Wide Variation With Highly Sensitive Cardiac Troponin-T Levels in European Americans and Blacks

A Meta-Analysis From Atherosclerosis Risk in Communities and Cardiovascular Health Studies

Bing Yu, MD, MSc, Maja Barbalic, PhD, Ariel Brautbar, MD, Vijay Nambi, MD, Ron C. Hoogeveen, PhD, Weihong Tang, PhD, Thomas H. Mosley, PhD, Jerome I. Rotter, MD, Christopher R. deFilippi, MD, Christopher J. O’Donnell, MD, Sekar Kathiresan, MD, Ken Rice, PhD, Susan R. Heckbert, MD, PhD, Christie M. Ballantyne, MD, Bruce M. Psaty, MD, PhD and Eric Boerwinkle, PhD on behalf of the CARDIoGRAM Consortium

Author Affiliations

From the Human Genetic Center, University of Texas Health Science Center at Houston, Houston, TX (B.Y., M.B., E.B.); Deptartment of Medicine (A.B., V.N., R.C.H., C.M.B.), and Human Genome Sequencing Center (E.B.), Baylor College of Medicine, Houston, TX; Department of Epidemiology, University of Minnesota, Minneapolis, MN (W.T.); Division of Geriatrics, University of Mississippi Medical Center, Jackson, MS (T.H.M.); Medical Genetics Institute, Cedars-Sinai Medical Center, Los Angeles, CA (J.I.R.); School of Medicine, University of Maryland, Baltimore, MD (C.R.D.); National Heart, Lung, and Blood Institute and Framingham Heart Study, National Institutes of Health, Bethesda, MD (C.J.O.D.); Center for Human Genetic Research & Cardiovascular Research Center, Massachusetts General Hospital and Department of Medicine, Harvard Medical School, Boston, MA (S.K.); Department of Biostatistics (K.R.), and Cardiovascular Health Research Unit & Department of Epidemiology (S.R.H.), University of Washington, Seattle, WA; and Cardiovascular Health Research Unit, Departments of Medicine, Epidemiology, and Health Services, University of Washington & Group Health Research Institute, Group Health Cooperative, Seattle, WA (B.M.P.).

Correspondence to Eric Boerwinkle, PhD, Human Genetic Center, University of Texas School of Public Health, 1200 Herman Pressler E-447, Houston, TX 77030. E-mail Eric.Boerwinkle@uth.tmc.edu

Abstract

Background—High levels of cardiac troponin T, measured by a highly sensitive assay (hs-cTnT), are strongly associated with incident coronary heart disease and heart failure. To date, no large-scale genome-wide association study of hs-cTnT has been reported. We sought to identify novel genetic variants that are associated with hs-cTnT levels.

Methods and Results—We performed a genome-wide association in 9491 European Americans and 2053 blacks free of coronary heart disease and heart failure from 2 prospective cohorts: the Atherosclerosis Risk in Communities Study and the Cardiovascular Health Study. Genome-wide association studies were conducted in each study and race stratum. Fixed-effect meta-analyses combined the results of linear regression from 2 cohorts within each race stratum and then across race strata to produce overall estimates and probability values. The meta-analysis identified a significant association at chromosome 8q13 (rs10091374; P=9.06×10⁻⁹) near the nuclear receptor coactivator 2 (NCOA2) gene. Overexpression of NCOA2 can be detected in myoblasts. An additional analysis using logistic regression and the clinically motivated 99th percentile cut point detected a significant association at 1q32 (rs12564445; P=4.73×10⁻⁸) in the gene TNNT2, which encodes the cardiac troponin T protein itself. The hs-cTnT-associated single-nucleotide polymorphisms were not associated with coronary heart disease in a large case-control study, but rs12564445 was significantly associated with incident heart failure in Atherosclerosis Risk in Communities Study European Americans (hazard ratio=1.16; P=0.004).

Conclusions—We identified 2 loci, near NCOA2 and in the TNNT2 gene, at which variation was significantly associated with hs-cTnT levels. Further use of the new assay should enable replication of these results.

 SOURCE:

Circulation: Cardiovascular Genetics.2013; 6: 82-88

Published online before print December 16, 2012,

doi: 10.1161/ CIRCGENETICS.112.963058


Genomics and Valvular Disease


Supravalvular Aortic Stenosis Elastin Arteriopathy


Giuseppe Merla, PhD, Nicola Brunetti-Pierri, MD, Pasquale Piccolo, PhD, Lucia Micale, PhD and Maria Nicla Loviglio, PhD, MSc

Author Affiliations

From the Medical Genetics Unit, IRCCS Casa Sollievo Della Sofferenza Hospital, San Giovanni Rotondo, Italy (G.M., L.M., M.N.L.); Telethon Institute of Genetics and Medicine, Napoli, Italy (N.B-P., P.P.); Department of Pediatrics, Federico II University of Naples, Naples, Italy (N.B-P.); and CIG Center for Integrative Genomics, University of Lausanne, Lausanne, Switzerland (M.N.L.).

Correspondence to Giuseppe Merla, PhD, Medical Genetics Unit, IRCCS Casa Sollievo della Sofferenza, viale Cappuccini, 71013 San Giovanni Rotondo, Italy. E-mail g.merla@operapadrepio.it

Abstract

Supravalvular aortic stenosis is a systemic elastin (ELN) arteriopathy that disproportionately affects the supravalvular aorta. ELN arteriopathy may be present in a nonsyndromic condition or in syndromic conditions such as Williams–Beuren syndrome. The anatomic findings include congenital narrowing of the lumen of the aorta and other arteries, such as branches of pulmonary or coronary arteries. Given the systemic nature of the disease, accurate evaluation is recommended to establish the degree and extent of vascular involvement and to plan appropriate interventions, which are indicated whenever hemodynamically significant stenoses occur. ELN arteriopathy is genetically heterogeneous and occurs as a consequence of haploinsufficiency of the ELN gene on chromosome 7q11.23, owing to either microdeletion of the entire chromosomal region or ELN point mutations. Interestingly, there is a prevalence of premature termination mutations resulting in null alleles among ELN point mutations. The identification of the genetic defect in patients with supravalvular aortic stenosis is essential for a definitive diagnosis, prognosis, and genetic counseling.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 692-696

doi: 10.1161/ CIRCGENETICS.112.962860

Genetic Loci for Coronary Calcification and Serum Lipids Relate to Aortic and Carotid Calcification

Daniel Bos, MD, M. Arfan Ikram, MD, PhD, Aaron Isaacs, PhD, Benjamin F.J. Verhaaren, MD, Albert Hofman, MD, PhD, Cornelia M. van Duijn, PhD, Jacqueline C.M. Witteman, PhD, Aad van der Lugt, MD, PhD and Meike W. Vernooij, MD, PhD

Author Affiliations

From the Departments of Radiology (D.B., M.A.I., B.F.J.V., A.v.d.L., M.W.V), Epidemiology (D.B., M.A.I., A.I., B.F.J.V., A.H., C.M.v.D., J.C.M.W., M.W.V.), and Genetic Epidemiology Unit (A.I., C.M.v.D.), Erasmus MC, Rotterdam, the Netherlands.

Correspondence to Meike W. Vernooij, MD, PhD, Department of Radiology, Erasmus MC, Gravendijkwal 230, PO Box 2040, 3000CA Rotterdam, the Netherlands. E-mail m.vernooij@erasmusmc.nl

Abstract

Background—Atherosclerosis in different vessel beds shares lifestyle and environmental risk factors. It is unclear whether this holds for genetic risk factors. Hence, for the current study genetic loci for coronary artery calcification and serum lipid levels, one of the strongest risk factors for atherosclerosis, were used to assess their relation with atherosclerosis in different vessel beds.

Methods and Results—From 1987 persons of the population-based Rotterdam Study, 3 single-nucleotide polymorphisms (SNPs) for coronary artery calcification and 132 SNPs for total cholesterol, low-density lipoprotein cholesterol, high-density lipoprotein cholesterol or triglycerides were used. To quantify atherosclerotic calcification as a marker of atherosclerosis, all participants underwent nonenhanced computed tomography of the aortic arch and carotid arteries. Associations between genetic risk scores of the joint effect of the SNPs and of all calcification were investigated. The joint effect of coronary artery calcification–SNPs was associated with larger calcification volumes in all vessel beds (difference in calcification volume per SD increase in genetic risk score: 0.15 [95% confidence interval, 0.11–0.20] in aorta, 0.14 [95% confidence interval, 0.10–0.18] in extracranial carotids, and 0.11 [95% confidence interval, 0.07–0.16] in intracranial carotids). The joint effect of total cholesterol SNPs, low-density lipoprotein SNPs, and of all lipid SNPs together was associated with larger calcification volumes in both the aortic arch and the carotid arteries but attenuated after adjusting for the lipid fraction and lipid-lowering medication.

Conclusions—The genetic basis for aortic arch and carotid artery calcification overlaps with the most important loci of coronary artery calcification. Furthermore, serum lipids share a genetic predisposition with both calcification in the aortic arch and the carotid arteries, providing novel insights into the cause of atherosclerosis.

 SOURCE:

Circulation: Cardiovascular Genetics.2013; 6: 47-53

Published online before print December 16, 2012,

doi: 10.1161/ CIRCGENETICS.112.963934


Joint Associations of 61 Genetic Variants in the Nicotinic Acetylcholine Receptor Genes with Subclinical Atherosclerosis in American Indians

A Gene-Family Analysis

Jingyun Yang, PhD*, Yun Zhu, MS*, Elisa T. Lee, PhD, Ying Zhang, PhD, Shelley A. Cole, PhD, Karin Haack, PhD, Lyle G. Best, BS MD, Richard B. Devereux, MD, Mary J. Roman, MD, Barbara V. Howard, PhD and Jinying Zhao, MD, PhD

Author Affiliations

From the Tulane University School of Public Health and Tropical Medicine, New Orleans, LA (J.Y., Y. Zhu, J.Z.); Center for American Indian Health Research, University of Oklahoma Health Sciences Center, Oklahoma City, OK (E.T.L., Y. Zhang); Texas Biomedical Research Institute, San Antonio, TX (S.A.C., K.H.); Missouri Breaks Industries Research Inc, Timber Lake, SD (L.G.B.); The New York Hospital-Cornell Medical Center, New York, NY (R.B.D., M.J.R.); MedStar Health Research Institute, Hyattsville, MD (B.V.H.); and Georgetown and Howard Universities Centers for Translational Sciences, Washington, DC (B.V.H.).

Correspondence to Jinying Zhao, MD, PhD, Department of Epidemiology, School of Public Health and Tropical Medicine, Tulane University, 1440 Canal St, SL18, New Orleans, LA 70112. E-mail jzhao5@tulane.edu

↵* These authors contributed equally to this work.

Abstract

Background—Atherosclerosis is the underlying cause of cardiovascular disease, the leading cause of morbidity and mortality in all American populations, including American Indians. Genetic factors play an important role in the pathogenesis of atherosclerosis. Although a single-nucleotide polymorphism (SNP) may explain only a small portion of variability in disease, the joint effect of multiple variants in a pathway on disease susceptibility could be large.

Methods and Results—Using a gene-family analysis, we investigated the joint associations of 61 tag SNPs in 7 nicotinic acetylcholine receptor genes with subclinical atherosclerosis, as measured by carotid intima-media thickness and plaque score, in 3665 American Indians from 94 families recruited by the Strong Heart Family Study (SHFS). Although multiple SNPs showed marginal association with intima-media thickness and plaque score individually, only a few survived adjustments for multiple testing. However, simultaneously modeling of the joint effect of all 61 SNPs in 7 nicotinic acetylcholine receptor genes revealed significant association of the nicotinic acetylcholine receptor gene family with both intima-media thickness and plaque score independent of known coronary risk factors.

Conclusions—Genetic variants in the nicotinic acetylcholine receptor gene family jointly contribute to subclinical atherosclerosis in American Indians who participated in the SHFS. These variants may influence the susceptibility of atherosclerosis through pathways other than cigarette smoking per se.

SOURCE:

Circulation: Cardiovascular Genetics.2013; 6: 89-96

Published online before print December 22, 2012,

doi: 10.1161/ CIRCGENETICS.112.963967


Heredity of Cardiovascular Disorders Inheritance


A Clinical Approach to Common Cardiovascular Disorders When There Is a Family History

The Implications of Inheritance for Clinical Management

Srijita Sen-Chowdhry, MBBS, MD, FESC, Daniel Jacoby, MD and William J. McKenna, MD, DSc, FESC

Author Affiliations

From the Institute of Cardiovascular Science, University College London, London, United Kingdom (S.S-C., W.J.M.); Department of Epidemiology, Imperial College, London, London, United Kingdom (S.S-C.); Division of Cardiology, Yale School of Medicine, New Haven, CT (D.J., W.J.M.).

Correspondence to Professor William J. McKenna, MD, DSc, FESC, Institute of Cardiovascular Science, University College London, The Heart Hospital, 16-18 Westmoreland Street, London, E-mail william.mckenna@uclh.nhs.uk

Introduction

Since the advent of genotyping, recognition of heritable disease has been perceived as an opportunity for genetic diagnosis or new gene identification studies to advance understanding of pathogenesis. Until recently, however, clinical application of DNA-based testing was confined largely to Mendelian disorders. Even within this remit, predictive testing of relatives is cost-effective only in diseases in which the majority of families harbor mutations in known causal genes, such as adult polycystic kidney disease and hypertrophic cardiomyopathy, but not dilated cardiomyopathy. Confirmatory genetic testing of index cases with borderline clinical features may be economic in the still smaller subset of diseases with limited locus heterogeneity, such as Marfan syndrome. Furthermore, Mendelian diseases account for ≈5% of total disease burden.1 Genome-wide association studies have made headway in elucidating the genetic contribution to the more common, complex diseases, and high throughput techniques promise to facilitate integration of genetic analysis into clinical practice. Nevertheless, many genes remain to be identified and implementation of genomic profiling as a population screening tool would not be cost-effective at present. The implications of heredity, however, extend beyond serving as a platform for genetic analysis, influencing diagnosis, prognostication, and treatment of both index cases and relatives, and enabling rational targeting of genotyping resources. This review covers acquisition of a family history, evaluation of heritability and inheritance patterns, and the impact of inheritance on subsequent components of the clinical pathway.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 467-476

doi: 10.1161/ CIRCGENETICS.110.959361

Clinical Considerations of Heritable Factors in Common Heart Failure

Thomas P. Cappola, MD, ScM and Gerald W. Dorn II, MD

Author Affiliations

From the Department of Medicine, University of Pennsylvania, Philadelphia, PA (T.P.C.), and Center for Pharmacogenomics, Washington University School of Medicine, St Louis, MO (G.W.D.II.).

Correspondence to Gerald W. Dorn II, MD, Center for Pharmacogenomics, Washington University, 660 S Euclid Ave, Campus Box 8220, St Louis, MO 63110. E-mail gdorn@dom.wustl.edu


Introduction

Heart failure is a common condition responsible for at least 290 000 deaths each year in the United States alone.1 A small minority of heart failure cases are attributed to Mendelian or familial cardiomyopathies. The majority of systolic heart failure cases are not familial but represent the end result of 1 or many conditions that primarily injure the myocardium sufficiently to diminish cardiac output in the absence of compensatory mechanisms. Paradoxically, because they also injure the myocardium, it is the chronic actions of the compensatory mechanisms that in many instances contribute to the progression from simple cardiac injury to dilated cardiomyopathy and overt heart failure. Thus, the epidemiology of common heart failure appears to be just as sporadic as its major antecedent conditions (atherosclerosis, diabetes, hypertension, and viral myocarditis).

Familial trends in preclinical cardiac remodeling2 and risk of developing heart failure3 reveal an important role for genetic modifiers in addition to clinical and environmental factors. Candidate gene studies performed over the past 10 years have identified a few polymorphic gene variants that modify risk or progression of common heart failure.4 Whole-genome sequencing will lead to the discovery of other genetic modifiers that were not candidates.5 The imminent availability of individual whole-genome sequences at a cost competitive with available genetic tests for familial cardiomyopathy will no doubt further expand the list of putative genetic heart failure modifiers. Heart failure risk alleles along with traditional clinical factors will need to be considered by clinical cardiologists in their design of optimal disease surveillance and prevention programs and in individually tailoring heart failure management.

The use of individual genetic make-up is likely to have the earliest and greatest impact on managing patients with heart failure by tailoring available pharmacotherapeutics to optimize patient response and minimize adverse effects (ie, the area of pharmacogenetics). Modern heart failure management has been derived and directed by the results of large, randomized, multicenter clinical trials. When standard therapies are applied according to the selection criteria used in these trials, they prolong average survival across affected populations or decrease the incidence of heart failure in populations at risk.6 For this reason, standardized treatment guidelines prescribe heart failure therapies according to trial designs, aiming for the same target doses and general treatment approaches,7 and largely ignore individual characteristics. In this article, we review established and emerging knowledge of genetic influence on common heart failure and try to anticipate how these genetic factors may be best used to eschew the cookie-cutter approach to heart failure management and move toward implementing a personalized medicine approach for the treatment and prevention of this important and prevalent disease.

The Concept of Genotype-Directed Personal Medical Management in Heart Failure

Variation in clinical heart failure progression and therapeutic response (either benefits or side effects) supports the need for a more individualized approach to disease management. On the basis of clinical stratification (eg, by etiology of heart failure as ischemic versus nonischemic, functional status, comorbid disease), physicians try to match each patient’s specific heart failure syndrome with a therapeutic regime devised to provide the most benefit. Standard heart failure pharmacotherapy currently comprises a minimum of 3 medications (angiotensin-converting enzyme [ACE] inhibitors, β-blockers, and aldosterone antagonists), with consideration of additional medications (hydralazine/isosorbide, angiotensin receptor blockers) and diuretics. The recommended target dosages for these agents, derived from their respective clinical trials, is rarely achieved,8 partly because of untoward clinical side effects such as low blood pressure or renal dysfunction. Accordingly, the published guidelines most often are applied in each individual patient using ad hoc approaches derived from personal experience and the “art of medicine.”

Technological advances in human genomics promise a different approach and are bringing cardiology into an era of clinically applied pharmacogenetics9 (whether we want to or not). As sequencing costs decline, it is not hard to envision that patients will present having had their entire genome already sequenced. The imperative to apply genome information in clinical settings will increase, as demonstrated by recent proof-of-concept studies.10 Our field seems poorly prepared for this type of evolution in care; Roden et al9 identified 3 major barriers: First is the absence of rapidly available genotype information in the clinical workflow. This barrier is being overcome with whole-genome sequencing, which (with proper analysis) promises a permanent and largely immutable genetic roadmap for individual disease risk and drug response at a cost comparable to many other clinical tests.11 Second, we must have the knowledge to properly apply information on genetic variants for the diseases we are managing and the drugs we are using. As we describe, this knowledge is accumulating for heart failure and for other cardiac conditions, and the rate at which we are gaining additional information and developing further expertise appears to be accelerating.

The third and perhaps most formidable barrier is the lack of clinical evidence showing how real-time application of genetic information can best benefit patients. As has been broadly communicated to the medical community and lay public, common functional gene variants in CYP2C19 can impair the transformation of clopidogrel into its active metabolite, leading to increased risk of stent thrombosis after percutaneous coronary intervention.12 The relevant question thus becomes the following: If physicians have this information at the time of clinical care and reacted by adjusting clopidogrel dose or substituting prasugrel, which is unaffected by CYP2C19 genotype,13 would there be any improvement in clinical outcome? It is also important to consider whether any observed benefits justify the additional costs of genetic testing and for the alternate drug. Studies are currently examining these questions, and similar clinical trials will prospectively examine whether a genotype-guided strategy of warfarin dosing will be superior to the standard genotype-blinded approach in reaching target anticoagulation goals. At this time, there are no similar prospective, randomized, blinded trials of genotype-guided care for common heart failure.

Emerging Variants

The variants described here are established, but new ones are emerging. Although findings in heart failure genome-wide association studies have been limited, we can expect additional common heart failure variants to emerge as sample sizes increase.65 The CHARGE (Cohorts for Heart and Aging Research in Genomic Epidemiology) consortium published a genome-wide association study of incident heart failure that tested for associations between >2.4 million HapMap-imputed polymorphisms in >20 000 subjects.7 They identified 2 loci associated with heart failure, rs10519210 (15q22, containing USP3 encoding a ubiquitin-specific protease) in subjects of European ancestry and rs11172782 (12q14, containing LRIG3 encoding a leucine-rich, immunoglobulin-like domain-containing protein of uncertain function) in subjects of African ancestry.66 In a companion study using the same population and genotyping results, mortality analysis of the subgroup of individuals who developed heart failure implicated an intronic SNP in CMTM7 (CKLF-like MARVEL transmembrane domain-containing 7).67 These genetic associations require independent replication and further study to identify the underlying biological mechanisms.

A recently published genome-wide association study by a European consortium on dilated cardiomyopathy identified common variants in BAG3 (BCL2-associated athanogene 3) associated with heart failure57 and identified rare BAG3 missense and truncation mutations that segregate with familial cardiomyopathy. These findings were consistent with an earlier exome-sequencing study that identified BAG3 as a familial dilated cardiomyopathy gene and showed recapitulation of cardiomyopathy with BAG3 morpholino knockdown in zebra fish.68 Together, these studies convincingly support variation in BAG3 as a genetic risk factor of cardiomyopathy and heart failure. It is noteworthy that both common and rare functional variations were identified at this locus. A unifying hypothesis for these findings, which needs to be formally tested, is that common variants in BAG3 serve as proxies for rare functional BAG3 mutations with large effects. In this situation, the underlying genetic lesion is a rare variant with a large functional effect. This has recently been described for common variants in MYH6 that correlated with rare functional MYH6 variants to cause sick sinus syndrome.69 It is premature to speculate on the clinical applications of these newer findings.

Moving Knowledge to Practice

A small number of genomic variants have been identified that modify heart failure by affecting well-understood physiological systems. The principal barrier preventing their adoption in practice may be lack of evidence showing how application of this information can best be used for clinical benefit. Trials testing genotype targeting of antiplatelet therapy and anticoagulation will be completed in the coming years. The findings from these studies will likely determine the level of enthusiasm for conducting genotype-guided trials of β-blockers and RAAS antagonists in heart failure. Given that the lifetime risk of heart failure in the United States is estimated at 1 in 5, even a small favorable effect on heart failure prevention or outcome through use of genome-guided therapy has the potential for a large public health impact. We therefore believe that a near-term goal should be to conduct pharmacogenomic trials in heart failure based on our current understanding of heart failure variants.

Looking ahead, unbiased approaches will continue to reveal a large number heart failure-modifying variants (both common and rare). Based on experience in other complex phenotypes, such has height70 and plasma lipid levels,71 the underlying genetic mechanisms for many new heart failure variants will be completely unknown, and their sheer number will preclude detailed experimentation using murine models to figure them out. Leveraging these variants for clinical application is a challenge that we will be forced to confront.

As our ability to identify rare, disease-causing variants improves through personal genome sequencing, we will be faced with the additional problem of how best to estimate the disease risk conferred by a sequence variant for which there has been no biological validation. In probabilistic terms, because there are 3 billion nucleotides in the human genome and over twice that many humans on the planet, it is likely that a nucleotide substitution for every position is represented in someone. Obviously, it will be impossible to recombinantly express and functionally characterize every DNA variant that is going to be implicated in heart failure. Bioinformatics filters have been used to try and separate functionally significant from insignificant variants based on the likelihood of changing transcript expression or protein function. These tools are limited but will improve if we tailor their results to the known characteristics of each gene product. For example, current approaches to categorize amino acid substitutions as conservative or nonconservative based only on charge or side chains can be improved by molecular modeling that incorporates protein-specific structure-function information. This approach has been used to estimate the pathogenicity of myosin heavy chain (MHC) mutations in an effort to determine which mutations are likely to cause familial cardiomyopathy when linkage analysis is not feasible.72 In concept, this approach can be applied to any protein for which structure-function activities have been finely mapped to distinct domains.

A promising extension of this approach may be to use evolutionary genetics to infer disease causality. Again, using the MHC genes as examples, human genome data show a greater prevalence of nonsynonymous gene variants in MYH6, which encodes the minor cardiac α-MHC isoform, compared with the adjacent MYH7, which encodes the major β-MHC isoform. This disparity suggests a greater tolerance for protein changes in the α-MHC isoform and negative selection against these in β-MHC. We can infer, therefore, that amino acid changes are more likely to have adverse impacts in MYH7-encoded β-MHC. If this paradigm survives prospective testing, then the forthcoming explosion of individual genetic data not only will present a massive problem in interpretation, but also will provide the genetic information by which analyses of rare sequence variants across large unaffected populations can help to differentiate the tolerable variants from those that are more likely to alter disease risk.

Each Reference above is found in:

http://circgenetics.ahajournals.org/content/4/6/701.full

SOURCE: 

Circulation: Cardiovascular Genetics.2011; 4: 701-709

doi: 10.1161/ CIRCGENETICS.110.959379


Pharmacogenomics


Hypertension Susceptibility Loci and Blood Pressure Response to Antihypertensives

Results From the Pharmacogenomic Evaluation of Antihypertensive Responses Study

Yan Gong, PhD, Caitrin W. McDonough, PhD, Zhiying Wang, MS, Wei Hou, PhD, Rhonda M. Cooper-DeHoff, PharmD, MS, Taimour Y. Langaee, PhD, Amber L. Beitelshees, PharmD, MPH, Arlene B. Chapman, MD, John G. Gums, PharmD, Kent R. Bailey, PhD, Eric Boerwinkle, PhD, Stephen T. Turner, MD and Julie A. Johnson, PharmD

Author Affiliations

From the Department of Pharmacotherapy and Translational Research (Y.G., C.W.M., R.M.C.-D., T.Y.L., J.G.G., J.A.J.), Department of Biostatistics, College of Medicine (W.H.), Division of Cardiovascular Medicine, College of Medicine (R.M.C.-D., J.A.J.), and Department of Community Health and Family Medicine (J.G.G.), University of Florida, Gainesville, FL; Division of Epidemiology, University of Texas at Houston, Houston, TX (Z.W., E.B.); Division of Endocrinology, Diabetes and Nutrition, University of Maryland, Baltimore, MD (A.L.B.); Renal Division, Emory University, Atlanta, GA (A.B.C.); and Division of Nephrology and Hypertension, Mayo Clinic, Rochester, MN (S.T.T.).

Correspondence to Yan Gong, PhD, Department of Pharmacotherapy and Translational Research, University of Florida, PO Box 100486, 1600 SW Archer Rd, Gainesville, FL 32610. E-mail gong@cop.ufl.edu.

Abstract

Background—To date, 39 single nucleotide polymorphisms (SNPs) have been associated with blood pressure (BP) or hypertension in genome-wide association studies in whites. Our hypothesis is that the loci/SNPs associated with BP/hypertension are also associated with BP response to antihypertensive drugs.

Methods and Results—We assessed the association of these loci with BP response to atenolol or hydrochlorothiazide monotherapy in 768 hypertensive participants in the Pharmacogenomics Responses of Antihypertensive Responses study. Linear regression analysis was performed on whites for each SNP in an additive model adjusting for baseline BP, age, sex, and principal components for ancestry. Genetic scores were constructed to include SNPs with nominal associations, and empirical P values were determined by permutation test. Genotypes of 37 loci were obtained from Illumina 50K cardiovascular or Omni1M genome-wide association study chips. In whites, no SNPs reached Bonferroni-corrected α of 0.0014, 6 reached nominal significance (P<0.05), and 3 were associated with atenolol BP response at P<0.01. The genetic score of the atenolol BP-lowering alleles was associated with response to atenolol (P=3.3×10⁻⁶ for systolic BP; P=1.6×10⁻⁶ for diastolic BP). The genetic score of the hydrochlorothiazide BP-lowering alleles was associated with response to hydrochlorothiazide (P=0.0006 for systolic BP; P=0.0003 for diastolic BP). Both risk score P values were <0.01 based on the empirical distribution from the permutation test.

Conclusions—These findings suggest that selected signals from hypertension genome-wide association studies may predict BP response to atenolol and hydrochlorothiazide when assessed through risk scoring.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 686-691

Published online before print October 19, 2012,

doi: 10.1161/ CIRCGENETICS.112.964080


Genetic Determinants of Statin-Induced Low-Density Lipoprotein Cholesterol Reduction

The Justification for the Use of Statins in Prevention: An Intervention Trial Evaluating Rosuvastatin (JUPITER) Trial

Daniel I. Chasman, PhD, Franco Giulianini, PhD, Jean MacFadyen, BA, Bryan J. Barratt, PhD, Fredrik Nyberg, MD, PhD, MPH and Paul M Ridker, MD, MPH

Author Affiliations

From the Center for Cardiovascular Disease Prevention (D.I.C., F.G., J.M., P.M.R.), JUPITER Trial Coordinating Center (D.I.C., F.G., J.M., P.M.R.), Brigham and Women’s Hospital and Harvard Medical School (D.I.C., P.M.R.), Boston, MA; Personalised Healthcare and Biomarkers, AstraZeneca Research and Development, Alderley Park, United Kingdom (B.J.B.); AstraZeneca Research and Development, Mölndal, Sweden (F.N.); and Unit of Occupational and Environmental Medicine, Department of Public Health and Community Medicine, Sahlgrenska Academy, University of Gothenburg, Gothenburg, Sweden (F.N.).

Correspondence to Daniel I. Chasman, PhD, Center for Cardiovascular Disease Prevention, Brigham and Women’s Hospital, 900 Commonwealth Ave E, Boston, MA 02215. E-mail dchasman@rics.bwh.harvard.edu

Abstract

Background—In statin trials, each 20 mg/dL reduction in cholesterol results in a 10–15% reduction of annual incidence rates for vascular events. However, interindividual variation in low-density lipoprotein cholesterol (LDL-C) response to statins is wide and may partially be determined on a genetic basis.

Methods and Results—A genome-wide association study of LDL-C response was performed among a total of 6989 men and women of European ancestry who were randomly allocated to either rosuvastatin 20 mg daily or placebo. Single nucleotide polymorphisms (SNPs) for genome-wide association (P<5×10⁻⁸) with LDL-C reduction on rosuvastatin were identified at ABCG2, LPA, and APOE, and a further association at PCSK9 was genome-wide significant for baseline LDL-C and locus-wide significant for LDL-C reduction. Median LDL-C reductions on rosuvastatin were 40, 48, 51, 55, 60, and 64 mg/dL, respectively, among those inheriting increasing numbers of LDL-lowering alleles for SNPs at these 4 loci (P trend=6.2×10⁻²⁰), such that each allele approximately doubled the odds of percent LDL-C reduction greater than the trial median (odds ratio, 1.9; 95% confidence interval, 1.8–2.1; P=5.0×10−41). An intriguing additional association with sub–genome-wide significance (P<1×10⁻⁶) was identified for statin related LDL-C reduction at IDOL, which mediates posttranscriptional regulation of the LDL receptor in response to intracellular cholesterol levels. In candidate analysis, SNPs in SLCO1B1 and LDLR were confirmed as associated with LDL-C lowering, and a significant interaction was observed between SNPs in PCSK9 and LDLR.

Conclusions—Inherited polymorphisms that predominantly relate to statin pharmacokinetics and endocytosis of LDL particles by the LDL receptor are common in the general population and influence individual patient response to statin therapy.

SOURCE:

Circulation: Cardiovascular Genetics.2012; 5: 257-264

Published online before print February 13, 2012,

doi: 10.1161/ CIRCGENETICS.111.961144

Genetic Variation in the β2 Subunit of the Voltage-Gated Calcium Channel and Pharmacogenetic Association With Adverse Cardiovascular Outcomes in the INternational VErapamil SR-Trandolapril STudy GENEtic Substudy (INVEST-GENES)

Yuxin Niu, PhD*, Yan Gong, PhD*, Taimour Y. Langaee, PhD, Heather M. Davis, PharmD, Hazem Elewa, PhD, Amber L. Beitelshees, PharmD, MPH, James I. Moss, PhD, Rhonda M. Cooper-DeHoff, PharmD, Carl J. Pepine, MD and Julie A. Johnson, PharmD

Author Affiliations

From the Department of Pharmacotherapy and Translational Research and Center for Pharmacogenomics (Y.N., Y.G., T.Y.L., H.M.D., H.E., J.I.M., R.M.C.-D., J.A.J.), College of Pharmacy, University of Florida, Gainesville, Fla; Division of Endocrinology, Diabetes and Nutrition (A.L.B.), University of Maryland School of Medicine, Baltimore, Md; and Division of Cardiovascular Medicine (R.M.C.-D., C.J.P., J.A.J.), University of Florida College of Medicine, Gainesville, Fla.

Correspondence to Julie A. Johnson, PharmD, Department of Pharmacotherapy and Translational Research, College of Pharmacy, University of Florida, PO Box 100486, Gainesville, FL 32610. E-mail Johnson@cop.ufl.edu

↵* Drs Niu and Gong contributed equally to this work.

Abstract

Background— Single-nucleotide polymorphisms (SNPs) within the regulatory β2 subunit of the voltage-gated calcium channel (CACNB2) may contribute to variable treatment response to antihypertensive drugs and adverse cardiovascular outcomes.

Methods and Results— SNPs in CACNB2 from 60 ethnically diverse individuals were identified and characterized. Three common SNPs (rs2357928, rs7069292, and rs61839258) and a genome-wide association study-identified intronic SNP (rs11014166) were genotyped for a clinical association study in 5598 hypertensive patients with coronary artery disease randomized to a β-blocker (BB) or a calcium channel blocker (CCB) treatment strategy in the INternational VErapamil SR-Trandolapril STudy GENEtic Substudy (INVEST-GENES). Reporter gene assays were conducted on the promoter SNP, showing association with clinical outcomes. Twenty-one novel SNPs were identified. A promoter A>G SNP (rs2357928) was found to have significant interaction with treatment strategy for adverse cardiovascular outcomes (P for interaction, 0.002). In whites, rs2357928 GG patients randomized to CCB were more likely to experience an adverse outcome than those randomized to BB treatment strategy, with adjusted hazard ratio (HR) (CCB versus BB) of 2.35 (95% CI, 1.19 to 4.66; P=0.014). There was no evidence for such treatment difference in AG (HR, 1.16; 95% CI, 0.75 to 1.79; P=0.69) and AA (HR, 0.63; 95% CI, 0.36 to 1.11; P=0.11) patients. This finding was consistent in Hispanics and blacks. CACNB2 rs11014166 showed similar pharmacogenetic effect in Hispanics, but not in whites or blacks. Reporter assay analysis of rs2357928 showed a significant increase in promoter activity for the G allele compared to the A allele.

Conclusions— These data suggest that genetic variation within CACNB2 may influence treatment-related outcomes in high-risk patients with hypertension.

Clinical Trial Registration— URL: http://www.clinicaltrials.gov. Unique identifier: NCT00133692.

SOURCE:

Circulation: Cardiovascular Genetics.2010; 3: 548-555

doi: 10.1161/ CIRCGENETICS.110.957654


Hepatic Metabolism and Transporter Gene Variants Enhance Response to Rosuvastatin in Patients With Acute Myocardial Infarction

The GEOSTAT-1 Study

Kristian M. Bailey, MBChB, Simon P.R. Romaine, BSc, Beryl M. Jackson, RGN, Amanda J. Farrin, MSc, Maria Efthymiou, MSc, Julian H. Barth, MD, Joanne Copeland, BSc, Terry McCormack, MBBS, Andrew Whitehead, MSc, Marcus D. Flather, MBBS, Nilesh J. Samani, MD, FMedSci, Jane Nixon, PhD, Alistair S. Hall, MD, PhD, Anthony J. Balmforth, PhD and on behalf of the SPACE ROCKET Trial Group

Author Affiliations

From the Division of Cardiovascular and Diabetes Research (K.M.B., S.P.R.R., B.M.J., A.J.B.), and Division of Cardiovascular and Neuronal Remodelling (A.S.H.), Multidisciplinary Cardiovascular Research Centre, Leeds Institute of Genetics, Health and Therapeutics, University of Leeds, Leeds, United Kingdom; Clinical Trials Research Unit (A.J.F., M.E., J.C., J.N.), University of Leeds, Leeds, United Kingdom; Clinical Biochemistry (J.H.B.), Leeds General Infirmary, Leeds, United Kingdom; Whitby Group Practice (T.M.), Spring Vale Medical Centre, Whitby, North Yorkshire, United Kingdom; Pharmacy Department (A.W.), Leeds General Infirmary, Leeds, United Kingdom; Clinical Trials and Evaluation Unit (M.D.F.), Royal Brompton and Harefield NHS Trust and Imperial College, London, United Kingdom; and Department of Cardiovascular Sciences (N.J.S.), University of Leicester, Leicester, United Kingdom.

Correspondence to Alistair S. Hall, Clinical Cardiology, Multidisciplinary Cardiovascular Research Centre (MCRC), G Floor, Jubilee Building, Leeds General Infirmary, Leeds, LS1 3EX, United Kingdom. E-mail A.S.Hall@leeds.ac.uk

* Dr Bailey, Mr Romaine, Dr Hall, and Dr Balmforth contributed equally to this study.

Abstract

Background— Pharmacogenetics aims to maximize benefits and minimize risks of drug treatment. Our objectives were to examine the influence of common variants of hepatic metabolism and transporter genes on the lipid-lowering response to statin therapy.

Methods and Results— The Genetic Effects On STATins (GEOSTAT-1) Study was a genetic substudy of Secondary Prevention of Acute Coronary Events—Reduction of Cholesterol to Key European Targets (SPACE ROCKET) (a randomized, controlled trial comparing 40 mg of simvastatin and 10 mg of rosuvastatin) that recruited 601 patients after myocardial infarction. We genotyped the following functional single nucleotide polymorphisms in the genes coding for the cytochrome P450 (CYP) metabolic enzymes, CYP2C9*2 (430C>T), CYP2C9*3 (1075A>C), CYP2C19*2 (681G>A), CYP3A5*1 (6986A>G), and hepatic influx and efflux transporters SLCO1B1 (521T>C) and breast cancer resistance protein (BCRP; 421C>A). We assessed 3-month LDL cholesterol levels and the proportion of patients reaching the current LDL cholesterol target of <70 mg/dL (<1.81 mmol/L). An enhanced response to rosuvastatin was seen for patients with variant genotypes of either CYP3A5 (P=0.006) or BCRP (P=0.010). Furthermore, multivariate logistic-regression analysis revealed that patients with at least 1 variant CYP3A5 and/or BCRP allele (n=186) were more likely to achieve the LDL cholesterol target (odds ratio: 2.289; 95% CI: 1.157, 4.527; P=0.017; rosuvastatin 54.0% to target vs simvastatin 33.7%). There were no differences for patients with variants of CYP2C9, CYP2C19, or SLCO1B1 in comparison with their respective wild types, nor were differential effects on statin response seen for patients with the most common genotypes for CYP3A5 and BCRP (n=415; odds ratio: 1.207; 95% CI: 0.768, 1.899; P=0.415).

Conclusion— The LDL cholesterol target was achieved more frequently for the 1 in 3 patients with CYP3A5 and/or BCRP variant genotypes when prescribed rosuvastatin 10 mg, compared with simvastatin 40 mg.

Clinical Trial Registration— URL: http://isrctn.org. Unique identifier: ISRCTN 89508434.

SOURCE:

Circulation: Cardiovascular Genetics.2010; 3: 276-285

Published online before print March 5, 2010,

doi: 10.1161/ CIRCGENETICS.109.898502


Comprehensive Whole-Genome and Candidate Gene Analysis for Response to Statin Therapy in the Treating to New Targets (TNT) Cohort

John F. Thompson, PhD, Craig L. Hyde, PhD, Linda S. Wood, MS, Sara A. Paciga, MA, David A. Hinds, PhD, David R. Cox, MD, PhD, G. Kees Hovingh, MD, PhD and John J.P. Kastelein, MD, PhD

Author Affiliations

From the Helicos BioSciences (J.F.T.), Cambridge, Mass; Molecular Medicine (J.F.T., L.S.W., S.A.P.) and Statistical Applications (C.L.H.), Pfizer Global Research and Development, Groton, Conn; Perlegen Sciences (D.A.H., D.R.C.), Mountain View, Calif; and Department of Vascular Medicine (G.K.H., J.J.P.K.), Academic Medical Center, Amsterdam, The Netherlands.

Correspondence to John J.P. Kastelein, MD, PhD, Department of Vascular Medicine, Academic Medical Center, Meibergdreef 9, Room F4-159.2, 1105 AZ Amsterdam, The Netherlands. E-mail j.j.kastelein@amc.uva.nl or j.s.jansen@amc.uva.nl

Abstract

Background— Statins are effective at lowering low-density lipoprotein cholesterol and reducing risk of cardiovascular disease, but variability in response is not well understood. To address this, 5745 individuals from the Treating to New Targets (TNT) trial were genotyped in a combination of a whole-genome and candidate gene approach to identify associations with response to atorvastatin treatment.

Methods and Results— A total of 291 988 single-nucleotide polymorphisms (SNPs) from 1984 individuals were analyzed for association with statin response, followed by genotyping top hits in 3761 additional individuals. None was significant at the whole-genome level in either the initial or follow-up test sets for association with low-density lipoprotein cholesterol, high-density lipoprotein cholesterol, or triglyceride response. In addition to the whole-genome platform, 23 candidate genes previously associated with statin response were analyzed in these 5745 individuals. Three SNPs in apoE were most highly associated with low-density lipoprotein cholesterol response, followed by 1 in PCSK9 with a similar effect size. At the candidate gene level, SNPs in HMGCR were also significant though the effect was less than with those in apoE and PCSK9. rs7412/apoE had the most significant association (P=6×10⁻³⁰), and its high significance in the whole-genome study (P=4×10⁻⁹) confirmed the suitability of this population for detecting effects. Age and gender were found to influence low-density lipoprotein cholesterol response to a similar extent as the most pronounced genetic effects.

Conclusions— Among SNPs tested with an allele frequency of at least 5%, only SNPs in apoE are found to influence statin response significantly. Less frequent variants in PCSK9 and smaller effect sizes in SNPs in HMGCR were also revealed.

SOURCE:

Circulation: Cardiovascular Genetics.2009; 2: 173-181

Published online before print February 12, 2009,

doi: 10.1161/ CIRCGENETICS.108.818062

Summary

Larry H. Bernstein, MD, FCAP

This review has examined a compendium of well regarded documents drawn from 248 articles in Circulation Cardiovascular Genetics from March 2010 to March 2013. The large amount of evidence obtained from large population studies identifying Genome Wide Analysis Studies (GWAS) examines a host of cardiac and vascular diseases in which there is association between specific single nucleotide peptides (SNPs), and gene loci, that may play or have no significant role in developing heart disease. It certainly is evidence of the role that the American Heart Association has is in supporting the leading research today for tomorrow’s patients.   It is too early to sort them out, but it speaks to a large volume of discovery in this area.

It raises another issue that we have been confronted with mostly since the second half of the 20th century.  What is that issue?  The issue, it appears to me, is the vast improvements in analytical technology so that “imprecision” is far less likely to be a confounder in biological measurements and this lends access to far better accuracy?  But from that question arises another! Accuracy only refers to what is measured, but does it give us better ability to explain a complex and dynamic process?  In other words, what is what we are looking at representative of in manageable events?   I think that this is the most important idea that should come out of the recent criticism of the trajectory that molecular genetics been on in the last 5 years.

It was still in an era that “BIG’ science was not the normal.  One could spend an enormous effort at stepwise purification of a protein or enzyme, or other biomolecule starting with a slurry made from 100 lbs of “chicken heart”, for example.  These separations were based on negative charges on the molecules and positive charges on the column, and the molecules of no interest were eluted by gradient elution.  Much was learned about large scale preparation from small scale trials.  But this work was not undertaken without the intent to carry out a number of investigations to understand the “functionality” of a link in a metabolic pathway.  The studies that followed the purification required kinetic investigation with a coenzyme, or with a synthetically modified coenzyme, amino acid sequencing, NMR studies, etc.  You could not put together a “mechanism” without having the minimum amount of necessary information for a reliable account.  It is probably this requirement that led to today’s “BIG” science, that is founded upon multiple methods, now large data bases, and teams of investigators across institutions and continents.  The acquisition of knowledge has been astounding, but the integration of knowledge has not caught up.

However, let’s see if we can sort out the most meaningful signals from what I too am beginning to call the “noisy channel”.  As often happens, important areas of research are opened up that are followed by significant discovery and, in the long run, many other dead end publications that have no lasting significance.  In order to do justice to the work, I’ll pick through documents I find interesting, keeping in mind there is a hidden layer of complexity of which only sufficient information leads to a better understanding.  As much literature calls attention to, much of what ails us has nothing to do with classical Mendelian genetics, and has a postgenomic component.

The most fascinating aspect of this is the withering “dark matter” of the genome. While that component may be silent or expressed, the understanding comes at a higher observed order.  The dark became light! The expression became subtle, like weak bond interactions. The underlying organization is a component of the adaptive ability of an organism or individual in an environment with plants and animals in a changing climate, at particular altitudes, with given water supplies, with disease vectors, and with endogenous sources of essential nutrients.  This brings into focus the regulatory role of the genome as just as important a factor as transmission of the genetic code, especially in somatic cell populations.

The remainder of this discussion deals specifically with my observations on cardiovascular genomics. The following conclusion is appropriate, if incomplete, at this time on circulating miRNAs, particularly miR-133a:

  • elevated levels of circulating miR-133a in patients with cardiovascular diseases originate mainly from the injured myocardium.
  • Circulating miR-133a can be used as a marker for cardiomyocyte death, and

A number of articles that cite this article suggest that it may be useful for following disease progression:
Plasma microRNAs serve as biomarkers of therapeutic efficacy and disease progression in hypertension-induced heart failure  Eur J Heart Fail  2013

MicroRNAs Within the Continuum of Postgenomics Biomarker Discovery Arterio. Thromb. Vasc. Bio. 2013;33:206-214

“Need for Rigor in Design, Reporting, and Interpretation of Transcriptomic Biomarker Studies”  J. Clin. Microbiol.. 2012;50:4192-4193

Circulating microRNAs as diagnostic biomarkers for cardiovascular diseases. Am. J. Physiol. Heart Circ. Physiol.. 2012;303:H1085-H1095,

Circulating MicroRNAs: Novel Biomarkers and Extracellular Communicators in Cardiovascular Disease? Circ. Res.. 2012;110:483-495

Circulating MicroRNAs: Biomarkers or Mediators of Cardiovascular Diseases?  Arterioscler. Thromb. Vasc. Bio. 2011;31:2383-2390,

Circulating MicroRNA-208b and MicroRNA-499 Reflect Myocardial Damage in Cardiovascular Disease MF Corsten, R Dennert, S Jochem, T Kuznetsova,  et al.

The finding refers to an association that is related to the appearance of a miRNA in the circulation of patients with acute cardiac ischemia, and particular released into the circulation of patients from injured myocardium.  This finding has to be distinguished from a finding of another miRNA released with acute injury.  In the case of miR499 (and miR208b), there is a comparison with plasma cTnT, and an ROC curve is produced.

The List of this follows:

Circulation: Cardiovascular Genetics 2010; 3: 499-506

Strikingly, in plasma from

  • acute myocardial infarction patients, cardiac myocyte–associated miR-208b and -499 were highly elevated, 1600-fold (P<0.005) and 100-fold (P<0.0005), respectively, as compared with control subjects. Receiver operating characteristic curve analysis revealed an area under the curve of 0.94 (P<10−10) for miR-208b and 0.92 (P<10−9) for miR-499. Both microRNAs correlated with plasma troponin T, indicating release of microRNAs from injured cardiomyocytes.
  • In patients with acute heart failure, only miR-499 was significantly elevated (2-fold), whereas
  • no significant changes in microRNAs studied could be observed in diastolic dysfunction.

Remarkably, plasma microRNA levels were not affected by a wide range of clinical confounders, including

  • age,
  • sex,
  • body mass index,
  • kidney function,
  • systolic blood pressure, and
  • white blood cell count.

This is miRNA with a different twist.  It appears that there are 3 types found in AMI (133a, 208b, 409).  But type 499 alone is increased with acute heart failure (no mention of chronic cardiomyopathy and no effect of estimated GFR, or of age).

If the problem was just of AMI, then we have to know what this brings to the table.  As it is the hs-troponins have yet to be shown to effectively not only increase the high sensitivity of the tests, but to decrease the confusion generated by the elevation.  The enormous improvement of a test that may be superior to the hs-ctn’s is for the patient with very indeterminiate shortness of breath, a nondefinitive ECG, and in a prodromal phase of AMI.  This happened in the past, and it may happen now, and it may account for many cases of silent MI that were found at autopsy.

Cited by
Plasma microRNAs serve as biomarkers of therapeutic efficacy and disease progression in hypertension-induced heart failure Eur J Heart Fail. 2013;0:hft018v1-hft018,
Circulating microRNAs as diagnostic biomarkers for cardiovascular diseases Am. J. Physiol. Heart Circ. Physiol.. 2012;303:H1085-H1095,

Circulation Editors’ Picks: Most Read Articles in Cardiovascular Genetics Circulation. 2012;126:e163-e169,
MicroRNAs in Patients on Chronic Hemodialysis (MINOS Study) CJASN. 2012;7:619-623,

Novel techniques and targets in cardiovascular microRNA research Cardiovasc Res. 2012;93:545-554,

Microparticles: major transport vehicles for distinct microRNAs in circulation Cardiovasc Res. 2012;93:633-644,

Profiling of circulating microRNAs: from single biomarkers to re-wired networks Cardiovasc Res. 2012;93:555-562,

Small but smart–microRNAs in the centre of inflammatory processes during cardiovascular diseases, the metabolic syndrome, and ageing   Cardiovasc Res. 2012;93:605-613,

Circulation: Heart Failure Editors’ Picks: Most Important Papers in Pathophysiology and Genetics Circ Heart Fail. 2012;5:e32-e49

Use of Circulating MicroRNAs to Diagnose Acute Myocardial Infarction   Clin. Chem. 2012;58:559-567,

Circulating microRNAs to identify human heart failure   Eur J Heart Fail. 2012;14:118-119,

Next Steps in Cardiovascular Disease Genomic Research–Sequencing, Epigenetics, and Transcriptomics  Clin. Chem. 2012;58:113-126,

Most Read in Cardiovascular Genetics on Biomarkers, Inherited Cardiomyopathies and Arrhythmias, Metabolomics, and Genomics Circ Cardiovasc Genet. 2011;4:e24-e30,

MicroRNA-126 modulates endothelial SDF-1 expression and mobilization of Sca-1+/Lin- progenitor cells in ischaemia  Cardiovasc Res. 2011;92:449-455,

The use of genomics for treatment is another matter, and has several factors, e.g., age, residual function after AMI, comorbidities

This is a lot of interesting work that opens as many questions as it answers. The observations are real, and they lead to questions relating to the heart and the circulation.  Maybe it will generate answers to very tough issues concerning hypertension, renal disease and the heart.  It is far too early to tell.  It appears that we are about to hear a cacophony of miR’s in a symphony on cardiac and circulatory diseases not be be pieced together soon. But we have many more tools at our disposal than we did when Karmen discovered and made a distinction between

  • Aspartate and Alanine aminotransferases in the late 1950s, followed in the 1960s by
  • Creatine phosphokinase, the
  • MB-isoenzyme of CK by Sobel, Shell and Kjeckshus,
  • isoenzyme-1 of lactate dehydrogenase, and later the
  • Troponins,

leading to the programs to “reduce the extent of infarct damage”.  Then came the

  • a- and b-type natriuretic peptides,

which are still not fully understood in their role in congestive heart failure and in renal disease.

One item strikes the imagination as a fruitful area of further study.   Genetic Determinants of Potassium Sensitivity and Hypertension.    Integrated Computational and Experimental Analysis of the Neuroendocrine Transcriptome in Genetic Hypertension Identifies Novel Control Points for the Cardiometabolic Syndrome

Essential hypertension, a common complex disease, displays substantial genetic influence. Contemporary methods to dissect the genetic basis of complex diseases such as the genomewide association study are powerful, yet a large gap exists betweens the fraction of population trait variance explained by such associations and total disease heritability.

The researchers

  • developed a novel, integrative method (combining animal models, transcriptomics, bioinformatics, molecular biology, and trait-extreme phenotypes)
  • to identify candidate genes for essential hypertension and the metabolic syndrome.

Method  …  transcriptome profiling on adrenal glands from blood pressure extreme mouse strains:

  1. the hypertensive BPH (blood pressure high) and
  2. hypotensive BPL (blood pressure low).

Results….   Microarray data clustering revealed

  • underexpression of intermediary metabolism transcripts in HIGH BLOOD PRESSURE.
  • The MITRA algorithm identified a conserved motif in the transcriptional regulatory regions of the underexpressed metabolic genes,
  • They decide that regulation through this motif contributed to the global underexpression.
  • Luciferase reporter assays demonstrated transcriptional activity of the motif through transcription factors
    • HOXA3,
    • SRY, and
    •  YY1.

They finally hypothesized that genetic variation at HOXA3, SRY, and YY1 might predict blood pressure and other metabolic syndrome traits in humans. Tagging variants for each locus were associated with

  • blood pressure in a human population blood pressure extreme sample with
  • the most extensive associations for YY1 tagging single nucleotide polymorphism rs11625658 on
  1. systolic blood pressure,
  2. diastolic blood pressure,
  3. body mass index, and
  4. fasting glucose.

Meta-analysis extended the YY1 results into 2 additional large population samples with significant effects preserved on diastolic blood pressure, body mass index, and fasting glucose.

It will take much more of this beautiful integrative work to open up our imagination as to what physiological processes are occurring.

Read Full Post »

When Clinical Application of miRNAs?

Author: Larry H Bernstein, MD, FCAP

Clinical Application of miRNAs Remains a Ways Off
When its time comes, prognostic tests will be first.
Patricia Fitzpatrick Dimond, Ph.D             GEN Insight & Intelligence

It’s still early to tell how well microRNAs (miRNAs) will prove clinically useful.  Preclinical research findings indicate their central role in controlling cellular pathways.
This novel class of nucleotides, about 20–25 nucleotides in length, affects gene expression by interacting with messenger RNAs. But unlike Small Interfering RNA,  siRNAs, miRNAs are encoded in the human genome and function as natural regulators of global gene expression.
Each of the more than 1,500 encoded miRNAs appears to regulate the expression of tens to hundreds of different genes, on-off switches, regulating multiple cellular functions including
  • growth and
  • proliferation.
miRNAs regulate the translation of genes through
  • sequence-specific binding to mRNA.

Depending on the degree of sequence complimentarity, they can inhibit

  • the translation and/or degradation of their target mRNAs.

Because of their role in controlling “suites” of genes and, ultimately, pathway function, these molecules have attracted considerable scientific and investor interest in the control of diseases ranging from cardiovascular diseases to cancer.

miRNAs target numerous biomolecules that play a role in carcinogenesis,
  • functioning as both tumor promoters or suppressors.
Aberrant expression of miRNAs
  • correlates with the development and progression of tumors;

inhibition of their expression can

  1. modulate the cancer phenotype,
  2. suggesting their potential as anticancer drug targets.

Further supporting their potential use as drug targets, miRNA expression profiling in a variety of tissue, cell, and disease types has revealed

  • a “miRNA signature” specific to those cell types or disease states.
Research

Carlo Croce, M.D., director of Human Cancer Genetics at the Ohio State University Comprehensive Cancer Center, and colleagues reported that

  • they identified a 9-miRNA signature that differentiated invasive (IDC) from in situ carcinoma (DCIS).

In studying the global changes of the miRNA repertoire along the transitions defining breast cancer progression, the scientists found that

  1. let-7d, miR-210, and miR-221 were downregulated in the in situ and
  2. upregulated in the invasive transition, thus
  3. featuring an expression reversal along the cancer progression path.
  4. in addition,  miRNAs for overall survival and time to metastasis.
Dr. Croce posed that targeted prognostic tests using miRNA will be available within the next two years.
  • the problem he suggests is validating the signature in a large enough cohort of patients.
They used deep sequencing, an extremely sensitive approach to the determination of miRNAs because you count the molecules. Studies have used microarrays and RT-PCR, and his group used general microarrays and validated RT-PCR.  Their method avoided the possibility of artifacts (by counting).  Sequencing permits counts of molecules to provide good data.

John F. McDonald, Ph.D., CSO Ovarian Cancer Institute, and colleagues at the Georgia Institute of Technology

  1. separately transfected two miRNAs (miR-7 and miR-128) into the ovarian cancer cell line (HEY) and
  2. then monitored global changes in gene expression levels.
  • 20% of the changes in expression patterns of hundreds to thousands of genes
  • could be attributed to direct miRNA–mRNA interactions, but
  • the majority of the changes were indirect,
involving the downstream consequences of miRNA-mediated changes in regulatory gene expression.
The pathways most significantly affected by miR-7 transfection, are involved with
  1. cell adhesion and
  2. developmental networks previously associated with epithelial-mesenchymal transitions and
  3. processes linked with metastasis.

http://www.genengnews.com/insight-and-intelligenceand153/clinical-application-of-mirnas-remains-a-ways-off/77899650/

ATVB in Focus
MicroRNAs 
From Basic Mechanisms to Clinical Application in Cardiovascular Medicine
Christian Weber, Ludwig-Maximilians-Univ and German Centre for Cardiovasc Res, Munich, Germany
Arterioscler Thromb Vasc Biol. 2013;33:168-169.  http://dx.doi.org/10.1161/ATVBAHA.112.300920
MicroRNAs (miRs) are small noncoding RNAs (≈23 nucleotides) that regulate gene expression at a posttranscriptional level by degradation or translational inhibition of target mRNAs. Initially discovered as regulators of development in plants, worms, and fruitflies,
miRs are emerging as
  • pivotal modulators of cardiovascular biology and disease in mice and men.
Besides a cell-specific transcription factor profile,
  • cell-specific miR-regulated gene expression is integral to cell fate and activation decisions.
Thus, the cell types involved in
  • atherosclerosis,
  • vascular disease, and
    • its myocardial sequelae may be
  • differentially regulated by distinct miRs, thereby
    • controlling highly complex processes
      • smooth muscle cell phenotype and
      • inflammatory responses of endothelial cells or macrophages.
The generation of mature miR strands requires several steps of processing of the primary miR gene transcript, including
  • cleavage of the terminal loop of miR-precursors by the RNase III enzyme,Dicer, to produce miR duplexes.
Although either strand of the miR duplex can be stably associated with an Argonaute (Ago) family protein,
  • preferential loading of a specific strand (ie, the guide strand) onto the miR-induced silencing complex (RISC) is common.
The strand that is not loaded into the RISC (ie, the passenger strand or miR*) is typically degraded.3 Strand selection may be tissue-specific, and an accumulation observed for both strands implies that
  • each strand can separately enter the silencing complex.4
Because of the often imperfect complementary binding of the miR seed sequence to the mRNA recognition element,
  • an individual miR can affect the expression of hundreds of target mRNAs.
http://atvb.ahajournals.org/content/33/2/168.extract

Life’s Tiniest Architects Pinpointed by Yale Researchers
If a genome is the blueprint for life, then the chief architects are
  • tiny slices of genetic material that orchestrate how we are assembled and function.
The study pinpoints the molecular regulators of epigenetics — the process by which unchanging genes along our DNA are switched on and off at precisely right time and place.
“Our genome is like a landscape with lakes, mountains, and rivers, but it is not yet a community or a city full of buildings,” said Haifan Lin, director of the Yale Stem Cell Center and senior author of the study. “What this system does is decide where and when to send out the masons, carpenters, and electricians to build a city or a community.”
In the past 20 years, scientists have discovered that some proteins, called epigenetic factors, traverse the static genome and turn the genes on or off. The staggering number of potential combinations of active and inactive genes explains why a relatively small number of genes can carry out such a wide range of functions.
What guides these epigenetic factors to their target? The answer:

  • specialized RNAs called piRNAs.
In the latest study, the Yale team discovered that
  • piRNAs guide epigenetic factors to numerous sites throughout the genome of the fruit fly Drosophila, where
    • these switches  work to turn genes on or off.
The dramatic change in gene expression patterns found illustrated
  • piRNAs key role in coordinating biological activity.
“This is the first major mechanism discovered that controls where epigenetic factors —the gene switches — are to be placed in the genome,” Lin said.
Several types of cancers appeared to be
  • triggered when the wrong kinds of piRNAs guide epigenetic factors to activate the wrong genes.
Blocking the action of these piRNAs should become a new opportunity to treat cancers, Lin said.
Xiao A. Huang and Hang Yin of Yale are co-lead authors of the paper.
The research was funded by a National Institutes of Health Pioneer Award to Haifan Lin and a grant from Connecticut Stem Cell Research Fund to
Lin and former Yale professor and co-author Michael Snyder, now of Stanford University.
English: A diagram showing at which stages in ...

English: A diagram showing at which stages in the DNA-mRNA-protein pathway expression can be controlled. (Photo credit: Wikipedia)

Virus-Encoded microRNAs

Virus-Encoded microRNAs (Photo credit: AJC1)

English: A Tet-ON doxycycline inducible transg...

English: A Tet-ON doxycycline inducible transgene expression system. (Photo credit: Wikipedia)


Read Full Post »

The Promise of Personalized Medicine

Reporter: Larry H Bernstein, MD, FCAP


 Realizing the Promise of Personalized Medicine

Harvard Business Review
MG Aspinal, RG Hamermesh
Obsolete business models, regulations, reimbursement systems, and physicians stand in the way
NewYear for Angels

NewYear for Angels (Photo credit: Wikipedia)

BusinessModel

BusinessModel (Photo credit: Wikipedia)


Read Full Post »

Attitudes of Patients about Personalized Medicine

Curator: Larry H Bernstein, MD, FCAP

Attitudes of Patients With Cancer About Personalized Medicine

SW Gray, K Hicks-Courant, et al.
Personalized Medicine

Personalized Medicine (Photo credit: Wikipedia)

Related articles

Read Full Post »

Understanding the Role of Personalized Medicine

Reporter: Larry H. Bernstein, MD, FCAP


Do Patients Understand the Role of Cancer Genetic Testing?

Maurie Markman, MD
Personalized Medicine

Personalized Medicine (Photo credit: Wikipedia)


Read Full Post »

English: Amino acid sequence of the molecule o...

English: Amino acid sequence of the molecule of the brain natriuretic peptide (BNP) 32 (functional). Português: Sequência de aminoácidos da molécula de BNP 32 (funcional). (Photo credit: Wikipedia)

Assessing Cardiovascular Disease with Biomarker

Author and Curator: Larry H Bernstein, MD, FCAP


A Changing expectation from cardiac biomarkers.

This article on Assessing Cardiovascular Disease with Biomarkers will demonstrate the unique role in the discipline evolution that each of the following biomarkers has played in our understanding of CVD risk:

The article is introduced with an entire section on the evolution of our knowledge of cardiac biomarkers and how concepts from thermodynamics have transformed
the way we investigate biochemical mechanisms, and how we have gone from a macro- to a micro- landscape of high complexity.  The same concepts from physics
have also transformed the mathematical stage upon which we model data.  BIG Data is not just about business!  We have entered a new domain of knowledge enabling.

(1)  Enzymes and Isoenzymes

  • AST, ALT, LD, alkaline phosphatase
  • Isoenzymes evolution and genomic loci for polypeptides
  • Emergence of pathway divergence and regulation from gene-loci peptide changes
  • A reflection to implications for biomarkers and therapeutic development based on critical links

(2)  Natriuretic Peptides

  •       Cause of Death: silent cardiac target organ damage (cTOD) (no so sign of cardiac disease)
  •       B Type natriuretic peptide in evolution of CHF
  •       2D and Doppler echocardiography and BNP serum level
  •       Amino terminal pro B-type Natriuretic Peptide
  •       Renal Effect on NT-proBNP
  •       pro-atrial natriuretic peptide

(3)     CRP as Biomarker, theory that lowering the C-reactive protein (CRP) level with statin therapy is predictive of cardiovascular outcomes independent of lowering the low-density lipoprotein (LDL) cholesterol level

(4)     CRP as an Inflammatory Agent

Acute phase reaction is a systemic response: physiological condition  in the beginning of an inflammatory process.

(5)     troponins and hs-troponins (I, T)

(6)     New Candidate  Biomarkers for NSTEMI

(7)    Guidelines for Cardiovascular Risk Assessment

(8)     Statistical Issues to be Resolved

Historical perspective

The use of cardiac markers emerged in the late 1950s, when the physician was faced with the problem of a patient with recent onset of squeezing, crushing, or heaviness in the chest, with or without a Q-wave or definitive ST elevation (acute injury), and perhaps a non specific elevation of the neutrophil count.   A medical student at Albert Einstein Medical school at the time, Arthur Karmen identified the first enzymatic test for acute myocardial infarct (MI), serum glutamic oxaloacetic acid transaminase (SGOT), which is renamed Aspartate Aminotransferase (AST) in a seminal study with Wroblewski and LaDue[1].  The enzyme is ubiquitous, and the authors published another observation that the SGPT, now referred to as Alanine Aminotransferase, has a greater specific activity in liver and myocardial infarct can be distinguished from necrotizing liver disease by using AST and ALT.  These two enzymes were among the three enzymes,with lactate dehydrogenase (LD) and alkaline phosphatase that appeared on the original Technicon (later Siemens) SMA-12 profile, prior to the designated panels used today.  At that time it was common for the pathologist to stain the heart lesion at autopsy in identifying the “ischemic necrosis” postmortem.

In 1957 Hunter and Markert described the five isoenzymes of lactate dehydrogenase, the most anodal migrating pattern was associated with heart and the most cathodal isoenzymes with liver, the five bands being combinations of two subunits.  These were described as different variants of the same enzyme having identical functions, but different tissue specific patterns, such that,  enzyme variants have altered gene loci that results in an amino acid change but catalyze the same reaction.  When mutation modifies the enzymatic catalysis, or its pattern of gene expression, then any of two (or more) variants may be favoured by natural selection and become specialized to different cell environments.  His group suggested that a single gene might somehow encode an array of isozymes differing in “structural variations,” a concept that seems to presage our current understanding of alternative mRNA splicing and post-translational protein modification. A former student of George beadle, he transformed the “concept of one gene one enzyme”  to “one gene one polypeptide”. By treating the enzyme with denaturing agents it was learned that LDH is a tetramer of two types of polypeptide chains (Appella and Markert, 1961). Thus the multiple-gene hypothesis was partially correct: Two different LDH subunits, each encoded by a distinct gene, re-sort themselves in various tetrameric combinations to give rise to five different isozymes (Markert, 1963). During the succeeding years Markert and his students and postdocs elucidated how the study of isozymes could contribute to our understanding of the biochemical variation that underlies cell differentiation and evolution, culminating in the new perspective presented in a Science paper (Markert et al., 1975) entitled “Evolution of a Gene.”

In the early 1960’s Nathan Kaplan postulated that the major LD-isoenzyme types were associated with fundamental differences in the metabolism of the tissue of origin, either catabolic (heart) or anabolic (liver), and skeletal muscle would appear to be in the same class as liver (ignore the ratio of fast and slow twitch), which was elaborated on further by studies of the flight wing patterns of birds.   These isoenzymes not only had different migration in an electrophoretic field and could be separated chromatographically, but they also had different kinetic properties. They all have the same Km, but the purified heart LD is inhibited by a ternary complex of the enzyme, the NAD, and pyruvate that forms, slowing the reaction in the forward direction (pyruvate to lactate).

At about the same time, Masahiro Chiga discovered that adenylate kinase, the enzyme that converts ATP to ADP, from skeletal muscle can be inhibited by inorganic S (myokinase), which led Bernstein and Russell to publish on the identification of adenylate kinase from heart in myocardial infarction using sulfhydryl inhibition in J Molec Cellular Cardiology.  Burton Sobel in the early 1970s showed that CK and the MB isoenzyme of CK, which has a more rapid increase and disappearance than the AST or LD ,  could be used to estimate the amount of cardiac damage in MI.   This meant that a test could be done at any time of day or night with a result in less than an hour.  He applied this to determining whether the extent of infarction was an important determinant of prognosis after myocardial infarction and furthermore, whether the extent of infarction could be modified by interventions that reduce myocardial oxygen requirements or increase myocardial oxygen supply. This work has had a major impact on how patients with acute myocardial infarction are treated and led to a reduction of mortality secondary to treatments, such as thrombolysis, that were validated initially with the methods developed. This led to an immunoassay for CK isoenzyme MB that was offered by Roche on the Cobas analyzer, and by Dupont on the ‘aca’. What emerged is a new imperative to reduce infarct size under the rubrick – “Time is Muscle”.

References

  1. Karmen Arthur, Wróblewski Felix, LaDue John S. TRANSAMINASE ACTIVITY IN HUMAN BLOOD. J Clin Invest. 1955; 34(1):126–133.
  2. LADUE JS, WROBLEWSKI F, KARMEN A. Serum glutamic oxaloacetic transaminase activity in human acute transmural myocardial infarction. Science 1956; 75(11).
  3. Hunter, R. L. and C.L. Merkert. (1957) Histochemical demonstration of enzymes separated by zone electrophoresis in starch gels. Science 125: 1294-1295.
  4. Bernstein L, Kerrigan M, Maisel H. Lactic dehydrogenase isoenzymes in lens and cornea. Exp Eye Res 1965; 5(3):999-1005. ICID: 844979
  5. Nathan O. Kaplan Papers. MSS 0099. UC San Diego::Mandeville Special Collections Library.

Enzyme-coenzyme-substrate complex. of pyridine nucleotide depend. dehydrogenases 1958.  box 39, folder 5.
Enzymatic studies with analogues of diphosphopyridine nucleotide 1959. box 39, folder 12.
Heterogeneity of the lactic dehydrogenases of new-born and adult rat heart as determined with enzyme analogs 1961. box 39, folder 37.
Regulatory effects of enzyme action 1961. box 39, folder 38.
Inhibition of dehydrogenase reactions by a substance formed from reduced dpn 1961. box 39, folder 40.
Lactic dehydrogenases: functions of the two types 1964. box 39, folder 67.
Lactate dehydrogenase – structure and function. 1964. box 40, folder 4.
Role of the two types of lactic dehydrogenases 1964. Box 40, folder 9.
Structural and functional properties of h and m subunits of lactic dehydrogenase 1965. Box 40, folder 12.

  • Bernstein LH, Everse J, Shioura N, Russell PJ. Detection of cardiac damage using a steady state assay for lactate dehydrogenase isoenzymes in serum. J Mol Cell Cardiol 1974; 6(4):297-315. ICID: 825597
  • Bernstein LH, Everse J.  Determination of the isoenzyme levels of lactate dehydrogenase. Methods Enzymol 1975; 41 47-52.
  • Bernstein LH. Automated kinetic determination of lactate dehydrogenase isoenzymes in serum. Clin Chem 1977; 23(10):1928-1930. ICID: 825616
  • Bernstein LH, Scinto P. Two methods compared for measuring LD-1/total LD activity in serum. Clin Chem 1986; 32(5):792-796. ICID: 825581
  1. Shell WE, Kjekshus JK, Sobel BE: Quantitative assessment of the extent of myocardial infarction in the conscious dog by means of analysis of serial changes in serum creatine phosphokinase activity. J Clin Invest 50:2614-2626, 1971.
  2. Bergmann SR, Fox KAA, Ter-Pogossian MM, Sobel BE (Washington University), Collen D (University of Leuven): Clot-selective coronary thrombolysis with tissue-type plasminogen activator. Science 220:1181-1183, 1983.
  3. Van de Werf F, Ludbrook PA, Bergmann SR, Tiefenbrunn AJ, Fox KAA, de Geest H, Verstraete M, Collen D, Sobel BE: Coronary thrombolysis with tissue-type plasminogen activator in patients with evolving myocardial infarction. N Engl J Med 310:609-613, 1984.
  • Adan J, Bernstein LH, Babb J. Can peak CK-MB segregate patients with acute myocardial infarction into different outcome classes?  Clin Chem 1985; 31(2):996-997. ICID: 844986
  • Bernstein LH, Reynoso G.  Creatine kinase B-subunit activity in serum in cases of suspected myocardial infarction: a prediction model based on the slope of MB increase and percentage CK-MB activity. Clin Chem 1983; 29(3):590-592. ICID: 825549
  • Bernstein LH, Horenstein JM, Sybers HB, Russell PJ.  Adenylate kinase in human tissue. II. Serum adenylate kinase and myocardial infarction. J Mol Cell Cardiol 1973; 5(1):71-85. ICID: 825590

A Metabolic Functional Meaning of Existence of Isoenzymes

There are many examples of  isozymes, such as glucokinase, a variant of hexokinase which is not inhibited by glucose 6-phosphate. It has different regulatory features and lower affinity for glucose (compared to other hexokinases). Alkaline and acid phosphatase isoenzymes were used briefly for a time in clinical diagnostics.  These isoenzymes are oligomeric proteins that have distinct subunits that affect their binding with substrate.  A distinctive type of protein that can form two or more different homo-oligomers, comes apart and changes shape to convert between forms is called a morpheein. The alternate shape may reassemble to a different oligomer, and the shape of the subunit dictates which oligomer is formed. Morpheeins can interconvert between forms under physiological conditions and can exist as an equilibrium of different oligomers. Features of morpheeins can be exploited for drug discovery. A small molecule compound can shift the equilibrium either by blocking or favoring formation of one of the oligomers. The equilibrium can be shifted using a small molecule that has a preferential binding affinity for only one of the alternate morpheein forms. This introduces the concept of allostericity.  Most allosteric effects can be explained by a model put forth by Monod, Wyman, and Changeux, and also by a model described by Koshland, Nemethy, and Filmer. Both postulate that enzyme subunits exist in one of two conformations, tensed (T) or relaxed (R), and that relaxed subunits bind substrate more readily than those in the tense state.  This concept provides a foundation for another generation of biomarkers than was the focus of the 20th century, and only has been investigated since the 1980’s, and takes another dimension after the completion of the Human Genome Project, opening a “Pandora’s box”. This moved biomedical science forward into an emerging field of ‘OMICs’, which tied small molecules into regulatory processes, transcription, and the possibility of identifying new biomarkers and developing new biomolecules that could modify disease progression.

References

  1. Bu Z, Callaway DJ. “Proteins MOVE! Protein dynamics and long-range allostery in cell signaling”. Adv in Protein Chemistry and Structural Biology 2011; 83: 163–221. doi:10.1016/B978-0-12-381262-9.00005-7. PMID 21570668.
  2.  Monod J, Wyman J, Changeux JP. On the nature of allosteric transitions:A plausible model. J Mol Biol, May 1965; 12:88-118.
  3.   Koshland DE, Némethy G, Filmer D. Comparison of experimental binding data and theoretical models in proteins containing subunits. Biochemistry. Jan 1966; 5(1):365-8
  4.  Jaffe EK. “Morpheeins – a new structural paradigm for allosteric regulation”. Trends Biochem Sci 2005; 30(9): 490–497. doi:10.1016/j.tibs.2005.07.003. PMID 16023348.
  5.  Huang Z, Zhu L, Cao Y, Wu G, Liu X, et al.  ASD: a comprehensive database of allosteric proteins and modulators. Nucleic Acids Res 2011; 39: D663-669

Fundamental Transformative Concepts Carried Over from Physics to Biomolecular Processes.

A colleague once noted that we are learning more and more about less and less.  This is the remarkable evolution of our thinking from macrostates to microstates and segmentation of processes, further leading us to exploration of interactions between states.  This has required a breakdown and a repeated remodeling or resynthesis of ideas based on new findings in science.  It has gradually driven medicial science to a greater dependence on chemistry and physics in underlying principle.  We can better envision the mechanism of evolution from the concepts put forth.

In 1824 Sadi Carnot published the concept that heat is lost in the conversion into work, using the term “caloric”, equivalent to entropy in the second law of thermodynamics.  Clausius then develops the concepts of interior work in 1854, i.e. that “which the atoms of the body exert upon each other”, and exterior work, i.e. that “which arise from foreign influences [to] which the body may be exposed”, anticipating the concept of entropy. He enunciated the passage of the quantity of heat Q from the temperature T1 to the temperature T2 has the equivalence-value entropy, symbolized by S :  dS = Q (1/T2 – 1/T1), which led to his 1865 statement on irreversible heat loss: I propose to name the quantity S the entropy of the system, after the Greek word [τροπη trope], the transformation. I have deliberately chosen the word entropy to be as similar as possible to the word energy.”  In 1876, physicist J. Willard Gibbs, building on the work of Clausius, Hermann von Helmholtz and others, proposed that the measurement of “available energy” ΔG in a thermodynamic system could be mathematically accounted for by subtracting the “energy loss” TΔS from total energy change of the system ΔH, and in 1877, Ludwig Boltzmann formulated the alternative definition of entropy S defined as:

S = kBlnΩ

where

kB is Boltzmann’s constant and

Ω is the number of microstates consistent with the given macrostate.

An analog to thermodynamic entropy is information entropy. Claude Shannon set out to mathematically quantify the statistical nature of “lost information” in phone-line signals  and developed  a concept of information entropy, a fundamental cornerstone of information theory. The close similarity between his new quantity and earlier work in thermodynamics is attributed to a visit and discussion with Jon von Neumann in 1949. Shannon then called the “measure of uncertainty” or attenuation in phone-line signals with reference to his new information theory.  This led to the elucidation of a signal (as opposed to noise, by Solomon Kullback, which became the basis for the measure of an optimum diagnostic decision point of a laboratory test by Bernstein and Rudolph, related to Eugene Rypka’s “Syndromic Clustering”.  The loop was closed by the Japanese mathematician Akaike, who brought Fisher’s statistical formulations and Kullback-Liebler distance into alignment.   This is not a digression because it has been central to underlying principles in resolution in spectroscopy, and to classification of biochemical molecular features.

Although Boltzmann first linked entropy and probability in 1877, it seems the relation was never expressed with a specific constant until Max Planck first introduced k, and gave an accurate value for it (1.346×10⁻²³ J/K, about 2.5% lower than today’s figure), in his derivation of the law of black body radiation in 1900–1901. Before 1900, equations involving Boltzmann factors were not written using the energies per molecule and the Boltzmann constant, but rather using a form of the gas constant R, and macroscopic energies for macroscopic quantities of the substance. The iconic terse form of the equation S = k log W on Boltzmann’s tombstone is in fact due to Planck, not Boltzmann. Planck actually introduced it in the same work as his h. Planck noted in his 1920 Nobel Prize acceptance : “:This constant is often referred to as Boltzmann’s constant, although, to my knowledge, Boltzmann himself never introduced it — a peculiar state of affairs.”  The Kullback–Leibler divergence (also information divergence, information gain, relative entropy, or KLIC) is a non-symmetric measure of the difference between two probability distributions P and Q, was  introduced by Solomon Kullback and Richard Leibler in 1951. KL-divergence of a model from reality may be estimated, to within a constant additive term, by a function (like the squares summed) of the deviations observed between data and the model’s predictions. When trying to fit parametrized models to data there are various estimators which attempt to minimize Kullback–Leibler divergence, such as, the familiar maximum likelihood  estimator.

References

  1. Planck, Max (2 June 1920), The Genesis and Present State of Development of the Quantum Theory (Nobel Lecture)
  2. Kalinin M, Kononogov S. “Boltzmann’s Constant, the Energy Meaning of Temperature, and Thermodynamic Irreversibility”, Measurement Techniques 2005; 48 (7): 632–36, doi:10.1007/s11018-005-0195-9
  3. Kullback S, Leibler RA “On Information and Sufficiency”. Annals of Mathematical Statistics 1951; 22 (1): 79–86. doi:10.1214/aoms/1177729694. MR 39968.
  4. Kullback S (1959) Information theory and statistics (John Wiley and Sons, NY).
  5. Jaynes ET(1957) Information theory and statistical mechanics, Physical Review 106:620
  6. Jaynes ET(1957) Information theory and statistical mechanics II, Physical Review 108:171
  7. Burnham KP and Anderson DR. (2002) Model Selection and Multimodel Inference: A Practical Information-Theoretic Approach, Second Edition (Springer Science, New York) ISBN 978-0-387-95364-9.
  8. Rudolph RA, Bernstein LH, Babb J.  Information induction for predicting acute myocardial infarction. Clin Chem 1988; 34(10):2031-2038. ICID: 825568

A New Imperative

Cardiovascular Biomarkers

I. BNP:

[A] Aids in the Prevention of Cardiac Events by Detecting Silent Ischemic Lesions and Selecting Patients for Imaging

12/17/12 · Emily Humphreys

Physicians use risk factors, such as history, exercise level, diabetes, blood pressure, lipid profiles, and other laboratory measurements to ascertain risk for cardiac events, which are not foolproof in predicting all cardiac events. Nonetheless, 40% to 50% of sudden cardiac deaths (SCD) occur before risk factors are able to predict cardiac events.2,3 Those who die suddenly with no so sign of cardiac disease often have silent cardiac target organ damage (cTOD).  While patients with silent ischemia have a 21-fold increase in risk of a coronary event.4 It has also been shown that cTODs such as left ventricular hypertrophy (LVH), left ventricular systolic dysfunction (LVSD), left ventricular diastolic dysfunction (LVDD), and left atrial enlargement (LAE) each independently predict cardiovascular events. 5,6,7,8 Nadir et al. hypothesized that identification of silent cTOD would aid in the prevention of cardiovascular events, including SCDs.9 To identify cTOD present, The Nadir group evaluated several known cardiac biomarkers including: B-type natriuretic peptide (BNP), high-sensitivity cardiac troponin T (hs-cTnT), microalbuminuria, the estimated glomerular filtration rate, and uric acid.  The lab results of 300 asymptomatic individuals recruited for the study were compared with primary screening using transthoracic echocardiography, stress echocardiography, and/or myocardial perfusion imaging.
  • 34% of study volunteers had evidence of a cTOD. Out of all biomarkers analyzed, BNP levels were significantly higher in those with cTOD compared with those without. BNP levels were also higher in those who had more than one form of cTOD compared with those who had a single form of cTOD.
  • Hs-cTnT also performed well, but BNP levels had the highest correlation to imaging data. The gold standard diagnostic tool for cardiovascular disease is imaging studies, such as echocardiography.
  • It is not standard practice to investigate healthy individuals for possible cTOD and would be costly and time consuming to perform imaging on these individuals.
  • Biomarkers like BNP could be used as a primary screening tool with follow-up image studies performed, if necessary.

The eventual hope is to reduce the mortality of cardiovascular diseases and prevent silent cTOD from leading to more serious and potentially life-threatening cardiac events.

References

1. Roger, V.L. (2012) ‘AHA statistical update: Heart disease and stroke statistics-2012 update. A report from the american heart association‘, Circulation, 125 (2012), (pp. e2-e220)

2. Chiuve, S.E., et al., (2006) ‘Healthy lifestyle factors in the primary prevention of coronary heart disease among men: Benefits among users and nonusers of lipid-lowering and antihypertensive medications‘ Circulation, 114 (2006), (pp. 160-167)

3.De Vreede-Swagemakers, J.J., et al. (1997) ‘Out-of-hospital cardiac arrest in the 1990s: A population-based study in the Maastricht area on incidence, characteristics and survival‘, Journal of the American College of Cardiology, 30 (1997), (pp. 1500-1505)

4. Rutter, M.K., et al. (2002) ‘Significance of silent ischemia and microalbuminuria in predicting coronary events in asymptomatic patients with type 2 diabetes‘, Journal of the American College of Cardiology, 40 (2002), (pp. 56-61)

5. Tsang, T.S., et al. (2003) ‘Prediction of risk for first age-related cardiovascular events in an elderly population: The incremental value of echocardiography‘, Journal of the American College of Cardiology, 42 (2003), (pp. 1199-1205)

6. Gosse, P., (2005) ‘Left ventricular hypertrophy—the problem and possible solutions‘,The Journal of International Medical Research, 33 (Suppl 1) (2005), (pp. 3A-11A)

7. Benjamin, E.J., et al. (1995) ‘Left atrial size and the risk of stroke and death‘ The Framingham Heart Study Circulation, 92 (4), (pp. 835-41)

8. Redfield, M.M., et al. (2003) ‘Burden of systolic and diastolic ventricular dysfunction in the community: Appreciating the scope of the heart failure epidemic‘, JAMA, 289 (2003), (pp. 194-202)

9. Nadir, M.A., et al., (2012) ‘Improving the primary prevention of cardiovascular events by using biomarkers to identify individuals with silent heart disease‘, Journal of American College of Cardiology, 60 (11), (pp. 960-968) Tags: , , , 

[B] Evaluating CHF patients in the emergency department

The role of B-type natriuretic peptide in the evaluation of congestive heart failure patients in emergency department

Congestive heart failure (CHF) is a severe cardiovascular disorder seen in the Emergency Department (ED). B-type Natriuretic Peptide (BNP) is usually ordered to evaluate the CHF severity.

However, it is difficult to interpret serum BNP level when different clinical entities existed.

The aim of this study is to illustrate the correlation between serum BNP level and

  • relevant clinical variables and
  • further determine the role of serum BNP in different CHF patients.

High variability of serum BNP levels exists in CHF patients with weak-to-moderate correlation effects particularly on obesity and diastolic/systolic HF.

Physicians should be cautious on interpreting BNP in different CHF populations.

[C]   NT-proBNP compared with ECHO

Comparison of N-Terminal Pro B-Natriuretic Peptide and Echocardiographic Indices in Patients with Mitral Regurgitation.  Shokoufeh Hajsadeghi1, Niloufar Samiei2, Masoud Moradi3, Maleki Majid2, et al. Corresponding author email: masoud_moradi65@yahoo.com

Abstract

Introduction: Echocardiographic indices can form the basis of the diagnosis of systolic and diastolic left ventricular (LV) dysfunction in patients with Mitral regurgitation (MR). However, using echocardiography alone may bring us to a diagnostic dead-end. The aim of this study was to compare N-Terminal pro B-natriuretic peptide (BNP) and echocardiographic indices in patients with mitral regurgitation.

Methods: 2D and Doppler echocardiography and BNP serum level were obtained from 54 patients with organic mild, moderate and severe MR.

Results: BNP levels were increased with symptoms in patients with mitral regurgitation (NYHAI: 5.7 ± 1.1, NYHAII: 6.9 ± 1.5, NYHAIII: 8.3 ± 2 pg/ml, P , 0.001). BNP plasma level were significantly correlated with MPI (myocardial performance index)(r = 0.399, P = 0.004), and following echocardiographic indices: LVEDV (r = 0.45, P , 0.001), LVESV (r = 0.54, P , 0.001), LVEDD (r = 0.48, P , 0.001), LVESD (r = 0.54, P , 0.001), dp/dt (r = −0.32, P = 0.019) and SPAP (r = 0.4, P = 0.006).

Conclusion: The present study showed that BNP may be useful in patients with MR and may confirm echocardiographic indices.

Keywords: mitral regurgitation, N-Terminal pro-B natriuretic peptide, echocardiographic indices.

The hypothesis assumes that there is a linear sequence of most effective screening that comes out of this study, from a b-type natriuretic peptide to the imaging.  It’s not clear that that is the case, and moreover, silent myocardial infarct is taken and lumped with other serious conditions affecting the myocardium, presumably through compromise of the end-artery circulation to the heart (R, L, and circumflex coronaries).  There is no mention of whether the patients were screened out for peripheral, carotid, or other associated artery disease (superior mesenteric).

I’ll assume that that is the case.  I see a problem with a linear, monothetic, “gold standard” approach, when the disease and the diagnosis of it is multivariate and requires a method that uses a classificatory approach.  We’ll return to that.

English: A Wiggers diagram, showing the cardia...

English: A Wiggers diagram, showing the cardiac cycle events occuring in the left ventricle. (Photo credit: Wikipedia)

[D]  reference normal for NT-proBNP

ABSTRACT

Background: The natriuretic peptides, B-type natriuretic peptide (BNP) and NT-proBNP that have emerged as tools for diagnosing congestive heart failure (CHF) are affected by age and renal insufficiency (RI).This study evaluates the reference value for interpreting NT-proBNP concentrations. Increasing concentrations of NT-proBNP are associated with co-morbidities, not merely CHF, resulting in altered volume status or myocardial filling pressures.

Methods: NT-proBNP was measured in a population with normal trans-thoracic echocardiograms (TTE) and free of anemia or renal impairment.

Selection of Patients: Study participants were seen in acute care for symptoms of shortness of breath suspicious for CHF.

Results: The median NT-proBNP for patients under 50 years is 27.6 pg/ml with an upper limit of 445 pg/ml, and for patients over 50 years the median was 142.3 pg/ml with an upper limit of 475.3 pg/ml. We introduce a transformed NT-proBNP that normalizes for decrease in glomerular filtration rate and eliminates the age factor.

Conclusion: We suggest that NT-proBNP levels can be more accurately interpreted only after removal of the major co-morbidities that affect an increase in this peptide in serum. The PRIDE study guidelines should be applied until presence or absence of comorbidities is diagnosed. With no comorbidities, the reference range for normal over 50 years of age can be reduced below 800 pg/ml. The effect shown in previous papers likely is due to increasing concurrent comorbidity with age.

Key Words: Congestive Heart Failure, Natriuretic peptides, Anemia, Chronic renal insufficiency

Statistical treatment:

The combined acute and blood donor study sets were kept separate and each analyzed for central tendency, distribution and variability. The two were combined after the comorbidities described above were extracted from the acute care study group. This resulted in a population that should be representative of an unaffected study population that could be used to establish a most representative reference range. The database was replicated several times and then patient rows were randomly deleted until there was an expanded combined and mixed data set with 6,700 entries. All of the database sets were used for analyses.

The results are reported in means with p < 0.05 as the measure of significance for difference between means. Independent Student’s t-tests were applied comparing NT-proBNP and anemia. Univariate ANOVAs were used to compare NT-proBNP levels with varying ranges of hemoglobin and age using SPSS 15.0 (SPSS, Chicago, IL). A linear regression analysis with linear fitting and confidence interval was performed using SYSTAT 12 (SYSTAT, San Jose, CA). The results are reported in means with p < 0.05 as the measure of significance for difference between means. Linear regression analysis, Independent Student’s t and Mann-Whitney tests were applied comparing NT-proBNP for age intervals. Reference range was determined using MedCalc 9.2.0.0 (Mariakerke, Belgium).

We observe the following changes with respect to NT-proBNP and age:
  • Sharp increase in NT-proBNP at over age 50
  • Increase in NT-proBNP at 7 percent per decade over 50
  • Decrease in eGFR at 4 percent per decade over 50
  • Slope of NT-proBNP increase with age is related to proportion of patients with eGFR less than 90
  •  NT-proBNP increase can be delayed or accelerated based on disease comorbidities
Adjustment of the NT-proBNP for eGFR and for age over 50 difference

We have carried out a normalization to adjust for both eGFR and for age over 50:

  • Take Log of NT-proBNP and multiply by 1000
  • Divide the result by eGFR (using MDRD[9] or Cockroft Gault[10])
  • Compare results for age under 50, 50-70, and over 70 years
  • Adjust to age under 50 years by multiplying by 0.66 and 0.56.

GFR (mL/min/1.73 m2) = 186 x (Scr)-1.154 x (Age)-0.203 x (0.742 if female) x (1.210 if African-American) (conventional units)

The equation does not require weight because the results are reported normalized to 1.73 m2 body surface area, which is an accepted average adult surface area.

Comparison of the mean + standard deviation of 607 blood donors and NYMH inpatients for the MDRD and Cockroft Gault (eCG), respectively gave 114.3, 43.7(MDRD); 105.0, 40.1 (eCG). The eCG is predicted by the regression: eCG = 0.059 + 0.918*MDRD. The mean + standard deviation for the age under 50 years and 50 or older is 106.5 + 14.7, 100.9 + 14.5 (MDRD); and 102.5 + 18.5, 98.4 + 20.8 (eCG). These differences are significant at < 0.0001, and 0.010, respectively.

The means comparison of the normalized NT-proBNP (NKLog[NT-proBNP]/eGFR) results in 23.4 and 18.7 for 307 non-donors and 300 donors, significant at p < 0.0001, assuming unequal variance). The difference is not significant for the MDRD normalized NT-proBNP (16.5, 6.6). The normalized by eCG result for 324 under age under 50 years and 283 age 50 years and older is 17.7 versus 18.2, significant at p = 0.0001. The MDRD calculated adjustment is 16.8 vs 16.9, which is not significant. The relationship between these is NKLog(NT-proBNP)/eCG = 4.47 + 0.948*NKLog(NT-proBNP)/MDRD. Figure 4 is a plot of the regression of NKLog(NTproBNP)/MDRD vs NKLog(NTproBNP)/eCG predicted over the full study population.

The reference range for the normalized Klog(NT-proBNP)/MDRD is described by a mean 13.99, median 13.12, and standard deviation 6.14 with a nonparametric upper limit of 24.7. A ROC curve is constructed comparing the NT-proBNP, the NKLog(NTproBNP)/MDRD and the ratio NTproBNP to NKLog(NTproBNP)/MDRD in the expanded full database. The area under the curve is 0.944 (0.938-0.950) for NKLog(NTproBNP)/MDRD with a base of 571 patients with early CHF and 6115 patients without. The reference range for NKLog(proBNP)/MDRD can be referenced to the percentiles as follows: 20, 8.78; 40, 11.92; 60, 14.85; 90, 21.10; 95, 24.73; 97.5, 29.54.

Conclusion: We suggest that NT-proBNP levels can be accurately assessed only after removal of the major confounding co-morbidities that increase this peptide in serum. We established our new range after establishing absence of co-morbidities. The value of this approach for screening purposes is an allowance for a considerably lower reference normal with a higher specificity based on the donor studies and the mixture model. This study finds that the reference range for NT-proBNP is age-dependent past age 50 years, mainly as the change relates to eGFR, and we introduce an age adjusted alternative measure, the normalized NT-proBNP using the MDRD transformation described.

NT-pro BNP reference range with blood donors and patients

Measure                                            NT-proBNP (pg/ml)                         After trimming extremes

Highest                                                    1110                                                                   599.4

Arithmetic mean                                   179.6                                                                   118.2

Geometric mean                                        68.7                                                                      54.4

Median                                                          52.6                                                                     42.6

Standard deviation                                250.5                                                                  150.6

D’Agostino-Pearson                          P = 0.0026                                                    P = 0.0091

97.5%

< 50 years                                                  526.9                                                                 445.0

> 50 years                                                1000                                                                    565.0

Upper Limit of Normal                           772.9                                                                475.3

95% confidence interval                   637.1 – 873.73                                      442.7 – 531.0

Bernstein LH, Zions MY, Alam ME, Haq SA, Heitner JF, et al.  What is the best approximation of reference normal for NT-proBNP? Clinical Levels for Enhanced Assessment of NT-proBNP (CLEAN)

Renal Effect on NT-proBNP

NT-proBNP is excreted by the kidney.  Therefore, GFR has to be taken into account in adjusting the reference range.  BNP, unlike the propeptide, is eliminated 80% by vascular endothelium.  What would be the effect of vascular endothelium erosion?  We don’t know.

The Cockroft Gault equation is widely used in hospitals for adjusting medication doses in hospital patients. The MDRD equation was developed for patients with renal insufficiency and has been shown to be comparable to CG for the population the MDRD is applied. However, the MDRD is only reported to a CLCR of only 60 ml/min and is not validated for age over 65 years. On the other hand, the body weight and BMI, necessary for calculating the CG formula are not routinely done for all patients or in all hospitals. We used 307 inpatients and calculated the MDRD up to 100 ml/min/m2, then used the results to predict the CG. The regression for MDRD versus the CG resulted in an r = 0.884, and a regression equation: CG = -21.1 + 1.172*(MDRD). The initial prediction of CG from MDRDe from 198 of the patients is defined by the regression: CGe = -64.6 + 1.866*MDRDe. (Deming)(95% CI: Intercept -84.5 to -42.8; slope 1.40 to 2.33).  The means, medians, standard deviations, and 97.5th percentiles, respectively, of the age, MDRDe and CGe (calculated from weight data) for the 307 patients are: age- 61.2, 62.0, 17.4, 91.3; MDRD – 121.5, 107.5, 55.9, 212.3; CG – 111.7, 98.7, 51.4, 195.0.

The NT-proBNP was adjusted using a log transform and the estimated GFR (glomerular filtration rate by the original method of Levey et al.  The result for reference corrected Nt proBNP is shown in Table 2.

Table 2.

Kruskal-Wallis test

Data KLOGNTPR
Factor codes MDRD60
Sample size

440

Factor

n

Average Rank

0

344

174.11

1

96

386.73

Test statistic

209.8311

Corrected for ties  Ht

209.8313

Degrees of Freedom (DF)

1

Significance level

P < 0.0001

[E]   Mid-region proANP in Emergency Room

Mid-region pro-hormone markers for diagnosis and prognosis in acute dyspnea: results from the BACH (Biomarkers in Acute Heart Failure) trial.
J Am Coll Cardiol 2010 May 11;55(19):2062-76 (ISSN: 1558-3597)
Maisel A; Mueller C; Nowak R; Peacock WF; Landsberg JW; Ponikowski P; Mockel M; Hogan C; Wu AH; Richards M; Clopton P; Filippatos GS; Di Somma S; Anand I; Ng L; Daniels LB; Neath SX; Christenson R; Potocki M; McCord J; Terracciano G; Kremastinos D; Hartmann O; von Haehling S; Bergmann A; Morgenthaler NG; Anker SD
VA San Diego Healthcare System, San Diego, California 92161, USA. amaisel@ucsd.edu.
OBJECTIVES: Our purpose was to assess the diagnostic utility of mid–regional pro-atrial natriuretic peptide (MR-proANP) for the diagnosis of acute heart failure (AHF) and the prognostic value of mid–regional pro-adrenomedullin (MR-proADM) in patients with AHF. BACKGROUND: There are some caveats and limitations to natriuretic peptide testing in the acute dyspneic patient. METHODS: The BACH (Biomarkers in Acute Heart Failure) trial was a prospective, 15-center, international study of 1,641 patients presenting to the emergency department with dyspnea. A noninferiority test of MR-proANP versus B-type natriuretic peptide (BNP) for diagnosis of AHF and a superiority test of MR-proADM versus BNP for 90-day survival were conducted. Other end points were exploratory. RESULTS: MR-proANP (> or =120 pmol/l) proved noninferior to BNP (> or =100 pg/ml) for the diagnosis of AHF (accuracy difference 0.9%). In tests of secondary diagnostic objectives, MR-proANP levels added to the utility of BNP levels in patients with intermediate BNP values and with obesity but not in renal insufficiency, the elderly, or patients with edema. Using cut-off values from receiver-operating characteristic analysis, the accuracy to predict 90-day survival of heart failure patients was 73% (95% confidence interval: 70% to 77%) for MR-proADM and 62% (95% confidence interval: 58% to 66%) for BNP (difference p < 0.001). In adjusted multivariable Cox regression, MR-proADM, but not BNP, carried independent prognostic value (p < 0.001). Results were consistent using NT-proBNP instead of BNP (p < 0.001). None of the biomarkers was able to predict rehospitalization or visits to the emergency department with clinical relevance. CONCLUSIONS: MR-proANP is as useful as BNP for AHF diagnosis in dyspneic patients and may provide additional clinical utility when BNP is difficult to interpret. MR-proADM identifies patients with high 90-day mortality risk and adds prognostic value to BNP. (Biomarkers in Acute Heart Failure [BACH]; NCT00537628). [Copyright 2010 American College of Cardiology Foundation. Published by Elsevier Inc. All rights reserved.].
Comment In: RefSource:J Am Coll Cardiol. 2010 May 11; 55(19):2077-9/PMID:20447529

II. CRP

[A] Predictor of benefit of lowering CRP with statin

Sever PS, Poulter NR, Chang CL, et al; ASCOT Investigators. Evaluation of C-reactive protein prior to and on-treatment as a predictor of benefit from atorvastatin: observations from the Anglo-Scandinavian Cardiac Outcomes Trial. Eur Heart J. 2012;33:486-494

The theory that lowering the C-reactive protein (CRP) level with statin therapy is predictive of cardiovascular outcomes independent of lowering the low-density lipoprotein (LDL) cholesterol level was first advanced by the JUPITER investigators.[1]

  • This study further fueled the debate on whether CRP measurement should be routine for monitoring cardiovascular disease risk. The ASCOT investigators entered this debate when they analyzed data from their trial to determine whether on-statin C-reactive protein level was associated with cardiovascular outcomes.[4]
  • The data in the nested case-control study were from persons recruited to ASCOT in the United Kingdom and Ireland, 9098 of whom were randomly assigned in the blood pressure-lowering arm to receive either amlodipine with or without perindopril or atenolol with or without bendroflumethiazide.[5] Within the whole blood-pressure-lowering group, 4853 persons with a total cholesterol level of 6.5 mmol/L or less (≤ 250 mg/dL) were further randomized to receive atorvastatin or placebo as part of the lipid-lowering arm.[6]
  • For the case-control study, 485 cardiovascular cases were age- and sex-matched with 1367 controls. As expected, the investigators found that baseline LDL cholesterol and CRP levels both predicted cardiovascular events.
  • However, neither the baseline nor the on-treatment CRP level was related to the magnitude of statin efficacy in the prevention of cardiovascular events, whereas the on-treatment LDL cholesterol level was strongly predictive. Including CRP in the Framingham model resulted in a “modest” (2.1%) improvement in risk prediction overall.

The investigators noted that this finding was in line with other prospective studies that showed statistically significant, but modest, absolute improvements with the use of CRP in clinical risk prediction.[7,8] They concluded that “in this hypertensive population selected on the basis of traditional, common coexisting risk factors, CRP did not usefully improve the prediction of cardiovascular events and, critically, reduction in CRP associated with statin therapy was not a predictor of cardiovascular outcome alone or in combination with LDL-cholesterol.”

Eugene Braunwald downplayed the ASCOT investigators’ conclusions in observing “the ASCOT results, albeit quite limited in size, are in fact remarkably similar to those of the [CARE, AFCAPS/TexCAPS, REVERSAL, A to Z], and JUPITER trials, especially in light of the fact that the dose of atorvastatin [in ASCOT] was only 10 mg, while some of the other trials used considerably larger equivalent doses of statins.”

My own take on this is that for at least two decades, there was a belief that the LDL lowering was the main effect of statins, until the (deep frozen) specimens were reexamined from the Framingham study using a hs CRP assay.  The investigation was to determine whether there is a predictor of CVD that is present when the traditional features are not present (which would have to include diabetes and hypertension).  The basis for the use of hsCRP became to identify patients who had sufficient risk to be treated with a statin.  The essential focus seemed to turn on whether statin treatment has efficacy in view of the differential between the LDL or the CRP on the magnitude of the effect.  The muscular effect of a statin then comes into view with the size dose and length of treatment.  However, the CRP measurement identified a relationship between development of the vascular disease and the inflammatory process independently of the STATIN treatment benefit.

Prof. Sever (Medscape): The key result that we found in the initial paper was that CRP, although an independent predictor of cardiovascular events in the hypertensive population, was really only a weak predictor, which is confirmed by the meta-analyses. Furthermore, when you incorporate CRP into a Framingham-style model, it really does not add any benefit or give any more information than if it had not been included in the model. LDL cholesterol is a much more important biomarker. Our second important conclusion addressed the question of whether, after starting a patient on statin therapy, the magnitude of lowering CRP by the statin and the level to which CRP has been reduced predicts cardiovascular outcome. The simple answer from our analyses was that it did not and that the benefits were all related to lowering LDL cholesterol. Our population comprised patients with stable hypertension and no history of coronary disease; likewise, the diabetes population in CARDS had no history of coronary heart disease. Oddly, PROVE IT-TIMI 22 involved persons who were selected from a high-risk coronary heart disease population simply because they had a high level of an inflammatory marker. So, to a certain extent, this is like comparing apples and oranges, and to find some unifying hypothesis on the basis of widely heterogeneous patient populations seems to be a little naive.

[B] Predictor of cardiovascular disease

Acute Phase Reactants as Novel Predictors of Cardiovascular Disease  M. S. Ahmed, A. B. Jadhav, A. Hassan, and Qing H. Meng SRN Inflammation 2012; Article ID 953461, 18 pages. doi:10.5402/2012/953461

  • Acute phase reaction is a systemic response which usually follows a physiological condition that takes place in the beginning of an inflammatory process.
  • This physiological change usually lasts 1-2 days. However, the systemic acute phase response usually lasts longer.
  • The aim of this systemic response is to restore homeostasis.
  1. These events are accompanied by upregulation of some proteins (positive acute phase reactants) and
  2. downregulation of others (negative acute phase reactants) during inflammatory reactions.

Cardiovascular diseases are accompanied by the elevation of several positive acute phase reactants such as

  • C-reactive protein (CRP),
  • serum amyloid A (SAA),
  • fibrinogen,
  • white blood cell count,
  • secretory nonpancreatic phospholipase 2-II (sPLA2-II),
  • ferritin, and
  • ceruloplasmin.

Cardiovascular disease is also accompanied by the reduction of important transport proteins such as

  • albumin, transferrin,
  • transthyretin,
  • retinol-binding protein,
  • antithrombin, and
  • transcortin.

In this paper, we will be discussing the biological activity and diagnostic and prognostic values of acute phase reactants with cardiovascular importance.

The potential therapeutic targets of these reactants will be also discussed.

.

[C] CRP as an Inflammatory Biomarker

CRP is an acute phase protein [7, 8] produced in the liver in response to interleukin- (IL-) 6 which is stimulated, in turn, by tumour necrosis factor-α (TNF-α) and IL-1 [8, 9].

Recent studies suggest that CRP plays a pivotal role in many aspects of atherogenesis including

  • LDL uptake by macrophage,
  • release of proinflammatory cytokines,
  • expression of monocyte chemotactic protein-1,
  • intercellular adhesion molecule-1, and vascular cellular adhesion molecule-1 [10–12].

Activation of inflammation and the acute phase reaction appear to play an important role, not only in the pathogenesis of atherosclerosis, but also in the initiation of the acute coronary syndrome (ACS) [13,14]. Cesari et al. suggested that the inflammatory markers CRP, IL-6, and TNF-α are independent predictors of cardiovascular events in older persons [14].

Diagnostic Value

CRP is also an early ischemic marker and elevated CRP is predictive of future adverse events [22, 23]. High-sensitivity CRP (hs-CRP) rises acutely after tissue injury, including myocardial infarction (MI). Intense cytokine production and inflammatory cell infiltration occur in the area of ischemia and necrosis. This increase of hs-CRP levels, in part, correlates with infarct size [24, 25]

CRP can be also used for patients screening in the primary prevention population [36]. Ockene et al. indicated that CRP is generally expressed at low levels (<1 mg/L) in healthy adults and levels remain relatively stable in the absence of an acute inflammatory stimulus [37].

Patients with unstable angina and CRP >3 mg/L at discharge are more likely to be readmitted for recurrent cardiovascular instability or MI within 1 year [38].

Pietilä et al. indicated that hs-CRP measurement is the strongest correlative factor for future clinical events due to arterial inflammation, myocardial infarction, unstable angina, stroke, and peripheral vascular disease in both diseased and apparently healthy asymptomatic patients [40].

The CRP plasma level also is the best risk assessment in patients with

  • either stable or unstable angina,
  • long term after myocardial infarction, and
  • in patients undergoing revascularization therapies [41].
  • One study showed the only independent cardiovascular risk indicators using multivariate, age adjusted and traditional risk analysis were CRP and Total/HDL cholesterol ratio.
  • If CRP, IL-6, and ICAM-1 levels are added to lipid levels, risk assessment can be improved over lipids alone.
  • Moreover, serum CRP may indicate the vulnerability of the plaque [40].

Prognostic Value

  • elevation of hs-CRP levels predicts a poor cardiovascular prognosis [42].
  • The extent of the inflammatory response to injury appears to have prognostic significance, which is independent of the extent of myocardial injury.
  • hs-CRP response after MI has been shown to predict future CHD morbidity and mortality independent of infarct size [43].
  • CRP is also a predictor of incident type 2 diabetes. As well, it adds a prognostic information on vascular risk at all levels of the metabolic syndrome [44].

__________________________________________________________________________________________________________________________

III.  Troponin(s) and hs-TnI/cTnT

Comparison of diagnostic accuracy between three different rules of interpreting high sensitivity troponin T results. Francesco Buccelletti; Leonarda Galiuto; Davide Marsiliani; Paolo Iacomini; et al. Intern Emerg Med 2012; 7, 365

Abstract

With the introduction of high sensitivity troponin-T (hs-TnT) assay, clinicians face more patients with ‘positive’ results but without myocardial infarction. Repeated hs-TnT determinations are warranted to improve specificity. The aim of this study was to compare diagnostic accuracy of three different interpretation rules for two hs-TnT results taken 6 h apart. After adjusting for clinical differences, hs-TnT results were recoded according to the three rules.

  • Rule1: hs-TnT >13 ng/L in at least one determination.
  • Rule2: change of >20 % between the two measures.
  • Rule3: change >50 % if baseline hs-TnT 14-53 ng/L and >20 % if baseline >54 ng/L.

The sensitivity, specificity and ROC curves were compared. The sensitivity analysis was used to generate post-test probability for any test result. Primary outcome was the evidence of coronary critical stenosis (CCS) on coronary angiography in patients with high-risk chest pain.

183 patients were analyzed (38.3 %) among all patients presenting with chest pain during the study period. CCS was found in 80 (43.7 %) cases.

The specificity was 0.62 (0.52-0.71), 0.76 (0.66-0.84) and 0.83 (0.74-0.89) for rules 1, 2 and 3, respectively (P < 0.01). Sensitivity decreased with increasing specificity (P < 0.01).

Overall diagnostic accuracy did not differ among the three rules (AUC curves difference P = 0.12). Sensitivity analysis showed a 25 % relative gain in predicting CCS using rule 3 compared to rule 1. Changes between two determinations of hs-TnT 6 h apart effectively improved specificity for CCS presence in high-risk chest pain patients.

There was a parallel loss in sensitivity that discouraged any use of such changes as a unique way to interpret the new hs-TnT results.

Advances in identifying NSTEMI biomarkers [Published 31 August 2012 | Article by Excerpta Medica | Tags: elderly, ami, biomarkers, diagnosis]

In the run-up to the ESC conference at the end of August, we review some recently published research on the hot topic of biomarkers for NSTEMI.

Prompt and accurate diagnosis of acute non-ST elevation myocardial infarction (NSTEMI) can be particularly challenging in elderly patients, as they often present with

  • atypical symptoms and/or have an inconclusive ECG.
  • the diagnostic value of cardiac troponin T (cTnT), an established marker of cardiac injury, is often limited as there is often non-coronary troponin elevation caused by concomitant conditions such as acute congestive heart failure.
  • Identifying new sensitive and specific biomarkers of NSTEMI in elderly patients is therefore important, and circulating microRNAs (miRs) are emerging as good candidates.

researchers evaluated the diagnostic potential of plasma levels of various miRs in elderly patients enrolled at presentation:

  • 92 acute NSTEMI patients (complicated by congestive heart failure in three-quarters of cases),
  • 81 patients with acute congestive heart failure without acute MI, and
  • 99 age-matched healthy people (the control group).

The researchers, from centers in Italy, found that levels of miR-1, miR-21, miR-133a, and miR-423-5p were 3-10 times higher in the patients with NSTEMI, compared with controls. Levels of miR-499-5p, meanwhile, were more than 80 times higher in the NSTEMI patients compared with the patients in the control group.

  • Levels of miR-499-5p and miR-21 were also significantly higher in the NSTEMI group compared with the group of patients with acute congestive heart failure without acute MI.
  • The researchers also found that miR-499-5p was similar to cTnT in being able to distinguish NSTEMI patients from the other two groups.
  • Also, a subgroup analysis of patients with a modest elevation in cTnT level at presentation (0.03-0.10 ng/mL) revealed that miR-499-5p had a diagnostic accuracy superior both to cTnT and to high sensitivity cTnT in differentiating NSTEMI from acute congestive heart failure.

International Journal of Cardiology

________________________________________________________________________________________________________________________________________________________________________

IV. Predicting cardiovascular mortality in NSTEMI patients

[A]  Japanese researchers studied 258 consecutive patients hospitalized for unstable angina and NSTEMI within 24 hours of the onset of chest symptoms, and followed them up for a median period of 49 months after admission. During this period there were 38 cardiovascular deaths (14.7%).

They reported that high-mobility group- box 1 (HMGB1), a nuclear protein and signaller of tissue damage, was “a potential and independent predictor of cardiovascular mortality in patients hospitalized for unstable angina and NSTEMI.

  • HMGB1,
  • cardiac troponin I,
  • Killip class greater than 1, and
  • age

were each independently and significantly associated with cardiovascular mortality.

……………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………

[B]  William LaFramboise et al.       BMC Med. 2012 Dec 5;10(1):157)
see Report by Aviva Lev-Ari (pharmaceuticalintelligence.com)  Coronary artery disease in symptomatic patients referred for coronary angiography: Predicted by Serum Protein Profiles

Significant differences were detected in circulating proteins from patients requiring revascularization including increased apolipoprotein B100 (APO-B100), C-reactive protein (CRP), fibrinogen, vascular cell adhesion molecule 1 (VCAM-1), myeloperoxidase (MPO), resistin, osteopontin, interleukin (IL)-1beta, IL-6, IL-10 and N-terminal fragment protein precursor brain natriuretic peptide (NT-pBNP) and decreased apolipoprotein A1 (APO-A1). Biomarker classification signatures comprising up to 5 analytes were identified using a tunable scoring function trained against 239 samples and validated with 120 additional samples. A total of 14 overlapping signatures classified patients without significant coronary disease (38% to 59% specificity) while maintaining 95% sensitivity for patients requiring revascularization. Osteopontin (14 times) and resistin (10 times) were most frequently represented among these diagnostic signatures. The most efficacious protein signature in validation studies comprised osteopontin (OPN), resistin, matrix metalloproteinase 7 (MMP7) and interferon gamma (IFNgamma) as a four-marker panel while the addition of either CRP or adiponectin (ACRP-30) yielded comparable results in five protein signatures.

______________________________________________________________________________________________________________________________________________________

V.  Assessing Cardiovascular Risk

Agency for Healthcare Research and Quality (AHRQ)

Assessing Cardiovascular Risk: Guideline Synthesis

Agency for Healthcare Research and Quality (AHRQ) Authors and Disclosures Posted: 03/01/2012

…………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………..

The Third MI Definition: An Expert Interview With Joseph Alpert In the new definition, the diagnosis of acute MI remains unchanged: That is, it applies where there is evidence of myocardial necrosis in a clinical setting consistent with acute myocardial ischemia. However, the criteria for diagnosis have been updated, with an emphasis on the biomarker cardiac troponin.

  1. The first essential criterion for diagnosis of MI is detection of a rise or fall in cardiac troponin, or CKMB if troponin is not available, with at least 1 value above the 99th percentile upper reference limit, plus at least 1 the following criteria:
  2. Symptoms of ischemia;
  3. ECG changes of new or presumed new ischemia (significant ST-segment T-wave changes or new left bundle branch block);
  4. Development of pathologic Q waves on ECG; or
  5. Imaging evidence of new loss of viable myocardium or new regional wall-motion abnormality.Other criteria include those for MI in sudden unexpected cardiac death and for MI during percutaneous coronary intervention (PCI) and coronary artery bypass graft surgery (CABG).

The guidance document supports the use of high-sensitivity cardiac troponin assays, especially for distinguishing myocardial injury not related to myocardial ischemia, such as that associated with heart failure or renal failure. These assays are available in Europe, and not in the United States. MI is designated as ST-segment elevation MI or non- ST-segment elevation MI, and as in the 2007 version, it is classified into 5 types on the basis of pathologic, clinical, and prognostic differences. These types have been updated in the latest version.

  1. Type 1 MI (spontaneous MI) is related to atherosclerotic plaque rupture or other event leading to thrombus formation in ≥ 1 of the coronary arteries, leading to decreased myocardial blood flow with ensuing necrosis;
  2.  Type 2 MI arises from a condition other than CAD;
  3.  Type 3 MI is deemed to have occurred when cardiac death occurs with symptoms suggestive of myocardial ischemia, but without biomarker values having been obtained; and
  4. Type 4 and 5 MIs are related to PCI and CABG, respectively, and have been redefined since 2007.

The new document also describes situations in which troponin levels are elevated in conditions where myocardial injury with necrosis is associated with predominantly nonischemic myocardial injury, such as heart failure, renal failure, myocarditis, arrhythmias, or pulmonary embolism.

__________________________________________________________________________________________________________________________________________________________________________

VI Statistical Problems

The normal or “bell shaped” curve is a plot of numerical values along the x-axis and the frequency of the occurrence on the y-axis.  If the set of measurements occurs as a random and independent event, we refer to this as parametric, and the distribution of the values is a bell shaped curve with all but 2.5% of the values included within both ends, with the mean or arithmetic average at the center, and with 67% of the sample contained within 1 standard deviation of the mean.  We view a reference range in terms of a homogeneous population.  This means that while all values might not be the same, the values are scattered within a distance from the mean that becomes less frequent as the distance is larger so that we can describe a mean and a 95% confidence interval around the mean.  In the problem we are discussing, the classic reference value could be determined with outliers removed, and it would most likely fit to a Receiver Operator Characteristic curve.  This became blurred when the high sensitivity assay was introduced, which included NOISE, which is really not noise but heterogeneous elements related to [a] vascular events that are not caused by plaque rupture, or [b] ischemia related to “piecemeal necrosis” which continued might predict a serious future event.  Hidden variables include – age, diurnal variation, racial factors, and disease (hypertension, CHF, type 2 diabetes, renal failure).

A majority have no ST elevation on EKG, considered definitive for AMI.  This makes the finding of elevated and increasing cardiac specific enzyme or protein in serum of paramount importance for specifying damaged cardiac muscle in a context of insufficient circulation.   We examine the classification of AMI using a combination of features of chest pain, EKG, and a sensitive cardiac marker, derived from the cardiac muscle filament.   An optimum value for a test cutoff is, such as cTnT, can be derived without using a prior determination of disease status. This is an alternative to first carrying out a study with a training set, and then repeating it with a validation set, provided there is sufficient information for classifying the data..  We have to construct a self-classifying table of ordered classes that have assigned measurable risks.   Haberman (4) discusses the underlying assumptions used by Magidson for association models of cross-classified data in calculating the maximum likelihood estimates (MLE) by using the log-likelihood ratio and a sum of squares representing deviations of parameters from their constraints. The Latent Class Analysis (LCA) developed by Magidson and Vermunt allows use of a traditional LCA or a regression model (Statistical Innovation. Belmont, MA).  .  The LCA model uses the variables – chest pain, EKG, and troponin T – to classify the data and to test the underlying structure using powerful fit measures, such as L2.  Chest pain has the value of “typical” or “other”.   EKG has the value ST depression or any other (for a non Q-wave study).  “cTnT” has the value  assigned by rank in the scaling intervals.   The results of such an analysis are displayed in Table 1.

Table 1. This LCA classification was constructed using the troponin T before hsTnT was available.

CTnT (mg/L) MI (6%)  Not MI (94%)
0-0.03 0.0008 0.8485
0.031-0.055 0.0009 0.0791
0.056-0.080 0.0009 0.0369
0.081-0.099 0.0010 0.0106
0.10-0.199 0.2026 0.0238
> 0.20 0.7939 0.0012

Eugene Rypka. Syndromic classification: A process for amplifying information using S-Clustering.  Nutrition 1996; 14(12: 827-829.

Stuart W Zarich, Keith Bradley, Inder Dip Mayall, Larry H Bernstein. Minor elevations in troponin T values enhance risk assessment in emergency department patients with suspected myocardial ischemia: analysis of novel troponin T cut-off values. Clin Chim Acta 2004; 343(1-2):223-229

Haberman SJ. Computation of maximum likelihood estimates in association models. J Am Stat Assoc 1995;90:1438-1446

Rudolph RA, Bernstein LH, Babb J.  Information Induction for the Diagnosis of  Myocardial Infarction. Clin Chem 1988; 34: 2031-8.

Vermoent JK, and Magidson J. Latent class cluster analysis. JA Hagenaars and AL McCutcheon (eds.), Advanced Latent Class Analysis. Cambridge, Cambridge University Press, 2000.

Bernstein LH, Qamar A, McPherson C, Zarich S. Evaluating a new graphical ordinal logit method (GOLDminer) in the diagnosis of myocardial infarction utilizing clinical features and laboratory data.   Yale J Biol Med 1999; 72: 259-268.

__________________________________________________________________________________________________________________________________________________________________________

VII. Conclusions I have made a number of comments to follow up on.  The diagnosis of myocardial infarct has been extended as a result of the emergence of the high sensitivity troponins, but the laboratory methods have not caught up with the technology as the identification of myocardial ischemia is broken down with fine granularity in order to

  • identify the high risk patients early
  • and manage them effectively at the earliest stage of disease evolution

We no longer ponder over

  1. ECG findings of new Q-qave, not previously seen
  2. ST elevation
  3. T-wave inversion

These are an indication of plaque rupture. There are strong associations between CRP, hyperhomocysteinemia, and then add the troponins and b-type natriuretic  and the pro b-type peptides.  These associations have to be analyzed by “syndromic classification”, described by Eugene Rypka. The study first described found great value in the BNP and proBNP.  Despite having the creatinine clearance, the NT-proBNP can’t be adequately interpreted without adjusting for the estimated glomerular filtration rate, and using a log transform for the high fold-increase with age.

There is much more to be done with capturing the information from the data we are generating.  The problem of classification requires accurate data measurement, but it also requires that features in scaled data are combined in meaningful ways.  That job is far from completed.

…………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………….

Below I paste all discussions on this post that are taking place on LinkedIn Group: Innovations in Cardiology:

Kathy Dowd, AuD • I am an audiologist representing the Academy of Doctors of Audiology for an initiative of early identification of hearing loss in adults with chronic diseases, including cardiovascular disease, thyroid disease, diabetes, etc. I am working on a new product that will automatically screen hearing of patients with these conditions and route them to audiologists for evaluation, treatment and counseling. Hearing loss is unidentified for most adults for 7-10. The psychological impact of hearing loss includes depression, isolation, confusion and poor job performance. We are focused on educating healthcare professionals on the need to identify this ‘silent epidemic’ as a co morbidity with most major illnesses.

Aviva Lev-Ari, PhD, RN • Dr. William LaFramboise

Thank you for your comment above and the reference to your most recent publication. It is very helpful. We are on the same page on this topic.

May I bring to the attention of the readers three sources which are shading additional light on that matter.

To Stent or Not? A Critical Decision

To Stent or Not? A Critical Decision

Obstructive coronary artery disease diagnosed by RNA levels of 23 genes – CardioDx heart disease test wins Medicare coverage

http://pharmaceuticalintelligence.com/2012/08/14/obstructive-coronary-artery-disease-diagnosed-by-rna-levels-of-23-genes-cardiodx-heart-disease-test-wins-medicare-coverage/http://pharmaceuticalintelligence.com/?s=PCI

Follow William
William LaFramboise • Thank you Aviva. The CardioDx approach is promising with heavy commercial support for use in a primary care practitioner’s office. However, RNA acquisition, purification and qRT-PCR expression analysis takes 2-3 days, is performed off-site, derives from a small subset of circulating inflammatory cells and is not yet directly correlated with functional proteomics. So its value in the Emergency Room and Chest Clinic is currently limited. The proteomics test we published revealed systemic serum changes in a small number of proteins known to be involved in atherosclerosis. It has a faster turnaround time (minutes to hours) that could be implemented in an emergency room or chest clinic. We are predominantly interested in using our test to “rule out” symptomatic patients who currently undergo coronary angiography but do NOT have clinically significant CAD. Our goal is to eliminate unecessary catheterizations while catching all patients that should undergo coronary angiography with a high probability of percutaneous intervention. Currently, the patients we are targeting all undergo catheterization; our test will hopefully allow us to identify at least some of these patients who do not have CAD and eliminate this expensive and risky procedure. However, we are in the pioneering stages of developing our test so there are miles to go before we establish and validate clinical efficacy.

Larry

Larry Bernstein • What you have indicated is practical proteomics. There is more to be done in line with what Dr Lev-Ari has indicated based on additional voluminous literature. What you have done with a not so large data set, and probably underpowered looks very interesting.

I f you were willing to share the data, now that it is publihed, I think that we can sharpen the results using a method of “identifying anomalies”, and even come up with estimated probabilities for meaningful classes. I think that the best you can get is defined by Kullback-Liebler distance.

Larry H Bernstein, MD
larry.bernstein@gmail.com

Biomarker classification signatures comprising up to 5 analytes were identified using a tunable scoring function trained against 239 samples and validated with 120 additional samples. A total of 14 overlapping signatures classified patients without significant coronary disease (38% to 59% specificity) while maintaining 95% sensitivity for patients requiring revascularization. Osteopontin (14 times) and resistin (10 times) were most frequently represented among these diagnostic signatures. The most efficacious protein signature in validation studies comprised osteopontin (OPN), resistin, matrix metalloproteinase 7 (MMP7) and interferon gamma (IFNgamma) as a four-marker panel while the addition of either CRP or adiponectin (ACRP-30) yielded comparable results in five protein signatures.

Proteins in the serum of CAD patients predominantly reflected (1) a positive acute phase, inflammatory response and (2) alterations in lipid metabolism, transport, peroxidation and accumulation.

Follow William
William LaFramboise • Our study (http://www.ncbi.nlm.nih.gov/pubmed/23216991) comprised discovery research using targeted immunochemical screening of retrospective patient samples using both Luminex and Aushon platforms as opposed to shotgun proteomics. Hence the costs constrained sample numbers. Nevertheless, our ability to predict outcome substantially exceeded available methods:

DISCUSSION
The Framingham CHD scores were statistically different between groups (P <0.001, unpaired Student’s t test) but they classified only 16% of the subjects without significant CAD (10 of 63) at a 95% sensitivity for patients with CAD. In contrast, our algorithm incorporating serum values for OPN, RES, CRP, MMP7 and IFNγ identified 63% of the subjects without significant CAD (40 of 63) at 95% sensitivity for patients with CAD. Thus, our multiplex serum protein classifier correctly identified four times as many patients as the Framingham index.

The addition of clinical variables to our scoring system should improve the acuity of our test as we move into the next phase. I appreciate your input and will contact you directly for further insights

Larry Bernstein • Bill La Fram..

our algorithm incorporating serum values for OPN, RES, CRP, MMP7 and IFNγ identified 63% of the subjects without significant CAD (40 of 63) at 95% sensitivity for patients with CAD

I think you can improve the algorithm with strong clinical features. The Goldman algorithm is stronger than the Framingham Index. Maybe its because the FI is epidemiological and is a measure of long term risk being present and does not indicate significant features at the time of presenting. The best features of the Goldman algorithm (without lab work) are – ECG (which may be arguable with NSEMI), but the presence of Afib or tachyarrhythmia could be added to that in weighting, and radiation actually should include symptoms of gall bladder (vagal nerve branch), and onset, characteristic and duration of pain, and SOB.

In your algorithm there isn’t any assessment of the hypercoagulable state, blood flow or Viscosity. There is a strong relationship between hyperhomocysteinemia and CVD, and the HHCys has ties to impaired methyl group transfers that maybe proinflammatory through more than one interaction: countering eNOS, related to Lp(a), un unknown relationship to iNOS (which becomes a counterpoise to eNOS), an effect on blood flow and viscosity, and a relationship to platelet aggregation.

Lp(a) was originally considered of less weight, except that it occurred in thin people from Asian Indian descent. The relationship to apo(B) and to dense LDL particles is now a factor. Sam Filligane uses Lp(a) in his ambulatory practice, and he also uses the PLAC test that Aviva has posted on.

The biggest problem we have is the amount of variability in the data physicians use. It makes metaanalysis a poor solution to the problem. The standardization of laboratory “panels” set up after CLIA 88 puts a real burden on the physician for unsubstantiated “cost benefits” in the light of today’s knowledge.

…………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………………….

English: Four chamber view on cardiovascular m...

English: Four chamber view on cardiovascular magnetic resonance imaging. (Photo credit: Wikipedia)

Other related articles on Assessing Cardiovascular Disease with Biomarkers published on this Open Access Online Scientific Journal, include the following:


Dr. Lev-Ari’s research on Assessing Cardiovascular Disease with Biomarkers includes

  • Biomarkers in vascular biology,
  • Biomarkers in molecular cardiology and
  • circulating Endothelial Progenitor Cells (cEPCs) as a Biomarker for cardiovascular marcovascular disease risk


Lev-Ari, A., (2012U). Cardiovascular Outcomes: Function of circulating Endothelial Progenitor Cells (cEPCs): Exploring Pharmaco-therapy targeted at Endogenous Augmentation of cEPCs

http://pharmaceuticalintelligence.com/2012/08/28/cardiovascular-outcomes-function-of-circulating-endothelial-progenitor-cells-cepcs-exploring-pharmaco-therapy-targeted-at-endogenous-augmentation-of-cepcs/

Lev-Ari, A., (2012T). Endothelial Dysfunction, Diminished Availability of cEPCs, Increasing CVD Risk for Macrovascular Disease – Therapeutic Potential of cEPCs

http://pharmaceuticalintelligence.com/2012/08/27/endothelial-dysfunction-diminished-availability-of-cepcs-increasing-cvd-risk-for-macrovascular-disease-therapeutic-potential-of-cepcs/

Lev-Ari, A., (2012S). Vascular Medicine and Biology: CLASSIFICATION OF FAST ACTING THERAPY FOR PATIENTS AT HIGH RISK FOR MACROVASCULAR EVENTS Macrovascular Disease – Therapeutic Potential of cEPCs

http://pharmaceuticalintelligence.com/2012/08/24/vascular-medicine-and-biology-classification-of-fast-acting-therapy-for-patients-at-high-risk-for-macrovascular-events-macrovascular-disease-therapeutic-potential-of-cepcs/

Lev-Ari, A. (2012a). Resident-cell-based Therapy in Human Ischaemic Heart Disease: Evolution in the PROMISE of Thymosin beta4 for Cardiac Repair

http://pharmaceuticalintelligence.com/2012/04/30/93/

Lev-Ari, A. (2012b). Triple Antihypertensive Combination Therapy Significantly Lowers Blood Pressure in Hard-to-Treat Patients with Hypertension and Diabetes

http://pharmaceuticalintelligence.com/2012/05/29/445/

Lev-Ari, A. (2012h). Macrovascular Disease – Therapeutic Potential of cEPCs: Reduction Methods for CV Risk

http://pharmaceuticalintelligence.com/2012/07/02/macrovascular-disease-therapeutic-potential-of-cepcs-reduction-methods-for-cv-risk/

Lev-Ari, A. (2012xx). Coronary artery disease in symptomatic patients referred for coronary angiography: Predicted by Serum Protein Profiles

http://pharmaceuticalintelligence.com/2012/12/29/coronary-artery-disease-in-symptomatic-patients-referred-for-coronary-angiography-predicted-by-serum-protein-profiles/

Lev-Ari, A. (2013a) forthcoming, based on:

Part III: (2006c) Biomarker for Therapeutic Targets of Cardiovascular Risk Reduction by cEPCs Endogenous Augmentation using New Combination Drug Therapy of Three Drug Classes and Several Drug Indications. Northeastern University, Boston, MA 02115

Special Considerations in Blood Lipoproteins, Viscosity, Assessment and Treatment                                    Larry Bernstein

New Insights on Nitric Oxide donors – Part IV                Larry Bernstein

The Essential Role of Nitric Oxide and Therapeutic NO Donor Targets in Renal Pharmacotherapy             Larry Bernstein

A second look at the transthyretin nutrition inflammatory conundrum                                                                  Larry Bernstein

What is the role of plasma viscosity in hemostasis and vascular disease risk?                                                        Larry Bernstein

Biochemistry of the Coagulation Cascade and Platelet Aggregation – Part I                                                            Larry Bernstein

Laboratory, Innovative Technology, Therapeutics                                                                                                            Larry Bernstein

Ubiquinin-Proteosome pathway, autophagy, the mitochondrion, proteolysis and cell apoptosis                 Larry Bernstein

Overview of new strategy for treatment of T2DM: SGLT2 inhibiting oral antidiabetic agents                             aviralvatsa

Mitochondrial dynamics and cardiovascular diseases          ritusaxena

Nitric Oxide and it’s impact on Cardiothoracic Surgery        tildabarliya

Telling NO to Cardiac Risk                                                                  sjwilliamspa

Read Full Post »

Identification of Biomarkers that are Related to the Actin Cytoskeleton

Curator and Writer: Larry H Bernstein, MD, FCAP

Article I Identification of Biomarkers that are Related to the Actin Cytoskeleton

This is Part I in a series of articles on Calcium and Cell motility.

The Series consists of the following articles:

Part I: Identification of Biomarkers that are Related to the Actin Cytoskeleton

Larry H Bernstein, MD, FCAP

http://pharmaceuticalintelligence.com/2012/12/10/identification-of-biomarkers-that-are-related-to-the-actin-cytoskeleton/

Part II: Role of Calcium, the Actin Skeleton, and Lipid Structures in Signaling and Cell Motility

Larry H. Bernstein, MD, FCAP, Stephen Williams, PhD and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/08/26/role-of-calcium-the-actin-skeleton-and-lipid-structures-in-signaling-and-cell-motility/

Part III: Renal Distal Tubular Ca2+ Exchange Mechanism in Health and Disease

Larry H. Bernstein, MD, FCAP, Stephen J. Williams, PhD
 and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/09/02/renal-distal-tubular-ca2-exchange-mechanism-in-health-and-disease/

Part IV: The Centrality of Ca(2+) Signaling and Cytoskeleton Involving Calmodulin Kinases and Ryanodine Receptors in Cardiac Failure, Arterial Smooth Muscle, Post-ischemic Arrhythmia, Similarities and Differences, and Pharmaceutical Targets

Larry H Bernstein, MD, FCAP, Justin Pearlman, MD, PhD, FACC and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/09/08/the-centrality-of-ca2-signaling-and-cytoskeleton-involving-calmodulin-kinases-and-ryanodine-receptors-in-cardiac-failure-arterial-smooth-muscle-post-ischemic-arrhythmia-similarities-and-differen/

Part V: Ca2+-Stimulated Exocytosis:  The Role of Calmodulin and Protein Kinase C in Ca2+ Regulation of Hormone and Neurotransmitter

Larry H Bernstein, MD, FCAP
and
Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/12/23/calmodulin-and-protein-kinase-c-drive-the-ca2-regulation-of-hormone-and-neurotransmitter-release-that-triggers-ca2-stimulated-exocytosis/

Part VI: Calcium Cycling (ATPase Pump) in Cardiac Gene Therapy: Inhalable Gene Therapy for Pulmonary Arterial Hypertension and Percutaneous Intra-coronary Artery Infusion for Heart Failure: Contributions by Roger J. Hajjar, MD

Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/08/01/calcium-molecule-in-cardiac-gene-therapy-inhalable-gene-therapy-for-pulmonary-arterial-hypertension-and-percutaneous-intra-coronary-artery-infusion-for-heart-failure-contributions-by-roger-j-hajjar/

Part VII: Cardiac Contractility & Myocardium Performance: Ventricular Arrhythmias and Non-ischemic Heart Failure – Therapeutic Implications for Cardiomyocyte Ryanopathy (Calcium Release-related Contractile Dysfunction) and Catecholamine Responses

Justin Pearlman, MD, PhD, FACC, Larry H Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/08/28/cardiac-contractility-myocardium-performance-ventricular-arrhythmias-and-non-ischemic-heart-failure-therapeutic-implications-for-cardiomyocyte-ryanopathy-calcium-release-related-contractile/

Part VIII: Disruption of Calcium Homeostasis: Cardiomyocytes and Vascular Smooth Muscle Cells: The Cardiac and Cardiovascular Calcium Signaling Mechanism

Justin Pearlman, MD, PhD, FACC, Larry H Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/09/12/disruption-of-calcium-homeostasis-cardiomyocytes-and-vascular-smooth-muscle-cells-the-cardiac-and-cardiovascular-calcium-signaling-mechanism/

Part IX: Calcium-Channel Blockers, Calcium Release-related Contractile Dysfunction (Ryanopathy) and Calcium as Neurotransmitter Sensor

Justin Pearlman, MD, PhD, FACC, Larry H Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN

Part X: Synaptotagmin functions as a Calcium Sensor: How Calcium Ions Regulate the fusion of vesicles with cell membranes during Neurotransmission

Larry H Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/09/10/synaptotagmin-functions-as-a-calcium-sensor-how-calcium-ions-regulate-the-fusion-of-vesicles-with-cell-membranes-during-neurotransmission/

Part XI: Sensors and Signaling in Oxidative Stress

Larry H. Bernstein, MD, FCAP

http://pharmaceuticalintelligence.com/2013/11/01/sensors-and-signaling-in-oxidative-stress/

Part XII: Atherosclerosis Independence: Genetic Polymorphisms of Ion Channels Role in the Pathogenesis of Coronary Microvascular Dysfunction and Myocardial Ischemia (Coronary Artery Disease (CAD))

Larry H Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/12/21/genetic-polymorphisms-of-ion-channels-have-a-role-in-the-pathogenesis-of-coronary-microvascular-dysfunction-and-ischemic-heart-disease/

In this article the Author will cover two types of biomarker on the function of actin in cytoskeleton mobility in situ.

  • First, is an application in developing the actin or other component, for a biotarget and then, to be able to follow it as

(a) a biomarker either for diagnosis, or

(b) for the potential treatment prediction of disease free survival.

  • Second, is mostly in the context of MI, for which there is an abundance of work to reference, and a substantial body of knowledge about

(a) treatment and long term effects of diet, exercise, and

(b) underlying effects of therapeutic drugs.

1.  Cell Membrane (cytoskeletal) Plasticity

Refer to … Squeezing Ovarian Cancer Cells to Predict Metastatic Potential: Cell Stiffness as Possible Biomarker

Reporter/curator: Prabodh Kandala, PhD

New Georgia Tech research shows that cell stiffness could be a valuable clue for doctors as they search for and treat cancerous cells before they’re able to spread. The findings, which are published in the journal PLoS One, found that highly metastatic ovarian cancer cells are several times softer than less metastatic ovarian cancer cells. This study used atomic force microscopy (AFM) to study the mechanical properties of various ovarian cell lines. A soft mechanical probe “tapped” healthy, malignant and metastatic ovarian cells to measure their stiffness. In order to spread, metastatic cells must push themselves into the bloodstream. As a result, they must be highly deformable and softer. This study results indicate that cell stiffness may be a useful biomarker to evaluate the relative metastatic potential of ovarian and perhaps other types of cancer cells.

Comparative gene expression analyses indicate that the reduced stiffness of highly metastatic HEY A8 cells is associated with actin cytoskeleton remodeling and microscopic examination of actin fiber structure in these cell lines is consistent with this prediction.   The results suggest either of two approaches. Atomic Force Microscopy is not normally used by pathologists in diagnostics. Electron microscopy requires space for making and cutting the embedded specimen, and a separate room for the instrument. The instrument is large and the technique was not suitable for anything other than research initially until EM gained importance in Renal Pathology. It has not otherwise been used.  This new method looks like it might be more justified over a spectrum of cases.

A.  Atomic Force Microscopy

So the first point related to microscopy is whether AFM has feasibility for routine clinical use in the pathologists’ hands. This requires:

  1. suitable size of equipment
  2.  suitable manipulation of the specimen
  3. The question of whether you are using overnight fixed specimen, or whether the material is used unfixed
  4. Nothing is said about staining of cells for identification.
  5. Then there is the question about whether this will increase the number of Pathologist Assistants used across the country, which I am not against.   This would be the end of “house” trained PAs, and gives more credence to the too few PA programs across the country. The PA programs have to be reviewed and accredited by NAACLS (I served 8 years on the Board). A PA is represented on the Board, and programs are inspected by qualified peers.   There is no academic recognition given to this for tenure and promotion in Pathology Departments, and a pathologist is selected for a medical advisory role by the ASCP, and must be a Medical Advisor to a MLS accredited Program.   The fact is that PAs do gross anatomic dictation of selected specimens, and they do autopsies under the guidance of a pathologist. This is the reality of the profession today. The pathologist has to be in attendance at a variety of quality review conferences, for surgical morbidity and mortality to obstetrics review, and the Cancer Review. Cytopathology and cytogenetics are in the pathology domain.   In the case of tumors of the throat, cervix, and accessible orifices, it seems plausible to receive a swab for preparation. However, sampling error is greater than for a biopsy. A directed needle biopsy or a MIS specimen is needed for the ovary.

B.  identification of biomarkers that are related to the actin cytoskeleton

The alternative to the first approach is the identification of biomarkers that are related to the actin cytoskeleton, perhaps in the nature of the lipid or apoprotein isoform that gives the cell membrane deformability. The method measuring by Atomic Force Microscopy is shown with the current method of cytological screening, and I call attention to cells clustered together that have a scant cytoplasm surrounding nuclei occupying 1/2 to 3/4 of the cell radius.  The cells are not anaplastic, but the clumps are suggestive of glnad forming epithelium.

English: Animation showing 3-D nature of clust...

English: Animation showing 3-D nature of cluster. Image:Serous carcinoma 2a – cytology.jpg (Photo credit: Wikipedia)

The cell membrane, also called the plasma memb...

The cell membrane, also called the plasma membrane or plasmalemma, is a semipermeable lipid bilayer common to all living cells. It contains a variety of biological molecules, primarily proteins and lipids, which are involved in a vast array of cellular processes. It also serves as the attachment point for both the intracellular cytoskeleton and, if present, the cell wall. (Photo credit: Wikipedia)

English: AFM bema detection

AFM non contact mode

AFM non contact mode (Photo credit: Wikipedia)

C.  The diagnosis of ovarian cancer can be problematic because it can have a long period of growth undetected.

On the other hand, it is easily accessible once there is reason to suspect it. They are terrible to deal with because they metastasize along the abdominal peritoneum and form a solid cake. It is a problem of location and silence until it is late. Once they do announce a presence on the abdominal wall, there is probably a serous effusion. It was not possible to rely on a single marker, but when CA125 was introduced, Dr. Marguerite Pinto, Chief of Cytology at Bridgeport Hospital-Yale New Haven Health came to the immnunochemistry lab and we worked out a method for analyzing effusions, as we had already done with carcinoembryonic antigen.       The use of CEA and CA125 was published by Pinto and Bernstein as a first that had an impact.  This was followed by a study with the Chief of Oncology, Dr. Martin Rosman, that showed that the 30 month survival of patients post treatment is predicted by the half-life of disappearance of CA125 in serum.  At the time of this writing, I am not sure of the extent of its use 20 years later. History has taught us that adoption can be slow, depending very much on dissemination from major academic medical centers.  On the other hand, concepts can also be stuck at academic medical centers because of a rigid and unprepared mindset in the professional community.  The best example of this is the story of Ignaz Semmelweis, the best student of Rokitansky in Vienna for discovering the cause and prevention of childbirth fever at a time that nursemaids had far better results at obstetrical delivery than physicians.  Contrary to this, Edward Jenner, the best student of John Hunter (anatomist, surgeon, and physician to James Hume), discovered vaccination from the observation that milkmaids did not get smallpox (cowpox was a better alternative).
Only this year a Nobel Prize in Physics was awarded to an Israeli scientist who, working in the US, was unable to convince his associates of his discovery of PSEUDOCRYSTALS. – Diagnostic efficiency of carcinoembryonic antigen and CA125 in the cytological evaluation of effusions. M M Pinto, L H Bernstein, R A Rudolph, D A Brogan, M Rosman Arch Pathol Lab Med 1992; 116(6):626-631 ICID: 825503 Article type: Review article – Immunoradiometric assay of CA 125 in effusions. Comparison with carcinoembryonic antigen. M M Pinto, L H Bernstein, D A Brogan, E Criscuolo Cancer 1987; 59(2):218-222 ICID: 825555 Article type: Review article – Carcinoembryonic antigen in effusions. A diagnostic adjunct to cytology. M M Pinto, L H Bernstein, D A Brogan, E M Criscuolo Acta Cytologica 1987; 31(2):113-118 ICID: 825557

Predictive Modeling

Ovarian Cancer a plot of the CA125 elimination half-life vs the Kullback-Liebler distance

Ca125 half-life vs Kullback Entropy                                                          HL vs Survival KM plot 

Troponin(s) T, I, C  and the contractile apparatus  (contributed by Aviva Lev-Ari, PhD, RN)


For 2012 – 2013 Frontier Contribution in Cardiology on Gene Therapy Solutions for Improving Myocardial Contractility, see

Lev-Ari, A. 8/1/2013 Calcium Cycling (ATPase Pump) in Cardiac Gene Therapy: Inhalable Gene Therapy for Pulmonary Arterial Hypertension and Percutaneous Intra-coronary Artery Infusion for Heart Failure: Contributions by Roger J. Hajjar, MD

http://pharmaceuticalintelligence.com/2013/08/01/calcium-molecule-in-cardiac-gene-therapy-inhalable-gene-therapy-for-pulmonary-arterial-hypertension-and-percutaneous-intra-coronary-artery-infusion-for-heart-failure-contributions-by-roger-j-hajjar/

For explanation of Conduction prior to Myocardial Contractility, see

Lev-Ari, A. 4/28/2013 Genetics of Conduction Disease: Atrioventricular (AV) Conduction Disease (block): Gene Mutations – Transcription, Excitability, and Energy Homeostasis

http://pharmaceuticalintelligence.com/2013/04/28/genetics-of-conduction-disease-atrioventricular-av-conduction-disease-block-gene-mutations-transcription-excitability-and-energy-homeostasis/

The contraction of skeletal muscle is triggered by nerve impulses, which stimulate the release of Ca2+ from the sarcoplasmic reticulum—a specialized network of internal membranes, similar to the endoplasmic reticulum, that stores high concentrations of Ca2+ ions. The release of Ca2+ from the sarcoplasmic reticulum increases the concentration of Ca2+ in the cytosol from approximately 10-7 to 10-5 M. The increased Ca2+ concentration signals muscle contraction via the action of two accessory proteins bound to the actin filaments: tropomyosin and troponin (Figure 11.25). Tropomyosin is a fibrous protein that binds lengthwise along the groove of actin filaments. In striated muscle, each tropomyosin molecule is bound to troponin, which is a complex of three polypeptides: troponin C (Ca2+-binding), troponin I (inhibitory), and troponin T (tropomyosin-binding).

  • When the concentration of Ca2+ is low, the complex of the troponins with tropomyosin blocks the interaction of actin and myosin, so the muscle does not contract.
  • At high concentrations, Ca2+ binding to troponin C shifts the position of the complex, relieving this inhibition and allowing contraction to proceed.

Figure 11.25

Association of tropomyosin and troponins with actin filaments. (A) Tropomyosin binds lengthwise along actin filaments and, in striated muscle, is associated with a complex of three troponins: troponin I (TnI), troponin C (TnC), and troponin T (TnT). In (more…)
Contractile Assemblies of Actin and Myosin in Nonmuscle Cells

Contractile assemblies of actin and myosin, resembling small-scale versions of muscle fibers, are present also in nonmuscle cells. As in muscle, the actin filaments in these contractile assemblies are interdigitated with bipolar filaments of myosin II, consisting of 15 to 20 myosin II molecules, which produce contraction by sliding the actin filaments relative to one another (Figure 11.26). The actin filaments in contractile bundles in nonmuscle cells are also associated with tropomyosin, which facilitates their interaction with myosin II, probably by competing with filamin for binding sites on actin.

Figure 11.26

Contractile assemblies in nonmuscle cells. Bipolar filaments of myosin II produce contraction by sliding actin filaments in opposite directions.

Two examples of contractile assemblies in nonmuscle cells, stress fibers and adhesion belts, were discussed earlier with respect to attachment of the actin cytoskeleton to regions of cell-substrate and cell-cell contacts (see Figures 11.13 and 11.14). The contraction of stress fibers produces tension across the cell, allowing the cell to pull on a substrate (e.g., the extracellular matrix) to which it is anchored. The contraction of adhesion belts alters the shape of epithelial cell sheets: a process that is particularly important during embryonic development, when sheets of epithelial cells fold into structures such as tubes.

The most dramatic example of actin-myosin contraction in nonmuscle cells, however, is provided by cytokinesis—the division of a cell into two following mitosis (Figure 11.27). Toward the end of mitosis in animal cells, a contractile ring consisting of actin filaments and myosin II assembles just underneath the plasma membrane. Its contraction pulls the plasma membrane progressively inward, constricting the center of the cell and pinching it in two. Interestingly, the thickness of the contractile ring remains constant as it contracts, implying that actin filaments disassemble as contraction proceeds. The ring then disperses completely following cell division.

Figure 11.27

Cytokinesis. Following completion of mitosis (nuclear division), a contractile ring consisting of actin filaments and myosin II divides the cell in two.

http://www.ncbi.nlm.nih.gov/books/NBK9961/

2.  Use of Troponin(s) in Diagnosis

Troponins T and I are released into the circulation at the time of an acute coronary syndrome (ACS).  Troponin T was first introduced by Roche (developed in Germany) for the Roche platform as a superior biomarker for identifying acute myocardial infarction (AMI), because of a monoclonal specificity to the cardiac troponin T.  It could not be measured on any other platform (limited license patent), so the Washington University Clinical Chemistry group developed a myocardiocyte specific troponin I that quickly became widely available to Beckman, and was adapted to other instruments.  This was intended to replace the CK isoenzyme MB, that is highly elevated in rhabdomyolysis associated with sepsis or with anesthesia in special cases.

The troponins I and T had a tenfold scale difference, and the Receiver Operator Curve Generated cutoff was accurate for AMI, but had significant elevation with end-stage renal disease.  The industry worked in concert to develop a high sensitivity assay for each because there were some missed AMIs just below the ROC cutoff, which could be interpreted as Plaque Rupture.  However, the concept of plaque rupture had to be reconsidered, and we are left with type1 and type 2 AMI (disregarding the case of post PCI or CABG related).   This led to the current establishment of 3 standard deviations above the lowest measureable level at 10% coefficient of variation.  This has been discussed sufficiently elsewhere.  It did introduce a problem in the use of the test as a “silver bullet” once the finer distinctions aqnd the interest in using the test for prognosis as well as diagnosis.   This is where the use of another protein associated with heart failure came into play – either the B type natriuretic peptide, or its propeptide, N-terminal pro BNP.  The prognostic value of using these markers, secreted by the HEART and acting on the kidneys (sodium reabsorption) has proved useful.  But there has not been a multivariate refinement of the use of a two biomarker approach.  In the following part D, I illustrate what can be done with an algorithmic approach to multiple markers.

Software Agent for Diagnosis of AMI

Isaac E. Mayzlin, Ph.D., David Mayzlin, Larry H. Bernstein, M.D. The so called gold standard of proof of a method is considered the Receiver-Operating Characteristic Curve, developed for detecting “enemy planes or missiles”, and adopted first by radiologists in medicine.  This matches the correct “hits” to the actual calssification and it is generally taught as a plot of sensitivity vs (1 – specifity).  But what if you had no “training” variable?  Work inspired by Eugene Rypka’s bacterial classification led to Rosser Rudolph’s application of the Entropy of Shannon and Weaver to identify meaningful information, referring to what was Kullback-Liebler distance as “effective information”.  This allowed Rudolph and Bernstein to classify using disease biomarkers obtaing the same results as the ROC curve using an apl program.  The same data set was used by Bernstein, Adan et al. previously, and was again used by Izaak Mayzlin from University of Moscow with a new wrinkle.  Dr. Mayzlin created a neural network (Maynet), and then did a traditional NN with training on the data, and also clustered the data using geometric distance clustering and trained on the clusters.  It was interesting to see that the optimum cluster separation was closely related to the number of classes and the accuracy of classification.  An earlier simpler model using the slope of the MB isoenzyme increase and percent of total CK activity was perhaps related to Burton Sobel’s work on CK-MB disappearance rate for infarct size. The main process consists of three successive steps: (1)       clustering performed on training data set, (2)       neural network’s training on clusters from previous step, and (3)       classifier’s accuracy evaluation on testing data. The classifier in this research will be the ANN, created on step 2, with output in the range [0,1], that provides binary result (1 – AMI, 0 – not AMI), using decision point 0.5. Table  1.  Effect  of  selection  of  maximum  distance  on  the  number  of  classes  formed  and  on  the accuracy of recognition by ANN

Clustering Distance Factor F(D = F * R) Number ofClasses Number of Nodes in The Hidden Layers Number of Misrecognized Patterns inThe TestingSet of 43 Percent ofMisrecognized
10.90.80.7 2414135 1,  02,  03,  01,  02,  03,  0 3,  2 3,  2 121121 1 1 2.34.62.32.34.62.3 2.3 2.3

– Creatine kinase B-subunit activity in serum in cases of suspected myocardial infarction: a prediction model based on the slope of MB increase and percentage CK-MB activity. L H Bernstein, G Reynoso Clin Chem 1983; 29(3):590-592 ICID: 825549 – Diagnosis of acute myocardial infarction from two measurements of creatine kinase isoenzyme MB with use of nonparametric probability estimation. L H Bernstein, I J Good, G I Holtzman, M L Deaton, J Babb.  Clin Chem 1989; 35(3):444-447 ICID: 825570 – Information induction for predicting acute myocardial infarction. R A Rudolph, L H Bernstein, J Babb. Clin Chem 1988; 34(10):2031-2038 ICID: 825568

Related articles

Related articles published on this Open Access Online Scientific Journal, include the following:

Calcium Cycling (ATPase Pump) in Cardiac Gene Therapy: Inhalable Gene Therapy for Pulmonary Arterial Hypertension and Percutaneous Intra-coronary Artery Infusion for Heart Failure: Contributions by Roger J. Hajjar, MD

Aviva Lev-Ari, PhD, RN 8/1/2013

http://pharmaceuticalintelligence.com/2013/08/01/calcium-molecule-in-cardiac-gene-therapy-inhalable-gene-therapy-for-pulmonary-arterial-hypertension-and-percutaneous-intra-coronary-artery-infusion-for-heart-failure-contributions-by-roger-j-hajjar/

High-Sensitivity Cardiac Troponin Assays- Preparing the United States for High-Sensitivity Cardiac Troponin Assays

Larry Bernstein, MD, FCAP 6/13/2013

http://pharmaceuticalintelligence.com/2013/06/13/high-sensitivity-cardiac-troponin-assays/

Dealing with the Use of the High Sensitivity Troponin (hs cTn) Assays

Larry Bernstein and Aviva Lev-Ari  5/18/2013

http://pharmaceuticalintelligence.com/2013/05/18/dealing-with-the-use-of-the-hs-ctn-assays/

Acute Chest Pain/ER Admission: Three Emerging Alternatives to Angiography and PCI – Corus CAD, hs cTn, CCTA

Aviva Lev-Ari  3/10/2013

http://pharmaceuticalintelligence.com/2013/03/10/acute-chest-painer-admission-three-emerging-alternatives-to-angiography-and-pci/

  • Redberg’s conclusions are correct for the initial screening. The issue has been whether to do further testing for low or intermediate risk patients.
  • The most intriguing finding that is not at all surprising is that the CCTA added very little in the suspect group with small or moderate risk.
  • The ultra sensitive troponin threw the ROC out the window
  • The improved assay does pick up minor elevations of troponin in the absence of MI.

Critical Care | Abstract | Cardiac ischemia in patients with septic …
Aviva Lev-Ari  6/26/2013
http://pharmaceuticalintelligence.com/2013/06/26/critical-care-abstract-cardiac-ischemia-in-patients-with-septic/

  • refer to:  Cardiac ischemia in patients with septic shock randomized to vasopressin or norepinephrine

Mehta S, Granton J,  Gordon AC, Cook DJ, et al.
Critical Care 2013, 17:R117   http://dx.doi.org/10.1186/cc12789
Troponin and CK levels, and rates of ischemic ECG changes were similar in the VP and NE groups. In multivariable analysis

  • only APACHE II was associated with 28-day mortality (OR 1.07, 95% CI 1.01-1.14, p=0.033).

Assessing Cardiovascular Disease with Biomarkers

Larry H Bernstein, MD, FCAP 12/25/2012

http://pharmaceuticalintelligence.com/2012/12/25/assessing-cardiovascular-disease-with-biomarkers/

Vascular Medicine and Biology: CLASSIFICATION OF FAST ACTING THERAPY FOR PATIENTS AT HIGH RISK FOR MACROVASCULAR EVENTS Macrovascular Disease – Therapeutic Potential of cEPCs

Aviva Lev-Ari, PhD, RN 8/24/2012

http://pharmaceuticalintelligence.com/2012/08/24/vascular-medicine-and-biology-classification-of-fast-acting-therapy-for-patients-at-high-risk-for-macrovascular-events-macrovascular-disease-therapeutic-potential-of-cepcs/

 PENDING Integration

  • ‘Ryanopathy’: causes and manifestations of RyR2 dysfunction in heart failureCardiovasc Res. 2013;98:240-247,
  • Up-regulation of sarcoplasmic reticulum Ca2+ uptake leads to cardiac hypertrophy, contractile dysfunction and early mortality in mice deficient in CASQ2Cardiovasc Res. 2013;98:297-306,
  • Myocardial Delivery of Stromal Cell-Derived Factor 1 in Patients With Ischemic Heart Disease: Safe and PromisingCirc. Res.. 2013;112:746-747,
  • Circulation Research Thematic Synopsis: Cardiovascular GeneticsCirc. Res.. 2013;112:e34-e50,
  • Gene and cytokine therapy for heart failure: molecular mechanisms in the improvement of cardiac functionAm. J. Physiol. Heart Circ. Physiol.. 2012;303:H501-H512,
  • Ryanodine Receptor Phosphorylation and Heart Failure: Phasing Out S2808 and “Criminalizing” S2814Circ. Res.. 2012;110:1398-1402,

http://circres.ahajournals.org/content/110/5/777.figures-only

Read Full Post »

Subtitle: Nitric Oxide, Peroxinitrite, and NO donors in Renal Function Loss

Curator and Author: Larry H. Bernstein, MD, FCAP

The Nitric Oxide and Renal is presented in FOUR parts:

Part I: The Amazing Structure and Adaptive Functioning of the Kidneys: Nitric Oxide

Part II: Nitric Oxide and iNOS have Key Roles in Kidney Diseases

Part III: The Molecular Biology of Renal Disorders: Nitric Oxide

Part IV: New Insights on Nitric Oxide donors 

Conclusion to this series is presented in

The Essential Role of Nitric Oxide and Therapeutic NO Donor Targets in Renal Pharmacotherapy

Part II.  Oxidative Stress and  Regulating a Balance of Redox Potential is Central to Disordered Kidney Function

We have already described the key role that nitric oxide and the NO synthases play in reduction of oxidative stress. The balance that has to be regulated between pro- and anti-oxidative as well as inflammatory elements necessary for renal function, critically involves the circulation of the kidney. It poses an inherent risk in the kidney, where the existence of a rich circulatory and high energy cortical outer region surrounds a medullary inner portion that is engaged in the  retention of water, the active transport of glucose, urea and uric acid nitrogenous waste, mineral balance and pH.  In this discussion we shall look at kidney function, NO, and the large energy fluxes in the medullary tubules and interstitium.   This is a continuation of of a series of posts on NO and NO related disorders, and the kidney in particular.

Part IIa. Nitric Oxide role in renal tubular epithelial cell function

Tubulointerstitial Nephritides
As part of the exponential growth in our understanding of nitric oxide (NO) in health and disease over the past 2 decades, the kidney has become appreciated as a major site where NO may play a number of important roles. Although earlier work on the kidney focused more on effects of NO at the level of larger blood vessels and glomeruli, there has been a rapidly growing body of work showing critical roles for NO in tubulointerstitial disease. In this review we discuss some of the recent contributions to this important field.
Mattana J, Adamidis A, Singhal PC. Nitric oxide and tubulointerstitial nephritides. Seminars in Nephrology 2004; 24(4):345-353.
Nitric oxide donors and renal tubular (subepithelial) matrix
Nitric oxide (NO) and its metabolite, peroxynitrite (ONOO-), are involved in renal tubular cell injury. If NO/ONOO- has an effect to reduce cell adhesion to the basement membrane, does this effect contribute to tubular obstruction and would it be partially responsible for the harmful effect of NO on the tubular epithelium during acute renal failure (ARF)?
Wangsiripaisan A, et al. examined the effect of the NO donors

  1. (z)-1-[2-(2-aminoethyl)-N-(2-ammonioethyl)amino]diazen-1- ium-1, 2-diolate (DETA/NO),
  2. spermine NONOate (SpNO), and
  3. the ONOO- donor 3-morpholinosydnonimine (SIN-1)

on cell-matrix adhesion to collagen types I and IV, and also fibronectin
using three renal tubular epithelial cell lines:

  1. LLC-PK1,
  2. BSC-1,
  3. OK.

It was only the exposure to SIN-1 that caused a dose-dependent impairment in cell-matrix adhesion. Similar results were obtained in the different cell types and matrix proteins. The effect of SIN-1 (500 microM) on LLC-PK1 cell adhesion was not associated with either cell death or alteration of matrix protein and was attenuated by either

  1. the NO scavenger 2-(4-carboxyphenyl)-4,4,5,5-tetramethylimidazoline-1-oxyl-3-oxide,
  2. the superoxide scavenger superoxide dismutase, or
  3. the ONOO- scavenger uric acid in a dose-dependent manner.

These investigators concluded in this seminal paper that ONOO- generated in the tubular epithelium during ischemia/reperfusion has the potential to impair the adhesion properties of tubular cells, which then may contribute to the tubular obstruction in ARF.

Wangsiripaisan A, Gengaro PE, Nemenoff RA, Ling H, et al. Effect of nitric oxide donors on renal tubular epithelial cell-matrix adhesion. Kidney Int 1999; 55(6):2281-8.

The reaction mechanism of Nitric oxide synthase

The reaction mechanism of Nitric oxide synthase (Photo credit: Wikipedia)

Nitric Oxide Synthase

Nitric Oxide Synthase (Photo credit: Wikipedia)

English: Reactions leading to generation of Ni...

English: Reactions leading to generation of Nitric Oxide and Reactive Nitrogen Species. Novo and Parola Fibrogenesis & Tissue Repair 2008 1:5 doi:10.1186/1755-1536-1-5 (Photo credit: Wikipedia)

Coexpressed Nitric Oxide Synthase and Apical β1 Integrins 

In sepsis-induced acute renal failure, actin cytoskeletal alterations result in shedding of proximal tubule epithelial cells (PTEC) and tubular obstruction. This study examined the hypothesis that inflammatory cytokines, released early in sepsis, cause PTEC cytoskeletal damage and alter integrin-dependent cell-matrix adhesion. The question of whether the intermediate nitric oxide (NO) modulates these cytokine effects was also examined.

After exposure of human PTEC to

  1. tumor necrosis factor-α,
  2. interleukin-1α, and
  3. interferon-γ,

the actin cytoskeleton was disrupted and cells became elongated, with extension of long filopodial processes.

Cytokines induced shedding of

  • viable,
  • apoptotic, and
  • necrotic PTEC,

which was dependent on NO synthesized by inducible NO synthase (iNOS) produced as a result of cytokine actions on PTEC.

Basolateral exposure of polarized PTEC monolayers to cytokines induced maximal NO-dependent cell shedding, mediated in part through NO effects on cGMP. Cell shedding was accompanied by dispersal of

  • basolateral β1 integrins and
  • E-cadherin,

with corresponding upregulation of integrin expression in clusters of cells elevated above the epithelial monolayer.

These cells demonstrated coexpression of iNOS and apically redistributed β1 integrins. These authors point out that the major ligand involved in cell anchorage was laminin, probably through interactions with the integrin α3β1. This interaction was downregulated by cytokines but was not dependent on NO. They posulate a mechanism by which inflammatory cytokines induce PTEC damage in sepsis, in the absence of hypotension and ischemia.

Glynne PA, Picot J and Evans TJ. Coexpressed Nitric Oxide Synthase and Apical β1 Integrins Influence Tubule Cell Adhesion after Cytokine-Induced Injury. JASN 2001; 12(11): 2370-2383.
Potentiation by Nitric Oxide of Apoptosis in Renal Proximal Tubule Cells

Proximal tubular epithelial cells (PTEC) exhibit a high sensitivity to undergo apoptosis in response to proinflammatory stimuli and immunosuppressors and participate in the onset of several renal diseases. This study examined the expression of inducible nitric oxide (NO) synthase after challenge of PTEC with bacterial cell wall molecules and inflammatory cytokines and analyzed the pathways that lead to apoptosis in these cells by measuring changes in the mitochondrial transmembrane potential and caspase activation.

The data show that the apoptotic effects of proinflammatory stimuli mainly were due to the expression of inducible NO synthase. Cyclosporin A and FK506 inhibited partially NO synthesis. However, both NO and immunosuppressors induced apoptosis, probably through a common mechanism that involved the irreversible opening of the mitochondrial permeability transition pore. Activation of caspases 3 and 7 was observed in cells treated with high doses of NO and with moderate concentrations of immunosuppressors. The conclusion is that the cooperation between NO and immunosuppressors that induce apoptosis in PTEC might contribute to the renal toxicity observed in the course of immunosuppressive therapy.

HORTELANO S, CASTILLA M, TORRES AM, TEJEDOR A, and BOSCÁ L. Potentiation by Nitric Oxide of Cyclosporin A and FK506- Induced Apoptosis in Renal Proximal Tubule Cells. J Am Soc Nephrol 2000; 11: 2315–2323.

Part IIb. Related studies with ROS and/or RNS on nonrenal epithelial cells

Reactive nitrogen species block cell cycle re-entry
Endogenous sources of reactive nitrogen species (RNS) act as second messengers in a variety of cell signaling events, whereas environmental sources of RNS like nitrogen dioxide (NO2) inhibit cell survival and growth through covalent modification of cellular macromolecules.

Murine type II alveolar cells arrested in G0 by serum deprivation were exposed to either NO2 or SIN-1, a generator of RNS, during cell cycle re-entry. In serum-stimulated cells, RNS blocked cyclin D1 gene expression, resulting in cell cycle arrest at the boundary between G0 and G1. Dichlorofluorescin diacetate (DCF) fluorescence indicated that RNS induced sustained production of intracellular hydrogen peroxide (H2O2), which normally is produced only transiently in response to serum growth factors.

Loading cells with catalase prevented enhanced DCF fluorescence and rescued cyclin D1 expression and S phase entry.

These studies indicate environmental RNS interfere with cell cycle re-entry through an H2O2-dependent mechanism that influences expression of cyclin D1 and progression from G0 to the G1 phase of the cell cycle.
Yuan Z, Schellekens H, Warner L, Janssen-Heininger Y, Burch P, Heintz NH. Reactive nitrogen species block cell cycle re-entry through sustained production of hydrogen peroxide. Am J Respir Cell Mol Biol. 2003;28(6):705-12. Epub 2003 Jan 10.
Peroxynitrite modulates MnSOD gene expression

Peroxynitrite (ONOO-) is a strong oxidant derived from nitric oxide (‘NO) and superoxide (O2.-), reactive nitrogen (RNS) and oxygen species (ROS) present in inflamed tissue. Other oxidant stresses, e.g., TNF-alpha and hyperoxia, induce mitochondrial, manganese-containing superoxide dismutase (MnSOD) gene expression.

3-morpholinosydnonimine HCI (SIN-1) (10 or 1000 microM)  increased MnSOD mRNA, but did not change hypoxanthine guanine phosphoribosyl transferase (HPRT) mRNA.
Authentic peroxynitrite (ONOO ) (100-500 microM) also increased MnSOD mRNA but did not change constitutive HPRT mRNA expression.  ONOO stimulated luciferase gene expression driven by a 2.5 kb fragment of the rat MnSOD gene 5′ promoter region.

MnSOD gene induction due to ONOO- was inhibited effectively by L-cysteine (10 mM) and partially inhibited by N-acetyl cysteine (50 mM) or pyrrole dithiocarbamate (10 mM).
.NO from 1-propanamine, 3-(2-hydroxy-2-nitroso-1-propylhydrazine) (PAPA NONOate) (100 or 1000 microM) did not change MnSOD or HPRT mRNA, nor did either H202 or NO2-, breakdown products of SIN-1 and ONOO, have any effect on MnSOD mRNA expression; ONOO- and SIN-1 also did not increase detectable MnSOD protein content or increase MnSOD enzymatic activity.
Nevertheless, increased steady state [O2.-] in the presence of .NO yields ONOO , and ONOO has direct, stimulatory effects on MnSOD transcript expression driven at the MnSOD gene 5′ promoter region inhibited completely by L-cysteine and partly by N-acetyl cysteine in lung epithelial cells. This raises a question of whether the same effect is seen in renal tubular epithelium.

Jackson RM, Parish G, Helton ES. Peroxynitrite modulates MnSOD gene expression in lung epithelial cells. Free Radic Biol Med. 1998; 25(4-5):463-72.

Comparative impacts of glutathione peroxidase-1 gene knockout on oxidative stress

Selenium-dependent glutathione peroxidase-1 (GPX1) protects against reactive-oxygen-species (ROS)-induced oxidative stress in vivo, but its role in coping with reactive nitrogen species (RNS) is unclear. Primary hepatocytes were isolated from GPX1-knockout (KO) and wild-type (WT) mice to test protection of GPX1 against cytotoxicity of

  • superoxide generator diquat (DQ),
  • NO donor S-nitroso-N-acetyl-penicillamine (SNAP) and
  • peroxynitrite generator 3-morpholinosydnonimine (SIN-1).

Treating cells with SNAP (0.1 or 0.25 mM) in addition to DQ produced synergistic cytotoxicity that minimized differences in apoptotic cell death and oxidative injuries between the KO and WT cells. Less protein nitrotyrosine was induced by 0.05-0.5 mM DQ+0.25 mM SNAP in the KO than in the WT cells.

Total GPX activity in the WT cells was reduced by 65 and 25% by 0.5 mM DQ+0.1 mM SNAP and 0.5 mM DQ, respectively.

Decreases in Cu,Zn-superoxide dismutase (SOD) activity and increases in Mn-SOD activity in response to DQ or DQ+SNAP were greater in the KO cells than in the WT cells.

The study indicates GPX1 was more effective in protecting hepatocytes against oxidative injuries mediated by ROS alone than by ROS and RNS together, and knockout of GPX1 did not enhance cell susceptibility to RNS-associated cytotoxicity. Instead, it attenuated protein nitration induced by DQ+SNAP.
To better understand the mechanism(s) underlying nitric oxide (. NO)-mediated toxicity, in the presence and absence of concomitant oxidant exposure, postmitotic terminally differentiated NT2N cells, which are incapable of producing . NO, were exposed to PAPA-NONOate (PAPA/NO) and 3-morpholinosydnonimine (SIN-1).
Exposure to SIN-1, which generated peroxynitrite (ONOO) in the range of 25-750 nM/min, produced a concentration- and time-dependent delayed cell death.

In contrast, a critical threshold concentration (>440 nM/min) was required for . NO to produce significant cell injury.
There is a largely necrotic lesion after ONOO exposure and an apoptotic-like morphology after . NO exposure. Cellular levels of reduced thiols correlated with cell death, and pretreatment with N-acetylcysteine (NAC) fully protected from cell death in either PAPA/NO or SIN-1 exposure.

NAC given within the first 3 h posttreatment further delayed cell death and increased the intracellular thiol level in SIN-1 but not . NO-exposed cells.
Cell injury from . NO was independent of cGMP, caspases, and superoxide or peroxynitrite formation.
Overall, exposure of non-. NO-producing cells to . NO or peroxynitrite results in delayed cell death, which, although occurring by different mechanisms,
appears to be mediated by the loss of intracellular redox balance.

Gow AJ, Chen Q, Gole M, Themistocleous M, Lee VM, Ischiropoulos H. Two distinct mechanisms of nitric oxide-mediated neuronal cell death show thiol dependency. Am J Physiol Cell Physiol. 2000; 278(6):C1099-107.

Oxidative stress

Oxidative stress (Photo credit: Wikipedia)

English: Binding of CAPON results in a reducti...

English: Binding of CAPON results in a reduction of NMDA receptor/nitric oxide synthase (NOS) complexes, leading to decreased NMDA receptor–gated calcium influx and a catalytically inactive nitric oxide synthase. Overexpression of either the full-length or the novel shortened CAPON isoform as reported by Brzustowicz and colleagues is, therefore, predicted to lead to impaired NMDA receptor–mediated glutamate neurotransmission. (Photo credit: Wikipedia)

NO2 effect on phosphatidyl choline

Nitrogen dioxide (NO2) inhalation affects the extracellular surfactant as well as the structure and function of type II pneumocytes. The studies had differences in oxidant concentration, duration of exposure, and mode of NO2 application.

This study evaluated the influence of the NO2 application mode on the phospholipid metabolism of type II pneumocytes . Rats were exposed to identical NO2 body doses (720 ppm x h), which were applied continuously (10 ppm for 3 d), intermittently (10 ppm for 8 h per day, for 9 d), and repeatedly (10 ppm for 3 d, 28 d rest, and then 10 ppm for 3 d). Immediately after exposure, type II cells were isolated and evaluated for

  • cell yield,
  • vitality,
  • phosphatidylcholine (PC) synthesis, and
  • secretion.

Type II pneumocyte cell yield was only increased from animals that had been continuously exposed to NO2, but vitality of the isolated type II pneumocytes was not affected by the NO2 exposure modes. Continuous application of 720 ppm x h NO2 resulted in increased activity of the cytidine-5-diphosphate (CDP)-choline pathway.

  • After continuous NO2 application,
  • specific activity of choline kinase,
  • cytidine triphosphate (CTP):cholinephosphate cytidylyltransferase,
  • uptake of choline, and
  • pool sizes of CDP-choline and PC

were significantly increased over those of controls.

Intermittent application of this NO2 body dose provoked less increase in PC synthesis and the synthesis parameters were comparable to those for cells from control animals after repeated exposure. Whereas PC synthesis in type II cells was stimulated by NO2, their secretory activity was reduced. Continuous exposure reduced the secretory activity most, whereas intermittent exposure nonsignificantly reduced this activity as compared with that of controls. The repeated application of NO2 produced no differences.

The authors conclude that type II pneumocytes adapt to NO2 atmospheres depending on the mode of its application, at least for the metabolism of PC and its secretion from isolated type II pneumocytes.   Further studies are necessary to determine whether additional metabolic activities will also adapt to NO2 atmospheres, and if these observations are specific for NO2 or represent effects generally due to oxidants.  The reader, however, asks whether this effect could also be found in renal epithelial cells, for which PC is not considered vital as for type II pneumocytes and possibly related to surfactant activity in the lung.

Müller B, Seifart C, von Wichert P, Barth PJ. Adaptation of rat type II pneumocytes to NO2: effects of NO2 application mode on phosphatidylcholine metabolism. Am J Respir Cell Mol Biol. 1998; 18(5): 712-20.

iNOS involved in immediate response to anaphylaxis

The generation of large quantities of nitric oxide (NO) is implicated in the pathogenesis of anaphylactic shock. The source of NO, however, has not been established and conflicting results have been obtained when investigators have tried to inhibit its production in anaphylaxis.

This study analyzed the expression of inducible nitric oxide synthase (iNOS) and endothelial nitric oxide synthase (eNOS) in a mouse model of anaphylaxis.

BALB/c mice were sensitized and challenged with ovalbumin to induce anaphylaxis. Tissues were removed from the heart and lungs, and blood was drawn at different time points during the first 48 hours after induction of anaphylaxis. The Griess assay was used to measure nitric oxide generation. Nitric oxide synthase expression was examined by reverse transcriptase polymerase chain reaction and immunohistochemistry.

A significant increase in iNOS mRNA expression and nitric oxide production was evident as early as 10 to 30 minutes after allergen challenge in both heart and lungs. In contrast, expression of eNOS mRNA was not altered during the course of the experiment.

The results support involvement of iNOS in the immediate physiological response of anaphylaxis.

Sade K, Schwartz IF, Etkin S, Schwartzenberg S, et al. Expression of Inducible Nitric Oxide
Synthase in a Mouse Model of Anaphylaxis. J Investig Allergol Clin Immunol 2007; 17(6):379-385.

Part IIc. Additional Nonrenal Related NO References

Nitrogen dioxide induces death in lung epithelial cells in a density-dependent manner.
Persinger RL, Blay WM, Heintz NH, Hemenway DR, Janssen-Heininger YM.
Am J Respir Cell Mol Biol. 2001 May;24(5):583-90.
PMID: 11350828 [PubMed – indexed for MEDLINE] Free Article
2.
Molecular mechanisms of nitrogen dioxide induced epithelial injury in the lung.
Persinger RL, Poynter ME, Ckless K, Janssen-Heininger YM.
Mol Cell Biochem. 2002 May-Jun;234-235(1-2):71-80. Review.
PMID: 12162462 [PubMed – indexed for MEDLINE]
3.
Nitric oxide and peroxynitrite-mediated pulmonary cell death.
Gow AJ, Thom SR, Ischiropoulos H.
Am J Physiol. 1998 Jan;274(1 Pt 1):L112-8.
PMID: 9458808 [PubMed – indexed for MEDLINE] Free Article
4.
Mitogen-activated protein kinases mediate peroxynitrite-induced cell death in human bronchial epithelial cells.
Nabeyrat E, Jones GE, Fenwick PS, Barnes PJ, Donnelly LE.
Am J Physiol Lung Cell Mol Physiol. 2003 Jun;284(6):L1112-20. Epub 2003 Feb 21.
PMID: 12598225 [PubMed – indexed for MEDLINE] Free Article
5.
Peroxynitrite inhibits inducible (type 2) nitric oxide synthase in murine lung epithelial cells in vitro.
Robinson VK, Sato E, Nelson DK, Camhi SL, Robbins RA, Hoyt JC.
Free Radic Biol Med. 2001 May 1;30(9):986-91.
PMID: 11316578 [PubMed – indexed for MEDLINE]
6.
Nitric oxide-mediated chondrocyte cell death requires the generation of additional reactive oxygen species.
Del Carlo M Jr, Loeser RF.
Arthritis Rheum. 2002 Feb;46(2):394-403.
PMID: 11840442 [PubMed – indexed for MEDLINE]
7.
Colon epithelial cell death in 2,4,6-trinitrobenzenesulfonic acid-induced colitis is associated with increased inducible nitric-oxide synthase expression and peroxynitrite production.
Yue G, Lai PS, Yin K, Sun FF, Nagele RG, Liu X, Linask KK, Wang C, Lin KT, Wong PY.
J Pharmacol Exp Ther. 2001 Jun;297(3):915-25.
PMID: 11356911 [PubMed – indexed for MEDLINE] Free Article

Summary

In this piece I have covered the conflicting roles of endogenous end inducible nitric oxide (eNOS and iNOS) in the reaction to reactive oxygen and nitrogen stress (ROS, RNS), and many experiments directed at sorting out these effects using continuous and intermittent  delivery of NO2, production of ONOO- from .NO, and  several agents that are used to upregulate and downregulate the underlying mechanism of response.  These investigations are not only carried out in experiments on renal function and apoptosis, but also there are similar examples taken from studies of lung and liver.  This forms a backdrop for the assessment of renal diseases:

  • immune related
  • acute traumatic injury
  • chronic

The continuation of the discussion will be in essays that follow.

A scheme of the shear stress-induced EDRF-NO m...

A scheme of the shear stress-induced EDRF-NO mechanism (Photo credit: Wikipedia)

Read Full Post »

The Molecular Biology of Renal Disorders: Nitric Oxide – Part III

Subtitle: Nitric Oxide, Peroxinitrite, and NO donors in Renal Function Loss 

Curator and Author: Larry H. Bernstein, MD, FCAP

Four Parts present this topic:

Part I: The Amazing Structure and Adaptive Functioning of the Kidneys: Nitric Oxide

Part II: Nitric Oxide and iNOS have Key Roles in Kidney Diseases

Part III: The Molecular Biology of Renal Disorders: Nitric Oxide

Part IV: New Insights on Nitric Oxide donors 

Conclusion to this series is presented in

The Essential Role of Nitric Oxide and Therapeutic NO Donor Targets in Renal Pharmacotherapy

Part III.  The Molecular Biology of Renal Disorders

Renal function affecting urine formation, electrolyte balance, nitrogen excretion, and vascular tone becomes acutely and/or chronically dysfunctional in metabolic, systemic inflammatory and immunological diseases of man. We have already described the key role that nitric oxide and the NO synthases play in reduction of oxidative stress, and we have seen that a balance has to be struck between pro- and anti-oxidative as well as inflammatory elements for avoidance of diseases, specifically involving the circulation. Similar stresses are important in the circulation, in liver disease, in pulmonary function, and in neurodegenerative disease.  In this discussion we continue to look at kidney function, NO and NO donors. This is an extension of a series of posts on NO and NO related disorders.

Part IIIa. Acute renal failure

Acute renal failure (ARF), characterized by sudden loss of the ability of the kidneys to

  1. excrete wastes,
  2. concentrate urine,
  3. conserve electrolytes, and
  4. maintain fluid balance,

is a frequent clinical problem, particularly in the intensive care unit, where it is associated with a mortality of between 50% and 80%.

This clinical entity was described as an acute loss of kidney function that occurred in severely injured crush victims because of histological evidence for patchy necrosis of renal tubules at autopsy. In the clinical setting, the terms ATN and acute renal failure (ARF) are frequently used interchangeably. However, ARF does not include increases in blood urea due to reversible renal vasoconstriction (prerenal azotemia) or urinary tract obstruction (postrenal azotemia). Acute hemodialysis was first used clinically during the Korean War in 1950 to treat military casualties, and this led to a decrease in mortality of the ARF clinical syndrome from about 90% to about 50%.

In the half century that has since passed, much has been learned about the pathogenesis of ischemic and nephrotoxic ARF in experimental models, but there has been very little improvement in mortality. This may be explained by changing demographics: the age of patients with ARF continues to rise, and comorbid diseases are increasingly common in this population. Both factors may obscure any increased survival related to improved critical care.

Examining the incidence of ARF in several military conflicts does, however, provide some optimism. The incidence of ARF in seriously injured casualties decreased between World War II and the Korean War, and again between that war and the Vietnam War, despite the lack of any obvious difference in the severity of the injuries. What was different was the rapidity of the fluid resuscitation of the patients. Fluid resuscitation on the battlefield with the rapid evacuation of the casualties to hospitals by helicopter began during the Korean War and was optimized further during the Vietnam War. For seriously injured casualties the incidence of ischemic ARF was one in 200 in the Korean War and one in 600 in the Vietnam War. This historical sequence of events suggests that early intervention could prevent the occurrence of ARF, at least in military casualties.

In experimental studies it has been shown that progression from an azotemic state associated with

  • renal vasoconstriction and
  • intact tubular function (prerenal azotemia)

to established ARF with tubular dysfunction occurs if the renal ischemia is prolonged. Moreover, early intervention with fluid resuscitation was shown to prevent the progression from prerenal azotemia to established ARF.

Diagnostic evaluation of ARF

One important question, therefore, is how to assure that an early diagnosis of acute renal vasoconstriction can be made prior to the occurrence of tubular dysfunction, thus providing the potential to prevent progression to established ARF. In this regard, past diagnostics relied on observation of the patient response to a fluid challenge:

  • decreasing levels of blood urea nitrogen (BUN) indicated the presence of reversible vasoconstriction, while
  • uncontrolled accumulation of nitrogenous waste products, i.e., BUN and serum creatinine, indicated established ARF.

This approach, however, frequently led to massive fluid overload in the ARF patient with resultant pulmonary congestion, hypoxia, and premature need for mechanical ventilatory support and/or hemodialysis. On this background the focus turned to an evaluation of urine sediment and urine chemistries to differentiate between renal vasoconstriction with intact tubular function and established ARF. It was well established that if tubular function was intact, renal vaso-constriction was associated with enhanced tubular sodium reabsorption. Specifically, the fraction of filtered sodium that is rapidly reabsorbed by normal tubules of the vasoconstricted kidney is greater than 99%. Thus, when nitrogenous wastes, such as creatinine and urea, accumulate in the blood due to a fall in glomerular filtration rate (GFR) secondary to renal vasoconstriction with intact tubular function,

the fractional excretion of filtered sodium (FENa = [(urine sodium × plasma creatinine) / (plasma sodium × urine creatinine)]) is less than 1%.

An exception to this physiological response of the normal kidney to vasoconstriction is when the patient is receiving a diuretic, including mannitol, or has glucosuria, which decreases tubular sodium reabsorption and increases FENa. It has recently been shown in the presence of diuretics that a rate of fractional excretion of urea (FEurea) of less than 35 indicates intact tubular function, thus favoring renal vasoconstriction rather than established ARF as a cause of the azotemia.

Mechanisms of ARF


Based on the foregoing comments, this discussion of mechanisms of ARF will not include nitrogenous-waste accumulation due to renal vasoconstriction with intact tubular function (prerenal azotemia) or urinary tract obstruction (postrenal azotemia). The mechanisms of ARF involve both vascular and tubular factors.

An ischemic insult to the kidney will in general be the cause of the ARF. While a decrease in renal blood flow with diminished oxygen and substrate delivery to the tubule cells is an important ischemic factor, it must be remembered that a relative increase in oxygen demand by the tubule is also a factor in renal ischemia.

Approximately 30–70% of these shed epithelial tubule cells in the urine are viable and can be grown in culture. Recent studies using cellular and molecular techniques have provided information relating to the structural abnormalities of injured renal tubules that occur both in vitro and in vivo.

In vitro studies using chemical anoxia have revealed abnormalities in the proximal tubule cytoskeleton that are associated with translocation of Na+/K+-ATPase from the basolateral to the apical membrane. A comparison of cadaveric transplanted kidneys with delayed versus prompt graft function has also provided important results regarding the role of Na+/K+-ATPase in ischemic renal injury.  This study demonstrated that, compared with kidneys with prompt graft function, those with delayed graft function had a significantly greater cytoplasmic concentration of Na+/K+-ATPase and actin-binding proteins — spectrin (also known as fodrin) and ankyrin — that had translocated from the basolateral membrane to the cytoplasm. Such a translocation of Na+/K+-ATPase from the basolateral membrane to the cytoplasm could explain the decrease in tubular sodium reabsorption that occurs with ARF.

The mechanisms whereby the critical residence of Na+/K+-ATPase in the basolateral membrane, which facilitates vectorial sodium transport, is uncoupled by hypoxia or ischemia have been an important focus of research. The actin-binding proteins, spectrin and ankyrin, serve as substrates for the calcium-activated cysteine protease calpain. In this regard, in vitro studies in proximal tubules have shown a rapid rise in cytosolic calcium concentration during acute hypoxia, which antedates the evidence of tubular injury as assessed by lactic dehydrogenase (LDH) release.  There is further evidence to support the importance of the translocation of Na+/K+-ATPase from the basolateral membrane to the cytoplasm during renal ischemia/reperfusion.

Specifically, calpain-mediated breakdown products of the actin-binding protein spectrin have been shown to occur with renal ischemia. Calpain activity was also demonstrated to be increased during hypoxia in isolated proximal tubules. Measurement of LDH release following calpain inhibition has demonstrated attenuation of hypoxic damage to proximal tubules. There was no evidence in proximal tubules during hypoxia of an increase in cathepsin, another cysteine protease. Further studies demonstrated a calcium-independent pathway for calpain activation during hypoxia. Calpastatin, an endogenous cellular inhibitor of calpain activation, was shown to be diminished during hypoxia in association with the rise in another cysteine protease, caspase. This effect of diminished calpastatin activity could be reversed by caspase inhibition. Proteolytic pathways that may be involved in calpain-mediated proximal tubule cell injury during hypoxia are illustrated. Calcium activation of phospholipase A has also been shown to contribute to renal tubular injury during ischemia.

Location of renal medulla

Location of renal medulla (Photo credit: Wikipedia)

Diagram of renal corpuscle structure

Diagram of renal corpuscle structure (Photo credit: Wikipedia)

English: Reactions leading to generation of Ni...

English: Reactions leading to generation of Nitric Oxide and Reactive Nitrogen Species. Novo and Parola Fibrogenesis & Tissue Repair 2008 1:5 doi:10.1186/1755-1536-1-5 (Photo credit: Wikipedia)

The reaction mechanism of Nitric oxide synthase

The reaction mechanism of Nitric oxide synthase (Photo credit: Wikipedia)

Tubular obstruction in ischemic ARF.


The existence of proteolytic pathways involving cysteine proteases, namely calpain and caspases, may therefore explain the decrease in proximal tubule sodium reabsorption and increased FENa secondary to proteolytic uncoupling of Na+/K+-ATPase from its basolateral membrane anchoring proteins. This tubular perturbation alone, however, does not explain the fall in GFR that leads to nitrogenous-waste retention and thus the rise in BUN and serum creatinine.

Decreased proximal tubule sodium reabsorption may lead to a decreased GFR during ARF. First of all, brush border membranes and cellular debris could provide the substrate for intraluminal obstruction in the highly resistant portion of distal nephrons. In fact, microdissection of individual nephrons of kidneys from patients with ARF demonstrated obstructing casts in distal tubules and collecting ducts. This observation could explain the dilated proximal tubules that are observed upon renal biopsy of ARF kidneys. The intraluminal casts in ARF kidneys stain prominently for Tamm-Horsfall protein (THP), which is produced in the thick ascending limb.

Importantly, THP is secreted into tubular fluid as a monomer but subsequently may become a polymer that forms a gel-like material in the presence of increased luminal Na+ concentration, as occurs in the distal nephron during clinical ARF with the decrease in tubular sodium reabsorption. Thus, the THP polymeric gel in the distal nephron provides an intraluminal environment for distal cast formation involving

  • viable,
  • apoptotic, and
  • necrotic cells.

The loss of the tubular epithelial cell barrier and/or the tight junctions between viable cells during acute renal ischemia could lead to a leak of glomerular filtrate back into the circulation. If this occurs and normally non-reabsorbable substances, such as inulin, leak back into the circulation, then a falsely low GFR will be measured as inulin clearance. It should be noted, however, that the degree of extensive tubular damage observed in experimental studies demonstrating tubular fluid backleak is rarely observed with clinical ARF in humans. Moreover, dextran sieving studies in patients with ARF demonstrated that, at best, only a 10% decrease in GFR could be explained by backleak of filtrate. Cadaveric transplanted kidneys with delayed graft function, however, may have severe tubular necrosis, and thus backleak of glomerular filtration may be more important in this setting.

Inflammation and NO

There is now substantial evidence for the involvement of inflammation in the pathogenesis of the decreased GFR associated with acute renal ischemic injury. In this regard, there is experimental evidence that iNOS may contribute to tubular injury during ARF. Hypoxia in isolated proximal tubules has been shown to increase NO release, and Western blot analysis in ischemic kidney homogenates has demonstrated increased iNOS protein expression. An antisense oligonucleotide was shown to block the upregulation of iNOS and afford functional protection against acute renal ischemia. Moreover, when isolated proximal tubules from iNOS, eNOS, and neuronal NO synthase (nNOS) knockout mice were exposed to hypoxia, only the tubules from the iNOS knockout mice were protected against hypoxia, as assessed by LDH release. The iNOS knockout mice were also shown to have lower mortality during ischemia/reperfusion than wild-type mice. There is also evidence that the scavenging of NO by oxygen radicals produces peroxynitrite that causes tubule damage during ischemia.

  • While iNOS may contribute to ischemic injury of renal tubules, there is evidence that the vascular effect of eNOS in the glomerular afferent arteriole is protective against ischemic injury.
  • In this regard, eNOS knockout mice have been shown to be more sensitive to endotoxin-related injury than normal mice.
  • Moreover, the protective role of vascular eNOS may be more important than the deleterious effect of iNOS at the tubule level during renal ischemia.

The basis for this tentative conclusion is the observation that treatment of mice with the nonspecific NO synthase (NOS) inhibitor L-NAME, which blocks both iNOS and eNOS, worsens renal ischemic injury.

It has also been demonstrated that NO may downregulate eNOS and is a potent inducer of heme oxygenase-1, which has been shown to be cytoprotective against renal injury. The MAPK pathway also appears to be involved in renal oxidant injury. Activation of extracellular signal–regulated kinase (ERK) or inhibition of JNK has been shown to ameliorate oxidant injury–induced necrosis in mouse renal proximal tubule cells in vitro. Upregulation of ERK may also be important in the effect of preconditioning whereby early ischemia affords protection against a subsequent ischemia/reperfusion insult. Alterations in cell cycling have also been shown to be involved in renal ischemic injury. Upregulation of p21, which inhibits cell cycling, appears to allow cellular repair and regeneration, whereas homozygous p21 knockout mice demonstrate enhanced cell necrosis in response to an ischemic insult.

Downregulated Upregulated
eNOS heme-oxygenase-1
ERK JNK
  p21

Prolonged duration of the ARF clinical course and the need for dialysis are major factors projecting a poor prognosis. Patients with ARF who require dialysis have a 50–70% mortality rate. Infection and cardiopulmonary complications are the major causes of death in patients with ARF. Excessive fluid administration in patients with established ARF may lead to

  • pulmonary congestion,
  • hypoxia,
  • the need for ventilatory support,
  • pneumonia, and
  • multiorgan dysfunction syndrome (80–90% mortality).

Until means to reverse the diminished host defense mechanisms in azotemic patients with clinical ARF are available, every effort should be made to avoid invasive procedures such as the placement of bladder catheters, intravenous lines, and mechanical ventilation. Over and above such supportive care, it may be that combination therapy will be necessary to prevent or attenuate the course of ARF. Such combination therapy must involve agents with potential beneficial effects on vascular tone, tubular obstruction, and inflammation.

Schrier RW, Wang W, Poole B, and Mitra A. Acute renal failure: definitions, diagnosis, pathogenesis, and therapy. The Journal of Clinical Investigation 2004; 114(1):5-14.

http://www.jci.org

Part IIIb.  Additional Related References on NO, oxidative stress and Kidney

Shelgikar PJ, Deshpande KH, Sardeshmukh AS, Katkam RV, Suryakarl AN. Role of oxidants and antioxidants in ARF patients undergoing hemodialysis. Indian J Nephrol 2005;15: 73-76.

Lee JW. Renal Dysfunction in Patients with Chronic Liver Disease. Electrolytes Blood Press 7:42-50, 2009ㆍdoi: 10.5049/EBP.2009.7.2.42.

Saadat H, et al.  Endothelial Nitric Oxide Function and Tubular Injury in Premature Infants. Int J App Sci and Technol 2012; 7(6): 77-81. www.ijastnet.com.


Amaresan MS. Cardiovascular disease in chronic kidney disease. Indian J Nephrol 2005;15: 1-7.

Traditional risk factors for CVD in CKD

  • Hypertension
  • Older Age
  • Diabetes Mellitus
  • Male gender
  •  White Race
  • Physical inactivity
  • High LDL
  • Low HDL
  • Smoking
  • Menopause
  • LVH

CKD Related CV Risk Factors


Blood Pressure ADMA (Asymmetric Dimethyl Arginine
Na+ Retention Hypervolemia
Insulin Resistance Anemia
Adiponectin Proteinuria & Hypoalbuminemia
Inflammation 5 Lipoxygenase
Homocysteinemia Genetic factors
ROS Lp (a)   
NO synthesis Iron over load
Ca++ x P++ Vit. C or E


S Vikrant, SC Tiwari. Essential Hypertension – Pathogenesis and Pathophysiology. J Indian Acad Clinical Medicine 2001; 2(3):141-161.

Pathogenesis of salt dependent hypertension. The hypothesis proposes that early hypertension is episodic and is mediated by a hyperactive sympathetic nervous system or activated renin-angiotensin system.

Cell membrane alterations

Hypotheses linking abnormal ionic fluxes to increased peripheral resistance through increase in cell sodium, calcium, or pH.

The hypertension that is more common in obese people may arise in large part from the insulin resistance and resultant hyperinsulinaemia that results from the increased mass of fat.

However, rather unexpectedly, insulin resistance may also be involved in hypertension in non-obese people.

The explanation for insulin resistance found in as many as half of nonobese hypertensive is not obvious and may involve one or more aspects of insulin’s action

Proposed mechanisms by which insulin resistance and/or hyperinsulinemia may lead to increased blood pressure.

  • Enhanced renal sodium and water reabsorption.
  • Increased blood pressure sensitivity to dietary salt intake
  • Augmentation of the pressure and aldosterone responses to AII
  • Changes in transmembrane electrolyte transport
  1. Increased intracellular sodium
  2. Decreased Na+/K+ – ATPase activity
  3. Increased intracellular Ca2+ pump activity
  4. Increased intracellular Ca2+ accumulation
  5. Stimulation of growth factors

Summary:  This portion of the discussion concerns mainly acute renal failure, but also expands upon the development of longer term renal tubular disease.  The last consideration is the link between essential hypertension, obesity and insulin resistance, and impaired renal water retention, sodium retention, decreased Na+/K+ – ATPase activity.  The issue of early intervention with fluid resuscitation is tempered by the risk of pulmonary edema as a significant complication.  A review of the literature indicates that both eNOS and iNOS have counter-effects in the genesis of ARF and CRF.  The protective role of vascular eNOS may be more important than the deleterious effect of iNOS at the tubule level during renal ischemia.


Read Full Post »

« Newer Posts - Older Posts »