Feeds:
Posts
Comments

Archive for the ‘Population Health Management, Nutrition and Phytochemistry’ Category

Medscape Update on Calcium and Cardiovascular Risk

Curator and Reporter: Larry H. Bernstein, MD, FCAP

New Data Dispute Calcium Cardiovascular Risk in Both Sexes

Article ID #82: New Data Dispute Calcium Cardiovascular Risk in Both Sexes. Published on 10/11/2013

WordCloud Image Produced by Adam Tubman

Nancy A. Melville   Oct 08, 2013

Medscape Medical News from the American Society for Bone and Mineral Research (ASBMR) 2013 Annual Meeting

BALTIMORE — Two new studies contribute further to the debate over the cardiovascular risk associated with supplementary or dietary calcium, each decidedly coming down on the side of no significant risk — to men or women.

“[Based on these findings], clinicians should continue to evaluate calcium intake, encourage adequate dietary intake, and if necessary, use supplements to reach but not exceed recommended intakes,” Douglas C. Bauer, MD, from the University of California, San Francisco, the lead author of the first study, told Medscape Medical News.

Results of both studies were reported at the recent American Society for Bone and Mineral Research (ASBMR) 2013 Annual Meeting.

Dr. Bauer’s observational trial is one of few contemporary studies to evaluate the level of risk among men, who are often poorly represented in calcium studies, he noted. The results showed no association between calcium dietary intake or supplementation and total or cardiovascular mortality. The second study was an updated meta-analysis of calcium supplementation among women and similarly demonstrated no increased risk for ischemic heart disease (with adjudicated outcomes) or total mortality in elderly women. It did draw some criticism for potential bias and contamination, however.

Nevertheless, says Robert Marcus, MD, a retired Stanford University bone specialist, the 2 studies are “powerful. The one involving men had very elegant, accurate reports of death and validated diagnosis of myocardial infarction, and the [study involving women] was also excellent work,” he commented.

“This field has been the subject of an enormous amount of controversy, ambiguity, and confusion for the past several years, and I think the most important thing is to help us come up with what is true,” he said. The quality of data to suggest an adverse effect of calcium is “very poor,” and there is now compelling evidence that there is little to substantiate this, he noted. But despite these reassuring new findings, public anxiety over a potential risk with calcium is unlikely to go away, he believes.

In recommendations issued in 2010, the ASBMR said that most adults 19 years of age and older require about 600 to 800 IUs of vitamin D daily and 1000 to 1200 mg of calcium daily through food and with supplements, if needed.

Contemporary Data on Calcium Intake in Men

The use of calcium supplements, predominantly with vitamin D, is an important therapy for the prevention of osteoporosis and its clinical consequences. But concerns about the cardiovascular safety of calcium have emerged periodically; in 2 alarming meta-analyses published in 2010 and 2011 by Dr. Mark Bolland and colleagues, for example, there was a 27% increase in MI among individuals allocated to calcium supplements in the first study and a 24% increased risk in the second.

More recently, a 40% increase in total mortality and up to a 50% increase in cardiovascular mortality was seen among women from a Swedish mammography cohort with a calcium intake exceeding 1400 mg per day. In that study, the effect on mortality appeared to be especially strong if a high dietary intake of calcium was combined with calcium supplements.

In their new study, Dr. Bauer and his colleagues set out to assess rates of dietary calcium intake, use of supplements, and mortality in a prospective cohort of 5967 men over the age of 65 years in the Osteoporotic Fractures in Men (MrOS) study.

The participants completed extensive surveys at baseline on their dietary calcium intake, and supplementation was verified by a review of pill bottles by trained staff.

Mean dietary calcium intake was 1142 ± 590 mg/day, with more than half — 65% — of participants reporting use of calcium supplements.

Over the 10-year follow-up, among 2022 men who died, 687 deaths were caused by cardiovascular disease. The highest mortality for CVD was seen in the quartile with the lowest intake from calcium supplementation.

And in models that adjusted for age, energy intake, and calcium use, men in the lowest quartile of total calcium intake (less than 621 mg per day) had higher total mortality compared with those in the highest quartile (more than 1565 mg of calcium per day).

Adjustment for additional confounding factors showed no association between calcium dietary intake and total or cardiovascular mortality (P for trend .51 and .79, respectfully). Likewise, there was no association between calcium supplementation and total or cardiovascular mortality.

The authors also conducted an additional analysis of calcium intake and adjudicated cardiovascular disease events in a subcohort of the study, MrOS Sleep, involving 3120 patients who took part in a 7-year follow-up, and again there was no higher risk for cardiovascular events associated with calcium intake.

The study did have is limitations, Dr. Bauer acknowledged, including the observational design, calcium intake being assessed with a food frequency questionnaire, and cause of death not being formally adjudicated. Nevertheless, the findings are important in demonstrating the level of risk among men in a contemporary setting, he pointed out.

“Contrary to the Swedish study of women, we found no evidence that calcium supplementation is harmful to men, even among those with the highest dietary calcium intake,” he concluded, recommending that future studies should include adjudicated outcomes.

Study in Men as Expected, but Female Research Questioned

In the second study reported at the ASBMR meeting, Joshua Lewis, MD, PhD, from the University of Western Australia, Perth, and colleagues reported a meta-analysis of 19 randomized controlled trials involving women over the age of 50 years who had received calcium supplementation for more than a year.

Importantly, the analysis included reports of adjudicated cardiovascular outcomes, which the researchers note is important because gastrointestinal events can be misreported as cardiac ones. They also assessed all-cause mortality.

Among 59,844 participants in the studies, there were 4646 deaths, and the relative risk for death among those randomized to calcium supplements was 0.96 (P = .18).

The relative risk for 3334 ischemic heart disease events among 46,843 participants was 1.02 (P = .053), and the risk for 1097 MI events among 49,048 participants was 1.09 (P =.21).

“The data from this meta-analysis does not support the concept that calcium supplementation with or without vitamin D increases the risk of ischemic heart disease or total mortality in elderly women,” concluded Dr. Lewis.

But bone specialist Ian Reid, MD, from the University of Auckland, New Zealand, who was a coauthor on some of the Bolland studies, said this analysis essentially repeats previous ones, but with the inclusion of 20,000 patients from the Women’s Health Initiative (WHI), many of whom continued to take their own calcium tablets, regardless of whether they were randomized to calcium or placebo.

These “contaminated” WHI data have the potential to mask the effect of calcium, he told Medscape Medical News. In addition, in a study from Denmark also included in the meta-analysis, subjects were not properly blinded to treatment assignment and the calcium and control groups were not comparable at baseline for cardiovascular risk, which introduced “major potential bias,” he added.

Regarding the results from the study in men by Dr. Bauer and colleagues, Dr. Reid said they were not surprising to him. “Generally, people who take calcium supplements have more health-conscious behaviors than those who do not and so have a lower baseline risk of heart disease” that can “obscure small adverse effects of drugs such as calcium,” he observed.

An effect has to be “very substantial” before it can be picked up in an observational study, because of the many confounders that can obscure such an effect, he concluded.

Dr. Bauer, Dr. Lewis, Dr. Reid, and Dr. Marcus have reported no financial relationships. MrOS is supported by funding from the National Institutes of Health.

American Society for Bone and Mineral Research 2013 Annual Meeting. Abstracts 1001 and 1002, presented October 4, 2013.

Related article in Pharmaceutical Intelligence:

Calcium (Ca) supplementation (>1400 mg/day): Higher Death Rates from all Causes and Cardiovascular Disease in Women
Aviva Lev-Ari, PhD. RN
http://pharmaceuticalintelligence.com/2013/02/19/calcium-ca-supplementation-1400-mgday-higher-death-rates-from-all-causes-and-cardiovascular-disease-in-women/

Read Full Post »

The Role of Tight Junction Proteins in Water and Electrolyte Transport


Reviewer and Curator: Larry H. Bernstein, MD, FCAP 


This article is Part II of a series that explores the physiology, genomics, and the proteomics of water and electrolytes in human and mammalian function in health and disease.  In this portion of curation, we examine the role of special proteins at the tight junctions of cells, including the claudins.  Consistent with the exploration of cation homeostasis, the last featured article is one of the altered handling of calcium (Ca2+) in CHF, and the closely regulated calcium efflux by the sodium-calcium exchanger (NCX).

The Role of Aquaporin and Tight Junction Proteins in the Regulation of Water Movement in Larval Zebrafish (Danio rerio).

Kwong RW, Kumai Y, Perry SF.
Department of Biology, University of Ottawa, Ottawa, Ontario, Canada.
PLoS One. 2013 Aug 14;8(8):e70764.
http://dx.doi.org/10.1371/journal.pone.0070764   eCollection 2013.

Teleost fish living in freshwater are challenged by passive water influx; however the molecular mechanisms regulating water influx in fish are not well understood. The potential involvement of aquaporins (AQP) and epithelial tight junction proteins in the regulation of transcellular and paracellular water movement was investigated in larval zebrafish (Danio rerio).

We observed that the half-time for saturation of water influx (K u) was 4.3±0.9 min, and reached equilibrium at approximately 30 min. These findings suggest a high turnover rate of water between the fish and the environment. Water influx was reduced by the putative AQP inhibitor phloretin (100 or 500 μM). Immunohistochemistry and confocal microscopy revealed that AQP1a1 protein was expressed in cells on the yolk sac epithelium. A substantial number of these AQP1a1-positive cells were identified as ionocytes, either H(+)-ATPase-rich cells or Na(+)/K(+)-ATPase-rich cells. AQP1a1 appeared to be expressed predominantly on the basolateral membranes of ionocytes, suggesting its potential involvement in regulating ionocyte volume and/or water flux into the circulation.

Additionally, translational gene knockdown of AQP1a1 protein reduced water influx by approximately 30%, further indicating a role for AQP1a1 in facilitating transcellular water uptake. On the other hand, incubation with the Ca(2+)-chelator EDTA or knockdown of the epithelial tight junction protein claudin-b significantly increased water influx. These findings indicate that the epithelial tight junctions normally act to restrict paracellular water influx. Together, the results of the present study provide direct in vivo evidence that water movement can occur through transcellular routes (via AQP); the paracellular routes may become significant when the paracellular permeability is increased.

PMID:  23967101  PMCID: PMC3743848    http://www.ncbi.nlm.nih.gov/pubmed/23967101

The tight junction protein claudin-b regulates epithelial permeability and sodium handling in larval zebrafish, Danio rerio.

Kwong RW, Perry SF.
Department of Biology, University of Ottawa, Ottawa, Ontario, Canada. wkwong@uottawa.ca
Am J Physiol Regul Integr Comp Physiol. Apr 1, 2013; 304(7):R504-13. http://dx.doi.org/10.1152/ajpregu.00385.2012  Epub 2013 Jan 30.

The functional role of the tight junction protein claudin-b in larval zebrafish (Danio rerio) was investigated. We showed that claudin-b protein is expressed at epithelial cell-cell contacts on the skin. Translational gene knockdown of claudin-b protein expression caused developmental defects, including edema in the pericardial cavity and yolk sac.

Claudin-b morphants exhibited an increase in epithelial permeability to the paracellular marker polyethylene glycol (PEG-4000) and fluorescein isothiocyanate-dextran (FD-4). Accumulation of FD-4 was confined mainly to the yolk sac and pericardial cavity in the claudin-b morphants, suggesting these regions became particularly leaky in the absence of claudin-b expression.

Additionally, Na(+) efflux was substantially increased in the claudin-b morphants, which contributed to a significant reduction in whole-body Na(+) levels. These results indicate that claudin-b normally acts as a paracellular barrier to Na(+). Nevertheless, the elevated loss of Na(+) in the morphants was compensated by an increase in Na(+) uptake.

Notably, we observed that the increased Na(+) uptake in the morphants was attenuated in the presence of the selective Na(+)/Cl(-)-cotransporter (NCC) inhibitor metolazone, or during exposure to Cl(-)-free water. These results suggested that the increased Na(+) uptake in the morphants was, at least in part, mediated by NCC. Furthermore, treatment with an H(+)-ATPase inhibitor bafilomycin A1 was found to reduce Na(+) uptake in the morphants, suggesting that H(+)-ATPase activity was essential to provide a driving force for Na(+) uptake. Overall, the results suggest that claudin-b plays an important role in regulating epithelial permeability and Na(+) handling in zebrafish.
PMID: 23364531   http://www.ncbi.nlm.nih.gov/pubmed/23364531

Evidence for a role of tight junctions in regulating sodium permeability in zebrafish (Danio rerio) acclimated to ion-poor water.

Kwong RW, Kumai Y, Perry SF.
Department of Biology, University of Ottawa, Ottawa, ON, Canada. wkwong@uottawa.ca
J Comp Physiol B. Feb 2013 ;183(2):203-13.
http://dx.doi.org/10.1007/s00360-012-0700-9  Epub 2012 Jul 29.

Freshwater teleosts are challenged by diffusive ion loss across permeable epithelia including gills and skin. Although the mechanisms regulating ion loss are poorly understood, a significant component is thought to involve paracellular efflux through pathways formed via tight junction proteins. The mammalian orthologue (claudin-4) of zebrafish (Danio rerio) tight junction protein, claudin-b, has been proposed to form a cation-selective barrier regulating the paracellular loss of Na(+).

The present study investigated the cellular localization and regulation of claudin-b, as well as its potential contribution to Na(+) homeostasis in adult zebrafish acclimated to ion-poor water. Using a green fluorescent protein-expressing line of transgenic zebrafish, we found that claudin-b was expressed along the lamellar epithelium as well as on the filament in the inter-lamellar regions. Co-localization of claudin-b and Na(+)/K(+)-ATPase was observed, suggesting its interaction with mitochondrion-rich cells. Claudin-b also appeared to be associated with other cell types, including the pavement cells. In the kidney, claudin-b was expressed predominantly in the collecting tubules. In addition,

exposure to ion-poor water caused a significant increase in claudin-b abundance as well as a decrease in Na(+) efflux, suggesting a possible role for claudin-b in regulating paracellular Na(+) loss. Interestingly, the whole-body uptake of a paracellular permeability marker, polyethylene glycol-400, increased significantly after prolonged exposure to ion-poor water, indicating that an increase in epithelial permeability is not necessarily coupled with an increase in passive Na(+) loss. Overall, our study suggests that in ion-poor conditions, claudin-b may contribute to a selective reduction in passive Na(+) loss in zebrafish.
PMID: 22843140   http://www.ncbi.nlm.nih.gov/pubmed/22843140

Claudin-16 and claudin-19 function in the thick ascending limb.

Hou J, Goodenough DA.
Washington University School of Medicine, Div Renal Diseases, St Louis, Missouri
Curr Opin Nephrol Hypertens. Sep 2010; 19(5):483-8. http://dx.doi.org/10.1097/MNH.0b013e32833b7125.

The thick ascending limb (TAL) of the loop of Henle is responsible for reabsorbing 25–40% of filtered Na+, 50–60% of filtered Mg2+ and 30–35% of filtered Ca2+. The dissociation of salt and water reabsorption in the TAL serves both to dilute the urine and to establish the corticomedullary osmolality gradient. Active transcellular salt reabsorption results in a lumen-positive transepithelial voltage that drives passive paracellular reabsorption of divalent cations. Claudins are the key components of the paracellular channel. The paracellular channels in the tight junction have properties of ion selectivity, pH dependence and anomalous mole fraction effects, similar to conventional transmembrane channels. Genetic mutations in claudin-16 and claudin-19 cause an inherited human renal disorder, familial hypomagnesemia with hypercalciuria and nephrocalcinosis (FHHNC).

In the TAL of Henle’s loop, the epithelial cells form a water-impermeable barrier, actively transport Na+ and Cl− via the transcellular route, and provide a paracellular pathway for the selective absorption of cations. Na+ K+ and Cl− enter the cell through the Na-K-2Cl cotransporter (NKCC2) in the luminal membrane. Na+ exits the cell through the Na+/K+-ATPase, in exchange for K+ entry. K+ is secreted into the lumen through the renal outer medullary potassium channel. Cl− leaves the cell through the basolateral Cl− channel, made up of two subunits, ClCKb and barttin. The polarized distribution of luminal K+ versus basolateral Cl− conductance generates a spontaneous voltage source (Vsp) of +7−8mV , depending on active transcellular NaCl reabsorption. With continuous NaCl reabsorption along the axis of the TAL segment, the luminal fluid is diluted to 30–60mmol/l  and a large NaCl transepithelial chemical gradient develops at the end of the TAL. Because the paracellular permeability of the TAL is cation-selective (with a PNa/PCl value between 2 and 4), the diffusion voltage (Vdi) is superimposed onto the active transport voltage (Vsp) and becomes the major source of the transepithelial voltage (Vte), which now increases up to +30mV.

Early in-vivo micropuncture studies have shown that approximately 50–60% of the filtered Mg2+ is reabsorbed in the TAL. The flux–voltage relationship indicates that Mg2+ is passively reabsorbed from the lumen to the peritubular space through the paracellular pathway in this segment, driven by a lumen positive Vte.  Vte is made of the sum of Vsp and Vdi. There are two prerequisites required for the paracellular Mg2+ reabsorption in the TAL: the lumen-positive Vte as the driving force and the paracellular permeability for the divalent cation Mg2+.

Claudin-16 and claudin-19 underlie familial hypercalciuric hypomagnesemia with nephrocalcinosis

Claudin-16 and claudin-19 play a major role in the regulation of magnesium reabsorption in the thick ascending limb (TAL). This review describes recent findings of the physiological function of claudin-16 and claudin-19 underlying normal transport function for magnesium reabsorption in the TAL. Mutations in the genes encoding the tight junction proteins claudin-16 and claudin-19 cause the inherited human renal disorder familial hypomagnesemia with hypercalciuria and nephrocalcinosis. FHHNC, OMIM #248250, is a rare autosomal recessive tubular disorder. As a consequence of excessive renal Mg2+ and Ca2+ wasting, patients develop the characteristic triad of hypomagnesemia, hypercalciuria and nephrocalcinosis. Recurrent urinary tract infections and polyuria/polydipsia are frequent initial symptoms. Other clinical symptoms include nephrolithiasis, abdominal pain, convulsions, muscular tetany, and failure to thrive. Additional laboratory findings include elevated serum parathyroid hormone levels before the onset of chronic renal failure, incomplete distal tubular acidosis, hypocitraturia, and hyperuricemia. In contrast to hypomagnesemia and secondary hypocalcemia (HSH, OMIM #602014), FHHNC is generally complicated by end-stage renal failure in early childhood or adolescence.

Simon et al. used the positional cloning strategy and identified claudin-16 (formerly known as paracellin-1), which is mutated in patients with FHHNC. Most mutations reported to date in claudin-16 are missense mutations clustering in the first extracellular loop composing the putative ion selectivity filter. Konrad et al. have found mutations in another tight junction gene encoding claudin-19 from new cohorts of FHHNC patients (OMIM #248190). The renal tubular phenotypes are indistinguishable between patients with mutations in claudin-16 and those with mutations in claudin-19. Although claudin-16 and claudin-19 underlie FHHNC and paracellular Mg2+ reabsorption in the TAL, the transient receptor potential channel melastatin 6 (TRPM6) regulates the apical entry of Mg2+ into the distal convoluted tubule epithelia. Mutations in TRPM6 cause the HSH syndrome.

These above data suggested the hypothesis that claudin-16 and/or claudin-19 forms a selective paracellular Mg2+/Ca2+ channel, which was tested in a number of in-vitro studies. Ikari et al. transfected low-resistance Madin-Darby canine kidney (MDCK) cells with claudin-16 and reported that the Ca2+ flux in these cells was increased in the apical to basolateral direction, whereas the Ca2+ flux in the opposite direction remained unchanged. The Mg2+ flux was without any noticeable change. Kausalya et al.  transfected the high-resistance MDCK-C7 cell line and found that claudin-16 only moderately increased Mg2+ permeability without any directional preference. The effects of claudin-16 on Mg2+/Ca2+ permeation appeared so small (<50%) that the Mg2+/Ca2+ channel theory incompletely explains the dramatic effect of mutations in claudin-16 on Mg2+ and Ca2+ homoeostasis in FHHNC patients. However, , Hou et al.  transfected the anion-selective LLC-PK1 cell line with claudin-16 and found a large increase in Na+ permeability (PNa) accompanied by a moderately enhanced Mg2+ permeability (PMg). The permeability of claudin-16 to other alkali metal cations was found to be: K+ > Rb+ > Na+.  Yu et al. emphasized that these residue replacements can influence protein structures that may have impacts on ion permeability independent of amino acid charge.

The cation selectivity of the tight junction is vital for generating the lumen positive transepithelial potential in the TAL, which drives paracellular absorption of magnesium. Claudin-16 and claudin-19 require each other for assembly into tight junctions in the TAL. Heteromeric claudin-16 and claudin-19 interaction forms a cation selective tight junction paracellular channel. Loss of either claudin-16 or claudin-19 in the mouse kidney abolishes the cation selectivity for the TAL paracellular pathway, leading to excessive renal wasting of magnesium.

Claudins interact with each other both intracellularly and intercellularly: they copolymerize linearly within the plasma membrane of the cell, together with the integral protein occludin, to form the classical intramembrane fibrils or strands visible in freeze-fracture replicas. These intramembrane interactions (side-to-side) can involve one claudin protein (homomeric or homopolymeric) or different claudins (heteromeric or heteropolymeric). In the formation of the intercellular junction, claudins may interact head-to-head with claudins in an adjacent cell, generating both homotypic and heterotypic claudin–claudin interactions. Using the split-ubiquitin yeast 2-hybrid assay, Hou et al. found strong claudin-16 and claudin-19 heteromeric interaction. The point mutations in claudin-16 (L145P, L151F, G191R, A209T, and F232C) or claudin-19 (L90P and G123R) that are known to cause human FHHNC disrupted the claudin-16 and claudin-19 heteromeric interaction. In mammalian cells such as the human embryonic kidney 293 cells, claudin-16 can be coimmunoprecipitated with claudin-19. Freeze-fracture replicas revealed the assembly of tight junction strands in L cells coexpressing claudin-16 and claudin-19, supporting their heteromeric interaction.

Coexpression of claudin-16 and claudin-19 in LLC-PK1 cells resulted in a dramatic upregulation of PNa and down-regulation of PCl, generating a highly cation-selective paracellular pathway. Certain FHHNC mutations in claudin-16 (L145P, L151F, G191R, A209T, and F232C) or claudin-19 (L90P and G123R) that disrupted their heteromeric interaction abolished this physiological change. As claudin-16 colocalizes with claudin-19 in the TAL epithelia of the kidney, claudin-16 and claudin-19 association through heteromeric interactions confers cation selectivity to the tight junction in the TAL. Human FHHNC mutations in claudin-16 or claudin-19 that abolish the cation selectivity diminish the lumen-positive Vdi as the driving force for Mg2+ and Ca2+ reabsorption, readily explaining the devastating phenotypes in FHHNC patients.  Hou et al. generated claudin-16 deficient mouse models using lentiviral transgenesis of siRNA to knock down claudin-16 expression by more than 99% in mouse kidneys. Claudin-16 knockdown mice show significantly reduced plasma Mg2+ levels and excessive urinary excretions (approximately four-fold) of Mg2+ and Ca2+. Calcium deposits are observed in the basement membranes of the medullary tubules and the interstitium in the kidney of claudin-16 knockdown mice. These phenotypes of claudin-16 knockdown mice recapitulate the symptoms in human FHHNC patients.

The paracellular reabsorption of Mg2+ and Ca2+ is driven by a lumen-positive Vte made up of two components: Vsp and Vdi. When isolated TAL segments were perfused ex vivo with symmetrical NaCl solutions, there was no difference in Vsp between claudin-16 knockdown and wild-type mice, indicating Vsp was normal in claudin-16 knockdown. Blocking the NKCC2 channel with furosemide (thus dissipating VSP), the cation selectivity (PNa/PCl) was significantly reduced from3.1 ± 0.3 in wild type to 1.5 ± 0.1 in claudin-16 knockdown, resulting in the loss of Vdi. When perfused with a NaCl gradient of 145mmol/l (bath) versus 30mmol/l (lumen), the resulting Vdi was +18mV in wild type, but only +6.6mV in claudin-16 knockdown. Thus, the reduction in Vdi accounted for a substantive loss of the driving force for Mg2+ and Ca2+ reabsorption.

Renal handling of Na+ in claudin-16 knockdown mice is more complex. In the early TAL segment, the transcellular and paracellular pathways form a current loop in which the currents traversing the two pathways are of equal size but opposite direction. Net luminal K+ secretion and basolateral Cl− absorption polarize the TAL epithelium and generate Vsp. As the paracellular pathway is cation selective (PNa/PCl=2–4 , the majority of the current driven by Vsp through the paracellular pathway is carried by Na+ moving from the lumen to the interstitium. Hebert et al. estimated that, for each Na+ absorbed through the trans-cellular pathway, one Na+ is absorbed through the paracellular pathway. With the loss of claudin-16 and the concomitant loss of paracellular cation selectivity, Na+ absorption through the paracellular pathway is reduced.  In the late TAL segment, dilution of NaCl in the luminal space creates an increasing chemical transepithelial gradient; back diffusion of Na+ through the cation-selective tight junction generates a lumen-positive Vdi across the epithelium. The paracellular absorption of Na+ will be diminished when Vdi equals Vsp, and reversed when Vdi exceeds Vsp. As an equilibrium potential, Vdi blocks further Na+ backleak into the lumen. Without claudin-16, Vdi will be markedly reduced well below normal, providing a driving force for substantial Na+ secretion. Indeed, claudin-16 knockdown mice had increased fractional excretion of Na+ (FENa) and developed hypotension and secondary hyperaldosteronism. The observed Na+ and volume loss are consistent with human FHHNC phenotypes. For example, polyuria and polydipsia are the most frequently reported symptoms from FHHNC patients.

Epithelial paracellular channels are increasingly understood to be formed from claudin oligomeric complexes. In the mouse TAL, claudin-16 and claudin-19 cooperate to form cation-selective paracellular channels required for normal levels of magnesium reabsorption. Different subsets of the claudin family of tight junction proteins are found distributed throughout the nephron, and understanding their roles in paracellular ion transport will be fundamental to understanding renal ion homeostasis.

Keywords: claudin; hypomagnesemia; thick ascending limb; tight junction; transepithelial voltage.     PMID: 20616717  PMCID: PMC3378375  http://www.ncbi.nlm.nih.gov/pubmed/20616717

Function and regulation of claudins in the thick ascending limb of Henle.

Günzel D, Yu AS.
Depart Clin Physiol, Charité, Campus Benjamin Franklin, Berlin, Germany.
Pflugers Arch. May 2009; 458(1):77-88.
http://dx.doi.org/10.1007/s00424-008-0589-z  Epub 2008 Sep 16.

The thick ascending limb (TAL) of Henle mediates transcellular reabsorption of NaCl while generating a lumen-positive voltage that drives passive paracellular reabsorption of divalent cations. Disturbance of paracellular reabsorption leads to Ca(2+) and Mg(2+) wasting in patients with the rare inherited disorder of familial hypercalciuric hypomagnesemia with nephrocalcinosis (FHHNC). Recent work has shown that the claudin family of tight junction proteins form paracellular pores and determine the ion selectivity of paracellular permeability. Importantly, FHHNC has been found to be caused by mutations in two of these genes, claudin-16 and claudin-19, and mice with knockdown of claudin-16 reproduce many of the features of FHHNC. Here, we review the physiology of TAL ion transport, present the current view of the role and mechanism of claudins in determining paracellular permeability, and discuss the possible pathogenic mechanisms responsible for FHHNC.

Tight junctions form the paracellular barrier in epithelia. Claudins are ~22 kDa proteins that were first identified by Mikio Furuse in the laboratory of the late Shoichiro Tsukita as proteins that copurified in a tight junction fraction from the chicken liver [23]. The observation that they were transmembrane proteins with 4 predicted membrane domains and 2 extracellular domains raised early on the possibility that they could play a key role in intercellular adhesion and formation of the paracellular barrier. In 1999, Richard Lifton’s group identified mutations in a novel gene, which they called paracellin, as the cause of familial hypercalciuric hypomagnesemia, an inherited disorder believed to be due to failure of paracellular reabsorption of divalent cations in the thick ascending limb of the renal tubule. Paracellin turned out to be a claudin family member (claudin-16). This suggested that claudins in general might be directly involved in regulating paracellular transport in all epithelia. This is now supported by numerous studies demonstrating that overexpressing or ablating expression of various claudin isoforms in cultured cell lines or in mice affects both the degree of paracellular permeability and its selectivity (vide infra). Furthermore, in mammals alone there are ~24 claudin genes and each exhibits a distinct tissue-specific, pattern of expression. Thus, the specific claudin isoform(s) expressed in each tissue might explain its paracellular permeability properties.

Each nephron segment expresses a unique set of multiple claudin isoforms, and each isoform is expressed in multiple segments, thus making a complicated picture which even varies between different species. The role of combinations of claudins in determining paracellular permeability properties has hardly been studied yet. In mouse, rabbit and cattle, the thick ascending limb of Henle’s loop is thought to express claudins 3, 10, 11, 16  in adulthood, and, at least in mouse, additionally claudin-6 during development. In addition, claudin-4 has been found in cattle and claudin-8 in rabbit. To date, the distribution of Claudin-19 has been investigated in mouse, rat, and man where its presence in the TAL was demonstrated.

The thick ascending limb (TAL) of Henle’s loop, working as “diluting segment” of the nephron, is characterized by two major properties: high transepithelial, resorptive transport of electrolytes and low permeability to water. Major players to achieve electrolyte transport are the apical Na+-K+-2Cl−symporter (NKCC2), the apical K+ channel ROMK, the basolateral Cl− channel (CLC-Kb) together with its subunit barttin and the basolateral Na+/K+-ATPase . The combined actions of these transport systems have been extensively reviewed and are therefore only briefly summarized here. Na+ and Cl− are resorbed by entering the cells apically through NKCC2 and leaving the cells basolaterally through the Na+/K+-ATPase and CLC-Kb, respectively. In contrast, K+ is either recycled across the apical membrane as it is entering through NKCC2 and leaving through ROMK, or even secreted, as it is also entering the cells basolaterally through the Na+/K+-ATPase. Taking these ion movements together, there is a net movement of positive charge from the basolateral to the apical side of the epithelium, giving rise to a lumen positive voltage (3 – 9 mV [11]; about 5 – 7 mV [30,31]; 7 – 8 mV [57]). Over the length of the TAL, luminal NaCl concentration decreases gradually to concentrations of 30 – 60 mM at the transition to the distal tubule, depending on the flow rate within the tubule (low flow rates resulting in low concentrations).

To keep up such a high gradient, the TAL epithelium has to be tight to water and various studies summarized by Burg and Good report water permeability values from 28 µm/s down to values indistinguishable from zero. Tight junctions of the TAL are, however, highly permeable to cations with PNa being about 2 – 2.7 fold, 2.5 fold or even up to 6 fold that of PCl. Amongst the monovalent cations, a permeability sequence of PK > PNa > PRb = PLi > PCs > Porganic cation was observed which is similar to Eisenman sequence VIII or IX, indicating a strong interaction between the permeating ion and the paracellular pore that enables at least partial removal of the hydration shell (see below). As reviewed by Burg and Good, the transepithelial sodium and chloride permeabilities, estimated from radioisotope fluxes, are high (in the range of 10 – 63·10−6 cm/s) and the transepithelial electrical resistance is correspondingly low (21 – 25 W cm2 ; 30 – 40 W cm2 ; 11 – 34 W cm2 . Blocking active transport by the application of furosemide or ouabain increases transepithelial resistance only slightly, indicating that the low values are primarily due to a very high paracellular permeability. Due to these properties of TAL epithelial cells, Na+ ions leak back into the lumen of the tubule, creating a diffusion (dilution) potential that adds another 10 – 15 mV to the lumen positive potential, so that considerable potential differences (25 mV ; 30 mV; cTAL 23 mV, mTAL 17 mV ) may be reached at very slow flow rates.

Considerable proportions of the initially filtrated Mg2+ (50 – 60%; 50 – 70%; 65 – 75%) and Ca2+ (20%; 30 – 35% are resorbed in the TAL. The transepithelial potential is considered to provide the driving force for the predominantly paracellular resorption of Mg2+ and Ca2+ as in many studies, transport of both divalent ions in the TAL has been found to be strictly voltage dependent (resorbtive at lumen positive potentials, zero at 0 mV and secretory at lumen negative potentials) and permeability considerable (PCa 7.7·10−6 cm/s, i.e. approximately 25% of PNa). There is however, some conflicting evidence, e.g. by Suki et al. and Friedman. Both studies used cTAL (cortical TAL) and found that decreasing the transepithelial potential by applying furosemide did either not alter the unidirectional lumen to bath Ca2+ flux (rabbit) or left a substantial net Ca2+ resorption (mouse). Similarly, Rocha et al. found that bath application of ouabain almost abolished the transepithelial potential, but hardly affected net Ca2+ resorption and conclude that (a) all segments of Henle’s loop are relatively impermeable to calcium and (b) net calcium resorption occurs in the thick ascending limb which cannot be explained by passive mechanisms.  Mandon et al. conclude that both Mg2+ and Ca2+ are transported in the cTAL but not in the mTAL (medullary TAL) of rat and mouse, although transepithelial potential differences were similar in both segments, and even if the transepithelial potential was experimentally elevated to values above 20 mV. Wittner et al. even found evidence that in mouse mTAL the passive permeability to divalent cations is very low and that Ca2+ and Mg2+ can be secreted into the luminal fluid under conditions which elicit large lumen-positive transepithelial potential differences. They conclude that this Ca2+ and Mg2+ transport is most probably of cellular origin. In contrast, in rabbit, both ions are transported along the whole length of the TAL.

Both, Mg2+ and Ca2+ resorption are modulated through the action of the basolateral Ca (and Mg) sensing receptor (CaSR) which is found along the entire nephron but especially in the loop of Henle, distal convoluted tubule (DCT) and the inner medullary collecting duct. Different modes of action on Ca2+ and Mg2+ homeostasis exist, such as an indirect action through the modulation of PTH secretion or direct effects on the cells expressing CaSR. In the TAL the latter model is based on the assumptions depicted above, i.e. that Mg2+ and Ca2+ are resorbed paracellularly, driven by the lumen positive potential, so that a reduction in NaCl resorption causes a reduction in driving force for Mg2+ and Ca2+ resorption. As reviewed by Hebert and Ward, CaSR is activated through an increase in basolateral Ca2+ and/or Mg2+ concentration which triggers an increase in the intracellular Ca2+ concentration. This reduces the activity of the adenylate cyclase which, in turn, inhibits transcellular transport of Na+ and Cl−. In addition, the increase in intracellular Ca2+ activates phospholipase A2 (PLA2) and thus increases the intracellular concentration of arachidonic acid and its derivative, 20-HETE. 20-HETE inhibits NKCC2, ROMK and the Na+/K+-ATPase and by this Mg2+ and Ca2+ resorption. In keeping with this hypothesis, mutations in CaSR affect Ca/Mg resorption. Inactivating mutations cause hypercalcemia, hypocalciuria, hypomagnesiuria and, in some patients hypermagnesemia. Conversely, activating mutations (gain of function mutations) lead to hypocalcemia, hypercalciuria, hypermagnesiuria and in up to 50% of the patients mild hypomagnesemia.

Bartter syndrome type I (mutations in NKCC2), and type II (mutations in ROMK) lead to hypercalciuria and thus cause nephrocalcinosis, but no hypomagnesemia is observed. Reports on hypermagnesiuria are conflicting: while Kleta and Bockenhauer link it to nephrocalcinosis seen in these patients, Rodriguez-Soriano states that patients with neonatal Bartter syndrome (i.e. type I or II) show a lack of hypermagnesiuria that may be explained by compensation in the DCT. Hypomagnesemia is occationally present in Bartter type III (CLC-Kb). However, here it is believed to be mainly due to effects on DCT, where CLC-Kb shows highest expression. Patients with Bartter syndrome IV (CLC-Kbsubunit barttin) may or may not present nephrocalcinosis, while Mg2+ homeostasis appears undisturbed. Interestingly, the largest effects on Mg2+-homeostasis are observed in Gitelman syndrome, a defect in the Na+/Cl− symport (NCC) predominantly found in the DCT, where Mg2+ is transported along the transcellular route. Affected patients suffer from hypomagnesemia, hypermagnesuria and hypocalciuria. The effect on Mg2+ in Gitelman syndrome is still poorly understood and possibly due to a concomitant down-regulation of TRPM6, the apical Mg2+ uptake channel in DCT.

More than 30 different claudin-16 mutations have now been reported in families with FHHNC. Because of the large number of unique mutations, it has not been possible to identify any clear qualitative correlation between the phenotype and individual mutations, although certain mutations are associated with greater severity of disease. In 2006, a second locus was identified, CLDN19, which encodes claudin-19. In the initial report, the phenotype appeared similar to that due to claudin-16 mutations, with the exception that there was a high prevalence of ocular abnormalities, including macular colobomata, nystagmus and myopia. Claudin-19 is normally expressed at high levels in the retina, but why it causes these ocular disorders is unknown.

In vitro studies of claudin function comprise inducible or non-inducible transfection of various cells lines with cDNA for claudins that are not endogenously expressed by the cell line used. Alternatively, cells can be transfected with siRNA directed against an endogenous claudin. In both cases, cells are then grown to confluence on permeable filter supports that allow measurement of transepithelial permeabilities. Before the results of permeability studies can be interpreted, however, several parameters have to be controlled.

First, special care has to be taken to make sure that the exogenous claudin is correctly inserted into the tight junction. This can be achieved e.g. by confocal laser scanning microscopy, colocalizing the claudin of interest  with a tight junction marker protein such as occludin.

Second, it has to be ensured that endogenous claudin expression remains unaffected, as permeability changes always result from the combined effects of alterations in endogenous and exogenous claudins.

Third, it has to be kept in mind that, typically, epithelia express several different claudins that act together to produce tissue specific permeability properties. Thus, ideally, a cell line should be chosen that provides a claudin background resembling that usually experienced by the claudin investigated. The latter two points may be the reason for contradicting results obtained in permeability studies expressing a specific claudin in different cell lines.

Studies of paracellular permeabilities can be divided into two groups, those employing electrophysiological measurements (e.g. determination of diffusion potentials), and those measuring ion or solute flux, using either radioactive isotopes or various analytical methods to determine the amount transported.

Although transepithelial conductances depend on paracellular permeabilities of the predominant ions in the bath solution, conductance changes alone cannot be used to predict ion permeabilities.

Firstly, conductances always depend on both ion and counter-ion, not on one ion species alone.

Secondly, transepithelial conductances are the sum of the conductances of the transcellular and paracellular pathways.

Thus, they only reflect paracellular permeability, if paracellular conductance dominates transepithelial conductance and if transcellular conductance remains constant throughout the experiment. This, however, is often not the case, as concentration changes of the ions investigated may affect transcellular conductance, e.g. by activating ion transporters or by inhibiting ion channels. Thirdly, the specific conductance of each solution employed may differ and has therefore to be assessed and taken into account. Thus, comparison of results from diffusion potential measurements or flux studies and conductance measurements may even yield contradicting results. For the same reasons, other methods based on pure conductance/resistance measurements, including the more sophisticated conductance scanning method or one-path impedance spectroscopy are not ion specific and do not allow the measurement of paracellular permeabilities to single ions.

In contrast to electrophysiological measurements, flux measurements are not limited to ions but can also be extended to uncharged molecules.  Flux measurements per se do not distinguish between transcellular or paracellular transport. Therefore, to estimate paracellular permeabilities, inhibition or at least estimation of the transcellular flux is necessary. Assuming that transcellular flux for energetic reasons is not easily reversible while paracellular flux is passive and thus generally assumed to be symmetric, the transcellular proportion is often estimated by calculating the difference between apical to basolateral and basolateral to apical fluxes. All flux measurements are very sensitive to the development of diffusion zones (“unstirred layers”) near the cells. These layers are depleted/enriched in the compound transported and thus alter the driving forces acting on these compounds, if bath solutions are not continually circulated. If ionic fluxes are investigated, transepithelial potentials may develop that diminish or completely inhibit the flux investigated.

All the techniques described above have been employed to investigate the function of claudin-16 and -19, especially with respect to their ability to increase paracellular permeability to divalent cations. The hypothesis, that claudin-16 (then called paracellin-1) may be a paracellular Mg2+ and Ca2+ pore was originally expressed by Simon et al. It was based on the findings that mutations in claudin-16 were the cause of the severe disturbance in Mg2+ and Ca2+ homeostasis in FHHNC patients together with the observations that claudin-16 is a tight junction protein located in the TAL, i.e. the nephron segment responsible for bulk Mg2+ resoption along the paracellular pathway. When, recently, it was found that claudin-19 mutations were underlying hitherto unexplained cases of FHHNC and that claudin-19 co-localized with claudin-16, the hypothesis was extended to claudin-19.

  1. Cole DEC, Quamme GA. Inherited disorders of renal magnesium handling. J Am Soc Nephrol 2000;11:1937–1947. [PubMed: 11004227]
  2. de Rouffignac C, Quamme G. Renal magnesium handling and its hormonal control. Physiol Rev 1994;74:305–322. [PubMed: 8171116]  
  3. Meij IC, van den Heuvel LP, Knoers NV. Genetic disorders of magnesium homeostasis. BioMetals 2002;15:297–307. [PubMed: 12206395]
  4. Satoh J, Romero MF. Mg2+ transport in the kidney. BioMetals 2002;15:285–295. [PubMed: 12206394]  
  5. Schlingmann KP, Konrad M, Seyberth HW. Genetics of hereditary disorders of magnesium homeostasis. Pediatr Nephrol 2004;19:13–25. [PubMed: 14634861]  
  6. Simon DB, Lu Y, Choate KA, et al. Paracellin-1, a renal tight junction protein required for paracellular Mg2+ resorption. Science 1999;285:103–106. [PubMed: 10390358]

PMID: 18795318  PMCID:  PMC2666100  http://www.ncbi.nlm.nih.gov/pubmed/18795318

Deletion of claudin-10 (Cldn10) in the thick ascending limb impairs paracellular sodium permeability and leads to hypermagnesemia and nephrocalcinosis.

Breiderhoff T, Himmerkus N, Stuiver M, Mutig K, Will C, Meij IC et al.
Max Delbrück Center for Molec Med, Berlin, Germany. t.breiderhoff@mdc-berlin.de

Erratum in Proc Natl Acad Sci. 2012 Sep 11;109(37):15072.
Proc Natl Acad Sci. Aug 28, 2012; 109(35):14241-6.   http://dx.doi.org/10.1073/pnas.1203834109. Epub 2012 Aug 13.

In the kidney, tight junction proteins contribute to segment specific selectivity and permeability of paracellular ion transport. In the thick ascending limb (TAL) of Henle’s loop, chloride is reabsorbed transcellularly, whereas sodium reabsorption takes transcellular and paracellular routes. TAL salt transport maintains the concentrating ability of the kidney and generates a transepithelial voltage that drives the reabsorption of calcium and magnesium. Thus, functionality of TAL ion transport depends strongly on the properties of the paracellular pathway. To elucidate the role of the tight junction protein claudin-10 in TAL function, we generated mice with a deletion of Cldn10 in this segment. We show that claudin-10 determines paracellular sodium permeability, and that its loss leads to hypermagnesemia and nephrocalcinosis. In isolated perfused TAL tubules of claudin-10-deficient mice, paracellular permeability of sodium is decreased, and the relative permeability of calcium and magnesium is increased. Moreover, furosemide-inhibitable transepithelial voltage is increased, leading to a shift from paracellular sodium transport to paracellular hyperabsorption of calcium and magnesium. These data identify claudin-10 as a key factor in control of cation selectivity and transport in the TAL, and deficiency in this pathway as a cause of nephrocalcinosis.

Whereas regulation of transporters and channels involved in trans-cellular ion transport has been characterized in much detail, the functional and molecular determinants of paracellular ion trans­port in the kidney remain incompletely understood. In the thick ascending limb (TAL) of Henle’s loop, both trans-cellular and paracellular ion transport pathways contribute to reabsorption of Na+, Cl−, Mg2+, and Ca2+. Na+ and Cl− are reabsorbed mostly transcellularly by the concerted action of chan­nels and transporters. Mutations in five of the genes involved lead to Bartter syndrome, a disorder characterized by salt wasting and polyuria. Whereas Cl− is transported exclusively transcellularly, ∼50% of the Na+ load, as well as Ca2+ and Mg2+, are reabsorbed via paracellular pathways. In the TAL, this paracellular route is highly cation-selective. The paracellular passage is largely controlled by the tight junction (TJ), a supramolecular structure of membrane-spanning proteins, their intracellular adapters, and scaffolding proteins. Claudins, a family comprising 27 members, are the main components of the TJ defining the permeability properties. They interact via their extracellular loops with corre­sponding claudins of the neighboring cell to allow or restrict pas­sage of specific solutes (5, 6). In the kidney, their expression pattern is closely related to the corresponding segment-specific solute reabsorption profile. Several claudins are expressed in the TAL, including claudin-16, -19, -10, -3, and -18 The importance of claudin-16 and -19 in this tissue is documented by mutations in CLDN16 and CLDN19, which cause familial hypomagnesemia, hypercalciuria, and nephrocalcinosis, an autosomal recessive dis­order that leads to end-stage renal disease. The relevance of CLDN16 for paracellular reabsorption of Mg2+ and Ca2+ was confirmed in mouse models with targeted gene disruption. In addition, claudin-14, expressed in the TAL of mice on a high-calcium diet, was identified as negative regulator of claudin-16 function (15), and sequence variants in CLDN14 have been asso­ciated with human kidney stone disease. The functional significance of claudin-10, which is also ex­pressed in the TAL, remains unclear. This TJ protein is expressed in two isoforms, claudin-10a and claudin-10b, which differ in their first extracellular loop. In cultured epithelial cells, heter-ologous expression of claudin-10a increases paracellular anion transport, whereas claudin-10b expression increases paracellular cation transport. Both isoforms are expressed differentially along the nephron, with claudin-10a found predominantly in cortical segments, whereas claudin-10b is enriched in the medullary region.  In the present study we generated a mouse model with a TAL-specific Cldn10 gene defect to query the role of this protein in renal paracellular in transport in vivo. We found that claudin-10 is crucial to paracellular Na+ handling in the TAL, and that its absence leads to a shift from paracellular sodium transport to paracellular hyperreabsorption of Ca2+ and Mg2+.

Analysis of claudin-10 expression in the kidney. (A) Western blot analysis of kidney membrane extracts from control (ctr) and cKO mice. A dramatic reduction in claudin-10 protein can be seen in kidneys of cKO mice. Levels of the TJ marker occludin are unchanged. (B) Gene expression analysis of Cldn10 variants on cDNA from isolated segments of the nephron. (C) Immunohistological detection of claudin-10 and markers for PCT (NHE3) and TAL (NKCC2) on sections from control mice (ctr) and cKO mice demonstrates no difference in the signal for claudin-10 in the PCT between WT and cKO. Claudin-10 is expressed in TAL tubules positive for NKCC2. No specific clau-din-10 staining is evident in the TAL of cKO mice. Claudin-10 is detected in TJs positive for ZO-1. This signal is absent in cKO mice, whereas ZO-1 staining is unchanged. (Scale bar: 25 μm.)

In control animals, claudin-10 is located mainly in the TAL, as documented by coimmunostaining with the Na+K+2Cl− cotrans-porter (NKCC2). In this segment, a large portion of the claudin-10 immunofluorescence signal is located outside of the TJ; however, claudin-10 is present in the TJ, as demonstrated by colocalization with the TJ protein ZO-1. PCTs positive for the sodium-proton exchanger NHE-3 showed a considerably weaker signal restricted to the TJ area. Claudin-10 immunoreactivity was virtually absent in NKCC2-positive tubules of cKO mice, in line with the activity of Cre recombinase in this cell type. The immu-noreactivity of claudin-10 in PCTs of cKOs remained unchanged, however. ZO-1 staining in TAL sections of cKOs was unchanged compared with controls, indicating no unspecific effect on TJ structures. The TJ localization of claudin-16 and claudin-19 in medullary rays was similar in cKOs and controls.   To investigate the phenotypic consequences of renal claudin-10 deficiency, we per­formed a histological examination of the kidneys of 10-wk-old cKO mice and their respective controls. Kidneys from cKO mice contained extensive medullary calcium deposits, as revealed by von Kossa and alizarin red S staining. The deposits were found along the outer stripe of the outer medulla. The detection of extensive calcification suggests alterations in renal ion homeostasis in mice deficient for claudin-10.  Serum Na+ and Cl− levels and their renal FE excretion rates were not different be­tween genotypes. In addition, serum creatinine and glomerular filtration rate were not altered compared with controls. Taken together, these findings indicate that calcium deposition does not nonpecifically affect overall glomerular or tubular function.

Fig 4. Gene expression analysis of renal claudins (A) and representative renal ion transporters and channels (B) by real-time PCR. Cldn10 deficiency results in differential gene expression of several genes. Values from cKO animals are shown relative to control mice (mean ± SEM). Wnk1, Wnk1-KS, Kcnj1, and Trpm6, n = 5/4; all other genes, n = 10/10. *P < 0.05; **P < 0.01; ***P < 0.001.    The thiazide-sensitive NaCl cotransporter NCC (Slc12a3), the protein involved in NaCl absorption in the DCT, and the respective inhibitory, kidney-specific kinase-defective KS-WNK1 were expressed at lower levels in the cKO mice. Taken together, these data suggest specific compensatory alterations in components of both paracellular and transcellular renal ion transport mechanisms in mice deficient in claudin-10 in the TAL.

Urinalysis demonstrated that the inhibition of TAL tubular transport by furosemide resulted in a completely differ­ent pattern of tubular Ca2+ and Mg2+ handling that identifies the TAL as the major nephron segment affected by claudin-10 deficiency.  Interestingly, the different effects on plasma Mg2+ and Ca2+ levels reflect the different major reabsorption sites of these ions. Some 60% of the filtered Mg2+ is reabsorbed in the TAL, compared with only 20% of the filtered Ca2+ load (20). Ca2+ hyperreabsorption in TAL seems to be balanced by reduced (proximal and) distal tubular Ca2+ transport. The hyperreabsorption of divalent cations in mice deficient in claudin-10 is in opposition to the loss of divalent cations seen in mouse models of claudin-16 deficiency and in human patients with mutation in CLDN16 or CLDN19. This finding indicates that claudins in the TAL have functions that differentially affect paracellular cation transport in this segment. Mice deficient for claudin-10b in the TAL exhibit decreased permeability for Na+ and increased permeability for Ca2+ and Mg2+, whereas in mice with claudin-16 or claudin-19 deficiency, decreased sodium per­meability in the TAL is paralleled by decreased reabsorption of Ca2+ and Mg2+.

1. Greger R (1981) Cation selectivity of the isolated perfused cortical thick ascending limb of Henle’s loop of rabbit kidney. Pflugers Arch 390:30–37.
2. Furuse M (2010) Molecular basis of the core structure of tight junctions. Cold Spring Harb Perspect Biol 2:a002907.
3. Konrad M, et al. (2006) Mutations in the tight-junction gene claudin 19 (CLDN19) are associated with renal magnesium wasting, renal failure, and severe ocular in­volvement. Am J Hum Genet 79:949–957.
4.  Simon DB, et al. (1999) Paracellin-1, a renal tight junction protein required for par-acellular Mg2+ resorption. Science 285:103–106.
5. Hou J, et al. (2007) Transgenic RNAi depletion of claudin-16 and the renal handling of magnesium. J Biol Chem 282:17114–17122.
6. Himmerkus N, et al. (2008) Salt and acid-base metabolism in claudin-16 knockdown mice: Impact for the pathophysiology of FHHNC patients. Am J Physiol Renal Physiol 295:F1641–F1647.

 PMID: 22891322  PMCID: PMC3435183   http://www.ncbi.nlm.nih.gov/pubmed/22891322

Paracellin-1 is critical for magnesium and calcium reabsorption in the human thick ascending limb of Henle.

Blanchard A, Jeunemaitre X, Coudol P, Dechaux M, Froissart M, et al.
Université Pierre et Marie Curie, INSERM and Laboratoire de Génétique Moléculaire, Hôpital Universitaire Européen Georges Pompidou, Paris, France. blanch@ccr.jussieu.fr
Kidney Int. 2001 Jun; 59(6):2206-15.

A new protein, named paracellin 1 (PCLN-1), expressed in human thick ascending limb (TAL) tight junctions, possibly plays a critical role in the control of magnesium and calcium reabsorption, since mutations of PCLN-1 are present in the hypomagnesemia hypercalciuria syndrome (HHS).
No functional experiments have demonstrated that TAL magnesium and calcium reabsorption were actually impaired in patients with HHS.
Genetic studies were performed in the kindred of two unrelated patients with HHS.

We found two yet undescribed mutations of PCLN-1 (Gly 162 Val, Ala 139 Val). In patients with HHS, renal magnesium and calcium reabsorptions were impaired as expected; NaCl renal conservation during NaCl deprivation and NaCl tubular reabsorption in diluting segment were intact. Furosemide infusion in CS markedly increased NaCl, Mg, and Ca urinary excretion rates. In HHS patients, furosemide similarly increased NaCl excretion, but failed to increase Mg and Ca excretion. Acute MgCl(2) infusion in CS and ERH patient provoked a dramatic increase in urinary calcium excretion without change in NaCl excretion. When combined with MgCl(2) infusion, furosemide infusion remained able to induce normal natriuretic response, but was unable to increase urinary magnesium and calcium excretion further. In HHS patients, calciuric response to MgCl(2) infusion was blunted.

In patients with HHS, levels of circulating renin and aldosterone were normal, suggesting normal blood and extracellular volume. In addition, HHS patient 2 was normally able to lower her sodium excretion below 10 mmol/day during sodium deprivation, and in HHS pa­tient 1, sodium reabsorption in the diluting segment was normal as assessed by hypotonic saline infusion.  After oral NH4Cl load: Minimal urinary pH was 5.8 (normal value <5.4), and maximal net acid excretion reached only 24 pmol/min (normal value >80). Both subjects had hypocitraturia. The latter data suggested in the two probands distal defect of urinary acidification, probably related to nephrocalcinosis.

Because the filtered load of calcium but not the filtered load of magnesium remains unchanged during acute magnesium infusion in humans, the increase in calcium excretion is a better index of the inhibitory effect of peritubular magnesium on renal tubular divalent cation transport.  Urinary sodium excretion remained almost constant in both subjects during MgCl2 infusion (data not shown). Accordingly, the FECa/FENa ratio, which should remain constant if sodium reabsorption was primarily affected, increased in the CS and EHR patient.  Before the furosemide infusion, serum ultrafilterable (UF) Ca concentrations were similar in patients with HHS and the controls. However, Ca excretion markedly differed and was approximately five times higher in HHS patients than in controls.

In the two patients with homozygous mutations in the PCLN-1 gene, an impairment in renal tubular magne­sium and calcium reabsorption with normal NaCl recla­recla­mation was demonstrated. Accordingly, comparative studies performed under baseline condition in one pa­tient with ERH and in HHS patients demonstrated that the magnesium and calcium excretion in HHS patients were inappropriately high when compared with serum magnesium and calcium concentrations. However, renal NaCl reabsorption in HHS patients was intact. There was no clinical evidence of extracellular fluid volume  contraction. Furthermore, basal circulating renin and aldosterone concentrations were normal and adapted to the normal Na intake. Finally, abnormal NaCl reclama­tion in the diluting segment of the nephron was excluded in one patient, while the other was able to adapt normally to a sodium deprived diet.

This study is the first to our knowledge to demonstrate that homozygous mutations of PCLN-1 result in a selective defect in paracellular Mg and Ca reabsorption in the TAL, with intact NaCl reabsorption ability at this site. In addition, the study supports a selective physiological effect of basolateral Mg(2+) and Ca(2+) concentration on TAL divalent cation paracellular permeability, that is, PCLN-1 activity.   PMID: 11380823   http://www.ncbi.nlm.nih.gov/pubmed/11380823

Development of a Novel Sodium-Hydrogen Exchanger Inhibitor for Heart Failure

Elizabeth Juneman*, Reza Arsanjani, Hoang M Thai, Jordan Lancaster, Jeffrey B Madwed, Steven Goldman
Citation: Elizabeth Juneman, et al. (2013) Development of a Novel Sodium-Hydrogen Exchanger Inhibitor for Heart Failure. J Cardio Vasc Med 1: 1-6

This study was designed to determine the potential therapeutic effects of a new sodium-hydrogen exchanger (NHE-1) inhibitor in the rat coronary artery ligation model of chronic heart failure. After the induction of acute myocardial infarction, rats were entered randomly dose dranging from 0.3 mg/kg, 1.0 mg/kg, and 3.0 mg/kg. Solid state micrometer hemodynamics, echocardiographic, and pressure-volume relationships were measured after 6 weeks of treatment. Treatment with this NHE- 1 inhibitor at 3 mg/kg increased (P< 0.05) ejection fraction from 23±3% (N=6) to 33±2% (N=13) while the 1 mg/kg dose decreased (P< 0.05) the infarct size in CHF rats from 21.7±1.4% (N=7) to 15.9±0.7% (N=3) and prevented (P< 0.05) dilatation of the left ventricle in CHF rats in diastole (1.0±0.1 cm, N=6) to 0.9±0.1 cm, N=10) and in systole (0.9±0.1 cm, N=6) to 0.8±0.1, N=10). These study results suggest that this new NHE-1 inhibitor may be potentially useful in treating CHF with an improvement in maladaptive left ventricule remodeling. Because the mechanism of action of this agent is entirely different than the currently applied approach in treating CHF that focuses on aggressive neurohormonal blockade and because this agent does not adversely affect important hemodynamic variables, further investigations with this agent may be warranted.

Keywords: Congestive heart failure; Sodium/hydrogen exchange; Cardiovascular disease; Cardiovascular drugs; CHF: Chronic Heart Failure; NHE-1: Sodium-Hydrogen Exchanger; NCX: Sodium-Calcium Exchanger; Ca2+: Calcium; Na+: Sodium; Na+-K+ATPase: Sodium-Potassium ATPase; NKCC: Sodium-Potassium-Chloride co-transporter; MI: Myocardial Infarction; BI: Boehringer Ingelheim; LV: left Ventricle; EF: Ejection Fraction; LVD: left ventricular dysfunction; PV: Pressure-Volume; SE: Standard Error; ARB: Angiotensin Receptor Blocker; ACE: Angiotensin Converting Enzyme

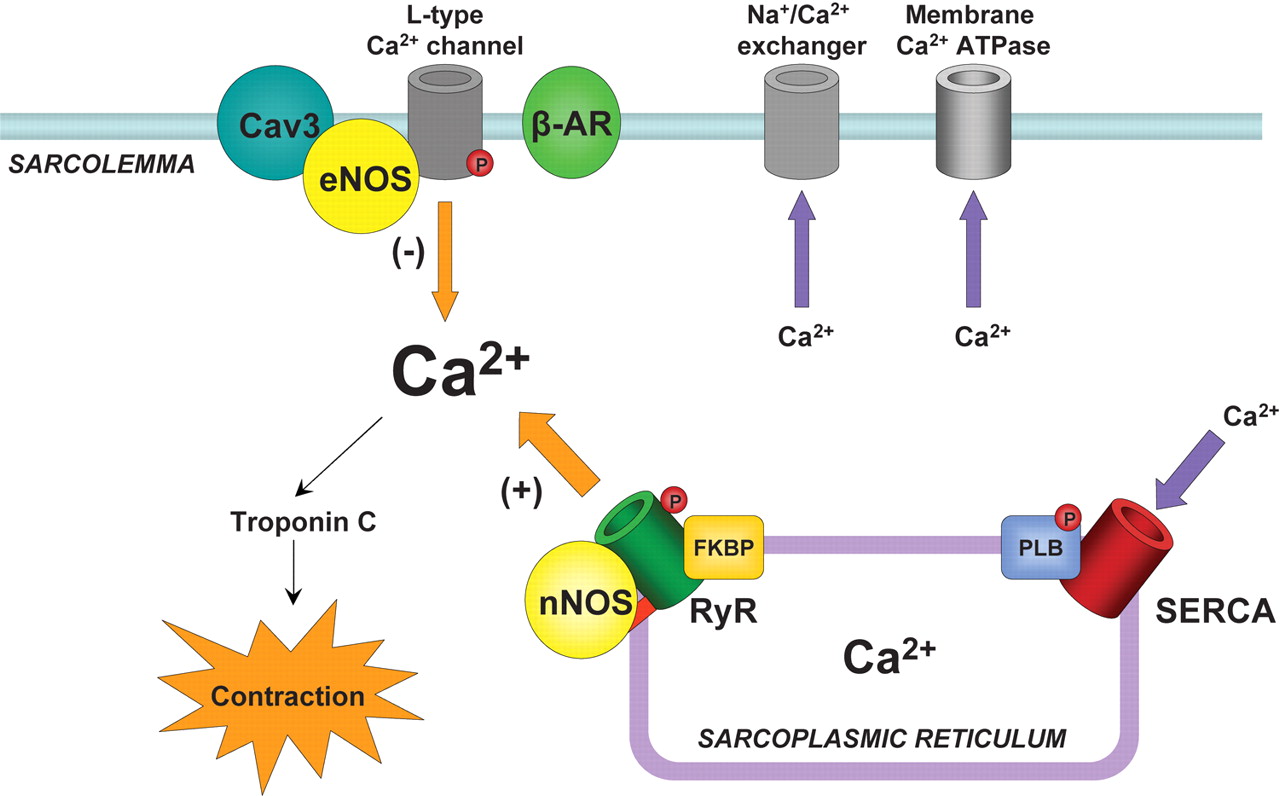
Without reviewing the pathophysiology of CHF here, altered calcium (Ca2+) handling is a hallmark of CHF. Intracellular Ca2+ concentration is closely regulated by sodium-calcium exchanger (NCX) and Ca2+ efflux is dependent on the intracellular sodium (Na+) concentration and trans-sarcolemmal Na gradient. Multiple channels including sodium-potassium ATPase (Na+-K+ ATPase), sodium-hydrogen exporter (NHE), sodium-bicarbonate co-transporter, sodium-potassium-chloride co-transporter (NKCC), and sodium-magnesium exchanger are responsible for regulation of intracellular sodium in cardiac myocytes. The intracellular concentration of Na+ is significantly increased in heart failure, primarily due to influx of Na+. The NHE plays an integral part in rise of intracellular Na+ concentration and development of hypertrophy in heart failure. Because of its multifaceted role in myocardial function, there has been interest in examining the effects of NHE-1 inhibitors in heart failure.

In this study we report the physiologic responses of a new NHE-1 inhibitor, in a rodent model of heart failure. Previous evaluation of the pharmacokinetic properties of this agent in rat and dog revealed low clearance and robust oral bioavailability, suggesting a potential for once daily oral administration. This new compound was found to be potentially effective in preventing ischemic injury in isolated cells systems and in ischemic injury in isolated cells systems and in a Langendorff isolated heart preparation. Based on these encouraging a pharmacokinetic data, and the established preclinical roof of principle, the next step in new drug development was to test this inhibitor in an appropriate disease-relevant animal model. For this, we chose the rat coronary ligation model of CHF, which is the established model of chronic ischemic heart failure and well performed in our laboratory. The model with permanent occlusion of the left coronary artery is important because this model a similar to the clinical syndrome of CHF. This rat coronary artery model of CHF is the same model used in the classic study defining the beneficial use of angiotensin converting enzyme inhibition with captopril in the treatment of CHF. Thus results in this model have the potential to be predictive of the clinical response seen in patients.

Results

In vivohemodynamic effect of NHE1: As noted previously by our laboratory, rats with severe CHF compared to Sham had changes (P< 0.05) in right ventricular weight, mean arterial pressure, tau, the time constant of LV relaxation, LV systolic pressure, LV end-diastolic pressure, +LVdP/dt, -LVdP/dt, dead volume and peak developed pressure. In this study, treatment resulted in no changes in body weight, chamber weight or hemodynamics. Because we stopped the lowest dose (0.3 mg/kg) there are only hemodynamic data with this dose in rats with CHF.

Echocardiographic changes in LV function and Dimensions with NHE1: Rats with CHF have decreases in EF accompanied by increases in LV systolic and diastolic dimensions. There was no change in anterior wallsystolic displacement. These data are consistent with other reports in this model showing that at 6 weeks after left coronary artery ligation, rats with large MIs have dilated left ventricles with LV remodeling and poor LV function (14,15). Treatment with the highest dose of 3 mg/kg increased (P< 0.05) ejection fraction from 23±3% (N=6) to 33±2% (N=13). Treatment with 1 mg/kg prevented maladaptive LV remodeling, it prevented (P< 0.05) dilatation of the LV in CHF rats in diastole (1.0±0.1 cm, N=6) to 0.9±0.1 cm, N=10) and in systole (0.9±0.1 cm, N=6) to 0.8±0.1, N=10) with no change anterior wall thickening.

Pressure-Volume relationships:  Although there are no significant changes in the PV relationships for either the Sham or CHF rats, there is a trend for the PV loop in CHF to be shifted toward the pressure axis with treatment. These data are consistent with the trend toward decreases in LV dimensions seen with treatment in CHF rats.

Discussion

This study can be viewed as a corollary of a pilot Phase II clinical trial to look for a signal of a beneficial physiologic effect of this new NHE-1 inhibitor in CHF. In terms of drug development, this is an appropriate approach, i.e., take an agent with a therapeutic focus, with an acceptable toxicology profile, alter its pharmacokinetics to improve its oral delivery and bioavailability and then study the drug in an appropriate animal model. The administration of this agent to rats with CHF after left coronary artery ligation resulted in a therapeutic benefit with an increase in EF and a decrease in infarct size in rats with the largest infarcts. There is a suggestion of the prevention of LV remodeling with decreases in LV end-diastolic and end-systolic dimensions accompanied by a similar trend in the PV loop with a shift toward the pressure axis. There were no changes in hemodynamics.

Importantly, the decrease in infarct size with no changes in hemodynamicswould positively affect LV remodeling by minimizing LV dilatation without changes in LV afterload. From a therapeutic perspective, an agent like this may be advantageous in the treatment of heart failure after MI. The lack of hemodynamic changes is not a clinical problem because we already have agents that decrease afterload and lower LV end-diastolic pressure such as angiotensin converting enzyme (ACE) inhibitors and angiotens in receptor blockers (ARBs). In treating CHF, we also have diuretics to control blood volume, which in turn reduces LV end-diastolic pressure. The other potential advantage of an NHE-1 inhibitor is that as opposed to our current use of aggressive neurohormonal blockade, this represents a different approach to treating CHF. This is attractive because we essentially have exhausted or maximized our effects of neurohumoral blockade and with no real new treatments for CHF introduced in the last 10-15 years, need to look for other approaches to treat CHF.

Drug development is obviously a complicated and expensive undertaking. In exploring this agent, we would proposea stepwise approach. In this case with an agent whose analogs have been studied extensively, our thought would be to perform a larger dose ranging study in CHF rats to define dose response curves for systolic function as well as obtain more information on pharmacokinetics, as well as diastolic function and structural changes.

An attractive aspect of this work is that we are examining an agent with a different mechanisms of action that current treatments for heart failure. The stimulus to study the agent in an animal model of heart failure was based on multifaceted roles of sodium-hydrogen exchangers on myocardial function. Nine isoforms of NHE have currently been identified, with NHE- 1 being the predominant isoform in the plasma membrane of the myocardium [3,24]. Because NHE is activated by intracellular acidosis, angiotensin II, and catecholamines, its activity is expectedly increased in heart failure. Inhibition of NHE-1 has previously been associated with decreased fibrosis, apoptosis, preserved contractility, and attenuation of hypertrophy and development of heart failure.

1. Baartscheer A, van Borren MMGJ (2008) Sodium Ion Transporters as New Therapeutic Targets in Heart Failure. Cardiovasc Hematol Agents Med Chem 6: 229-236.
2. Murphy E, Eisner DA (2009) Regulation of Intracellular and Mitochondrial Sodium in Health and Disease. Circ Res 104: 292-303
3. Despa S, Islam MA, Weber CR, Pogwizd SM, Bers DM (2002) Intracellular Na(+) Concentration is Elevated in Heart Failure but Na/K Pump Function is Unchanged. Circulation 105: 2543-2548.
4. Baartscheer A, Schumacher CA, van Borren MMGJ, Belterman CNW, Coronel R, et al. (2003) Increased Na+/H+-Exchange Activity is the Cause of Increased [Na+]i and Underlies Disturbed Calcium Handling in the Rabbit Pressure and Volume Overload Heart Failure Model. Cardiovasc Res 57: 1015-1024.
5.  Pieske B, Houser SR (2003) [Na+]i Handling in the Failing Human Heart. Cardiovasc Res 57: 874-886.
6.  Engelhardt S, Hein L, Keller U, Klämbt K, Lohse MJ (2002) Inhibition of Na(+)-H(+) Exchange Prevents Hypertrophy, Fibrosis, and Heart Failure in Beta(1)- Adrenergic Receptor Transgenic Mice. Circ Res 90: 814-819.
7.  Chen L, Chen CX, Gan XT, Beier N, Scholz W, et al. (2004) Inhibition and Reversal of Myocardial Infarction-Induced Hypertrophy and Heart Failure by NHE-1 Inhibition. Am J Physiol Heart Circ Physiol 286: 381-387.
8.  Marano G, Vergari A, Catalano L, Gaudi S, Palazzesi S, et al. (2004) Na+/ H+ Exchange Inhibition Attenuates Left Ventricular Remodeling and Preserves Systolic Function in Pressure-Overloaded Hearts. Br J Pharmacol 141: 526-532.
9. Goldman S, Raya TE (1995) Rat Infarct Model of Myocardial Infarction and Heart Failure. J Card Fail 1: 169-177.
10. Gaballa MA, Goldman S (2002) Ventricular Remodeling in Heart Failure. J Card Fail. 8: 476-485.
11. Pfeffer MA, Pfeffer JM, Steinberg C, Finn P (1985) Survival After Experimental Myocardial Infarction: Beneficial Effects of Long-Term Therapy with Captopril. Circulation 72: 406-412.
12. Raya TE, Gay RG, Aguirre M, Goldman S (1989) Importance of Venodilatation in Prevention of Left Ventricular Dilatation after Chronic Large Myocardial Infarction in Rats: A Comparison of Captopril and Hydralazine. Circ Res 64: 330-337.

Related articles in Pharmaceutical Intelligence:

Part I: Identification of Biomarkers that are Related to the Actin Cytoskeleton

Larry H Bernstein, MD, FCAP

http://pharmaceuticalintelligence.com/2012/12/10/identification-of-biomarkers-that-are-related-to-the-actin-cytoskeleton/

Part II: Role of Calcium, the Actin Skeleton, and Lipid Structures in Signaling and Cell Motility

Larry H. Bernstein, MD, FCAP, Stephen Williams, PhD and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/08/26/role-of-calcium-the-actin-skeleton-and-lipid-structures-in-signaling-and-cell-motility/

Part III: Renal Distal Tubular Ca2+ Exchange Mechanism in Health and Disease

Larry H. Bernstein, MD, FCAP, Stephen J. Williams, PhD
 and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/09/02/renal-distal-tubular-ca2-exchange-mechanism-in-health-and-disease/

Part IV: The Centrality of Ca(2+) Signaling and Cytoskeleton Involving Calmodulin Kinases and Ryanodine Receptors in Cardiac Failure, Arterial Smooth Muscle, Post-ischemic Arrhythmia, Similarities and Differences, and Pharmaceutical Targets

Larry H Bernstein, MD, FCAP, Justin Pearlman, MD, PhD, FACC and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/09/08/the-centrality-of-ca2-signaling-and-cytoskeleton-involving-calmodulin-kinases-and-ryanodine-receptors-in-cardiac-failure-arterial-smooth-muscle-post-ischemic-arrhythmia-similarities-and-differen/

Part V: Heart, Vascular Smooth Muscle, Excitation-Contraction Coupling (E-CC), Cytoskeleton, Cellular Dynamics and Ca2 Signaling

Larry H Bernstein, MD, FCAP, Justin Pearlman, MD, PhD, FACC and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/08/26/heart-smooth-muscle-excitation-contraction-coupling-cytoskeleton-cellular-dynamics-and-ca2-signaling/

Part VI: Calcium Cycling (ATPase Pump) in Cardiac Gene Therapy: Inhalable Gene Therapy for Pulmonary Arterial Hypertension and Percutaneous Intra-coronary Artery Infusion for Heart Failure: Contributions by Roger J. Hajjar, MD

Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/08/01/calcium-molecule-in-cardiac-gene-therapy-inhalable-gene-therapy-for-pulmonary-arterial-hypertension-and-percutaneous-intra-coronary-artery-infusion-for-heart-failure-contributions-by-roger-j-hajjar/

Part VII: Cardiac Contractility & Myocardium Performance: Ventricular Arrhythmiasand Non-ischemic Heart Failure – Therapeutic Implications for Cardiomyocyte Ryanopathy (Calcium Release-related Contractile Dysfunction) and Catecholamine Responses

Justin Pearlman, MD, PhD, FACC, Larry H Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/08/28/cardiac-contractility-myocardium-performance-ventricular-arrhythmias-and-non-ischemic-heart-failure-therapeutic-implications-for-cardiomyocyte-ryanopathy-calcium-release-related-contractile/

Part VIII: Disruption of Calcium Homeostasis: Cardiomyocytes and Vascular Smooth Muscle Cells: The Cardiac and Cardiovascular Calcium Signaling Mechanism

Justin Pearlman, MD, PhD, FACC, Larry H Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/09/12/disruption-of-calcium-homeostasis-cardiomyocytes-and-vascular-smooth-muscle-cells-the-cardiac-and-cardiovascular-calcium-signaling-mechanism/

Part IX: Calcium-Channel Blockers, Calcium Release-related Contractile Dysfunction (Ryanopathy) and Calcium as Neurotransmitter Sensor

Justin Pearlman, MD, PhD, FACC, Larry H Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN

Part X: Synaptotagmin functions as a Calcium Sensor: How Calcium Ions Regulate the fusion of vesicles with cell membranes during Neurotransmission

Larry H Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN

68-76.hwp

pone.0070764.g006  Morpholino knockdown of aquaporin-1a1 reduces water influx.       NIHMS262281.html

nihms81087f1  Localization of claudin proteins in mammalian kidney.      F1.medium  intracellular Mg2+ in normal and Mg2+ depleted immortalized mouse distal convoluted tubule (MDCT) cells

F2.small  membrane voltage influences Mg2+ uptake in MDCT cells    pnas.1203834109fig04  Gene expression analysis of renal claudins

Read Full Post »

The Affordable Care Act: A Considered Evaluation.

Part I.  The legislative act (ACA) and the model for implementation (Insurance Gateways).

Writer and Curator: Larry H. Bernstein, MD, FCAP
and
Curator and Editor: Aviva Lev-Ari, PhD, RN 
This discussion is composed as two distinct chapters.  The first is a clarification of what is contained in the Affordable Care Act (ACA), the model of care it is crafted from, the insurance mandate, the inclusion of groups considered high risk and uninsured, the inclusion of groups low risk and uninsured, and the economics involved in going from a fractured for profit health care industry to a more stable coverage for patients.  The second is taken from selected articles on the care process and the cost and consequences for improving quality at lower cost.   There are inherent problems at looking at this from a systems point of view, mainly impacted by the relationship of providers to hospitals and clinics, and by the relationships of insurers to the patients and providers in an Accountable Care Organization (ACO) model.
This article has the following two parts:

Part I. The legislative act (ACA) and the model for implementation (Insurance Gateways).

Part II.  The Implementation of the ACA, Impact on Physicians and Patients, and the Dis-Ease of the Accountable Care Organizations.

Part I

The legislative act (ACA) and the model for implementation (Insurance Gateways)

A. Access and Coverage of Healthcare Reform Mandate

About 2.5 million young adults from age 19 to 25 attained health coverage as a result of the Affordable Care Act, which took effect in September 2010, according to the U.S. Department of Health and Human Services. Prior to the law’s approval, some 13.7 million young adults were uninsured, nearly one-third of the nation’s total uninsured population, according to the nonprofit Kaiser Family Foundation.
Employer-sponsored health insurance forms the backbone of our health insurance system. This leaves small businesses difficult to provide their workers with comprehensive coverage. In 2007, only 25 percent of employees in small businesses had coverage through their own employers, compared with 74 percent of workers in large firms. Moreover, there are few sources of affordable coverage outside the employer-based system, leaving millions of employees in small businesses uninsured or with inadequate health insurance. In 2007, half as many workers in small businesses were uninsured or underinsured compared to employees in large businesses. Congressional health reform bills to reform the health system include provisions specifically aimed at helping small businesses and their employees gain access to affordable, comprehensive coverage.  Then there is another issue since the “Great Recession” of 2008, that there is no stable coverage for an unemployed workforce and indigent families with competing needs for food and health.  (Kaiser Health News, 2009; 67).
The law created insurance exchanges to close the gap.  Employer interest in insurance exchanges is growing. The Kaiser Family Foundation found that 29% of employers with 5,000 or more employees are considering private exchanges as an option for buying healthcare coverage for their employees. A day later, consulting firm Towers Watson released its Health Care Changes Ahead survey, which found that 37% of employers think private exchanges are a reasonable alternative to traditional employer coverage in 2014.
See Figure.  M. M. Doty, S. R. Collins, S. D. Rustgi, and J. L. Nicholson, Out of Options: Why So Many Workers in Small Businesses Lack Affordable Health Insurance, and How Health Care Reform Can Help, The Commonwealth Fund, September 2009.

Changes in Health Insurance Coverage in the Great Recession, 2007-2010

This issue brief examines changes in health insurance coverage over the last decade, with a focus on how changes in the economy, particularly during the “Great Recession” of 2007 to 2009, have affected coverage and the number of uninsured. The paper finds that the number of uninsured grew substantially during the first recession of the decade, increasing by 5 million people from 2000 to 2004; increased more slowly during the brief recovery, growing by 2.1 million people from 2004 to 2007; and then again rose significantly during the Great Recession, rising by 5.7 million people since 2007.
The paper also finds that coverage, especially for children, through the Medicaid and Children’s Health Insurance Programs helped to prevent even more people from being uninsured. While the number of uninsured children declined in recent years, the number of uninsured adults rose. The only notable drop in uninsured adults was for young adults ages 19-25 in 2010, most likely due to the provision of the health reform law that permits young adults to stay on their parents’ insurance. The paper also considers trends in coverage by work status, race and ethnicity, citizenship status and geographical region.
http://kff.org/medicaid/issue-brief/changes-in-health-insurance-coverage-in-the/

Uninsured adults with chronic conditions or disabilities: gaps in public insurance programs.

Pizer SD, Frakt AB, Iezzoni LI. US Department of Veterans Affairs in Boston, MA. 

Health Aff (Millwood). 2009;28(6):w1141-50. http://dx.doi.org/10.1377/hlthaff.28.6.w1141
http://www.ncbi.nlm.nih.gov/pubmed/19843552
Among nonelderly U.S. adults (ages 25-61), uninsurance rates increased from 13.7 percent in 2000 to 16.0 percent in 2005. Despite the existence of public insurance programs, rates remained high for low-income people reporting serious health conditions (25 percent across years) or disabilities (15 percent). Previous research has established that low-income workers, those facing more stringent Medicaid eligibility requirements, and people employed by smaller firms are more likely than others to lack health insurance. Residents of southern states had even higher rates (32 percent with health conditions, 22 percent with disabilities). Those who did not belong to a federally mandated Medicaid eligibility category were about twice as likely as others to be uninsured overall, and uninsurance among this group increased more rapidly over time.
To address this growing problem, President Barack Obama and leaders in Congress passed health insurance reform legislation that is still taking shape. A common feature of the major proposals at this point is that coverage would be expanded by building on existing arrangements. This approach allows people to keep their current insurance if they wish to do so. The Medicaid program is particularly complicated because it is jointly financed and operated by the federal and state governments and because each state has implemented it differently.
See Table 1.

Ultimately, if Congress decides not to eliminate categorical eligibility restrictions, our results indicate that the preservation of eligibility expansions for people with disabilities or chronic conditions would target a population that is particularly vulnerable to uninsurance and its deleterious effects on health.

How Many Are Underinsured? Trends Among U.S. Adults, 2003 And 2007

Cathy Schoen, Sara R. Collins, Jennifer L. Kriss and Michelle M. Doty
Health Aff 2008; 27(4) w298-w309  http://dx.doi.org/10.1377/hlthaff.27.4.w298
With health insurance moving toward greater patient cost sharing, this study finds a sharp increase in the number of underinsured people. Based on indicators of cost exposure relative to income, as of 2007 an estimated twenty-five million insured people ages 19–64 were underinsured—a 60 percent increase since 2003. The rate of increase was steepest among those with incomes above 200 percent of poverty, where underinsurance rates nearly tripled. In total, 42 percent of U.S. adults were underinsured or uninsured. The underinsured report high levels of access problems and financial stress. The findings underscore the need for policy attention to benefit design, to assure care and affordability.
See Table 1 and Table 2
About seven in ten underinsured adults had annual incomes below $40,000 or below 300 percent of poverty—similar to the income distribution of the uninsured. In contrast, nearly two-thirds of those with more adequate insurance had incomes above $40,000. Underinsured adults were more likely than either of the other two groups to have health problems.
Based on a composite access indicator that included going without at least one of four needed medical care services, more than half of the underinsured and two-thirds of the uninsured reported cost-related access problems during the year. Among adults with at least one chronic health problem, half of uninsured adults and two in five underinsured adults said that they skipped doses of or did not fill a prescription for their condition because of cost—double to triple the rate reported by those insured all year, not underinsured.

Healthcare Costs: Another Top 1% Issue

By Chris Kaiser, Cardiology Editor, MedPage Today  Sep 11, 2013  http://www.medpagetoday.com/TheGuptaGuide/PublicHealth/41539

In the U.S., the top 1% of patients ranked by their healthcare expenses accounted for 21% of total healthcare expenditures in 2010, with an annual mean expenditure of $87,570, according to 2010 Medical Expenditure Panel Survey from the Agency for Healthcare Research and Quality in Rockville, Md.  In addition, the top 5% of the U.S. population ranked by healthcare expenses accounted for half of the total of healthcare expenditures, with an annual mean expenditure of $40,876, wrote Steven B. Cohen, PhD, and Namrata Uberoi, MPH, in the Statistical Brief No. 421.  Both of these figures are down from 1996, when the top 1% accounted for 28% of the total healthcare expenditures and the top 5% accounted for slightly more than half.  The total healthcare expenditures for 2010 were $1.26 trillion.

It is important that policy makers are aware of the the “concentration of healthcare expenditures … to help discern the factors most likely to drive healthcare spending and the characteristics of the individuals who incur them,” the authors noted.

Overall, there was a huge divide between the top and bottom 50% of the population in terms of total healthcare expenses. The top 50% accounted for 97% of total healthcare costs, while the lower 50% accounted for only 3% of the total healthcare expenditures.  In terms of income status,

  • the top 5% of those designated as poor accounted for 57% of the total healthcare expenditures, with an annual mean expenditure of $46,600, while
  • the top 5% of those in the highest income group accounted for 45% of the total healthcare expenditures, with an annual mean expenditure of $40,800.

The report also broke down healthcare spending by the number of chronic conditions, age, race/ethnicity, sex, and insurance. The survey found that chronic diseases take a big chunk of healthcare dollars.

The top 5% of those with four or more chronic conditions accounted for 30% of all healthcare expenditures, with an annual mean of $82,000 — a figure that is

  • seven times higher than those in the top 5% with no chronic diseases and nearly
  • three times higher than the top 5% with one chronic condition.

A report from 2012 found that Medicare could cut up to 10% of its spending if it focused on chronic disease prevention and coordinated care for those with chronic conditions.   Conditioned on insurance coverage status, the uninsured had the most concentrated levels of healthcare expenditures and the lowest annual mean expenses. Regarding public insurance, the top 5% accounted for 56% of the total healthcare expenditures.

Virtually every state experienced deteriorating access to care for adults over the past decade

GM Kenney, S Zuckerman, D Goin, S McMorrow, Urban Institute  May 2012

We use the Behavioral Risk Factor Surveillance System (BRFSS) to examine state-level changes in three key access indicators over the past decade. Specifically, we explore changes in the likelihood of having unmet medical needs due to cost, receiving a routine checkup, and receiving a dental visit for all nonelderly adults and for the subgroup of uninsured adults. We also consider differentials in access between uninsured and insured adults within each state in 2010, and how these differences are reflected in the relationship between access to care and state-level uninsurance rates.

We find that the deterioration in access to care observed in national trends during the past decade was evident in virtually every state in the country. Similarly, consistent with the national trends, the situation deteriorated more for the uninsured than for other adults in most states, which exacerbated the differentials in access and use between the insured and uninsured that had prevailed at the beginning of the previous decade. At the end of the decade, the uninsured in every state were at a dramatic disadvantage relative to the insured across the three access measures we examined. This analysis suggests that the potential benefits of the coverage expansion in the Affordable Care Act (ACA) are large and exist in every state.

We also found that states with higher uninsurance rates have worse access to care for all three measures, which implies that these states have the most to gain from the ACA. In particular, the ACA coverage expansion has the potential to reduce unmet needs due to costs and other cost-related barriers, problems that are more severe in states with high uninsurance rates.

DOCUMENTATION ON THE URBAN INSTITUTE’S AMERICAN COMMUNITY SURVEY-HEALTH INSURANCE POLICY SIMULATION MODEL (ACS-HIPSM)

Matthew Buettgens, Dean Resnick, Victoria Lynch, and Caitlin Carroll    May 21, 2013

We use the Urban Institute’s American Community Survey – Health Insurance Policy Simulation Model (ACS-HIPSM) to estimate the effects of the Affordable Care Act on the non-elderly at the state and local level. This model builds off of the Urban Institute’s base HIPSM, which uses the Current Population Survey (CPS) as its core data set, matched to several other data sets including the Medical Expenditure Panel Survey-Household Component (MEPS-HC), to simulate changes under ACA. To create HIPSM-ACS, we apply the core behavioral components of the base HIPSM to ACS records to exploit the much larger sample size for more precise estimates at the state and sub-state level. The modeling on the ACS-HIPSM produces projections of coverage changes related to state Medicaid expansions, new health insurance options, subsidies for the purchase of health insurance, and insurance market reforms (see Appendix 1 for more detail on HIPSM).

We simulate eligibility for Medicaid/CHIP and subsidies using the Urban Institute Health Policy Center’s ACS Medicaid/CHIP Eligibility Simulation Model, which builds on the model developed for the CPS ASEC by Dubay and Cook.  (Dubay, L. and A. Cook. 2009. “How Will the Uninsured be Affected by Health Reform?” Washington, DC: Kaiser Commission on Medicaid and the Uninsured.)

We simulate both pre-ACA eligibility and the MAGI-based eligibility introduced by the ACA. This allows us to simulate different scenarios for Medicaid maintenance-of-eligibility under the ACA. The distinction between pre-ACA eligible and newly eligible is also important in determining the share of a beneficiary’s costs paid by the federal government.

Using the three-year pooled sample, the model simulates eligibility for comprehensive Medicaid and CHIP coverage or subsidy using available information on the regulations for implementing the ACA, including the amount and extent of income disregards for eligibility pathways that do not change under the ACA and for maintenance-of-eligibility for each program and state in place as of approximately June 2010.

Under the ACA income eligibility is based on the IRS tax definition of modified adjusted gross income (MAGI), which includes the following types of income for everyone who is not a tax-dependent child: wages, business income, retirement income, investment income, Social Security, alimony, unemployment compensation, and financial and educational assistance (see Modeling Unemployment Compensation in the appendix). MAGI also includes the income of any dependent children9 required to file taxes, which for 2009 is wage income greater than $5,700 and investment income greater than $950. To compute family income as a ratio of the poverty level, we sum the person-level MAGI across the tax unit.

Current eligibility is determined based on state rules for 2010. State rules include income thresholds for the appropriate family7 size, asset tests, parent/family status, and the amount and extent of disregards8, for each program and state in place as of the middle of 2010 .

we estimate two separate probit models, each with the following covariates:

  1. Age Category: 0 – 5, 6 – 18, 19 – 44, 45 – 64.
  2. Health Status
  3. Worker Status (Household Level)
  4. Wage (Logarithmic Transformation)
  5. HIU Income to Poverty Threshold Ratio
  6. Number of Children
  7. Presence of a child in Public Coverage
  8. Citizenship Status
  9. Number of Adults in the Family

The dependent variable is an indicator of non-group non-exchange policy holder status. Again we compare each respondent’s predicted probability to a standard uniform random number and assign enrollment in the non-group non-exchange to those observations with probabilities that exceed the random number. Appendix Table 5 shows the overall new enrollment in the non-group non-exchange coming out of our model. It shows that the large majority of non-group enrollees outside the exchange are expected to come from single-person policyholders.

We develop a model, again based on HIPSM output, to predict which single ESI policy holders in the ACS are likely to switch to a family plan. We restrict our model to HIUs in which there is at least one single policy holder and at least one other member of the HIU that could potentially be covered by an ESI family plan. The eligible dependents include those with baseline non-group or uninsurance that had not already taken up coverage in a previous model. Note that we only model moving from an individual plan to a family plan; we did not model adding a dependent to a current family plan. Within the eligible group of single ESI policy holders, we use the following covariates to estimate the probability that they will switch to a family ESI policy:

  1. HIU Type: Individual, Unmarried with child, Married without Child, or married with children
  2. Age Category: 0 – 5, 6 – 18, 19 – 44, 45 – 64.
  3. Health Status
  4.  Worker Status (Individual Level)
  5. •Wage (Logarithmic Transformation)
  6. •HIU Income to Poverty Threshold Ratio
  7. •HIU Income to Poverty Threshold Categories (<138% FPL, 138% – 200% FPL, 200% – 300% FPL, 300% – 400% FPL, 400%+ FPL)
  8. •Number of Children
  9.  Presence of a child in Public Coverage
  10.  Citizenship Status
  11.  Firm Size
  12.  Education Status

These estimates assume that the ACA is fully implemented with the Medicaid expansion in all states and that the same basic implementation decisions are made across the states. At the time of writing, even states such as Massachusetts which have been on the forefront of ACA implementation had not finalized their plans, so any modeling of variation in state decisions would necessarily involve a lot of guesswork. Also, it will take several years for enrollment in new programs such as the exchanges and Medicaid expansion to ramp up so the full effects that are estimated under the simulation model would not be felt until 2016 or later. Enrollment in the initial years would also be affected by state and federal decisions. For example, in the proposed rules released by HHS in January 2012, the deadline for establishing unified eligibility and enrollment between Medicaid and the exchange was pushed back to 2015.

Health insurance status change and emergency department use among US adults.

Ginde AA, Lowe RA, Wiler JL.
Department of Emergency Medicine, University of Colorado School of Medicine, Aurora, CO.   http://www.ncbi.nlm.nih.gov/pubmed/22450213 
Arch Intern Med. 2012 Apr 23;172(8):642-7.   http://dx.doi.org/10.1001/archinternmed
Recent events have increased the instability of health insurance coverage. We compared emergency department (ED) use by newly insured vs continuously insured adults and by newly uninsured vs continuously uninsured adults. Overall, 20.7% of insured adults and 20.0% of uninsured adults had at least 1 ED visit. However, 29.5% of newly insured adults compared with 20.2% of continuously insured adults had at least 1 ED visit. Similarly, 25.7% of newly uninsured adults compared with 18.6% of continuously uninsured adults had at least 1 ED visit. After adjusting for demographics, socioeconomic status, and health status, recent health insurance status change was independently associated with greater ED use for newly insured adults (incidence rate ratio [IRR], 1.32; 95% CI, 1.22-1.42 vs continuously insured adults) and for newly uninsured adults (IRR, 1.39; 95% CI, 1.26-1.54 vs continuously uninsured adults). Among newly insured adults, this association was strongest for Medicaid beneficiaries (IRR, 1.45) but was attenuated for those with private insurance (IRR, 1.24) (P < .001 for interaction). Recent changes in health insurance status for newly insured adults and for newly uninsured adults were associated with greater ED use.

Health Insurance and Access to Health Care in the United States

Catherine Hoffman, Julia Paradise
Annals of the New York Academy of Sciences 2008; 1136.    http://dx.doi.org/10.1196/annals.1425.007 
Reducing the Impact of Poverty on Health and Human Development: Scientific Approaches pages 149–160, June 2008

In the United States, where per capita health care costs are the highest in the world and continue to escalate, health insurance has become nearly essential. Having reasonable access to health care rests on many factors: the availability of health services in a community and personal care-seeking behavior, for example. However, these and other factors are often trumped by whether a person can afford the costs of needed care. Health insurance enables access to care by protecting individuals and families against the high and often unexpected costs of medical care, as well as by connecting them to networks and systems of health care providers.
Health insurance, poverty, and health are all interconnected in the United States. This article synthesizes a large and compelling body of health services research, finding a strong association between health insurance coverage and access to primary and preventive care, the treatment of acute and traumatic conditions, and the medical management of chronic illness. Moreover, by improving access to care, health insurance coverage is also fundamentally important to better health care and health outcomes. Research connects being uninsured with adverse health outcomes, including declines in health and function, preventable health problems, severe disease at the time of diagnosis, and premature mortality.
Most working-age adults obtain health coverage for themselves and their dependents as a benefit of employment. However, this benefit has been gradually eroding as health premiums, in tandem with higher health care costs, grow at a rate far outpacing rates of general inflation and wages. In 2005, 61% of the nonelderly had insurance through an employer, down from 66% in 2000.1 Low-wage workers are far less likely than higher-wage workers to have access to job-based coverage. In 2005, more than half of workers in poor families and more than a third of those in near-poor families had no offer of job-based coverage in the family.2 When it is available, health insurance is often unaffordable for low-income people, whose household budgets are strained to meet food, housing, and other basic needs.

Figure 1. Health insurance coverage of the nonelderly population, 2006.

http://onlinelibrary.wiley.com/store/10.1196/annals.1425.007/asset/image_n/NYAS_1136007_f1.gif    Source: Kaiser Commission on Medicaid and the Uninsured/Urban Institute analysis of Current Population Survey, March 2007.
Those with Medicaid coverage are the most likely to be in fair or poor health because the program’s eligibility requirements include being severely disabled and/or low-income (fig. 2).

Figure 2. Percentage of U.S. nonelderly population reporting fair or poor health, by income and insurance status, 2006.

http://onlinelibrary.wiley.com/store/10.1196/annals.1425.007/asset/image_t/NYAS_1136007_f2_thumb.gif       Source: Kaiser Commission on Medicaid and the Uninsured/Urban Institute analysis of Current Population Survey, March 2007.
The model for healthcare reform was selected from that enacted in Massachusetts. Important statements from the Massachusetts Act are as follows:
to promote patient-centeredness by, including, but not limited to, establishing

  • 1137 mechanisms to conduct patient outreach and education on the necessity and benefits of care
  • 1138 coordination, including group visits and chronic disease self-management programs;
  • 1139 demonstrating an ability to effectively involve patients in care transitions to improve the
  • 1140 continuity and quality of care across settings,
  • 1146 establishing mechanisms to protect patient provider choice,

Individual Mandate

A provision called the individual mandate, requires all Americans to buy some form of health insurance. Whether it is constitutional was in question before the Supreme Court. While the mandate is separate from the provision allowing young adults up to the age of 26 to be covered under their parents’ policies, the court could have decided to scrap the entire law — instead of just the mandate — leaving millions of young adults in the lurch. The mandate was upheld.

For many young adults, affording health insurance on their own will be particularly difficult.  The unemployment rate for young adults age 16 to 24 was 16.4% in March, twice the national average for the population as a whole.  And many of those who do find jobs, often aren’t being offered health benefits.  Less than a quarter, or 24%, of workers between the ages of 19 and 25 were offered health insurance by their employers in 2010, down from 34% in 2000, according to the Employee Benefit Research Institute, an independent public policy organization. Meanwhile, nearly 57% of the rest of the working population between the ages of 26 and 64 were covered.

B. Economics of Universal Delivery of Care – Stakeholders’ Trade offs

There is no question that repealing the Affordable Care Act would cause health costs to skyrocket, particularly for seniors who rely on Medicare to help pay for their healthcare.
According to a new report released by the Kaiser Family Foundation, a healthcare analysis non-profit, repealing the Affordable Care Act would be disastrous for seniors, who would be forced to pay higher premiums, prescription drug costs, and copayments.
According to the report, if health care reform is repealed:
  • Medicare Part A deductibles and copayments would increase.
  • Part B premiums would go up.
  • Savings from closing the Part D donut hole would be eliminated, and the gap in prescription drug coverage would be reopened; under the Affordable Care Act, an estimated 3.6 million Medicare Part D beneficiaries saved an average of $600 each in 2011 once they hit the donut hole, and the donut hole will be closed by 2020.
  • Free preventive services would be eliminated; under the Affordable Care Act, seniors can now get many preventive services for free, including an annual wellness visit, mammograms and other cancer screenings, and other important health services.

U.S. Faces Crisis in Cancer Care

http://www.biosciencetechnology.com/videos/2013/09/us-faces-crisis-cancer-care?et_cid=3474892&et_rid=442219320

Wed, 09/11/2013

Delivery of cancer care in the U.S. is facing a crisis stemming from a combination of factors—a growing demand for such care, a shrinking oncology work force, rising costs of cancer care, and the complexity of the disease and its treatment, says a new report from the Institute of Medicine. The report recommends ways to respond to these challenges and improve cancer care delivery, including by strengthening clinicians’ core competencies in caring for patients with cancer, shifting to team-based models of care, and communicating more effectively with patients.

Adding to stresses on the system is the complexity of cancer and its treatment, which has grown in recent years with the development of new therapies targeting specific abnormalities often present only in subsets of patients. Incorporating this new information into clinical care is challenging, the report says. Given the disease’s complexity, clinicians, patients, and patients’ families can find it difficult to formulate care plans with the necessary speed, precision, and quality; as a result, decisions about cancer care are often not sufficiently evidence-based.

Another challenge is the cost of cancer care, which is rising faster than other sectors of medicine, having increased from $72 billion in 2004 to $125 billion in 2010, says the report.  The single largest insurer for those over 65, the Centers for Medicare and Medicaid Services (CMS), is struggling financially.

The report recommends strategies for improving the care of cancer patients, grounded in six components of high-quality cancer care. The components are ordered based on the priority level with which they should be addressed.

  1. Engaged patients. The cancer care system should support patients in making informed medical decisions that are consistent with their needs, values, and preferences. Cancer care teams should provide patients and their families with understandable information about the cancer prognosis and the benefits, harms, and costs of treatments. The National Cancer Institute, the Centers for Medicare and Medicaid Services, and other stakeholders should improve the develop­ment and dissemination of this critical informa­tion, using decision aids when possible.  Patients with advanced cancer face specific communication and decision-making needs, and cancer care teams need to discuss their options, such as revisiting and implementing advance care plans. However, these difficult conversations do not occur as often as they should; recent studies found that 65 percent to 80 percent of cancer patients with poor prognoses incorrectly believed their treatment could result in a cure.
  2. An adequately staffed, trained, and coordinated work force. New models of team-based care are an effective way to promote coordinated cancer care and to respond to existing work-force shortages and demographic changes. And to achieve high-quality cancer care, the work force must include enough clinicians with essential core competencies for treating patients with cancer. Professional organizations that represent those who care for patients with cancer should define these core competencies, and organizations that deliver cancer care should ensure their clinicians have those skills.
  3. Evidence-based cancer care. A high-quality cancer care delivery system uses results from scientific research to inform medical decisions, but currently many medical decisions are not supported by sufficient evidence, the report says. Clinical research should gather evidence of the benefits and harms of various treatment options so that patients and their cancer care teams can make more informed treatment decisions. Research should also capture the impacts of treatment regimens on quality of life, symptoms, and patients’ overall experience with the disease. Additional research is needed on cancer interventions for older adults and those with multiple chronic diseases. The current system is poorly prepared to address the complex care needs of these patients.
  4. A learning health care information technology system for cancer care. A system is needed that can “learn” by enabling real-time analysis of data from cancer patients in a variety of care settings to improve knowledge and inform medical decisions. Professional organizations and the U.S. Department of Health and Human Services should develop and implement the learning health care system, and payers should create incentives for clinicians to participate as it develops.
  5. Translation of evidence into practice, quality measurement, and performance improvement. Tools and initiatives should be delivered to help clinicians quickly incorporate new medical knowledge into routine care. And quality measures are needed to provide a standardized way to assess the quality of cancer care delivered. These measures have the potential to drive improvements in care, inform patients, and influence clinician behavior and reimbursement.
  6. Accessible and affordable cancer care. Currently there are major disparities in access to cancer care among individuals who are of lower socio-economic status, are racial or ethnic minorities, lack health insurance coverage, and are older. HHS should develop a national strategy that leverages existing commu­nity interventions to provide accessible and afford­able cancer care, the report says. To improve the affordability of care, professional societies should publicly disseminate evidence-based information about cancer care practices that are unnecessary or where the harm may outweigh the benefits. CMS and other payers should design and evaluate new payment models that incentivize cancer care teams to provide care based on the best available evidence and that aligns with their patients’ needs. The current fee-for-service reimbursement system encourages a high volume of care, but fails to reward the provision of high-quality care.

Institute of Medicine Calls for Immediate Reforms in Health Care (2012)

By Kimberly Scott, Managing Editor, G2 Intelligence
A new report from the Institute of Medicine released Sept. 6 calls for a broad range of reforms to make timely changes to the U.S. health care system that would provide high-quality care at lower cost. “Unmanageable” complexity in the science and administration of health care, coupled with costs that have increased at a greater rate than the economy as a whole for 31 of the past 40 years, make the status quo “untenable,” said Best Care at Lower Cost: The Path to Continuously Learning Health Care in America.
“If unaddressed, the current shortfalls in the performance of the nation’s health care system will deepen on both quality and cost dimensions, challenging the well-being of Americans now and potentially far into the future,” the report said.
The report, which follows a series of IOM studies on various aspects of the U.S. health care system, was written by the IOM’s 18-member Committee on the Learning Healthcare System in America. It was sponsored by the Blue Shield of California Foundation, the Charina Endowment Fund, and the Robert Wood Johnson Foundation.
A theme of the report is that “health care now must be a team sport,” Smith said. Physicians in private practice interact with as many as 229 other physicians in 117 practices for their Medicare patients, he said. An elderly patient with multiple chronic diseases can be on up to 19 medications a day, he said. About 30 percent of health care spending in 2009, an estimated $750 billion, was wasted on
  • unnecessary services,
  • excessive administrative costs,
  • fraud, and other problems, the report said.
An estimated 75,000 deaths might have been avoided in 2005 if every state had delivered care at the quality of the best-performing state, it said.
The report is available at http://www.iom.edu

Graphical Excursion into National Healthcare Expenditures

Dan Munro, Forbes
According to the Deloitte Center for Health Solutions, this number has been historically underreported – by a significant amount. In their report (The Hidden Costs of U.S. Health Care), they cite two important components that have not been included in tradtional calculations. The first is out-of-pocket spending by consumers on professional services and the second is the “imputed value of supervisory care provided to a friend or family member.” Using a conservative annual growth rate of 4% (from Deloitte’s baseline year of 2010), here’s what Deloitte suggests is our real NHE.

 NHEbyDCforHS1  NHE annual growth rate of 4%

http://blogs-images.forbes.com/danmunro/files/2012/12/NHEbyDCforHS1.png

The Kaiser Family Foundation also provided a comparison of cumulative increases in health insurance premiums – relative to Workers’ Contributions, Inflation and Workers’ Earnings (from 2000 to 2012).

percentageincreasekff  % increase in HI premiums

http://blogs-images.forbes.com/danmunro/files/2012/12/percentageincreasekff.png

Another annual chart is Medscape’s Physician Compensation Report: 2012 Results (slide #2 – 2011 data).

salaries1  physician compensation  (Medscape)

For those that may be relying exclusively on the transformative effects of PPACA (Obamacare) – this chart highlights the nominal impact of PPACA reform on our National Healthcare Expenditure. It’s from a Commonwealth Fund Issue Brief (May, 2010) – The Impact of Health Reform on Health System Spending (Exhibit #3 – page 5).
NHE-BeforeAfter   nominal impact of PPACA reform on our National Healthcare Expenditure  (Commonwealth Fund)
This last one from Mary Meeker’s landmark report – USA, Inc. (slide #111) – is definitely not new but it is foundational. It compares per capita costs and life expectancy across all 34 OECD member countries using OECD data from 2009.
cost1  per capita costs and life expectancy across all 34 OECD member countries using OECD data from 2009.

C. Political Divisions – Destiny of Healthcare Reform

An Oncology Perspective on the Supreme Courts Pending Decision Regarding the Affordable Care Act

By SK Stranne, MG Halgren, P Shughart. Washington, DC.
Beginning on March 26, 2012, the Supreme Court of the United States heard oral arguments regarding challenges to the recent federal health care reform legislation. The Court scheduled this unusually lengthy series of arguments to last for three days—a reflection of both the high stakes and the complexity of the legal issues involved.  We provide a summary of the questions under consideration by the Supreme Court regarding the health care reform legislation, and we explore how the pending decision on this high-profile matter may impact the oncology community.
Congress enacted the reforms through two separate bills. The two laws, the Patient Protection and Affordable Care Act[1] and the Health Care and Education Reconciliation Act of 2010,[2] have become known collectively as the Affordable Care Act (ACA). The Court is not charged with deciding whether the ACA is good health care policy, only constitutionality.

Issues Before the Court

[1] whether Congress has exceeded its powers with respect to two specific provisions of the ACA
One of these provisions is the law’s requirement that individuals maintain a minimum level of health insurance, which is often referred to as the “minimum coverage requirement” or the “individual mandate.” The other contested provision is the law’s expansion of eligibility and financial support for the Medicaid program, through which the federal government provides grants to state governments to help fund health insurance for the poor.
[2] the Obama administration contended that two powers delegated to Congress each provide sufficient authority for the minimum coverage requirement
[a] Immediately preceding the minimum coverage requirement in the text of the ACA itself, Congress offered its own lengthy justification of why the Commerce Clause, which is a provision in the Constitution that delegates to Congress the power of regulating commerce among the states, authorizes this individual mandate.
[b] the problem is … as much as they say, ‘Well, we are not in the market,’ … [the uninsured] haven’t been able to meet the bill for cancer, and the rest of us end up paying because these people are getting cost-free health care.” Ruth Bader Ginsberg.
[c] the Constitution’s Taxing and Spending Clause also gives Congress authority to enact the minimum coverage requirement and collect a penalty for noncompliance via federal income tax returns.
The arguments in favor of the ACA’s Medicaid expansion relied on the Taxing and Spending Clause and also on the Appropriations Clause, both of which are generally regarded as giving Congress significant discretion in dictating how federal funds are spent. However, the Court has previously indicated that Congress may not use its spending power to unduly coerce the states. The ACA’s opponents argued that the Medicaid expansion is unconstitutionally coercive because it attaches new terms (ie, the requirement to cover more people) to substantial existing funds (ie, the grants the federal government already gives to the states for the original Medicaid program and its various pre-ACA expansions). Due to the size of the Medicaid program, the argument goes, the states have no real alternative but to continue participating in Medicaid under the ACA’s terms.
The severability discussion concerns whether the Court would strike only the provision in question, only the provision in question plus some closely related provisions, or the entire ACA. The arguments on this issue mainly addressed the minimum coverage requirement and focused on the degree to which certain provisions of the ACA are linked with that provision and what Congress would have intended to occur if the provision were found unconstitutional.

Convergence is Coming: A Brave New World

KPMG Report  by Liam Walsh
Healthcare payers, providers and life sciences companies should be thinking beyond transformation and focus more on convergence and the implications of operating in a collaborative and integrated healthcare delivery model.  This has come about because
  • the business of healthcare is changing to an ‘outcomes-based’ system
  • that compensates organizations based on the effectiveness of a product or service, not as a consumable.
The result is a driver of consolidation, and participants will fall substantially over the next decade. It is expected that the evolving system will bring about significant benefits with a more effective system when the dust settles.  However,patients will have less choice in the market, either due to services having been consolidated with one provider or because payer incentives drive patients to more cost-effective options. But the rapid development of a digitalized data handling with introduction of superior analytics, and moving more information onto ‘smart devices’ is already beginning to transform the way we source, deliver and pay for healthcare services.  The restructuring is transforming the healthcare business models.

Transforming Healthcare: From Volume to Value

KPMG Healthcare & Pharmaceuticals  Sept 2012
Over the next decade, all parts of the healthcare services and life sciences industry will need to change, from revenue based on volume to revenue based on value, to be sustainable and cost effective.  The emphasis on sustainability requires
  • contracting for healthcare value and
  • improving the productivity of the healthcare workforce.
Given the current high costs and variable outcomes, the U.S. healthcare system is undergoing an unprecedented transformation.

Bundle with Care — Rethinking Medicare Incentives for Post–Acute Care Services

Judith Feder, Ph.D.

n engl j med  2013; 369(5):400
Although health policy experts disagree on many issues, they largely agree on the shortcomings of fee-for-service payment. The inefficiency of a payment method that rewards increases in service volume, regardless
of health benefit, has become practically indefensible. But replacing discrete payments for each service with bundled payment for a set of services does not simply promote efficiency; it also potentially promotes
skimping on care or avoidance of costly patients.
The Medicare program already has considerable experience not only with capitation payments to health plans for the full range of Medicare services but also with bundled payments for sets of services: inpatient hospital services are bundled into “stays,” skilled-nursing-facility (SNF) services are bundled into “days,” and home-health-agency (HHA) services are bundled into “episodes.”
The tip-off to the risk involved in offering powerful incentives for these providers to keep costs low is the presence of extremely high and varied profits, in a service area devoid of standards for high-quality care. In 2010, SNFs and HHAs earned profits of 19%, on average, and the top quarter earned in excess of 27%.
In theory these high and widely varying profits might reflect variations in efficiency. But two factors other than relative efficiency probably explain these margins. First is that classification of patients into payment categories for rate-setting purposes
  • is not sufficiently precise to eliminate variation in expected costs among the patients within a category.
Second is the long history of patient selection in nursing homes and recent evidence that the HHAs with the highest profit margins
  • provide fewer visits, despite serving patients with greater measured care needs.
Given the weakness of patient classification and quality norms, policymakers would do well to heed previous advice that, in these circumstances, a hybrid approach better balances efficiency and appropriate care.
Rather than replace fee for service with a single-payment system, I believe we should rely ona hybrid approach in which both savings and risk are shared. Providers would receive a share, rather than the full amount, of any excess payments over the actual costs incurred. Similarly, Medicare would pay a share of any provider costs that exceeded the amount of prospective payments. To encourage efficiency, the system would ensure that providers could earn a sufficient share of profits but would also bear the larger share of losses.
Sharing savings and risk would essentially produce for Medicare, which sets payment rates administratively, profit levels similar to those a competitive market would provide. When some providers are earning  excessive profits in a market, others will offer services at lower prices (earning lower profits) to attract more business. Sharing savings and risk gives Medicare a means of keeping profits high enough to maintain access for beneficiaries, while narrowing the range of profit levels closer to those a competitive market would produce.

Study: Bigger hospitals drive cost increases

By MATT DOBIAS | 5/7/12
For everyone out there worried that President Barack Obama’s health reform law will spur monopolies and make it easier for hospitals to raise their prices, a new study says it’s already happening, and it’s not because of the health law.
A study in the May edition of Health Affairs finds that hospitals’ power to win steep payment increases — and insurers’ relative inability to resist — varies quite a bit from one market to another and from one kind of hospital or hospital network to another. Reputation, location and the type of medical services provided play a role.

State Laws Hinder Obamacare Effort To Enroll Uninsured

President Barack Obama has set aside $67 million to make it easier to enroll in his health-care overhaul. Laws pushed by Republicans in 12 states may keep that from happening. Under the Affordable Care Act, the U.S. government plans to pay a network of local groups known as navigators to explain the law’s new coverage options to the uninsured and guide them through its online insurance markets (Bloomberg News: Nussbaum and Wayne, 8/23/2013).

Modern Healthcare: Reform Update: Employers Take Closer Look At Private Insurance Exchanges

With public small-business insurance exchanges opening Oct. 1, two studies released this week show employer interest in private insurance exchanges is growing. …
  1. the Kaiser Family Foundation found that 29% of employers with 5,000 or more employees are considering private exchanges as an option for buying healthcare coverage for their employees.
  2. A day later, consulting firm Towers Watson released its Health Care Changes Ahead survey, which found that 37% of employers think private exchanges are a reasonable alternative to traditional employer coverage in 2014 (Block, 8/22).

D. Looking in on the ACOs

ObamaCare’s Health-Insurance Sticker Shock

By Merrill Matthews and Mark E Litow, Forbes
Thanks to mandates that take effect in 2014, premiums in individual markets will shoot up.
Central to ObamaCare are requirements that

  1. (1) health insurers accept everyone who applies (guaranteed issue),
  2. (2) cannot charge more based on serious medical conditions (modified community rating), and
  3. (3) include numerous coverage mandates that force insurance to pay for many often uncovered medical conditions.

Guaranteed issue incentivizes people to forgo buying a policy until they get sick and need coverage (and then drop the policy after they get well).  While ObamaCare imposes a financial penalty—

  • —to discourage people from gaming the system,
  • it is too low to be a real disincentive.

The result will be insurance pools that are smaller and sicker, and therefore more expensive.
How do we know these requirements will have such a negative impact on premiums? Eight states—New Jersey, New York, Maine, New Hampshire, Washington, Kentucky, Vermont and Massachusetts—enacted guaranteed issue and community rating in the mid-1990s and wrecked their individual (i.e., non-group) health-insurance markets.
States won’t experience equal increases in their premiums under ObamaCare.  Ironically, citizens in states that have acted responsibly over the years by adhering to standard actuarial principles and limiting the (often politically motivated) mandates will see the biggest increases, because their premiums have typically been the lowest.
While ObamaCare won’t take full effect until 2014, health-insurance premiums in the individual market are already rising, and not just because of routine increases in medical costs. Insurers are adjusting premiums now in anticipation of the guaranteed-issue and community-rating mandates starting next year. There are newly imposed mandates, such as the coverage for children up to age 26, and what qualifies as coverage is much more comprehensive and expensive. Consolidation in the hospital system has been accelerated by ObamaCare and its push for Accountable Care Organizations.
Unlike the federal government, health insurers can’t run perpetual deficits. Something will have to give, which will likely open the door to making health insurance a public utility completely regulated by the government.

Health Insurance Premiums Will Rise

Merrill Matthews, Resident Scholar at Institute for Policy Innovation, Forbes
Subsidies cover a portion of the cost of health insurance, up to a maximum out of pocket for the family. The amount of the subsidy is based both on the cost of coverage and income. There has been a lot of head scratching over how to deal with the fact

  • that a family’s income can vary significantly within a year, up or down, in ways no one predicted at the beginning of the year.

So how does the government determine the correct level of subsidy? The PPACA has so many unknowns in the mix that actuaries don’t know how much to charge. This is a problem for setting annual rates.

Traditionally in the individual market, where people buy their own (i.e., non-group) health coverage, applicants sign a contract and the insurance company guarantees that premium for a year. No more. Health insurers started sending out notices in January informing insurance brokers and agents that

  • the companies will no longer guarantee that premium rate.

After carefully evaluating its individual market and rates, Aetna decided to discontinue its offer of an initial 12-month rate guarantee. This change applies to policies with a January 15, 2013 or later effective date, in all states where plans are sold. Existing members who are currently in a rate guarantee period will not be affected. Aetna published a notice saying in part, “While the policies will not have a 12-month rate guarantee, we fully expect the rates to stay the same until December 31, 2013.” While that announcement may alleviate the concerns of some, Aetna is not the only company ending the rate guarantee.
While the individual market has been relatively small (about 19 million people, according to the Employee Benefit Research Institute) compared to those with employer-based coverage (about 156 million), most honest analysts expect millions of employers to drop coverage and dump their employees into the individual market.

ACOs Can Save Medicare $$$, Study Finds

By David Pittman, Washington Correspondent, MedPage Today. Aug 27, 2013
An accountable care organization (ACO) established by a private insurer reduced costs of care for Medicare enrollees, a study in Massachusetts found.  Providers participating in the Alternative Quality Contract (AQC) — an early commercial ACO backed by Blue Cross Blue Shield of Massachusetts — reduced spending on Medicare beneficiaries by 3.4% after 2 years compared with enrollee costs at nonparticipating providers, ( Journal of the American Medical Association).

Medicare enrollees served by 11 provider groups in the AQC from 2007-2010 were compared with Medicare patients served by non-AQC providers. The study looked at quarterly medical spending and five quality measures, such as avoidable hospitalizations and 30-day readmissions. The AQC started in 2009 with providers bearing a financial risk for spending in excess of a global budget, gaining from spending below the budget, and receiving rewards for meeting performance targets.
Per-enrollee spending was $150 higher for patients of AQC providers than for those of non-AQC providers before the ACO took effect in 2009. Year-1 savings weren’t significant (P=0.18), but

  • by year 2, the AQC lowered Medicare beneficiary spending by 3.4% and the difference in spending between the AQC and non-AQC providers had dropped to $51 (P=0.02)

Savings came from reductions in outpatient services, including

  • office visits,
  • emergency department visits,
  • minor procedures,
  • imaging, and lab tests.

Also, savings were greater in patients with five or more conditions (P=0.002). Previous research showed the AQC reduced quarterly spending on Blue Cross patients by $27 per enrollee in year two.
ACOs have received sour press of late as nine of 32 pioneer ACOs — Medicare’s first and most advanced ACO provider groups — told the agency last month they want to leave the program. Despite that outlook and ACOs’ struggles to achieve consistent cost savings, Medicare-led ACOs (253) now outnumber commercial ACOs (235), according to a recent report from the consulting group Leavitt Partners.

New Care Models Look at Social Factors in Health

By David Pittman, Washington Correspondent, MedPage Today. Aug 22, 2013
Models such as PCMHs, ambulatory intensive care units, and medical neighborhoods should thrive on connecting patients’ clinical care with broader social services that can help provide better housing and other benefits. (ReportingOnHealth.org)
“The medical neighborhood coordinates care for patients at a community level, working with organizations in the community that can help expand the impact of healthcare and, more specifically, focus on the social determinants,” Manchanda (founder and president of HealthBegins) said. “And this fits more into the model of community-centered health home.” (Medicaid Medical Home)

  • Lack of access to good housing, places to exercise, safe neighborhoods, and health food sources make people more vulnerable to heart disease, diabetes, obesity, and other diseases.

Evidence is growing linking people’s physical environments and social conditions to their health. Three in four doctors wished the healthcare system would pay for the cost associated with connecting patients with needed social services. That aspect of the situation is improving with advent of PCMHs and other delivery models which pay for the care coordination of the most at-risk patients. This will be addressed by electronic medical records (EMRs) will help collect social history if EMR vendors provide an avenue for it to be requested and stored. The facilitation of internet communications will allow clinicians to share data with social services about their patients, and connect with patients themselves.

What Do Employers Want From Hospitals? The Rules of the Road

Aegis Health Group. 2013; 5(7).
Corporate America has long viewed the healthcare system as one of the biggest drains on the economy—and on the profitability of businesses nationwide. With the advent of Accountable Care Organizations as the model of the future for managing overall population health, hospitals are ideally positioned to harness this opportunity

  • to build profitable partnerships with employers.

In this paper hospital executives will learn about new approaches to this challenge along with some simple, tried-and-true rules of the road for attaining mutually beneficial partnerships with employers.

Why does Corporate America think the current state of healthcare is a quagmire – and that they are in the middle of it?

COST OF POOR HEALTH IN BILLIONS

 Medical & Pharmaceutical     $227
Wage Replacement                  $117
Lost Productivity                        $232

They are ready to take control of the issues and turn them from business detractors to business advantages. Consider this:

  • »» According to the 17th annual Towers Watson Employer survey on “Purchasing Value in Healthcare,” employee healthcare costs have increased 42 percent since 2007.
  • »» Total costs average more than $11,600 per employee each year, with employers paying out 34 percent more compared to just five years ago.
  • »» Healthcare now costs employers $576 billion annually.
  • »» These dollars relate not only to insurance premiums and the actual cost of care provided, but absenteeism and lost productivity when workers either do not show up or perform marginally on the job due to illness.

On the flip side workers have felt the sting as well. With more employers scaling back benefits or selecting higher-deductible plans, employee out-of-pocket expenses and payroll deductions for premiums increased 82 percent, averaging $5,000 per year according to the same Towers Watson survey. The escalation of healthcare costs almost mirrors the increasingly poor health of U.S. adults. Only one in seven workers are of a normal weight and free from any chronic health conditions, such as diabetes, hypertension or heart disease.
A full 62 percent of employers want to increase employee wellness and preventive health programs. Hospitals are well positioned to provide

  • the medical talent, best practices and expertise required for a comprehensive workforce health initiative (WHI).

As the country moves toward an accountable care model of healthcare delivery, the timing has never been better for hospitals to take a leadership role in developing population health programs in the workplace and beyond.

Employee View: Who provides the greatest value in healthcare?

Primary Care                  60%
Prescription Drugs        50%
Hospitals                         47%
Specialty Care               46%
Wellness Programs      43%
Health Insurance
Plans                               39%
Retail Clinics                  31%
In a Deloitte Center for Health Solutions survey in 2012, employers ranked primary care and hospitals as providing the most value to the healthcare system. Yet it is not unusual for 30 percent of employees to report they have no primary care physician. These are consumers who may be at significant risk for hidden health problems that may become chronic conditions later on. Employers have a vested interest in linking these employees with a primary care doctor sooner rather than later.

What are the Six Sigma Elements of an Effective Workforce Health Initiative?

The most effective workforce health initiatives take a data-driven approach to enhancing the health of a defined population. The five key steps in the Six Sigma process actually reflect the major tactics of a WHI and population health strategy.

 48-Graph-4-30_2012  Age-Adjusted Prevalence of Cardiovascular Disease Risk Factors in Adults, U.S., 1961–2011

49-Graph-4-31_2012  hypertension, treated awareness

52-Graph-4-35_2012  Total Economic Costs of the Leading Diagnostic Groups, U.S., 2009

278px-Preventable_causes_of_death

8443-exhibit-2-7  nonelderly population uninsured

8443-exhibit-2-8  nonelderly uninsured under ACA with all states expanding Medicaid

8443-exhibit-2-3  increase in medicaid_CHIP all states expanding medicaid

Causes_of_death_by_age_group

correlates of in-hospital mortality

healthprices  time price of HC over 50 years

fs310_graph3  leading causes of death by income class worldwide

FUSA_INFOGRAPHIC_50-state-medicaid-expansion_rev_06-27-13_FACEBOOKCOVER

milliman1   2012 Milliman Medical Index

hhs_medicare_docs   participating in and billing Medicare

Read Full Post »

The Affordable Care Act: A Considered Evaluation. The Implementation of the ACA, Impact on Physicians and Patients, and the Dis-Ease of the Accountable Care Organizations.

The Affordable Care Act: A Considered Evaluation. Part II: The Implementation of the ACA, Impact on Physicians and Patients, and the Dis-Ease of the Accountable Care Organizations.

Writer and Curator: Larry H. Bernstein, MD, FCAP

and

Curator and Editor: Aviva Lev-Ari, PhD, RN 

Article ID #78: The Affordable Care Act: A Considered Evaluation. The Implementation of the ACA, Impact on Physicians and Patients, and the Dis-Ease of the Accountable Care Organizations. Published on 9/13/2013

WordCloud Image Produced by Adam Tubman

INTRODUCTION

This discussion is the second of two distinct chapters. The first is a clarification of what is contained in the Accountable Care Act (ACA), the model of care it is crafted from, the insurance mandate, the inclusion of groups considered high risk and uninsured, the inclusion of groups low risk and uninsured, and the economics involved in going from a fractured for profit health care industry to a more stable coverage for patients with problems in creating a new workable model from an actuarial standpoint, with the built in complexity of not just age, but education, achievement in the workforce, and a consolidating hospital and eldercare industry, the unpredictability of disease evolution, and add on the multicultural and social structures, as well as rapidly evolving communications and computational platforms needed to transform the U.S. Healthcare system.. The second is taken from selected articles on the care process in the New England Journal of Medicine about the cost and consequences for improving quality at lower cost. Dr. Justin Pearlman has chosen this topic to become as the Second Chapter in the Cardiovascular Disease Volume and Dr. Aviva Lev Ari has selected the sub-universe of sources been elaborated on in this Chapter

There are inherent problems at looking at this from a systems point of view, mainly impacted by the relationship of providers to hospitals and clinics, and by the relationships of insurers to the patients and providers in an Accountable Care Organization (ACO) model. These relationships have been evolving for many decades, first with the increased availability of highly skilled medical specialists trained in numerous university-based programs funded by Training Grants from the National Institutes of Health, then a high concentration of these skilled physicians in metropolitan locations, where there was an adequate patient-base for developing groups of refering physicians. Prior to WWII, there were many Asian physicians receiving their postgraduate training in the U.K. The number of foreign graduates coming to the U.S. Increased enormously with the opportunities that opened up in U.S. The first change in medical education that created a science-based professional came after the Flexner Report in 1910, sponsored by the Carnegie Endowment. Many aspects of the present-day American medical profession stem from the Flexner Report and its aftermath.The Report (also called Carnegie Foundation Bulletin Number Four) called on American medical schools to enact higher admission and graduation standards, and to adhere strictly to the protocols of mainstream science in their teaching and research. Joseph Goldberger discovered the cause of pellagra in 1916.  When the 1918 influenza pandemic struck Washington, physicians from the then PHS laboratory were pressed into service treating patients in the District of Columbia because so many local doctors fell ill.

goldberger 1916 Pellagra

http://www.nih.gov/about/lmedia/goldberger.jpg

In 1930, the Ransdell Act changed the name of the Hygienic Laboratory to National Institute (singular) of Health (NIH) and authorized the establishment of fellowships for research into basic biological and medical problems. The roots of this act extended to 1918, when chemists who had worked with the Chemical Warfare Service in World War I sought to establish an institute in the private sector to apply fundamental knowledge in chemistry to problems of medicine. In 1926, after no philanthropic patron could be found to endow such an institute, the proponents joined with Louisiana Senator Joseph E. Ransdell to seek federal sponsorship. The truncated form in which the bill was finally enacted in 1930 reflected the harsh economic realities imposed by the Great Depression. Nonetheless, this legislation marked a change in the attitude of the U.S. scientific community toward public funding of medical research.

bengston_lg nurse in bacteriology lab of NIH

http://history.nih.gov/exhibits/history/assets/images/bengston_lg.jpg

cholera_sm cholera epidemic of 19th century (Koch bacillus)

http://history.nih.gov/exhibits/history/assets/images/cholera_sm.jpg

Vaccines and therapies to deal with tropical diseases were also critically important to the WWII war effort by the PHS. At the NIH’s Rocky Mountain Laboratory in Hamilton, Montana, yellow fever and typhus vaccines were prepared for military forces. In Bethesda as well as through grants to investigators at universities a synthetic substitute for quinine was sought to treat malaria.  Research in the Division of Chemotherapy revealed that sodium deficiency was the critical element leading to death after burns or traumatic shock. This led to the widespread use of oral saline therapy as a first-aid measure on the battlefield. NIH and military physiologists collaborated on research into problems related to high altitude flying. As the war drew to a close, PHS officials guided through Congress the 1944 Public Health Service Act, which defined the shape of medical research in the post-war world. Two provisions in particular had an impact on the NIH. First, in 1946 the successful grants program of the NCI was expanded to the entire NIH. From just over $4 million in 1947, the program grew to more than $100 million in 1957 and to $1 billion in 1974. The entire NIH budget expanded from $8 million in 1947 to more than $1 billion in 1966. Between 1955 and 1968. In this period, there was expansion of the NIH extramural budget, as well, and the grants dispursed were in support of developing the medical faculty of the future. It has nothing to do with then organization of the practice of medicine, but it has contributed much to the widespread quality of american medical education.

flowchart_sm NIH 1949

http://history.nih.gov/exhibits/history/assets/images/flowchart_sm.jpg

 As the cost of healthcare was increasing, mainly after the Korean and Vietnam War periods, there was a medically initiated concept of a National not-for-profit health maintenance organization (HMO), which would be modeled after the likes of Mayo Clinic, Cleveland Clinic, the Kaiser Permanente Plan, and Geisinger. But the insurance industry was already mature, and the hospitals were closely tied to Aetna, CIGNA, and Blue Cross Blue Shields, which had the actuarial pieces needed. Then an HMO industry emerged with a for-profit motive. As the U.S. Became enmesshed in two military engagements in Iraq and Afganistan for a full decade, there was a fierce competition between the need to support military requirements and the need to support the welfare of the community, with brilliant accelerated achievements that brought the Human Genome Project to a successful conclusion in 2003, and from that emerged advances in both clinical laboratory diagnostics and imaging, and which portends to continuing significant advances in treatments in cardiology, surgery, endocrinology, and cancer. In order to succeed, there has been a redesign or rearrangement of how these services are delivered, with a business model intended to – in time – bring down costs, and to also improve quality. Ironically, there is an insufficiency of primary care physicians, even considering internal medicine, pediatrics, obstetrics, and general surgery, as well as osteopathic physicians.

Part I. The Establishment, Structure, and Nature of the Accountable Care Act (ACA)

Part II. The Implementation of the ACA, Impact on Physicians and Patients, and the Dis-Ease of the Accountable Care
Organizations.

Failure to Launch? The Independent Payment Advisory Board’s Uncertain Prospects

Jonathan Oberlander, Ph.D., and Marisa Morrison, B.A.
N Engl J Med 2013; 369:105-107July 11, 2013 http://dx.doi.org/10.1056/NEJMp1306051

The Affordable Care Act (ACA) established the IPAB as a 15-member, nonelected board. Among other duties, the IPAB is empowered to recommend changes to Medicare if projected per-beneficiary spending growth exceeds specified targets. If Congress does not enact legislation containing those proposals or alternative policies that achieve the same savings, the IPAB’s recommendations are to be implemented by the secretary of health and human services. President Obama has proposed strengthening the board’s role by lowering the Medicare spending targets that would trigger IPAB action.

Because the board is prohibited by law from making recommendations that raise revenues, increase cost sharing of Medicare beneficiaries, or restrict benefits and eligibility, it is expected to focus on savings from medical providers. In January 2013, the GOP adopted a House rule declaring that the IPAB “shall not apply” in the current Congress, thereby rejecting the special procedures that the ACA had established for congressional consideration of IPAB recommendations.

On April 30, the chief actuary of the Centers for Medicare and Medicaid Services released a report projecting Medicare spending growth during 2011–2015. According to the report, per-person Medicare spending will grow at an average rate of 1.15% during that period, far below the target growth rate set by the ACA — the average of the Consumer Price Index (CPI) and the Medical CPI (see graph).

8443-exhibit-2-3 increase in medicaid_CHIP all states expanding medicaid50-Graph-4-33_2012 Hospitalization Rates for Heart Failure, Ages 45–64 and 65 and Older, U.S., 1971–2010

8443-exhibit-2-7 nonelderly population uninsured52-Graph-4-35_2012 Total Economic Costs of the Leading Diagnostic Groups, U.S., 2009

http://www.nejm.org/na101/home/literatum/publisher/mms/journals/content/nejm/2013/nejm_2013.369.issue-2/nejmp1306051/20130708/images/small/nejmp1306051_f1.gif

Projected Growth in Medicare Per Capita Spending, the Consumer Price Index (CPI), and the Medical CPI, 2011–2015.

       healthprices time price of HC over 50 yearsjournal.pmed.0020133.g001 Global Mortality and Burden of Disease Attributable to Cardiovascular Diseases and Their Major Risk Factors for People 30 y of Age and Older

NHEbyDCforHS1 NHE annual growth rate of 4%      percentageincreasekff % increase in HI premiums

journal.pmed.0020133.t001 Risk and Socioeconomic Variables Used in the Analysis     T1.large uninsured by health and disability by region 2000-2005

T3.large uninsured by medicaid eligibility        T5 Characteristics Of Insurance, By Insurance Adequacy, Among Insured Adults Ages 19–64, 2007

The rate of increase in Medicare expenditures per enrollee has slowed since 2006, and because Medicare spending growth has moderated, the IPAB will be irrelevant to cost containment. 3 years after the ACA’s enactment, the IPAB still has no members. If no members are appointed, the power to recommend changes to Medicare when spending targets are exceeded does not disappear: it reverts to the secretary of health and human services.

The board’s appeal lies largely in its aspiration to remove politics from Medicare — to create a policymaking process that is informed by experts and insulated from pressures outside their professional overview. If Medicare spending growth accelerates, the IPAB’s role could expand. But that future is uncertain.

Causes_of_death_by_age_group

The Road Ahead for the Affordable Care Act

John E. McDonough, Dr.P.H.
N Engl J Med 2012; 367:199-201 http://dx.doi.org/10.1056/NEJMp1206845
http://www.nejm.org/doi/full/10.1056/NEJMp1206845

The Affordable Care Act (ACA), the U.S. health care reform law enacted in 2010, was upheld as constitutional by the U.S. Supreme Court on June 28, 2012. As a result of the Court’s ruling –

  • the individual responsibility requirement (the individual mandate to obtain insurance coverage),
  • insurance reforms such as the elimination of coverage exclusions for preexisting conditions,
  • the establishment of state health insurance exchanges, and
  • the provision of private health insurance subsidies

stand unaltered despite the Court-ordered switch in the basis for constitutional legitimacy from the Commerce Clause to Congress’s taxing authority.

One consequential outcome of the ruling is the continuing benefit, and harm averted, for millions of Americans from ACA provisions that have already been implemented. Those benefiting include more than 6 million young adults enrolled in their parents’ insurance plans, 5.2 million Medicare enrollees who have saved on prescription-drug costs because of the shrinking Part D “doughnut hole,” 600,000 new adult Medicaid enrollees in seven states that have already expanded Medicaid eligibility, 12.8 million consumers who will receive more than $1 billion in insurance-premium rebates, and many others.

Also undisturbed are the ACA’s numerous system reforms, such as accountable care organizations, patient-centered medical homes, the Prevention and Public Health Fund, and the Patient-Centered Outcomes Research Institute. Since the ACA’s passage, health system innovation has surged — a dynamic that would have been undermined by a negative Court ruling.

The biggest change involves Medicaid. The ACA required that Medicaid serve nearly all legal residents with incomes below 138% of the federal poverty level. As a result, there is a new inequity in the health system: by 2014, all Americans will have guaranteed access to affordable health insurance except adults with incomes below the poverty level who were previously ineligible for Medicaid (those with incomes between 100 and 138% of the poverty level will be allowed to obtain coverage through insurance exchanges). States have strong economic incentives to expand Medicaid, since the federal government will pay 100% of expansion costs between 2014 and 2016. By 2020, the federal share will drop to no less than 90% — much more generous than the 50 to 83% that the federal government contributes for traditional Medicaid and the Children’s Health Insurance Plan.

The current implementation queue includes writing definitions and rules for private health insurance markets, clarifying rules for determining required “essential health benefits,” explaining how employer-responsibility provisions will be devised, and much more. The ACA is the first U.S. law to attempt comprehensive reform touching nearly every aspect of our health system. The law addresses far more than coverage, including health system quality and efficiency, prevention and wellness, the health care workforce, fraud and abuse, long-term care, biopharmaceuticals, elder abuse and neglect, the Indian Health Service, and other matters.

Encouraging competition among health plans, even if one of them is “public,” will also fail to solve the cost problem. With the exception of highly integrated organizations, such as Kaiser Permanente, health plans have only two tools to control costs: financial disincentives for patients and fee reductions for providers. Acceptable out-of-pocket maximums, however, vitiate economic incentives to restrain use, particularly for expensive care such as inpatient care. Unable to alter provider behavior, health plans primarily try to avoid enrolling people who are likely to need costly care.

Budget Sequestration and the U.S. Health Sector

McDonough J.E.N Engl J Med 2013; 368:1269-1271 http://dx.doi.org/10.1056/NEJMp1303266

In August 2011, in an agreement to raise the nation’s debt ceiling, bipartisan majorities in the House and Senate approved the Budget Control Act of 2011 (BCA) to reduce the deficit by $1.2 trillion between 2013 and 2021. The BCA established a threat of across-the-board cuts, or “sequestration,” if the Joint Select Committee on Deficit Reduction failed to approve, and Congress to enact, alternative reductions. Sequestration became operational on March 1. Of the $1.2 trillion in cuts, $216 billion will be reductions in debt-service payments, and the remaining $984 billion will be split evenly over 9 years at $109 billion per year, and further adjusted and split evenly between cuts to national defense and nondefense functions at $42.667 billion each.

T2.large Adults Ages 19–64 Who Were Uninsured And Underinsured, By Various Characteristics, 2003 And 2007   T3.large uninsured by medicaid eligibility

The $42.667 billion per year in nondefense cuts will not fall equally on all health-related government programs. Nonexempt and nondefense discretionary funding faces reductions of 7.6 to 8.2% in this fiscal year; certain programs such as Medicare and community health centers will have 2% reductions; and certain programs such as Medicaid and the Veterans Health Administration are exempt.
nejmp1303266_t1 Impact of Budget Sequestration on Key Federal Health and Safety Programs,

Impact of Budget Sequestration on Key Federal Health and Safety Programs, Fiscal Year 2013.

http://www.nejm.org/na101/home/literatum/publisher/mms/journals/content/nejm/2013/nejm_2013.368.issue-14/nejmp1303266/20130618/images/small/nejmp1303266_t1.gif

Medicare funding will be cut by 2% ($11.08 billion) through reductions in payments to hospitals, physicians, and other health care providers, as well as insurers participating in Medicare Advantage (Part C). The BCA prohibits cuts affecting premiums for Medicare Parts B and D, cost sharing, Part D subsidies, and Part A trust-fund revenues. The sequestration cuts arrive just as Medicare is beginning to fully implement the savings and cuts required by the Affordable Care Act (ACA), which the Congressional Budget Office estimates will slow Medicare’s rate of growth by $716 billion between 2013 and 2022. The National Institutes of Health (NIH) faces an 8.2% across-the-board reduction for the 7 months remaining in fiscal 2013, equaling cuts of $1.55 billion.

The Centers for Disease Control and Prevention (CDC), which is still recovering from major budget reductions in 2011, anticipates effective reductions of 8 to 10% for the remainder of the year. The American Public Health Association has projected that the reductions could result in 424,000 fewer HIV tests (the CDC funded 3.26 million in 2010) and 50,000 fewer immunizations for adults and children (from a baseline of about 300 million), elimination of tuberculosis programs in 11 states, and shutting down of the National Healthcare Safety Network.

Unaffected for all 9 years of the sequester are most expenses associated with the ACA. Medicaid is exempt, as is funding for its expansion, beginning next January, to all lower-income Americans in states that choose to participate. Also exempt are private insurance subsidies that will be available next January through new health insurance exchanges, because they were designed as refundable tax credits, another BCA-exempt category. Finally, the Children’s Health Insurance Plan, the Supplemental Nutrition Assistance Program, Temporary Assistance to Needy Families, and Supplemental Security Income are all exempt.

Threading the Needle ‹ Medicaid and the 113th Congress

fs310_graph3 leading causes of death by income class worldwideFUSA_INFOGRAPHIC_50-state-medicaid-expansion_rev_06-27-13_FACEBOOKCOVER

Rosenbaum S.N Engl J Med 2012; 367:2368-2369 http://dx.doi.org/10.1056/NEJMp1213901

Medicaid is a veteran of decades of warfare over its size and cost. Nevertheless, the program now plays a vital role in the U.S. health care system and a foundational role in health care reform. The central question, as we approach a major debate over U.S. spending and federal deficits, is how to preserve this role and shield Medicaid from crippling spending reductions. The Budget Control Act, which provides the initial framework for this debate, insulates Medicaid from sequestration. Budgetary protections for Medicaid date to the 1980s, but today’s politics are less tolerant of programs for poor and vulnerable populations. Medicaid is also at a deep political disadvantage. Medicaid is unequaled among federal grant programs: more than 60 million children and adults rely on the program, and it’s projected to grow to 80 million beneficiaries by 2020 if all states adopt the eligibility expansion in the Affordable Care Act (ACA). Medicaid’s cost is driven by high enrollment, not excessive per capita spending.2 As a result, there’s very little money to wring out of Medicaid without shaking its structure in ways that reduce basic coverage. Medicaid is part of the base on which health care reform rests; if it is not expanded per the ACA, the nation will lose its chance at near-universal health insurance coverage, which is essential to achieving systemwide savings and halting a $50 billion annual cost shift to insurers and patients. Deep federal spending reductions could lead states to abandon Medicaid expansion as a result of a confluence of factors —

  • the still-fragile nature of many state economies,
  • the continuing ideological opposition to Medicaid expansion, and
  • the Supreme Court decision to permit states to opt out of such expansion altogether.

Considerable evidence shows its effectiveness: most recently, a study by Sommers et al. documented its positive effects on health and health care. Experts in Medicaid spending also acknowledge the program’s operational efficiencies, achieved by states through the aggressive use of managed care and strict controls on spending for long-term care. Much of the health care that Medicaid beneficiaries receive is furnished through safety-net providers such as community health centers, which are highly efficient and accustomed to operating on tight budgets with only limited access to costly specialty care. Furthermore, Medicaid’s physician payments are substantially lower than those from commercial insurers and Medicare — a disparity that unfortunately limits provider participation even as it helps to keep per capita spending low. Indeed, the CBO has found that insuring the poor through Medicaid will cost 50% less per capita than doing so through tax-subsidized private insurance plans offered through state health insurance exchanges.

nejmp1306051_f1 Projected Growth in Medicare Per Capita Spending, the Consumer Price Index (CPI), and the Medical CPI, 2011–2015

The essential task is to thread the needle by accelerating efficiency reforms in health care payment and organization that, in turn, can generate savings over time while not damaging Medicaid’s role as a pillar of health care reform. Of particular importance is a heightened focus, begun under the ACA, on reforms that emphasize community care for millions of severely disabled children and adults, including patients who are dually enrolled in Medicare and Medicaid and who rely heavily on long-term institutional care.

The Shortfalls of ‘Obamacare’

Wilensky G.R. N Engl J Med 2012; 367:1479-1481 http://dx.doi.org/10.1056/NEJMp1210763

U.S. health care suffers from three major problems: millions of people go without insurance, health care costs are rising at unaffordable rates, and the quality of care is not what it should be. The Affordable Care Act (ACA) primarily addresses the first — and easiest — of these problems by expanding coverage to a substantial number of the uninsured. Solutions to the other two remain aspirations. The ACA’s primary accomplishment is that approximately 30 million previously uninsured people may end up with coverage — about half with subsidized private coverage purchased in the mostly yet-to-be-formed state insurance exchanges and the other half through Medicaid expansions. The law’s most controversial provision remains the individual mandate, which requires people either to have insurance coverage or to pay a penalty. The penalty for not having insurance is very small, particularly for younger people with modest incomes. It would have been smarter to mimic Medicare’s policies: seniors who don’t purchase the voluntary parts of Medicare covering physician services and outpatient prescription drugs during the first year in which they lack comparable coverage must pay a penalty for every month they have gone without coverage whenever they finally do purchase it.

Despite widespread recognition that fee-for-service reimbursement rewards providers for the quantity and complexity of services and encourages fragmentation in care delivery, the ACA retains all the predominantly fee-for-service reimbursement strategies currently used in Medicare. Much of the coverage expansion is financed through Medicare budget savings, which are produced by reducing the fees paid by Medicare to institutional providers such as hospitals, home care agencies, and nursing homes — but using the same perverse reimbursement system currently in place. Reducing payments to institutional providers should not be confused with lowering the cost of providing care.

The ACA also provides Medicare “productivity adjustments,” which assume that inflation adjustments can be reduced over time because institutions will become more productive, whether or not hospitals and other providers actually find ways to increase their productivity. Unless these institutions find ways to reduce costs, lower Medicare reimbursements will force providers to bargain for higher payments from private insurers. And eventually, seniors’ access to services will be threatened. The Medicare actuary expects that 15% of institutional providers will lose money on their Medicare business by 2019, and the proportion will increase to 25% by 2030 — a situation that he calls unsustainable

Most troubling, the ACA contains no reform of the way physicians are paid, which is the most dysfunctional part of the Medicare program. Through the Resource-Based Relative Value Scale, physicians are reimbursed on the basis of service codes, and payment for each physician service is reduced whenever aggregate spending on physician services exceeds a prespecified limit. This system disregards whether clinicians are providing low-cost, high-value care for patients. Given physicians’ key role in providing patient care, it’s impossible to imagine a reformed delivery system without one that rewards them for providing clinically appropriate care efficiently.

What is needed are reforms that create clear financial incentives that promote value over volume, with active engagement by both consumers and the health care sector. Market-friendly reforms require empowering individuals, armed with good information and nondistorting subsidies, to choose the type of Medicare delivery system they want. Being market-friendly means allowing seniors to buy more expensive plans if they wish, by paying the extra cost out of pocket, or to buy coverage in health plans with more tightly structured delivery systems at lower prices if that’s what suits them. 

Financing Graduate Medical Education — Mounting Pressure for Reform

John K. Iglehart N Engl J Med 2012; 366:1562-1563 http:dx.doi.org/10.1056/NEJMp1114236
http://www.nejm.org/doi/full/10.1056/NEJMp1114236

Disparate voices from the White House, a national fiscal commission, Congress, a Medicare advisory body, private foundations, and academic medical leaders are advocating changes to Medicare’s investment in graduate medical education (GME), which currently totals $9.5 billion annually. They offer various prescriptions, including reducing federal support, developing new achievement measures for which GME programs should be held accountable, and seeking independent assessment of the governance and financing of training programs.

The influential GME community has withstood most past efforts to change Medicare’s GME policies. But recognizing today’s more challenging political environment, the Association of American Medical Colleges (AAMC) has begun discussing alternative methods of financing GME that could better align training with the future health care delivery system and address U.S. workforce needs. The association is also examining the influence of student debt on the enrollment of a diverse student body.

When Congress enacted Medicare in 1965, it assigned to the program functions that reached well beyond its mission of financing health care for the elderly. One function was supporting GME, at least until the society at large undertook “to bear such education costs in some other way.” Almost 50 years later, Medicare remains the largest supporter of GME, providing both direct payments to hospitals that cover medical education expenses related to the care of Medicare patients (about $3 billion per year) and an indirect medical education (IME) adjustment to teaching hospitals for the added patient-care costs associated with training (about $6.5 billion).

In its 2013 budget, unveiled on February 13, 2012, the Obama administration proposed reducing Medicare’s IME adjustment by $9.7 billion over 10 years, beginning in 2014, citing a report from the Medicare Payment Advisory Commission (MedPAC) indicating that Medicare’s IME adjustments “significantly exceed the actual added patient care costs these hospitals incur.” The administration also proposed that the secretary of health and human services be granted the authority to assess GME programs’ performance in instilling in residents the necessary skills to promote high-quality health care. Similarly, MedPAC had recommended redirecting about half the IME adjustments ($3.5 billion) into “incentive payments” that GME programs could earn by meeting performance standards. The Obama budget would also eliminate coverage of the IME expenses of free-standing children’s hospitals with pediatric residency programs — which do not treat Medicare patients — reducing their federal support by 66% (to $88 million). Moreover, Congress has revealed its uncertainty over how to change federal workforce policy. In the Affordable Care Act (ACA), Congress emphasized the importance of expanding the primary care workforce. But legislators rejected the AAMC’s call to expand the number of Medicare-funded GME positions by 15% in response to reported physician shortages in some specialties.

On December 21, seven senators — Democrats Michael Bennet (CO), Jeff Bingaman (NM), Mark Udall (CO), and Tom Udall (NM) and Republicans Mike Crapo (ID), Chuck Grassley (IA), and Jon Kyl (AZ) — sent a letter to the Institute of Medicine (IOM) encouraging it to “conduct an independent review of the governance and financing of our system of [GME].” They urged the IOM to explore subjects including accreditation; reimbursement policy; the use of GME to better predict and ensure adequate workforce supply in terms of type of provider, specialty, and demographic mix; GME’s role in care of the underserved; and use of GME to ensure the creation of a workforce with the skills necessary for addressing future health care needs. The senators emphasized their interest “in IOM’s observations about the uneven distribution of GME funding across states based on need and capacity, and how to address this inequity.” In an interview, Bingaman said he initiated the letter for the same reasons he had championed creation of a National Health Care Workforce Commission as part of the ACA: to strengthen the government’s resolve to do “a more credible job of assessing workforce shortages” and because he believes Medicare’s GME policies are “outmoded.”

The priorities cited in the IOM letter parallel some of the recommendations of a group of academic medical leaders who gathered at two conferences underwritten by the Josiah Macy Jr. Foundation. At the first conference, in October 2010, the top recommendation was that “an independent external review of the goals, governance, and financing of the GME system should be undertaken by the Institute of Medicine, or a similar body.”3 George Thibault, president of the Macy Foundation, says the group concluded that “because GME is a public good and is significantly financed with public dollars, the GME system must be accountable to the needs of the public.” Acknowledging that some people in academic medicine “favor a behind-the-scenes discussion of GME reform alternatives,” Thibault noted, “I believe we should be upfront, providing examples of change that could influence the thinking of policymakers.” The foundation awarded the IOM $750,000 — about half the support it needs for the GME study.

Among subjects under discussion are the collection of more data highlighting the importance of the safety-net functions and unique services of academic medical centers and the creation of a long-term vision for GME financing that is more closely aligned with emerging care delivery models, such as accountable care organizations. The association is also revisiting a potential financial model under which all health care payers would explicitly cover GME expenses. Private insurers maintain that they accomplish this implicitly by paying teaching hospitals more for clinical services than they pay most other hospitals. GME leaders think one possibility would be to include the costs of residency training when calculating premium amounts for products sold through health insurance exchanges. Similarly, a recent Carnegie Foundation report asserted that “GME redesign demands . . . a more broad-based, less politicized flow of funds.”

Dr. Darrell Kirch noted, CEO of AAMC, “A significant step forward is the announcement by the ACGME [Accreditation Council for Graduate Medical Education] describing major changes in how the nation’s residency programs will be accredited in the future, putting in place an outcomes-based evaluation system by which new physicians will be measured for their competency in performing the essential tasks necessary for clinical practice in the 21st century.”

Achieving Health Care Reform — How Physicians Can Help

Elliott S. Fisher, M.D., M.P.H., Donald M. Berwick, M.D., M.P.P., and Karen Davis, Ph.D.
N Engl J Med 2009; 360:2495-2497 http://dx.doi.org/10.1056/NEJMp0903923
http://www.nejm.org/doi/full/10.1056/NEJMp0903923

The recent commitment by several major stakeholders — including the American Medical Association — to slowing the growth of health care spending is a promising development. But the controversy about whether the organizations actually agreed to a 1.5-percentage-point reduction in annual spending growth is just one indication that success is still far from assured.

Two threats in particular put reform at risk: conflicting doctrines (regarding the creation of a new public insurance option and government support for comparative-effectiveness studies) and opposition to change among some current stakeholders. In the face of this uncertainty, physicians have a choice: to wait and see what happens or to lead the change our country needs. We’d prefer the latter.

The first level is aims. For health care reform, we propose that physicians, through their advocacy, help lead the country to embrace the so-called triple aim: better experience of care (safe, effective, patient-centered, timely, efficient, and equitable), better health for the population, and lower total per capita costs.

The second level is the design of the care processes that affect the patient — clinical “microsystems.” Health care microsystems are famously unreliable, variable in costs, and often unsafe. Physicians, through their participation in quality-improvement initiatives in their practices and hospitals, can and should lead the needed changes in the systems of care in which they work, to make them safer, more reliable, more patient-centered, and more affordable.

However, neither physicians nor anyone else on the front lines can improve care much on their own. Their most important source of support for improvement is the third level described by the IOM — the health care organizations that house almost all clinical microsystems and can ensure coordination among them. We need organizations large enough to be accountable for the full continuum of patients’ care as well as for achieving the triple aim. We will create a high-performing health care system only if integrated delivery systems become the mainstay of organizational design. Organizations could be virtually integrated, such as networks of independent physicians sharing electronic health records and administrative and clinical support for care management and quality improvement, or structurally integrated, such as multispecialty group practices or staff-model health maintenance organizations. Fostering the development of such accountable care organizations need not be disruptive to patients or providers: almost all physicians already work within natural referral networks that provide the vast majority of care to patients seen by the primary care physicians within the network.

Innovators-Prescription-New-Wave-of-Disruptive-Models-in-Healthcare

The IOM’s fourth level is the environment, which includes the payment, regulatory, legal, and educational systems. On this front, too, we need physician advocacy. The United States cannot achieve the triple aim without health insurance for everyone. Integrated delivery systems that are accountable for populations won’t thrive unless payment systems encourage their development and unless we change the laws and regulations — including proscriptions of gainsharing and anti-kickback rules — that prevent cooperation among health care professionals and organizations.

If stakeholders can agree on such a vision of health care reform, perhaps we could shift our focus from the conflict over whether a new public plan should be created to a more constructive insistence that all health plans, whether public or private, focus on the development of professionally led, integrated systems.

If health care providers and suppliers could actually achieve this reduction in growth rates, the federal government would harvest about $1.1 trillion in savings over the 11-year period — enough, perhaps, to close the deal on affordable health insurance for all. Others would also see savings: $497 billion for employers, $529 billion for state and local governments, and $671 billion for households. One simple way for physicians to start contributing to this goal is by reassessing and scaling back, where appropriate, their use of clinical practices now listed as “overused” by the National Quality Forum’s National Priorities Partnership.

Editor-in-Chief Eric J. Topol, MD, interviews Secretary of Health and Human Services (HHS) Kathleen Sebelius

Medscape

Editor’s Note: On the eve of the first anniversary of the Supreme Court’s ruling to uphold most provisions of the Affordable Care Act (ACA), Medscape Editor-in-Chief Eric J. Topol, MD, questioned Secretary of Health and Human Services (HHS) Kathleen Sebelius about the act’s effect on medical technology, clinical trial participation, genetic testing, primary care, and patient safety.

Introduction

Dr. Topol: We are experiencing a digital revolution in which technological advances are putting healthcare where it should be: in the hands of patients. How is the ACA helping to foster medical innovation?
Secretary Sebelius: A recent New York Times column, “Obamacare’s Other Surprise,”[1] by Thomas L. Friedman, echoes what we’ve been hearing from healthcare providers and innovators: Data that support medical decision-making and collaboration, dovetailing with new tools in the Affordable Care Act, are spurring the innovation necessary to deliver improved healthcare for more people at affordable prices.
Today we are focused on driving a smarter healthcare system with an emphasis on the quality — not quantity — of care. The healthcare law includes many tools to increase transparency, avoid costly mistakes and hospital readmissions, keep patients healthy, and test new payment and care delivery models, like Accountable Care Organizations (ACOs). Health information technology is a critical underpinning to this larger strategy.
In May we reached an important milestone in the adoption of health information technology. More than half of all doctors and other eligible providers, and nearly 80% of hospitals, are using electronic health records (EHRs) to improve care, an increase of at least 200% since 2008. Also in May, we announced a $1 billion challenge to help jump-start innovative projects that test creative ways to deliver high-quality medical care and lower costs to people enrolled in Medicare and Medicaid, following 81 Health Care Innovation Awards that HHS awarded last year.
Dr. Topol: Physicians have long lamented the lack of participation by patients in clinical trials, but the ACA is opening the door for greater participation by allowing patients to keep their health insurance while participating in clinical research. Are patients even aware that this provision now exists? How do you see it affecting clinical trial participation in the future?
Secretary Sebelius: In 2014, thanks to the ACA, insurance companies will no longer be able to deny patients from participating in an approved clinical trial for treatment of cancer or another life-threatening disease or condition, nor can they deny or limit the coverage of routine patient costs for items or services in connection with trial participation. For many patients, access to cutting-edge medicine available through clinical trials can increase their likelihood of survival. This is an important protection for patients that not only could have a life-altering impact, but it’s also one that serves to facilitate participation in research that is critical to expanding our knowledge base and finding cures and treatments for those illnesses that threaten the lives of Americans each day.
Dr. Topol: One of the intentions of the ACA is to increase the primary care workforce. This is critical as we approach 2014, when more Americans than ever will have either private insurance or Medicaid. Have you seen any movement in the primary care workforce? Are there concerns that there aren’t enough clinicians available to meet the forthcoming patient load?
Secretary Sebelius: Primary care providers are critical to ensuring better coordinated care and better health outcomes for all Americans. To meet the health needs of Americans, the Obama Administration has made the recruitment, training, and retention of primary care professionals a top priority.
Together, the ACA, the American Recovery and Reinvestment Act of 2009, and ongoing federal investments in the healthcare workforce have led to significant progress in training new primary care providers — such as physicians, nurse practitioners, and physician assistants — and encouraging primary care providers to practice in underserved areas, including:
Nearly tripling the National Health Service Corps;
Increasing the number of medical residents, nurse practitioners, and physician assistants trained in primary care, including placing over 1500 new primary care providers in underserved areas;
Creating primary care payment incentives for providers; and Redistributing unused residency positions and directing those slots for the training of primary care physicians.
Additionally, the ACA is modernizing the primary care training infrastructure, creating new primary care clinical training opportunities, supporting primary care practice, and improving payment and financial incentives for coordinated care.
Improving Hospital Safety
Dr. Topol: George Orwell once said that the hospital is the antechamber to the tomb. That was written decades ago, and unfortunately there’s still truth to that today. One in 4 hospital patients in America have a problem with medical mistakes, contract hospital-acquired infections, and experience medication errors. The ACA last year began linking Medicare payments to quality of patient care, offering financial incentives to hospitals that improve patient care. How is this working? Have there been any meaningful care improvements over the past year?
Secretary Sebelius: The ACA includes steps to improve the quality of healthcare and, in so doing, lowers costs for taxpayers and patients. This means avoiding costly mistakes and readmissions, keeping patients healthy, rewarding quality instead of quantity, and creating the health information technology infrastructure that enables new payment and delivery models to work. These reforms and investments will build a healthcare system that will ensure quality care for generations to come.
Already we have made significant progress:
Healthcare Spending Is Slowing
Secretary Sebelius: Medicare spending per beneficiary grew just 0.4% per capita in fiscal year 2012, continuing the pattern of very low growth in 2010 and 2011. Medicaid spending per beneficiary also decreased 0.9% in 2011, compared with 0.6% growth in 2010. Average annual increases in family premiums for employer-sponsored insurance were 6.2% from 2004 to 2008, 5.6% from 2009 to 2012, and 4.5% in 2012 alone.
Health Outcomes Are Improving and Adverse Events Are Decreasing
Secretary Sebelius: Several programs tie Medicare reimbursement for hospitals to their readmission rates, when patients have to come back into the hospital within 30 days of being discharged. Additionally, as part of a new ACA initiative, clinicians at some hospitals have reduced their early elective deliveries to close to zero, meaning fewer at-risk newborns and fewer admissions to the NICU.
Providers Are Engaged
Secretary Sebelius: In 2012, we debuted the Medicare Shared Savings Program and the Pioneer Accountable Care Organization Model. These programs encourage providers to invest in redesigning care for higher-quality and more efficient service delivery, without restricting patients’ freedom to go to the Medicare provider of their choice.
Over 250 organizations are participating in Medicare ACOs, serving approximately 4 million, or 8%, of Medicare beneficiaries. As existing ACOs choose to add providers and as more organizations join the program, participation in ACOs is expected to grow. ACOs are estimated to save up to $940 million in the first 4 years.
Bundle with Care ‹ Rethinking Medicare Incentives for Post­Acute Care Services

Feder J. N Engl J Med 2013; 369:400-401

A Medicare payment approach in which savings and risk are shared may achieve a better balance of cost, quality, and access than a system of single bundled payments, at least until our capacity to measure patients’ care needs and outcomes is sufficiently robust.

Healthcare Reform 2014: Mandated Coverage, Insurance Exchanges, and Employer Requirements

3 of 5 in Series: The Essentials of Healthcare Reform
http://www.dummies.com/how-to/content/healthcare-reform-2014-mandated-coverage-insurance.html

The Affordable Care Act federal and state officials are working with leaders in the health and insurance industries to restructure our nation’s healthcare system. That restructuring means most Americans will be required to have health insurance and most businesses will be required to offer it to their employees. It also means the creation of another kind of insurance plan called a health insurance exchange.

The government will require most Americans to have health insurance by 2014. The government has enacted this provision as a way to get healthy people who don’t feel the need to pay for coverage to buy insurance. That way, the healthy people can help fund the cost of people who require more medical care.

Several states filed, and lost, a suit against the federal government saying that it is unconstitutional to make individual citizens to buy health insurance.

If you don’t have coverage and you’re not in one of the groups that is an exception to the rule, you’ll pay a penalty. You may not be required to purchase health insurance if you

  • Face financial hardships.
  • Have been uninsured for less than three months.
  • Have religious objections.
  • Are American Indian.
  • Are a prison inmate.
  • Are an undocumented immigrant.

If you’re penalized, the amount you’ll be fined will go up each year for the first three years. In 2014, you’ll pay $95 or 1 percent of your taxable income, whichever is greater. In 2015, the fine will be $325 or 2 percent of taxable income, and in 2016 the penalty will be $695 or 2.5 percent of income. Each year after 2016, the government will refigure the fine based on a cost-of-living adjustment.

To help you meet the cost of mandated insurance, the government will offer premium credits and cost sharing subsidies if you and your family meet certain income guidelines and if you enroll in one of the new state-run insurance exchanges.

If your income falls between 133 and 400 percent of the federal poverty level (FPL), you could receive premium credits that will lower the maximum amount of premium you have to pay for your coverage.

  • There will be a catastrophic plan for people under 30 and for those who are exempt from mandated coverage.

States don’t have to set up the exchanges. If a state chooses not to, the federal government can come in and create them. States that do opt for exchanges will decide whether they’ll be run by a government or not-for-profit entity.

Health Care Reform — Why So Much Talk and So Little Action?

Victor R. Fuchs, Ph.D
N Engl J Med 2009; 360:208-209 http://dx.doi.org/10.1056/NEJMp0809733
http://www.nejm.org/doi/full/10.1056/NEJMp0809733

First, many organizations and individuals prefer the status quo. This category includes health insurance companies; manufacturers of drugs, medical devices, and medical equipment; companies that employ mostly young, healthy workers and therefore have lower health care costs than they would if required to help subsidize care for the poor and the sick; high-income employees, whose health insurance is heavily subsidized through a tax exemption for the portion of their compensation spent on health insurance; business leaders and others who are ideologically opposed to a larger role of government; highly paid physicians in some surgical and medical specialties; and workers who mistakenly believe that their employment-based insurance is a gift from their employer rather than an offset to their potential take-home pay.

Second, as Niccoló Machiavelli presciently wrote in 1513, “There is nothing more difficult to manage, more dubious to accomplish, nor more doubtful of success . . . than to initiate a new order of things. The reformer has enemies in all those who profit from the old order and only lukewarm defenders in all those who would profit from the new order.”

Third, our country’s political system renders Machiavelli’s Law of Reform particularly relevant in the United States, where many potential “choke points” offer opportunities to stifle change. The problem starts in the primary elections in so-called safe congressional districts, where special-interest money can exert a great deal of influence because of low voter turnout. The fact that Congress has two houses increases the difficulty of passing complex legislation, especially when several committees may claim jurisdiction over portions of a bill. Also, a supermajority of 60% may be needed to force a vote in the filibuster-prone Senate.

Fourth, reformers have failed to unite behind a single approach. Disagreement among reformers has been a major obstacle to substantial reform since early in the last century. According to historian Daniel Hirshfield, “Some saw health insurance primarily as an educational and public health measure, while others argued that it was an economic device to precipitate a needed reorganization of medical practice. . . . Some saw it as a device to save money for all concerned, while others felt sure that it would increase expenditures significantly.” These differences in objectives persist to this day.

Health insurers are opening stores alongside department stores, other typical mall tenants.

Jayne O’Donnell , USA TODAY
 http://www.usatoday.com/story/news/nation/2013/09/12/health-insurance-sales-retail-stores-malls/2789897/

,The new health law known as the Affordable Care Act means most uninsured Americans are required to have insurance beginning March 31 or pay a penalty at tax time in 2015.

Insurers need to sign up as many healthy, younger people as they can to pay for all of the older, sick customers they will be taking on. The law prohibits insurers from denying people insurance because of pre-existing health problems and limits how much more they can charge older than younger people.

So, for the first time, insurers are fiercely competing to attract individual consumers and turning to traditional retail marketing techniques to do so, luring them into stores with special events and using splashy advertising. As any retailer knows, they have the greatest chance of converting shoppers to customers once they have them in their retail locations or on their sites.

The Medical Breakthrough Nobody’s Talking About

Toby Cosgrove, CEO and President at Cleveland Clinic

http://www.linkedin.com/today/post/article/20130912184535-205372152-the-medical-breakthrough-nobody-s-talking-about

The latest medical breakthrough hasn’t gotten much press, but it’s changing medicine even as we speak. It’s the dawning realization that healthcare is not about how many patients you can see, how many tests and procedures you can order, or how much you can charge for these things. The breakthrough is the understanding that healthcare is a value proposition, which means getting patients the right care, at the right time, in the right place. It’s a matter of focusing on outcomes and cost, so that more Americans will start getting what they pay for in healthcare dollars.

Value-based care focuses on two targets: outcomes and cost. Until recently, providers pursued these goals separately, with doctors concentrating on outcomes and the administrators trying to control costs. Value-based care does something different. It works to bring these targets into alignment. The caregivers in a value-based provider work with cost-experts as a team to simultaneously improve outcomes and lower expenses.

Doctors, hospitals and payers are partners in the move to value-based care. The Affordable Care Act includes incentives for providers to improve outcomes and lower costs. But this is one breakthrough that will take time for implementation nationwide. Providers who make the transition early will be rewarded with more satisfied patients, lower expenses and pride in a job well done.

Six-Month Enforcement Delay After Guidance

According to AAMC, the language in the final rule requires that the order to admit a patient be written by a practitioner “who has admitting privileges at the hospital,” something that few residents have as they are not considered members of the hospital’s medical staff.

AAMC said it brought the issue to CMS’s attention during an Open Door Forum call Aug. 15. The agency acknowledged it did not intend to prohibit residents from admitting patients, and said it would be issuing a Q&A. However, AAMC said until the issue can be resolved “to the satisfaction of the teaching hospital community,” CMS should make clear to all contractors that no inpatient admission should be denied because it was ordered by a resident while under the supervision of an attending physician.

AAMC said CMS should delay enforcing the new requirements for at least six months following the release of the guidance so hospitals will have sufficient time to understand the rules, educate physicians and others, and ensure that they have put in place the mechanisms that are needed to comply with the new requirements.

“As short inpatient stays have been a focus of audits by [Recovery Audit Contractors], hospitals feel especially at risk for failure to properly implement CMS requirements,” AAMC said.

The letter is available at http://op.bna.com/hl.nsf/r?Open=nwel-9auqls.

Read Full Post »

Heart, Vascular Smooth Muscle, Excitation-Contraction Coupling (E-CC), Cytoskeleton, Cellular Dynamics and Ca2 Signaling

Heart, Vascular Smooth Muscle, Excitation-Contraction Coupling (E-CC), Cytoskeleton, Cellular Dynamics and Ca2 Signaling

Author and Curator: Larry H Bernstein, MD, FCAP

Author and Cardiovascular Three-volume Series, Editor: Justin Pearlman, MD, PhD, FACC, and

Curator: Aviva Lev-Ari, PhD, RN

Article V Heart, Vascular Smooth Muscle, Excitation-Contraction Coupling (E-CC), Cytoskeleton, Cellular Dynamics and Ca2 Signaling

Image created by Adina Hazan 06/30/2021

Abbreviations

AP, action potential; ARVD2, arrhythmogenic right ventricular cardiomyopathy type 2; CaMKII, Ca2+/calmodulim-dependent protein kinase II; CICR, Ca2+ induced Ca2+ release;CM, calmodulin; CPVT, catecholaminergic polymorphic ventricular tachycardia;  ECC, excitation–contraction coupling; FKBP12/12.6, FK506 binding protein; HF, heart failure; LCC, L-type Ca2+ channel;  P-1 or P-2, phosphatase inhibitor type-1 or type-2; PKA, protein kinase A; PLB, phosphoplamban; PP1, protein phosphatase 1; PP2A, protein phosphatase 2A; RyR1/2, ryanodine receptor type-1/type-2; SCD, sudden cardiac death; SERCA, sarcoplasmic reticulum Ca2+ ATPase; SL, sarcolemma; SR, sarcoplasmic reticulum.

This is Part V of a series on the cytoskeleton and structural shared thematics in cellular movement and cellular dynamics.

The Series consists of the following articles:

Part I: Identification of Biomarkers that are Related to the Actin Cytoskeleton

Larry H Bernstein, MD, FCAP

http://pharmaceuticalintelligence.com/2012/12/10/identification-of-biomarkers-that-are-related-to-the-actin-cytoskeleton/

Part II: Role of Calcium, the Actin Skeleton, and Lipid Structures in Signaling and Cell Motility

Larry H. Bernstein, MD, FCAP, Stephen Williams, PhD and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/08/26/role-of-calcium-the-actin-skeleton-and-lipid-structures-in-signaling-and-cell-motility/

Part III: Renal Distal Tubular Ca2+ Exchange Mechanism in Health and Disease

Larry H. Bernstein, MD, FCAP, Stephen J. Williams, PhD
 and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/09/02/renal-distal-tubular-ca2-exchange-mechanism-in-health-and-disease/

Part IV: The Centrality of Ca(2+) Signaling and Cytoskeleton Involving Calmodulin Kinases and Ryanodine Receptors in Cardiac Failure, Arterial Smooth Muscle, Post-ischemic Arrhythmia, Similarities and Differences, and Pharmaceutical Targets


Larry H Bernstein, MD, FCAP, Justin Pearlman, MD, PhD, FACC and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/09/08/the-centrality-of-ca2-signaling-and-cytoskeleton-involving-calmodulin-kinases-and-ryanodine-receptors-in-cardiac-failure-arterial-smooth-muscle-post-ischemic-arrhythmia-similarities-and-differen/

Part V: Heart, Vascular Smooth Muscle, Excitation-Contraction Coupling (E-CC), Cytoskeleton, Cellular Dynamics and Ca2 Signaling

Larry H Bernstein, MD, FCAP, Justin Pearlman, MD, PhD, FACC and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/08/26/heart-smooth-muscle-excitation-contraction-coupling-cytoskeleton-cellular-dynamics-and-ca2-signaling/

Part VI: Calcium Cycling (ATPase Pump) in Cardiac Gene Therapy: Inhalable Gene Therapy for Pulmonary Arterial Hypertension and Percutaneous Intra-coronary Artery Infusion for Heart Failure: Contributions by Roger J. Hajjar, MD

Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/08/01/calcium-molecule-in-cardiac-gene-therapy-inhalable-gene-therapy-for-pulmonary-arterial-hypertension-and-percutaneous-intra-coronary-artery-infusion-for-heart-failure-contributions-by-roger-j-hajjar/

Part VII: Cardiac Contractility & Myocardium Performance: Ventricular Arrhythmias and Non-ischemic Heart Failure – Therapeutic Implications for Cardiomyocyte Ryanopathy (Calcium Release-related Contractile Dysfunction) and Catecholamine Responses

Justin Pearlman, MD, PhD, FACC, Larry H Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN

http://pharmaceuticalintelligence.com/2013/08/28/cardiac-contractility-myocardium-performance-ventricular-arrhythmias-and-non-ischemic-heart-failure-therapeutic-implications-for-cardiomyocyte-ryanopathy-calcium-release-related-contractile/

In the first part, we discussed common MOTIFs across cell-types that are essential for cell division, embryogenesis, cancer metastasis, osteogenesis, musculoskeletal function, vascular compliance, and cardiac contractility.   This second article concentrates on specific functionalities for cardiac contractility based on Ca++ signaling in excitation-contraction coupling.  The modifications discussed apply specifically to cardiac muscle and not to skeletal muscle.  Considering the observations described might raise additional questions specifically address to the unique requirements of smooth muscle, abundant in the GI tract and responsible for motility in organ function, and in blood vessel compliance or rigidity. Due to the distinctly different aspects of the cardiac contractility and contraction force, and the interactions with potential pharmaceutical targets, there are two separate articles on calcium signaling and cardiac arrhythmias or heart failure (Part 2 and Part 3).  Part 2 focuses on the RYANODINE role in cardiac Ca(2+) signaling and its effect in heart failure.  Part 3 takes up other aspects of heart failure and calcium signaling with respect to phosporylation/dephosphorylation. I add a single review and classification of genetic cardiac disorders of the same cardiac Ca(2+) signaling and the initiation and force of contraction. Keep in mind that the heart is a syncytium, and this makes a huge difference compared with skeletal muscle dynamics. In Part 1 there was some discussion of the importance of Ca2+ signaling on innate immune system, and the immunology will be further expanded in a fourth of the series.

SUMMARY:

This second article on the cardiomyocyte and the Ca(2+) cycling between the sarcomere and the cytoplasm, takes a little distance from the discussion of the ryanodine that precedes it.  In this discussion we found that there is a critical phosphorylation/dephosphorylation balance that exists between Ca(+) ion displacement and it occurs at a specific amino acid residue on the CaMKIId, specific for myocardium, and there is a 4-fold increase in contraction and calcium release associated with this CAM kinase (ser 2809) dependent exchange.  These events are discussed in depth, and the research holds promise for therapeutic application. We also learn that Ca(2+) ion channels are critically involved in the generation of arrhythmia as well as dilated and hypertrophic cardiomyopathy.  In the case of arrhythmiagenesis, there are two possible manners by which this occurs.  One trigger is Ca(2+) efflux instability.  The other is based on the finding that when the cellular instability is voltage driven, the steady-state wave­length (separation of nodes in space) depends on electrotonic coupling between cells and the steepness of APD and CV restitution. The last article is an in depth review of the genetic mutations that occur in cardiac diseases.  It is an attempt at classifying them into reasonable groupings. What are the therapeutic implications of this? We see that the molecular mechanism of cardiac function has been substantially elucidated, although there are contradictions in experimental findings that are unexplained.  However, for the first time, it appears that personalized medicine is on a course that will improve health in the population, and the findings will allow specific targets designed for the individual with a treatable impairment in cardiac function that is identifiable early in the course of illness. This article is a continuation to the following articles on tightly related topics: Part I: Identification of Biomarkers that are Related to the Actin Cytoskeleton     Larry H Bernstein, MD, FCAP http://pharmaceuticalintelligence.com/2012/12/10/identification-of-biomarkers-that-are-related-to-the-actin-cytoskeleton/ Part II:  Role of Calcium, the Actin Skeleton, and Lipid Structures in Signaling and Cell Motility    Larry H. Bernstein, MD, FCAP, Stephen Williams, PhD and Aviva Lev-Ari, PhD, RN  http://pharmaceuticalintelligence.com/2013/08/26/role-of-calcium-the-actin-skeleton-and-lipid-structures-in-signaling-and-cell-motility/ Part III: Renal Distal Tubular Ca2+ Exchange Mechanism in Health and Disease    Larry H. Bernstein, MD, FCAP, Stephen J. Williams, PhD
 and  Aviva Lev-Ari, PhD, RN http://pharmaceuticalintelligence.com/2013/09/02/renal-distal-tubular-ca2-exchange-mechanism-in-health-and-disease/ Part  IV:  The Centrality of Ca(2+) Signaling and Cytoskeleton Involving Calmodulin Kinases and Ryanodine Receptors in Cardiac Failure, Arterial Smooth Muscle, Post-ischemic Arrhythmia, Similarities and Differences, and Pharmaceutical Targets Larry H Bernstein, MD, FCAP, Justin Pearlman, MD, PhD, FACC and Aviva Lev-Ari, PhD, RN  http:/pharmaceuticalintelligence.com/2013.09.089/lhbern/The Centrality of Ca(2+) Signaling and Cytoskeleton Involving Calmodulin Kinases and Ryanodine Receptors in Cardiac Failure, Arterial Smooth Muscle, Post-ischemic Arrhythmia, Similarities and Differences, and Pharmaceutical Targets

Part V:  Heart Smooth Muscle and Cardiomyocyte Cells: Excitation-Contraction Coupling & Ryanodine Receptor (RyR) type-1/type-2 in Cytoskeleton Cellular Dynamics and Ca2+ Signaling

Larry H Bernstein, MD, FCAP, Justin Pearlman, MD, PhD, FACC and Aviva Lev-Ari, PhD, RN http://pharmaceuticalintelligence.com/2013/08/26/heart-smooth-muscle-excitation-contraction-coupling-cytoskeleton-cellular-dynamics-and-ca2-signaling/ Part VI:  Calcium Cycling (ATPase Pump) in Cardiac Gene Therapy: Inhalable Gene Therapy for Pulmonary Arterial Hypertension and Percutaneous Intra-coronary Artery Infusion for Heart Failure: Contributions by Roger J. Hajjar, MD Curator: Aviva Lev-Ari, PhD, RN http://pharmaceuticalintelligence.com/2013/08/01/calcium-molecule-in-cardiac-gene-therapy-inhalable-gene-therapy-for-pulmonary-arterial-hypertension-and-percutaneous-intra-coronary-artery-infusion-for-heart-failure-contributions-by-roger-j-hajjar/ and Advanced Topics in Sepsis and the Cardiovascular System at its End Stage Larry H Bernstein, MD, FCAP  http://pharmaceuticalintelligence.com/2013/08/18/advanced-topics-in-sepsis-and-the-cardiovascular-system-at-its-end-stage/

The Role of Protein Kinases and Protein Phosphatases in the Regulation of Cardiac Sarcoplasmic Reticulum Function

EG Kranias, RC Gupta, G Jakab, HW Kim, NAE Steenaart, ST Rapundalo Molecular and Cellular Biochemistry 06/1988; 82(1):37-44. · 2.06 Impact Factor http://www.researchgate.net/publication/6420466_Protein_phosphatases_decrease_sarcoplasmic_reticulum_calcium_content_by_stimulating_calcium_release_in_cardiac_myocytes Canine cardiac sarcoplasmic reticulum is phosphorylated by

  • adenosine 3,5-monophosphate (cAMP)-dependent and
  • calcium calmodulin-dependent protein kinases on
  • a proteolipid, called phospholamban.

Both types of phosphorylation are associated with

  •  an increase in the initial rates of Ca(2+) transport by SR vesicles
  • which reflects an increased turnover of elementary steps of the calcium ATPase reaction sequence.

The stimulatory effects of the protein kinases on the calcium pump may be reversed by an endogenous protein phosphatase, which

  • can dephosphorylate both the CAMP-dependent and the calcium calmodulin-dependent sites on phospholamban.

Thus, the calcium pump in cardiac sarcoplasmic reticulum appears to be under reversible regulation mediated by protein kinases and protein phosphatases. calcium release calmodulin + ER Ca(2+) and contraction

Regulation of the Cardiac Ryanodine Receptor Channel by Luminal Ca2+ involves Luminal Ca2+ Sensing Sites

I Györke, S Györke.   Biophysical Journal 01/1999; 75(6):2801-10. · 3.65 Impact factor  http:// www.researchgate.net/publication/13459335/Regulation_of_the_cardiac_ryanodine_receptor_channel_by_luminal_Ca2_involves_luminal_Ca2_sensing_sites The mechanism of activation of the cardiac calcium release channel/ryanodine receptor (RyR) by luminal Ca(2+) was investigated in native canine cardiac RyRs incorporated into lipid bilayers in the presence of 0.01 microM to 2 mM Ca(2+) (free) and 3 mM ATP (total) on the cytosolic (cis) side and 20 microM to 20 mM Ca(2+) on the luminal (trans) side of the channel and with Cs+ as the charge carrier. Under conditions of low [trans Ca(2+)] (20 microM), increasing [cis Ca(2+)] from 0.1 to 10 microM caused a gradual increase in channel open probability (Po). Elevating [cis Ca(2+)] [cytosolic] above 100 microM resulted in a gradual decrease in Po. Elevating trans [Ca(2+)] [luminal] enhanced channel activity (EC50 approximately 2.5 mM at 1 microM cis Ca2+) primarily by increasing the frequency of channel openings. The dependency of Po on trans [Ca2+] [luminal] was similar at negative and positive holding potentials and was not influenced by high cytosolic concentrations of the fast Ca(2+) chelator, 1,2-bis(2-aminophenoxy)ethane-N,N,N, N-tetraacetic acid. Elevated luminal Ca(2+)

  1. enhanced the sensitivity of the channel to activating cytosolic Ca(2+), and it
  2. essentially reversed the inhibition of the channel by high cytosolic Ca(2+).

Potentiation of Po by increased luminal Ca(2+) occurred irrespective of whether the electrochemical gradient for Ca(2+) supported a cytosolic-to-luminal or a luminal-to-cytosolic flow of Ca(2+) through the channel. These results rule out the possibility that under our experimental conditions, luminal Ca(2+) acts by interacting with the cytosolic activation site of the channel and suggest that the effects of luminal Ca2+ are mediated by distinct Ca(2+)-sensitive site(s) at the luminal face of the channel or associated protein. F1.large  calcium movement and RyR2 receptor

Protein phosphatases Decrease Sarcoplasmic Reticulum Calcium Content by Stimulating Calcium Release in Cardiac Myocytes

D Terentyev, S Viatchenko-Karpinski, I Gyorke, R Terentyeva and S Gyorke Texas Tech University Health Sciences Center, Lubbock, TX J Physiol 2003; 552(1), pp. 109–118.  http://dx.doi.org/10.1113/jphysiol.2003.046367 Phosphorylation/dephosphorylation of Ca2+ transport proteins by cellular kinases and phosphatases plays an important role in regulation of cardiac excitation–contraction coupling; furthermore,

  • abnormal protein kinase and phosphatase activities have been implicated in heart failure.

However, the precise mechanisms of action of these enzymes on intracellular Ca2+ handling in normal and diseased hearts remains poorly understood. We have investigated

  •   the effects of protein phosphatases PP1 and PP2A on spontaneous Ca(2+) sparks and SR Ca(2+) load in myocytes permeabilized with saponin.

Exposure of myocytes to PP1 or PP2A caused a dramatic increase in frequency of Ca(2+) sparks followed by a nearly complete disappearance of events, which were accompanied by depletion of the SR Ca(2+) stores, as determined by application of caffeine. These changes in

  •  Ca(2+) release and
  • SR Ca(2+) load

could be prevented by the inhibitors of PP1 and PP2A phosphatase activities okadaic acid and calyculin A. At the single channel level, PP1 increased the open probability of RyRs incorporated into lipid bilayers. PP1-medited RyR dephosphorylation in our permeabilized myocytes preparations was confirmed biochemically by quantitative immunoblotting using a phosphospecific anti-RyR antibody. Our results suggest that

  •  increased intracellular phosphatase activity stimulates
  • RyR mediated SR Ca(2+) release
    • leading to depleted SR Ca(2+) stores in cardiac myocytes.

In heart muscle cells, the process of excitation–contraction (EC) coupling is mediated by

  •  Ca(2+) influx through sarcolemmal L-type Ca(2+) channels
  • activating Ca(2+) release channels (ryanodine receptors, RyRs) in the sarcoplasmic reticulum (SR).

Once activated, the RyR channels allow Ca(2+) to be released from the SR into the cytosol to induce contraction. This mechanism is known as Ca(2+)-induced calcium release (CICR) (Fabiato, 1985; Bers, 2002).  During relaxation, most of the Ca(2+) is resequestered into the SR by the Ca(2+)-ATPase. The amount of Ca(2+) released and the force of contraction depend on

  •  the magnitude of the Ca(2+) trigger signal,
  • the functional state of the RyRs and
  • the amount of Ca(2+) stored in the SR.

F1.large  calcium movement and RyR2 receptor Ca(2+) and contraction calcium release calmodulin + ER Reversible phosphorylation of proteins composing the EC coupling machinery plays an important role in regulation of cardiac contractility (Bers, 2002). Thus, during stimulation of the b-adrenergic pathway, phosphorylation of several target proteins, including

  • the L-type Ca(2+) channels,
  • RyRs and
  • phospholamban,

by protein kinase A (PKA) leads to an overall increase in SR Ca2+ release and contractile force in heart cells (Callewaert et al. 1988, Spurgeon et al. 1990; Hussain & Orchard, 1997; Zhou et al. 1999; Song et al. 2001; Viatchenko-Karpinski & Gyorke, 2001). PKA-dependent phosphorylation of the L-type Ca(2+) channels increases the Ca2+ current (ICa), increasing both

  • the Ca2+ trigger for SR Ca2+ release and
  • the SR Ca(2+) content

(Callewaert et al. 1988; Hussain & Orchard, 1997; Del Principe et al. 2001). Phosphorylation of phospholamban (PLB) relieves the tonic inhibition dephosphorylated PLB exerts on the SR Ca(2+)-ATPase (SERCA) resulting in enhanced SR Ca(2+) accumulation and enlarged Ca(2+) release (Kranias et al. 1985; Simmermann & Jones, 1998). With regard to the RyR, despite clear demonstration of phosphorylation of the channel in biochemical studies (Takasago et al. 1989; Yoshida et al. 1992), the consequences of this reaction to channel function have not been clearly defined. RyR phosphorylation by PKA and Ca(2+)–calmodulin dependent protein kinase (CaMKII) has been reported to increase RyR activity in lipid bilayers (Hain et al. 1995; Marx et al. 2000; Uehara et al. 2002). Moreover, it has been reported that in heart failure (HF), hyperphosphorylation of RyR causes

  •  the release of FK-506 binding protein (FKBP12.6) from the RyR,
    • rendering the channel excessively leaky for Ca(2+) (Marx et al. 2000).

However, other studies have reported no functional effects (Li et al. 2002) or even found phosphorylation to reduce RyR channel steady-state open probability (Valdivia et al. 1995; Lokuta et al. 1995).  The action of protein kinases is opposed by dephosphorylating phosphatases. Three types of protein phosphatases (PPs), referred to as PP1, PP2A and PP2B (calcineurin), have been shown to influence cardiac performance (Neumann et al. 1993; Rusnak & Mertz, 2000). Overall, according to most studies phosphatases appear to downregulate SR Ca(2+) release and contractile performance (Neumann et al. 1993; duBell et al. 1996, 2002; Carr et al. 2002; Santana et al. 2002). Furthermore, PP1 and PP2A activities appear to be increased in heart failure (Neumann, 2002; Carr et al. 2002). However, again the precise mode of action of these enzymes on intracellular Ca(2+) handling in normal and diseased hearts remains poorly understood.  In the present study, we have investigated the effects of protein phosphatases PP1 and PP2A on local Ca(2+) release events, Ca(2+) sparks, in cardiac cells. Our results show that

  •  phosphatases activate RyR mediated SR Ca(2+) release
    • leading to depletion of SR Ca(2+) stores.

These results provide novel insights into the mechanisms and potential role of protein phosphorylation/dephosphorylation in regulation of Ca(2+) signaling in normal and diseased hearts. F2.large   RyR and calcium

RESULTS

Effects of PP1 and PP2A on Ca2+ sparks and SR Ca(2+) content.

[1]  PP1 caused an early transient potentiation of Ca2+ spark frequency followed by a delayed inhibition of event occurrence. [2]  PP1 produced similar biphasic effects on the magnitude and spatio-temporal characteristics of Ca(2+) sparks Specifically, during the potentiatory phase (1 min after addition of the enzyme), PP1 significantly increased

  • the amplitude,
  • rise-time,
  • duration and
  • width of Ca(2+) sparks;

during the inhibitory phase (5 min after addition of the enzyme),

  •  all these parameters were significantly suppressed by PP1.

The SR Ca(2+) content decreased by 35 % or 69 % following the exposure of myocytes to either 0.5 or 2Uml_1 PP1, respectively (Fig. 1C). Qualitatively similar results were obtained with phosphatase PP2A. Similar to the effects of PP1, PP2A (5Uml_1) produced a transient increase in Ca(2+) spark frequency (~4-fold) followed by a depression of event occurrence and decreased SR Ca(2+) content (by 82 % and 65 %, respectively). Also similar to the action of PP1, PP2A increased

  •  the amplitude and
  • spatio-temporal spread (i.e. rise-time, duration and width) of Ca(2+) sparks at 1 min
  • and suppressed the same parameters at 5 min of exposure to the enzyme (Table 1).

Together, these results suggest that phosphatases enhance spark-mediated SR Ca2+ release, leading to decreased SR Ca(2+) content. Preventive effects of calyculin A and okadaic acid Preventive effects of ryanodine

PP1-mediated RyR dephosphorylation

F3.large  cardiomyocyte SR F3.large  cardiomyocyte SR F2.large   RyR and calcium coupled receptors coupled receptors The cardiac RyR is phosphorylated at Ser-2809 (in the rabbit sequence) by both PKA and CAMKII (Witcher et al. 1991; Marx et al. 2000). Although additional phosphorylation sites may exist on the RyR (Rodriguez et al. 2003), but Ser-2809 is believed to be the only site that is phosphorylated by PKA, and RyR hyperphosphorylation at this site has been reported in heart failure (Marx et al. 2000).  To test whether indeed phosphatases dephosphorylated the RyR in our permeabilized myocyte experiments we performed quantitative immunoblotting using an antibody that specifically recognizes the phosphorylated form of the RyR at Ser-2809 (Rodriguez et al. 2003). Myocytes exhibited a significant level of phosphorylation under baseline conditions. Maximal phosphorylation was 201 % of control. When exposed to 2Uml_1 PP1, RyR phosphorylation was 58 % of the control basal condition. Exposing to a higher PP1 concentration (10Uml_1) further reduced RyR phosphorylation to 22% of control. Thus, consistent with the results of our functional measurements,

  •  PP1 decreased RyR phosphorylation in cardiac myocytes.

Figure 1. Effects of PP1 on properties of Ca(2+) sparks and SR Ca(2+) content in rat permeabilized myocytes    see .  http://dx.doi.org/10.1113/jphysiol.2003.046367 A, spontaneous Ca(2+) spark images recorded under reference conditions, and 1 or 5 min after exposure of the cell to 2Uml_1 PP1. Traces below the images are Ca(2+) transients induced by application of 10 mM caffeine immediately following the acquisition of sparks before (3 min) and after (5 min) application of PP1 in the same cell. The Ca(2+) transients were elicited by a whole bath application of 10 mM caffeine. B, averaged spark frequency at early (1 min) and late (5 min) times following the addition of either 0.5 or 2Uml_1 of PP1 to the bathing solution. C, averaged SR Ca(2+) content for 0.5 or 2Uml_1 of PP1 measured before and 5 min after exposure to the enzyme. Data are presented as means ± S.E.M. of 6 experiments in different cells. Figure 2. Effects of PP2A on properties of Ca2+ sparks and SR Ca2+ content in rat permeabilized myocytes   see .  http://dx.doi.org/10.1113/jphysiol.2003.046367 A, spontaneous Ca(2+) spark images recorded under reference conditions, and 1 or 5 min after exposure of the cell to 5Uml_1 PP2A. Traces below the images are Ca(2+) transients induced by application of 10 mM caffeine immediately following the acquisition of sparks before (3 min) and after (5 min) application of PP2A in the same cell. B and C, averaged spark frequency (B) and SR Ca(2+) content (C) for the same conditions as in A. Data are presented as means ± S.E.M. of 6 experiments in different cells.

 DISCUSSION

In the present study, we have investigated the impact of physiologically relevant exogenous protein phosphatases PP1 and PP2A on RyR-mediated SR Ca(2+) release (measured as Ca(2+) sparks) in permeabilized heart cells. Our principal finding is that

  • phosphatases stimulated RyR channels lead to depleted SR Ca(2+) stores.

These results have important ramifications for understanding the mechanisms and role of protein phosphorylation/dephosphorylation in

  •  modulation of Ca(2+) handling in normal and diseased heart.

Modulation of SR Ca2+ release by protein phosphorylation/dephophorylation

Since protein dephosphorylation clearly resulted in increased functional activity of the Ca(+)release channel, our results imply that a reverse, phosphorylation reaction should reduce RyR activity. If indeed such effects take place, why do they not manifest in inhibition of Ca(+)sparks? One possibility is that enhanced Ca(+) uptake by SERCA

  •  masks or overcomes the effects phosphorylation may have on RyRs.

In addition, the potential inhibitory influence of protein phosphorylation on RyR activity in myocytes could be countered by feedback mechanisms  involving changes in luminal Ca(2+)(Trafford et al. 2002; Gyorke et al. 2002). In particular, reduced open probability of RyRs would be expected to lead to

  •  increased Ca2+ accumulation in the SR;
  • and increased intra-SR [Ca(2+)], in turn would
  • increase activity of RyRs at their luminal Ca(2+) regulatory sites

as demonstrated for the RyR channel inhibitor tetracaine (Gyorke et al. 1997; Overend et al. 1997). Thus

  • potentiation of SERCA
  • combined with the intrinsic capacity of the release mechanism to self-regulate

could explain at least in part why PKA-mediated protein phoshorylation results in maintained potentiation of Ca(2+) sparks despite a potential initial decrease in RyR activity.

Role of altered RyR Phosphorylation in Heart Failure

Marx et al. (2000) have proposed that  enhanced levels of circulating catecholamines lead to increased phosphorylation of RyR in heart failure.  Based on biochemical observations as well as on studying properties of single RyRs incorporated into artificial lipid bilayers, these investigators have hypothesized that

  •  hyperphosphorylation of RyRs contributes to pathogenesis of heart failure
    • by making the channel excessively leaky due to dissociation of FKBP12.6 from the channel.

We show that the mode of modulation of RyRs by phosphatases does not support this hypothesis as

  • dephosphorylation caused activation instead of

Interestingly, our results provide the basis for a different possibility in which

  •  dephophosphorylation of RyR rather than its phosphorylation causes depletion of SR Ca(2+) stores by stimulating RyRs in failing hearts.

It has been reported that PP1 and PP2 activities are increased in heart failure (Huang et al. 1999; Neumann et al. 1997; Neuman, 2002). Furthermore,  overexpression of PP1 or ablation of the endogenous PP1 inhibitor, l-1, results in

  • depressed contractile performance and heart failure (Carr et al. 2002).

Our finding that PP1 causes depletion of SR Ca(2+) stores by activating RyRs could account for, or contribute to, these results.

References

1 DelPrincipe F, Egger M, Pignier C & Niggli E (2001). Enhanced E-C coupling efficiency after beta-stimulation of cardiac myocytes. Biophys J 80, 64a. 2 Gyorke I & Gyorke S (1998). Regulation of the cardiac ryanodine receptor channel by luminal Ca2+ involves luminal Ca2+ sensing sites. Biophys J 75, 2801–2810. 3 Gyorke S, Gyorke I, Lukyanenko V, Terentyev D, Viatchenko-Karpinski S & Wiesner TF (2002). Regulation of sarcoplasmic reticulum calcium release by luminal calcium in cardiac muscle. Front Biosci 7, d1454–d1463. 4 Gyorke I, Lukyanenko V & Gyorke S (1997). Dual effects of tetracaine on spontaneous calcium release in rat ventricular myocytes. J Physiol 500, 297–309. 5 MacDougall LK, Jones LR & Cohen P (1991). Identification of the major protein phosphatases in mammalian cardiac muscle which dephosphorylate phospholamban. Eur J Biochem 196, 725–734. 6 Marx SO, Reiken S, Hisamatsu Y, Jayaraman T, Burkhoff D, Rosemblit N & Marks AR (2000). PKA phosphorylation dissociates FKBP12.6 from the calcium release channel (ryanodine receptor): defective regulation in failing hearts. Cell 101, 365–376. 7 Rodriguez P, Bhogal MS & Colyer J (2003). Stoichiometric phosphorylation of cardiac ryanodine receptor on serine-2809 by calmodulin-dependent kinase II and protein kinase A. J Biol Chem (in press).

The δC Isoform of CaMKII Is Activated in Cardiac Hypertrophy and Induces Dilated Cardiomyopathy and Heart Failure

T Zhang, LS Maier, ND Dalton, S Miyamoto, J Ross, DM Bers, JH Brown.  University of California, San Diego, La Jolla, Calif; and Loyola University, Chicago, Ill. Circ Res. 2003;92:912-919.    http://dx.doi.org/10.1161/01.RES.0000069686.31472.C5 Recent studies have demonstrated that transgenic (TG) expression of either Ca(2+)/calmodulin-dependent protein kinase IV (CaMKIV) or CaMKIIδB, both of which localize to the nucleus, induces cardiac hypertrophy. However,

  •  CaMKIV is not present in heart, and
  • cardiomyocytes express not only the nuclear CaMKIIδB
    • but also a cytoplasmic isoform, CaMKII δC.

In the present study, we demonstrate that

  1.  expression of the δC isoform of CaMKII is selectively increased and
  2. its phosphorylation elevated as early as 2 days and continuously for up to 7 days after pressure overload.

To determine whether enhanced activity of this cytoplasmic δC isoform of CaMKII can lead to phosphorylation of Ca(2+) regulatory proteins and induce hypertrophy, we generated TG mice that expressed the δC isoform of CaMKII.  Immunocytochemical staining demonstrated that the expressed transgene is confined to the cytoplasm of cardiomyocytes isolated from these mice. These mice develop a dilated cardiomyopathy with up to a 65% decrease in fractional shortening and die prematurely. Isolated myocytes are enlarged and exhibit reduced contractility and altered Ca2(2+) handling. Phosphorylation of the ryanodine receptor (RyR) at a CaMKII site is increased even before development of heart failure, and

  • CaMKII is found associated with the RyR  from the CaMKII TG mice.
  • Phosphorylation of phospholamban is increased specifically at the CaMKII but not at the PKA phosphorylation site.

These findings are the first to demonstrate that CaMKIIδC can mediate phosphorylation of Ca(2+) regulatory proteins in vivo and provide evidence for the involvement of CaMKIIδC activation in the pathogenesis of dilated cardiomyopathy and heart failure.  Multifunctional Ca(2+)/calmodulin-dependent protein kinases (CaM kinases or CaMKs) are transducers of Ca2+ signals that phosphorylate a wide range of substrates and thereby affect Ca(2+)-mediated cellular responses.1 The family includes CaMKI and CaMKIV, monomeric enzymes activated by CaM kinase kinase,2,3 and CaMKII, a multimer of 6 to 12 subunits activated by autophosphorylation.1 The CaMKII subunits α, β, γ, and δ show different tissue distributions,1 with

  • the δ isoform predominating in the heart.4–7
  • Splice variants of the δ isoform, characterized by the presence of a second variable domain,4,7 include δB, which contains a nuclear localization signal (NLS), and
  • δC, which does not. CaMKII composed of δB subunits localizes to the nucleus, whereas CaMKIIδC localizes to the cytoplasm.4,8,9

CaMKII has been implicated in several key aspects of acute cellular Ca(2+) regulation related to cardiac excitation-contraction (E-C) coupling. CaMKII

  • phosphorylates sarcoplasmic reticulum (SR) proteins including the ryanodine receptors (RyR2) and
  • phospholamban (PLB).10–14

Phosphorylation of RyR has been suggested to alter the channel open probability,14,15 whereas phosphorylation of PLB has been suggested to regulate SR Ca(2+) uptake.14 It is also likely that CaMKII phosphorylates the L-type Ca(2+) channel complex or an associated regulatory protein and thus

  1. mediates Ca(2+) current (ICa) facilitation.16-18 and
  2. the development of early after-depolarizations and arrhythmias.19

Thus, CaMKII has significant effects on E-C coupling and cellular Ca(2 +) regulation. Nothing is known about the CaMKII isoforms regulating these responses.  Contractile dysfunction develops with hypertrophy, characterizes heart failure, and is associated with changes in cardiomyocyte (Ca2+) homeostasis.20  CaMKII expression and activity are altered in the myocardium of rat models of hypertensive cardiac hypertrophy21,22 and heart failure,23 and

  • in cardiac tissue from patients with dilated cardiomyopathy.24,25

Several transgenic mouse models have confirmed a role for CaMK in the development of cardiac hypertrophy, as originally suggested by studies in isolated neonatal rat ventricular myocytes.9,26–28 Hypertrophy develops in transgenic mice that overexpress CaMKIV,27 but this isoform is not detectable in the heart,4,29 and CaMKIV knockout mice still develop hypertrophy after transverse aortic constriction (TAC).29  Transgenic mice overexpressing calmodulin developed severe cardiac hypertrophy,30 later shown to be associated with an increase in activated CaMKII31; the isoform of CaMKII involved in hypertrophy could not be determined from these studies. We recently reported that transgenic mice that overexpress CaMKIIδB, which is highly concentrated in cardiomyocyte nuclei, develop hypertrophy and dilated cardiomyopathy.32 To determine whether

  • in vivo expression of the cytoplasmic CaMKIIδC can phosphorylate cytoplasmic Ca(2+) regulatory proteins and
  • induce hypertrophy or heart failure,

we generated transgenic (TG) mice that expressed the δC isoform of CaMKII under the control of the cardiac specific α-myosin heavy chain (MHC) promoter. Our findings implicate CaMKIIδC in the pathogenesis of dilated cardiomyopathy and heart failure and suggest that

  • this occurs at least in part via alterations in Ca(2+) handling proteins.33

Ca(2+) and contraction RyR yuan_image3  Ca++ exchange yuan_image3  Ca++ exchange

Results

 Expression and Activation of CaMKIIδC Isoform After TAC

To determine whether CaMKII was regulated in pressure overload–induced hypertrophy, CaMKIIδ expression and phosphorylation were examined by Western blot analysis using left ventricular samples obtained at various times after TAC.  A selective increase (1.6-fold) in the lower band of CaMKIIδwas observed as early as 1 day and continuously for 4 days (2.3-fold) and 7 days (2-fold) after TAC (Figure 1A).  To confirm that CaMKIIδC was increased and determine whether this occurred at the transcriptional level, we performed semiquantitative RT-PCR using primers specific for the CaMKIIδC isoform. These experiments revealed that

  • mRNA levels for CaMKIIδC were increased 1 to 7 days after TAC (Figure 1B).

In addition to examining CaMKII expression, the activation state of CaMKII was monitored by its autophosphorylation, which confers Ca2-independent activity.

Figure 1. Expression and activation of CaMKII δC isoform after TAC.

see http://dx.doi.org/10.1161/01.RES.0000069686.31472.C5 A, Western blot analysis of total CaMKII in left ventricular (LV) homogenates obtained at indicated times after TAC. Cardiomyocytes transfected with CaMKIIδB and δC (right) served as positive controls and molecular markers. Top band (58 kDa) represents CaMKIIδB plus δ9, and the bottom band (56 kDa) corresponds to CaMKIIδC. *P0.05 vs control. B, Semiquantitative RT-PCR using primers specific for CaMKIIδC isoform (24 cycles) and GAPDH (19 cycles) using total RNA isolated from the same LV samples. C, Western blot analysis of phospho-CaMKII in LV homogenates obtained at various times after TAC. Three bands seen for each sample represent CaMKIIγ subunit (uppermost), CaMKIIδB plus δ9 (58 kDa), and CaMKIIδC (56 kDa). Quantitation is based on the sum of all of the bands. *P0.05 vs control.

 Figure 2. Expression and activation of CaMKII in CaMKIIδC transgenic mice.

see  http://dx.doi.org/10.1161/01.RES.0000069686.31472.C5 A, Transgene copy number based on Southern blots using genomic DNA isolated from mouse tails (digested with EcoRI). Probe (a 32P-labeled 1.7-kb EcoRI-SalI -MHC fragment) was hybridized to a 2.3-kb endogenous fragment (En) and a 3.9-kb transgenic fragment (TG). Transgene copy number was determined from the ratio of the 3.9-kb/2.3-kb multiplied by 2. B, Immunocytochemical staining of ventricular myocytes isolated from WT and CaMKIIδTG mice. Myocytes were cultured on laminin-coated slides overnight. Transgene was detected by indirect immunofluorescence staining using rabbit anti-HA antibody (1:100 dilution) followed by FITC-conjugated goat antirabbit IgG antibody (1:100 dilution). CaMKIIδB localization to the nucleus in CaMKIIδB TG mice (see Reference 32) is shown here for comparative purpose. C, Quantitation of the fold increase in CaMKIIδprotein expression in TGL and TGM lines. Different amounts of ventricular protein (numbers) from WT control, TG () and their littermates () were immunoblotted with an anti-CaMKIIδ antibody. Standard curve from the WT control was used to calculate fold increases in protein expression in TGL and TGM lines. D, Phosphorylated CaMKII in ventricular homogenates was measured by Western blot analysis (n5 for each group). **P0.01 vs WT.

 Generation and Identification of CaMKIIδC Transgenic Mice

TG mice expressing HA-tagged rat wild-type CaMKIIδC under the control of the cardiac-specific α-MHC promoter were generated as described in Materials and Methods. By Southern blot analysis, 3 independent TG founder lines carrying 3, 5, and 15 copies of the transgene were identified. They were designated as TGL (low copy number), TGM (medium copy number), and TGH (high copy number), The founder mice from the TGH line died at 5 weeks of age with marked cardiac enlargement.  The other two lines showed germline transmission of the transgene. The transgene was expressed only in the heart. Although CaMKII protein levels in TGL and TGM hearts were increased 12- and 17-fold over wild-type (WT) controls (Figure 2C), the amount of activated CaMKII was only increased 1.7- and 3-fold in TGL and TGM hearts (Figure 2D). The relatively small increase in CaMKII activity in the TG lines probably reflects the fact that the enzyme is not constitutively activated and that the availability of Ca2/CaM, necessary for activation of the overexpressed CaMKII, is limited. Importantly,

  • the extent of increase in active CaMKII in the TG lines was similar to that elicited by TAC.

 Cardiac Overexpression of CaMKIIδC Induces Cardiac Hypertrophy and Dilated Cardiomyopathy

There was significant enlargement of hearts from CaMKIIδC TGM mice by 8 to 10 weeks [see  http://dx.doi.org/10.1161/01.RES.0000069686.31472.C5%5D  (Figure 3A) and from TGL mice by 12 to 16 weeks. Histological analysis showed ventricular dilation (Figure 3B), cardiomyocyte enlargement (Figure 3C), and mild fibrosis (Figure 3D) in CaMKIIδC TG mice. Quantitative analysis of cardiomyocyte cell volume from 12-week-old TGM mice gave values of 54.7 + 0.1 pL for TGM (n = 96) versus 28.6 + 0.1 pL for WT littermates (n=94; P0.001). Ventricular dilation and cardiac dysfunction developed over time in proportion to the extent of transgene expression. Left ventricular end diastolic diameter (LVEDD) was increased by 35% to 45%, left ventricular posterior wall thickness (LVPW) decreased by 26% to 29% and fractional shortening decreased by 50% to 60% at 8 weeks for TGM and at 16 weeks for TGL. None of these parameters were significantly altered at 4 weeks in TGM or up to 11 weeks in TGL mice, indicating that heart failure had not yet developed.  Contractile function was significantly decreased. Figure 6. Dilated cardiomyopathy and dysfunction in CaMKIIδC TG mice at both whole heart and single cell levels.  [see Fig 6:  http://dx.doi.org/10.1161/01.RES.0000069686.31472.C5] C, Decreased contractile function in ventricular myocytes isolated from 12-week old TGM and WT controls presented as percent change of resting cell length (RCL) stimulated at 0.5 Hz. Representative trace and mean values are shown. *P0.05 vs WT. Figure 7. Phosphorylation of PLB in CaMKIIδC TG mice.  [see Fig 7: http://dx.doi.org/10.1161/01.RES.0000069686.31472.C5] Thr17 and Ser16 phosphorylated PLB was measured by Western blots using specific anti-phospho antibodies. Ventricular homogenates were from 12- to 14-week-old WT and TGM mice (A) or 4 to 5-week-old WT and TGM mice (B). Data were normalized to total PLB examined by Western blots (data not shown here). n = 6 to 8 mice per group; *P0.05 vs WT.

 Cardiac Overexpression of CaMKIIδC Results in Changes in the Phosphorylation of Ca2 Handling Proteins

To assess the possible involvement of phosphorylation of Ca2cycling proteins in the phenotypic changes observed in the CaMKIIC TG mice, we first compared PLB phosphorylation state in homogenates from 12- to 14-week-old TGM and WT littermates. Western blots using antibodies specific for phosphorylated PLB showed a 2.3-fold increase in phosphorylation of Thr17 (the CaMKII site) in hearts from TGM versus WT (Figure 7A). Phosphorylation of PLB at the CaMKII site was also increased 2-fold in 4- to 5-week-old TGM mice (Figure 7B). Significantly, phosphorylation of the PKA site (Ser16) was unchanged in either the older or the younger TGM mice (Figures 7A and 7B). (see  http://dx.doi.org/10.1161/01.RES.0000069686.31472.C5)  To demonstrate that the RyR2 phosphorylation changes observed in the CaMKII transgenic mice are not secondary to development of heart failure, we performed biochemical studies examining RyR2 phosphorylation in 4- to 5-week-old TGM mice. At this age, most mice showed no signs of hypertrophy or heart failure (see Figure 6B) and there was no significant increase in myocyte size (21.3 + 1.3 versus 27.7 + 4.6 pL; P0.14). Also, twitch Ca2 transient amplitude was not yet significantly depressed, and mean δ [Ca2+]i (1 Hz) was only 20% lower (192 + 36 versus 156 + 13 nmol/L; P0.47) versus 50% lower in TGM at 13 weeks.33  The in vivo phosphorylation of RyR2, determined by back phosphorylation, was significantly (2.10.3-fold; P0.05) increased in these 4- to 5-week-old TGM animals (Figure 8C), an increase equivalent to that seen in 12- to 14-week-old mice. We also performed the RyR2 back-phosphorylation assay using purified CaMKII rather than PKA. RyR2 phosphorylation at the CaMKII site was also significantly increased (2.2 + 0.3-fold; P0.05) in 4- to 5-week-old TGM mice (Figure 8C).  (http://dx.doi.org/10.1161/01.RES.0000069686.31472.C5) The association of CaMKII with the RyR2 is consistent with a physical interaction between this protein kinase and its substrate. The catalytic subunit of PKA and the phosphatases PP1 and PP2A were also present in the RyR2 immunoprecipitates, but not different in WT versus TG mouse hearts (Figure 8D). These data provide further evidence that

  • the increase in RyR2 phosphorylation, which precedes development of failure in the 4- to 5-week-old CaMKIIδC TG hearts, can be attributed to the increased activity of CaMKII.

 Discussion

  1. CaMKII is involved in the dynamic modulation of cellular
  2. Ca2 regulation and has been implicated in the development of cardiac hypertrophy and heart failure.14
  3. Published data from CaMK-expressing TG mice demonstrate that forced expression of CaMK can induce cardiac hypertrophy and lead to heart failure.27,32

However, the CaMK genes expressed in these mice are neither the endogenous isoforms of the enzyme nor the isoforms likely to regulate cytoplasmic Ca(2+) handling, because they localize to the nucleus.

  1.  the cytoplasmic cardiac isoform of CaMKII is upregulated at the expression level and is in the active state (based on autophosphorylation) after pressure overload induced by TAC.
  2.  two cytoplasmic CaMKII substrates (PLB and RyR) are phosphorylated in vivo when CaMKII is overexpressed and its activity increased to an extent seen under pathophysiological conditions.
  3. CaMKIIδ is found to associate physically with the RyR in the heart.
  4.  heart failure can result from activation of the cytoplasmic form of CaMKII and this may be due to altered Ca(2+) handling.

 Differential Regulation of CaMKIIδ Isoforms in Cardiac Hypertrophy

  1.  The isoform of CaMKII that predominates in the heart is the δ isoform.4–7 Neither the α nor the β isoforms are expressed and there is only a low level of expression of the γ isoforms.39
  2. Both δB and δC splice variants of CaMKIIδ are present in the adult mammalian myocardium36,40 and expressed in distinct cellular compartments.4,8,9

We suggest that the CaMKIIδ isoforms are differentially regulated in pressure-overload–induced hypertrophy, because the expression of CaMKIIδC is selectively increased as early as 1 day after TAC. Studies using RT-PCR confirm that

  • CaMKIIδC is regulated at the transcriptional level in response to TAC. In addition,
  • activation of both CaMKIIδB and CaMKIIδC, as indexed by autophosphorylation, increases as early as 2 days after TAC.
  • Activation of CaMKIIδB by TAC is relevant to our previous work indicating its role in hypertrophy.9,32
  • The increased expression, as well as activation of the CaMKIIδC isoform, suggests that it could also play a critical role in both the acute and longer responses to pressure overload.

In conclusion, we demonstrate here that CaMKIIδC can phosphorylate RyR2 and PLB when expressed in vivo at levels leading to 2- to 3-fold increases in its activity. Similar increases in CaMKII activity occur with TAC or in heart failure. Data presented in this study and in the accompanying article33 suggest that altered phosphorylation of Ca(2+) cycling proteins is a major component of the observed decrease in contractile function in CaMKIIδC TG mice. The occurrence of increased CaMKII activity after TAC, and of RyR and PLB phosphorylation in the CaMKIIδC TG mice suggest that

  • CaMKIIδC plays an important role in the pathogenesis of dilated cardiomyopathy and heart failure.

These results have major implications for considering CaMKII and its isoforms in exploring new treatment strategies for heart failure.

Cardiac Electrophysiological Dynamics From the Cellular Level to the Organ Level

Daisuke Sato and Colleen E. Clancy Department of Pharmacology, University of California – Davis, Davis, CA. Biomedical Engineering and Computational Biology 2013:5: 69–75 http://www.la-press.com.   http://dx.doi.org/10.4137/BECB.S10960 Abstract: Cardiac alternans describes contraction of the ventricles in a strong-weak-strong-weak sequence at a constant pacing fre­quency. Clinically, alternans manifests as alternation of the T-wave on the ECG and predisposes individuals to arrhythmia and sudden cardiac death. In this review, we focus on the fundamental dynamical mechanisms of alternans and show how alternans at the cellular level underlies alternans in the tissue and on the ECG. A clear picture of dynamical mechanisms underlying alternans is important to allow development of effective anti-arrhythmic strategies. The cardiac action potential is the single cellular level electrical signal that triggers contraction of the heart.1 Under normal conditions, the originating activation signal comes from a small bundle of tissue in the right atrium called the sinoatrial node (SAN). The action potentials generated by the SAN initiate an excitatory wave that, in healthy tissue, propagates smoothly through a well-defined path and causes excitation and contraction in the ventricles. In disease states, the normal excitation pathway is disrupted and a variety of abnormal rhythms can occur, including cardiac alternans, a well-known precursor to sudden cardiac death. Cardiac alternans was initially documented in 1872 by a German physician, Ludwig Traube.2 He observed contraction of the ventricles in a strong-weak-strong-weak sequence even though the pacing frequency was constant. Clinically, alternans mani­fests as alternation of the T-wave on the ECG, typi­cally in the microvolt range. It is well established that individuals with microvolt T-wave alternans are at much higher risk for arrhythmia and sudden cardiac death. A clear picture of physio­logical mechanisms underlying alternans is important to allow development of effective anti-arrhythmic drugs. It is also important to understand dynamical mechanisms because while the cardiac action poten­tial is composed of multiple currents, each of which confers specific properties, revelation of dynamical mechanisms provides a unified fundamental view of the emergent phenomena that holds independently of specific current interactions. The ventricular myocyte is an excitable cell pro­viding the cellular level electrical activity that under­lies cardiac contraction. Under resting conditions, the membrane potential is about -80 mV. When the cell is stimulated, sodium (Na) channels open and the membrane potential goes above 0 mV. Then, a few ms later, the inward current L-type calcium (Ca) current activates and maintains depolarization of the mem­brane potential. During this action potential plateau, several types of outward current potassium (K) chan­nels also activate. Depending on the balance between inward and outward currents, the action potential duration (APD) is determined.The diastolic interval (DI) that follows cellular repolarization describes the duration the cell resides in the resting state until the next excitation. During the DI, channels recover with kinetics determined by intrinsic time constants. APD restitution defines the relationship between the APD and the previous DI (Fig. 1 top panel). In most cases1, the APD becomes longer as the previous DI becomes longer due to recovery of the L-type Ca channel (Fig. 1, bottom panel), and thus the APD restitution curve has a positive slope. Figure 1. (Top): APD and DI. (Bottom): The physiological mechanism of APD alternans involves recovery from inactivation of ICaL.  [see  http://dx.doi.org/10.4137/BECB.S10960]

 Action Potential Duration Restitution

In 1968 Nolasco and Dahlen showed graphically that APD alternans occurs when the slope of the APD res­titution curve exceeds unity. Why is the steepness of the slope important? As shown graphically in Figure 2, APD alternans amplitude is multiplied by the slope of the APD restitution curve in each cycle. When the slope is larger than one, then the alternans amplitude will be amplified until the average slope reaches 1 or the cell shows a 2:1 stimulus to response ratio.  The one-dimensional mapping between APD and DI fails to explain quasi-periodic oscillation of the APD. Figure 2. APD restitution and dynamical mechanism of APD alternans.   [see  http://dx.doi.org/10.4137/BECB.S10960]

Calcium Driven Alternans

A strong-weak-strong-weak oscillation in contrac­tion implies that the Ca transient (CaT) is alternating. Until 1999 it was assumed that if the APD is alternat­ing then the CaT alternates because the CaT follows APD changes. However, Chudin et al showed that CaT can alternate even when APD is kept constant during pacing with a periodic AP clamp waveform.14 This implies that the intracellular Ca cycling has intrinsic nonlinear dynamics. A critical component in this process is the sarcoplasmic reticulum (SR), a subcellular organelle that stores Ca inside the cell. When Ca enters a cell through the L-type Ca channel (or reverse mode Na-Ca exchanger (NCX) ryanodine receptors open and large Ca releases occur from the SR (Ca induced Ca release). The amount of Ca release steeply depends on SR Ca load. This steep relation between Ca release and SR Ca load is the key to induce CaT alternans.  A one-dimensional map between Ca release and SR calcium load can be constructed to describe the relationship21 similar to the map used in APD restitution.

 Subcellular Alternans

A number of experimental and computational stud­ies have been undertaken to identify molecular mechanisms of CaT alternans by identifying the specific components in the calcium cycling process critical to formation of CaT alternans. These compo­nents include SR Ca leak and load, Ca spark frequency and amplitude, and rate of SR refilling. For example, experiments have shown that alternation in diastolic SR Ca is not required for CaT alternans.24 In addition, stochastic openings of ryanodine receptors (RyR) lead to Ca sparks that occur randomly, not in an alternating sequence that would be expected to underlie Ca altern-ans. So, how do local random sparks and constant dia­stolic SR calcium load lead to global CaT alternans? Mathematical models with detailed representations of subcellular Ca cycling have been developed in order to elucidate the underlying mechanisms. Model­ing studies have shown that even when SR Ca load is not changing, RyRs, which are analogous to ICaL in APD alternans, recover gradually from refractoriness. As RyR availability increases (for example during a long diastolic interval) a single Ca spark from a RyR will be larger in amplitude and recruit neighboring Ca release units to generate more sparks. The large resultant CaT causes depletion of the SR and when complete recovery of RyRs does not occur prior to the arrival of the next stimulus, the subsequent CaT will be small. This process results in an alternans of CaT amplitude from beat-to-beat.

 Coupling Between the Membrane Potential and Subcellular Calcium Dynamics

Importantly, the membrane voltage and intracellu­lar Ca cycling are coupled via Ca sensitive channels such as the L-type Ca channel and the sodium-calcium exchanger (NCX). The membrane voltage dynamics and the intracellular Ca dynamics are bi-directionally coupled. One direction is from voltage to Ca. As the DI becomes longer, the CaT usually becomes larger since the recovery time for the L-type Ca channel in increased and the SR Ca release becomes larger. The other direction is from Ca to voltage. Here we consider two major currents, NCX and ICaL. As the CaT becomes larger, forward mode NCX becomes larger and pro­longs APD. On the other hand, as the CaT becomes larger, ICaL becomes smaller due to Ca-induced inacti­vation, and thus, larger CaT shortens the APD. There­fore, depending on which current dominates, larger CaT can prolong or shorten APD. If a larger CaT pro­longs (shortens) the APD, then the coupling is positive (negative). The coupled dynamics of the membrane voltage and the intracellular Ca cycling can be cate­gorized by the instability of membrane voltage (steep APD restitution), instability of the intracellular Ca cycling (steep relation between Ca release versus SR Ca load), and the coupling (positive or negative). If the coupling is positive, alternans is electromechani­cally concordant (long-short-long-short APD cor­responds to large-small-large-small CaT sequence) regardless of the underlying instability mechanism. On the other hand, if the coupling is negative, alternans is electromechanically concordant in a voltage-driven regime. However, if alternans is Ca driven, alternans becomes electromechanically discordant (long-short-long-short APD corresponds to small-large-small-large CaT sequence). It is also possible to induce quasi- periodic oscillation of APD and CaT when volt­age and Ca instabilities contribute equally.

 Alternans in Higher Dimensions

Tissue level alternans in APD and CaT also occur and here we describe how the dynamical mechanism of alternans at the single cell level determines the phenomena in tissue. Spatially discordant alternans (SDA) where APDs in different regions of tissue alternate out-of-phase, is more arrhythmogenic since it causes large gradients of refractoriness and wave-break, which can initiate ventricular tachycardia and ventricular fibrillation. How is SDA induced? As the APD is a function of the previous DI, con­duction velocity (CV) is also function of the previ­ous DI (CV restitution) since the action potential propagation speed depends on the availability of the sodium channel. As the DI becomes shorter, sodium channels have less time to recover. Therefore, in general, as the DI becomes shorter, the CV becomes slower. When tissue is paced rapidly, action poten­tials propagate slowly near the stimulus, and thenac-celerate downstream as the DI becomes longer. This causes heterogeneity in APD (APD is shorter near the stimulus). During the following tissue excitation, APD becomes longer and the CV becomes faster at the pacing site then gradually APD becomes shorter and the CV becomes slower. The interaction between steep APD restitution and steep CV restitution creates SDA. This mechanism applies only when the cel­lular instability is voltage driven. When the cellular instability is Ca driven, the mechanism of SDA formation is different. If the volt­age-Ca coupling is negative, SDA can form without steep APD and CV restitution. The mechanism can be understood as follows. First, when cells are uncou­pled, alternans of APD and Ca are electromechanically discordant. If two cells are alternating in opposite phases, once these cells are coupled by voltage, due to electrotonic coupling, the membrane voltage of both cells is synchronized and thus APD becomes the same. This synchronization of APD amplifies the difference of CaT between two cells (Fig. 5 in). In other words it desynchronizes CaT. This instability mechanism is also found in subcellular SDA. In the case where the instability is Ca driven and the coupling is positive, there are several interest­ing distinctive phenomena that can occur. First, the profile of SDA of Ca contains a much steeper gra­dient at the node (point in space where no alternans occurs–cells downstream of the node are alternating out of phase with those upstream of the node) com­pared to the case of voltage driven SDA. Thus, the cellular mechanism of instability can be identified by evaluating the steepness of the alternans amplitude gradient in space around the node. When the cellular instability is voltage driven, the steady-state wave­length (separation of nodes in space) depends on electrotonic coupling between cells and the steepness of APD and CV restitution, regardless of the initial conditions. However, if the cellular instability is Ca driven, the location of nodes depends on the pacing history, which includes pacing cycle length and other parameters affected by pacing frequency. In this case, once the node is formed, the location of the node may be fixed, especially when Ca instability is strong. Such an explanation may apply to recent experimen­tal results. Summary In this review, we described how the origin of alternans at the cellular level (voltage driven, Ca drive, coupling between voltage and Ca) affects the formation of spatially discordant alternans at the tissue level. Cardiac alternans is a multi-scale emergent phenomenon. Channel properties determine the instability mechanism at the cellular level. Alternans mechanisms at cellular level determine SDA patterns at the tissue level. In order to understand alternans and develop anti-arrhythmic drug and therapy, multi-scale modeling of the heart is useful, which is increasingly enabled by emerging technologies such as general-purpose computing on graphics processing units (GPGPU) and cloud computing.

English: Diagram of contraction of smooth musc...

English: Diagram of contraction of smooth muscle fiber (Photo credit: Wikipedia)

Schematic representation of Calcium Cycling in Contractile and Proliferating VSMCs receptors voltage gated Ca(2) channel Marks-Wehrens Model and multiphosphorylation  site model ncpcardio0419-f4   calcium leak

Read Full Post »

Leaving Hospital Against Medical Advice (AMA): Higher Rates of Hospital Readmission and Death


Reporter: Aviva Lev-Ari, PhD, RN


Rates of readmission and death associated with leaving hospital against medical advice: a population-based study

CMAJ August 26, 2013 First published August 26, 2013, doi:10.1503/cmaj.130029

  1. Allan Garland,
  2. Clare D. Ramsey,
  3. Randy Fransoo,
  4. Kendiss Olafson,
  5. Daniel Chateau,
  6. Marina Yogendran,
  7. Allen Kraut

+Author Affiliations


  1. Department of Internal Medicine (Garland, Ramsey, Olafson, Kraut), Department of Community Health Sciences (Garland, Ramsey, Fransoo, Chateau, Kraut), Manitoba Center for Health Policy (Garland, Fransoo, Chateau, Yogendran), University of Manitoba, Winnipeg, Man.
  1. Allan Garland, E-mail agarland@hsc.mb.ca

Abstract

Background: Leaving hospital against medical advice may have adverse consequences. Previous studies have been limited by evaluating specific types of patients, small sample sizes and incomplete determination of outcomes. We hypothesized that leaving hospital against medical advice would be associated with increases in subsequent readmission and death.

Methods: In a population-based analysis involving all adults admitted to hospital and discharged alive in Manitoba from Apr. 1, 1990, to Feb. 28, 2009, we evaluated all-cause 90-day mortality and 30-day hospital readmission. We used multivariable regression, adjusted for age, sex, socioeconomic status, year of hospital admission, patient comorbidities, hospital diagnosis, past frequency of admission to hospital, having previously left hospital against medical advice and data clustering (patients with multiple admissions). For readmission, we assessed both between-person and within-person effects of leaving hospital against medical advice.

Results: Leaving against medical advice occurred in 21 417 of 1 916 104 index hospital admissions (1.1%), and was associated with higher adjusted rates of 90-day mortality (odds ratio [OR] 2.51, 95% confidence interval [CI] 2.18-2.89), and 30-day hospital readmission (within-person OR 2.10, CI 1.99-2.21; between-person OR 3.04, CI 2.79-3.30). In our additional analyses, elevated rates of readmission and death associated with leaving against medical advice were manifest within 1 week and persisted for at least 180 days after discharge.

Interpretation: Adults who left the hospital against medical advice had higher rates of hospital readmission and death. The persistence of these effects suggests that they are not solely a result of incomplete treatment of acute illness. Interventions aimed at reducing these effects may need to include longitudinal interventions extending beyond admission to hospital.

http://www.cmaj.ca/content/early/2013/08/26/cmaj.130029

Published: Aug 26, 2013 | Updated: Aug 26, 2013

By Chris Kaiser, Cardiology Editor, MedPage Today
Reviewed by Zalman S. Agus, MD; Emeritus Professor, Perelman School of Medicine at the University of Pennsylvania and Dorothy Caputo, MA, BSN, RN, Nurse Planner

Action Points

  • Adults who left the hospital against medical advice had higher rates of hospital readmission and death.
  • Note that the increased risk persisted for at least 180 days after discharge suggesting that they are not solely a result of incomplete treatment of acute illness.

In one of the largest and most comprehensive studies of its kind, researchers found that leaving the hospital against medical advice more than doubled the risk of mortality and rehospitalization, a risk that persisted out to 6 months.

Out of nearly 2 million index hospital admissions, the 1.1% of patients who left before being officially discharged were two-and-a-half times more likely to die within 90 days (OR 2.51), according toAllan Garland, MD, co-head of the section of critical care medicine at the University of Manitoba in Winnipeg, and colleagues.

Patients who left against medical advice also had three times the rate of readmissions in the month following their departure (OR 3.04), the researchers reported online in the Canadian Medical Association Journal.

The risk of readmission appears to be strongest early on, as one-quarter of rehospitalizations occurred within 1 day of leaving against the doctor’s orders and 75% occurred within 2 weeks.

“For both hospital readmission and death, the elevated rates among patients who left against medical advice started out high and then declined, but remained significantly elevated to at least 180 days,” wrote the authors.

One of the obvious reasons for early adverse events is incomplete treatment of the index acute illness. “But because the risk persisted out to 6 months, there are likely other factors involved,” Garland told MedPage Today in an interview.

One hypothesis is that these patients as a group are less compliant with medical advice or medication orders in the outpatient setting, he said.

“Even if we identify those at risk of leaving the hospital against medical advice and perform an intervention to keep them in the hospital, we might still need to address longer-term risk factors based on potential unhealthy outpatient behaviors,” Garland said.

This is all speculative at this point, he pointed out, but noted they are planning two additional phases of the study. These will evaluate why people leave against medical advice and then quantify personal characteristics and health habits that contribute to a general failure to adhere to physician advice.

“We already know that the strongest predictor for people leaving against medical advice is having done so in the past,” Garland said. “You might call them ‘frequent flyers,’ and an intervention at the hospital probably isn’t enough. We will probably need longitudinal interventions as well that address health habits.”

In related work yet unpublished, Garland’s group identified several index diagnoses that are associated with patients leaving the hospital against advice. These include substance abuse, overdose, tuberculosis, and diabetic ketoacidosis — findings that confirm similar smaller studies.

Patients less likely to leave against medical advice included those having major surgery and those admitted with a cancer diagnosis — unique findings because these patient populations are typically excluded from such studies, Garland said.

Most of the studies examining this topic have been small, or from single hospitals, or aimed at specific types of patients. In contrast, the current study looked at 1,916,104 adult admissions and live discharges over 19 years (1990–2009) in Manitoba with more than 21,000 incidents of patients leaving against medical advice (the most for one patient was 39 times).

The mean age of patients who left prematurely was 42, and 54 for those who stayed. Men were more likely than women to leave against medical advice, as were younger patients and those with certain chronic conditions such as hypertension and diabetes.

“It’s rare that patients want to leave against medical advice, but when they do, healthcare professionals should explain the risk to them,” Garland said. “They can point to our paper — which demonstrated in a rigorous and broad way — that what they’re about to do is known to be harmful.”

A limitation of the study is the potential for misclassified discharge information. Also, the authors had no data on the severity of the acute illness, nor did they know if readmissions or deaths were for the same reason as the index admission. Finally, results may not be applicable to regions that do not have publicly funded universal health coverage.

Although those with a lower income were more likely to leave the hospital against medical advice, it was not due to the potential burden of medical bills because Canada has universal health coverage.

Garland pointed to anecdotal evidence that suggests this group of patients feels outside financial pressure to resume work as soon as possible — an area that could be addressed during an inpatient intervention.

http://www.medpagetoday.com/TheGuptaGuide/PublicHealth/41182?xid=nl_mpt_guptaguide_2013-08-26&utm_source=guptaguide&utm_medium=email&utm_content=mpt&utm_campaign=08%7C26%7C2013&userid=99985&eun=g5099207d10r&email=avivalev-ari@alum.berkeley.edu&mu_id=5099207

Read Full Post »

Reporter and Curator: Dr. Sudipta Saha, Ph.D.

Conventional tumor markers are unsuitable for detecting carcinoma at an early stage and lack clinical efficacy and utility. Multiple classification analysis revealed that the variations in the levels of malonic acid and L-serine largely contributed to the separation of esophageal cancer; gastric cancer was characterized by changes in the levels of 3-hydroxypropionic acid and pyruvic acid; and L-alanine, glucuronoic lactone and L-glutamine contributed to the separation of colorectal cancer. Some metabolites are more sensitive for detecting gastrointestinal cancer than conventional biomarkers and thus metabolomics has the potential as an early diagnostic tool for cancer. Studies also showed that global metabolic profiling of colon mucosae would define metabolic signatures that not only discriminate malignant from normal mucosae, but also could distinguish the anatomical and clinicopathological characteristics of colorectal cancer. Thus it is suggested that metabolic profiling of colorectal cancer mucosae could provide new phenotypic biomarkers for colorectal cancer management.

A full spectrum of metabolic aberrations that are directly linked to colorectal cancer at early curable stages is critical for developing and deploying molecular diagnostic and therapeutic approaches that will significantly improve patient survival. A number of dysregulated metabolic pathways, such as glycolysis, tricarboxylic acid cycle, urea cycle, pyrimidine metabolism, tryptophan metabolism, polyamine metabolism, as well as gut microbial-host co-metabolism in colorectal cancer subjects are reported. Significantly increased tryptophan metabolism, and disturbed tricarboxylic acid cycle and the gut microflora metabolism were observed in the colorectal cancer patients. The urinary metabolite profile of postoperative colorectal cancer subjects altered significantly from that of the preoperative stage. The significantly down-regulated gut microflora metabolism and tricarboxylic acid cycle were observed in postoperative colorectal cancer subjects, presumably due to the colon flush involved in the surgical procedure and weakened physical conditions of the patients. The expression of 5-hydroxytryptophan significantly decreased in postsurgery cases, suggesting a recovered tryptophan metabolism toward healthy state. Abnormal histamine metabolism and glutamate metabolism were found only in the urine samples of colorectal cancer patients. There are distinct urinary metabolic footprints of colorectal cancer patients characterized by altered levels of metabolites derived from gut microbial-host co-metabolism. A panel of metabolite markers composed of citrate, hippurate, p-cresol, 2-aminobutyrate, myristate, putrescine, and kynurenate was able to discriminate colorectal cancer subjects from their healthy counterparts. These potential metabolite markers provide a novel and promising molecular diagnostic approach for the early detection of colorectal cancer.

Source References:

http://www.ncbi.nlm.nih.gov/pubmed/21773981

http://www.ncbi.nlm.nih.gov/pubmed/22792336

http://www.ncbi.nlm.nih.gov/pubmed/19063642

http://www.ncbi.nlm.nih.gov/pubmed/20121166

http://www.ncbi.nlm.nih.gov/pubmed/22148915

Read Full Post »

Reporter and Curator: Dr. Sudipta Saha, Ph.D.

The metabolite pool of cells and tissues represents the end result of metabolism determined by genetic, environmental and nutritional factors. The metabolic profile of biological systems is closely related to the individual phenotype and reflects the biological endpoint of a multitude of pathways and their interaction with any confounding stimuli. Cancer cells exhibit activation of specific metabolic pathways to compensate for their extremely high energy demands. Indeed increased glucose uptake and lactate production and decreased respiration are key phenomena of tumour cell metabolism. In particular, the generation of an acidic microenvironment through increased lactate production, even under aerobic conditions, may confer extracellular matrix degeneration and exert toxic effects on surrounding cell populations, while being harmless for the cancer cell itself. Thus, the metabolic adaptations may indeed be critical for the development of accelerated proliferation and the invasive growth of tumour cell populations. The molecular mechanisms underlying the metabolic hallmarks of cancer are still poorly understood, although genetic, epigenetic and environmental factors driving cancer development and progression will interact to determine the metabolic phenotype of tumour cells. Recent studies suggest that metabolic changes play a pivotal role in the biology of renal cell carcinoma – a tumour entity that is largely resistant to conventional chemo- and radiotherapy. The metabolic profile of renal tumours may thus serve as a reliable biomarker of malignant transformation and biological behaviour.

Recent advances in metabolic profiling technologies by providing quantitative measures of metabolite profiles from gas chromatography time-of-flight mass spectrometry (GC-TOF-MS) based technology present the opportunity to apply this technique in human specimens. Global metabolic profiling has emerged as a promising approach to characterize the metabolite pool within a cell, tissue or bodily fluid under certain conditions, such as health or disease status. Metabolic profiling is applied to monitor the health to disease continuum and has the potential of increasing our understanding of the mechanisms of disease. Thus the characterization of the metabolic features in tumours is expected to provide a better understanding of the mechanisms of malignant transformation and progression and may lead to the identification of metabolic biomarkers for cancer detection and prognostication. However, comparative profiling of low molecular weight compounds, such as sugars, lipids and amino acids, in cancer as compared to the corresponding normal tissue is a rather unexplored area. The objective of this study was to characterize the key metabolic features of renal cell carcinoma using GC-TOF-MS and mutual information as well as decision tree-based data analysis.

Hypoxia is key in tumour cell behaviour. Hypoxia, via hypoxia inducible factor, plays a key role in the metabolic changes in the kidney cancer cell and influences different pathways. Pathways that use tyrosine kinases and mammalian target of rapamycin are well studied. Hypoxia-related effects on vascular epithelial growth factors and angiogenesis will influence the metabolic status of the cell significantly. This is the basis of inhibitor-type drugs or antibody blocking agents and the effect on the clinical course of renal cell carcinoma patients. Detailed information about metabolic changes is crucial to understanding these mechanisms more clearly. Treating renal cell carcinoma patients is not like treating one disease. Renal cell carcinoma has different morphologic entities with distinct differences in cytogenetic background. These differences should be reflected in the different approaches of diagnostic and therapeutic strategies. This consideration will help to increase the efficacy of novel agents and decrease unnecessary side-effects. Metabolomics explains the importance of explaining genetic changes and the functional outcome of the tumour cells. In addition, epidemiologic differences in incidence and prevalence in different parts of the world may help provide insight into the etiology of kidney cancer. Factors that may influence renal cancer likelihood (eg, obesity, antihypertensive therapy) may have an explanation in metabolomics.

Source References:

http://www.europeanurology.com/article/S0302-2838(12)01352-8/fulltext

http://www.ncbi.nlm.nih.gov/pubmed/19845817

http://www.ncbi.nlm.nih.gov/pubmed/18072195

http://www.ncbi.nlm.nih.gov/pubmed/17123452

http://www.ncbi.nlm.nih.gov/pubmed/20464042

http://www.ncbi.nlm.nih.gov/pubmed/21930086

https://www.google.com.tw/url?sa=t&rct=j&q=&esrc=s&source=web&cd=8&cad=rja&ved=0CGwQFjAH&url=http%3A%2F%2Fjournals.sfu.ca%2Fcuaj%2Findex.php%2Fjournal%2Farticle%2Fdownload%2F665%2F466&ei=-ub8UbD0JcfolAXeyYGYBw&usg=AFQjCNFIzdti065pBEGKlEDkBDCPA4IwUw&sig2=scgq8qT9ffKa65MxAvpuNg&bvm=bv.50165853,d.dGI

Read Full Post »

The Role of the Harp and of Music in Medical Recovery

Curator: Aviva Lev-Ari, PhD, RN


Tchaikovsky Flashwaltz at Hadassah Hospital in Jerusalem 

UNEXPECTED CONCERT IN A HOSPITAL IN JERUSALEM – @Hadassah Hospital’s Lobby

 http://safeshare.tv/w/OXHZUxUXXN

More harp music

The Fountain — Marcel Lucien Grandjany – YouTube

http://m.youtube.com/watch?v=S1-LCnGojnw

This article is WORK-in-PROGRESS


Picture below features the Curator with Salvi’s Iris Model in Gold, Cable TV, Palo Alto, CA, 11/19/1989

Aviva with the Harp

Read Full Post »

Reporter and Curator: Dr. Sudipta Saha, Ph.D.

The prostate has long been known to exhibit unique metabolite profiles. In the last decade, advances in nuclear magnetic resonance spectroscopy and mass spectrometry have been applied toward identifying metabolic alterations in prostate cancer that may provide clinically useful biomarkers. As with genomics and proteomics, advances in technology and bioinformatics have led to the application of metabolomic profiling to prostate cancer—the high throughput evaluation of a large complement of metabolites in the prostate and how they are altered by disease perturbations. Recently, high profile publications have drawn attention to the potential of metabolomic analysis to identify biomarkers for early detection or disease progression from readily accessible body fluids as well as tissue specimens from biopsy and surgery.

Worldwide, the number of prostate cancer cases is approaching one million, and it is the sixth leading cause of cancer deaths in men. Both incidence and mortality are increasing in many traditionally low risk countries in Asia, and Central and Eastern Europe. Testing with serum prostate specific antigen has contributed to decreases in prostate cancer mortality in many developed countries, but the test and the diagnostic paradigm suffer from a number of problems, including low specificity of prostate specific antigen, inability to specify a cut-point below which cancer is unlikely, non-trivial false-negative rate for prostate biopsy, and over-diagnosis and over-treatment of relatively indolent tumors with low potential for morbidity or death if left untreated. For men diagnosed with prostate cancer, a number of algorithms primarily based on tumor pathology and prostate specific antigen are available to predict the likely clinical outcome. Although these prediction tools generally work well, there is still significant variability in outcomes for men at both the low and high end of the risk spectrum. Although distinct metabolic characteristics of the prostate have long been known, global metabolomic profiling of prostate cancer is at an early stage.

Studies of the metabolic alterations associated with prostate cancer have demonstrated characteristic decreases in citrate and polyamines, and increases in cholines, glycerophospholipids, lactate, and components of a number of pathways of amino acid metabolism. Results for sarcosine have been prominent but inconsistent. However, it is likely that inconsistent findings are not unique to sarcosine. Rather, the attention given to sarcosine has resulted in reports of validation efforts focused on this molecule, whereas reports from other metabolomic profiling studies have focused on discovery and have not emphasized null associations. Metabolite profiles with potential relevance to prostate cancer biology have been identified in tissue, bone, urine, expressed prostatic fluid, and plasma, and have correlated with clinical progression as well as established prognostic attributes. Given the relatively low cost of metabolomic profiling compared with the other ‘omics’ disciplines, and the parallel advances being made in molecular magnetic resonance imaging, metabolomics has great potential for application to detection of clinically significant disease and monitoring disease progression, in both the active surveillance and post-treatment settings. In addition, because of their functional significance, metabolomic biomarkers or profiles hold particular promise for addressing one of the current challenges to personalized medicine: co-development of targeted therapeutics and companion diagnostics.

Source References:

http://www.ncbi.nlm.nih.gov/pubmed/21930089

http://people.ucalgary.ca/~adeleon/paper_prostate.pdf

http://www.ctsi.ufl.edu/wp-content/uploads/2012/06/DeFeo-2011-A-decade-in-prostate.pdf

http://www.fasebj.org/cgi/content/meeting_abstract/21/6/A768-c

http://onlinelibrary.wiley.com/doi/10.1002/pros.22704/abstract

http://dept.stat.lsa.umich.edu/~gmichail/journal.pone.0021417.pdf

Read Full Post »

« Newer Posts - Older Posts »