Feeds:
Posts
Comments

Archive for the ‘Peripheral Arterial Disease & Peripheral Vascular Surgery’ Category

Carotid Endarterectomy (CEA) vs. Carotid Artery Stenting (CAS): Comparison of CMMS high-risk criteria on the Outcomes after Surgery:  Analysis of the Society for Vascular Surgery (SVS) Vascular Registry Data

Writer and Curator: Larry H. Bernstein, MD, FCAP

and

Curator: Aviva Lev-Ari, PhD, RN 

UPDATED on 1/30/2024

The Texas Heart Institute

WATCH Video

https://youtu.be/KobPZLWmLfQ?si=LUxy1gD9fCptj1E7

This week on Inside the Studio, both Dr. Joseph Rogers and Dr. Zvonimir Krajcer sit down with the 2024 Ray C. Fish Award Recipient Dr. Gary S. Roubin to discuss “Carotid Stenting: State of the Art.” Don’t miss out on our upcoming live talks, or catch up on previous recordings at https://www.texasheart.org/grandrounds.

Show the Transcript

UPDATED on 9/25/2021

1-Year Results From a Prospective Experience on CAS Using the CGuard Stent System: The IRONGUARD 2 Study

Peripheral

J Am Coll Cardiol Intv. , 14 (17) 1917–1923

Abstract

Objectives

The aim of this study was to evaluate the 1-year safety and efficacy of a dual-layered stent (DLS) for carotid artery stenting (CAS) in a multicenter registry.

Background

DLS have been proved to be safe and efficient during short-term follow-up. Recent data have raised the concern that the benefit of CAS performed with using a DLS may be hampered by a higher restenosis rate at 1 year.

Methods

From January 2017 to June 2019, a physician-initiated, prospective, multispecialty registry enrolled 733 consecutive patients undergoing CAS using the CGuard embolic prevention system at 20 centers. The primary endpoint was the occurrence of death and stroke at 1 year. Secondary endpoints were 1-year rates of transient ischemic attack, acute myocardial infarction, internal carotid artery (ICA) restenosis, in-stent thrombosis, and external carotid artery occlusion.

Results

At 1 year, follow-up was available in 726 patients (99.04%). Beyond 30 days postprocedure, 1 minor stroke (0.13%), four transient ischemic attacks (0.55%), 2 fatal acute myocardial infarctions (0.27%), and 6 noncardiac deaths (1.10%) occurred. On duplex ultrasound examination, ICA restenosis was found in 6 patients (0.82%): 2 total occlusions and 4 in-stent restenoses. No predictors of target ICA restenosis and/or occlusion could be detected, and dual-antiplatelet therapy duration (90 days vs 30 days) was not found to be related to major adverse cardiovascular event or restenosis occurrence.

Conclusions

This real-world registry suggests that DLS use in clinical practice is safe and associated with minimal occurrence of adverse neurologic events up to 12-month follow-up.

SOURCE

UPDATED on 8/5/2020

USPSTF advises against carotid artery stenosis screening

By Theresa Pablos, AuntMinnie staff writer

August 5, 2020 — The U.S. Preventive Services Task Force (USPSTF) is poised to once again recommend against screening for asymptomatic carotid artery stenosis. The task force reaffirmed its D rating in a draft recommendation statement published on August 4.

The USPSTF last weighed in on the topic in 2014, concluding with moderate certainty that the harms of screening for carotid artery stenosis in the general population outweighed the benefits. In its new draft recommendation statement, the agency reaffirmed that position, stating there was not enough new evidence to change its previous recommendation against screening with either carotid duplex ultrasound, CT angiography, or MR angiography.

“The USPSTF found no new substantial evidence that could change its recommendation and therefore reaffirms its recommendation,” the task force wrote.

In theory, screening the general population for stenosis could lead to early detection of narrowed blood vessels, thus enabling medical professionals to conduct potentially life-saving interventions, such as carotid endarterectomy (CEA) and carotid artery stenting (CAS). But the USPSTF concluded that the evidence it reviewed didn’t readily support that hypothesis.

The task force has consistently found limited evidence in favor of asymptomatic carotid artery stenosis screening, especially when compared with other medical therapies, such as statins and antihypertensive agents. And the evidence has been particularly lacking since the USPSTF’s last review in 2014.

USPSTF draft recommendation rationale for asymptomatic carotid artery stenosis
Detection Ultrasonography has reasonable sensitivity and specificity for detecting clinically relevant carotid artery stenosis, but it also yields many false-positive results in the general population.
Scanning the neck for carotid bruits has poor accuracy for clinically relevant carotid artery stenosis.
Benefits Direct evidence does not indicate that screening for asymptomatic carotid artery stenosis can improve stroke, mortality, or other adverse health outcomes.
Carotid endarterectomy (CEA) or carotid artery angioplasty and stenting (CAS) provides little or no benefit for improving stroke, myocardial infarction, mortality, or other adverse outcomes compared with current medical therapy.
Harms While direct evidence does not show that screening for asymptomatic carotid artery stenosis can cause harm, there are known harms with confirmatory testing and interventions.
Direct evidence supports that treating asymptomatic patients with CEA or CAS could cause harms, including stroke or death.
Harms related to screening and treating asymptomatic carotid artery stenosis have small-to-moderate magnitude.

After searching the scientific literature, USPSTF investigators found no recent eligible studies that directly investigated the benefits or harms of asymptomatic carotid artery stenosis screening. The two studies that were conducted on the topic in the past six years were both prematurely terminated and produced mixed results.

When looking at the benefits and harms of CEA or CAS, the authors found an additional two national datasets and three surgical registries that met their inclusion criteria. Rates of 30-day postoperative stroke or death after CEA ranged from 1.4% to 3.5% depending on the registry or database. Similarly, 30-day stroke or death after CAS ranged from 2.6% to 5.1%.

Based on the evidence — or lack thereof — the investigators concluded there wasn’t enough new information to change the D rating for asymptomatic carotid artery stenosis screening. However, they pointed out that two clinical trials are currently underway, which may shed light on the topic in the future.

“There were few new trials, all with methodologic concerns, examining the important question of the comparative effectiveness and harms of revascularization plus best medical treatment compared with best medical treatment alone,” they wrote. “The ongoing CREST-2 and ECST-2 trials will be the largest trials to address this issue.”

The draft recommendation is available for public comment through August 31. After the comment period has ended, the task force will publish its final recommendation.

USPSTF opens review of carotid stenosis screening
The U.S. Preventive Services Task Force (USPSTF) has posted a draft research plan on screening for asymptomatic carotid artery stenosis, an exam that…
USPSTF still against US carotid artery stenosis screening
The U.S. Preventive Services Task Force (USPSTF) has finalized its draft recommendation advising against the use of widespread ultrasound screening for…
USPSTF advises against carotid artery screening
The U.S. Preventive Services Task Force (USPSTF) has issued a draft recommendation against ultrasound screening for asymptomatic carotid artery stenosis…
USPSTF to revisit carotid artery stenosis screening
The U.S. Preventive Services Task Force (USPSTF) plans to review its guidelines on the use of imaging to screen patients for asymptomatic carotid artery…

SOURCE

https://www.auntminnie.com/index.aspx?sec=sup&sub=ult&pag=dis&ItemID=129787

UPDATED on 8/20/2018

Transcarotid Artery Revascularization Shows Favorable Outcomes in Patients With Carotid Artery Disease

First large body of real-world clinical evidence showing benefits of TCAR versus surgery presented at SVS 2018 Annual Meeting

Transcarotid Artery Revascularization Shows Favorable Outcomes in Patients With Carotid Artery Disease

July 30, 2018 — Silk Road Medical Inc. recently announced the presentation of real-world data for the treatment of patients with carotid artery disease at risk for stroke at the Society for Vascular Surgery 2018 Vascular Annual Meeting (VAM), June 20-23 in Boston. In a headline presentation, Marc Schermerhorn, M.D., of Beth Israel Deaconess Medical Center (Boston) shared, for the first time, results from the ongoing TransCarotid Artery Revascularization (TCAR) Surveillance Project, a key initiative of the Society for Vascular Surgery’s Vascular Quality Initiative (VQI).

The trial evaluated patients over a two-year period, with 1,182 patients receiving TCAR compared to 10,797 patients receiving carotid endarterectomy (CEA).

“Our overall findings showed that while patients receiving TCAR were sicker and more likely to be symptomatic with a higher degree of stenosis, the stroke and death rate compared to CEA was the same,” Schermerhorn said. “With TCAR, there were significantly lower cranial nerve injuries, less time spent in the operating room and fewer patients with a prolonged length of stay. I believe that clinicians should more widely adopt the TCAR technology as it has demonstrated both safety and efficacy and is an excellent alternative to CEA.”

Significant findings from the study showed TCAR to have:

  • Comparable rates of in-hospital stroke or death to CEA (TCAR, 1.6 percent; CEA, 1.4 percent, p=.33);
  • Lower rates of acute cranial nerve injury (TCAR, 0.6 percent; CEA, 1.8 percent, p<.001);
  • Shorter operative times (TCAR, 78 min; CEA, 111 min, p<.001); and
  • Shorter hospital stays, despite patients being older and sicker (percent of hospitals stays longer than one night: TCAR, 27%; CEA, 30%, p=0.046).

TCAR is a clinically proven procedure combining surgical principles of neuroprotection with minimally invasive endovascular techniques to treat blockages in the carotid artery at risk of causing a stroke. The TCAR Surveillance Project is the largest single body of evidence reported since the launch of TCAR in 2016.

Additional TCAR presentations highlighted at SVS VAM 2018 demonstrated similar results:

“Vascular Live: Latest Stroke Prevention Data Signals Standard of Care Potential in Carotid Revascularization” provided an interim update on the ROADSTER 2 Per Protocol data set. The ROADSTER 2 trial is a post-market study intended to enroll a minimum of 600 patients and with at least 70 percent enrollment completed by newly trained operators. Peter Schneider, M.D., of Kaiser Permanente (Honolulu) and co-principal investigator for the ROADSTER 2 trial, presented interim results on 470 patients. Schneider highlighted a 30-day stroke rate of 0.6 percent and a stroke/death rate of 0.9 percent, consistent with the outcomes seen in the pivotal ROADSTER trial.

“A Multi-Institutional Analysis of Contemporary Outcomes after TransCarotid Artery Revascularization versus Carotid Endarterectomy” compared outcomes of TCAR to CEA across four institutions. Alex King of University Hospitals Cleveland Medical Center (Ohio) presented results showing that patients undergoing TCAR (n=292), had similar 30-day stroke rates (TCAR, 1 percent; CEA, 1.1 percent, p=1.00) compared with patients undergoing CEA (n=371), despite being more likely to have significant comorbidities. Acute (TCAR, 0.3 percent; CEA, 4.1 percent, p<.01) and six-month cranial nerve injury rates (TCAR, 0 percent; CEA: 1.9 percent, p=0.02) were shown to be lower with TCAR vs CEA.

The Enroute Transcarotid Stent is intended to be used in conjunction with the Enroute Transcarotid Neuroprotection System (NPS) during the TCAR procedure. The Enroute Transcarotid NPS is used to directly access the common carotid artery and initiate high rate temporary blood flow reversal to protect the brain from stroke while delivering and implanting the Enroute Transcarotid Stent.

For more information: www.silkroadmed.com

This is a review of the impact of the Centers for Medair and Medicaid Services on carotid artery endovascular outcomes carried out by the Division of Vascular and Endovascular Surgery at Harvard Medical School, Partners.

The impact of Centers for Medicare and Medicaid Services high-risk criteria on outcome after carotid endarterectomy and carotid artery stenting in the SVS Vascular Registry.

Schermerhorn ML, Fokkema M, Goodney P, Dillavou ED, Jim J, Kenwood CT, Siami FS, White RA; SVS Outcomes Committee.
 J Vasc Surg. 2013 May;57(5):1318-24.   http://dx.doi.org/10.1016/j.jvs.2012.10.107. Epub 2013 Feb 11.
The Centers for Medicare and Medicaid Services (CMS) require high-risk (HR) criteria for carotid artery stenting (CAS) reimbursement. The impact of these criteria on outcomes after carotid endarterectomy (CEA) and CAS remains uncertain. Additionally, if these HR criteria are associated with more adverse events after CAS, then existing comparative effectiveness analysis of CEA vs CAS may be biased. We sought to elucidate this using data from the SVS Vascular Registry.
We analyzed 10,107 patients undergoing CEA (6370) and CAS (3737), stratified by CMS HR criteria. The primary endpoint was composite death, stroke, and myocardial infarction (MI) (major adverse cardiovascular event [MACE]) at 30 days. We compared baseline characteristics and outcomes using univariate and multivariable analyses.
CAS patients were more likely than CEA to have
  • preoperative stroke (26% vs 21%) or
  • transient ischemic attack (23% vs 19%) .
Although age ≥ 80 years was similar, CAS patients were more likely to have all other HR criteria.
For CEA, HR patients had higher MACEs than normal risk in both
  • symptomatic (7.3% vs 4.6%; P < .01) and
  • asymptomatic patients (5% vs 2.2%; P < .0001).
For CAS, HR status was not associated with a significant increase in MACE for
  • symptomatic (9.1% vs 6.2%; P = .24) or
  • asymptomatic patients (5.4% vs 4.2%; P = .61).
All CAS patients had MACE rates similar to HR CEA. After multivariable risk adjustment, CAS had higher rates than CEA
  • for MACE (odds ratio [OR], 1.2; 95% confidence interval [CI], 1.0-1.5),
  • death (OR, 1.5; 95% CI, 1.0-2.2), and
  • stroke (OR, 1.3; 95% CI,1.0-1.7),
whereas there was no difference in MI (OR, 0.8; 95% CI, 0.6-1.3).
Among CEA patients, MACE was predicted by:
  • age ≥ 80 (OR, 1.4; 95% CI, 1.02-1.8),
  • congestive heart failure (OR, 1.7; 95% CI, 1.03-2.8),
  • EF <30% (OR, 3.5; 95% CI, 1.6-7.7),
  • angina (OR, 3.9; 95% CI, 1.6-9.9),
  • contralateral occlusion (OR, 3.2; 95% CI, 2.1-4.7), and
  • high anatomic lesion (OR, 2.7; 95% CI, 1.33-5.6).
Among CAS patients, recent MI (OR, 3.2; 95% CI, 1.5-7.0) was predictive, and
  • radiation (OR, 0.6; 95% CI, 0.4-0.8) and
  • restenosis (OR, 0.5; 95% CI, 0.3-0.96) …..were protective for MACE
Although CMS HR criteria can successfully discriminate a group of patients at HR for adverse events after CEA, certain CMS HR criteria are more important than others. However, CEA appears safer for the majority of patients with carotid disease. Among patients undergoing CAS, non-HR status may be limited to restenosis and radiation.
This study was preceded by another publication 5-years earlier involving ML Schermerhorn, of the study above.

Risk-adjusted 30-day outcomes of carotid stenting and endarterectomy: results from the SVS Vascular Registry.

Sidawy AN, Zwolak RM, White RA, Siami FS, Schermerhorn ML, Sicard GA; Outcomes Committee for the Society for Vascular Surgery.
Department of Surgery, Washington VA Medical Center, Washington, DC, USA.
J Vasc Surg. 2009 Jan;49(1):71-9. http:/dx.doi.org/10.1016/j.jvs.2008.08.039. Epub 2008 Nov 22.
As of December 26, 2007, 6403 procedures with discharge data were entered by 287 providers at 56 centers on 2763 CAS patients (1450 with 30-day outcomes, 52.5%) and 3259 CEA patients (1368 with 30-day outcomes, 42%).
Of the total cohort, 98% of CEA and 70.7% of CAS (P < .001) were performed for atherosclerotic disease.
  • Restenosis accounted for 22.3% and
  • post-radiation induced stenosis in 4.5% of CAS patients.
Preprocedure lateralizing neurologic symptoms were present in a greater proportion of – CAS patients (49.2%) than CEA patients (42.4%, P < .001).
CAS patients also had higher preprocedure prevalence of
  1. coronary artery disease (CAD),
  2. MI,
  3. congestive heart failure (CHF),
  4. chronic obstructive pulmonary disease (COPD), and
  5. cardiac arrhythmia.
For CAS, death/stroke/MI at 30 days was
  • 7.13% for symptomatic patients and 4.60% for asymptomatic patients (P = .04).
For CEA, death/stroke/MI at 30 days was
  • 3.75% in symptomatic patients and 1.97% in asymptomatic patients (P = .05).
After risk-adjustment for age, history of stroke, diabetes, and American Society of Anesthesiologists (ASA) grade (ie, factors found to be significant confounders in outcomes using backwards elimination),
logistic regression analysis suggested better outcomes following CEA.
When CAS and CEA were compared in the treatment of atherosclerotic disease only, the difference in outcomes between the two procedures was more pronounced, with
  • death/stroke/MI 6.42% after CAS vs 2.62% following CEA, P < .0001.
With continued enrollment and follow-up, analysis of SVS-VR will supplement randomized trials by providing real-world comparisons of CAS and CEA with sufficient numbers to serve as an outcome assessment tool of important patient subsets and across the spectrum of peripheral vascular procedures.
J Vasc Surg. 2012 May;55(5):1313-20; discussion 1321. doi: 10.1016/j.jvs.2011.11.128. Epub 2012 Mar 28.

Society for Vascular Surgery (SVS) Vascular Registry evaluation of comparative effectiveness of carotid revascularization procedures stratified by Medicare age.

Jim J, Rubin BG, Ricotta JJ 2nd, Kenwood CT, Siami FS, Sicard GA; SVS Outcomes Committee.

Source

Washington University School of Medicine, St. Louis, Mo., USA.

Abstract

OBJECTIVE:

Recent randomized controlled trials have shown that age significantly affects the outcome of carotid revascularization procedures. This study used data from the Society for Vascular Surgery Vascular Registry (VR) to report the influence of age on the comparative effectiveness of carotid endarterectomy (CEA) and carotid artery stenting (CAS).

METHODS:

VR collects provider-reported data on patients using a Web-based database. Patients were stratified by age and symptoms. The primary end point was the composite outcome of death, stroke, or myocardial infarction (MI) at 30 days.

RESULTS:

As of December 7, 2010, there were 1347 CEA and 861 CAS patients aged < 65 years and 4169 CEA and 2536 CAS patients aged ≥ 65 years. CAS patients in both age groups were more likely to have a disease etiology of radiation or restenosis, be symptomatic, and have more cardiac comorbidities. In patients aged <65 years, the primary end point (5.23% CAS vs 3.56% CEA; P = .065) did not reach statistical significance. Subgroup analyses showed that CAS had a higher combined death/stroke/MI rate (4.44% vs 2.10%; P < .031) in asymptomatic patients but there was no difference in the symptomatic (6.00% vs 5.47%; P = .79) group. In patients aged ≥ 65 years, CEA had lower rates of death (0.91% vs 1.97%; P < .01), stroke (2.52% vs 4.89%; P < .01), and composite death/stroke/MI (4.27% vs 7.14%; P < .01). CEA in patients aged ≥ 65 years was associated with lower rates of the primary end point in symptomatic (5.27% vs 9.52%; P < .01) and asymptomatic (3.31% vs 5.27%; P < .01) subgroups. After risk adjustment, CAS patients aged ≥ 65 years were more likely to reach the primary end point.

CONCLUSIONS:

Compared with CEA, CAS resulted in inferior 30-day outcomes in symptomatic and asymptomatic patients aged ≥ 65 years. These findings do not support the widespread use of CAS in patients aged ≥ 65 years.

Related articles

Other related articles published in this Open Access Online Scientific Journal

Abdominal Aortic Aneurysm: Endovascular repair and open repair resulted in similar long-term survival  (Aviva Lev-Ari)
Competition in the Ecosystem of Medical Devices in Cardiac and Vascular Repair: Heart Valves, Stents, Catheterization Tools and Kits for Open Heart and Minimally Invasive Surgery (MIS)  (Aviva Lev-Ari)
Bioabsorbable Drug Coating Scaffolds, Stents and Dual Antiplatelet Therapy (Aviva Lev-Ari)
Vascular Repair: Stents and Biologically Active Implants (larryhbern)
Drug Eluting Stents: On MIT’s Edelman Lab’s Contributions to Vascular Biology and its Pioneering Research on DES  (larryhbern)
Transcatheter Aortic Valve Replacement (TAVR): Postdilatation to Reduce Paravalvular Regurgitation During TAVR with a Balloon-expandable Valve  (larryhbern)
Acute and Chronic Myocardial Infarction: Quantification of Myocardial Perfusion Viability – FDG-PET/MRI vs. MRI or PET alone  (Justin Pearlman, Aviva Lev-Ari)
Biomaterials Technology: Models of Tissue Engineering for Reperfusion and Implantable Devices for Revascularization (larryhbern)
Revascularization: PCI, Prior History of PCI vs CABG  (A Lev-Ari)
Accurate Identification and Treatment of Emergent Cardiac Events (larryhbern)
FDA Pending 510(k) for The Latest Cardiovascular Imaging Technology (A Lev-Ari)
The ACUITY-PCI score: Will it Replace Four Established Risk Scores — TIMI, GRACE, SYNTAX, and Clinical SYNTAX  (A Lev-Ari)
http://pharmaceuticalintelligence.com/2013/01/03/the-acuity-pci-score-will-it-replace-four-established-risk-scores-timi-grace-syntax-and-clinical-syntax/
Absorb™ Bioresorbable Vascular Scaffold: An International Launch by Abbott Laboratories (Aviva Lev-Ari)
Carotid Stenting: Vascular surgeons have pointed to more minor strokes in the stenting group and cardiologists to more myocardial infarctions in the CEA cohort. (A Lev-Ari)
Global Supplier Strategy for Market Penetration & Partnership Options (Niche Suppliers vs. National Leaders) in the Massachusetts Cardiology & Vascular Surgery Tools and Devices Market for Cardiac Operating Rooms and Angioplasty Suites (A Lev-Ari)
English: FIG. 513 – The internal carotid and v...

English: FIG. 513 – The internal carotid and vertebral arteries. Right side. Deutsch: Rechte Arteria carotis (Photo credit: Wikipedia)

Carotid Plaque Atherosclerotic plaque from a c...

Carotid Plaque Atherosclerotic plaque from a carotid endarterectomy specimen. This shows the bifurcation of the common into the internal and external carotid arteries. (Photo credit: Wikipedia)

Right common carotid artery - The Anatomy of t...

Right common carotid artery – The Anatomy of the Arteries Visual Guide, page 5 (of 57) (Photo credit: Rob Swatski)

Read Full Post »

Open Abdominal Aortic Aneurysm (AAA) repair (OAR) vs. Endovascular AAA Repair (EVAR) in Chronic Kidney Disease (CKD) Patients –  Comparison of Surgery Outcomes

Writer and Curator: Larry H. Bernstein, MD, FCAP

and

Curator: Aviva Lev-Ari, PhD, RN 

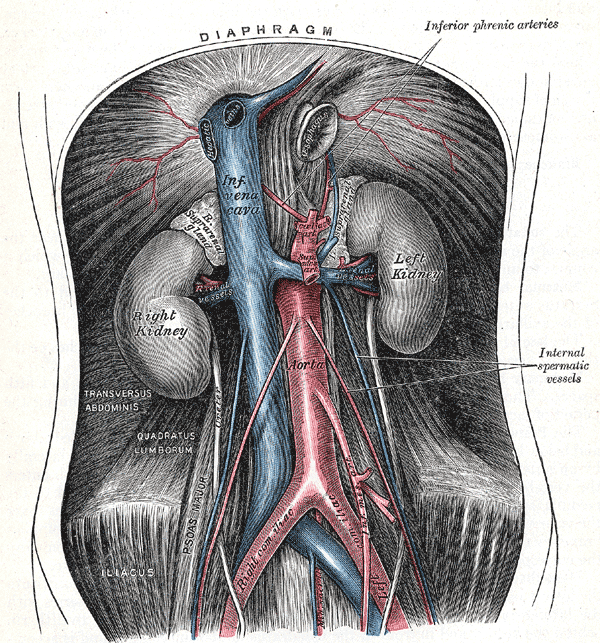
This is a review of the effects of CKD on increased morbidity and mortality of abdominal aortic aneurysm repair.   The abdominal aorta has branches to the superior mesenteric arteries proximally, and below that both renal arteries, which also supply the adrenals (suprarenal).
Severe atherosclerosis with plaque buildup and separation of the media from the endothelium, can migrate down the addominal aorta before frank rupture of an aneurysm.   Abdominal aortic aneurysm often extends from below the the renal arteries, to the internal spermatic vessels, or as far as the iliacs.

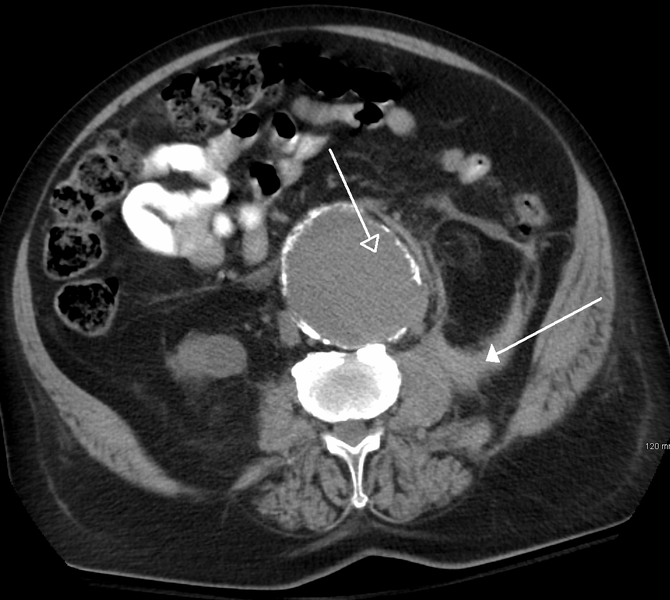
220px-Aortadiagramgray           Contrast-enhanced_CT_scan_demonstrating_abdominal_aortic_aneurysm

http://upload.wikimedia.org/wikipedia/commons/thumb/4/4a/Contrast-enhanced_CT_scan_demonstrating_abdominal_aortic_aneurysm.jpg/120px-Contrast-enhanced_CT_scan_demonstrating_abdominal_aortic_aneurysm.jpg

Of the visceral branches, the celiac artery and the superior and inferior mesenteric arteries are unpaired, while the suprarenals, renals, internal spermatics, and ovarian are paired. Of the parietal branches the inferior phrenics and lumbars are paired; the middle sacral is unpaired. The terminal branches are paired.
AAA is most common in men over age 65 years.  If it is expanding AAA causes sudden, severe, and constant low back, flank, abdominal, or groin pain (internal spermatic branch).  The presence of a pulsatile abdominal mass is virtually diagnostic but is found in less than half of all cases.  At least 65% of patients with a ruptured AAA die from sudden cardiovascular collapse before arriving at a hospital.
670px-RupturedAAA

EVAR for ruptured AAA

A study by Mehta et al assessed the effect of hemodynamic status on outcomes in 136 patients undergoing EVAR for ruptured AAAs.[1] The patients were divided into 2 groups:
(1) Hd-stable (systolic BP ≥80 mm Hg; n = 92 [68%]) and
(2) Hd-unstable (systolic BP < 80 mm Hg for >10 minutes; n = 44 [32%]).
The 30-day mortality, postoperative complications, need for secondary reinterventions, and midterm mortality were recorded. The 2 groups were found to be similar with respect to
  • comorbidities,
  • mean AAA maximum diameter (6.6 vs 6.4 cm),
  • need for on-the-table conversion to open repair (3% vs 7%), and
  • incidence of nonfatal complications (43% vs 38%) and secondary interventions (23% vs 25%).
  1. intraoperative need for aortic occlusion balloon,
  2.  mean estimated blood loss,
  3. incidence of developing abdominal compartment syndrome (ACS), and
  4. mortality
were all increased in the Hd-unstable group ([1]40% vs 6%, [2]744 vs 363 mL,[3] 29% vs 4%, and [4]33% vs 18%, respectively).

Open Surgery

Requires direct access to the aorta through an abdominal or retroperitoneal approach
Endovascular: Involves gaining access to the lumen of the abdominal aorta, usually via small incisions over the femoral vessels; an endograft, typically a cloth graft with a stent exoskeleton, is placed within the lumen of the AAA, extending distally into the iliac arteries.  Approximately 90% of abdominal aortic aneurysms are infrarenal.
The important surgical and endovascular anatomic considerations include associated renal and visceral artery involvement (either occlusive disease or involved in the aneurysm process) and the iliac artery (either occlusive disease or aneurysms). The length of the infrarenal aortic neck is important in helping determine the surgical approach (retroperitoneal vs transabdominal) and the location of the aortic cross clamp.

Endovascular Aneurysm Repair

Endovascular repair first became practical in the 1990s and although it is now an established alternative to open repair, its role is yet to be clearly defined. It is generally indicated in older, high-risk patients or patients unfit for open repair. However, endovascular repair is feasible for only a proportion of AAAs, depending on the morphology of the aneurysm. The main advantages over open repair are that there is less peri-operative mortality, less time in intensive care, less time in hospital overall and earlier return to normal activity. Disadvantages of endovascular repair include a requirement for more frequent ongoing hospital reviews, and a higher chance of further procedures being required.  According to the latest studies, the EVAR procedure does not offer any benefit for overall survival or health-related quality of life compared to open surgery, although aneurysm-related mortality is lower.

Aorta Anatomy and Pathology in AAA

The diameter of the aorta decreases in size from its thoracic portion to the abdominal and infrarenal portions. A normal aorta shows a reduction in medial elastin layers from the thoracic area to the abdominal portion. Elastin and collagen content are also reduced.  AAAs develop following degeneration of the media. The degeneration ultimately may lead to widening of the vessel lumen and loss of structural integrity.  
A multidisciplinary research program supported by the US National Heart, Lung, and Blood Institute identified proteolytic degradation of aortic wall connective tissue, inflammation and immune responses, biomechanical wall stress, and molecular genetics as mechanisms important in the development of AAA.  Similarly, surgical specimens of AAA reveal inflammation, with infiltration by lymphocytes and macrophages; thinning of the media; and marked loss of elastin.
Through gene microarray analysis, various genes involved in extracellular matrix degradation, inflammation, and other processes observed in AAA formation have been shown to be up-regulated, while others that may serve to prevent this occurrence are down-regulated. The combination of proteolytic degradation of aortic wall connective tissue, inflammation and immune responses, biomechanical wall stress, and molecular genetics represents a dynamic process that leads to aneurysmal deterioration of aortic tissue.
mortality caused by aortic aneurysm
1.  Mehta M, Paty PS, Byrne J, Roddy SP, Taggert JB, Sternbach Y, et al. The impact of hemodynamic status on outcomes of endovascular abdominal aortic aneurysm repair for rupture. J Vasc Surg. May 2013;57(5):1255-60. [Medline].
2.  Blanchard JF, Armenian HK, Friesen PP. Risk factors for abdominal aortic aneurysm: results of a case-control study. Am J Epidemiol. Mar 15 2000;151(6):575-83. [Medline].
3.  Lederle FA, Johnson GR, Wilson SE, Chute EP, Littooy FN, Bandyk D, et al. Prevalence and associations of abdominal aortic aneurysm detected through screening. Aneurysm Detection and Management (ADAM) Veterans Affairs Cooperative Study Group. Ann Intern Med. Mar 15 1997;126(6):441-9. [Medline].
4.   Wassef M, Baxter BT, Chisholm RL, Dalman RL, Fillinger MF, Heinecke J, et al. Pathogenesis of abdominal aortic aneurysms: a multidisciplinary research program supported by the National Heart, Lung, and Blood Institute. J Vasc Surg. Oct 2001;34(4):730-8. [Medline].
5.   [Guideline] U.S. Preventive Services Task Force. Screening for abdominal aortic aneurysm: recommendation statement. Ann Intern Med. Feb 1 2005;142(3):198-202. [Medline]. [Full Text].

Impact of chronic kidney disease on outcomes after abdominal aortic aneurysm repair

Patel VI, Lancaster RT, Mukhopadhyay S, Aranson NJ, Conrad MF, et al.
J Vasc Surg. 2012 Nov;56(5):1206-13.      http://dx.doi.org/10.1016/j.jvs.2012.04.037. Epub 2012 Aug 1.
Chronic kidney disease (CKD) is associated with increased morbidity and death after open abdominal aortic aneurysm (AAA) repair (OAR). This study highlights the effect of CKD on outcomes after endovascular AAA (EVAR) and OAR in contemporary practice.
The National Surgical Quality Improvement Program (NSQIP) Participant Use File (2005-2008) was queried by Current Procedural Terminology (American Medical Association, Chicago, Ill) code to identify EVAR or OAR patients, who were grouped by CKD class as having mild (CKD class 1 or 2), moderate (CKD class 3), or severe (CKD class 4 or 5) renal disease. Propensity score analysis was performed to match OAR and EVAR patients with mild CKD with those with moderate or severe CKD. Comparative analysis of mortality and clinical outcomes was performed based on CKD strata.
We identified 8701 patients who were treated with EVAR (n = 5811) or OAR (n = 2890) of intact AAAs. Mild, moderate, and severe CKD was present in 63%, 30%, and 7%, respectively. CKD increased (P < .01) overall mortality, with rates of 1.7% (mild), 5.3% (moderate), and 7.7% (severe) in unmatched patients undergoing EVAR or OAR. Operative mortality rates in patients with severe CKD were as high as 6.2% for EVAR and 10.3% for OAR.
Severity of CKD was associated with increasing frequency of risk factors; therefore, propensity matching to control for comorbidities was performed, resulting in similar baseline clinical and demographic features of patients with mild compared with those with moderate or severe disease.
In propensity-matched cohorts, moderate CKD increased the risk of 30-day mortality
  • for EVAR (1.9% mild vs 3.2% moderate; P = .013) and
  • OAR (3.1% mild vs 8.4% moderate; P < .0001).
Moderate CKD was also associated with increased morbidity in patients treated with
  • EVAR (8.3% mild vs 12.8% moderate; P < .0001) or
  • OAR (25.2% mild vs 32.4% moderate; P = .001).
Similarly, severe CKD increased the risk of 30-day mortality
  • for EVAR (2.6% mild vs 5.7% severe; P = .0081) and
  • OAR (4.1% mild vs 9.9% severe; P = .0057).
Severe CKD was also associated with increased morbidity in patients treated with
  • EVAR (10.6% mild vs 19.2% severe; P < .0001) or
  • OAR (31.1% mild vs 39.6% severe; P = .04).
The presence of moderate or severe CKD in patients considered for AAA repair is associated with significantly increased mortality and therefore should figure prominently in clinical decision making. The high mortality of AAA repair in patients with severe CKD is such that elective repair in such patients is not advised, except in extenuating clinical circumstances.

Related articles published on this Open Access Online Scientific Journal 

Effect of Hospital Characteristics on Outcomes of Endovascular Repair of Descending Aortic Aneurysms in US Medicare Population

Larry H. Bernstein, MD, FCAP 

http://pharmaceuticalintelligence.com/2013/06/27/effect-of-hospital-characteristics-on-outcomes-of-endovascular-repair-of-descending-aortic-aneurysms-in-us-medicare-population/

Abdominal Aortic Aneurysms (AAA): Albert Einstein’s Operation by Dr. Nissen
Aviva Lev-Ari, PhD, RN
No Early Symptoms – An Aortic Aneurysm Before It Ruptures – Is There A Way To Know If I Have it?
Justin D Pearlman, MD, PhD, FACC and Aviva Lev-Ari, PhD, RN
First-of-Its-Kind FDA Approval for ‘AUI’ Device with Endurant II AAA Stent Graft: Medtronic Expands in Endovascular Aortic Repair in the United States
Aviva Lev-Ari, PhD, RN
Abdominal Aortic Aneurysm: Endovascular repair and open repair resulted in similar long-term survival
Aviva Lev-Ari, PhD, RN
EUROPCR 2013, Paris 5/21-5/24, 2013 Conference for Cardiolovascular Intervention and Interventional Medicine
Aviva Lev-Ari, PhD, RN
Genomics & Genetics of Cardiovascular Disease Diagnoses: A Literature Survey of AHA’s Circulation Cardiovascular Genetics, 3/2010 – 3/2013
Aviva Lev-Ari, PhD, RN and Larry Bernstein, MD, FCAP
Competition in the Ecosystem of Medical Devices in Cardiac and Vascular Repair: Heart Valves, Stents, Catheterization Tools and Kits for Open Heart and Minimally Invasive Surgery (MIS)
Aviva Lev-Ari, PhD, RN
Bioabsorbable Drug Coating Scaffolds, Stents and Dual Antiplatelet Therapy
Aviva Lev-Ari, PhD, RN
Vascular Repair: Stents and Biologically Active Implants
Larry  Bernstein, MD, FCAP
Drug Eluting Stents: On MIT’s Edelman Lab’s Contributions to Vascular Biology and its Pioneering Research on DES
Larry H. Bernstein, MD, FCAP 
Coronary Artery Disease – Medical Devices Solutions: From First-In-Man Stent Implantation, via Medical Ethical Dilemmas to Drug Eluting Stents
Aviva Lev-Ari, PhD, RN
Survivals Comparison of Coronary Artery Bypass Graft (CABG) and Percutaneous Coronary Intervention (PCI) / Coronary Angioplasty
Larry Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN
Trans-apical Transcatheter Aortic Valve Replacement in a Patient with Severe and Complex Left Main Coronary Artery Disease (LMCAD)
Larry Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN
Transcatheter Aortic Valve Replacement (TAVR): Postdilatation to Reduce Paravalvular Regurgitation During TAVR with a Balloon-expandable Valve
Larry Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN
Svelte Medical Systems’ Drug-Eluting Stent: 0% Clinically-Driven Events Through 12-Months in First-In-Man Study
Aviva Lev-Ari, PhD, RN
Acute and Chronic Myocardial Infarction: Quantification of Myocardial Perfusion Viability – FDG-PET/MRI vs. MRI or PET alone  (Justin Pearlman, Aviva Lev-Ari)
Biomaterials Technology: Models of Tissue Engineering for Reperfusion and Implantable Devices for Revascularization
Larry Bernstein, MD, FCAP and Aviva Lev-Ari, PhD, RN
Revascularization: PCI, Prior History of PCI vs CABG
Aviva Lev-Ari, PhD, RN
Accurate Identification and Treatment of Emergent Cardiac Events
Larry Bernstein, MD, FCAP
FDA Pending 510(k) for The Latest Cardiovascular Imaging Technology
Aviva Lev-Ari, PhD, RN
The ACUITY-PCI score: Will it Replace Four Established Risk Scores — TIMI, GRACE, SYNTAX, and Clinical SYNTAX
Aviva Lev-Ari, PhD, RN
Nitric Oxide and it’s impact on Cardiothoracic Surgery
Tilda Barliya, PhD
CABG or PCI: Patients with Diabetes – CABG Rein Supreme
Aviva Lev-Ari, PhD, RN
To Stent or Not? A Critical Decision
Aviva Lev-Ari, PhD, RN
Endothelin Receptors in Cardiovascular Diseases: The Role of eNOS Stimulation
Aviva Lev-Ari, PhD, RN
Absorb™ Bioresorbable Vascular Scaffold: An International Launch by Abbott Laboratories
Aviva Lev-Ari, PhD, RN
Carotid Stenting: Vascular surgeons have pointed to more minor strokes in the stenting group and cardiologists to more myocardial infarctions in the CEA cohort.
Aviva Lev-Ari, PhD, RN
New Drug-Eluting Stent Works Well in STEMI
Aviva Lev-Ari, PhD, RN
Global Supplier Strategy for Market Penetration & Partnership Options (Niche Suppliers vs. National Leaders) in the Massachusetts Cardiology & Vascular Surgery Tools and Devices Market for Cardiac Operating Rooms and Angioplasty Suites
Aviva Lev-Ari, PhD, RN
Abdominal Aortic Aneurysm in Computer Tomography

Abdominal Aortic Aneurysm in Computer Tomography (Photo credit: Wikipedia)

Read Full Post »

Effect of Hospital Characteristics on Outcomes of Endovascular Repair of Descending Aortic Aneurysms in US Medicare Population

Writer and Curator: Larry H. Bernstein, MD, FCAP 

and

Curator: Aviva Lev-Ari, PhD, RN 

Impact of hospital volume and type on outcomes of open and endovascular repair of descending thoracic aneurysms in the United States Medicare population.

Patel VI, Mukhopadhyay S, Ergul E, Aranson N, …., Cambria RP.
Journal of vascular surgery 2013;    http://dx.doi.org/10.1016/j.jvs.2013.01.035


Open surgery for thoracic aortic aneurysm has had success, but it carries complication risks.  In 2004, a much less invasive procedure, thoracic endovascular repair (TEVAR) was introduced. It eliminated a need for open surgery in many patients, but not all were suitable candidtes .  The advances in endovascular technology and procedural breakthroughs  since it was introduced has contributed to a dramatic transformation of the specialty of thoracic aortic surgery. The decision of which patients require open surgery is necessarily determined by the limitations of the procedure and the condition of the patient.
Thoracic endovascular aortic repair (TEVAR) is a minimally invasive alternative to conventional open surgical reconstruction for the treatment of thoracic aortic aneurysm. TEVAR procedures can be challenging and, at times, extraordinarily difficult.  Meticulous assessment of anatomy and preoperative procedure planning are absolutely paramount to produce optimal outcomes. The rapidly Increased use of TEVAR has produced favorable outcomes of TEVAR compared with open abdominal repair for descending thoracic aortic aneurysms (DTAs).   But the success of these procedure depends on requisite skills, and following guidelines intended for use in quality-improvement programs that assess the standard of care expected from all physicians who perform TEVAR procedures.
Currently, there is a diverse array of endografts that are commercially available to treat the thoracic aorta. Multiple studies have demonstrated excellent outcomes of thoracic endovascular aortic repair for the treatment of thoracic aortic aneurysms, with less reported perioperative morbidity and mortality in comparison with conventional open repair. Additionally, similar outcomes have been demonstrated for the treatment of type B dissections. However, the technology remains relatively novel, and larger studies with longer term outcomes are necessary to more fully evaluate the role of endovascular therapy for the treatment of thoracic aortic disease.
The MGH/Partners vascular surgeons evaluated the effect of case volume and hospital teaching status on clinical outcomes of intact DTA repair to gain an insight into whether there was a variability in DTAs outcomes based on hospital size, patient mix, number of procedures, staff characteristics, and teaching status.  This study was needed for establishing the type of procedure most suited to the type of patient, and to obtain the most accurate analysis of cost requirements based on resource allocation for reimbursement purposes.
The Medicare Provider Analysis and Review (MEDPAR) data set (2004 to 2007) was queried to identify open repair or TEVAR for DTA. Hospitals were stratified by DTA volume into high volume (HV; ≥8 cases/y) or low volume (LV; <8 cases/y) and teaching or nonteaching. The effect of hospital variables on the primary study end point of 30-day mortality and secondary end points of 30-day complications and long-term survival after open repair and TEVAR DTA repair were studied using univariate testing, multivariable regression modeling, Kaplan-Meier survival analysis, and Cox proportional hazards regression modeling.
They identified 763 hospitals performing 3554 open repairs and 3517 TEVARs. Overall DTA repair increased (P < .01) from 1375 in 2004 to 1987 in 2007. The proportion of hospitals performing open repair significantly decreased from 95% in 2004 to 57% in 2007 (P < .01), whereas
  • those performing TEVAR increased (P < .01) from 24% to 76%.
Overall repair type shifted from open (74% in 2004, the year before initial commercial availability of TEVAR) to TEVAR (39% open in 2007; P < .01). The fraction of open repairs at LV hospitals
  • decreased from 56% in 2004 to 44% in 2007 (P < .01), whereas
  • TEVAR increased from 24% in 2004 to 51% in 2007 (P < .01).
Overall mortality during the study interval for
  •  open repair was 15% at LV hospitals vs 11% at HV hospitals (P < .01), whereas
  • TEVAR mortality was similar, at 3.9% in LV vs 5.5% in HV hospitals (P = .43).
LV was independently associated with increased mortality after open repair (odds ratio, 1.4; 95% confidence interval, 1.1-1.8; P < .01) but not after TEVAR. There was no independent effect of hospital teaching status on mortality or complications after open repair or TEVAR repair.
The total number of DTA repairs significantly increased after the introduction of TEVAR for DTA. Operative mortality for TEVAR is independent of hospital volume and type, whereas
  • mortality after open surgery is lower at HV hospitals.
While the TEVAR mortality is significantly less than that of open surgery, the mortality in open surgery is higher for LV hospitals.  The data suggests that TEVAR can be safely performed across a spectrum of hospitals, whereas open surgery should be performed only at HV hospitals.
  1. Standard of Practice for the Endovascular Treatment of Thoracic Aortic Aneurysms and Type B Dissections. Fanelli F, and  Dake MD.  Cardiovasc Intervent Radiol. 2009 September; 32(5): 849–860.  http://dx.doi.org/10.1007/s00270-009-9668-6  PMCID: PMC2744786
  2. Thoracic aortic aneurysms and dissections: endovascular treatment. Baril DT, Cho JS, Chaer RA, Makaroun MS. Division of Vascular Surgery, University of Pittsburgh Medical Center, Pittsburgh, PA. Mt Sinai J Med. 2010 May-Jun;77(3):256-69.  http://dx.doi.org/10.1002/msj.20178.

Related Articles in Pharmaceuticval Intelligence

Abdominal Aortic Aneurysms (AAA): Albert Einstein’s Operation by Dr. Nissen   (Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/2013/06/11/abdominal-aortic-aneurysms-aaa-albert-einsteins-operation-by-dr-nissen/

The Heart Surgery Specialty: heart transplant, lung transplant, heart-lung transplantation, aortic valve surgery, bypass surgery, minimally invasive cardiac surgery, heart valve surgery, removal of cardiac tumors, reoperation valve surgery  (Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/?p=14092&preview=true

No Early Symptoms – An Aortic Aneurysm Before It Ruptures – Is There A Way To Know If I Have it?
(Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/2013/06/10/no-early-symptoms-an-aortic-aneurysm-before-it-ruptures-is-there-a-way-to-know-if-i-have-it/

First-of-Its-Kind FDA Approval for ‘AUI’ Device with Endurant II AAA Stent Graft: Medtronic Expands in Endovascular Aortic Repair in the United States   (Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/2013/05/30/first-of-its-kind-fda-approval-for-aui-device-with-endurant-ii-aaa-stent-graft-medtronic-expands-in-endovascular-aortic-repair-in-the-united-states/

Abdominal Aortic Aneurysm: Endovascular repair and open repair resulted in similar long-term survival
(Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/2012/12/03/abdominal-aortic-aneurysm-endovascular-repair-and-open-repair-resulted-in-similar-long-term-survival/

EUROPCR 2013, Paris 5/21-5/24, 2013 Conference for Cardiolovascular Intervention and Interventional Medicine  (Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/2013/05/29/europcr-2013-paris-521-524-2013-conference-for-cardiolovascular-intervention-and-interventional-medicine/

Genomics & Genetics of Cardiovascular Disease Diagnoses: A Literature Survey of AHA’s Circulation Cardiovascular Genetics, 3/2010 – 3/2013  (Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/2013/03/07/genomics-genetics-of-cardiovascular-disease-diagnoses-a-literature-survey-of-ahas-circulation-cardiovascular-genetics-32010-32013/

Competition in the Ecosystem of Medical Devices in Cardiac and Vascular Repair: Heart Valves, Stents, Catheterization Tools and Kits for Open Heart and Minimally Invasive Surgery (MIS)  (Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/2012/06/22/competition-in-the-ecosystem-of-medical-devices-in-cardiac-and-vascular-repair-heart-valves-stents-catheterization-tools-and-kits-for-open-heart-and-minimally-invasive-surgery-mis/

Bioabsorbable Drug Coating Scaffolds, Stents and Dual Antiplatelet Therapy (Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/2013/05/29/bioabsorbable-drug-coating-scaffolds-stents-and-dual-antiplatelet-therapy/

Vascular Repair: Stents and Biologically Active Implants (larryhbern)
http://pharmaceuticalintelligence.com/2013/05/04/stents-biologically-active-implants-and-vascular-repair/

Drug Eluting Stents: On MIT’s Edelman Lab’s Contributions to Vascular Biology and its Pioneering Research on DES  (larryhbern)
http://pharmaceuticalintelligence.com/2013/04/25/contributions-to-vascular-biology/

Coronary Artery Disease – Medical Devices Solutions: From First-In-Man Stent Implantation, via Medical Ethical Dilemmas to Drug Eluting Stents  (Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/2012/08/13/coronary-artery-disease-medical-devices-solutions-from-first-in-man-stent-implantation-via-medical-ethical-dilemmas-to-drug-eluting-stents/

Survivals Comparison of Coronary Artery Bypass Graft (CABG) and Percutaneous Coronary Intervention (PCI) / Coronary Angioplasty (larryhbern)
http://pharmaceuticalintelligence.com/2013/06/23/comparison-of-cardiothoracic-bypass-and-percutaneous-interventional-catheterization-survivals/

Trans-apical Transcatheter Aortic Valve Replacement in a Patient with Severe and Complex Left Main Coronary Artery Disease (LMCAD) (larryhbern)
http://pharmaceuticalintelligence.com/2013/06/17/management-of-difficult-trans-apical-transcatheter-aortic-valve-replacement-in-a-patient-with-severe-and-complex-arterial-disease/

Transcatheter Aortic Valve Replacement (TAVR): Postdilatation to Reduce Paravalvular Regurgitation During TAVR with a Balloon-expandable Valve  (larryhbern)
http://pharmaceuticalintelligence.com/2013/06/17/postdilatation-to-reduce-paravalvular-regurgitation-during-transcatheter-aortic-valve-replacement/

Svelte Medical Systems’ Drug-Eluting Stent: 0% Clinically-Driven Events Through 12-Months in First-In-Man Study  (Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/2013/05/28/svelte-medical-systems-drug-eluting-stent-0-clinically-driven-events-through-12-months-in-first-in-man-study/

Acute and Chronic Myocardial Infarction: Quantification of Myocardial Perfusion Viability – FDG-PET/MRI vs. MRI or PET alone  (Justin Pearlman, Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/2013/05/22/acute-and-chronic-myocardial-infarction-quantification-of-myocardial-viability-fdg-petmri-vs-mri-or-pet-alone/

Biomaterials Technology: Models of Tissue Engineering for Reperfusion and Implantable Devices for Revascularization (larryhbern)
http://pharmaceuticalintelligence.com/2013/05/05/bioengineering-of-vascular-and-tissue-models/

Revascularization: PCI, Prior History of PCI vs CABG  (A Lev-Ari)
http://pharmaceuticalintelligence.com/2013/04/25/revascularization-pci-prior-history-of-pci-vs-cabg/

Accurate Identification and Treatment of Emergent Cardiac Events (larryhbern)
http://pharmaceuticalintelligence.com/2013/03/15/accurate-identification-and-treatment-of-emergent-cardiac-events/

FDA Pending 510(k) for The Latest Cardiovascular Imaging Technology (A Lev-Ari)
http://pharmaceuticalintelligence.com/2013/01/28/fda-pending-510k-for-the-latest-cardiovascular-imaging-technology/

The ACUITY-PCI score: Will it Replace Four Established Risk Scores — TIMI, GRACE, SYNTAX, and Clinical SYNTAX  (A Lev-Ari)
http://pharmaceuticalintelligence.com/2013/01/03/the-acuity-pci-score-will-it-replace-four-established-risk-scores-timi-grace-syntax-and-clinical-syntax/

Nitric Oxide and it’s impact on Cardiothoracic Surgery  (tildabarliya)
http://pharmaceuticalintelligence.com/2012/12/15/nitric-oxide-and-its-impact-on-cardiothoracic-surgery/

CABG or PCI: Patients with Diabetes – CABG Rein Supreme (A Lev-Ari)
http://pharmaceuticalintelligence.com/2012/11/05/cabg-or-pci-patients-with-diabetes-cabg-rein-supreme/

To Stent or Not? A Critical Decision (A Lev-Ari)
http://pharmaceuticalintelligence.com/2012/10/23/to-stent-or-not-a-critical-decision/

Endothelin Receptors in Cardiovascular Diseases: The Role of eNOS Stimulation (A Lev-Ari)
http://pharmaceuticalintelligence.com/2012/10/04/endothelin-receptors-in-cardiovascular-diseases-the-role-of-enos-stimulation/

Absorb™ Bioresorbable Vascular Scaffold: An International Launch by Abbott Laboratories
(Aviva Lev-Ari)
http://pharmaceuticalintelligence.com/2012/09/29/absorb-bioresorbable-vascular-scaffold-an-international-launch-by-abbott-laboratories/

Carotid Stenting: Vascular surgeons have pointed to more minor strokes in the stenting group and cardiologists to more myocardial infarctions in the CEA cohort. (A Lev-Ari)
http://pharmaceuticalintelligence.com/2012/09/21/carotid-stenting-vascular-surgeons-have-pointed-to-more-minor-strokes-in-the-stenting-group-and-cardiologists-to-more-myocardial-infarctions-in-the-cea-cohort/

New Drug-Eluting Stent Works Well in STEMI (A Lev-Ari)
http://pharmaceuticalintelligence.com/2012/08/22/new-drug-eluting-stent-works-well-in-stemi/

lobal Supplier Strategy for Market Penetration & Partnership Options (Niche Suppliers vs. National Leaders) in the Massachusetts Cardiology & Vascular Surgery Tools and Devices Market for Cardiac Operating Rooms and Angioplasty Suites (A Lev-Ari)
http://pharmaceuticalintelligence.com/2012/06/22/global-supplier-strategy-for-market-penetration-partnership-options-niche-suppliers-vs-national-leaders-in-the-massachusetts-cardiology-vascular-surgery-tools-and-devices-market-for-car/

Histopathological image of dissecting aneurysm...

Histopathological image of dissecting aneurysm of thoracic aorta in a patient without evidence of Marfan syndrome. The damaged aorta was surgically removed and replaced by artificial vessel. Victoria blue & HE stain. (Photo credit: Wikipedia)

Diagram of aortic aneurysm Figure A shows a no...

Diagram of aortic aneurysm Figure A shows a normal aorta. Figure B shows a thoracic aortic aneurysm (which is located behind the heart). Figure C shows an abdominal aortic aneurysm located below the arteries that supply blood to the kidneys. (Photo credit: Wikipedia)

Thoracic aorta

Thoracic aorta (Photo credit: Wikipedia)

Open Heart Surgery

Open Heart Surgery (Photo credit: Wikipedia)

Read Full Post »

CVD Core

CVD Core

Reporter: Aviva Lev-Ari, PhD, RN

Article ID #62: CVD Core. Published on 6/26/2013

WordCloud Image Produced by Adam Tubman

When this post will be ready it needs be place

under below link 

http://pharmaceuticalintelligence.com/biomed-e-books/cardiovascular-diseases-causes-risks-and-management/introduction-to-the-three-volume-series-core-research-on-cardiovascular-diseases/

See in red my comments, below

Cardiovascular Diseases: Causes, Risks and Management

Justin D. Pearlman MD PhD MA FACC, Editor

Cardiovascular diseases comprise problems of the heart and blood vessels, including rhythm, blood supply, blood pressure, birth defects, or damage from cholesterol, tobacco, street drugs, radiation, viruses, bacteria, or fungi.

Thus the category includes heart failure (inadequate pump function), heart or vessel infection (endocarditis, vasculitis), birth defects (congenital heart disease)

Cardiovascular Diseases: Causes, Risks and Management

Justin D. Pearlman MD ME PhD MA FACC, Editor


Leaders in Pharmaceutical Business Intelligence

Aviva Lev-Ari, PhD, RN

Director and Founder

Editor-in-Chief

Other e-Books  in the  BioMedicine Series

Perspectives on Nitric Oxide in Disease Mechanisms

Human Immune System in Health and in Disease

Metabolic Genomics & Pharmaceutics

Infectious Disease & New Antibiotic Targets

Cancer Biology and Genomics for Disease Diagnosis

Nanotechnology in Drug Delivery

Genomics Orientations for Personalized Medicine 

This book is a comprehensive review of Innovations in Cardiovascular Medicine, including the latest discoveries in

  • Cardiac Medical Imaging,
  • Regenerative Medicine,
  • Pharmacotherapy,
  • Medical Devices for Cardiac Repair,
  • Genomics, and opportunities for Targeted Therapy.

It is written by experts in their respective subspecialties. The e-Book’s articles have been published on the Open Access Online Scientific Journal, since April 2012.  All new articles on this subject will continue to be incorporated with periodical updates.

http://www.pharmaceuticalIntelligence.com

The Journal is a scientific, medical and business, multi-expert authoring environment for information syndication in domains of Life Sciences, Medicine, Pharmaceutical and Healthcare Industries, BioMedicine, Medical Technologies & Devices. Scientific critical interpretations and original articles are written by PhDs, MDs, MD/PhDs, PharmDs, Technical MBAs as Experts, Authors, Writers (EAWs) on an Equity Sharing basis.

The Editor, Justin D. Pearlman MD ME PhD MA FACC, has many different perspectives developed during the years, including:

  • Chief of Cardiology,
  • non-invasive imaging,
  • molecular biology,
  • mathematics,
  • imaging research

contributed a number of firsts:

  • non-endemic Chagas diagnosis,
  • intensity projection angiography,
  • magnetization tagging,
  • myocardial injury mapping by magnetic resonance contrast retention,
  • myocardial viability by MRI,
  • atheroma lipid liquid crystal characterization,
  • outpatient inotropic infusion therapy,
  • angiogenesis imaging,
  • multimodal in vivo stem cell imaging,
  • real-time velocity beam MRI,
  • in vivo microscopic MRI,
  • dobutamine stress echocardiography for low gradient valve disease,
  • alternative stress tests,
  • diagnostic electrocardiography in magnetic environments,
  • statistical methods to solve error propagation of large array genomics,
  • discovery of monocyte role in native coronary collateral development,
  • image tracked stem cell treatment of  heart attacks,
  • singularity editing in differential topology.


Preface to the Three Volume Series

Cardiovascular disease has been a leading cause of death and disability and so it has also been a major focus for intense research, development, and progress. Knowledge of the causes, risks, and best practices for management continually change. That is why a dynamic electronic living textbook presents an exciting opportunity to help you keep current with the ephemeral leading edge. This book is an outgrowth of the commitment of Leaders in Pharmaceutical Business Intelligence to present the most exciting timely and pertinent advances of our day, in a continual medium to stay fresh and up to date. We hope diverse multispecialty perspectives will help you in your quest to understand, adapt and advance the leading edge of cardiovascular disease causes, risks and best practices management.

On the Diagnosis of Cardiovascular Disease: causes, manifestations, consequences and priorities

Doctors aim to spend their time on prevention, diagnosis, and disease management. More and more the time is diverted to expanding demands for documentation and bureaucratic navigation. This article focuses on the art of diagnosis, with examples based on cardiovascular diseases. Diagnosis cannot be achieved without a knowledge of the causes (etiology) of ailments, a necessary but not sufficient component of diagnosis. The causes broadly relate to nature and nurture, how our biological system develops and functions (nature), and its interactions with the outside world driven in part by behavior, diet, exposures, and activities (nurture). The nature of our individuality has been traced to the human genome, a map of code for protein products that build our structures and mediate our body part functions. Numerous blood tests have been devised to check the expression and activity level of such genomic products to identify disease and characterize its stage. The role of diet, behavior, exposures, activities or lack thereof is well established as a complicit factor in disease development and progression.

The art of diagnosis is designed to find out what is wrong. Literally, it is a flow of knowing, based on knowledge of causes of ailments, probabilities (prevalence), consequences, manifestations, priorities (which would be most urgent) and tests: CPCMPT. Review of those elements generates a list of concerns, often expressed as a “differential diagnosis” which is  a prioritized list of plausible explanations for the observations, patient’s report of symptoms and findings from patient examination. The second stage of diagnosis, called the “work-up,” selects and applies tests to stratify the list of possibilities further as well as to characterize the manifestations and stage of disease. Technically, analysis of biological samples, imaging studies and intervention trials each represent tests; however, they are often viewed as distinct tools with just the former labeled as tests (biological samples include blood tests, urine tests, sputum or saliva samples, and biopsies). The primary goal of the work-up is to establish one or more specific diagnoses as the cause of ailment. The secondary goal of the work-up is to characterize the manifestations and stage of disease to define expectations and clarify options for the disease management. The third goal is to develop a management a plan to slow or stop the ailment, decrease risks of complications, slow or stop progression of disease manifestations or otherwise minimize functional impairment.

The manifestations of disease are categorized as signs and symptoms.

  • Signs are observable evidence of consequences,
  • Symptoms are subjective complaints.

A major component of diagnostic skill is the ability to identify and characterize correctly signs and symptoms of all relevant disease conditions. A second major component of diagnostic skill is the ability to select appropriate tests and interpret their significance in context, in keeping with the patient’s presentation.

When someone sees a doctor about chest pain, coronary artery disease is a prominent consideration. The most common causes of chest pain are mechanical (muscle and bone, e.g., muscle spasms, muscle and bone inflammation), but those conditions are not generally life-threatening. The consequences of blocked arteries – arrhythmia, permanent weakness of the heart, blood clots, pulmonary emboli, stroke, cardiogenic shock, death – raise the stakes and push coronary disease high in priority even when the probabilities are low. The prioritization of the differential diagnosis list has multiple considerations: urgency (how quickly it can worsen), severity of consequences, and the probabilities of a macrovascualar event (prevalence, risk factors). A ten percent risk of coronary disease typically takes precedence over a 70% likelihood of muscle spasm in terms of diagnostic testing.

The road map for the construction of our individuality as humans has been fully mapped: the human genome. Genetic variation means we are not fully determined by the mix of genes inherited from our parents. In addition to the genetic material on our 48 chromosomes, and the genetic material in mitochondria inherited from the mother, there are spontaneous changes in the genetic code, and there are modifications that affect gene expression (which codes produce gene products, quantities, rates, and post-production modifications).

The causes of cardiovascular disease are defined by Murphy’s law: what can go wrong will. However, on the nature side, most malfunctions are too severe to reach the light of day, so there is a limited list of disease mechanisms associated with sufficient viability to reach medical attention. Those mechanisms can be summarized by a mnemonic: diseases can develop new metals in-flame, a-fact externs generated (disease mechanisms: congenital, developmental, neoplastic, metabolic, inflammatory, infectious, extrinsic (e.g. stab wound), and degenerative). A taxonomy of cardiovascular diseases can be constructed in various ways: (1) itemize the major cardiovascular functions and subclassify the dysfunctions, (2) itemize by principle anatomic involvement and subclassify by pathology, (3) classify by mechanism of disease, etiology. Compendiums of cardiovascular disease may be found in: (1) French’s Differential Diagnosis, (2) Robbins and Angel Pathology, (3) Guyton’s Textbook of Physiology, as well as cardiovascular disease textbooks such as Hurst, Braunwald, Mayo Clinic, Cleveland Clinic…

Diagnosis takes many forms. The paranoid inclusive approach, manifested as “medical student syndrome”, considers any semblance of a sign or symptom vaguely similar to a disease manifestation as a frightening prospect worthy of detailed pursuit. The minimalist pragmatic approach commonly attributed to general practitioners focuses on reassurance, and pursuit of persisting complaints that match a common ailment. That approach has been summarized by the advice: when you hear hoof beats think of horses, not zebras. Specialists, on the other hand, are taught to consider all possibilities, with due consideration to urgency and treatability, so that zebras are not punished.

The healthcare system promotes the idea of generalists serving as the front line, identifying who can be managed simply, with specialists serving as finishers for more complex cases or cases requiring special skills. A flaw in that model is the need for detailed knowledge of zebras and subtle findings that may represent an urgent issue at the front line for triage. If the generalist does not know that mild symptoms from mitral valve disease or aortic valve disease may require urgent detailed assessment, patients may be referred to a specialist too late to prevent consequences that requires an earlier intervention.

Parsimony in diagnosis refers to identifying the fewest number of diagnoses that explain all the findings. The concept has been attributed to Osler, and it builds on a guiding procedure voiced in the middle ages by Occum, known as Occum’s razor: when deciding between two explanations, favor the one that requires the fewest assumptions. Parsimony is a useful guide for diagnosis of a previously healthy patient who develops a number of findings that are temporally coherent. After age 65 (official geriatrics age), physicians are taught to abandon parsimony and expect more diagnoses than findings.

A study of difficult diagnoses lead to the concept of a pivotal finding as one that has a narrow differential list. The diagnostic process is prone to errors, including cognitive biases, which may benefit from computer assistance. Intuition and analytics can be applied to reduce cognitive bias. The author developed a just-in-time social networking system within a software package called Missive(c) that enables rapid access to such tools, combining efficiency in documentation with improved quality of analysis and reports (faster and better).

Among older Americans, more are hospitalized for heart failure than for any other medical condition (diastolic failure=stiff heart, systolic failure= inadequate pumping).

Genomics – the study of the genetic basis for disease – is rapidly expanding knowledge about etiology (cause of disease), and it helps identify opportunities for accurate diagnosis and treatment. The American Heart Association journal CIRCULATION has published 348 relevant articles related to cardiovascular genomics from 2010-2013.  For example, just on the subtopic of atherosclerosis (hardening of arteries), genomics offers major progress. The genetic factors that affect arterial stiffness are strongly related to a very common underlying health concern, hypertension (high blood pressure). The counterpart to genetics is environment (nature versus nurture), but genetics carries the trump cards because it determines the sensitivities to environment.

anatomy

physiology

laboratory tests

interventional trials

Boundaries of the Domain: Cardiovascular Diseases: Causes, Risks and Management – Volume 1,2,3


The scope of cardiovascular disease scholarly contributions will grow to include: anatomy, surgery, molecular biology, ethics, imaging (echo, nuclear, PET, MRI, OCT, CT), congenital, stress tests, ECG, electrophysiology/rhythm/channelopathies, pacing, resynchronizing, AICD, cardiomyopathies, syncope, valve disease, aorta, renal artery, thrombosis, venous diseases, vasculitis, endothelium, metabolic syndrome, dyslipidemia, risk factors, biomarkers, hypertension, embolism, pulmonary hypertension, cardiac tumors, women’s health, CAD, Angina,  Stem cells, complications of MI, thrombolysis, rehabilitation, reflexes, hormones, diastology, pharmaceuticals, myocarditis, hypertrophy, failure, shock, hemodynamics, interventions, contrast nephropathy, and contrast systemic fibrosis, as well as other relevant topics you may suggest.

An overview of the Core Research on Cardiovascular Diseases is based on the following NINE articles: 

Have only the article title as a live link of the following 9 [originally were on CVD Zero, title and links, now only links]

  1. http://pharmaceuticalintelligence.com/2013/05/15/diagnosis-of-cardiovascular-disease-treatment-and-prevention-current-predicted-cost-of-care-and-the-promise-of-individualized-medicine-using-clinical-decision-support-systems-2/ 
  2. http://pharmaceuticalintelligence.com/2013/05/04/cardiovascular-diseases-decision-support-systems-for-disease-management-decision-making/ 
  3. http://pharmaceuticalintelligence.com/2013/03/07/genomics-genetics-of-cardiovascular-disease-diagnoses-a-literature-survey-of-ahas-circulation-cardiovascular-genetics-32010-32013/
  4. http://pharmaceuticalintelligence.com/2013/05/17/synthetic-biology-on-advanced-genome-interpretation-for-gene-variants-and-pathways-what-is-the-genetic-base-of-atherosclerosis-and-loss-of-arterial-elasticity-with-aging/ 
  5. http://pharmaceuticalintelligence.com/2013/05/11/arterial-elasticity-in-quest-for-a-drug-stabilizer-isolated-systolic-hypertension-caused-by-arterial-stiffening-ineffectively-treated-by-vasodilatation-antihypertensives/ 
  6. http://pharmaceuticalintelligence.com/2013/05/24/imaging-biomarker-for-arterial-stiffness-pathways-in-pharmacotherapy-for-hypertension-and-hypercholesterolemia-management/ 
  7. http://pharmaceuticalintelligence.com/2013/04/28/genetics-of-conduction-disease-atrioventricular-av-conduction-disease-block-gene-mutations-transcription-excitability-and-energy-homeostasis/
  8. http://pharmaceuticalintelligence.com/2013/05/07/on-devices-and-on-algorithms-arrhythmia-after-cardiac-surgery-prediction-and-ecg-prediction-of-paroxysmal-atrial-fibrillation-onset/ 
  9. http://pharmaceuticalintelligence.com/2013/05/22/acute-and-chronic-myocardial-infarction-quantification-of-myocardial-viability-fdg-petmri-vs-mri-or-pet-alone

The main points are

[bring here ONLY the INTRODUCTION and the Summary of each, THEN The EDITOR will provide perspective on the Research and the current STate of Cardiology in the US in 2013/2014]

A. Now you provide ONLY links to 

Volume #

Contributors to Volume #

eTOCS in Volume #

REPEAT A. for each Volume

Volume One: Causes of Cardiovascular Diseases

Table of Contents

Hardening of the arteries is described as atherosclerosis, or porridge-like wall changes with scarring, which leads to heart attacks, high blood pressure, stroke, and organ injury mediated by ischemia (insufficient nutrient blood supply). The causes are both nature (genetic) and nurture (behavior, diet). Specifics of the causes guide diagnosis and management.

Chapter 1.2: Genomics

The completion of the human genome map was a major accomplishment, as gene products make signals, receptors and building blocks that establish health and disease. However, it is just a stepping stone, not explaining why, where, or how the gene products are regulated and  interact.

Chapter 1.3: Cardiovascular Imaging

Imaging applies a principle of physics (light transmission, sound transmission, xray transmission, magnetic resonance, radioactivity) to provide a map of interior structures and/or activities. Image processing (computing) derives further information than simple display of an observed tissue-sensitive parameter. In the case of computed tomography (CT), magnetic resonance (MRI), positron-emission tomography (PET), and single-photon emission tomography (SPECT),  computer reformatting of image data is essential.

Volume Two: Risk Assessment of Cardiovascular Diseases

Contributors

Table of Contents

Cardiovascular disease is the leading cause of death and disability, affecting more than four times as many people as all forms of cancer combined.

Chapter  2.2: Testing for cardiovascular risk

The volunteer population of Framingham Massachusetts provided decades of data clarifying determinants of risk for cardiovascular diseases. That data helped establish the usefulness of cholesterol screening, and lead to the search for additional tests to identify risk and guide management.

Chapter 2.3: Biomarkers

Biomarkers are chemistry levels (concentrations in the blood) that identify injury or risk for injury.

Volume Three: Management of Cardiovascular Diseases

Contributors

Chapter  3.1: Therapeutic Genomics

As the mysteries of the human genome products are unraveled, we get closer to identifying key components. One of them is Thymosin beta 4 (Tβ4) , which plays an essential role in cardiac and blood vessel development and regeneration. It may lead to breakthroughs in angiogenesis and vasculogenesis, or new vessel development, mimicking the behavior of the lucky few who develop new vessels, or collaterals, as a natural bypass system, without requiring a surgeon to provide a blood supply to avoid or limit heart attacks.

Chapter 3.2: Image guidance of Therapy

The US government is helping to sponsor new imaging methods, while they also inhibit it by adding new taxes.

Chapter 3.3: Drug therapy

Emerging new therapies are presented, along with the biological basis.

Chapter 3.4: Cardiovascular Interventions

Technological advances enable minimally invasive solutions to problems previously addressed by surgery or autopsy.

Introduction 


Contributors above, need a LINK to the appropriate contributors in each volume. Table of Contents of each volume above need a LINK to the eTOCS of each volume.  

Please UPDATE all links ABOVE to the appropriate locations in the respective volumes, after implementing the carry over, remove links below EXCEPT CVD1,2,3 and remove this comment of mine in RED, here

REFERENCES for CVD CORE

A.  Diagnosis of Cardiovascular Disease and Cost of Care

Bernstein, HL and A. Lev-Ari 5/15/2013 Diagnosis of Cardiovascular Disease, Treatment and Prevention: Current & Predicted Cost of Care and the Promise of Individualized Medicine Using Clinical Decision Support Systems

http://pharmaceuticalintelligence.com/2013/05/15/diagnosis-of-cardiovascular-disease-treatment-and-prevention-current-predicted-cost-of-care-and-the-promise-of-individualized-medicine-using-clinical-decision-support-systems-2/ 

B. Cardiovascular Diseases: Disease Management Decision Making – use of CDSS

Pearlman, JD and A. Lev-Ari 5/4/2013 Cardiovascular Diseases: Decision Support Systems for Disease Management Decision Making

http://pharmaceuticalintelligence.com/2013/05/04/cardiovascular-diseases-decision-support-systems-for-disease-management-decision-making/ 

C. Genomics & Genetics of Cardiovascular Disease Diagnoses

Lev-Ari, A. and L H Bernstein 3/7/2013 Genomics & Genetics of Cardiovascular Disease Diagnoses: A Literature Survey of AHA’s Circulation Cardiovascular Genetics, 3/2010 – 3/2013

http://pharmaceuticalintelligence.com/2013/03/07/genomics-genetics-of-cardiovascular-disease-diagnoses-a-literature-survey-of-ahas-circulation-cardiovascular-genetics-32010-32013/

D.  Genetic Base of Atherosclerosis and Loss of Arterial Elasticity with Aging

Lev-Ari, A. 5/17/2013 Synthetic Biology: On Advanced Genome Interpretation for Gene Variants and Pathways: What is the Genetic Base of Atherosclerosis and Loss of Arterial Elasticity with Aging

http://pharmaceuticalintelligence.com/2013/05/17/synthetic-biology-on-advanced-genome-interpretation-for-gene-variants-and-pathways-what-is-the-genetic-base-of-atherosclerosis-and-loss-of-arterial-elasticity-with-aging/ 

E.  Hypertension and Vascular Compliance: 2013 Thought Frontier – An Arterial Elasticity Focus

Pearlman, JD and A. Lev-Ari 5/11/2013 Hypertension and Vascular Compliance: 2013 Thought Frontier – An Arterial Elasticity Focus

http://pharmaceuticalintelligence.com/2013/05/11/arterial-elasticity-in-quest-for-a-drug-stabilizer-isolated-systolic-hypertension-caused-by-arterial-stiffening-ineffectively-treated-by-vasodilatation-antihypertensives/ 

F.  Arterial Stiffness: Pharmacotherapy for Hypertension and Hypercholesterolemia Management

Pearlman, JD and A. Lev-Ari 5/24/2013 Imaging Biomarker for Arterial Stiffness: Pathways in Pharmacotherapy for Hypertension and Hypercholesterolemia Management

http://pharmaceuticalintelligence.com/2013/05/24/imaging-biomarker-for-arterial-stiffness-pathways-in-pharmacotherapy-for-hypertension-and-hypercholesterolemia-management/ 

G. Genetics of Conduction Disease

Lev-Ari, A. 4/28/2013 Genetics of Conduction Disease: Atrioventricular (AV) Conduction Disease (block): Gene Mutations – Transcription, Excitability, and Energy Homeostasis

http://pharmaceuticalintelligence.com/2013/04/28/genetics-of-conduction-disease-atrioventricular-av-conduction-disease-block-gene-mutations-transcription-excitability-and-energy-homeostasis/

H.  Arrhythmia after Cardiac Surgery Prediction and ECG Prediction of Paroxysmal Atrial Fibrillation Onset

Pearlman, JD and A. Lev-Ari 5/7/2013 On Devices and On Algorithms: Arrhythmia after Cardiac Surgery Prediction and ECG Prediction of Paroxysmal Atrial Fibrillation Onset

http://pharmaceuticalintelligence.com/2013/05/07/on-devices-and-on-algorithms-arrhythmia-after-cardiac-surgery-prediction-and-ecg-prediction-of-paroxysmal-atrial-fibrillation-onset/ 

I.  Myocardial Infarction: Quantification of Myocardial Perfusion Viability

Pearlman, JD and A. Lev-Ari 5/22/2013 Acute and Chronic Myocardial Infarction: Quantification of Myocardial Perfusion Viability – FDG-PET/MRI vs. MRI or PET alone

http://pharmaceuticalintelligence.com/2013/05/22/acute-and-chronic-myocardial-infarction-quantification-of-myocardial-viability-fdg-petmri-vs-mri-or-pet-alone/

Read Full Post »

Abdominal Aortic Aneurysms (AAA): Albert Einstein’s Operation by Dr. Nissen

Reporter: Aviva Lev-Ari, PhD, RN

On June 11, 2013, I received the following comment by Dr. Miranda, to my article, an Interview with Dr. Richard Cambria, Chief Vascular Surgery, MGH, Boston

No Early Symptoms – An Aortic Aneurysm Before It Ruptures – Is There A Way To Know If I Have it?

Efrain Miranda, Ph.D. • It is true that abdominal aortic aneurysms (AAA) are mostly asymptomatic, until they rupture. By luck, some are identified. An example was a AAA found in Albert Einstein by Dr. Nissen when Einstein went for abdominal surgery for something completely unrelated! In my experience, I have found many AAA’s in individuals who had a totally different cause of death.
http://clinanat.com/mtd/153-aneurysm

I am presenting here the the CASE of an AAA found in Albert Einstein by Dr. Nissen when Einstein went for abdominal surgery for something completely unrelated!

A Moment in History

Dr. Rudolph Nissen
Dr. Rudolf Nissen
(1896 – 1981)

Dr Nissen’s life is extraordinary. Born in the city of Neisse, Germany in 1896, he was the son of a local surgeon. He studied medicine in the Universities of Munich, Marburg, and Breslau. He was the pupil of the famous pathologist Albert Aschoff (discoverer of the heart’s AV node, along with Sunao Tawara).

Nissen became a professor of surgery in Berlin, and in 1933 moved to Turkey where he was placed in charge of the Department of Surgery of the University of Istanbul. In 1939 he moved to the US, first to the Massachusetts General Hospital and later to the Jewish Hospital in Brooklyn, New York. After becoming a US citizen, he moved again in 1952 to Basel, Switzerland as Chief of the Department of Surgery, where he retired in 1967. He died in 1981.

His contributions to surgery are innumerable. He wrote over 30 books and 450 journal articles. Known for the development in 1956 of what is today known as the “Nissen fundoplication” for esophageal hiatus hernia surgery, Nissen also worked with his assistant, Dr. Mario Rossetti to develop the “floppy Nissen fundoplication”, also known as the “Nissen-Rossetti procedure”. This would be enough to honor this man, still, he (with Sauerbruch) performed the first lung lobectomy and the first pneumonectomy (called then a total pneumonectomy). In 1949 he performed the first esophagectomy with a gastroesophagostomy.

His personal life is even more interesting. Drafted at 20, he fought in WWI and was wounded several times. In 1933, under the Nazi regime,  he was ordered to fire all the Jewish-German assistants under his care. Being Jewish himself, he was told that he would keep his job, Nissen could not take this. He resigned his position and moved out of Germany.

Another little known fact is that he operated on Albert Einstein in 1948. He operated on Einstein because of intestinal cysts. Having found a developing abdominal aortic aneurysm, he reinforced it with cellophane, undoubtedly giving his patient a few extra years to live. Einstein died in 1955.

As a personal side note, our good friend Dr. Aaron Ruhalter scrubbed in with Dr. Nissen while serving as a surgical resident at the Brooklyn Jewish Hospital!

Sources:
1. “Rudolf Nissen: The man behind the fundoplication” Schein et al. Surgery 1999;125:347-53 
2. “Rudolf Nissen (1896–1981)-Perspective” Liebermann-Meffert, D. J Gastrointest Surg (2010) 14 (Suppl 1):S58–S61
3. “The Life of Rudolf Nissen: Advancing Surgery Through Science and Principle” Fults, DW; Taussky, P. World J Surg (2011) 35:1402–1408 
4. “Total Pneumonectomy” Nissen, R. Ann Thorac Surg 1980; 29:390-394 
5. “Historical Development of Pulmonary Surgery” Nissen, R. Am J Surg 80: Jan 1955 9- 15 áclav Treitz (1819-1872): Czechoslovakian Pathoanatomist and Patriot” Fox, RS; Fox, CG; Graham, WP. World J. Surg. 9, 361-366, 1985 
Original image courtesy of Universität Basel.

http://clinanat.com/mtd/153-aneurysm


Read Full Post »

« Newer Posts